
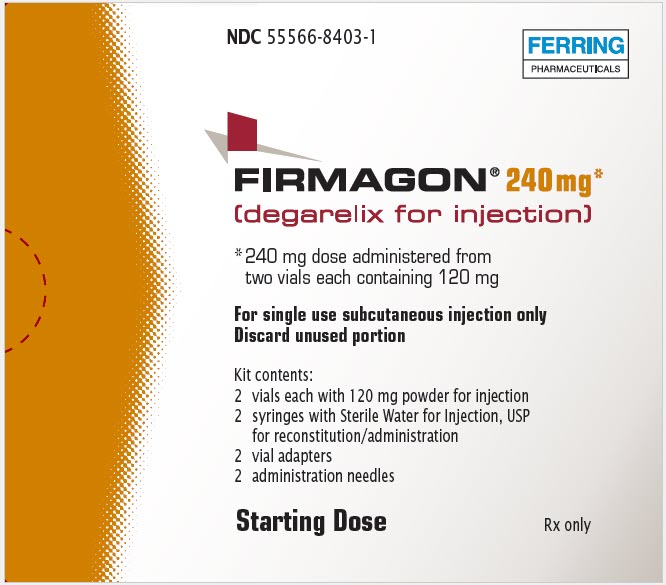
FIRMAGON Degarelix Kit — NDC 55566-8403-1 (Billing 55566-8403-01)
This is a package of FIRMAGON Degarelix Kit from Ferring Pharmaceuticals Inc., marketed since Mar 2009 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 55566-8403-1 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 55566 labeler · 8403 product · 1 package
- Package marketed since
- Mar 2, 2009
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 5556684031 8
- Medicaid fills, this package
- 58 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 064873
- GCN: 16946
- GPI-14 (Medi-Span): 21405525102131
- HICL (First Databank): 036138
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 828749
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Gonadotropin Releasing Hormone Receptor Antagonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Degarelix injection is used to treat advanced prostate cancer (cancer that begins in the prostate [a male reproductive gland]). Degarelix injection is in a class of medications called gonadotropin-releasing hormone (GnRH) receptor antagonists. It works by decreasing the amount of testosterone (a male hormone) produced by the body. This may slow or stop the spread of prostate cancer cells that need testosterone to grow.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $398.38 | — |
| Medicare drug plans payPart D · Q2 2026 | $761.98 | — |
| Medicare Part B allowsASP · J9155 | $4.481 / J9155 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 55566-8403-01 You're viewing this Main listing | 1 KIT in 1 CARTON * 3 mL in 1 VIAL, GLASS * 3 mL in 1 SYRINGE | 2009-03-02 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Firmagonthis 55566-8403-01 | Ferring | 1 kit | — | — | FDA listed | — |
| Firmagon 55566-8303-01 | Ferring | 1 kit | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9415085 ↗ | Method of use | U-1895 | Apr 27, 2032 |
| US 9579359 ↗ | Method of use | U-1978 | Feb 10, 2029 |
| US 9579359 ↗ | Method of use | U-1978 | Feb 10, 2029 |
| US 12514898 ↗ | Method of use | U-1978 | Feb 20, 2029 |
| US 12514898 ↗ | Method of use | U-1978 | Feb 20, 2029 |
| US 10695398 ↗ | Method of use | U-1895 | Apr 27, 2032 |
| US 10695398 ↗ | Method of use | U-1895 | Apr 27, 2032 |
| US 12533387 ↗ | Method of use | U-4417 | Feb 20, 2029 |
| US 12533387 ↗ | Method of use | U-4417 | Feb 20, 2029 |
| US 10973870 ↗ | Method of use | U-1978 | Feb 10, 2029 |
| US 10973870 ↗ | Method of use | U-1978 | Feb 10, 2029 |
| US 9415085 ↗ | Method of use | U-1895 | Apr 27, 2032 |
| US 10729739 ↗ | Method of use | U-1978 | Feb 10, 2029 |
| US 10729739 ↗ | Method of use | U-1978 | Feb 10, 2029 |
| US 11766468 ↗ | Method of use | U-1978 | Apr 27, 2032 |
| US 11766468 ↗ | Method of use | U-1978 | Apr 27, 2032 |
| US 11826397 ↗ | Method of use | U-1978 | Apr 27, 2032 |
| US 11826397 ↗ | Method of use | U-1978 | Apr 27, 2032 |
Is there a generic version of FIRMAGON 2 X 120 MG KIT?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Ferring Pharmaceuticals Inc. labeler code 55566
- Cervidil Dinoprostone 10 mg/241mg Insert NDC 55566-2800-1
- Stimate desmopressin acetate 1.5 mg/mL Spray NDC 55566-3000-0
- ENDOMETRIN Progesterone 100 mg Insert NDC 55566-6500-3
- CLENPIQ SODIUM PICOSULFATE, MAGNESIUM OXIDE, and ANHYDROUS CITRIC ACID 10 mg/175mL; 3.5 g/175mL; 12 g/175mL Liquid NDC 55566-6800-1
- Menopur menotropins Kit NDC 55566-7501-2
- FIRMAGON Degarelix Kit NDC 55566-8303-1
- Rebyota Donor Human Stool 50000000000 [CFU]/150mL Suspension NDC 55566-9800-2
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE FIRMAGON ® is indicated for treatment of patients with advanced prostate cancer. FIRMAGON is a GnRH receptor antagonist indicated for treatment of patients with advanced prostate cancer. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION FIRMAGON is for subcutaneous use only Starting Dosage: 240 mg given as two injections of 120 mg each ( 2.1 ) Maintenance Dosage: 80 mg administered as a single injection every 28 days ( 2.1 )
2.1Dosing information FIRMAGON is administered as a subcutaneous injection in the abdominal region only at the dosages in Table 1 below. Table 1: FIRMAGON Recommended Dosages Starting Dosage Maintenance Dosage – Administered once every 28 days 240 mg given as two subcutaneous injections of 120 mg at a concentration of 40 mg/mL The first maintenance dose should be given 28 days after the starting dose. 80 mg given as one subcutaneous injection at a concentration of 20 mg/mL
2.2Reconstitution and Administration Instructions FIRMAGON is to be administered by a healthcare professional only . Before administering FIRMAGON read the Instructions for reconstitution and administration carefully. As with other drugs administered by subcutaneous injection, the injection site should vary periodically.
Injections should be given only in areas of the abdomen that will not be exposed to pressure, e.g., not close to waistband or belt nor close to the ribs. FIRMAGON is supplied as a powder to be reconstituted with Sterile Water for Injection, USP. Starting dose (240 mg): Two single-dose vials each delivering 120 mg of degarelix in a white to off-white lyophilized powder for reconstitution supplied with diluent in two prefilled syringes.
Each vial is to be reconstituted with a prefilled syringe containing 3 mL of Sterile Water for Injection. 3 mL is withdrawn to deliver 120 mg degarelix at a concentration of 40 mg/mL. Maintenance dose (80 mg): One single-dose vial delivering 80 mg of degarelix in a white to off-white lyophilized powder for reconstitution supplied with diluent in one prefilled syringe.
Each vial is to be reconstituted with a prefilled syringe containing 4.2 mL of Sterile Water for Injection. 4 mL is withdrawn to deliver 80 mg degarelix at a concentration of 20 mg/mL. Follow the instructions for reconstitution closely and read the complete instructions before performing the subcutaneous injection.
Reconstituted drug must be administered within one hour after addition of Sterile Water for Injection, USP. Do not shake the vials. Follow aseptic technique.
FIRMAGON 240 mg Starting Dose Kit contains: 2 vials containing the 120 mg FIRMAGON powder (a) 2 syringes containing Sterile Water for Injection, USP (b) 2 vial adapters (c) 2 25 gauge × 1 inch injection needles (d) 2 plunger rods (e) FIRMAGON 80 mg Maintenance Dose Kit contains: 1 vial containing the 80 mg FIRMAGON powder (f) 1 syringe containing Sterile Water for Injection, USP (g) 1 vial adapter (h) 1 25 gauge × 1 inch injection needle (i) 1 plunger rod (j) In addition the healthcare professional will need: gloves (k) alcohol pads (l) a clean, flat surface (m) to work on, like a table a sharps disposal container (n) for throwing away your used needles and syringes.
See " Disposing used needles and syringes " at the end of these instructions. The drug product must be prepared using the following instructions: NOTE: The mixing process must be repeated for the two injections of the Starting Dose prior to injecting the product into the patient's abdomen. Step 1: Attaching the vial adaptor to the vial Thoroughly wash your hands using soap and water and put on a pair of clean gloves.
Place all the supplies required on a clean surface. Check that there is powder in the FIRMAGON vial and that the Sterile Water for Injection, USP is clear and free from particles. IMPORTANT: DO NOT USE if there is no powder in the vial or the Sterile Water for Injection, USP is discolored.
Uncap the vial containing the FIRMAGON powder (o). Wipe the vial rubber stopper with an alcohol pad. IMPORTANT: Do not touch the top of the vial after wiping.
Peel off the seal from the vial adaptor cover. IMPORTANT: Do not touch the vial adapter. Firmly press the vial adaptor (p) onto the vial containi… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For injection: FIRMAGON (240 mg): Two single-dose vials each delivering 120 mg of degarelix in a white to off-white lyophilized powder for reconstitution supplied with diluent in two prefilled syringes. FIRMAGON (80 mg): One single-dose vial delivering 80 mg of degarelix in a white to off-white lyophilized powder for reconstitution supplied with diluent in one prefilled syringe. For injection: FIRMAGON (240 mg): Two single-dose vials each delivering 120 mg of degarelix in a lyophilized powder for reconstitution supplied with diluent in two prefilled syringes ( 3 ) FIRMAGON (80 mg): One single-dose vial delivering 80 mg of degarelix in a lyophilized powder for reconstitution supplied with diluent in one prefilled syringe ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS FIRMAGON is contraindicated in patients with history of severe hypersensitivity to degarelix or to any of the product components [see Warnings and Precautions (5.1) ] . Patients with history of severe hypersensitivity reactions to degarelix or to any of the product components ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypersensitivity: Anaphylaxis, urticaria and angioedema have been reported. Discontinue FIRMAGON if a severe hypersensitivity reaction occurs and manage as clinically indicated ( 5.1 ) QT Interval Prolongation: Androgen deprivation therapy treatment with FIRMAGON may prolong the QT interval. ( 5.2 ) Embryo-Fetal Toxicity: FIRMAGON can cause fetal harm. ( 5.4 , 8.1 )
5.1Hypersensitivity Reactions FIRMAGON is contraindicated in patients with history of severe hypersensitivity to degarelix or to any of the product components [see Contraindications (4) ]. Hypersensitivity reactions, including anaphylaxis, urticaria and angioedema, have been reported post-marketing with FIRMAGON. In case of a severe hypersensitivity reaction, discontinue FIRMAGON immediately if the injection has not been completed, and manage as clinically indicated.
Patients with a known history of severe hypersensitivity reactions to FIRMAGON should not be re-challenged with FIRMAGON.
5.2QT Interval Prolongation Androgen deprivation therapy may prolong the QT interval. Providers should consider whether the benefits of androgen deprivation therapy outweigh the potential risks in patients with congenital long QT syndrome, congestive heart failure, frequent electrolyte abnormalities, and in patients taking drugs known to prolong the QT interval. Electrolyte abnormalities should be corrected.
Consider periodic monitoring of electrocardiograms and electrolytes. In the randomized, active-controlled trial comparing FIRMAGON to leuprolide, periodic electro-cardiograms were performed. Seven patients, three (<1%) in the pooled degarelix group and four (2%) patients in the leuprolide 7.5 mg group, had a QTcF ≥ 500 msec.
From baseline to end of study, the median change for FIRMAGON was 12.3 msec and for leuprolide was 16.7 msec.
5.3Laboratory Testing FIRMAGON results in suppression of the pituitary gonadal system. Results of diagnostic tests of the pituitary gonadotropic and gonadal functions conducted during and after FIRMAGON may be affected. The therapeutic effect of FIRMAGON should be monitored by measuring serum concentrations of prostate-specific antigen (PSA) periodically. If PSA increases, serum concentrations of testosterone should be measured.
5.4Embryo-Fetal Toxicity Based on findings in animal studies, FIRMAGON can cause fetal harm and loss of pregnancy when administered to a pregnant woman. In animal developmental and reproductive toxicity studies in rats and rabbits, oral administration of degarelix during organogenesis caused embryo-fetal lethality and abortion as well as increased post-implantation loss and decreased the number of live fetuses in animals at doses less than the clinical loading dose based on body surface area. Advise pregnant patients and females of reproductive potential of the potential risk to the fetus [see Use in Specific Populations (8.1) ].
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (≥10%) are injection site reactions (e.g., pain, erythema, swelling or induration), hot flashes, and increases in serum levels of transaminases and gamma-glutamyltransferase (GGT) ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Ferring at 1-888-FERRING (1-888-337-7464) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. FIRMAGON was studied in a randomized, open-label trial in which patients with prostate cancer were randomized to receive FIRMAGON (subcutaneous) or leuprolide (intramuscular) monthly for 12 months [see Clinical Studies (14) ] .
The most common adverse reactions (≥10%) during FIRMAGON therapy are injection site reactions (e.g., pain, erythema, swelling or induration), hot flashes, and increases in serum levels of transaminases and gamma-glutamyltransferase (GGT). The majority of the adverse reactions were Grade 1 or 2, with Grade 3/4 adverse reaction incidences of 1% or less. Adverse reactions reported in ≥ 5% of patients treated with FIRMAGON (subcutaneous) 240 mg starting dose and then 80 mg maintenance dose once every 28 days or who were treated with 7.5 mg of leuprolide (intramuscular) every 28 days are shown in Table 2.
Table 2: Adverse Reactions Reported in ≥ 5% of Patients FIRMAGON 240/80 mg (subcutaneous) N = 207 Leuprolide 7.5 mg (intramuscular) N = 201 Any adverse reaction 79% 78% Body as a whole Injection site reactions Includes pain, erythema, swelling, induration, or nodule. 35% <1% Weight increase 9% 12% Chills 5% 0% Cardiovascular system Hot flash 26% 21% Hypertension 6% 4% Digestive system Increases in Transaminases and GGT 10% 5% Constipation 5% 5% Musculoskeletal system Back pain 6% 8% Arthralgia 5% 9% Urogenital system Urinary tract infection 5% 9% The following adverse reactions occurred in 1 to < 5% of patients treated with FIRMAGON: Body as a whole: Asthenia, fatigue, fever, night sweats Digestive system: Nausea Nervous system: Dizziness, headache, insomnia The following adverse reactions, not already listed, occurred in ≥ 1% of patients treated in any study with FIRMAGON: Reproductive System: Erectile dysfunction, testicular atrophy Endocrine Disorders: Gynecomastia General : Hyperhidrosis Gastrointestinal : Diarrhea Injection Site Reactions The most frequently reported adverse reactions at the injection sites were pain (28%), erythema (17%), swelling (6%), induration (4%) and nodule (3%).
These adverse reactions were mostly transient, of mild to moderate intensity, occurred primarily with the starting dose and led to few discontinuations (<1%). Grade 3 injection site reactions occurred in 2% or less of patients receiving FIRMAGON. Hepatic Laboratory Abnormalities Hepatic laboratory abnormalities were primarily Grade 1 or 2 and were generally reversible.
Grade 3 hepatic laboratory abnormalities occurred in less than 1% of patients. FIRMAGON Extension Study The safety of FIRMAGON administered once every 28 days was evaluated further in an extension study (NCT00451958) in 385 patients who completed the above active-controlled trial. Of the 385 patients, 251 patients continued treatment with FIRMAGON and 135 patients crossed over treatment from leuprolide to FIRMAGON.
The median treatment duration on the extension study was approximately 43 months (range 1 to 58 months). The most common adverse reactions reported in ≥10% of the patients were injection site reactions (e.g., pain, erythema, swelling, induration or inflammation), pyrexia, hot flush, weight loss or gain, fatigue, increases in serum levels of hepatic transaminases and GGT. One percent of patients had injection site infections including abscess.
Hepatic laboratory abnormalities in the ex… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS No drug-drug interaction studies were conducted. Degarelix is not a substrate for the human CYP450 system. Degarelix is not an inducer or inhibitor of the CYP450 system in vitro . Therefore, clinically significant CYP450 pharmacokinetic drug-drug interactions are unlikely.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Females and males of reproductive potential: FIRMAGON may impair fertility ( 8.3 ) Patients with severe liver or kidney dysfunction have not been studied and caution is therefore warranted ( 8 )
8.1Pregnancy Risk Summary The safety and efficacy of FIRMAGON have not been established in women. Based on findings in animal studies and mechanism of action, FIRMAGON can cause fetal harm and loss of pregnancy when administered to a pregnant woman [ see Clinical Pharmacology (12.1) ]. There are no human data on the use of FIRMAGON in pregnant women to inform the drug-associated risk.
In animal developmental and reproductive toxicity studies in rats and rabbits, oral administration of degarelix during organogenesis caused embryo-fetal lethality and abortion as well as increased post-implantation loss and decreased the number of live fetuses in animals at doses less than the clinical loading dose based on body surface area ( see Data ). Advise pregnant patients and females of reproductive potential of the potential risk to the fetus. Data Animal Data When degarelix was given to rabbits during early organogenesis at doses of 0.002 mg/kg/day (about 0.02% of the clinical loading dose based on body surface area), there was an increase in early post-implantation loss.
Degarelix given to rabbits during mid and late organogenesis at doses of 0.006 mg/kg/day (about 0.05% of the clinical loading dose based on body surface area) caused embryo/fetal lethality and abortion. When degarelix was given to female rats during early organogenesis, at doses of 0.0045 mg/kg/day (about 0.036% of the clinical loading dose based on body surface area), there was an increase in early post-implantation loss. When degarelix was given to female rats during mid and late organogenesis, at doses of 0.045 mg/kg/day (about 0.36% of the clinical loading dose based on body surface area), there was an increase in the number of minor skeletal abnormalities and variants.
8.2Lactation The safety and efficacy of FIRMAGON have not been established in females. There are no data on the presence of degarelix in human milk, the effects on the breastfed child, or the effects on milk production. Because many drugs are present in human milk and because of the potential for serious adverse reactions in a breastfed child from degarelix, a decision should be made whether to discontinue nursing or discontinue the drug taking into account the importance of the drug to the mother.
8.3Females and Males of Reproductive Potential Infertility Based on findings in animals and mechanism of action, degarelix may impair fertility in males and females of reproductive potential [see Nonclinical Toxicology (13.1) ].
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
8.5Geriatric Use Of the total number of subjects in clinical studies of FIRMAGON, 82% were age 65 and over, while 42% were age 75 and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, but greater sensitivity of some older individuals cannot be ruled out.
8.6Renal Impairment No pharmacokinetic studies in renally impaired patients have been conducted. At least 20-30% of a given dose of degarelix is excreted unchanged in the urine. A population pharmacokinetic analysis of data from the randomized study demonstrated that there is no significant effect of mild renal impairment [creatinine clearance (CrCL) 50-80 mL/min] on either the degarelix concentration or testosterone concentration.
Data on patients with moderate or severe renal impairment is limited and therefore degarelix should be used with caution in patients with CrCL < 50 mL/min.
8.7Hepatic Impairment Patients with hepatic impairment were excluded from the randomized trial. A single dose of 1 mg degarelix administered as an intravenous infusion over 1 hour was studied in 16 non-prostate cancer patients with either mild (Child Pugh A) or moderate… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The safety and efficacy of FIRMAGON have not been established in women. Based on findings in animal studies and mechanism of action, FIRMAGON can cause fetal harm and loss of pregnancy when administered to a pregnant woman [ see Clinical Pharmacology (12.1) ]. There are no human data on the use of FIRMAGON in pregnant women to inform the drug-associated risk.
In animal developmental and reproductive toxicity studies in rats and rabbits, oral administration of degarelix during organogenesis caused embryo-fetal lethality and abortion as well as increased post-implantation loss and decreased the number of live fetuses in animals at doses less than the clinical loading dose based on body surface area ( see Data ). Advise pregnant patients and females of reproductive potential of the potential risk to the fetus. Data Animal Data When degarelix was given to rabbits during early organogenesis at doses of 0.002 mg/kg/day (about 0.02% of the clinical loading dose based on body surface area), there was an increase in early post-implantation loss.
Degarelix given to rabbits during mid and late organogenesis at doses of 0.006 mg/kg/day (about 0.05% of the clinical loading dose based on body surface area) caused embryo/fetal lethality and abortion. When degarelix was given to female rats during early organogenesis, at doses of 0.0045 mg/kg/day (about 0.036% of the clinical loading dose based on body surface area), there was an increase in early post-implantation loss. When degarelix was given to female rats during mid and late organogenesis, at doses of 0.045 mg/kg/day (about 0.36% of the clinical loading dose based on body surface area), there was an increase in the number of minor skeletal abnormalities and variants.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects in clinical studies of FIRMAGON, 82% were age 65 and over, while 42% were age 75 and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE There have been no reports of overdose with FIRMAGON. In the case of overdose, however, discontinue FIRMAGON, treat the patient symptomatically, and institute supportive measures.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Degarelix is a GnRH receptor antagonist. It binds reversibly to the pituitary GnRH receptors, thereby reducing the release of gonadotropins and consequently testosterone.
12.2Pharmacodynamics A single dose of 240 mg FIRMAGON causes a decrease in the plasma concentrations of luteinizing hormone (LH) and follicle stimulating hormone (FSH), and subsequently testosterone. FIRMAGON is effective in achieving and maintaining testosterone suppression below the castration level of 50 ng/dL. Figure 1: Plasma Testosterone Levels from Day 0 to 364 for Degarelix 240 mg/80 mg (Median with Interquartile Ranges) Figure 1
12.3Pharmacokinetics Absorption FIRMAGON forms a depot upon subcutaneous administration, from which degarelix is released to the circulation. Following administration of FIRMAGON 240 mg at a product concentration of 40 mg/mL, the mean Cmax was 26.2 ng/mL (coefficient of variation, CV 83%) and the mean AUC was 1054 ng∙day/mL (CV 35%). Typically Cmax occurred within 2 days after subcutaneous administration.
In prostate cancer patients at a product concentration of 40 mg/mL, the pharmacokinetics of degarelix were linear over a dose range of 120 to 240 mg. The pharmacokinetic behavior of the drug is strongly influenced by its concentration in the injection solution. Distribution The distribution volume of degarelix after intravenous (> 1 L/kg) or subcutaneous administration (> 1000L) indicates that degarelix is distributed throughout total body water.
In vitro plasma protein binding of degarelix is estimated to be approximately 90%. Metabolism Degarelix is subject to peptide hydrolysis during the passage of the hepato-biliary system and is mainly excreted as peptide fragments in the feces. No quantitatively significant metabolites were detected in plasma samples after subcutaneous administration.
In vitro studies have shown that degarelix is not a substrate, inducer or inhibitor of the CYP450 or p-glycoprotein transporter systems. Excretion Following subcutaneous administration of 240 mg FIRMAGON at a concentration of 40 mg/mL to prostate cancer patients, degarelix is eliminated in a biphasic fashion, with a median terminal half-life of approximately 53 days. The long half-life after subcutaneous administration is a consequence of a very slow release of degarelix from the FIRMAGON depot formed at the injection site(s).
Approximately 20-30% of a given dose of degarelix was renally excreted, suggesting that approximately 70-80% is excreted via the hepato-biliary system in humans. Following subcutaneous administration of degarelix to prostate cancer patients the clearance is approximately 9 L/hr. Effect of Age, Weight and Race There was no effect of age, weight or race on the degarelix pharmacokinetic parameters or testosterone concentration.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Degarelix is a GnRH receptor antagonist. It binds reversibly to the pituitary GnRH receptors, thereby reducing the release of gonadotropins and consequently testosterone.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING FIRMAGON is available as: NDC 55566-8403-1, Starting dose – One carton contains: Two single-dose vials each delivering 120 mg of degarelix in a white to off-white lyophilized powder for injection Two prefilled syringes each containing 3 mL of Sterile Water for Injection, USP Two vial adapters Two administration needles NDC 55566-8303-1, Maintenance dose – One carton contains: One single-dose vial delivering 80 mg of degarelix in a white to off-white lyophilized powder for injection One prefilled syringe containing 4.2 mL of Sterile Water for Injection, USP One vial adapter One administration needle Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F). [see USP Controlled Room Temperature].
📦 Storage and Handling ▾
Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F). [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION FIRMAGON is a sterile lyophilized powder for injection containing degarelix (as the acetate) and mannitol. Degarelix is a synthetic linear decapeptide amide containing seven unnatural amino acids, five of which are D-amino acids. The acetate salt of degarelix is a white to off-white amorphous powder of low density as obtained after lyophilization.
The chemical name of degarelix is D-Alaninamide, N -acetyl-3-(2-naphthalenyl)-D-alanyl-4-chloro-D-phenylalanyl-3-(3-pyridinyl)-D-alanyl-L-seryl-4-[[[(4S)-hexahydro-2,6-dioxo-4-pyrimidinyl]carbonyl]amino]-L phenylalanyl-4-[(aminocarbonyl)amino]-D-phenylalanyl-L-leucyl- N 6–(1-methylethyl)-L-lysyl-L-prolyl. It has an empirical formula of C 82 H 103 N 18 O 16 Cl and a molecular weight of 1632.3 Da. Degarelix acetate has the following structural formula: FIRMAGON is available in two packaging configurations: Starting Dose: Two vial carton with each vial delivering 120 mg of degarelix (equivalent to the median value of 126 mg degarelix acetate).
Each 120 mg dose contains 150 mg mannitol. Maintenance Dose: One-vial carton delivering 80 mg of degarelix (equivalent to the median value of 84 mg degarelix acetate). Each 80 mg dose contains 200 mg mannitol.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Hypersensitivity Inform patients that if they have experienced severe hypersensitivity with degarelix or to any of the product components, FIRMAGON is contraindicated [see Contraindications (4) ]. Instruct patients to immediately report signs of a severe hypersensitivity reaction [see Warnings and Precautions (5.1) ].
QT Interval Prolongation Advise patients that androgen deprivation therapy treatment with FIRMAGON may prolong the QT interval. Inform patients of the signs and symptoms of QT prolongation. Advise patients to contact their healthcare provider immediately for signs or symptoms of QT prolongation [see Warnings and Precautions (5.2) ].
Androgen Deprivation Inform patients about adverese reactions related to androgen deprivation therapy with FIRMAGON, including hot flashes, flushing of the skin, increased weight, decreased sex drive, and difficulties with erectile function [see Adverse Reactions (6.1) ] . Injection Site Reactions Inform patients that FIRMAGON may cause redness, swelling, and itching at the injection site. Advise patients that these adverse reactions are usually mild, self limiting, and decrease within three days [see Adverse Reactions (6.1) ] .
Infertility Inform patients that FIRMAGON may cause infertility [see Use in Specific Populations (8.3) ].
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption FIRMAGON forms a depot upon subcutaneous administration, from which degarelix is released to the circulation. Following administration of FIRMAGON 240 mg at a product concentration of 40 mg/mL, the mean Cmax was 26.2 ng/mL (coefficient of variation, CV 83%) and the mean AUC was 1054 ng∙day/mL (CV 35%). Typically Cmax occurred within 2 days after subcutaneous administration.
In prostate cancer patients at a product concentration of 40 mg/mL, the pharmacokinetics of degarelix were linear over a dose range of 120 to 240 mg. The pharmacokinetic behavior of the drug is strongly influenced by its concentration in the injection solution. Distribution The distribution volume of degarelix after intravenous (> 1 L/kg) or subcutaneous administration (> 1000L) indicates that degarelix is distributed throughout total body water.
In vitro plasma protein binding of degarelix is estimated to be approximately 90%. Metabolism Degarelix is subject to peptide hydrolysis during the passage of the hepato-biliary system and is mainly excreted as peptide fragments in the feces. No quantitatively significant metabolites were detected in plasma samples after subcutaneous administration.
In vitro studies have shown that degarelix is not a substrate, inducer or inhibitor of the CYP450 or p-glycoprotein transporter systems. Excretion Following subcutaneous administration of 240 mg FIRMAGON at a concentration of 40 mg/mL to prostate cancer patients, degarelix is eliminated in a biphasic fashion, with a median terminal half-life of approximately 53 days. The long half-life after subcutaneous administration is a consequence of a very slow release of degarelix from the FIRMAGON depot formed at the injection site(s).
Approximately 20-30% of a given dose of degarelix was renally excreted, suggesting that approximately 70-80% is excreted via the hepato-biliary system in humans. Following subcutaneous administration of degarelix to prostate cancer patients the clearance is approximately 9 L/hr. Effect of Age, Weight and Race There was no effect of age, weight or race on the degarelix pharmacokinetic parameters or testosterone concentration.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics A single dose of 240 mg FIRMAGON causes a decrease in the plasma concentrations of luteinizing hormone (LH) and follicle stimulating hormone (FSH), and subsequently testosterone. FIRMAGON is effective in achieving and maintaining testosterone suppression below the castration level of 50 ng/dL. Figure 1: Plasma Testosterone Levels from Day 0 to 364 for Degarelix 240 mg/80 mg (Median with Interquartile Ranges) Figure 1
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The safety and efficacy of FIRMAGON were evaluated in an open-label, multi-center, randomized, parallel-group study (NCT00295750) in patients with prostate cancer. A total of 620 patients were randomized to receive one of two FIRMAGON dosing regimens or leuprolide for one year: a. FIRMAGON at a starting dose of 240 mg (40 mg/mL) followed by monthly doses of 80 mg (20 mg/mL) subcutaneously, b. leuprolide 7.5 mg intramuscularly monthly. c.
FIRMAGON at a starting dose of 240 mg (40 mg/mL) followed by monthly doses of 160 mg (40 mg/mL) subcutaneously. FIRMAGON is not approved for use with monthly doses of 160 mg (40 mg/mL) subcutaneously. Serum levels of testosterone were measured at screening, on Day 0, 1, 3, 7, 14, and 28 in the first month, and then monthly until the end of the study.
The clinical trial population (n=610) across all treatment arms had an overall median age of approximately 73 (range 50 to 98). The ethnic/racial distribution was 84% white, 6% black and 10% others. Disease stage was distributed approximately as follows: 20% metastatic, 29% locally advanced (T3/T4 Nx M0 or N1 M0), 31% localized (T1 or T2 N0 M0) and 20% classified as other (including patients whose disease metastatic status could not be determined definitively - or patients with PSA relapse after primary curative therapy).
In addition, the median testosterone baseline value across treatment arms was approximately 400 ng/dL. The primary objective was to demonstrate that FIRMAGON is effective achieving and maintaining testosterone suppression to castration levels (T ≤ 50 ng/dL) during 12 months of treatment. The results are shown in Table 3.
Table 3: Medical Castration Rates (Testosterone ≤ 50 ng/dL) from Day 28 to Day 364 FIRMAGON 240/80 mg N=207 Leuprolide 7.5 mg N=201 No. of Responders 202 194 Castration Rate (95% CIs) Kaplan Meier estimates within group 97.2% (93.5; 98.8) 96.4% (92.5; 98.2) Percentage changes in testosterone from baseline to Day 28 (median with interquartile ranges) are shown in Figure 2 and the percentages of patients who attained the medical castration of testosterone ≤ 50 ng/dL are summarized in Table 4. Figure 2: Percentage Change in Testosterone from Baseline by Treatment Group until Day 28 (Median with Interquartile Ranges) Table 4: Percentage of Patients Attaining Testosterone ≤ 50 ng/dL within the First 28 Days FIRMAGON 240/80 mg N=207 Leuprolide 7.5 mg N=201 Day 1 52% 0% Day 3 96% 0% Day 7 99% 1% Day 14 99% 18% Day 28 100% 100% In the clinical trial, PSA levels were monitored as a secondary endpoint.
PSA levels were lowered by 64% two weeks after administration of FIRMAGON, 85% after one month, 95% after three months, and remained suppressed throughout the one year of treatment. These PSA results should be interpreted with caution because of the heterogeneity of the patient population studied. No evidence has shown that the rapidity of PSA decline is related to a clinical benefit.
Figure 2
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Degarelix was administered subcutaneously to rats every 2 weeks for 2 years at doses of 2, 10 and 25 mg/kg (about 9, 45 and 120% of the recommended human loading dose on a mg/m 2 basis). Long term treatment with degarelix at 25 mg/kg caused an increase in the combined incidence of benign hemangiomas plus malignant hemangiosarcomas in females. Degarelix was administered subcutaneously to mice every 2 weeks for 2 years at doses of 2, 10 and 50 mg/kg (about 5, 22 and 120% of the recommended human loading dose (240 mg) on a mg/m 2 basis).
There was no statistically significant increase in tumor incidence associated with this treatment. Degarelix did not cause genetic damage in standard in vitro assays (bacterial mutation, human lymphocyte chromosome aberration) nor in in vivo rodent bone marrow micronucleus tests. Single degarelix doses of ≥ 1 mg/kg (about 5% of the clinical loading dose on a mg/m 2 basis) caused reversible infertility in male rats.
Single doses of ≥ 0.1 mg/kg (about 0.5% of the clinical loading dose on a mg/m 2 basis) caused a decrease in fertility in female rats.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Degarelix was administered subcutaneously to rats every 2 weeks for 2 years at doses of 2, 10 and 25 mg/kg (about 9, 45 and 120% of the recommended human loading dose on a mg/m 2 basis). Long term treatment with degarelix at 25 mg/kg caused an increase in the combined incidence of benign hemangiomas plus malignant hemangiosarcomas in females. Degarelix was administered subcutaneously to mice every 2 weeks for 2 years at doses of 2, 10 and 50 mg/kg (about 5, 22 and 120% of the recommended human loading dose (240 mg) on a mg/m 2 basis).
There was no statistically significant increase in tumor incidence associated with this treatment. Degarelix did not cause genetic damage in standard in vitro assays (bacterial mutation, human lymphocyte chromosome aberration) nor in in vivo rodent bone marrow micronucleus tests. Single degarelix doses of ≥ 1 mg/kg (about 5% of the clinical loading dose on a mg/m 2 basis) caused reversible infertility in male rats.
Single doses of ≥ 0.1 mg/kg (about 0.5% of the clinical loading dose on a mg/m 2 basis) caused a decrease in fertility in female rats.
📄 Patient Package Insert ▾
Patient Information FIRMAGON (FIRM-uh-gahn) (degarelix for injection) What is FIRMAGON? FIRMAGON is a prescription medicine used in the treatment of advanced prostate cancer. It is not known if FIRMAGON is safe or effective in children.
Who should not receive FIRMAGON? Do not receive FIRMAGON if you are allergic to degarelix or any ingredient in FIRMAGON. See the end of this leaflet for a complete list of ingredients in FIRMAGON.
Talk to your healthcare provider before receiving FIRMAGON if you have any of these conditions. Before receiving FIRMAGON, tell your healthcare provider about all your medical conditions, including if you: have any heart problems including a condition called long QT syndrome. have problems with blood levels such as sodium, potassium, calcium, and magnesium have kidney or liver problems are pregnant or plan to become pregnant. FIRMAGON can cause harm to your unborn baby and loss of pregnancy (miscarriage) are breastfeeding or plan to breastfeed.
It is not known if FIRMAGON passes into your breast milk. You and your healthcare provider should decide if you will receive FIRMAGON or breastfeed. You should not do both.
Tell your healthcare provider about all the medicines you take , including prescription and over-the-counter medicines, vitamins, and herbal supplements. Know the medicines you take. Keep a list of them and show it to your healthcare provider and pharmacist when you get a new medicine.
How will I receive FIRMAGON? You will receive an injection of FIRMAGON from your healthcare provider. The injection site will always be in the stomach (abdominal area).
The injection site will change within the stomach area each time you receive a dose of FIRMAGON. Two injections are given as a first dose. The following monthly doses are one injection.
Do not rub or scratch the injection site. Make sure your injection site is free of any pressure from belts, waistbands or other types of clothing. Always set up an appointment for your next injection.
What are the possible side effects of FIRMAGON? FIRMAGON can cause serious side effects, including: Serious allergic reactions. Get medical help right away if you get any of these symptoms: trouble breathing or wheezing severe itching swelling of your face, lips, mouth, or tongue Disorder of the heart's electrical activity.
Your healthcare provider may do tests during treatment with FIRMAGON to check your heart for a condition called long QT syndrome. The common side effects of FIRMAGON include: injection site pain, redness, and swelling hot flashes weight gain increase in some liver enzymes Other side effects include decreased sex drive and erectile function problems. Tell your healthcare provider if you have any side effect that bothers you or that does not go away.
These are not all the possible side effects. Call your healthcare provider for medical advice about side effects. You may report side effects to FDA at 1-800-FDA-1088.
General information about the safe and effective use of FIRMAGON. Medicines are sometimes prescribed for conditions that are not mentioned in a Patient Information leaflet. Do not use FIRMAGON for a condition for which it was not prescribed.
Do not give FIRMAGON to other people, even if they have the same symptoms that you have. It may harm them. You can ask your pharmacist or healthcare provider for information about FIRMAGON that is written for health professionals.
What are the ingredients in FIRMAGON? Active ingredient: degarelix (as acetate) Inactive ingredient: mannitol MANUFACTURED FOR: FERRING PHARMACEUTICALS INC., PARSIPPANY, NJ 07054 Manufactured in Germany For more information, go to www.FIRMAGON.com or call 1-888-337-7464. This Patient Information has been approved by the U.S.
Food and Drug Administration. 02/2020
📄 Recent Major Changes ▾
Warnings and Precautions, Embryo-Fetal Toxicity ( 5.4 ) 02/2020
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 240 mg Kit Carton NDC 55566-8403-1 FERRING PHARMACEUTICALS FIRMAGON ® 240 mg* (degarelix for injection) *240 mg dose administered from two vials each containing 120 mg For single use subcutaneous injection only Discard unused portion Kit contents: 2 vials each with 120 mg powder for injection 2 syringes with Sterile Water for Injection, USP for reconstitution/administration 2 vial adapters 2 administration needles Starting Dose Rx only PRINCIPAL DISPLAY PANEL - 240 mg Kit Carton
PRINCIPAL DISPLAY PANEL - 80 mg Kit Carton NDC 55566-8303-1 FERRING PHARMACEUTICALS FIRMAGON ® 80 mg (degarelix for injection) For single use subcutaneous injection only Discard unused portion Kit contents: 1 vial with 80 mg powder for injection 1 syringe with Sterile Water for Injection, USP for reconstitution/administration 1 vial adapter 1 administration needle Maintenance Dose (28 Days) Rx only PRINCIPAL DISPLAY PANEL - 80 mg Kit Carton
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |