
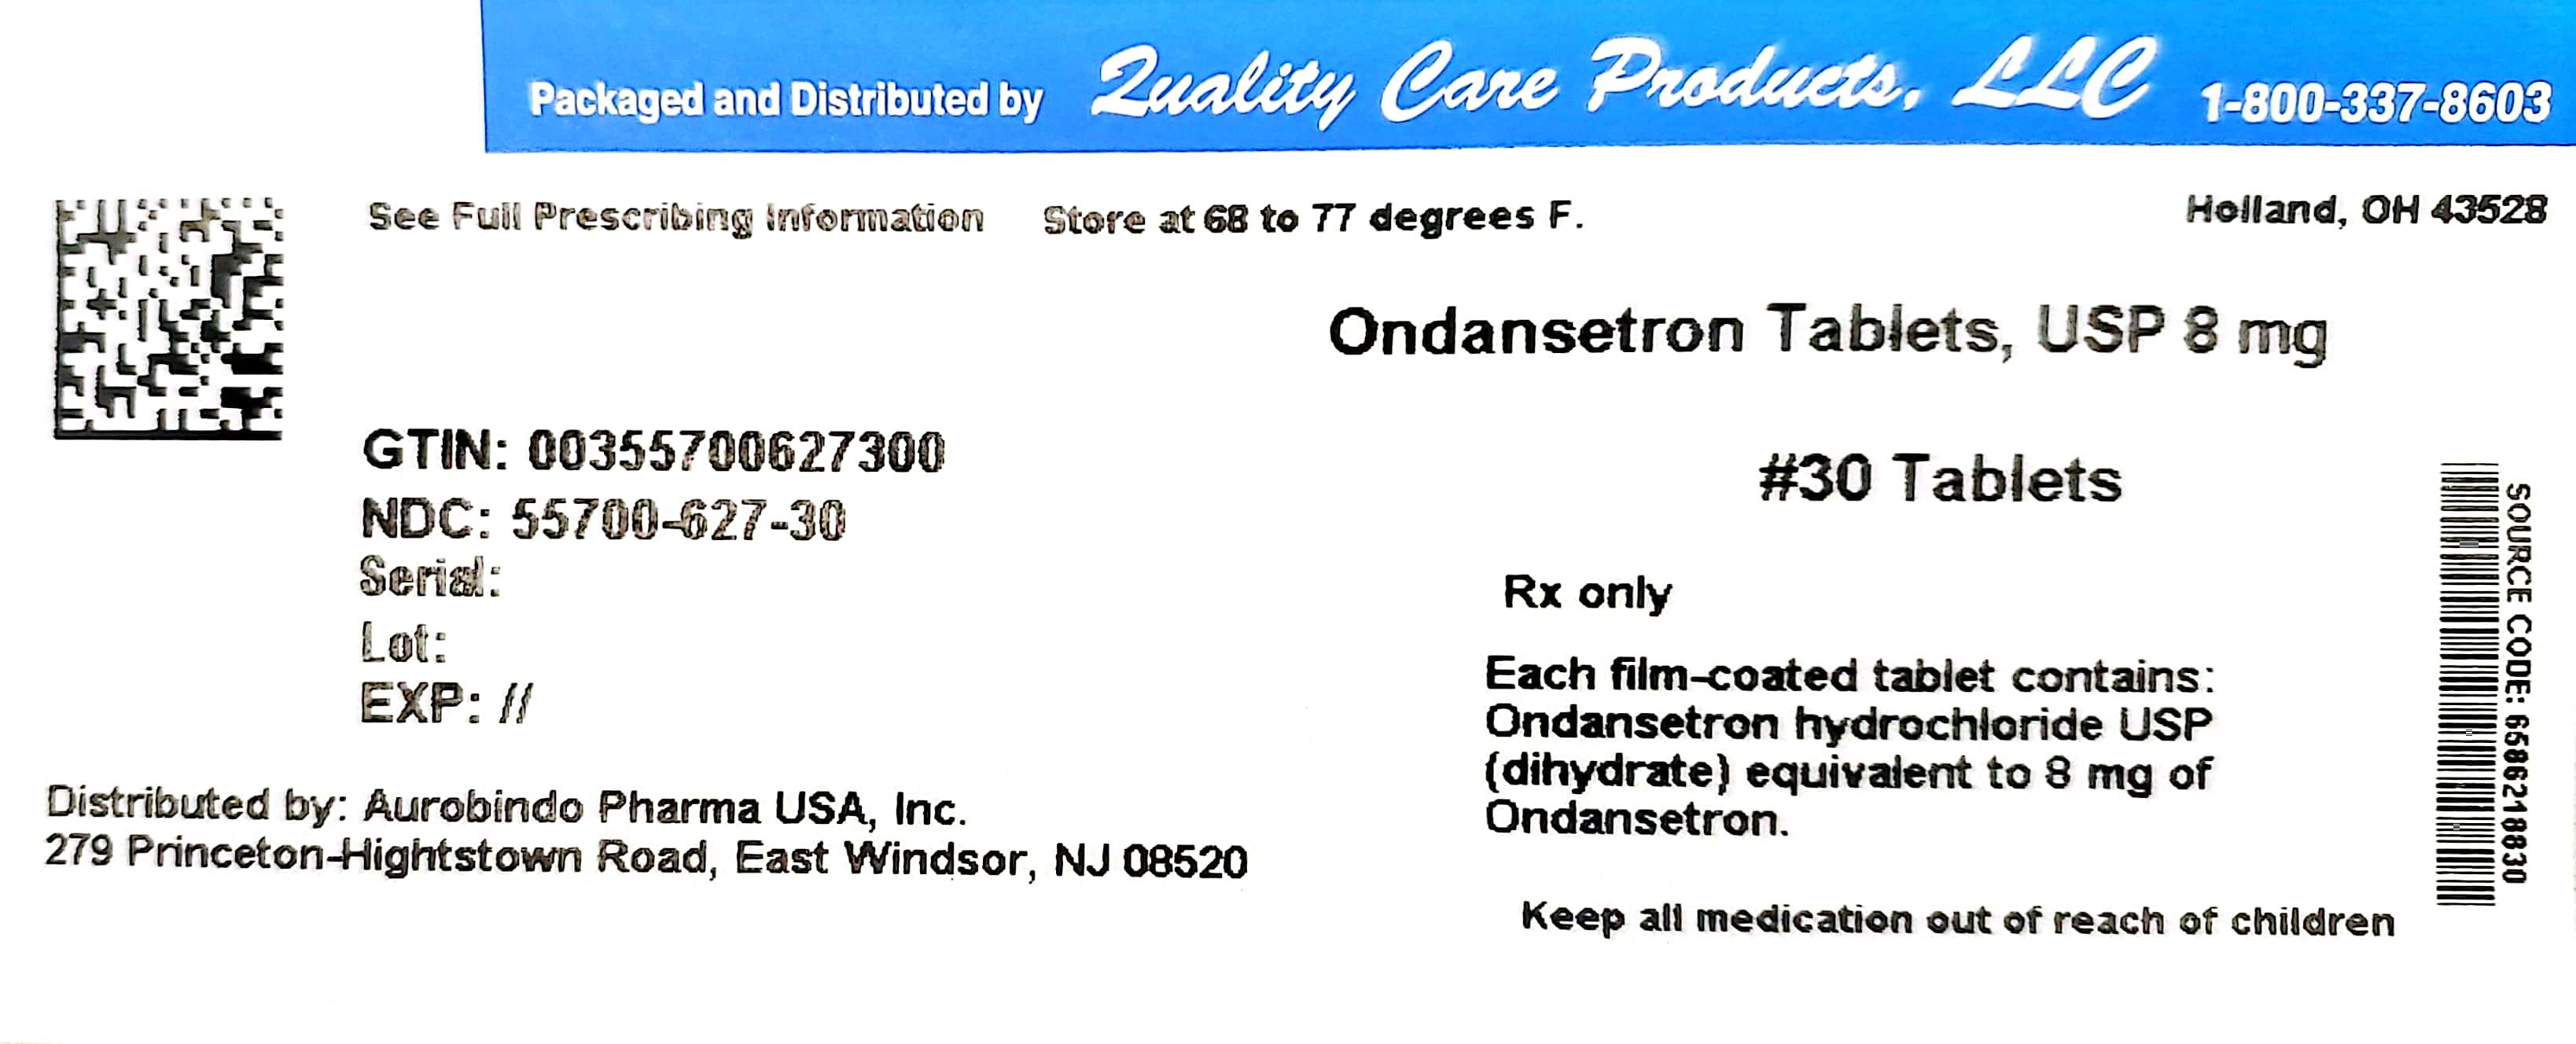
Ondansetron Hydrochloride 8 mg Tablet, Film Coated, 20-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Serotonin-3 Receptor Antagonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Ondansetron is used to prevent nausea and vomiting caused by cancer chemotherapy, radiation therapy, and surgery. Ondansetron is in a class of medications called serotonin 5-HT3 receptor antagonists. It works by blocking the action of serotonin, a natural substance that may cause nausea and vomiting.
Read the full MedlinePlus article ↗- Not at all. Ondansetron is approved to prevent nausea and vomiting from cancer chemotherapy, radiation therapy to the abdomen or whole body, and surgery. So you might receive it be...
- What exactly is ondansetron used for — is it just for chemo patients?
- The regular tablet is swallowed like any other pill. The orally disintegrating tablet (ODT) is placed on your tongue and allowed to dissolve — don't chew or swallow it whole. For c...
- How do I take the tablet or the dissolving tablet correctly?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1854 | $3.71 / 20 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| ondansetron 8 mg 00904-6552-61 | Major | 1 tablet | $0.081 | AB | Availability likely | — |
| Ondansetron 8 mg 16714-0160-01 | NorthStar | 30 tablets | $0.081 | AB | Availability likely | — |
| Ondansetron Hydrochloride 8 mg 50268-0622-15 | AvPAK | 1 tablet | $0.081 | AB | Availability likely | — |
| Ondansetron Hydrochloride 8 mg 57237-0076-30 | Rising | 30 tablets | $0.081 | AB | Availability likely | — |
| Ondansetron 8 mg 62135-0351-05 | Chartwell | 500 tablets | $0.081 | — | Availability likely | — |
| Ondansetron Hydrochloride 8 mg 65862-0188-03 | Aurobindo | 3 tablets | $0.081 | — | Availability likely | — |
| Ondansetron Hydrochloride 8 mg 68084-0221-01 | American | 1 tablet | $0.081 | AB | Availability likely | — |
| Ondansetron 8 mg 68462-0106-30 | Glenmark | 30 tablets | $0.081 | AB | Availability likely | — |
| Ondansetron 8 mg 69339-0172-03 | Natco | 30 tablets | $0.081 | AB | Availability likely | — |
| ondansetron hydrochloride 8 mg 62756-0131-01 | Sun | 30 tablets | $0.092 | — | FDA listed | — |
| Ondansetron 8 mg 63304-0459-30 | Sun | 30 tablets | $0.099 | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 42708-0059-05 | QPharma, | 5 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 42708-0179-05 | QPharma, | 5 tablets | — | AB | FDA listed | — |
| Ondansetron 8 mg 43063-0770-06 | PD-Rx | 6 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 43063-0792-06 | PD-Rx | 6 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 50090-3185-00 | A-S | 4 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 50090-4671-00 | A-S | 4 tablets | — | AB | FDA listed | — |
| Ondansetron 8 mg 51407-0004-05 | Golden | 500 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 51655-0016-27 | Northwind | 12 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 51655-0813-54 | Northwind | 15 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 54348-0821-00 | Pharmpak, | 1 tablet | — | AB | FDA listed | — |
| Ondansetron 8 mg 55111-0154-01 | Dr. | 100 tablets | — | AB | FDA listed | — |
| ondansetron 8 mg 55154-7879-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mgthis 55700-0627-20 | Quality | 20 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 60760-0658-10 | St. | 10 tablets | — | AB | FDA listed | — |
| Ondansetron 8 mg 63187-0065-10 | Proficient | 10 tablets | — | AB | FDA listed | — |
| ondansetron 8 mg 63187-0513-10 | Proficient | 10 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 63187-0709-06 | Proficient | 6 tablets | — | AB | FDA listed | — |
| Ondansetron 8 mg 63850-0004-01 | Natco | 30 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 67046-1242-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 68071-1742-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Ondansetron 8 mg 68071-3713-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Ondansetron 8 mg 68071-3801-01 | NuCare | 10 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 68071-4328-01 | NuCare | 10 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 68071-4705-04 | NuCare | 4 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 68071-4966-04 | NUCARE | 4 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 68788-8582-01 | Preferred | 10 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 68788-9402-01 | Preferred | 10 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 70518-3511-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Ondansetron 8 mg 70518-4245-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 71205-0744-10 | Proficient | 10 tablets | — | AB | FDA listed | — |
| ondansetron 8 mg 71335-0815-00 | Bryant | 5 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 71335-1357-00 | Bryant | 5 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 71610-0119-88 | Aphena | 900 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 72162-2365-05 | Bryant | 500 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 76420-0916-00 | Asclemed | 1000 tablets | — | AB | FDA listed | — |
| Ondansetron HCL 8 mg 80425-0074-01 | Advanced | 10 tablets | — | AB | FDA listed | — |
| Ondansetron HCL 8 mg 80425-0075-01 | Advanced | 10 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 85509-1076-01 | PHOENIX | 10 tablets | — | AB | FDA listed | — |
| Ondansetron Hydrochloride 8 mg 85766-0053-05 | Sportpharm | 5 tablets | — | AB | FDA listed | — |
| ondansetron 8 mg 67877-0170-30 | Ascend | 30 tablets | — | AB | FDA listed | — |
| ondansetron hydrochloride 8 mg 83980-0018-10 | Ipca | 1000 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 55700-0627-10 | 10 TABLET, FILM COATED in 1 BOTTLE (55700-627-10) | 2018-05-18 | Active |
| 55700-0627-12 | 12 TABLET, FILM COATED in 1 BOTTLE (55700-627-12) | 2018-05-18 | Discontinued by firm |
| 55700-0627-20 You're viewing this | 20 TABLET, FILM COATED in 1 BOTTLE (55700-627-20) | 2018-05-18 | Active |
| 55700-0627-30 | 30 TABLET, FILM COATED in 1 BOTTLE (55700-627-30) | 2018-05-18 | Active |
You're viewing one of 4 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 55700-0627-20?
What is the difference between NDC 55700-0627-20 and NDC 55700-0627-10?
What NDC number is used to bill for this package of Ondansetron Hydrochloride 8 mg Tablet, Film Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Ondansetron tablets are indicated for the prevention of nausea and vomiting associated with: highly emetogenic cancer chemotherapy, including cisplatin greater than or equal to 50 mg/m 2 initial and repeat courses of moderately emetogenic cancer chemotherapy radiotherapy in patients receiving either total body irradiation, single high-dose fraction to the abdomen, or daily fractions to the abdomen Ondansetron tablets are also indicated for the prevention of postoperative nausea and/or vomiting.
Ondansetron tablets are a 5-HT 3 receptor antagonist indicated for the prevention of: nausea and vomiting associated with highly emetogenic cancer chemotherapy, including cisplatin greater than or equal to 50 mg/m 2 (1) nausea and vomiting associated with initial and repeat courses of moderately emetogenic cancer chemotherapy (1) nausea and vomiting associated with radiotherapy in patients receiving either total body irradiation, single high-dose fraction to the abdomen, or daily fractions to the abdomen (1) postoperative nausea and/or vomiting (1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION See full prescribing information for the recommended dosage in adults and pediatrics. (2) Patients with severe hepatic impairment: do not exceed a total daily dose of 8 mg. (2.2 , 8.6 )
2.1Dosage The recommended dosage regimens for adult and pediatric patients are described in Table 1 and Table 2, respectively. Corresponding doses of ondansetron tablets, ondansetron orally disintegrating tablets and ondansetron oral solution may be used interchangeably. Table 1: Adult Recommended Dosage Regimen for Prevention of Nausea and Vomiting Indication Dosage Regimen Highly Emetogenic Cancer Chemotherapy A single 24 mg dose administered 30 minutes before the start of single-day highly emetogenic chemotherapy, including cisplatin greater than or equal to 50 mg/m 2 Moderately Emetogenic Cancer Chemotherapy 8 mg administered 30 minutes before the start of chemotherapy, with a subsequent 8 mg dose 8 hours after the first dose.
Then administer 8 mg twice a day (every 12 hours) for 1 to 2 days after completion of chemotherapy. Radiotherapy For total body irradiation : 8 mg administered 1 to 2 hours before each fraction of radiotherapy each day. For single high-dose fraction radiotherapy to the abdomen : 8 mg administered 1 to 2 hours before radiotherapy, with subsequent 8 mg doses every 8 hours after the first dose for 1 to 2 days after completion of radiotherapy.
For daily fractionated radiotherapy to the abdomen : 8 mg administered 1 to 2 hours before radiotherapy, with subsequent 8 mg doses every 8 hours after the first dose for each day radiotherapy is given. Postoperative 16 mg administered 1 hour before induction of anesthesia. Table 2: Pediatric Recommended Dosage Regimen for Prevention of Nausea and Vomiting Indication Dosage Regimen Moderately Emetogenic Cancer Chemotherapy 12 to 17 years of age: 8 mg administered 30 minutes before the start of chemotherapy, with a subsequent 8 mg dose 8 hours after the first dose.
Then administer 8 mg twice a day (every 12 hours) for 1 to 2 days after completion of chemotherapy. 4 to 11 years of age: 4 mg administered 30 minutes before the start of chemotherapy, with a subsequent 4 mg dose 4 and 8 hours after the first dose. Then administer 4 mg three times a day for 1 to 2 days after completion of chemotherapy.
2.2Dosage in Hepatic Impairment In patients with severe hepatic impairment (Child-Pugh score of 10 or greater), do not exceed a total daily dose of 8 mg [see Use in Specific Populations (8.6) , Clinical Pharmacology (12.3) ] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Ondansetron tablets USP, 4 mg are white to off-white, oval shaped, film-coated tablets debossed with ‘F’ on one side and ‘91’ on the other side. Ondansetron tablets USP, 8 mg are yellow colored, oval shaped, film-coated tablets debossed with ‘F’ on one side and ‘92’ on the other side. Ondansetron tablets USP, 24 mg are pink colored, oval shaped, film-coated tablets debossed with ‘C’ on one side and ‘71’ on the other side.
Tablets: 4 mg, 8 mg, and 24 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Ondansetron tablets are contraindicated in patients: known to have hypersensitivity (e.g., anaphylaxis) to ondansetron or any of the components of the formulation [see Adverse Reactions (6.2) ] receiving concomitant apomorphine due to the risk of profound hypotension and loss of consciousness Patients known to have hypersensitivity (e.g., anaphylaxis) to ondansetron or any components of the formulation. (4) Concomitant use of apomorphine (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypersensitivity reactions including anaphylaxis and bronchospasm : Discontinue ondansetron if suspected. Monitor and treat promptly per standard of care until signs and symptoms resolve. (5.1) QT interval prolongation and Torsade de Pointes : Avoid in patients with congenital long QT syndrome; monitor with electrocardiograms (ECGs) if concomitant electrolyte abnormalities, cardiac failure or arrhythmias, or use of other QT prolonging drugs.
(5.2) Serotonin syndrome : Reported with 5-HT 3 receptor antagonists alone but particularly with concomitant use of serotonergic drugs. If such symptoms occur, discontinue ondansetron and initiate supportive treatment. If concomitant use of ondansetron with other serotonergic drugs is clinically warranted, patients should be made aware of a potential increased risk for serotonin syndrome.
(5.3) Masking of progressive ileus and/or gastric distention following abdominal surgery or chemotherapy-induced nausea and vomiting : Monitor for decreased bowel activity, particularly in patients with risk factors for gastrointestinal obstruction. (5.4)
5.1Hypersensitivity Reactions Hypersensitivity reactions, including anaphylaxis and bronchospasm, have been reported in patients who have exhibited hypersensitivity to other selective 5-HT 3 receptor antagonists. If hypersensitivity reactions occur, discontinue use of ondansetron; treat promptly per standard of care and monitor until signs and symptoms resolve [see Contraindications (4)] .
5.2QT Prolongation Electrocardiogram (ECG) changes including QT interval prolongation have been seen in patients receiving ondansetron. In addition, postmarketing cases of Torsade de Pointes have been reported in patients using ondansetron. Avoid ondansetron in patients with congenital long QT syndrome.
ECG monitoring is recommended in patients with electrolyte abnormalities (e.g., hypokalemia or hypomagnesemia), congestive heart failure, bradyarrhythmias, or patients taking other medicinal products that lead to QT prolongation [see Clinical Pharmacology (12.2) ] .
5.3Serotonin Syndrome The development of serotonin syndrome has been reported with 5-HT 3 receptor antagonists alone. Most reports have been associated with concomitant use of serotonergic drugs (e.g., selective serotonin reuptake inhibitors (SSRIs), serotonin and norepinephrine reuptake inhibitors (SNRIs), monoamine oxidase inhibitors, mirtazapine, fentanyl, lithium, tramadol, and intravenous methylene blue). Some of the reported cases were fatal.
Serotonin syndrome occurring with overdose of ondansetron alone has also been reported. The majority of reports of serotonin syndrome related to 5-HT 3 receptor antagonist use occurred in a post-anesthesia care unit or an infusion center. Symptoms associated with serotonin syndrome may include the following combination of signs and symptoms: mental status changes (e.g., agitation, hallucinations, delirium, and coma), autonomic instability (e.g., tachycardia, labile blood pressure, dizziness, diaphoresis, flushing, hyperthermia), neuromuscular symptoms (e.g., tremor, rigidity, myoclonus, hyperreflexia, incoordination), seizures, with or without gastrointestinal symptoms (e.g., nausea, vomiting, diarrhea).
Patients should be monitored for the emergence of serotonin syndrome, especially with concomitant use of ondansetron and other serotonergic drugs. If symptoms of serotonin syndrome occur, discontinue ondansetron and initiate supportive treatment. Patients should be informed of the increased risk of serotonin syndrome, especially if ondansetron is used concomitantly with other serotonergic drugs [see Drug Interactions (7.1) , Overdosage (10) ] .
5.4Masking of Progressive Ileus and Gastric Distension The use of ondansetron in patients following abdominal surgery or in patients with chemotherapy-induced nausea and vomiting may mask a progressive ileus and/or gastric distension. Monitor for decreased bowel activity, particularly in patie…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reactions in adults for the: prevention of chemotherapy-induced (greater than or equal to 5%) are: headache, malaise/fatigue, constipation, diarrhea (6.1) prevention of radiation-induced nausea and vomiting (greater than or equal to 2%) are: headache, constipation, and diarrhea (6.1) prevention of postoperative nausea and vomiting (greater than or equal to 9%) are: headache and hypoxia (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. The following adverse reactions have been reported in clinical trials of patients treated with ondansetron, the active ingredient of ondansetron tablets. A causal relationship to therapy with ondansetron was unclear in many cases.
Prevention of Chemotherapy-Induced Nausea and Vomiting The most common adverse reactions reported in greater than or equal to 4% of 300 adults receiving a single 24 mg dose of ondansetron orally in 2 trials for the prevention of nausea and vomiting associated with highly emetogenic chemotherapy (cisplatin greater than or equal to 50 mg/m 2 ) were: headache (11%) and diarrhea (4%). The most common adverse reactions reported in 4 trials in adults for the prevention of nausea and vomiting associated with moderately emetogenic chemotherapy (primarily cyclophosphamide-based regimens) are shown in Table 3.
Table 3: Most Common Adverse Reactions in Adults a for the Prevention of Nausea and Vomiting Associated with Moderately Emetogenic Chemotherapy [Primarily Cyclophosphamide-based Regimens] a Reported in greater than or equal to 5% of patients treated with ondansetron and at a rate that exceeded placebo. Adverse Reaction Ondansetron 8 mg Twice Daily (n = 242) Placebo (n = 262) Headache 58 (24%) 34 (13%) Malaise/fatigue 32 (13%) 6 (2%) Constipation 22 (9%) 1 (<1%) Diarrhea 15 (6%) 10 (4%) Less Common Adverse Reactions Central Nervous System: Extrapyramidal reactions (less than 1% of patients).
Hepatic: Aspartate transaminase (AST) and/or alanine transaminase (ALT) values exceeded twice the upper limit of normal in approximately 1% to 2% of 723 patients receiving ondansetron and cyclophosphamide-based chemotherapy in U.S. clinical trials. The increases were transient and did not appear to be related to dose or duration of therapy. On repeat exposure, similar transient elevations in transaminase values occurred in some courses, but symptomatic hepatic disease did not occur.
The role of cancer chemotherapy in these biochemical changes is unclear. Liver failure and death has been reported in cancer patients receiving concurrent medications, including potentially hepatotoxic cytotoxic chemotherapy and antibiotics. The etiology of the liver failure is unclear.
Integumentary: Rash (approximately 1% of patients). Other (less than 2%): Anaphylaxis, bronchospasm, tachycardia, angina, hypokalemia, electrocardiographic alterations, vascular occlusive events, and grand mal seizures. Except for bronchospasm and anaphylaxis, the relationship to ondansetron is unclear.
Prevention of Radiation-Induced Nausea and Vomiting The most common adverse reactions (greater than or equal to 2%) reported in patients receiving ondansetron and concurrent radiotherapy were similar to those reported in patients receiving ondansetron and concurrent chemotherapy and were headache, constipation, and diarrhea. Prevention of Postoperative Nausea and Vomiting The most common adverse reactions reported in adults in trial(s) of prevention of postoperative nausea and vomiting are shown in Table 4. In these trial(s), patients were receiving multiple concomitant perioperative and postopera…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Serotonergic Drugs Serotonin syndrome (including altered mental status, autonomic instability, and neuromuscular symptoms) has been described following the concomitant use of 5-HT 3 receptor antagonists and other serotonergic drugs, including selective serotonin reuptake inhibitors (SSRIs) and serotonin and noradrenaline reuptake inhibitors (SNRIs). Monitor for the emergence of serotonin syndrome. If symptoms occur, discontinue ondansetron and initiate supportive treatment [see Warnings and Precautions (5.3) ] .
7.2Drugs Affecting Cytochrome P-450 Enzymes Ondansetron does not itself appear to induce or inhibit the cytochrome P-450 drug-metabolizing enzyme system of the liver [see Clinical Pharmacology (12.3) ] . Because ondansetron is metabolized by hepatic cytochrome P-450 drug-metabolizing enzymes (CYP3A4, CYP2D6, CYP1A2), inducers or inhibitors of these enzymes may change the clearance and, hence, the half-life of ondansetron. In patients treated with potent inducers of CYP3A4 (i.e., phenytoin, carbamazepine, and rifampin), the clearance of ondansetron was significantly increased and ondansetron blood concentrations were decreased.
However, on the basis of available data, no dosage adjustment for ondansetron is recommended for patients on these drugs [see Clinical Pharmacology (12.3) ] .
7.3Tramadol Although no pharmacokinetic drug interaction between ondansetron and tramadol has been observed, data from 2 small trials indicate that when used together, ondansetron may increase patient-controlled administration of tramadol. Monitor patients to ensure adequate pain control when ondansetron is administered with tramadol.
7.4Chemotherapy Carmustine, etoposide, and cisplatin do not affect the pharmacokinetics of ondansetron. In a crossover trial in 76 pediatric patients, intravenous ondansetron did not increase systemic concentrations of high-dose methotrexate.
7.5Alfentanil and Atracurium Ondansetron does not alter the respiratory depressant effects produced by alfentanil or the degree of neuromuscular blockade produced by atracurium. Interactions with general or local anesthetics have not been studied.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Available data do not reliably inform the association of ondansetron and adverse fetal outcomes. Published epidemiological studies on the association between ondansetron and fetal outcomes have reported inconsistent findings and have important methodological limitations hindering interpretation ( see Data ). Reproductive studies in rats and rabbits did not show evidence of harm to the fetus when ondansetron was administered during organogenesis at approximately 6 and 24 times the maximum recommended human oral dose of 24 mg/day, based on body surface area, respectively ( see Data ).
The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Human Data Methodological limitations of the epidemiology studies preclude a reliable evaluation of the potential risk of adverse fetal outcomes with the use of ondansetron in pregnancy.
Two large retrospective cohort studies of ondansetron use in pregnancy have been published. In one study with 1,349 infants born to women who reported the use of ondansetron or received an ondansetron prescription in the first trimester, no increased risk for major congenital malformations was seen in aggregate analysis. In this same study, however, a sub-analysis for specific malformations reported an association between ondansetron exposure and cardiovascular defect (odds ratio (OR) 1.62 [95% CI (1.04, 2.14)]) and cardiac septal defect (OR 2.05 [95% CI (1.19, 3.28)]).
The second study examined 1970 women who received ondansetron prescription during pregnancy and reported no association between ondansetron exposure and major congenital malformations, miscarriage or stillbirth, and infants of low-birth weight or small for gestational age. Important methodological limitations with these studies include the uncertainty of whether women who filled a prescription actually took the medication, the concomitant use of other medications or treatments, and other unadjusted confounders that may account for the study findings.
A case-control study evaluating associations between several common non-cardiac malformations and multiple antiemetic drugs reported an association between maternal use of ondansetron and isolated cleft palate (reported adjusted OR = 2.37 [95% CI (1.18, 4.76)]). However, this association could be a chance finding, given the large number of drugs-birth defect comparisons in this study. It is unknown whether ondansetron exposure in utero in the cases of cleft palate occurred during the time of palate formation (the palate is formed between the 6 th and 9 th weeks of pregnancy) or whether mothers of infants with cleft palate used other medications or had other risk factors for cleft palate in the offspring.
In addition, no cases of isolated cleft palate were identified in the aforementioned 2 large retrospective cohort studies. At this time, there is no clear evidence that ondansetron exposure in early pregnancy can cause cleft palate. Animal Data In embryo-fetal development studies in rats and rabbits, pregnant animals received oral doses of ondansetron up to 15 mg/kg/day and 30 mg/kg/day, respectively, during the period of organogenesis.
With the exception of a slight decrease in maternal body weight gain in the rabbits, there were no significant effects of ondansetron on the maternal animals or the development of the offspring. At doses of 15 mg/kg/day in rats and 30 mg/kg/day in rabbits, the maternal exposure margin was approximately 6 and 24 times the maximum recommended human oral dose of 24 mg/day, respectively, based on body surface area. In a pre- and postnatal developmental toxicity study, pregnant rats received oral doses of ondansetron up to 15 mg/kg/day from Day 17 of pregnancy to litter Day 21.
With the ex…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data do not reliably inform the association of ondansetron and adverse fetal outcomes. Published epidemiological studies on the association between ondansetron and fetal outcomes have reported inconsistent findings and have important methodological limitations hindering interpretation ( see Data ). Reproductive studies in rats and rabbits did not show evidence of harm to the fetus when ondansetron was administered during organogenesis at approximately 6 and 24 times the maximum recommended human oral dose of 24 mg/day, based on body surface area, respectively ( see Data ).
The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Human Data Methodological limitations of the epidemiology studies preclude a reliable evaluation of the potential risk of adverse fetal outcomes with the use of ondansetron in pregnancy.
Two large retrospective cohort studies of ondansetron use in pregnancy have been published. In one study with 1,349 infants born to women who reported the use of ondansetron or received an ondansetron prescription in the first trimester, no increased risk for major congenital malformations was seen in aggregate analysis. In this same study, however, a sub-analysis for specific malformations reported an association between ondansetron exposure and cardiovascular defect (odds ratio (OR) 1.62 [95% CI (1.04, 2.14)]) and cardiac septal defect (OR 2.05 [95% CI (1.19, 3.28)]).
The second study examined 1970 women who received ondansetron prescription during pregnancy and reported no association between ondansetron exposure and major congenital malformations, miscarriage or stillbirth, and infants of low-birth weight or small for gestational age. Important methodological limitations with these studies include the uncertainty of whether women who filled a prescription actually took the medication, the concomitant use of other medications or treatments, and other unadjusted confounders that may account for the study findings.
A case-control study evaluating associations between several common non-cardiac malformations and multiple antiemetic drugs reported an association between maternal use of ondansetron and isolated cleft palate (reported adjusted OR = 2.37 [95% CI (1.18, 4.76)]). However, this association could be a chance finding, given the large number of drugs-birth defect comparisons in this study. It is unknown whether ondansetron exposure in utero in the cases of cleft palate occurred during the time of palate formation (the palate is formed between the 6 th and 9 th weeks of pregnancy) or whether mothers of infants with cleft palate used other medications or had other risk factors for cleft palate in the offspring.
In addition, no cases of isolated cleft palate were identified in the aforementioned 2 large retrospective cohort studies. At this time, there is no clear evidence that ondansetron exposure in early pregnancy can cause cleft palate. Animal Data In embryo-fetal development studies in rats and rabbits, pregnant animals received oral doses of ondansetron up to 15 mg/kg/day and 30 mg/kg/day, respectively, during the period of organogenesis.
With the exception of a slight decrease in maternal body weight gain in the rabbits, there were no significant effects of ondansetron on the maternal animals or the development of the offspring. At doses of 15 mg/kg/day in rats and 30 mg/kg/day in rabbits, the maternal exposure margin was approximately 6 and 24 times the maximum recommended human oral dose of 24 mg/day, respectively, based on body surface area. In a pre- and postnatal developmental toxicity study, pregnant rats received oral doses of ondansetron up to 15 mg/kg/day from Day 17 of pregnancy to litter Day 21.
With the exception of a slight reduction…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of orally administered ondansetron have been established in pediatric patients 4 years and older for the prevention of nausea and vomiting associated with moderately emetogenic cancer chemotherapy. Use of ondansetron in these age-groups is supported by evidence from adequate and well- controlled studies of ondansetron in adults with additional data from 3 open-label, uncontrolled, non-US trials in 182 pediatric patients aged 4 to 18 years with cancer who were given a variety of cisplatin or noncisplatin regimens [see Dosage and Administration (2.2) , Clinical Studies (14.1) ] .
Additional information on the use of ondansetron in pediatric patients may be found in Ondansetron Injection prescribing information. The safety and effectiveness of orally administered ondansetron have not been established in pediatric patients for: prevention of nausea and vomiting associated with highly emetogenic cancer chemotherapy prevention of nausea and vomiting associated with radiotherapy prevention of postoperative nausea and/or vomiting
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects enrolled in cancer chemotherapy-induced and postoperative nausea and vomiting in U.S.- and foreign-controlled clinical trials, for which there were subgroup analyses, 938 (19%) were aged 65 years and older. No overall differences in safety or effectiveness were observed between subjects 65 years of age and older and younger subjects. A reduction in clearance and increase in elimination half-life were seen in patients older than 75 years compared with younger subjects [see Clinical Pharmacology (12.3) ] .
There were an insufficient number of patients older than 75 years of age and older in the clinical trials to permit safety or efficacy conclusions in this age-group. Other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. No dosage adjustment is needed in elderly patients.
🆘 Overdosage ▾
10 OVERDOSAGE There is no specific antidote for ondansetron overdose. Patients should be managed with appropriate supportive therapy. In addition to the adverse reactions listed above, the following adverse reactions have been described in the setting of ondansetron overdose: “Sudden blindness” (amaurosis) of 2 to 3 minutes’ duration plus severe constipation occurred in one patient that was administered 72 mg of ondansetron intravenously as a single dose.
Hypotension (and faintness) occurred in a patient that took 48 mg of ondansetron tablets. Following infusion of 32 mg over only a 4-minute period, a vasovagal episode with transient second-degree heart block was observed. In all instances, the adverse reactions resolved completely.
Pediatric cases consistent with serotonin syndrome have been reported after inadvertent oral overdoses of ondansetron (exceeding estimated ingestion of 5 mg per kg) in young children. Reported symptoms included somnolence, agitation, tachycardia, tachypnea, hypertension, flushing, mydriasis, diaphoresis, myoclonic movements, horizontal nystagmus, hyperreflexia, and seizure. Patients required supportive care, including intubation in some cases, with complete recovery without sequelae within 1 to 2 days.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ondansetron is a selective 5-HT 3 receptor antagonist. While its mechanism of action has not been fully characterized, ondansetron is not a dopamine-receptor antagonist. Serotonin receptors of the 5-HT 3 type are present both peripherally on vagal nerve terminals and centrally in the chemoreceptor trigger zone of the area postrema.
It is not certain whether ondansetron’s antiemetic action is mediated centrally, peripherally, or in both sites. However, cytotoxic chemotherapy appears to be associated with release of serotonin from the enterochromaffin cells of the small intestine. In humans, urinary 5-hydroxyindoleacetic acid (5-HIAA) excretion increases after cisplatin administration in parallel with the onset of emesis.
The released serotonin may stimulate the vagal afferents through the 5-HT 3 receptors and initiate the vomiting reflex.
12.2Pharmacodynamics In healthy subjects, single intravenous doses of 0.15 mg/kg of ondansetron had no effect on esophageal motility, gastric motility, lower esophageal sphincter pressure, or small intestinal transit time. Multiday administration of ondansetron has been shown to slow colonic transit in healthy subjects. Ondansetron has no effect on plasma-prolactin concentrations.
Cardiac Electrophysiology QTc interval prolongation was studied in a double-blind, single-intravenous dose, placebo- and positive- controlled, crossover trial in 58 healthy subjects. The maximum mean (95% upper confidence bound) difference in QTcF from placebo after baseline correction was 19.5 (21.8) milliseconds and 5.6 (7.4) milliseconds after 15- minute intravenous infusions of 32 mg and 8 mg of ondansetron injection, respectively. A significant exposure- response relationship was identified between ondansetron concentration and ΔΔQTcF.
Using the established exposure-response relationship, 24 mg infused intravenously over 15 minutes had a mean predicted (95% upper prediction interval) ΔΔQTcF of 14.0 (16.3) milliseconds. In contrast, 16 mg infused intravenously over 15 minutes using the same model had a mean predicted (95% upper prediction interval) ΔΔQTcF of 9.1 (11.2) milliseconds. In this study, the 8 mg dose infused over 15 minutes did not prolong the QT interval to any clinically relevant extent.
12.3Pharmacokinetics Absorption Ondansetron is absorbed from the gastrointestinal tract and undergoes some first-pass metabolism. Mean bioavailability in healthy subjects, following administration of a single 8 mg tablet, is approximately 56%. Ondansetron systemic exposure does not increase proportionately to dose.
The area under curve (AUC) from a 16 mg tablet was 24% greater than predicted from an 8 mg tablet dose. This may reflect some reduction of first-pass metabolism at higher oral doses. Food Effects: Bioavailability is also slightly enhanced by the presence of food.
Distribution Plasma protein binding of ondansetron as measured in vitro was 70% to 76% over the concentration range of 10 to 500 ng/mL. Circulating drug also distributes into erythrocytes. Elimination Metabolism and Excretion: Ondansetron is extensively metabolized in humans, with approximately 5% of a radiolabeled dose recovered as the parent compound from the urine.
The metabolites are observed in the urine. The primary metabolic pathway is hydroxylation on the indole ring followed by subsequent glucuronide or sulfate conjugation. In vitro metabolism studies have shown that ondansetron is a substrate for human hepatic cytochrome P-450 enzymes, including CYP1A2, CYP2D6, and CYP3A4.
In terms of overall ondansetron turnover, CYP3A4 played the predominant role. Because of the multiplicity of metabolic enzymes capable of metabolizing ondansetron, it is likely that inhibition or loss of one enzyme (e.g., CYP2D6 genetic deficiency) will be compensated by others and may result in little change in overall rates of ondansetron elimination. Although some nonconjugated metabolites have pharmacologic activ…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ondansetron is a selective 5-HT 3 receptor antagonist. While its mechanism of action has not been fully characterized, ondansetron is not a dopamine-receptor antagonist. Serotonin receptors of the 5-HT 3 type are present both peripherally on vagal nerve terminals and centrally in the chemoreceptor trigger zone of the area postrema.
It is not certain whether ondansetron’s antiemetic action is mediated centrally, peripherally, or in both sites. However, cytotoxic chemotherapy appears to be associated with release of serotonin from the enterochromaffin cells of the small intestine. In humans, urinary 5-hydroxyindoleacetic acid (5-HIAA) excretion increases after cisplatin administration in parallel with the onset of emesis.
The released serotonin may stimulate the vagal afferents through the 5-HT 3 receptors and initiate the vomiting reflex.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Ondansetron Tablets USP, 4 mg are white to off-white, oval shaped, film-coated tablets debossed with ‘F’ on one side and ‘91’ on the other side. Ondansetron Tablets USP, 8 mg are yellow colored, oval shaped, film-coated tablets debossed with ‘F’ on one side and ‘92’ on the other side. 55700-627-10 55700-627-12 55700-627-20 55700-627-30 Ondansetron Tablets USP, 24 mg are pink colored, oval shaped, film-coated tablets debossed with ‘C’ on one side and ‘71’ on the other side.
Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Protect from light.
📋 Description ▾
11 DESCRIPTION The active ingredient in ondansetron tablets, USP is ondansetron hydrochloride as the dihydrate, the racemic form of ondansetron and a selective blocking agent of the serotonin 5-HT 3 receptor type. Chemically it is (±) 1, 2, 3, 9-tetrahydro-9-methyl-3-[(2-methyl-1H-imidazol-1-yl)methyl]-4H-carbazol-4-one, monohydrochloride, dihydrate. It has the following structural formula: The molecular formula is C 18 H 19 N 3 O•HCl•2H 2 O, representing a molecular weight of 365.9.
Ondansetron hydrochloride USP (dihydrate) is a white to off-white powder that is soluble in water and normal saline. Ondansetron tablets, USP for oral administration contain ondansetron hydrochloride USP (dihydrate) equivalent to 4 mg or 8 mg or 24 mg of ondansetron. Each film-coated tablet also contains the inactive ingredients anhydrous lactose, microcrystalline cellulose, pregelatinized starch (maize), magnesium stearate, triacetin, titanium dioxide and hypromellose.
In addition 8 mg tablet also contains iron oxide yellow and 24 mg tablet also contains iron oxide red. Meets USP dissolution test 6. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION QT Prolongation Inform patients that ondansetron tablets may cause serious cardiac arrhythmias such as QT prolongation. Instruct patients to tell their healthcare provider right away if they perceive a change in their heart rate, if they feel lightheaded, or if they have a syncopal episode. Hypersensitivity Reactions Inform patients that ondansetron tablets may cause hypersensitivity reactions, some as severe as anaphylaxis and bronchospasm.
Instruct patients to immediately report any signs and symptoms of hypersensitivity reactions, including fever, chills, rash, or breathing problems to their healthcare provider. Masking of Progressive Ileus and Gastric Distension Inform patients following abdominal surgery or those with chemotherapy-induced nausea and vomiting that ondansetron tablets may mask signs and symptoms of bowel obstruction. Instruct patients to immediately report any signs or symptoms consistent with a potential bowel obstruction to their healthcare provider.
Drug Interactions Instruct the patient to report the use of all medications, especially apomorphine, to their healthcare provider. Concomitant use of apomorphine and ondansetron may cause a significant drop in blood pressure and loss of consciousness. Advise patients of the possibility of serotonin syndrome with concomitant use of ondansetron and another serotonergic agent such as medications to treat depression and migraines.
Advise patients to seek immediate medical attention if the following symptoms occur: changes in mental status, autonomic instability, neuromuscular symptoms with or without gastrointestinal symptoms. Distributed by: Aurobindo Pharma USA, Inc. 2400 Route 130 North Dayton, NJ 08810 Manufactured by: Aurobindo Pharma Limited Hyderabad–500 038, India Revised: 11/2017