
Lisdexamfetamine Dimesylate 60 mg Tablet, Chewable, 100-count — NDC 57664-088-88 (Billing 57664-0088-88)
This is a package of 100 tablets of Lisdexamfetamine Dimesylate 60 mg Tablet, Chewable from Sun Pharmaceutical Industries, Inc., marketed since Aug 2023 and currently FDA-listed; retail pharmacies pay about $3.65 per tablet (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 57664-088-88 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 57664 labeler · 088 product · 88 package
- Package marketed since
- Aug 25, 2023
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 100 EA per package
- Barcode (UPC-A, from the NDC)
- 3 5766408888 3
- Medicaid fills, this package
- 2,139 prescriptions in the last four reported quarters
- FDA record last changed
- Aug 13, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 077146
- GCN: 43065
- HICL (First Databank): 034486
- AHFS class code: 28:20.04.00
- RxCUI (RxNorm): 854830
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Central Nervous System Stimulant class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Lisdexamfetamine is used to treat two conditions: ADHD in adults and kids age 6 and older, and moderate to severe binge eating disorder in adults. It's not approved for weight loss...
- What exactly is lisdexamfetamine used for?
- The most common ones are decreased appetite, trouble sleeping, dry mouth, nausea, and weight loss. Some people also feel jittery or anxious, especially early on. Most of these tend...
- What are the most common side effects I should expect?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $3.646 | $364.60 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $6.98 | $698.33 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $8.85 | $885.32 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 57664-0088-88 You're viewing this Main listing | 100 TABLET, CHEWABLE in 1 BOTTLE | 2023-08-25 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lisdexamfetamine Dimesylate 60 mg 00406-5129-01 | SpecGx | 100 tablets | $3.646 | AB | Availability likely | — |
| lisdexamfetamine dimesylate 60 mg 00480-9744-01 | Teva | 100 tablets | $3.646 | AB | Availability likely | — |
| Lisdexamfetamine Dimesylate 60 mg 31722-0326-01 | Camber | 100 tablets | $3.646 | AB | Availability likely | — |
| Lisdexamfetamine Dimesylate 60 mgthis 57664-0088-88 | Sun | 100 tablets | $3.646 | AB | Availability likely | — |
| Lisdexamfetamine dimesylate 60 mg 70010-0219-01 | Granules | 100 tablets | $3.646 | AB | Availability likely | — |
| Lisdexamfetamine dimesylate 60 mg 72205-0137-91 | Novadoz | 100 tablets | $3.646 | AB | Availability likely | — |
| Vyvanse 60 mg 59417-0120-01 | Takeda | 100 tablets | $12.365 | AB | Availability likely | +239% |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Sun Pharmaceutical Industries, Inc. labeler code 57664
- Levorphanol Tartrate 3 mg Tablet NDC 57664-058-88
- Lisdexamfetamine Dimesylate 10 mg Tablet, Chewable NDC 57664-083-88
- Lisdexamfetamine Dimesylate 20 mg Tablet, Chewable NDC 57664-084-88
- Lisdexamfetamine Dimesylate 30 mg Tablet, Chewable NDC 57664-085-88
- Lisdexamfetamine Dimesylate 40 mg Tablet, Chewable NDC 57664-086-88
- Lisdexamfetamine Dimesylate 50 mg Tablet, Chewable NDC 57664-087-88
- Methylphenidate Hydrochloride 5 mg Tablet NDC 57664-228-08
- Methylphenidate Hydrochloride 10 mg Tablet NDC 57664-229-08
- Methylphenidate Hydrochloride 20 mg Tablet NDC 57664-230-08
- Nitrofurantion 25 mg Capsule NDC 57664-231-18
- Nitrofurantion 50 mg Capsule NDC 57664-232-18
- Nitrofurantion 100 mg Capsule NDC 57664-233-18
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: ABUSE, MISUSE, AND ADDICTION Lisdexamfetamine dimesylate has a high potential for abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Misuse and abuse of CNS stimulants, including lisdexamfetamine dimesylate, can result in overdose and death [see Overdosage (10) ] , and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection. Before prescribing lisdexamfetamine dimesylate, assess each patient’s risk for abuse, misuse, and addiction.
Educate patients and their families about these risks, proper storage of the drug, and proper disposal of any unused drug. Throughout lisdexamfetamine dimesylate treatment, reassess each patient’s risk of abuse, misuse, and addiction and frequently monitor for signs and symptoms of abuse, misuse, and addiction [see Warnings and Precautions (5.1) , Drug Abuse and Dependence (9.2) ]. WARNING: ABUSE, MISUSE, AND ADDICTION See full prescribing information for complete boxed warning.
Lisdexamfetamine dimesylate has a high potential for abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Misuse and abuse of CNS stimulants, including lisdexamfetamine dimesylate, can result in overdose and death ( 5.1 , 9.2 , 10 ): Before prescribing lisdexamfetamine dimesylate, assess each patient’s risk for abuse, misuse, and addiction. Educate patients and their families about these risks, proper storage of the drug, and proper disposal of any unused drug.
Throughout treatment, reassess each patient’s risk and frequently monitor for signs and symptoms of abuse, misuse, and addiction.
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Lisdexamfetamine dimesylate capsules and lisdexamfetamine dimesylate chewable tablets are indicated for the treatment of: Attention Deficit Hyperactivity Disorder (ADHD) in adults and pediatric patients 6 years and older [see Clinical Studies ( 14.1 )] Moderate to severe binge eating disorder (BED) in adults [see Clinical Studies ( 14.2 )] . Limitations of Use: The use of lisdexamfetamine dimesylate is not recommended in pediatric patients younger than 6 years of age because they had higher plasma exposure and a higher incidence of adverse reactions (e.g., weight loss) than patients 6 years and older at the same dosage [see Warnings and Precautions (5.5), Use in Specific Populations (8.4)].
Lisdexamfetamine dimesylate is not indicated or recommended for weight loss. Use of other sympathomimetic drugs for weight loss has been associated with serious cardiovascular adverse events. The safety and effectiveness of lisdexamfetamine dimesylate for the treatment of obesity have not been established [see Warnings and Precautions ( 5.2 )] .
Lisdexamfetamine dimesylate capsules and lisdexamfetamine dimesylate chewable tablets are a central nervous system (CNS) stimulant indicated for the treatment of ( 1 ): Attention Deficit Hyperactivity Disorder (ADHD) in adults and pediatric patients 6 years and older Moderate to severe binge eating disorder (BED) in adults Limitations of Use: The use of lisdexamfetamine dimesylate is not recommended in pediatric patients younger than 6 years of age because they had higher plasma exposure and a higher incidence of adverse reactions (e.g., weight loss) than patients 6 years and older at the same dosage (5.5, 8.4) Lisdexamfetamine dimesylate is not indicated for weight loss.
Use of other sympathomimetic drugs for weight loss has been associated with serious cardiovascular adverse events. The safety and effectiveness of lisdexamfetamine dimesylate for the treatment of obesity have not been established ( 5.2 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Prior to treatment, assess for presence of cardiac disease ( 2.4 ) Severe renal impairment: Maximum dose is 50 mg/day ( 2.5 ) End stage renal disease (ESRD): Maximum dose is 30 mg/day ( 2.5 )
2.1Pre-treatment Screening Prior to treating patients with lisdexamfetamine dimesylate, assess: for the presence of cardiac disease (i.e., perform a careful history, family history of sudden death or ventricular arrhythmia, and physical exam) [see Warnings and Precautions (5.2) ]. the family history and clinically evaluate patients for motor or verbal tics or Tourette’s syndrome before initiating lisdexamfetamine dimesylate [see Warnings and Precautions (5.8) ].
2.2General Administration Information Take lisdexamfetamine dimesylate orally in the morning with or without food; avoid afternoon doses because of the potential for insomnia. Lisdexamfetamine dimesylate may be administered in one of the following ways: Information for lisdexamfetamine dimesylate capsules: Swallow lisdexamfetamine dimesylate capsules whole, or Open capsules, empty and mix the entire contents with yogurt, water, or orange juice. If the contents of the capsule include any compacted powder, a spoon may be used to break apart the powder.
The contents should be mixed until completely dispersed. Consume the entire mixture immediately . It should not be stored.
The active ingredient dissolves completely once dispersed; however, a film containing the inactive ingredients may remain in the glass or container once the mixture is consumed. Information for lisdexamfetamine dimesylate chewable tablets: Lisdexamfetamine dimesylate chewable tablets must be chewed thoroughly before swallowing. Lisdexamfetamine dimesylate capsules can be substituted with lisdexamfetamine dimesylate chewable tablets on a unit per unit/mg per mg basis (for example, 30 mg capsules for 30 mg chewable tablet) [see Clinical Pharmacology ( 12.3 ) ].
Do not take anything less than one capsule or chewable tablet per day. A single dose should not be divided.
2.3Dosage for Treatment of ADHD The recommended starting dosage in adults and pediatric patients 6 years and older is 30 mg once daily in the morning. Dosage may be adjusted in increments of 10 mg or 20 mg at approximately weekly intervals up to maximum recommended dosage of 70 mg once daily [see Clinical Studies ( 14.1 )] .
2.4Dosage for Treatment of Moderate to Severe BED in Adults The recommended starting dosage in adults is 30 mg once daily to be titrated in increments of 20 mg at approximately weekly intervals to achieve the recommended target dose of 50 mg to 70 mg once daily. The maximum recommended dosage is 70 mg once daily [see Clinical Studies ( 14.2 )] . Discontinue lisdexamfetamine dimesylate if binge eating does not improve.
2.5Dosage in Patients with Renal Impairment In patients with severe renal impairment (GFR 15 to < 30 mL/min/1.73 m 2 ), the maximum dosage should not exceed 50 mg once daily. In patients with end stage renal disease (ESRD, GFR < 15 mL/min/1.73 m 2 ), the maximum recommended dosage is 30 mg once daily [see Use in Specific Populations ( 8.6 )] .
2.6Dosage Modifications due to Drug Interactions Agents that alter urinary pH can impact urinary excretion and alter blood levels of amphetamine. Acidifying agents (e.g., ascorbic acid) decrease blood levels, while alkalinizing agents (e.g., sodium bicarbonate) increase blood levels. Adjust lisdexamfetamine dimesylate dosage accordingly [see Drug Interactions ( 7.1 )] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Lisdexamfetamine Dimesylate Capsules: Capsules 10 mg: Pink opaque cap/pink opaque body (imprinted with 'RM46' on cap and '10 mg' on body). Capsules 20 mg: Off white opaque cap /off white opaque body (imprinted with 'RM47' on cap and '20 mg' on body). Capsules 30 mg: Orange opaque cap/white opaque body (imprinted with 'RM48' on cap and '30 mg' on body).
Capsules 40 mg: Dark green opaque cap/white opaque body (imprinted with 'RM49' on cap and '40 mg' on body). Capsules 50 mg: Blue opaque cap/white opaque body (imprinted with 'RM50' on cap and '50 mg' on body). Capsules 60 mg: Aqua blue opaque cap/aqua blue opaque body (imprinted with 'RM51' on cap and '60 mg' on body).
Capsules 70 mg: Blue opaque cap/orange opaque body (imprinted with 'RM52' on cap and '70 mg' on body). Lisdexamfetamine Dimesylate Chewable Tablets: Chewable tablets 10 mg: White to off-white round shaped tablet debossed with ‘10’ on one side and ‘S83’ on the other side Chewable tablets 20 mg: White to off-white hexagonal shaped tablet debossed with ‘20’ on one side and ‘S84’ on the other side Chewable tablets 30 mg: White to off-white arc triangular shaped tablet debossed with ‘30’ on one side and ‘S85’ on the other side Chewable tablets 40 mg: White to off-white capsule shaped tablet debossed with ‘40’ on one side and ‘S86’ on the other side Chewable tablets 50 mg: White to off-white arc square shaped tablet debossed with ‘50’ on one side and ‘S87’ on the other side Chewable tablets 60 mg: White to off-white arc diamond shaped tablet debossed with ‘60’ on one side and ‘S88’ on the other side Capsules: 10 mg, 20 mg, 30 mg, 40 mg, 50 mg, 60 mg, 70 mg ( 3 ) Chewable tablets: 10 mg, 20 mg, 30 mg, 40 mg, 50 mg, 60 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Lisdexamfetamine dimesylate is contraindicated in patients with: Known hypersensitivity to amphetamine products or other ingredients of lisdexamfetamine dimesylate capsules and lisdexamfetamine dimesylate chewable tablets. Anaphylactic reactions, Stevens-Johnson Syndrome, angioedema, and urticaria have been observed in postmarketing reports [see Adverse Reactions ( 6.2 )] . Patients taking monoamine oxidase inhibitors (MAOIs), or within 14 days of stopping MAOIs (including MAOIs such as linezolid or intravenous methylene blue), because of an increased risk of hypertensive crisis [see Warnings and Precautions ( 5.7 ) and Drug Interactions ( 7.1 )].
Known hypersensitivity to amphetamine products or other ingredients in lisdexamfetamine dimesylate capsules and lisdexamfetamine dimesylate chewable tablets ( 4 ) Use with monoamine oxidase (MAO) inhibitor, or within 14 days of the last MAO inhibitor dose ( 4 , 7.1 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Risks to Patients with Serious Cardiac Disease: Avoid use in patients with known structural cardiac abnormalities, cardiomyopathy, serious cardiac arrhythmia, coronary artery disease, or other serious cardiac disease (5.2) Increased Blood Pressure and Heart Rate: Monitor blood pressure and pulse. (5.3) Psychiatric Adverse Reactions: Prior to initiating lisdexamfetamine dimesylate, screen patients for risk factors for developing a manic episode. If new psychotic or manic symptoms occur, consider discontinuing lisdexamfetamine dimesylate.
(5.4) Long-Term Suppression of Growth in Pediatric Patients: Closely monitor growth (height and weight) in pediatric patients. Pediatric patients not growing or gaining height or weight as expected may need to have their treatment interrupted. (5.5) Peripheral Vasculopathy, including Raynaud’s phenomenon: Careful observation for digital changes is necessary during lisdexamfetamine dimesylate treatment.
Further clinical evaluation (e.g., rheumatology referral) may be appropriate for patients who develop signs or symptoms of peripheral vasculopathy. (5.6) Serotonin Syndrome: Increased risk when co-administered with serotonergic agents (e.g., SSRIs, SNRIs, triptans), but also during overdosage situations. If it occurs, discontinue lisdexamfetamine dimesylate and initiate supportive treatment ( 4 , 5.7 , 10 ) Motor and Verbal Tics, and Worsening of Tourette’s Syndrome: Before initiating lisdexamfetamine dimesylate, assess the family history and clinically evaluate patients for tics or Tourette’s syndrome.
Regularly monitor patients for the emergence or worsening of tics or Tourette’s syndrome. Discontinue treatment if clinically appropriate. (5.8)
5.1Abuse, Misuse, and Addiction Lisdexamfetamine dimesylate has a high potential for abuse and misuse. The use of lisdexamfetamine dimesylate exposes individuals to the risks of abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Lisdexamfetamine dimesylate can be diverted for non-medical use into illicit channels or distribution [see Drug Abuse and Dependence (9.2) ].
Misuse and abuse of CNS stimulants, including lisdexamfetamine dimesylate, can result in overdose and death [see Overdosage (10) ] , and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection. Before prescribing lisdexamfetamine dimesylate, assess each patient’s risk for abuse, misuse, and addiction. Educate patients and their families about these risks and proper disposal of any unused drug.
Advise patients to store lisdexamfetamine dimesylate in a safe place, preferably locked, and instruct patients to not give lisdexamfetamine dimesylate to anyone else. Throughout lisdexamfetamine dimesylate treatment, reassess each patient’s risk of abuse, misuse, and addiction and frequently monitor for signs and symptoms of abuse, misuse, and addiction.
5.2Risks to Patients with Serious Cardiac Disease Sudden death has been reported in patients with structural cardiac abnormalities or other serious cardiac disease who were treated with CNS stimulants at the recommended ADHD dosage. Avoid lisdexamfetamine dimesylate use in patients with known structural cardiac abnormalities, cardiomyopathy, serious cardiac arrhythmia, coronary artery disease, or other serious cardiac disease.
5.3Increased Blood Pressure and Heart Rate CNS stimulants cause an increase in blood pressure (mean increase about 2 to 4 mm Hg) and heart rate (mean increase about 3 to 6 bpm). Some patients may have larger increases. Monitor all lisdexamfetamine dimesylate-treated patients for potential tachycardia and hypertension.
5.4Psychiatric Adverse Reactions Exacerbation of Pre-existing Psychosis CNS stimulants may exacerbate symptoms of behavior disturbance and thought disorder in patients with a pre-existing psychotic disorder. Induction of a Manic Episode in Patients with Bipolar Disorder CNS stimul… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: Known hypersensitivity to amphetamine products or other ingredients of lisdexamfetamine dimesylate capsules and lisdexamfetamine dimesylate chewable tablets [see Contraindications ( 4 )] Hypertensive Crisis When Used Concomitantly with Monoamine Oxidase Inhibitors [see Contraindications ( 4 ) and Drug Interactions ( 7.1 )] Abuse, Misuse, and Addiction [see Boxed Warning, Warnings and Precautions ( 5.1 ), and Drug Abuse and Dependence ( 9.2 , 9.3 )] Risks to Patients with Serious Cardiac Disease [see Warnings and Precautions ( 5.2 )] Increased Blood Pressure and Heart Rate [see Warnings and Precautions ( 5.3 )] Psychiatric Adverse Reactions [see Warnings and Precautions ( 5.4 )] Long-Term Suppression of Growth in Pediatric Patients [see Warnings and Precautions ( 5.5 )] Peripheral Vasculopathy, including Raynaud’s phenomenon [see Warnings and Precautions ( 5.6 )] Serotonin Syndrome [see Warnings and Precautions ( 5.7 )] Motor and Verbal Tics, and Worsening of Tourette’s Syndrome [see Warnings and Precautions (5.8) ] Most common adverse reactions (incidence ≥ 5% and at a rate at least twice placebo) in pediatric patients ages 6 to 17 years, and/or adults with ADHD were anorexia, anxiety, decreased appetite, decreased weight, diarrhea, dizziness, dry mouth, irritability, insomnia, nausea, upper abdominal pain, and vomiting ( 6.1 ) Most common adverse reactions (incidence ≥5% and at a rate at least twice placebo) in adults with BED were dry mouth, insomnia, decreased appetite, increased heart rate, constipation, feeling jittery, and anxiety ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Sun Pharmaceutical Industries, Inc. at 1-800-406-7984 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Attention Deficit Hyperactivity Disorder The safety data in this section is based on data from the 4-week controlled parallel-group clinical studies of lisdexamfetamine dimesylate in pediatric and adult patients with ADHD [see Clinical Studies ( 14.1 )] .
Adverse Reactions Associated with Discontinuation of Treatment in ADHD Clinical Trials In the controlled trial in pediatric patients ages 6 to 12 years (Study 1), 8% (18/218) of lisdexamfetamine dimesylate-treated patients discontinued due to adverse reactions compared to 0% (0/72) of placebo-treated patients. The most frequently reported adverse reactions (1% or more and twice rate of placebo) were ECG voltage criteria for ventricular hypertrophy, tic, vomiting, psychomotor hyperactivity, insomnia, decreased appetite and rash [2 instances for each adverse reaction, i.e., 2/218 (1%)].
Less frequently reported adverse reactions (less than 1% or less than twice rate of placebo) included abdominal pain upper, dry mouth, weight decreased, dizziness, somnolence, logorrhea, chest pain, anger and hypertension. In the controlled trial in pediatric patients ages 13 to 17 years (Study 4), 3% (7/233) of lisdexamfetamine dimesylate-treated patients discontinued due to adverse reactions compared to 1% (1/77) of placebo-treated patients. The most frequently reported adverse reactions (1% or more and twice rate of placebo) were decreased appetite (2/233; 1%) and insomnia (2/233; 1%).
Less frequently reported adverse reactions (less than 1% or less than twice rate of placebo) included irritability, dermatillomania, mood swings, and dyspnea. In the controlled adult trial (Study 7), 6% (21/358) of lisdexamfetamine dimesylate-treated patients discontinued due to adverse reactions compared to 2% (1/62) of placebo-treated patients. The most frequently reported adverse reactions (1% or more and twice ra… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Acidifying and Alkalinizing Agents: Agents that alter urinary pH can alter blood levels of amphetamine. Acidifying agents decrease amphetamine blood levels, while alkalinizing agents increase amphetamine blood levels. Adjust lisdexamfetamine dimesylate dosage accordingly ( 2.6 , 7.1 )
7.1Drugs Having Clinically Important Interactions with Amphetamines Table 5 Drugs having clinically important interactions with amphetamines. table 5
7.2Interference with Laboratory Test Allow for an adequate washout period between administration of lisdexamfetamine dimesylate and radioactive diagnostic agents used for dopamine transporter (DAT) visualization. Lisdexamfetamine dimesylate can interfere with the test results of a radioactive diagnostic agent (ioflupane I-123) that is used for DAT visualization by binding and internalization of the DAT, which may result in lower DAT in the striatum. This may lead to false-positive diagnostic results.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy : May cause fetal harm ( 8.1 ) Lactation: Breastfeeding not recommended ( 8.2 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ADHD medications during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Psychostimulants at 1-866-961-2388 or visiting online at https://womensmentalhealth.org/clinical-and researchprograms/pregnancyregistry/adhd-medications/. Risk Summary The limited available data from published literature and postmarketing reports on use of lisdexamfetamine dimesylate in pregnant women are not sufficient to inform a drug-associated risk for major birth defects and miscarriage.
Adverse pregnancy outcomes, including premature delivery and low birth weight, have been seen in infants born to mothers dependent on amphetamines [see Clinical Considerations] . In animal reproduction studies, lisdexamfetamine dimesylate (a prodrug of d-amphetamine) had no effects on embryo-fetal morphological development or survival when administered orally to pregnant rats and rabbits throughout the period of organogenesis. Pre- and postnatal studies were not conducted with lisdexamfetamine dimesylate.
However, amphetamine (d- to l- ratio of 3:1) administration to pregnant rats during gestation and lactation caused a decrease in pup survival and a decrease in pup body weight that correlated with a delay in developmental landmarks at clinically relevant doses of amphetamine. In addition, adverse effects on reproductive performance were observed in pups whose mothers were treated with amphetamine. Long-term neurochemical and behavioral effects have also been reported in animal developmental studies using clinically relevant doses of amphetamine [see Data] .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Fetal/Neonatal Adverse Reactions Amphetamines, such as lisdexamfetamine dimesylate, cause vasoconstriction and thereby may decrease placental perfusion. In addition, amphetamines can stimulate uterine contractions increasing the risk of premature delivery. Infants born to amphetamine-dependent mothers have an increased risk of premature delivery and low birth weight.
Monitor infants born to mothers taking amphetamines for symptoms of withdrawal such as feeding difficulties, irritability, agitation, and excessive drowsiness. Data Animal Data Lisdexamfetamine dimesylate had no apparent effects on embryo-fetal morphological development or survival when administered orally to pregnant rats and rabbits throughout the period of organogenesis at doses of up to 40 and 120 mg/kg/day, respectively. These doses are approximately 5.5 and 33 times, respectively, the maximum recommended human dose (MRHD) of 70 mg/day given to adults, on a mg/m 2 body surface area basis.
A study was conducted with amphetamine (d- to l- enantiomer ratio of 3:1) in which pregnant rats received daily oral doses of 2, 6, and 10 mg/kg from gestation day 6 to lactation day 20. All doses caused hyperactivity and decreased weight gain in the dams. A decrease in pup survival was seen at all doses.
A decrease in pup body weight was seen at 6 and 10 mg/kg which correlated with delays in developmental landmarks, such as preputial separation and vaginal opening. Increased pup locomotor activity was seen at 10 mg/kg on day 22 postpartum but not at 5 weeks postweaning. When pups were tested for reproductive performance at maturation, gestational weight gain, number of implantations, and number of delivered pups were decreased in the group whose mothers… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ADHD medications during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Psychostimulants at 1-866-961-2388 or visiting online at https://womensmentalhealth.org/clinical-and researchprograms/pregnancyregistry/adhd-medications/. Risk Summary The limited available data from published literature and postmarketing reports on use of lisdexamfetamine dimesylate in pregnant women are not sufficient to inform a drug-associated risk for major birth defects and miscarriage.
Adverse pregnancy outcomes, including premature delivery and low birth weight, have been seen in infants born to mothers dependent on amphetamines [see Clinical Considerations] . In animal reproduction studies, lisdexamfetamine dimesylate (a prodrug of d-amphetamine) had no effects on embryo-fetal morphological development or survival when administered orally to pregnant rats and rabbits throughout the period of organogenesis. Pre- and postnatal studies were not conducted with lisdexamfetamine dimesylate.
However, amphetamine (d- to l- ratio of 3:1) administration to pregnant rats during gestation and lactation caused a decrease in pup survival and a decrease in pup body weight that correlated with a delay in developmental landmarks at clinically relevant doses of amphetamine. In addition, adverse effects on reproductive performance were observed in pups whose mothers were treated with amphetamine. Long-term neurochemical and behavioral effects have also been reported in animal developmental studies using clinically relevant doses of amphetamine [see Data] .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Fetal/Neonatal Adverse Reactions Amphetamines, such as lisdexamfetamine dimesylate, cause vasoconstriction and thereby may decrease placental perfusion. In addition, amphetamines can stimulate uterine contractions increasing the risk of premature delivery. Infants born to amphetamine-dependent mothers have an increased risk of premature delivery and low birth weight.
Monitor infants born to mothers taking amphetamines for symptoms of withdrawal such as feeding difficulties, irritability, agitation, and excessive drowsiness. Data Animal Data Lisdexamfetamine dimesylate had no apparent effects on embryo-fetal morphological development or survival when administered orally to pregnant rats and rabbits throughout the period of organogenesis at doses of up to 40 and 120 mg/kg/day, respectively. These doses are approximately 5.5 and 33 times, respectively, the maximum recommended human dose (MRHD) of 70 mg/day given to adults, on a mg/m 2 body surface area basis.
A study was conducted with amphetamine (d- to l- enantiomer ratio of 3:1) in which pregnant rats received daily oral doses of 2, 6, and 10 mg/kg from gestation day 6 to lactation day 20. All doses caused hyperactivity and decreased weight gain in the dams. A decrease in pup survival was seen at all doses.
A decrease in pup body weight was seen at 6 and 10 mg/kg which correlated with delays in developmental landmarks, such as preputial separation and vaginal opening. Increased pup locomotor activity was seen at 10 mg/kg on day 22 postpartum but not at 5 weeks postweaning. When pups were tested for reproductive performance at maturation, gestational weight gain, number of implantations, and number of delivered pups were decreased in the group whose mothers had been given 10 mg/kg.
A number of studies from the literature in rodents indicate that prenatal or early postnatal ex… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of lisdexamfetamine dimesylate have not been established in pediatric patients below the age of 6 years. ADHD Safety and effectiveness of lisdexamfetamine dimesylate have been established in pediatric patients with ADHD ages 6 to 17 years [see Dosage and Administration ( 2.3 ), Adverse Reactions ( 6.1 ), Clinical Pharmacology ( 12.3 ), and Clinical Studies ( 14.1 )] . Safety and efficacy of lisdexamfetamine dimesylate were evaluated in a double-blind, randomized, parallel-group, placebo-controlled, fixed-dose study in pediatric patients ages 4 to 5 years with ADHD, followed by a 1-year open-label extension study.
In these studies, patients experienced elevated rates of adverse reactions, including weight loss, decreased BMI, decreased appetite, insomnia, infections (upper respiratory and nasopharyngitis), irritability, and affect lability. With the same lisdexamfetamine dimesylate dose, mean steady state exposure of dextroamphetamine was approximately 44% higher in pediatric patients ages 4 to 5 years compared to the pediatric patients ages 6 to 11 years. BED Safety and effectiveness of lisdexamfetamine dimesylate have not been established in pediatric patients with BED less than 18 years of age.
Growth Suppression Growth should be monitored during treatment with stimulants, including lisdexamfetamine dimesylate, and pediatric patients who are not growing or gaining weight as expected may need to have their treatment interrupted [see Warnings and Precautions ( 5.5 ) and Adverse Reactions ( 6.1 )] . Juvenile Animal Data Studies conducted in juvenile rats and dogs at clinically relevant doses showed growth suppression that partially or fully reversed in dogs and female rats but not in male rats after a four-week drug-free recovery period.
A study was conducted in which juvenile rats received oral doses of 4, 10, or 40 mg/kg/day of lisdexamfetamine dimesylate from day 7 to day 63 of age. These doses are approximately 0.3, 0.7, and 3 times the maximum recommended human daily dose of 70 mg on a mg/m 2 basis for a child. Dose-related decreases in food consumption, bodyweight gain, and crown-rump length were seen; after a four-week drug-free recovery period, bodyweights and crown-rump lengths had significantly recovered in females but were still substantially reduced in males.
Time to vaginal opening was delayed in females at the highest dose, but there were no drug effects on fertility when the animals were mated beginning on day 85 of age. In a study in which juvenile dogs received lisdexamfetamine dimesylate for 6 months beginning at 10 weeks of age, decreased bodyweight gain was seen at all doses tested (2, 5, and 12 mg/kg/day, which are approximately 0.5, 1, and 3 times the maximum recommended human daily dose on a mg/m 2 basis for a child). This effect partially or fully reversed during a four- week drug-free recovery period.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of lisdexamfetamine dimesylate did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience and pharmacokinetic data [see Clinical Pharmacology ( 12.3 )] have not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should start at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Clinical Effects of Overdose Overdose of CNS stimulants is characterized by the following sympathomimetic effects: Cardiovascular effects including tachyarrhythmias, and hypertension or hypotension. Vasospasm, myocardial infarction, or aortic dissection may precipitate sudden cardiac death. Takotsubo cardiomyopathy may develop.
CNS effects including psychomotor agitation, confusion, and hallucinations. Serotonin syndrome, seizures, cerebral vascular accidents, and coma may occur. Life-threatening hyperthermia (temperatures greater than 104°F) and rhabdomyolysis may develop.
Overdose Management Consider the possibility of multiple drug ingestion. The pharmacokinetic profile of lisdexamfetamine dimesylate should be considered when treating patients with overdose. Lisdexamfetamine and d-amphetamine are not dialyzable.
Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Lisdexamfetamine is a prodrug of dextroamphetamine. Amphetamines are non-catecholamine sympathomimetic amines with CNS stimulant activity. The exact mode of therapeutic action in ADHD and BED is not known.
12.2Pharmacodynamics Amphetamines block the reuptake of norepinephrine and dopamine into the presynaptic neuron and increase the release of these monoamines into the extraneuronal space. The parent drug, lisdexamfetamine, does not bind to the sites responsible for the reuptake of norepinephrine and dopamine in vitro .
12.3Pharmacokinetics Pharmacokinetic studies after oral administration of lisdexamfetamine dimesylate have been conducted in healthy adult (capsule and chewable tablet formulations) and pediatric (6 to 12 years) patients with ADHD (capsule formulation). After single dose administration of lisdexamfetamine dimesylate, pharmacokinetics of dextroamphetamine was found to be linear between 30 mg and 70 mg in a pediatric study (6 to 12 years), and between 50 mg and 250 mg in an adult study. Dextroamphetamine pharmacokinetic parameters following administration of lisdexamfetamine dimesylate in adults exhibited low inter-subject (<25%) and intra-subject (<8%) variability.
There is no accumulation of lisdexamfetamine and dextroamphetamine at steady state in healthy adults. Absorption Capsule formulation Following single-dose oral administration of lisdexamfetamine dimesylate capsule (30 mg, 50 mg, or 70 mg) in patients ages 6 to 12 years with ADHD under fasted conditions, T max of lisdexamfetamine and dextroamphetamine was reached at approximately 1 hour and 3.5 hours post dose, respectively. Weight/Dose normalized AUC and C max values were the same in pediatric patients ages 6 to 12 years as the adults following single doses of 30 mg to 70 mg lisdexamfetamine dimesylate capsule.
Effect of food on capsule formulation Neither food (a high fat meal or yogurt) nor orange juice affects the observed AUC and C max of dextroamphetamine in healthy adults after single-dose oral administration of 70 mg of lisdexamfetamine dimesylate capsules. Food prolongs T max by approximately 1 hour (from 3.8 hours at fasted state to 4.7 hours after a high fat meal or to 4.2 hours with yogurt). After an 8-hour fast, the AUC for dextroamphetamine following oral administration of lisdexamfetamine dimesylate in solution and as intact capsules were equivalent.
Chewable Tablet formulation After a single dose administration of 60 mg lisdexamfetamine dimesylate chewable tablet in healthy subjects under fasted conditions, T max of lisdexamfetamine and dextroamphetamine was reached at approximately 1 hour and 4.4 hours post dose, respectively. Compared to 60 mg lisdexamfetamine dimesylate capsule, exposure (C max and AUC) to lisdexamfetamine was about 15% lower. The exposure (C max and AUC inf ) of dextroamphetamine is similar between lisdexamfetamine dimesylate chewable tablet and lisdexamfetamine dimesylate capsule.
Effect of food on tablet formulation Administration of 60 mg lisdexamfetamine dimesylate chewable tablet with food (a high-fat meal) decreases the exposure (C max and AUC inf ) of dextroamphetamine by about 5% to 7%, and prolongs mean T max by approximately 1 hour (from 3.9 hours at fasted state to 4.9 hours). Elimination Plasma concentrations of unconverted lisdexamfetamine are low and transient, generally becoming non-quantifiable by 8 hours after administration. The plasma elimination half-life of lisdexamfetamine typically averaged less than one hour in volunteers ages 6 years and older.
The plasma elimination half-life of dextroamphetamine was approximately 8.6 to 9.5 hours in pediatric patients 6 to 12 years and 10 to 11.3 hours in healthy adults. Metabolism Lisdexamfetamine is converted to dextroamphetamine and l-lysine primarily in blood due to the hydrolytic activity of red blood cells after oral administration of lisdexamfetamine dimesylate. In vitro data demonstrated that red… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Lisdexamfetamine is a prodrug of dextroamphetamine. Amphetamines are non-catecholamine sympathomimetic amines with CNS stimulant activity. The exact mode of therapeutic action in ADHD and BED is not known.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Lisdexamfetamine Dimesylate Capsules: Lisdexamfetamine dimesylate capsules 10 mg: White to off-white powder filled in pink opaque cap and pink opaque body imprinted with 'RM46' on cap and '10 mg' on body in black ink, bottles of 100 CRC, NDC 57664-046-88 Lisdexamfetamine dimesylate capsules 20 mg: White to off-white powder filled in off white opaque cap and off white opaque imprinted with 'RM47' on cap and '20 mg' on body in black ink, bottles of 100 CRC, NDC 57664-047-88 Lisdexamfetamine dimesylate capsules 30 mg: White to off-white powder filled in orange opaque cap and white opaque body imprinted with 'RM48' on cap and '30 mg' on body in black ink, bottles of 100 CRC, NDC 57664-048-88 Lisdexamfetamine dimesylate capsules 40 mg: White to off-white powder filled dark green opaque cap and white opaque body imprinted with 'RM49' on cap and '40 mg' on body in black ink, bottles of 100 CRC, NDC 57664-049-88 Lisdexamfetamine dimesylate capsules 50 mg: White to off-white powder filled in blue opaque cap and white opaque body imprinted with 'RM50' on cap and '50 mg' on body in black ink, bottles of 100 CRC, NDC 57664-050-88 Lisdexamfetamine dimesylate capsules 60 mg: White to off-white powder filled in aqua blue opaque cap and aqua blue opaque body imprinted with 'RM51' on cap and '60 mg' on body in black ink, bottles of 100 CRC, NDC 57664-051-88 Lisdexamfetamine dimesylate capsules 70 mg: White to off-white powder filled in blue opaque cap and orange opaque body imprinted with 'RM52' on cap and '70 mg' on body in black ink, bottles of 100 CRC, NDC 57664-052-88 Lisdexamfetamine Dimesylate Chewable Tablets: Lisdexamfetamine dimesylate chewable tablets 10 mg: White to off-white round shaped tablet debossed with ‘10’ on one side and ‘S83’ on the other side, bottles of 100 CRC, NDC 57664-083-88 Lisdexamfetamine dimesylate chewable tablets 20 mg: White to off-white hexagonal shaped tablet debossed with ‘20’ on one side and ‘S84’ on the other side, bottles of 100 CRC, NDC 57664-084-88 Lisdexamfetamine dimesylate chewable tablets 30 mg: White to off-white arc triangular shaped tablet debossed with ‘30’ on one side and ‘S85’ on the other side, bottles of 100 CRC, NDC 57664-085-88 Lisdexamfetamine dimesylate chewable tablets 40 mg: White to off-white capsule shaped tablet debossed with ‘40’ on one side and ‘S86’ on the other side, bottles of 100 CRC, NDC 57664-086-88 Lisdexamfetamine dimesylate chewable tablets 50 mg: White to off-white arc square shaped tablet debossed with ‘50’ on one side and ‘S87’ on the other side, bottles of 100 CRC, NDC 57664-087-88 Lisdexamfetamine dimesylate chewable tablets 60 mg: White to off-white arc diamond shaped tablet debossed with ‘60’ on one side and ‘S88’ on the other side, bottles of 100 CRC, NDC 57664-088-88
16.2Storage and Handling Dispense in a tight, light-resistant container as defined in the USP. Store at room temperature 20ºC to 25ºC (68ºF to 77ºF); excursions permitted between 15ºC to 30ºC (59ºF to 86ºF) [see USP Controlled Room Temperature] .
📋 Description ▾
11 DESCRIPTION Lisdexamfetamine dimesylate capsules and lisdexamfetamine dimesylate chewable tablets, a CNS stimulants, are for once-a-day oral administration. The chemical designation for lisdexamfetamine dimesylate is (2S)-2,6-diamino- N -[(1 S )-1-methyl-2-phenylethyl] hexanamide dimethanesulfonate. The molecular formula is C 15 H 25 N 3 O•(CH 4 O 3 S) 2 , which corresponds to a molecular weight of 455.60.
The chemical structure is: Lisdexamfetamine dimesylate is a white to off-white powder that is soluble in water (792 mg/mL). Information for Lisdexamfetamine Dimesylate Capsules: Lisdexamfetamine dimesylate capsules contain 10 mg, 20 mg, 30 mg, 40 mg, 50 mg, 60 mg, and 70 mg of lisdexamfetamine dimesylate (equivalent to 5.8 mg, 11.6 mg, 17.3 mg, 23.1 mg, 28.9 mg, 34.7 mg, and 40.5 mg of lisdexamfetamine). Inactive ingredients: black iron oxide, croscarmellose sodium, gelatin, magnesium stearate, microcrystalline cellulose, propylene glycol, shellac, and titanium dioxide.
The capsule shells also contain one or more of the following: FD&C Red #3, D&C Red #28, FD&C Red #40, FD&C Yellow #6, FD&C Blue #1, and yellow iron oxide. Information for Lisdexamfetamine Dimesylate Chewable Tablets: Lisdexamfetamine dimesylate chewable tablets contain 10 mg, 20 mg, 30 mg, 40 mg, 50 mg, and 60 mg of lisdexamfetamine dimesylate (equivalent to 5.8 mg, 11.6 mg, 17.3 mg, 23.1 mg, 28.9 mg, and 34.7 mg of lisdexamfetamine). Inactive ingredients: colloidal silicon dioxide, corn maltodextrin, croscarmellose sodium, guar gum, magnesium stearate, mannitol, microcrystalline cellulose, modified corn starch, propylene glycol, sucralose, strawberry flavor.
Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Abuse, Misuse, and Addiction Educate patients and their families about the risks of abuse, misuse, and addiction of lisdexamfetamine dimesylate, which can lead to overdose and death, and proper disposal of any unused drug [see Warnings and Precautions (5.1) , Drug Abuse and Dependence (9.2), Overdosage (10)]. Advise patients to store lisdexamfetamine dimesylate in a safe place, preferably locked, and instruct patients to not give lisdexamfetamine dimesylate to anyone else.
Risks to Patients with Serious Cardiac Disease Advise patients that there are potential risks to patients with serious cardiac disease, including sudden death, with lisdexamfetamine dimesylate use. Instruct patients to contact a healthcare provider immediately if they develop symptoms such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease [see Warnings and Precautions (5.2) ]. Increased Blood Pressure and Heart Rate Instruct patients that lisdexamfetamine dimesylate can cause elevations of their blood pressure and pulse rate and they should be monitored for such effects.
Psychiatric Adverse Reactions Advise patients that lisdexamfetamine dimesylate at recommended doses may cause psychotic or manic symptoms even in patients without prior history of psychotic symptoms or mania [see Warnings and Precautions (5.4) ]. Long-Term Suppression of Growth in Pediatric Patients Advise patients that lisdexamfetamine dimesylate may cause slowing of growth including weight loss [see Warnings and Precautions (5.5) ]. Circulation problems in fingers and toes [Peripheral vasculopathy, including Raynaud’s phenomenon] Instruct patients beginning treatment with lisdexamfetamine dimesylate about the risk of peripheral vasculopathy, including Raynaud’s phenomenon, and associated signs and symptoms: fingers or toes may feel numb, cool, painful, and/or may change from pale, to blue, to red.
Instruct patients to report to their physician any new numbness, pain, skin color change, or sensitivity to temperature in fingers or toes. Instruct patients to call their physician immediately with any signs of unexplained wounds appearing on fingers or toes while taking lisdexamfetamine dimesylate. Further clinical evaluation (e.g., rheumatology referral) may be appropriate for certain patients [see Warnings and Precautions (5.6) ].
Serotonin Syndrome Caution patients about the risk of serotonin syndrome with concomitant use of lisdexamfetamine dimesylate and other serotonergic drugs including SSRIs, SNRIs, triptans, tricyclic antidepressants, fentanyl, lithium, tramadol, tryptophan, buspirone, St. John’s Wort, and with drugs that impair metabolism of serotonin (in particular MAOIs, both those intended to treat psychiatric disorders and also others such as linezolid [see Contraindications (4) , Warnings and Precautions (5.7) and Drug Interactions (7.1) ].
Advise patients to contact their healthcare provider or report to the emergency room if they experience signs or symptoms of serotonin syndrome. Concomitant Medications Advise patients to notify their physicians if they are taking, or plan to take, any prescription or over-the-counter drugs because there is a potential for interactions [see Drug Interactions (7.1) ]. Advise patient or caregiver of steps to take with lisdexamfetamine dimesylate when a laboratory imaging procedure is ordered [see Drug Interactions (7.2)].
Motor and Verbal Tics, and Worsening of Tourette’s Syndrome Advise patients that motor and verbal tics and worsening of Tourette’s Syndrome may occur during treatment with lisdexamfetamine dimesylate. Instruct patients to notify their healthcare provider if emergence of new tics or worsening of tics or Tourette’s syndrome occurs [see Warnings and Precautions (5.8) ]. Pregnancy Registry Advise patients that there is a pregnancy exposure registry that monitors pregnancy ou… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
MEDICATION GUIDE Lisdexamfetamine Dimesylate (lis dex′′ am fet′ a meen di mes' i late) Capsules, CII Lisdexamfetamine (lis dex′′ am fet′ a meen di mes' i late) Dimesylate Chewable Tablets, CII What is the most important information I should know about lisdexamfetamine dimesylate? Lisdexamfetamine dimesylate may cause serious side effects, including: Abuse, misuse, and addiction. Lisdexamfetamine dimesylate has a high chance for abuse and misuse and may lead to substance use problems, including addiction.
Misuse and abuse of lisdexamfetamine dimesylate, other amphetamine containing medicines, and methylphenidate containing medicines, can lead to overdose and death. The risk of overdose and death is increased with higher doses of lisdexamfetamine dimesylate or when it is used in ways that are not approved, such as snorting or injection. Your healthcare provider should check you or your child’s risk for abuse, misuse, and addiction before starting treatment with lisdexamfetamine dimesylate and will monitor you or your child during treatment.
Lisdexamfetamine dimesylate may lead to physical dependence after prolonged use, even if taken as directed by your healthcare provider. Do not give lisdexamfetamine dimesylate to anyone else. See “ What is lisdexamfetamine dimesylate ? ” for more information.
Keep lisdexamfetamine dimesylate in a safe place and properly dispose of any unused medicine. See " How should I store lisdexamfetamine dimesylate ? " for more information. Tell your healthcare provider if you or your child have ever abused or been dependent on alcohol, prescription medicines, or street drugs.
Risks for people with serious heart disease. Sudden death has happened in people who have heart defects or other serious heart disease. Your healthcare provider should check you or your child carefully for heart problems before starting treatment with lisdexamfetamine dimesylate.
Tell your healthcare provider if you or your child have any heart problems, heart disease, or heart defects. Call your healthcare provider right away or go to the nearest hospital emergency room right away if you or your child have any signs of heart problems such as chest pain, shortness of breath, or fainting during treatment with lisdexamfetamine dimesylate. Increased blood pressure and heart rate. Your healthcare provider should check you or your child’s blood pressure and heart rate regularly during treatment with lisdexamfetamine dimesylate.
Mental (psychiatric) problems, including: new or worse behavior and thought problems new or worse bipolar illness new psychotic symptoms (such as hearing voices, or seeing or believing things that are not real) or new manic symptoms Tell your healthcare provider about any mental problems you or your child have or about a family history of suicide, bipolar illness, or depression. Call your healthcare provider right away if you or your child have any new or worsening mental symptoms or problems during treatment with lisdexamfetamine dimesylate, especially hearing voices, seeing or believing things that are not real, or new manic symptoms.
What is lisdexamfetamine dimesylate? Lisdexamfetamine dimesylate is a central nervous system (CNS) stimulant prescription medicine used for the treatment of: Attention Deficit Hyperactivity Disorder (ADHD) in adults and children 6 years of age and older. Lisdexamfetamine dimesylate may help increase attention and decrease impulsiveness and hyperactivity in people with ADHD.
Moderate to severe binge eating disorder (BED) in adults. Lisdexamfetamine dimesylate may help reduce the number of binge eating days in people with BED. Lisdexamfetamine dimesylate is not recommended for use in children under 6 years of age with ADHD.
Lisdexamfetamine dimesylate is not for weight loss. It is not known if lisdexamfetamine dimesylate is safe and effective for the treatment of obesity. It is not known if lisdexamfetamine dimesylate is safe and effective for use in children with BED.
Lisdexamfet… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Pharmacokinetic studies after oral administration of lisdexamfetamine dimesylate have been conducted in healthy adult (capsule and chewable tablet formulations) and pediatric (6 to 12 years) patients with ADHD (capsule formulation). After single dose administration of lisdexamfetamine dimesylate, pharmacokinetics of dextroamphetamine was found to be linear between 30 mg and 70 mg in a pediatric study (6 to 12 years), and between 50 mg and 250 mg in an adult study. Dextroamphetamine pharmacokinetic parameters following administration of lisdexamfetamine dimesylate in adults exhibited low inter-subject (<25%) and intra-subject (<8%) variability.
There is no accumulation of lisdexamfetamine and dextroamphetamine at steady state in healthy adults. Absorption Capsule formulation Following single-dose oral administration of lisdexamfetamine dimesylate capsule (30 mg, 50 mg, or 70 mg) in patients ages 6 to 12 years with ADHD under fasted conditions, T max of lisdexamfetamine and dextroamphetamine was reached at approximately 1 hour and 3.5 hours post dose, respectively. Weight/Dose normalized AUC and C max values were the same in pediatric patients ages 6 to 12 years as the adults following single doses of 30 mg to 70 mg lisdexamfetamine dimesylate capsule.
Effect of food on capsule formulation Neither food (a high fat meal or yogurt) nor orange juice affects the observed AUC and C max of dextroamphetamine in healthy adults after single-dose oral administration of 70 mg of lisdexamfetamine dimesylate capsules. Food prolongs T max by approximately 1 hour (from 3.8 hours at fasted state to 4.7 hours after a high fat meal or to 4.2 hours with yogurt). After an 8-hour fast, the AUC for dextroamphetamine following oral administration of lisdexamfetamine dimesylate in solution and as intact capsules were equivalent.
Chewable Tablet formulation After a single dose administration of 60 mg lisdexamfetamine dimesylate chewable tablet in healthy subjects under fasted conditions, T max of lisdexamfetamine and dextroamphetamine was reached at approximately 1 hour and 4.4 hours post dose, respectively. Compared to 60 mg lisdexamfetamine dimesylate capsule, exposure (C max and AUC) to lisdexamfetamine was about 15% lower. The exposure (C max and AUC inf ) of dextroamphetamine is similar between lisdexamfetamine dimesylate chewable tablet and lisdexamfetamine dimesylate capsule.
Effect of food on tablet formulation Administration of 60 mg lisdexamfetamine dimesylate chewable tablet with food (a high-fat meal) decreases the exposure (C max and AUC inf ) of dextroamphetamine by about 5% to 7%, and prolongs mean T max by approximately 1 hour (from 3.9 hours at fasted state to 4.9 hours). Elimination Plasma concentrations of unconverted lisdexamfetamine are low and transient, generally becoming non-quantifiable by 8 hours after administration. The plasma elimination half-life of lisdexamfetamine typically averaged less than one hour in volunteers ages 6 years and older.
The plasma elimination half-life of dextroamphetamine was approximately 8.6 to 9.5 hours in pediatric patients 6 to 12 years and 10 to 11.3 hours in healthy adults. Metabolism Lisdexamfetamine is converted to dextroamphetamine and l-lysine primarily in blood due to the hydrolytic activity of red blood cells after oral administration of lisdexamfetamine dimesylate. In vitro data demonstrated that red blood cells have a high capacity for metabolism of lisdexamfetamine; substantial hydrolysis occurred even at low hematocrit levels (33% of normal).
Lisdexamfetamine is not metabolized by cytochrome P450 enzymes. Excretion Following oral administration of a 70 mg dose of radiolabeled lisdexamfetamine dimesylate to 6 healthy subjects, approximately 96% of the oral dose radioactivity was recovered in the urine and only 0.3% recovered in the feces over a period of 120 hours. Of the radioactivity recovered in the urine, 42% of the dose was related to amphetamine, 25% to hippu… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Amphetamines block the reuptake of norepinephrine and dopamine into the presynaptic neuron and increase the release of these monoamines into the extraneuronal space. The parent drug, lisdexamfetamine, does not bind to the sites responsible for the reuptake of norepinephrine and dopamine in vitro .
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Attention Deficit Hyperactivity Disorder (ADHD) Pediatric Patients Ages 6 to 12 Years with ADHD A double-blind, randomized, placebo-controlled, parallel-group study (Study 1) was conducted in pediatric patients ages 6 to 12 years (N=290) who met DSM-IV criteria for ADHD (either the combined type or the hyperactive-impulsive type). Patients were randomized to receive final doses of 30 mg, 50 mg, or 70 mg of lisdexamfetamine dimesylate or placebo once daily in the morning for a total of four weeks of treatment. All patients receiving lisdexamfetamine dimesylate were initiated on 30 mg for the first week of treatment.
Patients assigned to the 50 mg and 70 mg dose groups were titrated by 20 mg per week until they achieved their assigned dose. The primary efficacy outcome was change in Total Score from baseline to endpoint in investigator ratings on the ADHD Rating Scale (ADHD-RS), an 18-item questionnaire with a score range of 0-54 points that measures the core symptoms of ADHD which includes both hyperactive/impulsive and inattentive subscales. Endpoint was defined as the last post-randomization treatment week (i.e., Weeks 1 through 4) for which a valid score was obtained.
All lisdexamfetamine dimesylate dose groups were superior to placebo in the primary efficacy outcome. Mean effects at all doses were similar; however, the highest dose (70 mg/day) was numerically superior to both lower doses (Study 1 in Table 6). The effects were maintained throughout the day based on parent ratings (Conners’ Parent Rating Scale) in the morning (approximately 10 am), afternoon (approximately 2 pm), and early evening (approximately 6 pm).
A double-blind, placebo-controlled, randomized, crossover design, analog classroom study (Study 2) was conducted in pediatric patients ages 6 to 12 years (N=52) who met DSM-IV criteria for ADHD (either the combined type or the hyperactive-impulsive type). Following a 3-week open- label dose optimization with Adderall XR ®, patients were randomly assigned to continue their optimized dose of Adderall XR (10 mg, 20 mg, or 30 mg), lisdexamfetamine dimesylate (30 mg, 50 mg, or 70 mg), or placebo once daily in the morning for 1 week each treatment.
Efficacy assessments were conducted at 1, 2, 3, 4.5, 6, 8, 10, and 12 hours post-dose using the Swanson, Kotkin, Agler, M.Flynn, and Pelham Deportment scores (SKAMP-DS), a 4-item subscale of the SKAMP with scores ranging from 0 to 24 points that measures deportment problems leading to classroom disruptions. A significant difference in patient behavior, based upon the average of investigator ratings on the SKAMP-DS across the 8 assessments were observed between patients when they received lisdexamfetamine dimesylate compared to patients when they received placebo (Study 2 in Table 6).
The drug effect reached statistical significance from hours 2 to 12 post-dose, but was not significant at 1 hour. A second double-blind, placebo-controlled, randomized, crossover design, analog classroom study (Study 3) was conducted in pediatric patients ages 6 to 12 years (N=129) who met DSM-IV criteria for ADHD (either the combined type or the hyperactive-impulsive type). Following a 4-week open-label dose optimization with lisdexamfetamine dimesylate (30 mg, 50 mg, 70 mg), patients were randomly assigned to continue their optimized dose of lisdexamfetamine dimesylate or placebo once daily in the morning for 1 week each treatment.
A significant difference in patient behavior, based upon the average of investigator ratings on the SKAMP-Deportment scores across all 7 assessments conducted at 1.5, 2.5, 5.0, 7.5, 10.0, 12.0, and 13.0 hours post-dose, were observed between patients when they received lisdexamfetamine dimesylate compared to patients when they received placebo (Study 3 in Table 6, Figure 4). Pediatric Patients Ages 13 to 17 Years with ADHD A double-blind, randomized, placebo-controlled, parallel-group study (Study 4) was conducted in pediatric patients age… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance Lisdexamfetamine dimesylate capsules and lisdexamfetamine dimesylate chewable tablets contain lisdexamfetamine, a prodrug of amphetamine, a Schedule II controlled substance.
9.2Abuse Lisdexamfetamine dimesylate has a high potential for abuse and misuse which can lead to the development of a substance use disorder, including addiction [see Warnings and Precautions (5.1) ] . Lisdexamfetamine dimesylate can be diverted for non-medical use into illicit channels or distribution. Abuse is the intentional non-therapeutic use of a drug, even once, to achieve a desired psychological or physiological effect.
Misuse is the intentional use, for therapeutic purposes, of a drug by an individual in a way other than prescribed by a health care provider or for whom it was not prescribed. Drug addiction is a cluster of behavioral, cognitive, and physiological phenomena that may include a strong desire to take the drug, difficulties in controlling drug use (e.g., continuing drug use despite harmful consequences, giving a higher priority to drug use than other activities and obligations), and possible tolerance or physical dependence.
Misuse and abuse of lisdexamfetamine, a prodrug of amphetamine, may cause increased heart rate, respiratory rate, or blood pressure; sweating; dilated pupils; hyperactivity; restlessness; insomnia; decreased appetite; loss of coordination; tremors; flushed skin; vomiting; and/or abdominal pain. Anxiety, psychosis, hostility, aggression, and suicidal or homicidal ideation have also been observed with CNS stimulants abuse and/or misuse. Misuse and abuse of CNS stimulants, including lisdexamfetamine dimesylate, can result in overdose and death [see Overdosage (10) ] , and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection.
Studies of Lisdexamfetamine Dimesylate in Drug Abusers A randomized, double-blind, placebo-control, cross-over, abuse liability study in 38 patients with a history of drug abuse was conducted with single-doses of 50, 100, or 150 mg of lisdexamfetamine dimesylate, 40 mg of immediate-release d-amphetamine sulphate (a controlled II substance), and 200 mg of diethylpropion hydrochloride (a controlled IV substance). Lisdexamfetamine dimesylate 100 mg produced significantly less “Drug Liking Effects” as measured by the Drug Rating Questionnaire-Subject score, compared to d-amphetamine 40 mg; and 150 mg of lisdexamfetamine dimesylate demonstrated similar “Drug-Liking Effects” compared to 40 mg of d-amphetamine and 200 mg of diethylpropion.
Intravenous administration of 50 mg lisdexamfetamine dimesylate to individuals with a history of drug abuse produced positive subjective responses on scales measuring "Drug Liking", "Euphoria", "Amphetamine Effects", and "Benzedrine Effects" that were greater than placebo but less than those produced by an equivalent dose (20 mg) of intravenous d-amphetamine.
9.3Dependence Physical Dependence Lisdexamfetamine dimesylate may produce physical dependence. Physical dependence is a state that develops as a result of physiological adaptation in response to repeated drug use, manifested by withdrawal signs and symptoms after abrupt discontinuation or a significant dose reduction of a drug. Withdrawal signs and symptoms after abrupt discontinuation or dose reduction following prolonged use of CNS stimulants including lisdexamfetamine dimesylate include dysphoric mood; depression; fatigue; vivid, unpleasant dreams; insomnia or hypersomnia; increased appetite; and psychomotor retardation or agitation.
Tolerance Lisdexamfetamine dimesylate may produce tolerance. Tolerance is a physiological state characterized by a reduced response to a drug after repeated administration (i.e., a higher dose of a drug is required to produce the same effect that was once obtained at a lower dose).
🔒 Controlled Substance ▾
9.1Controlled Substance Lisdexamfetamine dimesylate capsules and lisdexamfetamine dimesylate chewable tablets contain lisdexamfetamine, a prodrug of amphetamine, a Schedule II controlled substance.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, and Impairment of Fertility Carcinogenesis Carcinogenicity studies of lisdexamfetamine dimesylate have not been performed. No evidence of carcinogenicity was found in studies in which d-, l-amphetamine (enantiomer ratio of 1:1) was administered to mice and rats in the diet for 2 years at doses of up to 30 mg/kg/day in male mice, 19 mg/kg/day in female mice, and 5 mg/kg/day in male and female rats. Mutagenesis Lisdexamfetamine dimesylate was not clastogenic in the mouse bone marrow micronucleus test in vivo and was negative when tested in the E. coli and S. typhimurium components of the Ames test and in the L5178Y/TK +/- mouse lymphoma assay in vitro .
Impairment of Fertility Amphetamine (d- to l-enantiomer ratio of 3:1) did not adversely affect fertility or early embryonic development in the rat at doses of up to 20 mg/kg/day.
13.2Animal Toxicology and/or Pharmacology Acute administration of high doses of amphetamine (d- or d, l-) has been shown to produce long- lasting neurotoxic effects, including irreversible nerve fiber damage, in rodents. The significance of these findings to humans is unknown.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, and Impairment of Fertility Carcinogenesis Carcinogenicity studies of lisdexamfetamine dimesylate have not been performed. No evidence of carcinogenicity was found in studies in which d-, l-amphetamine (enantiomer ratio of 1:1) was administered to mice and rats in the diet for 2 years at doses of up to 30 mg/kg/day in male mice, 19 mg/kg/day in female mice, and 5 mg/kg/day in male and female rats. Mutagenesis Lisdexamfetamine dimesylate was not clastogenic in the mouse bone marrow micronucleus test in vivo and was negative when tested in the E. coli and S. typhimurium components of the Ames test and in the L5178Y/TK +/- mouse lymphoma assay in vitro .
Impairment of Fertility Amphetamine (d- to l-enantiomer ratio of 3:1) did not adversely affect fertility or early embryonic development in the rat at doses of up to 20 mg/kg/day.
📄 Recent Major Changes ▾
Indications and Usage (1) 09/2025 Warnings and Precautions (5.5) 09/2025
📄 Package Label / Principal Display Panel ▾
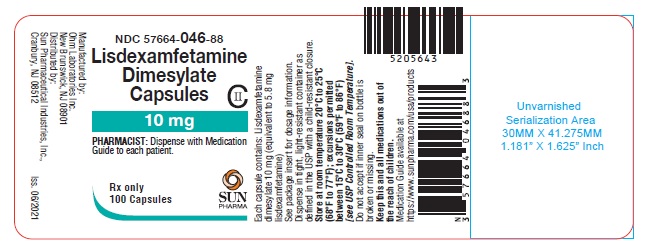
PRINCIPAL DISPLAY PANEL-10mg Capsules PDP Caps-10mg
PRINCIPAL DISPLAY PANEL-20mg Capsules PDP Caps - 20mg
PRINCIPAL DISPLAY PANEL-30mg Capsules PDP Caps-30mg
PRINCIPAL DISPLAY PANEL-40mg Capsules PDP Caps - 40mg
PRINCIPAL DISPLAY PANEL-50mg Capsules PDP Caps - 50mg
PRINCIPAL DISPLAY PANEL-60mg Capsules PDP Caps - 60mg
PRINCIPAL DISPLAY PANEL-70mg Capsules PDP Caps-70mg
PRINCIPAL DISPLAY PANEL-10mg Chewable Tablets PDP-Chew-10mg
PRINCIPAL DISPLAY PANEL-20mg Chewable Tablets PDP-Chew-20mg
PRINCIPAL DISPLAY PANEL-30mg Chewable Tablets PDP-Chew-30mg
PRINCIPAL DISPLAY PANEL-40mg Chewable Tablets PDP-Chew-40mg
PRINCIPAL DISPLAY PANEL-50mg Chewable Tablets PDP-Chew-50mg
PRINCIPAL DISPLAY PANEL-60mg Chewable Tablets PDP-Chew-60mg