
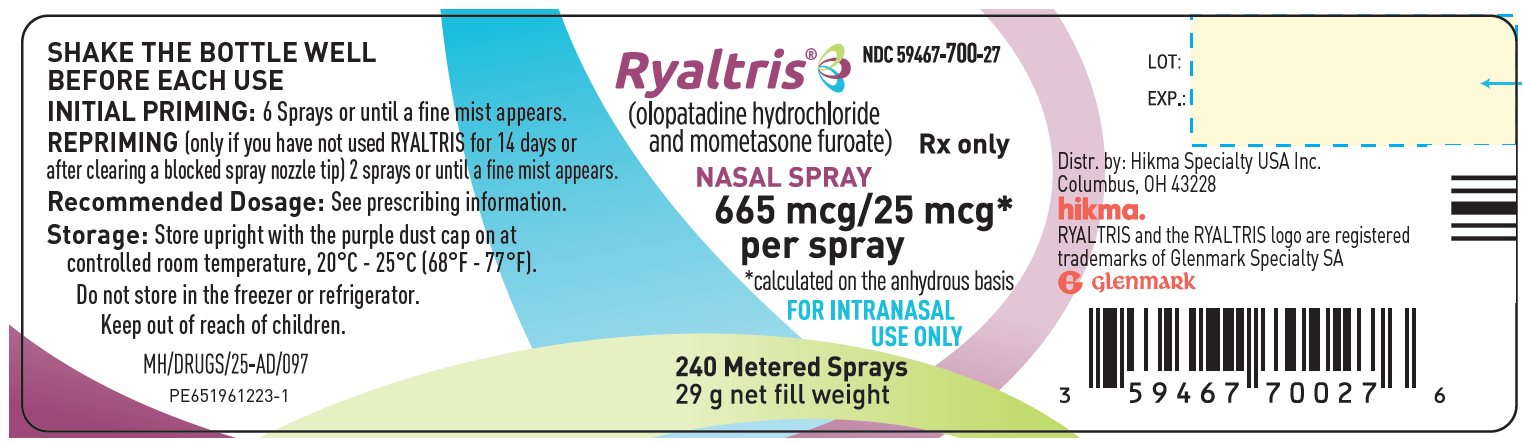
Ryaltris olopatadine hydrochloride and mometasone furoate 665 ug; 25 ug Spray, Metered
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Corticosteroid class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Ryaltris is a bit more than a standard allergy spray. It combines two active ingredients: olopatadine, an antihistamine that blocks the histamine trigger behind sneezing and itchin...
- What is Ryaltris actually for — is it just a regular allergy spray?
- It can. Drowsiness was reported by some patients in clinical studies, so it's worth being cautious — especially the first few times you use it. Avoid driving or running heavy machi...
- Shake the bottle well before every single use — that's important. Before you use it for the very first time, prime the pump by spraying 6 times into the air until a fine mist comes...
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII F5UM2KM3W7
Benzalkonium chloride is a chemical compound that works as a preservative and antimicrobial agent in medications. It prevents bacterial and fungal growth in liquid formulations to keep the product safe during storage and use.
-
UNII K679OBS311
Carboxymethylcellulose sodium is a plant-derived thickening agent made from cellulose. In medicines, it acts as a binder to hold ingredients together, a disintegrant to help the tablet break apart, or a thickener in liquids.
-
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 70WT22SF4B
A mineral salt that acts as a buffer to maintain the pH balance of the medication. It helps stabilize the drug's potency and prevents unwanted chemical changes during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $7.672 | — |
| Medicaid paysCMS SDUD · 12 mo | $8.39 | — |
| Medicare drug plans payPart D · Q2 2026 | $8.11 | — |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ryaltris 665 ug/1; 25 ugthis 59467-0700-27 | HIKMA | 1 bottle | $7.671 | — | Availability likely | — |
| Ryaltris 665 ug/1; 25 ug 68462-0659-27 | Glenmark | 1 bottle | $7.671 | — | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 10765686 ↗ | Method of use | U-3295 | Sep 4, 2034 |
| US 10758550 ↗ | Method of use | U-3296 | Sep 4, 2034 |
| US 10646500 ↗ | Method of use | U-3297 | Sep 4, 2034 |
| US 10548907 ↗ | Method of use | U-3297 | Sep 4, 2034 |
| US 11400101 ↗ | Method of use | U-3297 | Sep 4, 2034 |
| US 12064442 ↗ | Method of use | U-3297 | Sep 4, 2034 |
| US 10016443 ↗ | Method of use | U-3297 | Sep 4, 2034 |
| US 10517880 ↗ | Method of use | U-3297 | Sep 4, 2034 |
| US 9750754 ↗ | Method of use | U-3297 | Sep 4, 2034 |
| US 9078923 ↗ | Method of use | U-3297 | Sep 4, 2034 |
| US 12653833 ↗ | Method of use | U-4564 | Nov 21, 2044 |
| US 11679210 ↗ | Drug product | — | Sep 3, 2038 |
| US 10561672 ↗ | Drug product | — | Sep 4, 2034 |
| US 9370483 ↗ | Drug product | — | Sep 4, 2034 |
| US 10376526 ↗ | Drug product | — | Sep 4, 2034 |
| US 12303635 ↗ | Drug substance | — | Apr 8, 2039 |
| US 9937189 ↗ | Drug product | — | Sep 4, 2034 |
| Code | What it grants | Expires |
|---|---|---|
| NPP | New Patient Population | Jul 7, 2029 |
Is there a generic version of RYALTRIS 665-25 MCG SPRAY?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 59467-0700-27 You're viewing this | 12 CARTON in 1 BOX (59467-700-27) / 1 BOTTLE, SPRAY in 1 CARTON / 240 SPRAY, METERED in 1 BOTTLE, SPRAY | $7.67 / g | — | 2022-08-15 | Active |
| 59467-0700-84 | 12 CARTON in 1 BOX (59467-700-84) / 1 BOTTLE, SPRAY in 1 CARTON / 56 SPRAY, METERED in 1 BOTTLE, SPRAY | — | — | 2022-08-15 | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 59467-0700-27?
What NDC number is used to bill for this package of Ryaltris olopatadine hydrochloride and mometasone furoate 665 ug; 25 ug Spray, Metered?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE RYALTRIS is indicated for the treatment of symptoms of seasonal allergic rhinitis in adult and pediatric patients 12 years of age and older. RYALTRIS is a combination of olopatadine, a histamine-1 (H1)-receptor inhibitor, and mometasone furoate, a corticosteroid, indicated for the treatment of symptoms of seasonal allergic rhinitis in adult and pediatric patients 12 years of age and older. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION For nasal use only. The recommended dosage of RYALTRIS is 2 sprays (2 sprays deliver a total of 1,330 mcg of olopatadine hydrochloride and 50 mcg of mometasone furoate) in each nostril twice daily. • Shake the bottle well before each use. • Prime RYALTRIS before initial use by releasing 6 sprays or until a fine mist appears. When RYALTRIS has not been used for 14 or more days, re-prime by releasing 2 sprays or until a fine mist appears. • Avoid spraying RYALTRIS into the eyes or mouth. • For nasal use only ( 2 ) • Recommended dosage: 2 sprays in each nostril twice daily ( 2 ) • Prime before initial use by releasing 6 sprays or until a fine mist appears and when it has not been used for 14 or more days by releasing 2 sprays or until a fine mist appears.
( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Nasal spray: 665 mcg of olopatadine hydrochloride and 25 mcg of mometasone furoate in each spray Nasal spray: 665 mcg of olopatadine hydrochloride and 25 mcg of mometasone furoate in each spray. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS RYALTRIS is contraindicated in patients with known hypersensitivity to any ingredients of RYALTRIS. Hypersensitivity reactions, including wheezing, has occurred after nasal administration of mometasone furoate [see Warnings and Precautions ( 5.4 )]. Patients with known hypersensitivity to any ingredients of RYALTRIS, including mometasone furoate. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Epistaxis, nasal ulcerations, nasal septal perforations, impaired wound healing, and Candida albicans infection: Monitor patients periodically for signs of adverse reactions on the nasal mucosa. ( 5.1 ) • Somnolence: Avoid engaging in hazardous occupations requiring complete mental alertness and motor coordination such as driving or operating machinery when taking RYALTRIS. ( 5.2 ) • Avoid concurrent use of alcohol or other central nervous system (CNS) depressants with RYALTRIS because additional reductions in alertness and additional impairment of CNS performance may occur.
( 5.2 ) • Glaucoma and cataracts: Monitor patients with a change in vision or with a history of increased intraocular pressure, glaucoma, and/or cataracts. ( 5.3 ) • Hypersensitivity Reactions: Hypersensitivity reactions can occur with RYALTRIS. Hypersensitivity reactions including wheezing, have occurred after the nasal administration of mometasone furoate.
Discontinue RYALTRIS if such reactions occur. ( 5.4 ) • Immunosuppression and Risk of Infections: Potential worsening of existing tuberculosis; fungal, bacterial, viral, or parasitic infections; or ocular herpes simplex. More serious or even fatal course of chickenpox or measles in susceptible patients: Use caution in patients with the above because of the potential for worsening of these infections.
( 5.5 ) • Hypercorticism and adrenal suppression with misuse or use of higher-than-recommended dosages or at the regular dosage in susceptible patients at risk for such effects ( 5.6 ) • Potential reduction in growth velocity in children: Routinely monitor the growth in pediatric patients receiving RYALTRIS. ( 5.7 , 8.4 )
5.1Local Nasal Adverse Reactions Epistaxis Epistaxis was observed in 1% of patients treated with RYALTRIS and 0.6% of patients who received placebo in 2-week studies in patients with seasonal allergic rhinitis [see Adverse Reactions ( 6.1 )]. Nasal Ulceration and Nasal Septal Perforation Instances of nasal ulceration and nasal septal perforation have occurred in patients following the nasal application of antihistamines such as RYALTRIS. Monitor patients periodically for signs of adverse effects on the nasal mucosa.
Impaired Nasal Wound Healing Because of the inhibitory effect of corticosteroids on wound healing, patients who have experienced recent nasal septal ulcers, nasal surgery, or nasal trauma should avoid use of RYALTRIS until healing has occurred. Local Candida Infection Localized infections of the nose and pharynx with Candida albicans have occurred from nasal administration of mometasone furoate. When such an infection occurs, discontinue RYALTRIS and institute appropriate local or systemic therapy.
Patients using RYALTRIS over several months or longer should be examined periodically for evidence of Candida infection.
5.2Somnolence and Impaired Mental Alertness Patients should be cautioned against engaging in hazardous occupations requiring complete mental alertness and motor coordination, such as operating machinery or driving a motor vehicle, after administration of RYALTRIS. Concurrent use of RYALTRIS with alcohol or other central nervous system (CNS) depressants should be avoided because additional reductions in alertness and additional impairment of CNS performance may occur. Somnolence was reported in 0.3% of patients treated with RYALTRIS and none of the patients who received placebo in 2-week studies in patients with seasonal allergic rhinitis [see Adverse Reactions ( 6.1 )] .
5.3Glaucoma and Cataracts Nasal and inhaled corticosteroids including RYALTRIS can result in the development of glaucoma and/or cataracts. Therefore, close monitoring is warranted in patients with a change in vision or with a history of increased intraocular pressure, glaucoma, and/or cataracts.
5.4Hypersensitivity Reactions Hypersensitivity reactions can occur with RYALTRIS. Hypersensitivity reactions including wheezing, have occurred after the nasal administratio…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in labeling: • Local Nasal Adverse Reactions [see Warnings and Precautions ( 5.1 )] • Somnolence and Impaired Mental Alertness [see Warnings and Precautions ( 5.2 )] • Glaucoma and Cataracts [see Warnings and Precautions ( 5.3 )] • Hypersensitivity Reactions [see Warnings and Precautions ( 5.4 )] • Immunosuppression and Risk of Infections [see Warnings and Precautions ( 5.5 )] • Hypercorticism and Adrenal Suppression [see Warnings and Precautions ( 5.6 ), Use in Specific Populations ( 8.4 )] • Effect on Growth [see Warnings and Precautions ( 5.7 )] The most common adverse reactions (≥1% incidence) are dysgeusia, epistaxis, and nasal discomfort.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Hikma Specialty USA Inc. at 1-800-962-8364 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared with rates in the clinical studies of another drug and may not reflect the rates observed in practice. Adults and Pediatric Patients 12 Years of Age and Older The pooled RYALTRIS safety population reflects exposure to RYALTRIS at 2 sprays (2 sprays deliver a total of 1,330 mcg of olopatadine hydrochloride and 50 mcg of mometasone furoate) in each nostril twice daily in a total of 1189 patients from Studies 1 and 2 [see Clinical Studies (14)] and from three additional placebo and/or active-controlled studies in patients with allergic rhinitis.
One placebo controlled study was a 52-week safety study. In this study, 393 patients were exposed to RYALTRIS for one year, and no new safety signals were observed. The RYALTRIS safety population described below reflects exposure to RYALTRIS at 2 sprays (2 sprays deliver a total of 1,330 mcg of olopatadine hydrochloride and 50 mcg of mometasone furoate) in each nostril twice daily for two weeks duration in a total of 789 patients, including 596 patients from Studies 1 and 2 [see Clinical Studies (14)], and 36 and 157 from two additional placebo and active-controlled studies in patients with seasonal allergic rhinitis.
The demographics of the RYALTRIS-treated patients were 12 to 81 years of age (mean age of 40 years; 67% female; 81% White, 15% Black/African American and 3% Other). Table 1 lists adverse reactions from the safety population reported with frequencies ≥1% and more frequently than placebo in patients treated with RYALTRIS. Somnolence was reported in <1% (2 of 789) of patients treated with RYALTRIS and no patients treated with placebo.
Table 1: Adverse Reactions with ≥1% Incidence that Were Reported More Frequently with RYALTRIS than Placebo in the Safety Population in Adult and Pediatric Patients 12 Years of Age and Older with Seasonal Allergic Rhinitis RYALTRIS N=789 n (%) Olopatadine HCl Nasal Spray * N=751 n (%) Mometasone Furoate Nasal Spray * N=746 n (%) Placebo N=776 n (%) Dysgeusia 24 (3.0) 16 (2.1) 0 (0) 2 (0.3) Epistaxis 8 (1.0) 11 (1.5) 6 (0.8) 5 (0.6) Nasal discomfort 8 (1.0) 4 (0.5) 4 (0.5) 6 (0.8) * Non-US approved drugs
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS No formal drug-drug interaction studies have been performed with RYALTRIS. The drug interactions of the combination are expected to reflect those of the individual components [see Clinical Pharmacology ( 12.3 )] .
7.1Central Nervous System Depressants Concurrent use of RYALTRIS with alcohol or other central nervous system depressants should be avoided because somnolence and impairment of central nervous system performance may occur [see Warnings and Precautions ( 5.2 )] .
7.2Inhibitors of Cytochrome P450 3A4 Studies have shown that mometasone furoate, a component of RYALTRIS, is primarily and extensively metabolized to multiple metabolites. In vitro studies have confirmed the primary role of cytochrome P450 (CYP) 3A4 in the metabolism of this compound. Concomitant administration of CYP3A4 inhibitors may inhibit the metabolism of, and increase the mometasone furoate plasma concentration and potentially increase the risk for adverse reactions.
Caution should be exercised when considering the coadministration of RYALTRIS with strong CYP3A4 inhibitors [see Clinical Pharmacology ( 12.3 )] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no available data on RYALTRIS or mometasone furoate use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage or other adverse maternal or fetal outcomes. Postmarketing experience with antihistamines, with similar mechanism of action to olopatadine, have not identified a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. However, there are no published human data specific to olopatadine.
Animal reproduction studies have not been conducted with RYALTRIS. However, animal reproduction studies are available for olopatadine hydrochloride and mometasone furoate. Oral administration of olopatadine hydrochloride to pregnant rats and rabbits caused a decrease in the number of live fetuses at maternal doses approximately 120 and 1600 times the maximum recommended human daily intranasal dose (MRHDID) on a mg/m 2 basis, respectively (see Data) .
In animal reproduction studies with pregnant mice, rats, or rabbits, mometasone furoate caused increased fetal malformations and decreased fetal survival and growth following administration of doses that produced exposures approximately 1 to 16 times the MRHDID on a mcg/m 2 or AUC basis (see Data) . However, experience with oral corticosteroids suggests that rodents are more prone to teratogenic effects from corticosteroid exposure than humans. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data No reproductive toxicology studies were conducted with RYALTRIS; however, studies are available for olopatadine hydrochloride and mometasone furoate, as described below.
Olopatadine hydrochloride In an oral embryo-fetal development study, pregnant rats were dosed throughout the period of organogenesis at doses up to 600 mg/kg/day. Maternal toxicity, producing death and reduced maternal body weight gain was observed at 600 mg/kg/day (approximately 1200 times the MRHDID on a mg/m 2 basis). Olopatadine produced cleft palate at 60 mg/kg/day (approximately 120 times the MRHDID on a mg/m 2 basis) and decreased embryo-fetal viability and reduced fetal weight in rats at 600 mg/kg/day (approximately 1200 times the MRHDID on a mg/m 2 basis).
In an oral embryo-fetal development study, pregnant rabbits were dosed throughout the period of organogenesis at doses up to 400 mg/kg/day. A decrease in the number of live fetuses was observed at 400 mg/kg/day (approximately 1600 times the MRHDID on a mg/m 2 basis). In peri-/post-natal toxicity studies, pregnant rats received oral doses of olopatadine up to 600 mg/kg/day during late gestation and throughout the lactation period.
Olopatadine produced decreased neonatal survival at 60 mg/kg/day (approximately 120 times the MRHDID on a mg/m 2 basis) and reduced body weight gain in pups at 4 mg/kg/day (approximately 7 times the MRHDID on a mg/m 2 basis). These effects appeared attributable to exposure of pups via the milk as demonstrated in a cross-fostered study in which pups of untreated dams cross-fostered to dams treated with 60 mg/kg/day olopatadine orally during the lactation period exhibited decreased body weight gain. Mometasone furoate In an embryo-fetal development study with pregnant mice dosed throughout the period of organogenesis, mometasone furoate produced cleft palate at a dose approximately equivalent to the MRHDID (on a mcg/m 2 basis with maternal subcutaneous doses of 60 mcg/kg and above) and decreased fetal survival at approximately 4 times the MRHDID (on a mcg/m 2 basis with a maternal subcutaneous dose of 180 mcg/kg).
No toxicity was observed with a dose that produced an…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no available data on RYALTRIS or mometasone furoate use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage or other adverse maternal or fetal outcomes. Postmarketing experience with antihistamines, with similar mechanism of action to olopatadine, have not identified a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. However, there are no published human data specific to olopatadine.
Animal reproduction studies have not been conducted with RYALTRIS. However, animal reproduction studies are available for olopatadine hydrochloride and mometasone furoate. Oral administration of olopatadine hydrochloride to pregnant rats and rabbits caused a decrease in the number of live fetuses at maternal doses approximately 120 and 1600 times the maximum recommended human daily intranasal dose (MRHDID) on a mg/m 2 basis, respectively (see Data) .
In animal reproduction studies with pregnant mice, rats, or rabbits, mometasone furoate caused increased fetal malformations and decreased fetal survival and growth following administration of doses that produced exposures approximately 1 to 16 times the MRHDID on a mcg/m 2 or AUC basis (see Data) . However, experience with oral corticosteroids suggests that rodents are more prone to teratogenic effects from corticosteroid exposure than humans. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data No reproductive toxicology studies were conducted with RYALTRIS; however, studies are available for olopatadine hydrochloride and mometasone furoate, as described below.
Olopatadine hydrochloride In an oral embryo-fetal development study, pregnant rats were dosed throughout the period of organogenesis at doses up to 600 mg/kg/day. Maternal toxicity, producing death and reduced maternal body weight gain was observed at 600 mg/kg/day (approximately 1200 times the MRHDID on a mg/m 2 basis). Olopatadine produced cleft palate at 60 mg/kg/day (approximately 120 times the MRHDID on a mg/m 2 basis) and decreased embryo-fetal viability and reduced fetal weight in rats at 600 mg/kg/day (approximately 1200 times the MRHDID on a mg/m 2 basis).
In an oral embryo-fetal development study, pregnant rabbits were dosed throughout the period of organogenesis at doses up to 400 mg/kg/day. A decrease in the number of live fetuses was observed at 400 mg/kg/day (approximately 1600 times the MRHDID on a mg/m 2 basis). In peri-/post-natal toxicity studies, pregnant rats received oral doses of olopatadine up to 600 mg/kg/day during late gestation and throughout the lactation period.
Olopatadine produced decreased neonatal survival at 60 mg/kg/day (approximately 120 times the MRHDID on a mg/m 2 basis) and reduced body weight gain in pups at 4 mg/kg/day (approximately 7 times the MRHDID on a mg/m 2 basis). These effects appeared attributable to exposure of pups via the milk as demonstrated in a cross-fostered study in which pups of untreated dams cross-fostered to dams treated with 60 mg/kg/day olopatadine orally during the lactation period exhibited decreased body weight gain. Mometasone furoate In an embryo-fetal development study with pregnant mice dosed throughout the period of organogenesis, mometasone furoate produced cleft palate at a dose approximately equivalent to the MRHDID (on a mcg/m 2 basis with maternal subcutaneous doses of 60 mcg/kg and above) and decreased fetal survival at approximately 4 times the MRHDID (on a mcg/m 2 basis with a maternal subcutaneous dose of 180 mcg/kg).
No toxicity was observed with a dose that produced an exposure approximately one-hal…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of RYALTRIS for the treatment of symptoms associated with seasonal allergic rhinitis have been established in pediatric patients 12 years and older. Use of RYALTRIS for this indication is supported by evidence from adequate and well-controlled studies in adult and pediatric patients 12 years and older [see Clinical Studies (14)] . The safety and effectiveness of RYALTRIS in pediatric patients below the age of 12 years have not been established.
Effect on Growth Controlled clinical studies have shown that nasal corticosteroids may cause a reduction in growth velocity in pediatric patients. This effect has been observed in the absence of laboratory evidence of HPA axis suppression, suggesting that growth velocity is a more sensitive indicator of systemic corticosteroid exposure in pediatric patients than some commonly used tests of HPA axis function. The long-term effects of this reduction in growth velocity associated with nasal corticosteroids, including the impact on final adult height, are unknown.
The potential for “catch up” growth following discontinuation of treatment with nasal corticosteroids has not been adequately studied. The growth of pediatric patients receiving nasal corticosteroids, including RYALTRIS, should be monitored routinely (e.g., via stadiometry). The potential growth effects of prolonged treatment should be weighed against clinical benefits obtained and the risk/benefits of non-corticosteroid treatment alternatives.
The potential of mometasone furoate nasal spray 50 mcg to cause growth suppression in susceptible patients or when given at higher doses cannot be ruled out.
🧓 Geriatric Use ▾
8.5Geriatric Use There were 20 patients 65 years of age and older treated with RYALTRIS in the clinical studies for seasonal allergic rhinitis [see Clinical Studies ( 14 )] . Of the RYALTRIS-treated patients in these studies, 16 (2.7%) were between 65 to 75 years of age, while 4 (0.7%) were 75 years of age and older. Clinical studies of RYALTRIS did not include sufficient numbers of patients 65 years of age and older to determine whether they respond differently from younger adult patients.
🆘 Overdosage ▾
10 OVERDOSAGE RYALTRIS contains both olopatadine hydrochloride and mometasone furoate; therefore, the risks associated with overdosage for the individual components described below apply to RYALTRIS. Olopatadine Hydrochloride: Symptoms of antihistamine overdose may include drowsiness in adults and children. Agitation and restlessness, followed by drowsiness in children.
Should overdose occur, symptomatic or supportive treatment is recommended. Mometasone Furoate: Chronic overdosage with any corticosteroid may result in signs or symptoms of hypercorticism [see Warnings and Precautions ( 5.6 )] .
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action RYALTRIS contains both olopatadine hydrochloride and mometasone furoate. The mechanisms of action described below for the individual components apply to RYALTRIS. Olopatadine Hydrochloride Olopatadine is a histamine-1 (H1) receptor inhibitor.
The antihistaminic activity of olopatadine has been documented in isolated tissues, animal models, and humans. Mometasone Furoate Mometasone furoate is a corticosteroid demonstrating potent anti-inflammatory activity. The precise mechanism of corticosteroid action on allergic rhinitis is not known.
Corticosteroids have been shown to have a wide range of inhibitory effects on multiple cell types (e.g., mast cells, eosinophils, neutrophils, macrophages, and lymphocytes) and mediators (e.g., histamine, eicosanoids, leukotrienes, and cytokines) involved in inflammation.
12.2Pharmacodynamics Cardiac Electrophysiology A study specifically designed to evaluate the effect of RYALTRIS on the QT interval has not been conducted. In a 12-month study, 429 patients treated with olopatadine hydrochloride two sprays per nostril (665 mcg per spray) twice daily, no evidence of any effect of olopatadine hydrochloride on QT prolongation has been observed. HPA Axis Effect A study specifically designed to evaluate the effect of RYALTRIS on the HPA axis has not been conducted.
In one study, daily nasal doses of 200 and 400 mcg of mometasone furoate and oral dose of 10 mg prednisone were compared to placebo in 64 patients (22 to 44 years of age) with allergic rhinitis. Adrenal function before and after 36 consecutive days of treatment was assessed by measuring plasma cortisol levels following a 6-hour cosyntropin infusion and by measuring 24-hour urinary free cortisol levels. Mometasone furoate at both the 200- and 400-mcg dose, was not associated with a statistically significant decrease in mean plasma cortisol levels post-cosyntropin infusion or a statistically significant decrease in the 24-hour urinary free cortisol levels compared to placebo.
A statistically significant decrease in the mean plasma cortisol levels post-cosyntropin infusion and 24-hour urinary free cortisol levels was detected in the prednisone treatment group compared to placebo.
12.3Pharmacokinetics Absorption After repeated nasal administration of 2 sprays per nostril of RYALTRIS (2660 mcg of olopatadine hydrochloride and 100 mcg of mometasone furoate) twice daily in patients with seasonal allergic rhinitis, the mean (± standard deviation) peak plasma exposure (C max ) was 19.80 ± 7.01 ng/mL for olopatadine and 9.92 ± 3.74 pg/mL for mometasone furoate, and the mean exposure over the dosing regimen (AUC tau ) was 88.77 ± 23.87 ng/mL*hr for olopatadine and 58.40 ± 27.00 pg/mL*hr for mometasone furoate.
The median time to peak exposure from a single dose was 1 hour for both olopatadine and mometasone furoate. Distribution The protein binding of olopatadine was moderate at approximately 55% in human serum and independent of drug concentration over the range of 0.1 to 1000 ng/mL. Olopatadine binds predominately to human serum albumin.
The in vitro protein binding for mometasone furoate was reported to be 98% to 99% in concentration range of 5 to 500 ng/mL. Elimination Following single‑dose nasal administration of a combination of olopatadine and mometasone furoate, the mean elimination half-lives of olopatadine and mometasone furoate were 9 and 18 hours, respectively. Olopatadine is mainly eliminated through urinary excretion.
Approximately 70% of a [ 14 C] olopatadine hydrochloride oral dose was recovered in urine with 17% in the feces. Of the drug‑related material recovered within the first 24 hours in the urine, 86% was unchanged olopatadine, with the balance comprised of olopatadine N-oxide and N-desmethyl olopatadine. Any absorbed drug is excreted as metabolites mostly via the bile, and to a limited extent, into the urine.
Metabolism Olopatadine is not extensively metabolized. Based on pl…
🧬 Mechanism of Action ▾
12.1Mechanism of Action RYALTRIS contains both olopatadine hydrochloride and mometasone furoate. The mechanisms of action described below for the individual components apply to RYALTRIS. Olopatadine Hydrochloride Olopatadine is a histamine-1 (H1) receptor inhibitor.
The antihistaminic activity of olopatadine has been documented in isolated tissues, animal models, and humans. Mometasone Furoate Mometasone furoate is a corticosteroid demonstrating potent anti-inflammatory activity. The precise mechanism of corticosteroid action on allergic rhinitis is not known.
Corticosteroids have been shown to have a wide range of inhibitory effects on multiple cell types (e.g., mast cells, eosinophils, neutrophils, macrophages, and lymphocytes) and mediators (e.g., histamine, eicosanoids, leukotrienes, and cytokines) involved in inflammation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING RYALTRIS (NDC 59467-700-27) is supplied in a white plastic bottle fitted with a metered‑dose spray nozzle unit. Each bottle contains a net fill weight of 31 g and will deliver 240 metered sprays in addition to six (6) initial priming sprays [see Description ( 11 )] . Each spray delivers a volume of 0.1 mL suspension as a fine mist, containing 665 mcg of olopatadine hydrochloride equivalent to 600 mcg of olopatadine (base) and 25 mcg of mometasone furoate monohydrate (on the anhydrous basis).
The bottle should be discarded after 240 sprays have been used. Storage Store RYALTRIS upright with the purple dust cap on at room temperature (see USP Controlled Room Temperature, between 20°C and 25°C, or between 68°F and 77°F, with excursions permitted between 15°C to 30°C or between 59°F to 86°F). Do not store in a freezer or refrigerator.
📋 Description ▾
11 DESCRIPTION RYALTRIS is a metered-dose manual nasal spray unit containing an aqueous suspension of a fixed‑dose combination of a histamine-1 (H1) receptor inhibitor (olopatadine hydrochloride) and a corticosteroid (mometasone furoate monohydrate). Olopatadine hydrochloride is a white, sparingly water‑soluble crystalline powder. The chemical name for olopatadine hydrochloride is 2‑[(11Z)-11-[3-(dimethylamino)propylidene]-6H-benzo[c][1]benzoxepin-2-yl]acetic acid hydrochloride.
It has a molecular weight of 373.88, and its molecular formula is C 21 H 23 NO 3 •HCl with the following chemical structure: Mometasone furoate monohydrate is an anti-inflammatory corticosteroid having the chemical name [(8S,9R,10S,11S,13S,14S,16R,17R)-9-chloro-17-(2-chloroacetyl)-11-hydroxy-10,13,16-trimethyl-3-oxo-6,7,8,11,12,14,15,16-octahydrocyclopenta[a]phenanthren-17-yl] furan-2-carboxylate;hydrate and the following chemical structure: Mometasone furoate monohydrate is a white powder, with an empirical formula of C 27 H 30 C l2 O 6 •H 2 O and a molecular weight of 539.45.
It is practically insoluble in water; slightly soluble in methanol, ethanol, and isopropanol; soluble in acetone and chloroform; and freely soluble in tetrahydrofuran. Its partition coefficient between octanol and water is >5000. RYALTRIS is a nasal spray containing an isotonic aqueous suspension of olopatadine hydrochloride (equivalent to 0.6% w/v olopatadine base) and mometasone furoate monohydrate (equivalent to 0.025% w/w mometasone furoate on the anhydrous basis).
After initial priming (6 sprays), each metered spray delivers 100 microliters of suspension containing 665 mcg of olopatadine hydrochloride (equivalent to 600 mcg olopatadine base) and 25 mcg of mometasone furoate. RYALTRIS also contains benzalkonium chloride, carboxymethyl cellulose sodium, dibasic sodium phosphate heptahydrate, edetate disodium, hydrochloric acid, microcrystalline cellulose, polysorbate 80, sodium chloride, sodium hydroxide, and water. It has a pH of approximately 3.7 [see How Supplied/Storage and Handling ( 16 )] . structureolopatadine structuremometasone
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Local Nasal Adverse Reactions Nasal antihistamines are associated with epistaxis, nasal ulceration, and nasal septal perforation. Nasal corticosteroids are associated with epistaxis, nasal septal perforation, Candida albicans infection, and impaired wound healing [see Warnings and Precautions ( 5.1 )] .
Somnolence and Impaired Mental Alertness Patients should be cautioned against engaging in hazardous occupations requiring complete mental alertness and motor coordination such as driving or operating machinery after administration of RYALTRIS [see Warnings and Precautions ( 5.2 )] . Somnolence has been reported in some patients (2 of 789 patients) taking RYALTRIS in controlled clinical studies in seasonal allergic rhinitis [see Adverse Reactions ( 6.1 )] . Concurrent Use of Alcohol and Other Central Nervous System Depressants Patients should be advised to avoid concurrent use of RYALTRIS with alcohol or other CNS depressants because additional reductions in alertness and additional impairment of CNS performance may occur [see Warnings and Precautions ( 5.2 )] .
Administration Information Patients should be instructed to shake the bottle well before each use and prime RYALTRIS before initial use by releasing 6 sprays or until a fine mist appears. When RYALTRIS has not been used for 14 days or more, patients should re-prime with 2 sprays or until a fine mist appears. Patients should be instructed to avoid spraying RYALTRIS into their eyes [see Dosage and Administration ( 2 )] .
Glaucoma and Cataracts Patients should be informed that nasal and inhaled corticosteroids may result in the development of glaucoma and/or cataracts. Therefore, close monitoring is warranted in patients with a change in vision or with a history of increased intraocular pressure, glaucoma, and/or cataracts [see Warnings and Precautions ( 5.3 )] . Hypersensitivity Reactions Hypersensitivity reactions can occur with RYALTRIS.
Hypersensitivity reactions including wheezing, have occurred after the nasal administration of mometasone furoate. Discontinue RYALTRIS if such reactions occur [see Contraindications ( 4 ) and Warnings and Precautions ( 5.4 )] . Immunosuppression and Risk of Infections Persons who are on immunosuppressant doses of corticosteroids should be warned to avoid exposure to chickenpox or measles, and patients should also be advised that if they are exposed, medical advice should be sought without delay.
Inform patients of potential worsening of existing tuberculosis; fungal, bacterial, viral, or parasitic infections; or ocular herpes simplex [see Warnings and Precautions ( 5.5 )] . Potential Drug Interactions Patients should be advised to be cautious if RYALTRIS is co-administered with ketoconazole or other known strong CYP3A4 inhibitors (e.g., ritonavir, cobicistat-containing products, atazanavir, clarithromycin, indinavir, itraconazole, nefazodone, nelfinavir, saquinavir, telithromycin) [see Drug Interactions ( 7.2 )] .
Distributed by: Hikma Specialty USA Inc. Columbus, OH 43228 RYALTRIS and the RYALTRIS logo are registered trademarks of Glenmark Specialty SA Under license from Glenmark Specialty SA Revised: April 2025 PN 141197 glenmarklogo