
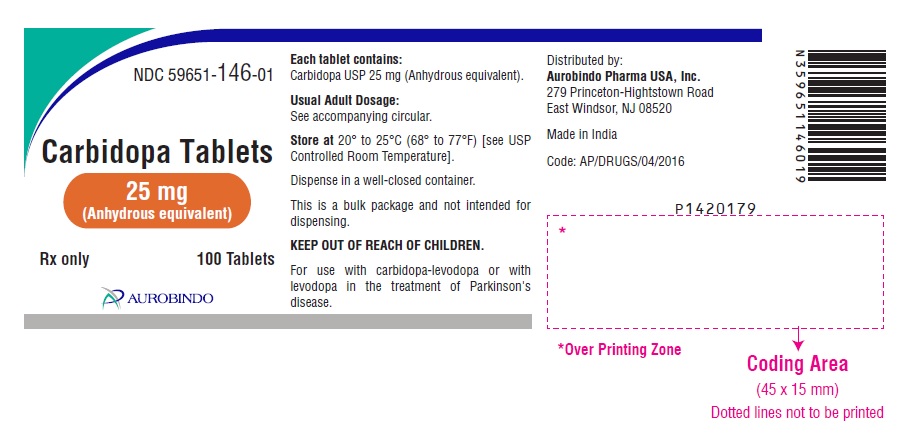
Carbidopa 25 mg Tablet, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Aromatic Amino Acid Decarboxylation Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Levodopa and carbidopa is used to treat the symptoms of Parkinson's disease and Parkinson's-like symptoms that may develop after encephalitis (swelling of the brain) or injury to the nervous system caused by carbon monoxide poisoning or manganese poisoning. Levodopa is in a class of medications called central nervous system agents. It works by being converted to dopamine in the brain (the natural substance that is low in Parkinson's and causes the symptoms of tremor, stiffness, and slowness of movement). Carbidopa is in a class of medications called decarboxylase inhibitors. It works by preven...
Read the full MedlinePlus article ↗- Carbidopa makes levodopa work much better. Without it, most of the levodopa you swallow gets converted to dopamine in your body before it ever reaches your brain — causing nausea a...
- Why do I need to take carbidopa? Can't I just take levodopa by itself?
- The most common ones are involuntary movements — things like twisting, writhing, or jerking — as well as nausea, dizziness, and unusual drowsiness. Those involuntary movements can...
- What side effects should I actually watch out for?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Carbidopa — tap one for details:
Carbidopa may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 7T9FYH5QMK
A plant-derived powder that serves as a binder and filler in tablets and capsules. It helps hold ingredients together, adds bulk, and aids in smooth tablet disintegration when swallowed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.533 | $53.25 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $1.05 | $105.00 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $1.29 | $129.05 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Carbidopa 25 mg 16714-0067-01 | NorthStar | 100 tablets | $0.532 | AB | Availability likely | — |
| Carbidopa 25 mg 42799-0123-01 | Edenbridge | 100 tablets | $0.532 | AB | Availability likely | — |
| Carbidopa 25 mgthis 59651-0146-01 | Aurobindo | 100 tablets | $0.532 | AB | Availability likely | — |
| Carbidopa 25 mg 70710-1221-01 | Zydus | 100 tablets | $0.532 | AB | Availability likely | — |
| Carbidopa 25 mg 43386-0980-01 | Lupin | 100 tablets | $1.245 | AB | FDA listed | +134% |
| Carbidopa 25 mg 68682-0200-25 | Oceanside | 100 tablets | $1.346 | AB | FDA listed | +153% |
| Lodosyn 25 mg 25010-0711-15 | Bausch | 100 tablets | — | AB | FDA listed | — |
| Carbidopa 25 mg 40032-0980-01 | Novel | 100 tablets | — | AB | FDA listed | — |
| Carbidopa 25 mg 70771-1355-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 59651-0146-01 You're viewing this | 100 TABLET in 1 BOTTLE (59651-146-01) | 2019-10-21 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Carbidopa tablets are indicated for use with carbidopa-levodopa or with levodopa in the treatment of the symptoms of idiopathic Parkinson’s disease (paralysis agitans), postencephalitic parkinsonism, and symptomatic parkinsonism, which may follow injury to the nervous system by carbon monoxide intoxication and/or manganese intoxication. Carbidopa tablets are for use with carbidopa-levodopa in patients for whom the dosage of carbidopa-levodopa provides less than adequate daily dosage (usually 70 mg daily) of carbidopa.
Carbidopa tablets are for use with levodopa in the occasional patient whose dosage requirement of carbidopa and levodopa necessitates separate titration of each medication. Carbidopa tablets are used with carbidopa-levodopa or with levodopa to permit the administration of lower doses of levodopa with reduced nausea and vomiting, more rapid dosage titration, and with a somewhat smoother response. However, patients with markedly irregular (“on-off”) responses to levodopa have not been shown to benefit from the addition of carbidopa.
Since carbidopa prevents the reversal of levodopa effects caused by pyridoxine, supplemental pyridoxine (vitamin B 6 ), can be given to patients when they are receiving carbidopa and levodopa concomitantly or as carbidopa-levodopa. Although the administration of carbidopa tablets permits control of parkinsonism and Parkinson’s disease with much lower doses of levodopa, there is no conclusive evidence at present that this is beneficial other than in reducing nausea and vomiting, permitting more rapid titration, and providing a somewhat smoother response to levodopa.
Certain patients who responded poorly to levodopa alone have improved when carbidopa and levodopa were given concurrently. This was most likely due to decreased peripheral decarboxylation of levodopa rather than to a primary effect of carbidopa on the peripheral nervous system. Carbidopa has not been shown to enhance the intrinsic efficacy of levodopa.
In deciding whether to give carbidopa tablets with carbidopa-levodopa or with levodopa to patients who have nausea and/or vomiting, the physician should be aware that, while many patients may be expected to improve, some may not. Since one cannot predict which patients are likely to improve, this can only be determined by a trial of therapy. It should be further noted that in controlled trials comparing carbidopa and levodopa with levodopa alone, about half the patients with nausea and/or vomiting on levodopa alone improved spontaneously despite being retained on the same dose of levodopa during the controlled portion of the trial.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Whether given with carbidopa-levodopa or with levodopa, the optimal daily dose of carbidopa must be determined by careful titration. Most patients respond to a 1:10 proportion of carbidopa and levodopa, provided the daily dosage of carbidopa is 70 mg or more a day. The maximum daily dosage of carbidopa should not exceed 200 mg, since clinical experience with larger dosages is limited.
If the patient is taking carbidopa-levodopa, the amount of carbidopa in carbidopa-levodopa should be considered when calculating the total amount of carbidopa to be administered each day. Patients Receiving Carbidopa-Levodopa Who Require Additional Carbidopa Some patients taking carbidopa-levodopa may not have adequate reduction in nausea and vomiting when the dosage of carbidopa is less than 70 mg a day, and the dosage of levodopa is less than 700 mg a day. When these patients are taking carbidopa-levodopa, 25 mg of carbidopa may be given with the first dose of carbidopa-levodopa each day.
Additional doses of 12.5 mg or 25 mg may be given during the day with each dose of carbidopa-levodopa. Carbidopa may be given with any dose carbidopa-levodopa as required for optimum therapeutic response. The maximum daily dosage of carbidopa, given as carbidopa and as carbidopa-levodopa), should not exceed 200 mg.
Patients Requiring Individual Titration of Carbidopa and Levodopa Dosage Although carbidopa-levodopa is the most frequently used of carbidopa and levodopa administration, there may be an occasional patient who requires individually titrated doses of these two drugs. In these patients, carbidopa should be initiated at a dosage of 25 mg three or four times a day. The two drugs should be given at the same time, starting with no more than one-fifth (20%) to one-fourth (25%) of the previous or recommended daily dosage of levodopa when given without carbidopa.
In patients already receiving levodopa therapy, at least twelve hours should elapse between the last dose of levodopa and initiation of therapy with carbidopa and levodopa. A convenient way to initiate therapy in these patients is in the morning following a night when the patient has not taken levodopa for at least twelve hours. Health care providers who prescribe separate doses of carbidopa and levodopa should be thoroughly familiar with the directions for use of each drug.
Dosage Adjustment Dosage of carbidopa may be adjusted by adding or omitting one-half or one tablet a day. Because both therapeutic and adverse responses occur more rapidly with combined therapy than when only levodopa is given, patients should be monitored closely during the dose adjustment period. Specifically, involuntary movements will occur more rapidly when carbidopa and levodopa are given concomitantly than when levodopa is given without carbidopa.
The occurrence of involuntary movements may require dosage reduction. Blepharospasm may be a useful early sign of excess dosage in some patients. Current evidence indicates other standard antiparkinsonian drugs may be continued while carbidopa and levodopa are being administered.
However, the dosage of such other standard antiparkinsonian drugs may require adjustment. Interruption of Therapy Sporadic cases of hyperpyrexia and confusion have been associated with dose reductions and withdrawal of carbidopa-Levodopa) or carbidopa-levodopa Extended Release. Patients should be observed carefully if abrupt reduction or discontinuation of carbidopa-levodopa or carbidopa-levodopa Extended-Release is required, especially if the patient is receiving neuroleptics.
(See WARNINGS .) If general anesthesia is required, therapy may be continued as long as the patient is permitted to take fluids and medication by mouth. When therapy is interrupted temporarily, the patient should be observed for symptoms resembling NMS, and the usual daily dosage may be resumed as soon as the patient is able to take medication orally.
⛔ Contraindications ▾
CONTRAINDICATIONS Carbidopa tablets are contraindicated in patients with known hypersensitivity to any component of this drug. Nonselective monoamine oxidase (MAO) inhibitors are contraindicated for use with levodopa or carbidopa-levodopa combination products with or without carbidopa. These inhibitors must be discontinued at least two weeks prior to initiating therapy with levodopa.
Carbidopa-levodopa or levodopa may be administered concomitantly with the manufacturer’s recommended dose of an MAO inhibitor with selectivity for MAO type B (e.g., selegiline HCl) (see PRECAUTIONS , Drug Interactions ). Levodopa or carbidopa-levodopa products, with or without carbidopa, are contra-indicated in patients with narrow-angle glaucoma.
⚠️ Warnings ▾
WARNINGS Carbidopa has no antiparkinsonian effect when given alone. It is indicated for use with carbidopa-levodopa or levodopa. Carbidopa does not decrease adverse reactions due to central effects of levodopa.
When carbidopa is to be given to carbidopa-naive patients who are being treated with levodopa alone, the two drugs should be given at the same time. At least twelve hours should elapse between the last dose of levodopa and initiation of therapy with carbidopa and levodopa in combination. Start with no more than one-fifth (20%) to one-fourth (25%) of the previous daily dosage of levodopa when given without carbidopa.
See the DOSAGE AND ADMINISTRATION section before initiating therapy. The addition of carbidopa with levodopa or carbidopa-levodopa reduces the peripheral effects (nausea, vomiting) due to decarboxylation of levodopa; however, carbidopa does not decrease the adverse reactions due to the central effects of levodopa. Because carbidopa permits more levodopa to reach the brain and more dopamine to be formed, certain adverse central nervous system (CNS) effects, e.g., dyskinesias (involuntary movements), may occur at lower dosages and sooner with levodopa in combination with carbidopa than with levodopa alone.
Falling Asleep During Activities of Daily Living and Somnolence Patients taking carbidopa-levodopa products alone or with other dopaminergic drugs have reported suddenly falling asleep without prior warning of sleepiness while engaged in activities of daily living (includes operation of motor vehicles). Some of these episodes resulted in automobile accidents. Although many of these patients reported somnolence while on dopaminergic medications, some did perceive that they had no warning signs, such as excessive drowsiness, and believed that they were alert immediately prior to the event.
Some patients reported these events one year after the initiation of treatment. Falling asleep while engaged in activities of daily living usually occurs in patients experiencing pre-existing somnolence, although some patients may not give such a history. For this reason, prescribers should continually reassess patients for drowsiness or sleepiness especially since some of the events occur after the start of treatment.
Prescribers should be aware that patients may not acknowledge drowsiness or sleepiness until directly questioned about drowsiness or sleepiness during specific activities. Patients who have already experienced somnolence or an episode of sudden sleep onset should not participate in these activities during treatment with carbidopa when taking it with other carbidopa-levodopa products. Before initiating treatment with carbidopa, advise patients about the potential to develop drowsiness and ask specifically about factors that may increase the risk for somnolence with carbidopa such as the use of concomitant sedating medications and the presence of sleep disorders.
Consider discontinuing carbidopa in patients who report significant daytime sleepiness or episodes of falling asleep during activities that require active participation (e.g., conversations, eating, etc.). If treatment with carbidopa continues, patients should be advised not to drive and to avoid other potentially dangerous activities that might result in harm if the patients become somnolent. There is insufficient information to establish that dose reduction will eliminate episodes of falling asleep while engaged in activities of daily living.
Hyperpyrexia and Confusion: Sporadic cases of a symptom complex resembling neuroleptic malignant syndrome (NMS) have been reported in association with dose reductions or withdrawal of certain antiparkinsonian agents such as levodopa, carbidopa-levodopa, or carbidopa-levodopa extended-release. Therefore, patients should be observed carefully when the dosage of levodopa or carbidopa-levodopa is reduced abruptly or discontinued, especially if the patient is receiving neuroleptics. NMS is an uncommon but life-threate…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Carbidopa has not been demonstrated to have any overt pharmacodynamic actions in the recommended doses. The only adverse reactions that have been observed have been with concomitant use of carbidopa with other drugs such as levodopa, and with carbidopa-levodopa combination products. When carbidopa is administered concomitantly with levodopa or carbidopa-levodopa combination products, the most common adverse reactions have included dyskinesias such as choreiform, dystonic, and other involuntary movements, and nausea.
Other adverse reactions reported with carbidopa when administered concomitantly with levodopa alone or carbidopa-levodopa combination products were psychotic episodes including delusions, hallucinations, and paranoid ideation, depression with or without development of suicidal tendencies, and dementia. Convulsions also have occurred; however, a causal relationship with concomitant use of carbidopa and levodopa has not been established. The following other adverse reactions have been reported with levodopa and carbidopa-levodopa combination products.
These same adverse reactions may also occur when carbidopa is administered with these products. Body as a Whole: abdominal pain and distress, asthenia, chest pain, fatigue. Cardiovascular: cardiac irregularities, hypertension, myocardial infarction, hypotension including orthostatic hypotension, palpitation, phlebitis, syncope.
Gastrointestinal: anorexia, bruxism, burning sensation of the tongue, constipation, dark saliva, development of duodenal ulcer, diarrhea, dry mouth, dyspepsia, dysphagia, flatulence, gastrointestinal bleeding, gastrointestinal pain, heartburn, hiccups, sialorrhea, taste alterations, vomiting. Hematologic: hemolytic and non-hemolytic anemia, leukopenia, thrombocytopenia, agranulocytosis. Hypersensitivity: angioedema, urticaria, pruritus, Henoch-Schonlein purpura, bullous lesions (including pemphigus-like reactions).
Metabolic: edema, weight gain, weight loss. Musculoskeletal: back pain, leg pain, muscle cramps, shoulder pain. Nervous System/Psychiatric: Psychotic episodes including delusions, hallucinations and paranoid ideation, neuroleptic malignant syndrome (NMS, see WARNINGS ), bradykinetic episodes (“on-off” phenomenon), confusion, agitation, dizziness, somnolence, dream abnormalities including nightmares, insomnia, paresthesia, headache, depression with or without development of suicidal tendencies, dementia, pathological gambling, increased libido including hypersexuality, impulse control symptoms.
Convulsions also have occurred; however, a causal relationship with carbidopa and levodopa, has not been established. Respiratory: upper respiratory infection, dyspnea, pharyngeal pain, cough. Skin: flushing, increased sweating, malignant melanoma (see also CONTRAINDICATIONS ), rash, alopecia, dark sweat.
Special Senses: oculogyric crises, diplopia, blurred vision, dilated pupils. Urogenital: dark urine, priapism, urinary frequency, urinary incontinence, urinary retention, urinary tract infection. Laboratory Tests: abnormalities in alkaline phosphatase, SGOT (AST), SGPT (ALT), lactic dehydrogenase, bilirubin, blood urea nitrogen (BUN), Coombs test; elevated serum glucose; decreased hemoglobin and hematocrit; decreased white blood cell count and serum potassium; increased serum creatinine and uric acid; white blood cells, bacteria and blood in the urine; protein and glucose in the urine.
Miscellaneous: bizarre breathing patterns, faintness, hoarseness, hot flashes, malaise, neuroleptic malignant syndrome, sense of stimulation.
🔄 Drug Interactions ▾
Dyskinesia Carbidopa may potentiate the dopaminergic side effects of levodopa and may cause or exacerbate preexisting dyskinesia.
🔄 Drug / Laboratory Test Interactions ▾
Depression Patients treated with carbidopa and carbidopa-levodopa should be observed carefully for the development of depression with concomitant suicidal tendencies.
🤰 Pregnancy ▾
Information for Patients It is important that carbidopa with levodopa be taken at regular intervals according to the schedule outlined by the health care provider. Caution patients not to change the prescribed dosage regimen and not to add any additional antiparkinson medications, including other carbidopa-levodopa preparations without first consulting a physician. Advise patients that sometimes a ‘wearing-off’ effect may occur at the end of the dosing interval.
Tell patients to notify the prescriber if such response poses a problem to lifestyle. Patients should be advised that occasionally dark color (red, brown, or black) may appear in saliva, urine, or sweat after ingestion of carbidopa and levodopa. Although the color appears to be clinically insignificant, garments may become discolored.
The patient should be advised that a change in diet to foods that are high in protein may delay the absorption of levodopa and may reduce the amount taken up in the circulation. Excessive acidity also delays stomach emptying thus delaying the absorption of levodopa. Iron salts (such as in multivitamin tablets) may also reduce the amount of levodopa available in the body.
The above factors may reduce the clinical effectiveness of the carbidopa and levodopa therapy. Alert patients to the possibility of sudden onset of sleep during daily activities, in some cases without awareness or warning signs, when they are taking dopaminergic agents, including levodopa. Advise patients to exercise caution while driving or operating machinery and that if they have experience somnolence and/or sudden sleep onset, they must refrain from these activities.
(See WARNINGS , Falling Asleep During Activities of Daily Living and Somnolence General .) There have been reports of patients experiencing intense urges to gamble, increased sexual urges, and other intense urges, and the inability to control these urges while taking one or more of the medications that increase central dopaminergic tone and that are generally used for the treatment of Parkinson’s disease, including carbidopa and levodopa. Although it is not proven that the medications caused these events, these urges were reported to have stopped in some cases when the dose was reduced or the medication was stopped.
Prescribers should ask patients about the development of new or increased gambling urges, sexual urges, or other intense urges while taking carbidopa and levodopa. Physicians should consider dose reduction or stopping carbidopa and levodopa if a patient develops such urges while taking carbidopa with carbidopa/levodopa (See PRECAUTIONS , Impulse Control/Compulsive Behaviors ).
🧒 Pediatric Use ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis There were no significant differences between treated and control rats with respect to mortality or neoplasia in a 96-week study of carbidopa at oral doses of 25, 45, or 135 mg/kg/day. Combinations of carbidopa and levodopa (10 to 20, 10 to 50, 10 to 100 mg/kg/day) were given orally to rats for 106 weeks. No effect on mortality or incidence and type of neoplasia was seen when compared to concurrent controls.
Mutagenesis Mutagenicity studies have not been performed with either carbidopa or the combination of carbidopa and levodopa. Fertility Carbidopa had no effect on the mating performance, fertility, or survival of the young when administered orally to rats at doses of 30, 60, or 120 mg/kg/day. The highest dose caused a moderate decrease in body weight gain in males.
The administration of carbidopa-levodopa at dose levels of 10 to 20, 10 to 50, or 10 to 100 mg/kg/day did not adversely affect the fertility of male or female rats, their reproductive performance, or the growth and survival of the young. Pregnancy Pregnancy Category C: There are no adequate and well-controlled studies with carbidopa in pregnant women. It has been reported from individual cases that levodopa crosses the human placental barrier, enters the fetus, and is metabolized.
Carbidopa concentrations in fetal tissue appeared to be minimal. Carbidopa should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Carbidopa, at doses as high as 120 mg/kg/day, was without teratogenic effects in the mouse or rabbit.
In the rabbit, but not in the mouse, carbidopa-levodopa produced visceral anomalies, similar to those seen with levodopa alone, at approximately 7 times the maximum recommended human dose. The teratogenic effect of levodopa in rabbits was unchanged by the concomitant administration of carbidopa. Nursing Mothers It is not known whether carbidopa is excreted in human milk.
Because many drugs are excreted in human milk, and because of their potential for serious adverse reactions in nursing infants, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the nursing woman. Pediatric Use Safety and effectiveness in pediatric patients have not been established, and use of the drug in patients below the age of 18 is not recommended.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of carbidopa did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and concomitant disease and other drug therapy.
🆘 Overdosage ▾
OVERDOSAGE No reports of overdose with carbidopa have been received. Management of overdosage with carbidopa is the same as that with levodopa or carbidopa-levodopa preparations. In the event of overdosage, general supportive measures should be employed, along with immediate gastric lavage.
Intravenous fluids should be administered judiciously, and an adequate airway maintained. Electrocardiographic monitoring should be instituted and the patient carefully observed for the development of arrhythmias; if required, appropriate antiarrhythmic therapy should be given. The possibility that the patient may have taken other drugs as well as carbidopa should be taken into consideration.
To date, no experience has been reported with dialysis; hence, its value in overdosage is not known. Pyridoxine is not effective in reversing the actions of carbidopa. Based on studies in which high doses of levodopa and/or carbidopa were administered, a significant proportion of rats and mice given single oral doses of levodopa of approximately 1500 to 2000 mg/kg are expected to die.
A significant proportion of infant rats of both sexes are expected to die at a dose of 800 mg/kg. A significant proportion of rats are expected to die after treatment with similar doses of carbidopa. The addition of carbidopa in a 1:10 ratio with levodopa increases the dose at which a significant proportion of mice are expected to die to 3360 mg/kg.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Parkinson’s disease is a progressive, neurodegenerative disorder of the extrapyramidal nervous system affecting the mobility and control of the skeletal muscular system. Its characteristic features include resting tremor, rigidity, and bradykinetic movements. Symptomatic treatments, such as levodopa therapies, may permit the patient better mobility.
Mechanism of Action Current evidence indicates that symptoms of Parkinson’s disease are related to depletion of dopamine in the corpus striatum. Administration of dopamine is ineffective in the treatment of Parkinson’s disease apparently because it does not cross the blood-brain barrier. However, levodopa, the metabolic precursor of dopamine, does cross the blood-brain barrier, and presumably is converted to dopamine in the brain.
This is thought to be the mechanism whereby levodopa relieves symptoms of Parkinson’s disease. Pharmacodynamics When levodopa is administered orally it is rapidly decarboxylated to dopamine in extracerebral tissues so that only a small portion of a given dose is transported unchanged to the central nervous system. For this reason, large doses of levodopa are required for adequate therapeutic effect and these may often be accompanied by nausea and other adverse reactions, some of which are attributable to dopamine formed in extracerebral tissues.
The incidence of levodopa-induced nausea and vomiting is less when carbidopa is used with levodopa than when levodopa is used without carbidopa. In many patients, this reduction in nausea and vomiting will permit more rapid dosage titration. Carbidopa inhibits decarboxylation of peripheral levodopa.
Carbidopa has not been demonstrated to have any overt pharmacodynamic actions in the recommended doses. It does not appear to cross the blood-brain barrier readily and does not affect the metabolism of levodopa within the central nervous system at doses of carbidopa that are recommended for maximum effective inhibition of peripheral decarboxylation of levodopa. Since its decarboxylase-inhibiting activity is limited primarily to extracerebral tissues, administration of carbidopa with levodopa makes more levodopa available for transport to the brain.
However, since levodopa and carbidopa compete with certain amino acids for transport across the gut wall, the absorption of levodopa and carbidopa may be impaired in some patients on a high protein diet. Pharmacokinetics Carbidopa reduces the amount of levodopa required to produce a given response by about 75% and, when administered with levodopa, increases both plasma levels and the plasma half-life of levodopa, and decreases plasma and urinary dopamine and homovanillic acid. In clinical pharmacologic studies, simultaneous administration of separate tablets of carbidopa and levodopa produced greater urinary excretion of levodopa in proportion to the excretion of dopamine when compared to the two drugs administered at separate times.
Supplemental pyridoxine (vitamin B 6 ) can be given to patients when they are receiving carbidopa and levodopa concomitantly or the fixed combination carbidopa-levodopa or carbidopa-levodopa extended release. Previous reports in the medical literature cautioned that high doses of vitamin B 6 should not be taken by patients on levodopa therapy alone because exogenously administered pyridoxine would enhance the metabolism of levodopa to dopamine. The introduction of carbidopa to levodopa therapy, which inhibits the peripheral decarboxylation of levodopa to dopamine, counteracts the metabolic-enhancing effect of pyridoxine.
Carbidopa is combined with levodopa in carbidopa-levodopa and carbidopa-levodopa extended release tablets.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Carbidopa Tablets, 25 mg: White to off-white, round shaped, uncoated scored tablets debossed with “R” above the score line and “1” below the score line on one side and plain on other side. They are supplied as follows: Bottles of 100’s NDC 59651-146-01 Storage Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. Distributed by: Aurobindo Pharma USA, Inc.
279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 038, India Issued: June 2018
📋 Description ▾
DESCRIPTION Carbidopa, an inhibitor of aromatic amino acid decarboxylation, is a white to yellowish white powder, slightly soluble in water, very slightly soluble in ethanol (96%), practically insoluble in methylene chloride, with a molecular weight of 244.3. It is designated chemically as (–)-L-α-hydrazino-α-methyl-β-(3,4-dihydroxybenzene) propanoic acid monohydrate. Its molecular formula is C 10 H 14 N 2 O 4 •H 2 O and its structural formula is: Each tablet contains 25 mg of carbidopa USP (anhydrous equivalent).
Inactive ingredients are magnesium stearate, microcrystalline cellulose and pregelatinized starch (maize). Tablet content is expressed in terms of anhydrous carbidopa which has a molecular weight of 226.3. chemical structure
💬 Information for Patients ▾
Impulse Control/Compulsive Behaviors Postmarketing reports suggest that patients treated with anti-Parkinson medications can experience intense urges to gamble, increased sexual urges, intense urges to spend money uncontrollably, binge eating, and other intense urges. Patients may be unable to control these urges while taking one or more of the medications that are used for the treatment of Parkinson’s disease and that increase central dopaminergic tone, including carbidopa taken with levodopa and carbidopa. In some cases, although not all, these urges were reported to have stopped when the dose of anti-Parkinson medications was reduced or discontinued.
Because patients may not recognize these behaviors as abnormal it is important for prescribers to specifically ask patients or their caregivers about the development of new or increased gambling urges, sexual urges, uncontrolled spending or other urges while being treated with carbidopa. Physicians should consider dose reduction or stopping carbidopa or levodopa if a patient develops such urges while taking carbidopa with carbidopa/levodopa.