
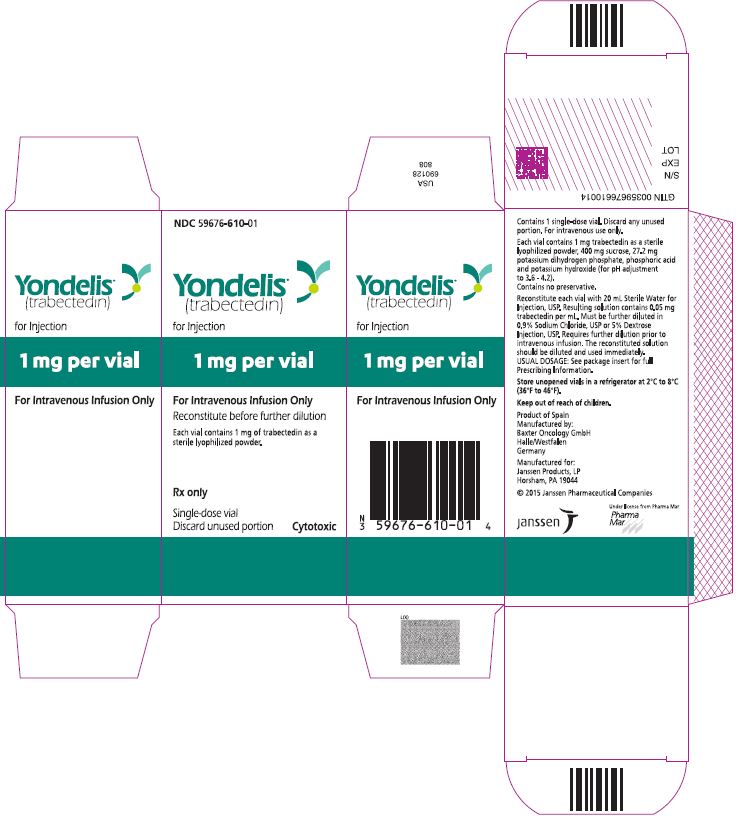
YONDELIS Trabectedin .05 mg/mL Injection, Powder, Lyophilized, For Solution, 20 mL
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Alkylating Drug class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Trabectedin injection is used to treat liposarcoma (a cancer that begins in fat cells) or leiomyosarcoma (a cancer that begins in smooth muscle tissue) that has spread to other parts of the body and cannot be treated with surgery in people who have already been treated with certain chemotherapy medications. Trabectedin is in a class of medications called alkylating agents. It works by slowing or stopping the growth of cancer cells in your body.
Read the full MedlinePlus article ↗- Trabectedin injection — sold as Yondelis and Evdi — is used to treat two specific types of soft tissue cancer: liposarcoma (cancer of fat tissue) and leiomyosarcoma (cancer of smoo...
- What exactly is trabectedin used to treat?
- Trabectedin is given as an IV infusion that runs continuously over 24 hours — so it's a full-day treatment in a clinical setting. You'll come in once every 3 weeks, which is one tr...
- How is this drug given, and how often will I need to come in?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Trabectedin — tap one for details:
Trabectedin may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 4J9FJ0HL51
Potassium phosphate, monobasic is a salt compound used in medicines as a pH buffer and electrolyte source. It helps stabilize the acidity level of liquid and powdered formulations.
-
UNII E4GA8884NN
Phosphoric acid is a weak mineral acid used in medicines as a buffer and pH adjuster. It helps stabilize the product and control its acidity level.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $3,862.28 | $77,245.69 / 20 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9999 | No ASP payment limit on file for J9999 this quarter. | |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Yondelis .05 mg/mLthis 59676-0610-01 | Janssen | 20 ml | — | — | FDA listed | — |
| Evdi .05 mg/mL 60505-6423-00 | Apotex | 1 vial | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8895557 ↗ | Drug product | — | Jan 7, 2028 |
| US 8895557*PED ↗ | Drug product | — | Jul 7, 2028 |
Is there a generic version of YONDELIS 1 MG VIAL?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 59676-0610-01 You're viewing this | 20 mL in 1 VIAL, SINGLE-USE (59676-610-01) | 2015-10-23 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE YONDELIS ® is indicated for the treatment of adult patients with unresectable or metastatic liposarcoma or leiomyosarcoma who received a prior anthracycline-containing regimen [see Clinical Studies (14) ] . YONDELIS is an alkylating drug indicated for the treatment of adult patients with unresectable or metastatic liposarcoma or leiomyosarcoma who received a prior anthracycline-containing regimen ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administer at 1.5 mg/m 2 as a 24-hour intravenous infusion, every 3 weeks through a central venous line ( 2.1 , 2.6 ) Premedication: dexamethasone 20 mg intravenously, 30 min before each infusion ( 2.3 ) Hepatic Impairment: Administer at 0.9 mg/m 2 as a 24-hour intravenous infusion, every 3 weeks through a central venous line in patients with moderate hepatic impairment ( 2.2 )
2.1Recommended Dosage The recommended dose is 1.5 mg/m 2 administered as an intravenous infusion over 24 hours through a central venous line every 21 days (3 weeks), until disease progression or unacceptable toxicity.
2.2Recommended Dosage in Patients with Hepatic Impairment The recommended dosage of YONDELIS in patients with moderate hepatic impairment (bilirubin levels greater than 1.5 times to 3 times the upper limit of normal, and AST and ALT less than 8 times the upper limit of normal) is 0.9 mg/m 2 every 21 days (3 weeks). Do not administer YONDELIS to patients with severe hepatic impairment (bilirubin levels above 3 times the upper limit of normal, and any AST and ALT) [ see Use in Specific Populations (8.6) and Clinical Pharmacology (12.3) ] .
2.3Premedication Administer dexamethasone 20 mg intravenously 30 minutes prior to each dose of YONDELIS.
2.4Dosage Modifications for Adverse Reactions Permanently discontinue YONDELIS for: Persistent adverse reactions requiring a delay in dosing of more than 3 weeks. Adverse reactions requiring dose reduction following YONDELIS administered at 1.0 mg/m 2 for patients with normal hepatic function or at 0.3 mg/m 2 for patients with pre-existing moderate hepatic impairment. Severe liver dysfunction: bilirubin two times the upper limit of normal, and AST or ALT three times the upper limit of normal, and alkaline phosphatase less than two times the upper limit of normal in the prior treatment cycle for patients with normal liver function at baseline.
Exacerbation of liver dysfunction in patients with pre-existing moderate hepatic impairment. Capillary leak syndrome. Rhabdomyolysis.
Grade 3 or 4 cardiac adverse events (AEs) indicative of cardiomyopathy or for subjects with an LVEF that decreases below the lower limit of normal. The recommended dose modifications for adverse reactions are listed in Table 1. Once reduced, the dose of YONDELIS should not be increased in subsequent treatment cycles.
Table 1: Recommended Dosage Modification Laboratory Result or Adverse Reaction DELAY next dose of YONDELIS for up to 3 weeks REDUCE next dose of YONDELIS by one dose level for adverse reaction(s) during prior cycle Platelets Less than 100,000 platelets/microliter Less than 25,000 platelets/microliter Absolute neutrophil count Less than 1,500 neutrophils/microliter Less than 1,000 neutrophils/microliter with fever/infection Less than 500 neutrophils/microliter lasting more than 5 days Total bilirubin Greater than the upper limit of normal Greater than the upper limit of normal Aspartate aminotransferase (AST) or alanine aminotransferase (ALT) More than 2.5 times the upper limit of normal More than 5 times the upper limit of normal Alkaline phosphatase (ALP) More than 2.5 times the upper limit of normal More than 2.5 times the upper limit of normal Creatine phosphokinase More than 2.5 times the upper limit of normal More than 5 times the upper limit of normal Other non-hematologic adverse reactions Grade 3 or 4 Grade 3 or 4 The recommended starting doses and dose reductions for YONDELIS are listed in Table 2: Table 2: Recommended Starting Doses and Dose Reductions Starting Dose and Dose Reduction For patients with normal hepatic function or mild hepatic impairment Including patients with bilirubin greater than 1 to 1.5 times the upper limit of normal, and any AST or ALT. prior to initiation of YONDELIS treatment For patients with moderate hepatic impairment Including patients with bilirubin levels greater than 1.5 times to 3 times the upper limit of normal, and AST and ALT less than 8 times…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For injection: 1 mg, lyophilized powder in single-dose vial for reconstitution. For injection: 1 mg sterile lyophilized powder in a single-dose vial ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS YONDELIS is contraindicated in patients with known severe hypersensitivity, including anaphylaxis, to trabectedin. Known hypersensitivity to trabectedin ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Neutropenic sepsis: Severe, and fatal, neutropenic sepsis may occur. Monitor neutrophil count during treatment. Withhold YONDELIS for neutrophil count < 1,500/mcL ( 2.4 , 5.1 ) Rhabdomyolysis: Rhabdomyolysis may occur.
Monitor creatine phosphokinase (CPK) levels prior to each administration. Withhold YONDELIS for CPK more than 2.5 times the upper limit of normal. ( 2.4 , 5.2 ) Hepatotoxicity: Hepatotoxicity may occur.
Monitor and delay and/or reduce dose if needed ( 5.3 ) Cardiomyopathy: Severe and fatal cardiomyopathy can occur. Patients with left ventricular ejection fraction (LVEF) < lower limit of normal, prior cumulative anthracycline dose of ≥300 mg/m 2 , age ≥65 years, or a history of cardiovascular disease may be at increased risk of developing new or worsening cardiac dysfunction. Discontinue YONDELIS in patients who develop decreased LVEF or cardiomyopathy ( 2.4 , 5.4 ) Capillary leak syndrome: Monitor and discontinue YONDELIS for capillary leak syndrome ( 5.5 ) Embryo-fetal toxicity: Can cause fetal harm.
Advise of potential risk to a fetus and use effective contraception ( 5.7 , 8.1 , 8.3 )
5.1Neutropenic Sepsis Neutropenic sepsis, including fatal cases, can occur with YONDELIS. In Trial ET743-SAR-3007, the incidence of Grade 3 or 4 neutropenia, based on laboratory values, in patients receiving YONDELIS was 43% (161/378). The median time to the first occurrence of Grade 3 or 4 neutropenia was 16 days (range: 8 days to 9.7 months); the median time to complete resolution of neutropenia was 13 days (range: 3 days to 2.3 months).
Febrile neutropenia (fever ≥38.5 °C with Grade 3 or 4 neutropenia) occurred in 18 patients (5%) treated with YONDELIS. Ten patients (2.6%) experienced neutropenic sepsis, 5 of whom had febrile neutropenia, which was fatal in 4 patients (1.1%). Assess neutrophil count prior to administration of each dose of YONDELIS and periodically throughout the treatment cycle.
Withhold or reduce dose of YONDELIS based on severity of adverse reaction [see Dosage and Administration (2.4) ] .
5.2Rhabdomyolysis YONDELIS can cause rhabdomyolysis and musculoskeletal toxicity. In Trial ET743-SAR-3007, rhabdomyolysis leading to death occurred in 3 (0.8%) of the 378 patients receiving YONDELIS. Elevations in creatine phosphokinase (CPK) occurred in 122 (32%) of the 378 patients receiving YONDELIS, including Grade 3 or 4 CPK elevation in 24 patients (6%), compared to 15 (9%) of the 172 patients receiving dacarbazine with any CPK elevation, including 1 patient (0.6%) with Grade 3 CPK elevation.
Among the 24 patients receiving YONDELIS with Grade 3 or 4 CPK elevation, renal failure occurred in 11 patients (2.9%); rhabdomyolysis with the complication of renal failure occurred in 4 of these 11 patients (1.1%). The median time to first occurrence of Grade 3 or 4 CPK elevations was 2 months (range: 1 to 11.5 months). The median time to complete resolution was 14 days (range: 5 days to 1 month).
Assess CPK levels prior to each administration of YONDELIS. Withhold, reduce dose, or permanently discontinue based on severity of adverse reaction [see Dosage and Administration (2.4) ] .
5.3Hepatotoxicity Hepatotoxicity, including hepatic failure, can occur with YONDELIS. Patients with serum bilirubin levels above the upper limit of normal or AST or ALT levels >2.5 × upper limit of normal were not enrolled in Trial ET743-SAR-3007. In Trial ET743-SAR-3007, the incidence of Grade 3–4 elevated liver function tests (LFTs; defined as elevations in ALT, AST, total bilirubin, or alkaline phosphatase) was 35% (134/378) in patients receiving YONDELIS.
The median time to development of Grade 3–4 elevation in ALT or AST was 29 days (range: 3 days to 11.5 months). Of the 134 patients with Grade 3–4 elevations in LFTs, 114 (85%) experienced complete resolution with the median time to complete resolution of 13 days (range: 4 days to 4.4 months). In Trial ET743-SAR-3007, the incidence of drug-induced liver injury (d…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in more detail in other sections of the labeling: Anaphylaxis [see Contraindications (4) ] Neutropenic Sepsis [see Warnings and Precautions (5.1) ] Rhabdomyolysis [see Warnings and Precautions (5.2) ] Hepatotoxicity [see Warnings and Precautions (5.3) ] Cardiomyopathy [see Warnings and Precautions (5.4) ] Capillary Leak Syndrome [see Warnings and Precautions (5.5) ] Extravasation Resulting in Tissue Necrosis [see Warnings and Precautions (5.6) ] The most common (≥20%) adverse reactions are nausea, fatigue, vomiting, constipation, decreased appetite, diarrhea, peripheral edema, dyspnea, and headache.
The most common (≥5%) grades 3–4 laboratory abnormalities are: neutropenia, increased ALT, thrombocytopenia, anemia, increased AST, and increased creatine phosphokinase. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Janssen Products, LP at 1-800-526-7736 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data described below reflect exposure to YONDELIS in 755 patients with soft tissue sarcoma including 197 (26%) patients exposed to YONDELIS for greater than or equal to 6 months and 57 (8%) patients exposed to YONDELIS for greater than or equal to 1 year.
The safety of YONDELIS was evaluated in six open-label, single-arm trials, in which 377 patients received YONDELIS and one open-label, randomized, active-controlled clinical trial in which 378 patients received YONDELIS (Trial ET743-SAR-3007). All patients received YONDELIS at the recommended dosing regimen of 1.5 mg/m 2 administered as an intravenous infusion over 24 hours once every 3 weeks (q3wk, 24-h). The median age was 54 years (range: 18 to 81 years), 63% were female, and all patients had metastatic soft tissue sarcoma.
Tables 3 and 4 present selected adverse reactions and laboratory abnormalities, respectively, observed in Trial ET743-SAR-3007, an open-label, randomized (2:1), active-controlled trial in which 550 patients with previously treated leiomyosarcoma or liposarcoma (dedifferentiated, myxoid round cell, or pleomorphic) received YONDELIS 1.5 mg/m 2 intravenous infusion over 24 hours once every 3 weeks (n=378) or dacarbazine 1000 mg/m 2 intravenous infusion over 20 to 120 minutes once every 3 weeks (n=172) [see Clinical Studies (14) ] .
All patients treated with YONDELIS were required to receive dexamethasone 20 mg intravenous injection 30 minutes prior to start of the YONDELIS infusion. In Trial ET743-SAR-3007, patients had been previously treated with an anthracycline- and ifosfamide-containing regimen or with an anthracycline-containing regimen and one additional cytotoxic chemotherapy regimen. The trial excluded patients with known central nervous system metastasis, elevated serum bilirubin or significant chronic liver disease, such as cirrhosis or active hepatitis, and history of myocardial infarction within 6 months, history of New York Heart Association Class II to IV heart failure, or abnormal left ventricular ejection fraction at baseline.
The median age of patients in Trial ET743-SAR-3007 was 57 years (range: 17 to 81 years), with 69% female, 77% White, 12% Black or African American, 4% Asian, and <1% American Indian or Alaska Native. The median duration of exposure to trabectedin was 13 weeks (range: 1 to 127 weeks) with 30% of patients exposed to YONDELIS for greater than 6 months and 7% of patients exposed to YONDELIS for greater than 1 year. In Trial ET743-SAR-3007, adverse reactions resulting in permanent discontinuation of YONDELIS occurred in 26% (98/378) of patients; the most common were increased liver tests (defined as ALT, AST, alkaline phosphatase, bilirubin) (5.6%), thrombocyt…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS CYP3A inhibitors: Avoid concomitant strong CYP3A inhibitors ( 7.1 ) CYP3A inducers: Avoid concomitant strong CYP3A inducers ( 7.2 )
7.1Effect of Cytochrome CYP3A Inhibitors Coadministration of YONDELIS with ketoconazole, a strong CYP3A inhibitor, increased systemic exposure of trabectedin by 66%. Avoid using strong CYP3A inhibitors (e.g., oral ketoconazole, itraconazole, posaconazole, voriconazole, clarithromycin, telithromycin, indinavir, lopinavir, ritonavir, boceprevir, nelfinavir, saquinavir, telaprevir, nefazodone, conivaptan) in patients taking YONDELIS. If a strong CYP3A inhibitor for short-term use (i.e., less than 14 days) must be used, administer the strong CYP3A inhibitor 1 week after the YONDELIS infusion, and discontinue it the day prior to the next YONDELIS infusion [see Clinical Pharmacology (12.3) ] .
7.2Effect of Cytochrome CYP3A Inducers Coadministration of YONDELIS with rifampin, a strong CYP3A inducer, decreased systemic exposure of trabectedin by 31%. Avoid using strong CYP3A inducers (e.g., rifampin, phenobarbital, St. John's wort) in patients taking YONDELIS [see Clinical Pharmacology (12.3) ] .
Drug Interactions Effect of Strong CYP3A Inhibitors on Trabectedin Coadministration of multiple doses of ketoconazole (200 mg twice daily for 7.5 days) with a single dose of YONDELIS (0.58 mg/m 2 ) on day 1 increased trabectedin dose-normalized AUC by 66% and C max by 22% compared to a single YONDELIS dose (1.3 mg/m 2 ) given alone. Effect of Strong CYP3A Inducers on Trabectedin Coadministration of multiple doses of rifampin (600 mg daily for 6 days) with a single YONDELIS dose (1.3 mg/m 2 ) on day 6 decreased trabectedin AUC by 31% and C max by 21% compared to a single YONDELIS dose (1.3 mg/m 2 ) given alone.
Effect of Trabectedin on CYP Enzymes In vitro , trabectedin has limited inhibition or induction potential of major CYP enzymes (CYP1A2, 2A6, 2B6, 2C9, 2C19, 2D6, 2E1, and 3A4).
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed ( 8.2 ) Hepatic Impairment: Do not administer YONDELIS to patients with severe hepatic impairment ( 8.6 , 12.3 )
8.1Pregnancy Risk Summary Based on its mechanism of action, trabectedin can cause fetal harm when administered during pregnancy [see Clinical Pharmacology (12.1) ] . There are no available data with the use of YONDELIS during pregnancy. Animal reproductive and developmental studies at relevant doses have not been conducted with trabectedin; however, placental transfer of trabectedin was demonstrated in pregnant rats.
Advise pregnant woman of the potential risk to a fetus. The background risk of major birth defects and miscarriage for the indicated population are unknown; however, the background risk in the U.S. general population of major birth defects is 2 to 4% and of miscarriage is 15 to 20% of clinically recognized pregnancies.
8.2Lactation Risk Summary There are no data on the presence of trabectedin in human milk, the effects on the breastfed child, or the effects on milk production. Because of the potential for serious adverse reactions from YONDELIS in a breastfed child, advise a nursing woman to discontinue nursing during treatment with and for 3 months after the last dose of YONDELIS.
8.3Females and Males of Reproductive Potential Pregnancy Testing Verify the pregnancy status of females of reproductive potential prior to initiating YONDELIS [see Use in Specific Populations (8.1) ] . Contraception Females Advise female patients of reproductive potential to use effective contraception during and for 8 months after the last dose of YONDELIS [see Use in Specific Populations (8.1) ] . Males YONDELIS may damage spermatozoa, resulting in possible genetic and fetal abnormalities.
Advise males with a female sexual partner of reproductive potential to use effective contraception during and for 5 months after the last dose of YONDELIS [see Nonclinical Toxicology (13.1) ] . Infertility YONDELIS may result in decreased fertility in males and females [see Nonclinical Toxicology (13.1) ] .
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. Safety (n=61) and efficacy (n=58) were assessed across five open-label studies (NCT00006463, NCT01453283, NCT00005625, NCT00070109, and ET-B-023-00) in pediatric patients (aged 2 to <17 years) with pediatric histotypes of sarcoma (predominantly rhabdomyosarcoma, osteosarcoma, Ewing sarcoma, and non-rhabdomyosarcoma soft tissue sarcoma). No new safety signals were observed in pediatric patients across these studies.
Pharmacokinetic parameters in 17 pediatric patients (aged 3 to 17 years) were within the range of values previously observed in adults given the same dose per body surface area.
8.5Geriatric Use Clinical studies of YONDELIS did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects.
8.6Hepatic Impairment The mean trabectedin exposure was (97%) higher in patients with moderate (bilirubin levels greater than 1.5 to 3 times the upper limit of normal, and AST and ALT less than 8 times the upper limit of normal) hepatic impairment compared to patients with normal (total bilirubin ≤ the upper limit of normal, and AST and ALT ≤ the upper limit of normal) liver function. Reduce YONDELIS dose in patients with moderate hepatic impairment [see Dosage and Administration (2.2) and Clinical Pharmacology (12.3) ] .
Do not administer YONDELIS to patients with severe hepatic impairment (bilirubin levels above 3 times the upper limit of normal, and any AST and ALT) [see Warnings and Precautions (5.3) ] .
8.7Renal Impairment No dose adjustment is recommended in patients with mild [creatinine clearance (CLcr) 60–89 mL/min] or moderate (CLcr of 30–59 mL/min) renal impairment. The pharmacokinetics of trabectedin has not been evaluated in patients with severe renal impairment (CLcr <30 mL/min) or end stage renal di…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on its mechanism of action, trabectedin can cause fetal harm when administered during pregnancy [see Clinical Pharmacology (12.1) ] . There are no available data with the use of YONDELIS during pregnancy. Animal reproductive and developmental studies at relevant doses have not been conducted with trabectedin; however, placental transfer of trabectedin was demonstrated in pregnant rats.
Advise pregnant woman of the potential risk to a fetus. The background risk of major birth defects and miscarriage for the indicated population are unknown; however, the background risk in the U.S. general population of major birth defects is 2 to 4% and of miscarriage is 15 to 20% of clinically recognized pregnancies.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. Safety (n=61) and efficacy (n=58) were assessed across five open-label studies (NCT00006463, NCT01453283, NCT00005625, NCT00070109, and ET-B-023-00) in pediatric patients (aged 2 to <17 years) with pediatric histotypes of sarcoma (predominantly rhabdomyosarcoma, osteosarcoma, Ewing sarcoma, and non-rhabdomyosarcoma soft tissue sarcoma). No new safety signals were observed in pediatric patients across these studies.
Pharmacokinetic parameters in 17 pediatric patients (aged 3 to 17 years) were within the range of values previously observed in adults given the same dose per body surface area.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of YONDELIS did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects.
🆘 Overdosage ▾
10 OVERDOSAGE There is no specific antidote for YONDELIS. Hemodialysis is not expected to enhance the elimination of YONDELIS because trabectedin is highly bound to plasma proteins (97%) and not significantly renally excreted.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Trabectedin is an alkylating drug that binds guanine residues in the minor groove of DNA, forming adducts and resulting in a bending of the DNA helix towards the major groove. Adduct formation triggers a cascade of events that can affect the subsequent activity of DNA binding proteins, including some transcription factors, and DNA repair pathways, resulting in perturbation of the cell cycle and eventual cell death.
12.2Pharmacodynamics Cardiac Electrophysiology The effect of trabectedin on the QT/QTc interval was evaluated in 75 patients who received placebo on day 1 and trabectedin (1.3 mg/m 2 ) as a 3-hour intravenous infusion on day 2. No patients in the study showed a QTc interval exceeding 500 msec or more than 60 msec increase from baseline, and no large changes in the mean QTc interval (i.e., >20 msec) were observed.
12.3Pharmacokinetics The pharmacokinetics of trabectedin is characterized by a rapid decline phase at the end of the infusion and slower exponential phases. Population pharmacokinetic analyses suggest that the pharmacokinetics of trabectedin is dose-proportional (over the dose range of 0.024 to 1.8 mg/m 2 ) and exposure is time-independent. No accumulation of trabectedin in plasma is observed upon repeated administrations every 3 weeks.
Distribution Binding of trabectedin to human plasma proteins was approximately 97%, independent of trabectedin concentrations ranging from 10 ng/mL to 100 ng/mL. Steady state volume of distribution of trabectedin exceeds 5000 L. Elimination The estimated mean (% coefficient of variation) clearance of trabectedin is
31.5L/hr (50%) and the terminal elimination half-life is approximately 175 hours. Metabolism CYP3A is the predominant CYP enzyme responsible for the hepatic metabolism of trabectedin. Trabectedin was extensively metabolized with negligible unchanged drug in urine and feces following administration of trabectedin to humans.
Excretion In patients with solid tumors, following a 3-hour or a 24-hour intravenous infusion of 14 C-labeled trabectedin, 64% of the total administered radioactive dose was recovered in 24 days, with 58% in feces and 6% in urine. Specific Populations The following population characteristics are not associated with a clinically significant effect on the pharmacokinetics of trabectedin: sex, age (19 to 83 years), body weight (36 to 148 kg), body surface area (0.9 to 2.8 m 2 ), mild hepatic impairment, or mild to moderate renal impairment.
The effects of severe hepatic impairment, severe renal impairment or end stage renal disease on trabectedin exposure are unknown. Hepatic Impairment The geometric mean dose normalized trabectedin exposure (AUC) increased by 97% (90% CI: 20%, 222%) in patients with moderate hepatic impairment (bilirubin levels greater than 1.5 times to 3 times the upper limit of normal and AST and ALT less than 8 times the upper limit of normal) following administration of a single YONDELIS dose of 0.58 mg/m 2 or 0.9 mg/m 2 compared to patients with normal liver function following administration of a single YONDELIS dose of 1.3 mg/m 2 [see Dosage and Administration (2.2) and Use in Specific Populations (8.6) ] .
Drug Interactions Effect of Strong CYP3A Inhibitors on Trabectedin Coadministration of multiple doses of ketoconazole (200 mg twice daily for 7.5 days) with a single dose of YONDELIS (0.58 mg/m 2 ) on day 1 increased trabectedin dose-normalized AUC by 66% and C max by 22% compared to a single YONDELIS dose (1.3 mg/m 2 ) given alone. Effect of Strong CYP3A Inducers on Trabectedin Coadministration of multiple doses of rifampin (600 mg daily for 6 days) with a single YONDELIS dose (1.3 mg/m 2 ) on day 6 decreased trabectedin AUC by 31% and C max by 21% compared to a single YONDELIS dose (1.3 mg/m 2 ) given alone.
Effect of Trabectedin on CYP Enzymes In vitro , trabectedin has limited inhibition or induction potential of major CYP enzymes (CYP1A2, 2A6, 2B6, 2C9, 2C19, 2D6,…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Trabectedin is an alkylating drug that binds guanine residues in the minor groove of DNA, forming adducts and resulting in a bending of the DNA helix towards the major groove. Adduct formation triggers a cascade of events that can affect the subsequent activity of DNA binding proteins, including some transcription factors, and DNA repair pathways, resulting in perturbation of the cell cycle and eventual cell death.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING YONDELIS ® is supplied in a single-dose glass vial containing 1 mg trabectedin. Each carton contains one vial (NDC: 59676-610-01). Storage and Handling Store YONDELIS vials in a refrigerator at 2 °C to 8 °C (36 °F to 46 °F). YONDELIS is a hazardous drug. Follow applicable special handling and disposal procedures. 1
📦 Storage and Handling ▾
Storage and Handling Store YONDELIS vials in a refrigerator at 2 °C to 8 °C (36 °F to 46 °F). YONDELIS is a hazardous drug. Follow applicable special handling and disposal procedures. 1
📋 Description ▾
11 DESCRIPTION Trabectedin is an alkylating drug with the chemical name (1' R ,6 R ,6a R ,7 R ,13 S ,14 S ,16 R )-5-(acetyloxy)-3',4',6,6a,7,13,14,16-octahydro-6',8,14-trihydroxy-7',9-dimethoxy-4,10,23-trimethyl-spiro[6,16-(epithiopropanoxymethano)-7,13-imino-12 H -1,3-dioxolo[7,8]isoquino[3,2- b ][3]benzazocine-20,1'(2' H )-isoquinolin]-19-one. The molecular formula is C 39 H 43 N 3 O 11 S. The molecular weight is 761.84 daltons.
The chemical structure is shown below: Trabectedin is hydrophobic and has a low solubility in water. YONDELIS ® (trabectedin) for injection is supplied as a sterile lyophilized white to off-white powder/cake in a single-dose vial. Each single-dose vial contains 1 mg of trabectedin, 27.2 mg potassium dihydrogen phosphate, 400 mg sucrose, and phosphoric acid and potassium hydroxide (for pH adjustment to 3.6 – 4.2).
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Myelosuppression : Inform patients of the risks of myelosuppression. Instruct patients to immediately contact their healthcare provider for fever or unusual bruising, bleeding, tiredness, or paleness [see Warnings and Precautions (5.1) ] .
Rhabdomyolysis : Advise patients to contact their healthcare provider if they experience severe muscle pain or weakness, or if they experience reddish-brown urine [see Warnings and Precautions (5.2) ] . Hepatotoxicity : Advise patients to contact their healthcare provider immediately for yellowing of skin and eyes (jaundice), pain in the upper right quadrant, severe nausea or vomiting, difficulty in concentrating, disorientation, or confusion [see Warnings and Precautions (5.3) ] . Cardiomyopathy : Advise patients to contact their healthcare provider immediately for new onset chest pain, shortness of breath, fatigue, lower extremity edema, or heart palpitations [see Warnings and Precautions (5.4) ] .
Capillary leak syndrome : Advise patients to report symptoms such as edema with or without hypotension [see Warnings and Precautions (5.5) and Adverse Reactions (6.2) ] . Extravasation : Inform patients of the risks of extravasation and to notify their healthcare provider for redness, swelling, itchiness and discomfort or leakage at the injection site [see Warnings and Precautions (5.6) ] . Hypersensitivity : Advise patients to seek immediate medical attention for symptoms of allergic reactions including difficulty breathing, chest tightness, wheezing, severe dizziness or light-headedness, swelling of the lips or skin rash [see Contraindications (4) ] .
Embryofetal toxicity : Advise pregnant women of the potential risk to a fetus. Advise females to contact their healthcare provider if they become pregnant, or if pregnancy is suspected, during treatment with YONDELIS [see Warnings and Precautions (5.7) and Use in Specific Populations (8.1) ] . Females and males of reproductive potential : Advise females of reproductive potential to use effective contraception during treatment with YONDELIS and for at least 8 months after last dose.
Advise males with female partners of reproductive potential to use effective contraception during treatment with YONDELIS and for at least 5 months after the last dose [see Warnings and Precautions (5.7) and Use in Specific Populations (8.3) ] . Lactation : Advise females not to breastfeed during treatment with and for 3 months after the last dose of YONDELIS [see Use in Specific Populations (8.2) ] .