
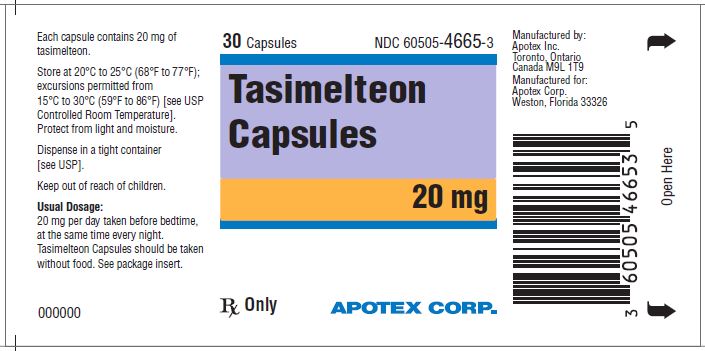
Tasimelteon 20 mg Capsule, 30-count — NDC 60505-4665-3 (Billing 60505-4665-03)
This is a package of 30 capsules of Tasimelteon 20 mg Capsule from Apotex Corp., marketed since Jan 2024 and currently FDA-listed; retail pharmacies pay about $228.25 per capsule (NADAC). It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 60505-4665-3 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 60505 labeler · 4665 product · 3 package
- Package marketed since
- Jan 5, 2024
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 30 EA per package
- Barcode (UPC-A, from the NDC)
- 3 6050546653 5
- Medicaid fills, this package
- 437 prescriptions in the last four reported quarters
- FDA record last changed
- Oct 8, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 072007
- GCN: 36068
- HICL (First Databank): 040927
- AHFS class code: 28:24.48.00
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
Clinical
Tasimelteon is used to treat non-24-hour sleep-wake disorder (non-24; a condition that occurs mainly in people who are blind in which the body's natural clock is out of sync with the normal day-night cycle and causes a disrupted sleep schedule) in adults. It is also used to treat nighttime sleep problems in adults and children 3 years of age and older with Smith-Magenis Syndrome (SMS; a developmental disorder). Tasimelteon is in a class of medications called melatonin receptor agonists. It works similarly to melatonin, a natural substance in the brain that is needed for sleep.
Read the full MedlinePlus article ↗- It treats Non-24-Hour Sleep-Wake Disorder in adults, a body-clock problem that disrupts sleep. Hetlioz is also used for nighttime sleep problems in Smith-Magenis Syndrome, as capsu...
- Take it about an hour before bedtime, at the same time every night, on an empty stomach. Food, especially a high-fat meal, can make it work less well. Follow your prescriber’s dire...
- If you can’t take it at about the usual time, skip that night’s dose. Take the next dose at your regular time. Don’t double up.
- What happens if I miss a dose of Tasimelteon?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Tasimelteon — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $228.248 | $6,847.44 / 30 capsules |
| Medicaid paysCMS SDUD · 12 mo | $435.85 | $13,075.53 / 30 capsules |
| Medicare drug plans payPart D · Q2 2026 | $560.94 | $16,828.19 / 30 capsules |
Where does this data come from?
- CMS NADAC weekly file · file of Oct 7, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 60505-4665-03 You're viewing this Main listing | 30 CAPSULE in 1 BOTTLE | $228.25 / ea | $6,847.44 | 2024-01-05 | — | Active |
| 60505-4665-09 60505-4665-9 | 90 CAPSULE in 1 BOTTLE | — | — | 2024-01-05 | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 60505-4665-09?
What NDC number is used to bill for this package of Tasimelteon 20 mg Capsule?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tasimelteon 20 mg 00480-4490-56 | Teva | 30 capsules | $228.248 | — | Availability likely | — |
| Tasimelteon 20 mgthis 60505-4665-03 | Apotex | 30 capsules | $228.248 | AB | Availability likely | — |
| Tasimelteon 20 mg 69238-2548-03 | Amneal | 30 capsules | $228.248 | AB | Availability likely | — |
| Hetlioz 20 mg 43068-0220-01 | Vanda | 30 capsules | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Oct 7, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Tasimelteon inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII PN2ZH5LOQY
A synthetic red dye approved by the FDA for use in foods, medicines, and cosmetics. It serves as a colorant to make tablets, capsules, and liquids visually distinctive for product identification.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Apotex Corp. labeler code 60505
- Prasugrel 10 mg Tablet, Film Coated NDC 60505-4643-3
- macitentan 10 mg Tablet, Film Coated NDC 60505-4644-3
- Eslicarbazepine Acetate 200 mg Tablet NDC 60505-4658-3
- Eslicarbazepine Acetate 400 mg Tablet NDC 60505-4659-3
- Eslicarbazepine Acetate 600 mg Tablet NDC 60505-4660-6
- Eslicarbazepine Acetate 800 mg Tablet NDC 60505-4661-3
- Pirfenidone 267 mg Tablet NDC 60505-4681-7
- Pirfenidone 801 mg Tablet NDC 60505-4682-9
- Solifenacin Succinate 5 mg Tablet, Film Coated NDC 60505-4702-3
- Solifenacin Succinate 10 mg Tablet, Film Coated NDC 60505-4703-3
- Brivaracetam 10 mg Tablet NDC 60505-4723-6
- Brivaracetam 25 mg Tablet NDC 60505-4724-6
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Tasimelteon capsules are a melatonin receptor agonist. Tasimelteon capsules are indicated for the treatment of Non 24-Hour Sleep-Wake Disorder (Non-24) in adults ( 1 )
1.1Non-24-Hour Sleep-Wake Disorder (Non-24) Tasimelteon capsules are indicated for the treatment of Non-24 in adults.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Indicated Population Dosage Form Body Weight Recommended Dosage Non-24 ( 2.2 ) Adults Capsules Not applicable 20 mg one hour prior to bedtime Tasimelteon capsules and tasimelteon oral suspension are not substitutable ( 2.1 ) Administer at the same time every night ( 2.2 ) Take without food ( 2.4 )
2.1Non-Interchangeability between Tasimelteon Capsules and Tasimelteon Oral Suspension Tasimelteon capsules and tasimelteon oral suspension are not substitutable [see Clinical Pharmacology ( 12.3 )].
2.2Recommended Dosage for Tasimelteon Capsules for Non-24 Adults The recommended dosage of tasimelteon capsules in adults is 20 mg one hour before bedtime, at the same time every night. Because of individual differences in circadian rhythms, drug effect may not occur for weeks or months.
2.4Important Administration Information Administer tasimelteon capsules without food [see Clinical Pharmacology ( 12.3 )]. If a patient is unable to take tasimelteon capsules at approximately the same time on a given night, they should skip that dose and take the next dose as scheduled.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsules: 20 mg hard gelatin capsule with dark blue, opaque body and dark blue, opaque cap. Imprinted “APO” and “TAS” over “20” in white ink. Capsules: 20 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS May cause somnolence: After taking tasimelteon capsules, patients should limit their activity to preparing for going to bed, because tasimelteon capsules can impair the performance of activities requiring complete mental alertness ( 5.1 )
5.1Somnolence After taking tasimelteon capsules, patients should limit their activity to preparing for going to bed. Tasimelteon capsules can potentially impair the performance of activities requiring complete mental alertness.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reactions (incidence >5% and at least twice as high on tasimelteon than on placebo) were headache, increased alanine aminotransferase, nightmares or unusual dreams, and upper respiratory or urinary tract infection ( 6.1) To report SUSPECTED ADVERSE REACTIONS, contact Apotex Corp. at 1-800-706-5575 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. More than 2080 subjects have been treated with at least one dose of tasimelteon, of which more than 380 have been treated for > 26 weeks and more than 170 have been treated for > 1 year. Non-24-Hour Sleep-Wake Disorder (Non-24) A 26-week, parallel-arm placebo-controlled study (Study 1) evaluated tasimelteon (n=42) compared to placebo (n=42) in patients with Non-24.
A randomized-withdrawal, placebo-controlled study of 8 weeks duration (Study 2) also evaluated tasimelteon (n=10), compared to placebo (n=10), in patients with Non-24. In placebo-controlled studies, 6% of patients exposed to tasimelteon discontinued treatment due to an adverse event, compared with 4% of patients who received placebo. Table 2 shows the incidence of adverse reactions from Study 1.
Table 2: Adverse Reactions in Study 1 Tasimelteon N=42 Placebo N=42 Headache 17 % 7 % Alanine aminotransferase increased 10 % 5 % Nightmare/abnormal dreams 10 % 0 % Upper respiratory tract infection 7 % 0 % Urinary tract infection 7 % 2 % *Adverse reactions with an incidence > 5% and at least twice as high on tasimelteon than on placebo are displayed.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Strong CYP1A2 inhibitors (e.g., fluvoxamine): Avoid use of tasimelteon in combination with strong CYP1A2 inhibitors because of increased exposure ( 7.1 , 12.3 ) Strong CYP3A4 inducers (e.g., rifampin): Avoid use of tasimelteon in combination with rifampin or other CYP3A4 inducers, because of decreased exposure ( 7.2 , 12.3 )
7.1Strong CYP1A2 Inhibitors (e.g., fluvoxamine) Avoid use of tasimelteon in combination with fluvoxamine or other strong CYP1A2 inhibitors because of a potentially large increase in tasimelteon exposure and greater risk of adverse reactions [see Clinical Pharmacology ( 12.3 )].
7.2Strong CYP3A4 Inducers (e.g., rifampin) Avoid use of tasimelteon in combination with rifampin or other CYP3A4 inducers because of a potentially large decrease in tasimelteon exposure with reduced efficacy [see Clinical Pharmacology ( 12.3 )].
7.3Beta-Adrenergic Receptor Antagonists (e.g., acebutolol, metoprolol) Beta-adrenergic receptor antagonists have been shown to reduce the production of melatonin via specific inhibition of beta-1 adrenergic receptors. Nighttime administration of beta-adrenergic receptor antagonists may reduce the efficacy of tasimelteon.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Hepatic impairment: Tasimelteon has not been studied in patients with severe hepatic impairment and is not recommended in these patients ( 8.6 )
8.1Pregnancy Risk Summary Available postmarketing case reports with tasimelteon use in pregnant women are not sufficient to evaluate drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. In pregnant rats, no embryofetal developmental toxicity was observed at exposures of 50 mg/kg/day, or up to 24 times higher than the human exposure at the maximum recommended human dose (MRHD) (see Data). The estimated background risk of major birth defects and miscarriage for the indicated populations are unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data In pregnant rats administered tasimelteon at oral doses of 5, 50, or 500 mg/kg/day during the period of organogenesis, there were no effects on embryofetal development. The highest dose tested is approximately 240 times the MRHD of 20 mg/day, based on mg/m 2 body surface area.
In pregnant rabbits administered tasimelteon at oral doses of 5, 30, or 200 mg/kg/day during the period of organogenesis, embryolethality and embryofetal toxicity (reduced fetal body weight and delayed ossification) were observed at the highest dose tested. The highest dose is approximately 200 times the MRHD. Oral administration of tasimelteon at 50, 150, or 450 mg/kg/day to rats throughout organogenesis resulted in persistent reductions in body weight, delayed sexual maturation, and physical development, and neurobehavioral impairment in offspring at the highest dose tested which is approximately 220 times the MRHD based on mg/m 2 body surface area.
Reduced body weight in offspring was also observed at the mid-dose. The no effect dose (NOEL), (50 mg/kg/day) is approximately 25 times the MRHD based on mg/m 2 body surface area.
8.2Lactation Risk Summary There are no data on the presence of tasimelteon or its metabolites in human or animal milk, the effects on the breastfed infant, or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for tasimelteon and any potential adverse effects on the breastfed infant from tasimelteon or from the underlying maternal condition.
8.4Pediatric Use Safety and effectiveness of tasimelteon capsules for the treatment of Non-24 in pediatric patients have not been established. Juvenile Animal Toxicity Data Juvenile rats received oral doses of tasimelteon at 50, 150, or 450 mg/kg from weaning (day 21) through adulthood (day 90). These doses are approximately 12 to 108 times the maximum recommended human dose (MRHD) of 20 mg based on a mg/m 2 body surface area.
Toxicity was observed mainly at the highest dose and included mortality (females only), tremors, unsteady gait, decrease in growth and development compared to controls. The former reflected as decreases in bone growth, bone mineral content, bone ossification, and a delay in attainment of sexual maturation. Tasimelteon had no effect on fertility, reproduction, or learning and memory.
The No Observed Adverse Effect Level (NOAEL) is 150 mg/kg/day, which is approximately 178 times the MRHD based on AUC.
8.5Geriatric Use The risk of adverse reactions may be greater in elderly (>65 years) patients than younger patients because exposure to tasimelteon is increased by approximately 2-fold compared with younger patients.
8.6Hepatic Impairment Dose adjustment is not necessary in patients with mild or moderate hepatic impairment. Tasimelteon has not been studied in patients with severe hepatic impairment (Child-Pugh Class C). Therefore, tasimelteon is not recommended for use in patients with severe hepatic impairment [see Clinical Pharmacology ( 12.3 )].
8.7Smokers Smoking causes in… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available postmarketing case reports with tasimelteon use in pregnant women are not sufficient to evaluate drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. In pregnant rats, no embryofetal developmental toxicity was observed at exposures of 50 mg/kg/day, or up to 24 times higher than the human exposure at the maximum recommended human dose (MRHD) (see Data). The estimated background risk of major birth defects and miscarriage for the indicated populations are unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data In pregnant rats administered tasimelteon at oral doses of 5, 50, or 500 mg/kg/day during the period of organogenesis, there were no effects on embryofetal development. The highest dose tested is approximately 240 times the MRHD of 20 mg/day, based on mg/m 2 body surface area.
In pregnant rabbits administered tasimelteon at oral doses of 5, 30, or 200 mg/kg/day during the period of organogenesis, embryolethality and embryofetal toxicity (reduced fetal body weight and delayed ossification) were observed at the highest dose tested. The highest dose is approximately 200 times the MRHD. Oral administration of tasimelteon at 50, 150, or 450 mg/kg/day to rats throughout organogenesis resulted in persistent reductions in body weight, delayed sexual maturation, and physical development, and neurobehavioral impairment in offspring at the highest dose tested which is approximately 220 times the MRHD based on mg/m 2 body surface area.
Reduced body weight in offspring was also observed at the mid-dose. The no effect dose (NOEL), (50 mg/kg/day) is approximately 25 times the MRHD based on mg/m 2 body surface area.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of tasimelteon capsules for the treatment of Non-24 in pediatric patients have not been established. Juvenile Animal Toxicity Data Juvenile rats received oral doses of tasimelteon at 50, 150, or 450 mg/kg from weaning (day 21) through adulthood (day 90). These doses are approximately 12 to 108 times the maximum recommended human dose (MRHD) of 20 mg based on a mg/m 2 body surface area.
Toxicity was observed mainly at the highest dose and included mortality (females only), tremors, unsteady gait, decrease in growth and development compared to controls. The former reflected as decreases in bone growth, bone mineral content, bone ossification, and a delay in attainment of sexual maturation. Tasimelteon had no effect on fertility, reproduction, or learning and memory.
The No Observed Adverse Effect Level (NOAEL) is 150 mg/kg/day, which is approximately 178 times the MRHD based on AUC.
🧓 Geriatric Use ▾
8.5Geriatric Use The risk of adverse reactions may be greater in elderly (>65 years) patients than younger patients because exposure to tasimelteon is increased by approximately 2-fold compared with younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE There is limited premarketing clinical experience with the effects of an overdosage of tasimelteon. As with the management of any overdose, general symptomatic and supportive measures should be used, along with immediate gastric lavage where appropriate. Intravenous fluids should be administered as needed.
Respiration, pulse, blood pressure, and other appropriate vital signs should be monitored, and general supportive measures employed. While hemodialysis was effective at clearing tasimelteon and the majority of its major metabolites in patients with renal impairment, it is not known if hemodialysis will effectively reduce exposure in the case of overdose. As with the management of any overdose, the possibility of multiple drug ingestion should be considered.
Contact a poison control center for current information on the management of overdose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism by which tasimelteon exerts its therapeutic effect in patients with Non-24 is unclear. However, tasimelteon is an agonist at melatonin MT 1 and MT 2 receptors which are thought to be involved in the control of circadian rhythms.
12.2Pharmacodynamics Tasimelteon is an agonist at MT 1 and MT 2 receptors with greater affinity for the MT 2 as compared to the MT 1 receptor (Ki = 0.304 nM and 0.07 nM, respectively). The major metabolites of tasimelteon have less than one-tenth of the binding affinity of the parent molecule for both the MT 1 and MT 2 receptors.
12.3Pharmacokinetics The pharmacokinetics of tasimelteon is linear over doses ranging from 3 to 300 mg (0.15 to 15 times the recommended daily dosage). The pharmacokinetics of tasimelteon and its metabolites did not change with repeated daily dosing. Absorption The absolute oral bioavailability is 38.3%.
The peak concentration (T max ) of tasimelteon capsule occurred approximately 0.5 to 3 hours after fasted oral administration. Effect of food When administered with a high-fat meal, the C max of tasimelteon was 44% lower than when given in a fasted state, and the median T max was delayed by approximately 1.75 hours. Therefore, tasimelteon capsules should be taken without food.
Distribution The apparent oral volume of distribution of tasimelteon at steady state in young healthy subjects is approximately 59 to 126 L. At therapeutic concentrations, tasimelteon is about 90% bound to proteins. Metabolism Tasimelteon is extensively metabolized.
Metabolism of tasimelteon consists primarily of oxidation at multiple sites and oxidative dealkylation resulting in opening of the dihydrofuran ring followed by further oxidation to give a carboxylic acid. CYP1A2 and CYP3A4 are the major isozymes involved in the metabolism of tasimelteon. Phenolic glucuronidation is the major phase II metabolic route.
Major metabolites had 13-fold or less activity at melatonin receptors compared to tasimelteon. Elimination Following oral administration of radiolabeled tasimelteon, 80% of total radioactivity was excreted in urine and approximately 4% in feces, resulting in a mean recovery of 84%. Less than 1% of the dose was excreted in urine as the parent compound.
The observed mean elimination half-life for tasimelteon is 1.3 ± 0.4 hours. The mean terminal elimination half-life ± standard deviation of the main metabolites ranges from 1.3 ± 0.5 to 3.7 ± 2.2. Repeated once daily dosing with tasimelteon does not result in changes in pharmacokinetic parameters or significant accumulation of tasimelteon.
Studies in Specific Populations Elderly In elderly subjects, tasimelteon exposure increased by approximately two-fold compared with non-elderly adults. Gender The mean overall exposure of tasimelteon was approximately 20 to 30% greater in female than in male subjects. Race The effect of race on exposure of tasimelteon was not evaluated.
Hepatic Impairment The pharmacokinetic profile of a 20 mg dose of tasimelteon was compared among eight subjects with mild hepatic impairment (Child-Pugh Score ≥5 and ≤6 points), eight subjects with moderate hepatic impairment (Child-Pugh Score ≥7 and ≤9 points), and 13 healthy matched controls. Tasimelteon exposure was increased less than two-fold in subjects with moderate hepatic impairment. Therefore, no dose adjustment is needed in patients with mild or moderate hepatic impairment.
Tasimelteon has not been studied in patients with severe hepatic impairment (Child-Pugh Class C) and is not recommended in these patients. Renal Impairment The pharmacokinetic profile of a 20 mg dose of tasimelteon was compared among eight subjects with severe renal impairment (estimated glomerular filtration rate [eGFR] ≤ 29 mL/min/1.73m 2 ), eight subjects with end-stage renal disease (ESRD) (GFR < 15 mL/min/1.73m 2 ) requiring hemodialysis, and sixteen healthy matched controls. There was no apparent relationship between tasimelteon… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism by which tasimelteon exerts its therapeutic effect in patients with Non-24 is unclear. However, tasimelteon is an agonist at melatonin MT 1 and MT 2 receptors which are thought to be involved in the control of circadian rhythms.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Tasimelteon 20 mg capsules are available as hard gelatin capsules with dark blue, opaque body and dark blue, opaque cap. Imprinted “APO” and “TAS” over “20” in white ink. Bottles of 30 NDC 60505-4665-3 Bottles of 90 NDC 60505-4665-9 Storage and Handling Store tasimelteon capsules at 20°C to 25°C (68°F to 77°F); excursions permitted from 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Protect from exposure to light and moisture.
📋 Description ▾
11 DESCRIPTION Tasimelteon is a melatonin receptor agonist, chemically designated as (1 R-trans )- N -[[2-(2,3-Dihydrobenzofuran-4-yl)cycloprop-1-yl]methyl]propanamide, containing two chiral centers. The molecular formula is C 15 H 19 NO 2 , and the molecular weight is 245.32 g/mol. The structural formula is: Tasimelteon is a white to off-white powder.
It is very slightly soluble in cyclohexane, slightly soluble in water and freely soluble or very soluble in methanol, 95% ethanol, acetonitrile, isopropanol, propylene glycol and ethyl acetate. Tasimelteon capsules are intended for oral administration. Each capsule contains 20 mg of tasimelteon and the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, magnesium stearate, and microcrystalline cellulose.
Each hard gelatin capsule consists of FD&C Blue #1, FD&C Red #3, and FD&C Yellow #6, gelatin and titanium dioxide. The imprinting ink consists of povidone, propylene glycol, shellac, sodium hydroxide and titanium dioxide.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients to limit their activities to preparing for going to bed after taking tasimelteon capsules because tasimelteon can potentially impair the performance of activities requiring complete mental alertness [see Warnings and Precautions ( 5.1 )] . Administration Information for tasimelteon capsules [see Dosage and Administration ( 2.1 , 2.2 , 2.4 )] . Advise patients to take tasimelteon capsules without food.
Advise patients to take tasimelteon capsules before bedtime at the same time every night. Advise patients to skip the dose that night if they cannot take tasimelteon capsules at approximately the same time on a given night. Advise patients to swallow tasimelteon capsules whole.
Non-24 (tasimelteon capsules) Advise patients that because of individual differences in circadian rhythms, daily use for several weeks or months may be necessary before benefit from tasimelteon capsules is observed [see Dosage and Administration ( 2.2 )] . APOTEX INC. TASIMELTEON CAPSULES 20 mg Manufactured By Apotex Inc.
Toronto, Ontario Canada M9L 1T9 Manufactured For Apotex Corp. Weston, Florida USA 33326 Rev. 5
🍼 Nursing Mothers ▾
8.2Lactation Risk Summary There are no data on the presence of tasimelteon or its metabolites in human or animal milk, the effects on the breastfed infant, or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for tasimelteon and any potential adverse effects on the breastfed infant from tasimelteon or from the underlying maternal condition.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of tasimelteon is linear over doses ranging from 3 to 300 mg (0.15 to 15 times the recommended daily dosage). The pharmacokinetics of tasimelteon and its metabolites did not change with repeated daily dosing. Absorption The absolute oral bioavailability is 38.3%.
The peak concentration (T max ) of tasimelteon capsule occurred approximately 0.5 to 3 hours after fasted oral administration. Effect of food When administered with a high-fat meal, the C max of tasimelteon was 44% lower than when given in a fasted state, and the median T max was delayed by approximately 1.75 hours. Therefore, tasimelteon capsules should be taken without food.
Distribution The apparent oral volume of distribution of tasimelteon at steady state in young healthy subjects is approximately 59 to 126 L. At therapeutic concentrations, tasimelteon is about 90% bound to proteins. Metabolism Tasimelteon is extensively metabolized.
Metabolism of tasimelteon consists primarily of oxidation at multiple sites and oxidative dealkylation resulting in opening of the dihydrofuran ring followed by further oxidation to give a carboxylic acid. CYP1A2 and CYP3A4 are the major isozymes involved in the metabolism of tasimelteon. Phenolic glucuronidation is the major phase II metabolic route.
Major metabolites had 13-fold or less activity at melatonin receptors compared to tasimelteon. Elimination Following oral administration of radiolabeled tasimelteon, 80% of total radioactivity was excreted in urine and approximately 4% in feces, resulting in a mean recovery of 84%. Less than 1% of the dose was excreted in urine as the parent compound.
The observed mean elimination half-life for tasimelteon is 1.3 ± 0.4 hours. The mean terminal elimination half-life ± standard deviation of the main metabolites ranges from 1.3 ± 0.5 to 3.7 ± 2.2. Repeated once daily dosing with tasimelteon does not result in changes in pharmacokinetic parameters or significant accumulation of tasimelteon.
Studies in Specific Populations Elderly In elderly subjects, tasimelteon exposure increased by approximately two-fold compared with non-elderly adults. Gender The mean overall exposure of tasimelteon was approximately 20 to 30% greater in female than in male subjects. Race The effect of race on exposure of tasimelteon was not evaluated.
Hepatic Impairment The pharmacokinetic profile of a 20 mg dose of tasimelteon was compared among eight subjects with mild hepatic impairment (Child-Pugh Score ≥5 and ≤6 points), eight subjects with moderate hepatic impairment (Child-Pugh Score ≥7 and ≤9 points), and 13 healthy matched controls. Tasimelteon exposure was increased less than two-fold in subjects with moderate hepatic impairment. Therefore, no dose adjustment is needed in patients with mild or moderate hepatic impairment.
Tasimelteon has not been studied in patients with severe hepatic impairment (Child-Pugh Class C) and is not recommended in these patients. Renal Impairment The pharmacokinetic profile of a 20 mg dose of tasimelteon was compared among eight subjects with severe renal impairment (estimated glomerular filtration rate [eGFR] ≤ 29 mL/min/1.73m 2 ), eight subjects with end-stage renal disease (ESRD) (GFR < 15 mL/min/1.73m 2 ) requiring hemodialysis, and sixteen healthy matched controls. There was no apparent relationship between tasimelteon CL/F and renal function, as measured by either estimated creatinine clearance or eGFR.
Subjects with severe renal impairment had a 30% lower clearance, and clearance in subjects with ESRD was comparable to that of healthy subjects. No dose adjustment is necessary for patients with renal impairment. Smokers (smoking is a moderate CYP1A2 inducer) Tasimelteon exposure decreased by approximately 40% in smokers, compared to non-smokers [see Use in Specific Populations ( 8.7 )] .
Drug Interaction Studies No potential drug interactions were identified in in vitro studies with CYP inducers or inhibitors of CYP1A1, CYP1A2, CYP2… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Tasimelteon is an agonist at MT 1 and MT 2 receptors with greater affinity for the MT 2 as compared to the MT 1 receptor (Ki = 0.304 nM and 0.07 nM, respectively). The major metabolites of tasimelteon have less than one-tenth of the binding affinity of the parent molecule for both the MT 1 and MT 2 receptors.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Non-24-Hour Sleep-Wake Disorder (Non-24) The effectiveness of tasimelteon in the treatment of Non-24-Hour Sleep-Wake Disorder (Non-24) was established in two randomized double-masked, placebo-controlled, multicenter, parallel-group studies (Studies 1 and 2) in totally blind patients with Non-24. In study 1, 84 patients with Non-24 (median age 54 years) were randomized to receive tasimelteon capsules 20 mg or placebo, one hour prior to bedtime, at the same time every night for up to 6 months. Study 2 was a randomized withdrawal trial in 20 patients with Non-24 (median age 55 years) that was designed to evaluate the maintenance of efficacy of tasimelteon after 12-weeks.
Patients were treated for approximately 12 weeks with tasimelteon capsules 20 mg one hour prior to bedtime, at the same time every night. Patients in whom the calculated time of peak melatonin level (melatonin acrophase) occurred at approximately the same time of day (in contrast to the expected daily delay) during the run-in phase were randomized to receive placebo or continue treatment with tasimelteon capsules 20 mg for 8 weeks. Study 1 and Study 2 evaluated the duration and timing of nighttime sleep and daytime naps via patient-recorded diaries.
During Study 1, patient diaries were recorded for an average of 88 days during screening, and 133 days during randomization. During Study 2, patient diaries were recorded for an average of 57 days during the run-in phase, and 59 days during the randomized-withdrawal phase. Because symptoms of nighttime sleep disruption and daytime sleepiness are cyclical in patients with Non-24, with severity varying according to the state of alignment of the individual patient’s circadian rhythm with the 24-hour day (least severe when fully aligned, most severe when 12 hours out of alignment), efficacy endpoints for nighttime total sleep time and daytime nap duration were based on the 25% of nights with the least nighttime sleep, and the 25% of days with the most daytime nap time.
In Study 1, patients in the tasimelteon group had, at baseline, an average 195 minutes of nighttime sleep and 137 minutes of daytime nap time on the 25% of most symptomatic nights and days, respectively. Treatment with tasimelteon resulted in a significant improvement, compared with placebo, for both of these endpoints in Study 1 and Study 2 (see Table 3). Table 3: Effects of Tasimelteon Capsules 20 mg on Nighttime Sleep Time and Daytime Nap Time in Study 1 and Study 2 Study 1 Study 2 Change from Baseline Tasimelteon Capsules 20 MG N=42 Placebo N=42 Tasimelteon Capsules 20 MG N=10 Placebo N=10 Nighttime sleep time on 25% most symptomatic nights (minutes) 50 22 -7 -74 Daytime nap time on 25% most symptomatic days (minutes) -49 -22 -9 50 A responder analysis of patients with both ≥ 45 minutes increase in nighttime sleep and ≥ 45 minutes decrease in daytime nap time was conducted in Study 1: 29% (n=12) of patients treated with tasimelteon, compared with 12% (n=5) of patients treated with placebo met the responder criteria.
14.1Non-24-Hour Sleep-Wake Disorder (Non-24) The effectiveness of tasimelteon in the treatment of Non-24-Hour Sleep-Wake Disorder (Non-24) was established in two randomized double-masked, placebo-controlled, multicenter, parallel-group studies (Studies 1 and 2) in totally blind patients with Non-24. In study 1, 84 patients with Non-24 (median age 54 years) were randomized to receive tasimelteon capsules 20 mg or placebo, one hour prior to bedtime, at the same time every night for up to 6 months. Study 2 was a randomized withdrawal trial in 20 patients with Non-24 (median age 55 years) that was designed to evaluate the maintenance of efficacy of tasimelteon after 12-weeks.
Patients were treated for approximately 12 weeks with tasimelteon capsules 20 mg one hour prior to bedtime, at the same time every night. Patients in whom the calculated time of peak melatonin level (melatonin acrophase) occurred at approximately… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance Tasimelteon is not a controlled substance under the Controlled Substances Act.
9.2Abuse Tasimelteon did not produce any abuse-related signals in animal behavioral studies. Rats did not self-administer tasimelteon, suggesting that the drug does not have rewarding properties. There were also no signs or symptoms indicative of abuse potential in clinical studies with tasimelteon.
9.3Dependence Discontinuation of tasimelteon in humans following chronic administration did not produce withdrawal signs. Tasimelteon does not appear to produce physical dependence.
🔒 Controlled Substance ▾
9.1Controlled Substance Tasimelteon is not a controlled substance under the Controlled Substances Act.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Tasimelteon was administered orally for up to two years to mice (30, 100, and 300 mg/kg/day) and rats (20, 100, and 250 mg/kg/day). No evidence of carcinogenic potential was observed in mice; the highest dose tested is approximately 75 times the maximum recommended human dose (MRHD) of 20 mg/day, based on a mg/m 2 body surface area. In rats, the incidence of liver tumors was increased in males (adenoma and carcinoma) and females (adenoma) at 100 and 250 mg/kg/day; the incidence of tumors of the uterus (endometrial adenocarcinoma) and uterus and cervix (squamous cell carcinoma) were increased at 250 mg/kg/day.
There was no increase in tumors at the lowest dose tested in rats, which is approximately 10 times the MRHD based on a mg/m 2 body surface area. Mutagenesis Tasimelteon was negative in an in vitro bacterial reverse mutation (Ames) assay, an in vitro cytogenetics assay in primary human lymphocytes, and an in vivo micronucleus assay in rats. Impairment of Fertility When male and female rats were given tasimelteon at oral doses of 5, 50, or 500 mg/kg/day prior to and throughout mating and continuing in females to gestation day 7, estrus cycle disruption and decreased fertility were observed at all but the lowest dose tested.
The no-effect dose for effects on female reproduction (5 mg/kg/day) is approximately 2 times the MRHD based on a mg/m 2 body surface area.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Tasimelteon was administered orally for up to two years to mice (30, 100, and 300 mg/kg/day) and rats (20, 100, and 250 mg/kg/day). No evidence of carcinogenic potential was observed in mice; the highest dose tested is approximately 75 times the maximum recommended human dose (MRHD) of 20 mg/day, based on a mg/m 2 body surface area. In rats, the incidence of liver tumors was increased in males (adenoma and carcinoma) and females (adenoma) at 100 and 250 mg/kg/day; the incidence of tumors of the uterus (endometrial adenocarcinoma) and uterus and cervix (squamous cell carcinoma) were increased at 250 mg/kg/day.
There was no increase in tumors at the lowest dose tested in rats, which is approximately 10 times the MRHD based on a mg/m 2 body surface area. Mutagenesis Tasimelteon was negative in an in vitro bacterial reverse mutation (Ames) assay, an in vitro cytogenetics assay in primary human lymphocytes, and an in vivo micronucleus assay in rats. Impairment of Fertility When male and female rats were given tasimelteon at oral doses of 5, 50, or 500 mg/kg/day prior to and throughout mating and continuing in females to gestation day 7, estrus cycle disruption and decreased fertility were observed at all but the lowest dose tested.
The no-effect dose for effects on female reproduction (5 mg/kg/day) is approximately 2 times the MRHD based on a mg/m 2 body surface area.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL 20 mg 30s Representative sample of labeling (see HOW SUPPLIED section of complete listing): APOTEX CORP. NDC 60505-4665-3 Tasimelteon Capsules 20 mg 30 counts Rx only