
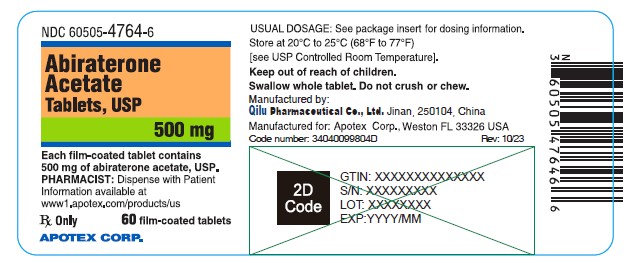
abiraterone acetate 500 mg Tablet, Film Coated, 60-count — NDC 60505-4764-6 (Billing 60505-4764-06) · Product 60505-4764
NDC 60505-4764-6 (billing 60505-4764-06) is a package of 60 tablets of abiraterone acetate 500 mg Tablet, Film Coated from Apotex Corp., marketed since Jul 2021 and currently FDA-listed; retail pharmacies pay about $2.59 per tablet (NADAC). It is the main listing for product NDC 60505-4764, its only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 077249
- GCN: 43205
- GPI-14 (Medi-Span): 21406010200330
- HICL (First Databank): 037571
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 1918042
- 11-digit billing NDC: 60505476406
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Sep 24, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Cytochrome P450 17A1 Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Sep 24, 2026
Clinical
- It treats prostate cancer that has spread. Abiraterone acetate tablets, Abirtega and Zytiga are used for metastatic castration-resistant and metastatic high-risk castration-sensiti...
- Take it once a day and swallow the tablets whole with water. With abiraterone acetate tablets, Abirtega or Zytiga, don't eat for 2 hours before or 1 hour after your dose, because f...
- How should I take it, and does food matter?
- Abiraterone can cause a hormone imbalance, leading to high blood pressure, low potassium and fluid retention. The steroid is part of your treatment. Don't skip it or stop suddenly,...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Abiraterone Acetate — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $2.594 | $155.66 / 60 tablets |
| Medicaid paysCMS SDUD · 12 mo | $10.72 | $642.99 / 60 tablets |
| Medicare drug plans payPart D · Q2 2026 | $10.71 | $642.84 / 60 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 60505-4764-06 60505-4764-6 You're viewing this Main listing | 60 TABLET, FILM COATED in 1 BOTTLE (60505-4764-6) | 2021-07-16 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Abiraterone Acetate 500 mg 00378-6921-91 | Mylan | 60 tablets | $2.594 | AB | Availability likely | — |
| Abiraterone Acetate 500 mg 60219-1754-06 | Amneal | 60 tablets | $2.594 | AB | Availability likely | — |
| abiraterone acetate 500 mgthis 60505-4764-06 | Apotex | 60 tablets | $2.594 | AB | Availability likely | — |
| Abiraterone 500 mg 68001-0673-06 | BluePoint | 60 tablets | $2.594 | AB | Availability likely | — |
| abiraterone acetate 500 mg 68462-0882-60 | Glenmark | 60 tablets | $2.594 | AB | Availability likely | — |
| Abiraterone Acetate 500 mg 69238-1754-06 | Amneal | 60 tablets | $2.594 | AB | Availability likely | — |
| Abiraterone acetate 500 mg 71921-0177-06 | Florida | 60 tablets | $2.594 | AB | Availability likely | — |
| abiraterone acetate 500 mg 72603-0111-01 | NORTHSTAR | 60 tablets | $2.594 | AB | Availability likely | — |
| Abiraterone 500 mg 82009-0140-60 | Quallent | 60 tablets | $2.594 | AB | Availability likely | — |
| Abiraterone Acetate 500 mg 82293-0002-10 | Novugen | 60 tablets | $2.594 | AB | Availability likely | — |
| Abiraterone Acetate 500 mg 43598-0468-38 | Dr. | 60 tablets | — | AB | FDA listed | — |
| Zytiga 500 mg 57894-0195-06 | Janssen | 60 tablets | — | AB | FDA listed | — |
| Abiraterone Acetate 500 mg 72162-2151-06 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Abiraterone 500 mg 72205-0285-05 | Novadoz | 500 tablets | — | AB | FDA listed | — |
| Abiraterone Acetate 500 mg 51407-0989-60 | Golden | 60 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 36SFW2JZ0W
Hypromellose 2910 is a plant-based thickening agent derived from cellulose. In medicines, it forms a protective coating on tablets or capsules and controls how quickly the drug dissolves and releases into your body.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
14 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Abiraterone acetate is indicated in combination with prednisone for the treatment of patients with Metastatic castration-resistant prostate cancer (CRPC) Metastatic high-risk castration-sensitive prostate cancer (CSPC) Abiraterone acetate is a CYP17 inhibitor indicated in combination with prednisone for the treatment of patients with metastatic castration-resistant prostate cancer (CRPC). ( 1 ) metastatic high-risk castration-sensitive prostate cancer (CSPC). ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Metastatic castration-resistant prostate cancer: Abiraterone acetate 1,000 mg orally once daily with prednisone 5 mg orally twice daily. ( 2.1 ) Metastatic castration-sensitive prostate cancer: Abiraterone acetate 1,000 mg orally once daily with prednisone 5 mg orally once daily. ( 2.2 ) Patients receiving abiraterone acetate should also receive a gonadotropin-releasing hormone (GnRH) analog concurrently or should have had bilateral orchiectomy.
Abiraterone acetate tablets must be taken as a single dose once daily on an empty stomach. Do not eat food 2 hours before and 1 hour after taking abiraterone acetate. The tablets must be swallowed whole with water.
Do not crush or chew tablets. ( 2.3 ) Dose Modification: For patients with baseline moderate hepatic impairment (Child-Pugh Class B), reduce the abiraterone acetate starting dose to 250 mg once daily. ( 2.4 ) For patients who develop hepatotoxicity during treatment, hold abiraterone acetate until recovery.
Retreatment may be initiated at a reduced dose. Abiraterone acetate should be discontinued if patients develop severe hepatotoxicity. ( 2.4 )
2.1Recommended Dose for Metastatic CRPC The recommended dose of abiraterone acetate is 1,000 mg (two 500 mg tablets or four 250 mg tablets) orally once daily with prednisone 5 mg orally twice daily.
2.2Recommended Dose for Metastatic High-risk CSPC The recommended dose of abiraterone acetate is 1,000 mg (two 500 mg tablets or four 250 mg tablets) orally once daily with prednisone 5 mg administered orally once daily.
2.3Important Administration Instructions Patients receiving abiraterone acetate should also receive a gonadotropin-releasing hormone (GnRH) analog concurrently or should have had bilateral orchiectomy. Abiraterone acetate tablets must be taken as a single dose once daily on an empty stomach. Do not eat food 2 hours before and 1 hour after taking abiraterone acetate. The tablets must be swallowed whole with water. Do not crush or chew tablets.
2.4Dose Modification Guidelines in Hepatic Impairment and Hepatotoxicity Hepatic Impairment In patients with baseline moderate hepatic impairment (Child-Pugh Class B), reduce the recommended dose of abiraterone acetate to 250 mg once daily. In patients with moderate hepatic impairment monitor ALT, AST, and bilirubin prior to the start of treatment, every week for the first month, every two weeks for the following two months of treatment and monthly thereafter. If elevations in ALT and/or AST greater than 5 × upper limit of normal (ULN) or total bilirubin greater than 3 × ULN occur in patients with baseline moderate hepatic impairment, discontinue abiraterone acetate and do not re-treat patients with abiraterone acetate [see Use in Specific Populations (8.6) and Clinical Pharmacology (12.3) ] .
Do not use abiraterone acetate in patients with baseline severe hepatic impairment (Child-Pugh Class C). Hepatotoxicity For patients who develop hepatotoxicity during treatment with abiraterone acetate (ALT and/or AST greater than 5 × ULN or total bilirubin greater than 3 × ULN), interrupt treatment with abiraterone acetate [see Warnings and Precautions (5.3) ]. Treatment may be restarted at a reduced dose of 750 mg once daily following return of liver function tests to the patient's baseline or to AST and ALT less than or equal to 2.5 × ULN and total bilirubin less than or equal to 1.5 × ULN .
For patients who resume treatment, monitor serum transaminases and bilirubin at a minimum of every two weeks for three months and monthly thereafter. If hepatotoxicity recurs at the dose of 750 mg once daily, re-treatment may be restarted at a reduced dose of 500 mg once daily following return of liver function tests to the patient's baseline or to AST and ALT less than or equal to 2.5 × ULN and total bilirubin less than or equal to 1.5 × ULN . If hepatotoxicity recurs at the reduced dose of 500 mg once daily, discontinue treatment with abiraterone acetate.
Permanently dis… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets (500 mg): light purple, oval-shaped, film-coated tablets debossed with "125" on one side. Film-Coated Tablet 500 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Mineralocorticoid excess: Closely monitor patients with cardiovascular disease. Control hypertension and correct hypokalemia before treatment. Monitor blood pressure, serum potassium and symptoms of fluid retention at least monthly.
( 5.1 ) Adrenocortical insufficiency: Monitor for symptoms and signs of adrenocortical insufficiency. Increased dosage of corticosteroids may be indicated before, during and after stressful situations. ( 5.2 ) Hepatotoxicity: Can be severe and fatal.
Monitor liver function and modify, interrupt, or discontinue abiraterone acetate dosing as recommended. ( 5.3 ) Increased fractures and mortality in combination with radium Ra 223 dichloride: Use of abiraterone acetate plus prednisone/prednisolone in combination with radium Ra 223 dichloride is not recommended. ( 5.4 ) Embryo-Fetal Toxicity: Abiraterone acetate can cause fetal harm.
Advise males with female partners of reproductive potential to use effective contraception. ( 5.5 , 8.1 , 8.3 ) Hypoglycemia: Severe hypoglycemia has been reported in patients with pre-existing diabetes who are taking medications containing thiazolidinediones (including pioglitazone) or repaglinide. Monitor blood glucose in patients with diabetes and assess if antidiabetic agent dose modifications are required.
( 5.6 )
5.1Hypokalemia, Fluid Retention, and Cardiovascular Adverse Reactions due to Mineralocorticoid Excess Abiraterone acetate may cause hypertension, hypokalemia, and fluid retention as a consequence of increased mineralocorticoid levels resulting from CYP17 inhibition [see Clinical Pharmacology (12.1) ] . Monitor patients for hypertension, hypokalemia, and fluid retention at least once a month. Control hypertension and correct hypokalemia before and during treatment with abiraterone acetate.
In the combined data from 4 placebo-controlled trials using prednisone 5 mg twice daily in combination with 1,000 mg abiraterone acetate daily, grades 3–4 hypokalemia were detected in 4% of patients on the abiraterone acetate arm and 2% of patients on the placebo arm. Grades 3–4 hypertension were observed in 2% of patients each arm and grades 3–4 fluid retention in 1% of patients each arm. In LATITUDE (a randomized placebo-controlled, multicenter clinical trial), which used prednisone 5 mg daily in combination with 1,000 mg abiraterone acetate daily, grades 3–4 hypokalemia were detected in 10% of patients on the abiraterone acetate arm and 1% of patients on the placebo arm, grades 3–4 hypertension were observed in 20% of patients on the abiraterone acetate arm and 10% of patients on the placebo arm.
Grades 3–4 fluid retention occurred in 1% of patients each arm [see Adverse Reactions (6) ] . Closely monitor patients whose underlying medical conditions might be compromised by increases in blood pressure, hypokalemia or fluid retention, such as those with heart failure, recent myocardial infarction, cardiovascular disease, or ventricular arrhythmia. In postmarketing experience, QT prolongation and Torsades de Pointes have been observed in patients who develop hypokalemia while taking abiraterone acetate.
The safety of abiraterone acetate in patients with left ventricular ejection fraction <50% or New York Heart Association (NYHA) Class III or IV heart failure (in COU-AA-301) or NYHA Class II to IV heart failure (in COU-AA-302 and LATITUDE) has not been established because these patients were excluded from these randomized clinical trials [see Clinical Studies (14) ] .
5.2Adrenocortical Insufficiency Adrenal insufficiency occurred in 0.3% of 2230 patients taking abiraterone acetate and in 0.1% of 1763 patients taking placebo in the combined data of the 5 randomized, placebo-controlled clinical studies. Adrenocortical insufficiency was reported in patients receiving abiraterone acetate in combination with prednisone, following interruption of daily steroids and/or with concurrent infection or stress. Monitor patients for symptoms and signs of adrenoc… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following are discussed in more detail in other sections of the labeling: Hypokalemia, Fluid Retention, and Cardiovascular Adverse Reactions due to Mineralocorticoid Excess [see Warnings and Precautions (5.1) ] . Adrenocortical Insufficiency [see Warnings and Precautions (5.2) ] . Hepatotoxicity [see Warnings and Precautions (5.3) ] .
Increased Fractures and Mortality in Combination with Radium Ra 223 Dichloride [see Warnings and Precautions (5.4) ]. The most common adverse reactions (≥10%) are fatigue, arthralgia, hypertension, nausea, edema, hypokalemia, hot flush, diarrhea, vomiting, upper respiratory infection, cough, and headache. ( 6.1 ) The most common laboratory abnormalities (>20%) are anemia, elevated alkaline phosphatase, hypertriglyceridemia, lymphopenia, hypercholesterolemia, hyperglycemia, and hypokalemia.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Apotex Corp. at 1-800-706-5575 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Two randomized placebo-controlled, multicenter clinical trials (COU-AA-301 and COU-AA-302) enrolled patients who had metastatic CRPC in which abiraterone acetate was administered orally at a dose of 1,000 mg daily in combination with prednisone 5 mg twice daily in the active treatment arms.
Placebo plus prednisone 5 mg twice daily was given to patients on the control arm. A third randomized placebo-controlled, multicenter clinical trial (LATITUDE) enrolled patients who had metastatic high-risk CSPC in which abiraterone acetate was administered at a dose of 1,000 mg daily in combination with prednisone 5 mg once daily. Placebos were administered to patients in the control arm.
Additionally, two other randomized, placebo-controlled trials were conducted in patients with metastatic CRPC. The safety data pooled from 2230 patients in the 5 randomized controlled trials constitute the basis for the data presented in the Warnings and Precautions, Grade 1–4 adverse reactions, and Grade 1–4 laboratory abnormalities. In all trials, a gonadotropin-releasing hormone (GnRH) analog or prior orchiectomy was required in both arms.
In the pooled data, median treatment duration was 11 months (0.1, 43) for abiraterone acetate-treated patients and 7.2 months (0.1, 43) for placebo-treated patients. The most common adverse reactions (≥10%) that occurred more commonly (>2%) in the abiraterone acetate arm were fatigue, arthralgia, hypertension, nausea, edema, hypokalemia, hot flush, diarrhea, vomiting, upper respiratory infection, cough, and headache. The most common laboratory abnormalities (>20%) that occurred more commonly (≥2%) in the abiraterone acetate arm were anemia, elevated alkaline phosphatase, hypertriglyceridemia, lymphopenia, hypercholesterolemia, hyperglycemia, and hypokalemia.
Grades 3–4 adverse events were reported for 53% of patients in the abiraterone acetate arm and 46% of patients in the placebo arm. Treatment discontinuation was reported in 14% of patients in the abiraterone acetate arm and 13% of patients in the placebo arm. The common adverse events (≥1%) resulting in discontinuation of abiraterone acetate and prednisone were hepatotoxicity and cardiac disorders.
Deaths associated with treatment-emergent adverse events were reported for 7.5% of patients in the abiraterone acetate arm and 6.6% of patients in the placebo arm. Of the patients in the abiraterone acetate arm, the most common cause of death was disease progression (3.3%). Other reported causes of death in ≥5 patients included pneumonia, cardio-respiratory arrest, death (no additional information), and general physical health deterioration.
COU-AA-301: Metastatic CRPC Following Chemotherapy COU-AA-… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS CYP3A4 Inducers: Avoid concomitant strong CYP3A4 inducers during abiraterone acetate treatment. If a strong CYP3A4 inducer must be co-administered, increase the abiraterone acetate dosing frequency. ( 2.5 , 7.1 ) CYP2D6 Substrates: Avoid co-administration of abiraterone acetate with CYP2D6 substrates that have a narrow therapeutic index.
If an alternative treatment cannot be used, exercise caution and consider a dose reduction of the concomitant CYP2D6 substrate. ( 7.2 )
7.1Drugs that Inhibit or Induce CYP3A4 Enzymes Based on in vitro data, abiraterone acetate is a substrate of CYP3A4. In a dedicated drug interaction trial, co-administration of rifampin, a strong CYP3A4 inducer, decreased exposure of abiraterone by 55%. Avoid concomitant strong CYP3A4 inducers during abiraterone acetate treatment.
If a strong CYP3A4 inducer must be co-administered, increase the abiraterone acetate dosing frequency [see Dosage and Administration (2.5) and Clinical Pharmacology (12.3) ] . In a dedicated drug interaction trial, co-administration of ketoconazole, a strong inhibitor of CYP3A4, had no clinically meaningful effect on the pharmacokinetics of abiraterone [see Clinical Pharmacology (12.3) ] .
7.2Effects of Abiraterone on Drug Metabolizing Enzymes Abiraterone acetate is an inhibitor of the hepatic drug-metabolizing enzymes CYP2D6 and CYP2C8. In a CYP2D6 drug-drug interaction trial, the C max and AUC of dextromethorphan (CYP2D6 substrate) were increased 2.8- and 2.9-fold, respectively, when dextromethorphan was given with abiraterone acetate 1,000 mg daily and prednisone 5 mg twice daily. Avoid co-administration of abiraterone acetate with substrates of CYP2D6 with a narrow therapeutic index (e.g., thioridazine).
If alternative treatments cannot be used, consider a dose reduction of the concomitant CYP2D6 substrate drug [see Clinical Pharmacology (12.3) ] . In a CYP2C8 drug-drug interaction trial in healthy subjects, the AUC of pioglitazone (CYP2C8 substrate) was increased by 46% when pioglitazone was given together with a single dose of 1,000 mg abiraterone acetate. Therefore, patients should be monitored closely for signs of toxicity related to a CYP2C8 substrate with a narrow therapeutic index if used concomitantly with abiraterone acetate [see Clinical Pharmacology (12.3) and Warnings and Precautions (5.6) ] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Do not use abiraterone acetate in patients with baseline severe hepatic impairment (Child-Pugh Class C). ( 8.6 )
8.1Pregnancy Risk Summary The safety and efficacy of abiraterone acetate have not been established in females. Based on findings from animal studies and the mechanism of action, abiraterone acetate can cause fetal harm and potential loss of pregnancy. There are no human data on the use of abiraterone acetate in pregnant women.
In animal reproduction studies, oral administration of abiraterone acetate to pregnant rats during organogenesis caused adverse developmental effects at maternal exposures approximately ≥ 0.03 times the human exposure (AUC) at the recommended dose (see Data ). Data Animal Data In an embryo-fetal developmental toxicity study in rats, abiraterone acetate caused developmental toxicity when administered at oral doses of 10, 30 or 100 mg/kg/day throughout the period of organogenesis (gestational days 6–17). Findings included embryo-fetal lethality (increased post implantation loss and resorptions and decreased number of live fetuses), fetal developmental delay (skeletal effects) and urogenital effects (bilateral ureter dilation) at doses ≥10 mg/kg/day, decreased fetal ano-genital distance at ≥30 mg/kg/day, and decreased fetal body weight at 100 mg/kg/day.
Doses ≥10 mg/kg/day caused maternal toxicity. The doses tested in rats resulted in systemic exposures (AUC) approximately 0.03, 0.1 and 0.3 times, respectively, the AUC in patients.
8.2Lactation Risk Summary The safety and efficacy of abiraterone acetate have not been established in females. There is no information available on the presence of abiraterone in human milk, or on the effects on the breastfed child or milk production.
8.3Females and Males of Reproductive Potential Contraception Males Based on findings in animal reproduction studies and its mechanism of action, advise males with female partners of reproductive potential to use effective contraception during treatment and for 3 weeks after the final dose of abiraterone acetate [see Use in Specific Populations (8.1) ] . Infertility Based on animal studies, abiraterone acetate may impair reproductive function and fertility in males of reproductive potential [see Nonclinical Toxicology (13.1) ].
8.4Pediatric Use Safety and effectiveness of abiraterone acetate in pediatric patients have not been established.
8.5Geriatric Use Of the total number of patients receiving abiraterone acetate in randomized clinical trials, 70% of patients were 65 years and over and 27% were 75 years and over. No overall differences in safety or effectiveness were observed between these elderly patients and younger patients. Other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
8.6Patients with Hepatic Impairment The pharmacokinetics of abiraterone were examined in subjects with baseline mild (N=8) or moderate (N=8) hepatic impairment (Child-Pugh Class A and B, respectively) and in 8 healthy control subjects with normal hepatic function. The systemic exposure (AUC) of abiraterone after a single oral 1,000 mg dose of abiraterone acetate increased by approximately 1.1-fold and 3.6-fold in subjects with mild and moderate baseline hepatic impairment, respectively compared to subjects with normal hepatic function.
In another trial, the pharmacokinetics of abiraterone were examined in subjects with baseline severe (N=8) hepatic impairment (Child-Pugh Class C) and in 8 healthy control subjects with normal hepatic function. The systemic exposure (AUC) of abiraterone increased by approximately 7-fold and the fraction of free drug increased 2-fold in subjects with severe baseline hepatic impairment compared to subjects with normal hepatic function. No dosage adjustment is necessary for patients with baseline mild hepatic impairment.
In patients with basel… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The safety and efficacy of abiraterone acetate have not been established in females. Based on findings from animal studies and the mechanism of action, abiraterone acetate can cause fetal harm and potential loss of pregnancy. There are no human data on the use of abiraterone acetate in pregnant women.
In animal reproduction studies, oral administration of abiraterone acetate to pregnant rats during organogenesis caused adverse developmental effects at maternal exposures approximately ≥ 0.03 times the human exposure (AUC) at the recommended dose (see Data ). Data Animal Data In an embryo-fetal developmental toxicity study in rats, abiraterone acetate caused developmental toxicity when administered at oral doses of 10, 30 or 100 mg/kg/day throughout the period of organogenesis (gestational days 6–17). Findings included embryo-fetal lethality (increased post implantation loss and resorptions and decreased number of live fetuses), fetal developmental delay (skeletal effects) and urogenital effects (bilateral ureter dilation) at doses ≥10 mg/kg/day, decreased fetal ano-genital distance at ≥30 mg/kg/day, and decreased fetal body weight at 100 mg/kg/day.
Doses ≥10 mg/kg/day caused maternal toxicity. The doses tested in rats resulted in systemic exposures (AUC) approximately 0.03, 0.1 and 0.3 times, respectively, the AUC in patients.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of abiraterone acetate in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of patients receiving abiraterone acetate in randomized clinical trials, 70% of patients were 65 years and over and 27% were 75 years and over. No overall differences in safety or effectiveness were observed between these elderly patients and younger patients. Other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE Human experience of overdose with abiraterone acetate is limited. There is no specific antidote. In the event of an overdose, stop abiraterone acetate, undertake general supportive measures, including monitoring for arrhythmias and cardiac failure and assess liver function.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Abiraterone acetate is converted in vivo to abiraterone, an androgen biosynthesis inhibitor, that inhibits 17 α-hydroxylase/C17,20-lyase (CYP17). This enzyme is expressed in testicular, adrenal, and prostatic tumor tissues and is required for androgen biosynthesis. CYP17 catalyzes two sequential reactions: 1) the conversion of pregnenolone and progesterone to their 17α-hydroxy derivatives by 17α-hydroxylase activity and 2) the subsequent formation of dehydroepiandrosterone (DHEA) and androstenedione, respectively, by C17, 20 lyase activity.
DHEA and androstenedione are androgens and are precursors of testosterone. Inhibition of CYP17 by abiraterone can also result in increased mineralocorticoid production by the adrenals [see Warnings and Precautions (5.1) ] . Androgen sensitive prostatic carcinoma responds to treatment that decreases androgen levels.
Androgen deprivation therapies, such as treatment with GnRH agonists or orchiectomy, decrease androgen production in the testes but do not affect androgen production by the adrenals or in the tumor. Abiraterone acetate decreased serum testosterone and other androgens in patients in the placebo-controlled clinical trial. It is not necessary to monitor the effect of abiraterone acetate on serum testosterone levels.
Changes in serum prostate specific antigen (PSA) levels may be observed but have not been shown to correlate with clinical benefit in individual patients.
12.2Pharmacodynamics Cardiac Electrophysiology In a multi-center, open-label, single-arm trial, 33 patients with metastatic CRPC received abiraterone acetate orally at a dose of 1,000 mg once daily at least 1 hour before or 2 hours after a meal in combination with prednisone 5 mg orally twice daily. Assessments up to Cycle 2 Day 2 showed no large changes in the QTc interval (i.e., >20 ms) from baseline. However, small increases in the QTc interval (i.e., <10 ms) due to abiraterone acetate cannot be excluded due to study design limitations.
12.3Pharmacokinetics Following administration of abiraterone acetate, the pharmacokinetics of abiraterone have been studied in healthy subjects and in patients with metastatic CRPC. In vivo , abiraterone acetate is converted to abiraterone. In clinical studies, abiraterone acetate plasma concentrations were below detectable levels (<0.2 ng/mL) in >99% of the analyzed samples.
Absorption Following oral administration of abiraterone acetate to patients with metastatic CRPC, the median time to reach maximum plasma abiraterone concentrations is 2 hours. Abiraterone accumulation is observed at steady-state, with a 2-fold higher exposure (steady-state AUC) compared to a single 1,000 mg dose of abiraterone acetate. At the dose of 1,000 mg daily in patients with metastatic CRPC, steady-state values (mean ± SD) of C max were 226 ± 178 ng/mL and of AUC were 993 ± 639 ng.hr/mL.
No major deviation from dose proportionality was observed in the dose range of 250 mg to 1,000 mg. However, the exposure was not significantly increased when the dose was doubled from 1,000 to 2,000 mg (8% increase in the mean AUC). Systemic exposure of abiraterone is increased when abiraterone acetate is administered with food.
In healthy subjects abiraterone C max and AUC 0–∞ were approximately 7- and 5-fold higher, respectively, when a single dose of abiraterone acetate was administered with a low-fat meal (7% fat, 300 calories) and approximately 17- and 10-fold higher, respectively, when a single dose of abiraterone acetate was administered with a high-fat (57% fat, 825 calories) meal compared to overnight fasting. Abiraterone AUC 0–∞ was approximately 7-fold or 1.6-fold higher, respectively, when a single dose of abiraterone acetate was administered 2 hours after or 1 hour before a medium fat meal (25% fat, 491 calories) compared to overnight fasting.
Systemic exposures of abiraterone in patients with metastatic CRPC, after repeated dosing of abiraterone acetate we… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Abiraterone acetate is converted in vivo to abiraterone, an androgen biosynthesis inhibitor, that inhibits 17 α-hydroxylase/C17,20-lyase (CYP17). This enzyme is expressed in testicular, adrenal, and prostatic tumor tissues and is required for androgen biosynthesis. CYP17 catalyzes two sequential reactions: 1) the conversion of pregnenolone and progesterone to their 17α-hydroxy derivatives by 17α-hydroxylase activity and 2) the subsequent formation of dehydroepiandrosterone (DHEA) and androstenedione, respectively, by C17, 20 lyase activity.
DHEA and androstenedione are androgens and are precursors of testosterone. Inhibition of CYP17 by abiraterone can also result in increased mineralocorticoid production by the adrenals [see Warnings and Precautions (5.1) ] . Androgen sensitive prostatic carcinoma responds to treatment that decreases androgen levels.
Androgen deprivation therapies, such as treatment with GnRH agonists or orchiectomy, decrease androgen production in the testes but do not affect androgen production by the adrenals or in the tumor. Abiraterone acetate decreased serum testosterone and other androgens in patients in the placebo-controlled clinical trial. It is not necessary to monitor the effect of abiraterone acetate on serum testosterone levels.
Changes in serum prostate specific antigen (PSA) levels may be observed but have not been shown to correlate with clinical benefit in individual patients.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Abiraterone Acetate Tablets, USP are available in the strengths and packages listed below: Abiraterone Acetate 500 mg film-coated Tablets, USP Light purple, oval-shaped tablets debossed with “125” on one side. NDC 60505-4764-6 60 tablets available in high-density polyethylene bottles Storage and Handling Store at 20°C to 25°C (68°F to 77°F); excursions permitted in the range from 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature] . Keep out of reach of children.
Based on its mechanism of action, abiraterone acetate tablets, USP may harm a developing fetus. Women who are pregnant or women who may be pregnant should not handle abiraterone acetate 250 mg uncoated tablets, USP or other abiraterone acetate tablets, USP if broken, crushed, or damaged without protection, e.g., gloves [see Use in Specific Populations (8.1) ] .
📦 Storage and Handling ▾
Storage and Handling Store at 20°C to 25°C (68°F to 77°F); excursions permitted in the range from 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature] . Keep out of reach of children. Based on its mechanism of action, abiraterone acetate tablets, USP may harm a developing fetus.
Women who are pregnant or women who may be pregnant should not handle abiraterone acetate 250 mg uncoated tablets, USP or other abiraterone acetate tablets, USP if broken, crushed, or damaged without protection, e.g., gloves [see Use in Specific Populations (8.1) ] .
📋 Description ▾
11 DESCRIPTION Abiraterone acetate, USP, the active ingredient of abiraterone acetate tablets, USP is the acetyl ester of abiraterone. Abiraterone is an inhibitor of CYP17 (17α-hydroxylase/C17,20-lyase). Each abiraterone acetate tablet, USP contains 500 mg of abiraterone acetate, USP.
Abiraterone acetate, USP is designated chemically as (3β)-17-(3-pyridinyl) androsta-5,16-dien-3-yl acetate and its structure is: Abiraterone acetate, USP is a white to off-white, non-hygroscopic, crystalline powder. Its molecular formula is C 26 H 33 NO 2 and it has a molecular weight of 391.55. Abiraterone acetate, USP is a lipophilic compound with an octanol-water partition coefficient of 5.12 (Log P) and is practically insoluble in water.
The pKa of the aromatic nitrogen is 5.19. Abiraterone acetate tablets, USP are available in 500 mg film-coated tablets with the following inactive ingredients: 500 mg film-coated tablets: colloidal silicon dioxide, croscarmellose sodium, hypromellose, lactose monohydrate, magnesium stearate, microcrystalline cellulose PH101, and sodium lauryl sulfate. The coating, Opadry ® 85F100098-CN Purple, contains iron oxide black, iron oxide red, polyethylene glycol, polyvinyl alcohol, talc, and titanium dioxide.
Meets USP Dissolution Test 3. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information) Hypokalemia, Fluid Retention, and Cardiovascular Adverse Reactions Inform patients that abiraterone acetate is associated with hypertension, hypokalemia, and peripheral edema that may lead to QT prolongation and Torsades de Pointes in patients who develop hypokalemia while taking abiraterone acetate. Advise patients that their blood pressure, serum potassium and signs and symptoms of fluid retention will be monitored clinically at least monthly.
Advise patients to adhere to corticosteroids and to report symptoms of hypertension, hypokalemia, or edema to their healthcare provider [see Warnings and Precautions (5.1) ] . Adrenocortical Insufficiency Inform patients that abiraterone acetate with prednisone is associated with adrenal insufficiency. Advise patients to report symptoms of adrenocortical insufficiency to their healthcare provider [see Warnings and Precautions (5.2) ] .
Hepatotoxicity Inform patients that abiraterone acetate is associated with severe hepatotoxicity. Inform patients that their liver function will be monitored using blood tests. Advise patients to immediately report symptoms of hepatotoxicity to their healthcare provider [see Warnings and Precautions (5.3) ] .
Hypoglycemia Inform patients that severe hypoglycemia has been reported when abiraterone acetate was administered to patients with pre-existing diabetes who were receiving medications containing thiazolidinediones (including pioglitazone) or repaglinide, antidiabetic drugs. Advise patients with diabetes to monitor glucose levels during and after treatment with abiraterone acetate [see Warnings and Precautions (5.6) and Drug Interactions (7.2) ]. Use in Combination with Radium Ra 223 Dichloride Advise patients that radium Ra 223 dichloride showed an increase in mortality and an increased rate of fracture when used in combination with abiraterone acetate plus prednisone/prednisolone.
Inform patients to speak with their healthcare provider about any other medications or treatment they are currently taking for prostate cancer [see Warnings and Precautions (5.4) ] . Dosing and Administration Inform patients that abiraterone acetate is taken once daily with prednisone (once or twice daily according to their healthcare provider's instructions) and to not interrupt or stop either of these medications without consulting their healthcare provider. Inform patients receiving GnRH therapy that they need to maintain this treatment during the course of treatment with abiraterone acetate.
Instruct patients to take abiraterone acetate tablets as a single dose once daily on an empty stomach . Instruct patients to not eat food 2 hours before and 1 hour after taking abiraterone acetate. Abiraterone acetate taken with food causes increased exposure and may result in adverse reactions.
Instruct patients to swallow tablets whole with water and not to crush or chew the tablets [see Dosage and Administration (2.3) ] . Inform patients that if they miss a dose of abiraterone acetate or prednisone, they should take their normal dose the following day. If more than one daily dose is skipped, inform patients to contact their healthcare provider [see Dosage and Administration (2.3) ] .
Embryo-Fetal Toxicity Inform patients that abiraterone acetate may harm a developing fetus and can cause loss of pregnancy. Advise males with female partners of reproductive potential to use effective contraception during treatment and for 3 weeks after the final dose of abiraterone acetate [see Use in Specific Populations (8.1) ] . Advise females who are pregnant or women who may be pregnant not to handle abiraterone acetate 250 mg uncoated tablets or other abiraterone acetate tablets if broken, crushed, or damaged without protection, e.g., gloves [see Use in Specific Populations (8.1) and How Supplied/Storage and Handling (16) ] .
Infertility Advise male patients that abiraterone a… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Following administration of abiraterone acetate, the pharmacokinetics of abiraterone have been studied in healthy subjects and in patients with metastatic CRPC. In vivo , abiraterone acetate is converted to abiraterone. In clinical studies, abiraterone acetate plasma concentrations were below detectable levels (<0.2 ng/mL) in >99% of the analyzed samples.
Absorption Following oral administration of abiraterone acetate to patients with metastatic CRPC, the median time to reach maximum plasma abiraterone concentrations is 2 hours. Abiraterone accumulation is observed at steady-state, with a 2-fold higher exposure (steady-state AUC) compared to a single 1,000 mg dose of abiraterone acetate. At the dose of 1,000 mg daily in patients with metastatic CRPC, steady-state values (mean ± SD) of C max were 226 ± 178 ng/mL and of AUC were 993 ± 639 ng.hr/mL.
No major deviation from dose proportionality was observed in the dose range of 250 mg to 1,000 mg. However, the exposure was not significantly increased when the dose was doubled from 1,000 to 2,000 mg (8% increase in the mean AUC). Systemic exposure of abiraterone is increased when abiraterone acetate is administered with food.
In healthy subjects abiraterone C max and AUC 0–∞ were approximately 7- and 5-fold higher, respectively, when a single dose of abiraterone acetate was administered with a low-fat meal (7% fat, 300 calories) and approximately 17- and 10-fold higher, respectively, when a single dose of abiraterone acetate was administered with a high-fat (57% fat, 825 calories) meal compared to overnight fasting. Abiraterone AUC 0–∞ was approximately 7-fold or 1.6-fold higher, respectively, when a single dose of abiraterone acetate was administered 2 hours after or 1 hour before a medium fat meal (25% fat, 491 calories) compared to overnight fasting.
Systemic exposures of abiraterone in patients with metastatic CRPC, after repeated dosing of abiraterone acetate were similar when abiraterone acetate was taken with low-fat meals for 7 days and increased approximately 2-fold when taken with high-fat meals for 7 days compared to when taken at least 2 hours after a meal and at least 1 hour before a meal for 7 days. Given the normal variation in the content and composition of meals, taking abiraterone acetate with meals has the potential to result in increased and highly variable exposures.
Distribution Abiraterone is highly bound (>99%) to the human plasma proteins, albumin and alpha-1 acid glycoprotein. The apparent steady-state volume of distribution (mean ± SD) is 19,669 ± 13,358 L. In vitro studies show that at clinically relevant concentrations, abiraterone acetate and abiraterone are not substrates of P-glycoprotein (P-gp) and that abiraterone acetate is an inhibitor of P-gp.
Elimination In patients with metastatic CRPC, the mean terminal half-life of abiraterone in plasma (mean ± SD) is 12 ± 5 hours. Metabolism Following oral administration of 14 C-abiraterone acetate as capsules, abiraterone acetate is hydrolyzed to abiraterone (active metabolite). The conversion is likely through esterase activity (the esterases have not been identified) and is not CYP mediated.
The two main circulating metabolites of abiraterone in human plasma are abiraterone sulphate (inactive) and N-oxide abiraterone sulphate (inactive), which account for about 43% of exposure each. CYP3A4 and SULT2A1 are the enzymes involved in the formation of N-oxide abiraterone sulphate and SULT2A1 is involved in the formation of abiraterone sulphate. Excretion Following oral administration of 14 C-abiraterone acetate, approximately 88% of the radioactive dose is recovered in feces and approximately 5% in urine.
The major compounds present in feces are unchanged abiraterone acetate and abiraterone (approximately 55% and 22% of the administered dose, respectively). Specific Populations Patients with Hepatic Impairment The pharmacokinetics of abiraterone was examined in subjects with baseline mild… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Cardiac Electrophysiology In a multi-center, open-label, single-arm trial, 33 patients with metastatic CRPC received abiraterone acetate orally at a dose of 1,000 mg once daily at least 1 hour before or 2 hours after a meal in combination with prednisone 5 mg orally twice daily. Assessments up to Cycle 2 Day 2 showed no large changes in the QTc interval (i.e., >20 ms) from baseline. However, small increases in the QTc interval (i.e., <10 ms) due to abiraterone acetate cannot be excluded due to study design limitations.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy and safety of abiraterone acetate with prednisone was established in three randomized placebo-controlled international clinical studies. All patients in these studies received a GnRH analog or had prior bilateral orchiectomy. Patients with prior ketoconazole treatment for prostate cancer and a history of adrenal gland or pituitary disorders were excluded from these trials.
Concurrent use of spironolactone was not allowed during the study period. COU-AA-301: Patients with metastatic CRPC who had received prior docetaxel chemotherapy In COU-AA-301 (NCT00638690), a total of 1195 patients were randomized 2:1 to receive either abiraterone acetate orally at a dose of 1,000 mg once daily in combination with prednisone 5 mg orally twice daily (N=797) or placebo once daily plus prednisone 5 mg orally twice daily (N=398). Patients randomized to either arm were to continue treatment until disease progression (defined as a 25% increase in PSA over the patient's baseline/nadir together with protocol-defined radiographic progression and symptomatic or clinical progression), initiation of new treatment, unacceptable toxicity or withdrawal.
The following patient demographics and baseline disease characteristics were balanced between the treatment arms. The median age was 69 years (range 39–95) and the racial distribution was 93% Caucasian, 3.6% Black, 1.7% Asian, and 1.6% Other. Eighty-nine percent of patients enrolled had an ECOG performance status score of 0–1 and 45% had a Brief Pain Inventory-Short Form score of ≥4 (patient's reported worst pain over the previous 24 hours).
Ninety percent of patients had metastases in bone and 30% had visceral involvement. Seventy percent of patients had radiographic evidence of disease progression and 30% had PSA-only progression. Seventy percent of patients had previously received one cytotoxic chemotherapy regimen and 30% received two regimens.
The protocol pre-specified interim analysis was conducted after 552 deaths and showed a statistically significant improvement in overall survival (OS) in patients treated with abiraterone acetate with prednisone compared to patients in the placebo with prednisone arm (Table 9 and Figure 1). An updated survival analysis was conducted when 775 deaths (97% of the planned number of deaths for final analysis) were observed. Results from this analysis were consistent with those from the interim analysis (Table 7).
Table 7: Overall Survival of Patients Treated with Either Abiraterone Acetate or Placebo in Combination with Prednisone in COU-AA-301 (Intent-to-Treat Analysis) Abiraterone Acetate with Prednisone (N=797) Placebo with Prednisone (N=398) Primary Survival Analysis Deaths (%) 333 (42%) 219 (55%) Median survival (months) (95% CI) 14.8 (14.1, 15.4) 10.9 (10.2, 12.0) p-value p-value is derived from a log-rank test stratified by ECOG performance status score (0–1 vs. 2), pain score (absent vs. present), number of prior chemotherapy regimens (1 vs.
2), and type of disease progression (PSA only vs. radiographic). <0.0001 Hazard ratio (95% CI) Hazard Ratio is derived from a stratified proportional hazards model. Hazard ratio <1 favors abiraterone acetate with prednisone. 0.646 (0.543, 0.768) Updated Survival Analysis Deaths (%) 501 (63%) 274 (69%) Median survival (months) (95% CI) 15.8 (14.8, 17.0) 11.2 (10.4, 13.1) Hazard ratio (95% CI) 0.740 (0.638, 0.859) Figure 1: Kaplan-Meier Overall Survival Curves in COU-AA-301 (Intent-to-Treat Analysis) Figure 1 COU-AA-302: Patients with metastatic CRPC who had not received prior cytotoxic chemotherapy In COU-AA-302 (NCT00887198), 1088 patients were randomized 1:1 to receive either abiraterone acetate orally at a dose of 1,000 mg once daily (N=546) or Placebo orally once daily (N=542).
Both arms were given concomitant prednisone 5 mg twice daily. Patients continued treatment until radiographic or clinical (cytotoxic chemotherapy, radiation or surgical treatment for cancer, pain requiring chroni… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, and Impairment of Fertility A two-year carcinogenicity study was conducted in rats at oral abiraterone acetate doses of 5, 15, and 50 mg/kg/day for males and 15, 50, and 150 mg/kg/day for females. Abiraterone acetate increased the combined incidence of interstitial cell adenomas and carcinomas in the testes at all dose levels tested. This finding is considered to be related to the pharmacological activity of abiraterone.
Rats are regarded as more sensitive than humans to developing interstitial cell tumors in the testes. Abiraterone acetate was not carcinogenic in female rats at exposure levels up to 0.8 times the human clinical exposure based on AUC. Abiraterone acetate was not carcinogenic in a 6-month study in the transgenic (Tg.rasH2) mouse.
Abiraterone acetate and abiraterone was not mutagenic in an in vitro microbial mutagenesis (Ames) assay or clastogenic in an in vitro cytogenetic assay using primary human lymphocytes or an in vivo rat micronucleus assay. In repeat-dose toxicity studies in male rats (13- and 26-weeks) and monkeys (39-weeks), atrophy, aspermia/hypospermia, and hyperplasia in the reproductive system were observed at ≥50 mg/kg/day in rats and ≥250 mg/kg/day in monkeys and were consistent with the antiandrogenic pharmacological activity of abiraterone.
These effects were observed in rats at systemic exposures similar to humans and in monkeys at exposures approximately 0.6 times the AUC in humans. In a fertility study in male rats, reduced organ weights of the reproductive system, sperm counts, sperm motility, altered sperm morphology and decreased fertility were observed in animals dosed for 4 weeks at ≥30 mg/kg/day orally. Mating of untreated females with males that received 30 mg/kg/day oral abiraterone acetate resulted in a reduced number of corpora lutea, implantations and live embryos and an increased incidence of pre-implantation loss.
Effects on male rats were reversible after 16 weeks from the last abiraterone acetate administration. In a fertility study in female rats, animals dosed orally for 2 weeks until day 7 of pregnancy at ≥30 mg/kg/day had an increased incidence of irregular or extended estrous cycles and pre-implantation loss (300 mg/kg/day). There were no differences in mating, fertility, and litter parameters in female rats that received abiraterone acetate.
Effects on female rats were reversible after 4 weeks from the last abiraterone acetate administration. The dose of 30 mg/kg/day in rats is approximately 0.3 times the recommended dose of 1,000 mg/day based on body surface area. In 13- and 26-week studies in rats and 13- and 39-week studies in monkeys, a reduction in circulating testosterone levels occurred with abiraterone acetate at approximately one half the human clinical exposure based on AUC.
As a result, decreases in organ weights and toxicities were observed in the male and female reproductive system, adrenal glands, liver, pituitary (rats only), and male mammary glands. The changes in the reproductive organs are consistent with the antiandrogenic pharmacological activity of abiraterone acetate.
13.2Animal Toxicology and/or Pharmacology A dose-dependent increase in cataracts was observed in rats after daily oral abiraterone acetate administration for 26 weeks starting at ≥50 mg/kg/day (similar to the human clinical exposure based on AUC). In a 39-week monkey study with daily oral abiraterone acetate administration, no cataracts were observed at higher doses (2 times greater than the clinical exposure based on AUC).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, and Impairment of Fertility A two-year carcinogenicity study was conducted in rats at oral abiraterone acetate doses of 5, 15, and 50 mg/kg/day for males and 15, 50, and 150 mg/kg/day for females. Abiraterone acetate increased the combined incidence of interstitial cell adenomas and carcinomas in the testes at all dose levels tested. This finding is considered to be related to the pharmacological activity of abiraterone.
Rats are regarded as more sensitive than humans to developing interstitial cell tumors in the testes. Abiraterone acetate was not carcinogenic in female rats at exposure levels up to 0.8 times the human clinical exposure based on AUC. Abiraterone acetate was not carcinogenic in a 6-month study in the transgenic (Tg.rasH2) mouse.
Abiraterone acetate and abiraterone was not mutagenic in an in vitro microbial mutagenesis (Ames) assay or clastogenic in an in vitro cytogenetic assay using primary human lymphocytes or an in vivo rat micronucleus assay. In repeat-dose toxicity studies in male rats (13- and 26-weeks) and monkeys (39-weeks), atrophy, aspermia/hypospermia, and hyperplasia in the reproductive system were observed at ≥50 mg/kg/day in rats and ≥250 mg/kg/day in monkeys and were consistent with the antiandrogenic pharmacological activity of abiraterone.
These effects were observed in rats at systemic exposures similar to humans and in monkeys at exposures approximately 0.6 times the AUC in humans. In a fertility study in male rats, reduced organ weights of the reproductive system, sperm counts, sperm motility, altered sperm morphology and decreased fertility were observed in animals dosed for 4 weeks at ≥30 mg/kg/day orally. Mating of untreated females with males that received 30 mg/kg/day oral abiraterone acetate resulted in a reduced number of corpora lutea, implantations and live embryos and an increased incidence of pre-implantation loss.
Effects on male rats were reversible after 16 weeks from the last abiraterone acetate administration. In a fertility study in female rats, animals dosed orally for 2 weeks until day 7 of pregnancy at ≥30 mg/kg/day had an increased incidence of irregular or extended estrous cycles and pre-implantation loss (300 mg/kg/day). There were no differences in mating, fertility, and litter parameters in female rats that received abiraterone acetate.
Effects on female rats were reversible after 4 weeks from the last abiraterone acetate administration. The dose of 30 mg/kg/day in rats is approximately 0.3 times the recommended dose of 1,000 mg/day based on body surface area. In 13- and 26-week studies in rats and 13- and 39-week studies in monkeys, a reduction in circulating testosterone levels occurred with abiraterone acetate at approximately one half the human clinical exposure based on AUC.
As a result, decreases in organ weights and toxicities were observed in the male and female reproductive system, adrenal glands, liver, pituitary (rats only), and male mammary glands. The changes in the reproductive organs are consistent with the antiandrogenic pharmacological activity of abiraterone acetate.
📄 Patient Package Insert ▾
This Patient Information has been approved by the U.S. Food and Drug Administration. Revised: October 2021 PATIENT INFORMATION Abiraterone Acetate Tablets, USP [aʺ bir aʹ ter one asʹ e tate] Patient Information Leaflet available at www1.apotex.com/products/us What is abiraterone acetate?
Abiraterone acetate is a prescription medicine that is used along with prednisone. Abiraterone acetate is used to treat men with prostate cancer that has spread to other parts of the body. It is not known if abiraterone acetate is safe and effective in females or children.
Before taking abiraterone acetate, tell your healthcare provider about all of your medical conditions, including if you: have heart problems have liver problems have diabetes have a history of adrenal problems have a history of pituitary problems are receiving any other treatment for prostate cancer are pregnant or plan to become pregnant. Abiraterone acetate can cause harm to your unborn baby and loss of pregnancy (miscarriage). Females who are or may become pregnant should not handle abiraterone acetate uncoated tablets or other abiraterone acetate tablets if broken, crushed, or damaged without protection, such as gloves. have a partner who is pregnant or may become pregnant.
Males who have female partners who are able to become pregnant should use effective birth control (contraception) during treatment with abiraterone acetate and for 3 weeks after the last dose of abiraterone acetate. are breastfeeding or plan to breastfeed. It is not known if abiraterone acetate passes into your breastmilk. Tell your healthcare provider about all the medicines you take or treatments you receive , including prescription and over-the-counter medicines, vitamins, and herbal supplements.
Abiraterone acetate can interact with many other medicines. You should not start or stop any medicine before you talk with the healthcare provider that prescribed abiraterone acetate. Know the medicines you take.
Keep a list of them with you to show to your healthcare provider and pharmacist when you get a new medicine. How should I take abiraterone acetate? Take abiraterone acetate and prednisone exactly as your healthcare provider tells you.
Take your prescribed dose of abiraterone acetate 1 time a day. Your healthcare provider may change your dose if needed. Do not change or stop taking your prescribed dose of abiraterone acetate or prednisone without talking with your healthcare provider first.
Take abiraterone acetate tablets as a single dose one time a day on an empty stomach . Do not eat food 2 hours before and 1 hour after taking abiraterone acetate. Do not take abiraterone acetate with food.
Taking abiraterone acetate with food may cause more of the medicine to be absorbed by the body than is needed and this may cause side effects. Swallow abiraterone acetate tablets whole. Do not crush or chew tablets.
Take abiraterone acetate tablets with water. If you miss a dose of abiraterone acetate or prednisone, take your prescribed dose the following day. If you miss more than 1 dose, tell your healthcare provider right away.
Your healthcare provider will do blood tests to check for side effects. What are the possible side effects of abiraterone acetate? Abiraterone acetate may cause serious side effects including: High blood pressure (hypertension), low blood potassium levels (hypokalemia), fluid retention (edema), and irregular heartbeats can happen during treatment with abiraterone acetate.
This can be life threatening. To decrease the chance of this happening, you must take prednisone with abiraterone acetate exactly as your healthcare provider tells you. Your healthcare provider will check your blood pressure, do blood tests to check your potassium levels, and check for any signs and symptoms of fluid retention every month during treatment with abiraterone acetate.
Tell your healthcare provider if you get any of the following symptoms: dizziness fast or irregular heartbeats feel faint or lightheaded… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Dosage and Administration, Important Administration Instructions ( 2.3 ) 8/2021 Warnings and Precautions, Hypoglycemia ( 5.6 ) 10/2020
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 500 mg Tablet Bottle Label-60 film-coated tablets NDC 60505-4764-6 Abiraterone Acetate Tablets, USP 500 mg Each film-coated tablet contains 500 mg of Abiraterone acetate, USP Rx only 60 film-coated tablets PRINCIPAL DISPLAY PANEL - 500 mg Tablet Bottle Label