
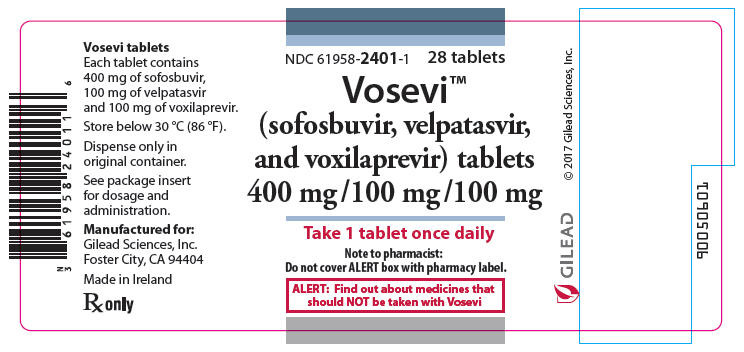
Vosevi SOFOSBUVIR, VELPATASVIR, and VOXILAPREVIR 400 mg; 100 mg; 100 mg Tablet, Film Coated, 28-count — NDC 61958-2401-1 (Billing 61958-2401-01)
This is a package of 28 tablets of Vosevi SOFOSBUVIR, VELPATASVIR, and VOXILAPREVIR 400 mg; 100 mg; 100 mg Tablet, Film Coated from Gilead Sciences, Inc., marketed since Jul 2017 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 61958-2401-1 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 61958 labeler · 2401 product · 1 package
- Package marketed since
- Jul 18, 2017
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 28 EA per package
- Barcode (UPC-A, from the NDC)
- 3 6195824011 6
- Medicaid fills, this package
- 1,130 prescriptions in the last four reported quarters
- FDA record last changed
- Oct 8, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 077584
- GCN: 43634
- GPI-14 (Medi-Span): 12359903800330
- HICL (First Databank): 044428
- AHFS class code: 08:18.40.16
- RxCUI (RxNorm): 1939329
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Hepatitis C Virus Nucleotide Analog NS5B Polymerase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
The combination of sofosbuvir, velpatasvir, and voxilaprevir is used to treat chronic (long-term) hepatitis C infection (swelling of the liver caused by a virus) in adults who have already received other HCV treatments. Sofosbuvir is a non-nucleoside NS5B polymerase inhibitor. It works by decreasing the amount of hepatitis C virus in the body. Velpatasvir is a hepatitis C virus (HCV) NS5A inhibitor. It works by stopping the virus that causes hepatitis C from spreading inside the body. Voxilaprevir is in a class of medications called HCV NS3/4A protease inhibitors. It works by decreasing the am...
Read the full MedlinePlus article ↗- Vosevi is a rescue option for people with hepatitis C whose earlier treatment didn't fully clear the virus. It combines three different antivirals that each attack hepatitis C in a...
- What exactly is Vosevi for, and why am I taking it when I've already tried hepatitis C treatment before?
- Taking Vosevi with food is really important — eating a meal dramatically increases how much of each drug your body absorbs. Without food, you may not get enough of the medication i...
- Why do I have to take Vosevi with food? What happens if I forget and take it on an empty stomach?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $869.58 | $24,348.16 / 28 tablets |
| Medicare drug plans payPart D · Q2 2026 | $861.88 | $24,132.61 / 28 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 61958-2401-01 You're viewing this Main listing | 28 TABLET, FILM COATED in 1 BOTTLE, PLASTIC | 2017-07-18 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Vosevi 400 mg/1; 100 mg/1; 100 mgthis 61958-2401-01 | Gilead | 28 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8940718 ↗ | Drug substance | U-2039 | Nov 16, 2032 |
| US 8575135 ↗ | Drug substance | U-2040 | Nov 16, 2032 |
| US 8921341 ↗ | Drug substance | U-2040 | Nov 16, 2032 |
| US 8921341 ↗ | Drug substance | U-2039 | Nov 16, 2032 |
| US 7964580 ↗ | Drug substance | U-2039 | Mar 26, 2029 |
| US 7964580 ↗ | Drug substance | U-2040 | Mar 26, 2029 |
| US 8618076 ↗ | Drug substance | U-2040 | Dec 11, 2030 |
| US 9085573 ↗ | Drug substance | U-2040 | Mar 21, 2028 |
| US 9085573 ↗ | Drug substance | U-2039 | Mar 21, 2028 |
| US 8334270 ↗ | Drug substance | U-2040 | Mar 21, 2028 |
| US 8889159 ↗ | Drug substance | U-2040 | Mar 26, 2029 |
| US 9284342 ↗ | Drug substance | U-2040 | Sep 13, 2030 |
| US 9284342 ↗ | Drug substance | U-2039 | Sep 13, 2030 |
| US 8580765 ↗ | Drug substance | U-2040 | Mar 21, 2028 |
| US 8580765 ↗ | Drug substance | U-2039 | Mar 21, 2028 |
| US 8735372 ↗ | Drug substance | U-2040 | Mar 21, 2028 |
| US 8334270 ↗ | Drug substance | U-2039 | Mar 21, 2028 |
| US 8575135 ↗ | Drug substance | U-2039 | Nov 16, 2032 |
| US 8618076 ↗ | Drug substance | U-2039 | Dec 11, 2030 |
| US 8735372 ↗ | Drug substance | U-2039 | Mar 21, 2028 |
| US 8633309 ↗ | Drug substance | U-2039 | Mar 26, 2029 |
| US 8889159 ↗ | Drug substance | U-2039 | Mar 26, 2029 |
| US 8957046 ↗ | Method of use | U-2040 | Mar 21, 2028 |
| US 8957046 ↗ | Method of use | U-2039 | Mar 21, 2028 |
| US 11338007 ↗ | Method of use | U-2039 | Jun 1, 2037 |
| US 11338007 ↗ | Method of use | U-2040 | Jun 1, 2037 |
| US 8940718 ↗ | Drug substance | U-2040 | Nov 16, 2032 |
| US 11116783 ↗ | Method of use | U-2039 | Jan 30, 2034 |
| US 11116783 ↗ | Method of use | U-2040 | Jan 30, 2034 |
| US 8633309 ↗ | Drug substance | U-2040 | Mar 26, 2029 |
| US 9868745 ↗ | Drug substance | — | Nov 16, 2032 |
| US 10912814 ↗ | Drug product | — | Jun 1, 2037 |
| US 9296782 ↗ | Drug substance | — | Jul 17, 2034 |
| US 8580765*PED ↗ | Drug product | — | Sep 21, 2028 |
| US 8334270*PED ↗ | Drug product | — | Sep 21, 2028 |
| US 7964580*PED ↗ | Drug product | — | Sep 26, 2029 |
| US 8575135*PED ↗ | Drug product | — | May 16, 2033 |
| US 8618076*PED ↗ | Drug product | — | Jun 11, 2031 |
| US 8921341*PED ↗ | Drug product | — | May 16, 2033 |
| US 8735372*PED ↗ | Drug product | — | Sep 21, 2028 |
| US 8633309*PED ↗ | Drug product | — | Sep 26, 2029 |
| US 9085573*PED ↗ | Drug product | — | Sep 21, 2028 |
| US 8940718*PED ↗ | Drug product | — | May 16, 2033 |
| US 8889159*PED ↗ | Drug product | — | Sep 26, 2029 |
| US 9284342*PED ↗ | Drug product | — | Mar 13, 2031 |
| US 11338007*PED ↗ | Drug product | — | Dec 1, 2037 |
| US 11116783*PED ↗ | Drug product | — | Jul 30, 2034 |
Is there a generic version of VOSEVI 400-100-100 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Sofosbuvir, Velpatasvir, and Voxilaprevir inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 1364PS73AF
Acetone is a clear, volatile liquid solvent. In medications, it helps dissolve or extract active ingredients during manufacturing and may be used in certain liquid formulations or coating processes.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII D9C330MD8B
Copovidone is a synthetic polymer made by combining two types of plastic-like molecules. It acts as a binder and film-former to help hold tablet ingredients together and improve how the medicine dissolves in your body.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
16 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Gilead Sciences, Inc. labeler code 61958
- Odefsey emtricitabine, rilpivirine hydrochloride, and tenofovir alafenamide 200 mg; 25 mg; 25 mg Tablet NDC 61958-2101-1
- Epclusa Velpatasvir and Sofosbuvir 100 mg; 400 mg Tablet, Film Coated NDC 61958-2201-1
- Epclusa Velpatasvir and Sofosbuvir 50 mg; 200 mg Tablet, Film Coated NDC 61958-2203-1
- Epclusa Velpatasvir and Sofosbuvir 50 mg; 200 mg Pellet NDC 61958-2204-1
- Epclusa Velpatasvir and Sofosbuvir 37.5 mg; 150 mg Pellet NDC 61958-2205-1
- Vemlidy tenofovir alafenamide 25 mg Tablet NDC 61958-2301-1
- Biktarvy bictegravir sodium, emtricitabine, and tenofovir alafenamide fumarate 50 mg; 200 mg; 25 mg Tablet NDC 61958-2501-1
- Biktarvy bictegravir sodium, emtricitabine, and tenofovir alafenamide fumarate 30 mg; 120 mg; 15 mg Tablet NDC 61958-2505-1
- Biktarvy bictegravir sodium, emtricitabine, and tenofovir alafenamide fumarate 30 mg; 120 mg; 15 mg Tablet NDC 61958-2506-1
- Veklury remdesivir 100 mg Injection, Powder, Lyophilized, For Solution NDC 61958-2901-1
- Sunlenca LENACAPAVIR SODIUM 300 mg Tablet, Film Coated NDC 61958-3001-1
- Sunlenca LENACAPAVIR SODIUM Kit NDC 61958-3002-1
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RISK OF HEPATITIS B VIRUS REACTIVATION IN PATIENTS COINFECTED WITH HCV AND HBV Test all patients for evidence of current or prior hepatitis B virus (HBV) infection before initiating treatment with VOSEVI. HBV reactivation has been reported in HCV/HBV coinfected patients who were undergoing or had completed treatment with HCV direct-acting antivirals (DAA) and were not receiving HBV antiviral therapy. Some cases have resulted in fulminant hepatitis, hepatic failure, and death.
Monitor HCV/HBV coinfected patients for hepatitis flare or HBV reactivation during HCV treatment and post-treatment follow-up. Initiate appropriate patient management for HBV infection as clinically indicated [see Warnings and Precautions (5.1) ]. WARNING: RISK OF HEPATITIS B VIRUS REACTIVATION IN PATIENTS COINFECTED WITH HCV AND HBV See full prescribing information for complete boxed warning.
Hepatitis B virus (HBV) reactivation has been reported, in some cases resulting in fulminant hepatitis, hepatic failure, and death. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE VOSEVI is indicated for the treatment of adult patients with chronic hepatitis C virus (HCV) infection without cirrhosis or with compensated cirrhosis (Child-Pugh A) who have [see Dosage and Administration (2.2) and Clinical Studies (14) ]: genotype 1, 2, 3, 4, 5, or 6 infection and have previously been treated with an HCV regimen containing an NS5A inhibitor. genotype 1a or 3 infection and have previously been treated with an HCV regimen containing sofosbuvir without an NS5A inhibitor. Additional benefit of VOSEVI over sofosbuvir/velpatasvir was not shown in adults with genotype 1b, 2, 4, 5, or 6 infection previously treated with sofosbuvir without an NS5A inhibitor.
VOSEVI is a fixed-dose combination of sofosbuvir, a hepatitis C virus (HCV) nucleotide analog NS5B polymerase inhibitor, velpatasvir, an HCV NS5A inhibitor, and voxilaprevir, an HCV NS3/4A protease inhibitor, and is indicated for the treatment of adult patients with chronic HCV infection without cirrhosis or with compensated cirrhosis (Child-Pugh A) who have ( 1 , 2.2 , 14 ): genotype 1, 2, 3, 4, 5, or 6 infection and have previously been treated with an HCV regimen containing an NS5A inhibitor. genotype 1a or 3 infection and have previously been treated with an HCV regimen containing sofosbuvir without an NS5A inhibitor.
Additional benefit of VOSEVI over sofosbuvir/velpatasvir was not shown in adults with genotype 1b, 2, 4, 5, or 6 infection previously treated with sofosbuvir without an NS5A inhibitor.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Testing: Prior to initiating VOSEVI, test all patients for HBV infection by measuring HBsAg and anti-HBc. ( 2.1 ) Recommended dosage: One tablet (400 mg of sofosbuvir, 100 mg of velpatasvir, and 100 mg of voxilaprevir) taken orally once daily with food. ( 2.2 ) See recommended treatment regimen and duration in table below ( 2.2 ): Genotype Patients Previously Treated with an HCV Regimen Containing: VOSEVI Duration 1, 2, 3, 4, 5, or 6 An NS5A inhibitor In clinical trials, prior NS5A inhibitor experience included daclatasvir, elbasvir, ledipasvir, ombitasvir, or velpatasvir.
12 weeks 1a or 3 Sofosbuvir without an NS5A inhibitor In clinical trials, prior treatment experience included sofosbuvir with or without any of the following: peginterferon alfa/ribavirin, ribavirin, HCV NS3/4A protease inhibitor (boceprevir, simeprevir, or telaprevir). 12 weeks For patients with renal impairment including end stage renal disease on dialysis, follow the dosage recommendations in the table above. ( 2.3 ) VOSEVI is not recommended in patients with moderate or severe hepatic impairment (Child-Pugh B or C).
( 2.4 , 5.2 )
2.1Testing Prior to the Initiation of Therapy Test all patients for evidence of current or prior HBV infection by measuring hepatitis B surface antigen (HBsAg) and hepatitis B core antibody (anti-HBc) before initiating HCV treatment with VOSEVI [see Warnings and Precautions (5.1) ].
2.2Recommended Dosage The recommended dosage of VOSEVI is one tablet, taken orally, once daily with food [see Clinical Pharmacology (12.3) ]. One tablet of VOSEVI contains 400 mg of sofosbuvir, 100 mg of velpatasvir, and 100 mg of voxilaprevir. Table 1 shows the recommended treatment regimen and duration based on patient population.
Table 1 Recommended Treatment Regimen and Duration in Adults Without Cirrhosis or With Compensated Cirrhosis (Child-Pugh A) Genotype Patients Previously Treated with an HCV Regimen Containing: VOSEVI Duration 1, 2, 3, 4, 5, or 6 An NS5A inhibitor In clinical trials, prior NS5A inhibitor experience included daclatasvir, elbasvir, ledipasvir, ombitasvir, or velpatasvir. 12 weeks 1a or 3 Sofosbuvir without an NS5A inhibitor In clinical trials, prior treatment experience included sofosbuvir with or without any of the following: peginterferon alfa/ribavirin, ribavirin, HCV NS3/4A protease inhibitor (boceprevir, simeprevir, or telaprevir).
12 weeks
2.3Renal Impairment No dosage adjustment of VOSEVI is recommended in patients with any degree of renal impairment including patients on dialysis [see Use in Specific Populations (8.6) and Clinical Pharmacology (12.3) ].
2.4Moderate or Severe Hepatic Impairment VOSEVI is not recommended in patients with moderate or severe hepatic impairment (Child-Pugh B or C) due to higher exposures of voxilaprevir in these patients [see Warnings and Precautions (5.2) , Use in Specific Populations (8.7) , and Clinical Pharmacology (12.3) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Each VOSEVI tablet contains 400 mg of sofosbuvir, 100 mg of velpatasvir, and 100 mg of voxilaprevir. The tablets are beige, capsule-shaped, film-coated, and debossed with "GSI" on one side and " " on the other side. Tablets: 400 mg sofosbuvir, 100 mg velpatasvir, and 100 mg voxilaprevir ( 3 ) Figure
⛔ Contraindications ▾
4 CONTRAINDICATIONS VOSEVI is contraindicated with rifampin [see Drug Interactions (7.3) , and Clinical Pharmacology (12.3) ]. Coadministration with rifampin. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Risk of Hepatitis B Virus Reactivation: Test all patients for evidence of current or prior HBV infection before initiation of HCV treatment. Monitor HCV/HBV coinfected patients for HBV reactivation and hepatitis flare during HCV treatment and post-treatment follow-up. Initiate appropriate patient management for HBV infection as clinically indicated.
( 5.1 ) Risk of Hepatic Decompensation/Failure in Patients with Evidence of Advanced Liver Disease: Hepatic decompensation/failure, including fatal outcomes, have been reported mostly in patients with cirrhosis and baseline moderate or severe liver impairment (Child-Pugh B or C) treated with HCV NS3/4A protease inhibitor-containing regimens. Monitor for clinical and laboratory evidence of hepatic decompensation. Discontinue VOSEVI in patients who develop evidence of hepatic decompensation/failure.
( 5.2 ) Bradycardia with Amiodarone Coadministration: Serious symptomatic bradycardia may occur in patients taking amiodarone with VOSEVI, a sofosbuvir-containing regimen, particularly in patients also receiving beta blockers, or those with underlying cardiac comorbidities and/or advanced liver disease. Coadministration of amiodarone with VOSEVI is not recommended. In patients without alternative viable treatment options, cardiac monitoring is recommended.
( 5.3 , 7.3 )
5.1Risk of Hepatitis B Virus Reactivation in Patients Coinfected with HCV and HBV Hepatitis B virus (HBV) reactivation has been reported in HCV/HBV coinfected patients who were undergoing or had completed treatment with HCV direct-acting antivirals, and who were not receiving HBV antiviral therapy. Some cases have resulted in fulminant hepatitis, hepatic failure, and death. Cases have been reported in patients who are HBsAg positive and also in patients with serologic evidence of resolved HBV infection (i.e., HBsAg negative and anti-HBc positive).
HBV reactivation has also been reported in patients receiving certain immunosuppressant or chemotherapeutic agents; the risk of HBV reactivation associated with treatment with HCV direct-acting antivirals may be increased in these patients. HBV reactivation is characterized as an abrupt increase in HBV replication manifesting as a rapid increase in serum HBV DNA level. In patients with resolved HBV infection reappearance of HBsAg can occur.
Reactivation of HBV replication may be accompanied by hepatitis, i.e., increases in aminotransferase levels and, in severe cases, increases in bilirubin levels, liver failure, and death can occur. Test all patients for evidence of current or prior HBV infection by measuring HBsAg and anti-HBc before initiating HCV treatment with VOSEVI. In patients with serologic evidence of HBV infection, monitor for clinical and laboratory signs of hepatitis flare or HBV reactivation during HCV treatment with VOSEVI and during post-treatment follow-up.
Initiate appropriate patient management for HBV infection as clinically indicated.
5.2Risk of Hepatic Decompensation/Failure in Patients with Evidence of Advanced Liver Disease Postmarketing cases of hepatic decompensation/failure, including those with fatal outcomes, have been reported in patients treated with HCV NS3/4A protease inhibitor-containing regimens, including treatment with VOSEVI. Reported cases occurred in patients with baseline cirrhosis with and without moderate or severe liver impairment (Child-Pugh B or C). Because these events are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
In patients with compensated cirrhosis (Child-Pugh A) or evidence of advanced liver disease such as portal hypertension, perform hepatic laboratory testing as clinically indicated; and monitor for signs and symptoms of hepatic decompensation such as the presence of jaundice, ascites, hepatic encephalopathy, and variceal hemorrhage. Discontinue VOSEVI in patients who… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described below and elsewhere in labeling: Serious Symptomatic Bradycardia When Coadministered with Amiodarone [see Warnings and Precautions (5.3) ]. The most common adverse reactions (incidence greater than or equal to 10%, all grades) observed with treatment with VOSEVI for 12 weeks were headache, fatigue, diarrhea, and nausea. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Gilead Sciences, Inc. at 1-800-GILEAD-5 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse Reactions in HCV-Infected Subjects without Cirrhosis or with Compensated Cirrhosis The adverse reactions data for VOSEVI were derived from two Phase 3 clinical trials (POLARIS-1 and POLARIS-4) that evaluated a total of 445 subjects infected with genotype 1, 2, 3, 4, 5, or 6 HCV, without cirrhosis or with compensated cirrhosis (Child-Pugh A), who received VOSEVI for 12 weeks.
VOSEVI was studied in placebo- and active-controlled (sofosbuvir/velpatasvir) trials [see Clinical Studies (14.1 and 14.2) ]. The proportion of subjects who permanently discontinued treatment due to adverse events was 0.2% for subjects who received VOSEVI for 12 weeks. The most common adverse reactions (adverse events assessed as causally related by the investigator and at least 10%) were headache, fatigue, diarrhea, and nausea in subjects treated with VOSEVI for 12 weeks.
Table 2 lists adverse reactions (adverse events assessed as causally related by the investigator, all grades) observed in at least 5% of subjects receiving 12 weeks of treatment with VOSEVI in the Phase 3 clinical trials. The side-by-side tabulation is to simplify presentation; direct comparison across trials should not be made due to differing trial designs. Table 2 Adverse Reactions (All Grades) Reported in ≥5% of Subjects With HCV Without Cirrhosis or With Compensated Cirrhosis Receiving VOSEVI in POLARIS-1 and POLARIS-4 POLARIS-1 POLARIS-4 VOSEVI 12 weeks (N=263) Placebo 12 weeks (N=152) VOSEVI 12 weeks (N=182) SOF/VEL 12 weeks (N=151) Headache 21% 14% 23% 23% Fatigue 17% 15% 19% 23% Diarrhea 13% 9% 14% 3% Nausea 13% 7% 10% 3% Asthenia 6% 4% 4% 6% Insomnia 6% 3% 3% 1% In POLARIS-1, of the subjects receiving VOSEVI who experienced adverse reactions, 99% were mild or moderate (Grade 1 or 2) in severity.
In POLARIS-4, of the subjects receiving VOSEVI who experienced adverse reactions, all the reported adverse reactions were mild or moderate (Grade 1 or 2) in severity. Less Common Adverse Reactions Reported in Clinical Trials The following adverse reactions occurred in less than 5% of subjects without cirrhosis or with compensated cirrhosis treated with VOSEVI for 12 weeks and are included because of a potential causal relationship. Rash: In the POLARIS-1 and POLARIS-4 trials, rash occurred in less than 1% and 2% of subjects treated with VOSEVI, respectively.
Rash was reported in 1% of subjects treated with placebo in POLARIS-1 and was not reported by any subject taking sofosbuvir/velpatasvir in POLARIS-4. No serious adverse reactions of rash occurred, and all rashes were mild or moderate in severity. Depression: In the POLARIS-1 and POLARIS-4 trials, depressed mood occurred in less than 1% and 1% of subjects treated with VOSEVI, respectively.
Depressed mood was not reported by any subject taking placebo in POLARIS-1 and was reported in 1% of subjects treated with sofosbuvir/velpatasvir in POLARIS-4. No serious adverse reactions of depressed mood occurred and all events were mild or moderate in severity. Laboratory Abnormalities Lipase Elevations: Isolated, asymptomatic lipase elevations of greater than 3×ULN were observed in POLARIS-1 in 2% of subjects treate… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS P-gp inducers and/or moderate to strong CYP inducers (e.g., St. John's wort, carbamazepine): May decrease concentrations of sofosbuvir, velpatasvir, and/or voxilaprevir. Use of VOSEVI with P-gp inducers and/or moderate to strong CYP inducers is not recommended.
( 5.4 , 7 ) Consult the full prescribing information prior to use for potential drug interactions. ( 4 , 5.3 , 5.4 , 7 ) Clearance of HCV infection with direct acting antivirals may lead to changes in hepatic function, which may impact safe and effective use of concomitant medications. Frequent monitoring of relevant laboratory parameters (INR or blood glucose) and dose adjustments of certain concomitant medications may be necessary.
( 7.3 )
7.1Potential for Other Drugs to Affect VOSEVI Sofosbuvir, velpatasvir, and voxilaprevir are substrates of drug transporters P-gp and BCRP while GS-331007 (predominant circulating metabolite of sofosbuvir) is not. Voxilaprevir is also a substrate of OATP1B1 and OATP1B3. In vitro, slow metabolic turnover of velpatasvir by CYP2B6, CYP2C8, and CYP3A4 and of voxilaprevir by CYP1A2, CYP2C8, and primarily CYP3A4 was observed.
Drugs that are inducers of P-gp and/or moderate to strong inducers of CYP2B6, CYP2C8, or CYP3A4 (e.g., St. John's wort, carbamazepine) may significantly decrease plasma concentrations of sofosbuvir, velpatasvir, and/or voxilaprevir leading to reduced therapeutic effect of VOSEVI. The use of these agents with VOSEVI is not recommended [see Warnings and Precautions (5.4) and Clinical Pharmacology (12.3) ].
VOSEVI may be coadministered with P-gp, BCRP, and CYP inhibitors. The use of OATP inhibitors which may substantially increase exposure of voxilaprevir (e.g., cyclosporine) with VOSEVI is not recommended [see Clinical Pharmacology (12.3) ].
7.2Potential for VOSEVI to Affect Other Drugs Velpatasvir and voxilaprevir are inhibitors of drug transporters P-gp, BCRP, OATP1B1, and OATP1B3. Velpatasvir is also an inhibitor of OATP2B1. Coadministration of VOSEVI with drugs that are substrates of these transporters may alter the exposure of such drugs.
Coadministration of VOSEVI with BCRP substrates (e.g., methotrexate, mitoxantrone, imatinib, irinotecan, lapatinib, rosuvastatin, sulfasalazine, topotecan) is not recommended [see Clinical Pharmacology (12.3) ].
7.3Established and Potentially Significant Drug Interactions Clearance of HCV infection with direct acting antivirals may lead to changes in hepatic function, which may impact the safe and effective use of concomitant medications. For example, altered blood glucose control resulting in serious symptomatic hypoglycemia has been reported in diabetic patients in postmarketing case reports and published epidemiological studies. Management of hypoglycemia in these cases required either discontinuation or dose modification of concomitant medications used for diabetes treatment.
Frequent monitoring of relevant laboratory parameters (e.g., International Normalized Ratio [INR] in patients taking warfarin, blood glucose levels in diabetic patients) or drug concentrations of concomitant medications such as cytochrome P450 substrates with a narrow therapeutic index (e.g., certain immunosuppressants) is recommended to ensure safe and effective use. Dose adjustments of concomitant medications may be necessary. Table 3 provides a listing of established or potentially clinically significant drug interactions.
The drug interactions described are based on studies conducted with either VOSEVI, the components of VOSEVI (sofosbuvir, velpatasvir, and/or voxilaprevir), or are predicted drug interactions that may occur with VOSEVI [see Contraindications (4) , Warnings and Precautions (5.3 , 5.4) , and Clinical Pharmacology (12.3) ]. Table 3 Potentially Significant Drug Interactions: Alteration in Dose or Regimen May Be Recommended Based on Drug Interaction Studies or Predicted Interaction This table is not all inclusive. Concomitant Drug Class: Drug Name Effect on Concentra… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary No adequate human data are available to establish whether or not VOSEVI poses a risk to pregnancy outcomes. In animal reproduction studies, no evidence of adverse developmental outcomes was observed with the components of VOSEVI (sofosbuvir, velpatasvir, or voxilaprevir) at exposures greater than those in humans at the recommended human dose (RHD) [see Data ] . During organogenesis in the mouse, rat, and rabbit, systemic exposures (AUC) of velpatasvir were approximately 23 (mice), 4 (rats), and 0.5 (rabbits) times the exposure in humans at the RHD, while exposures of voxilaprevir were approximately 141 (rats) and 4 (rabbits) times the exposure in humans at the RHD.
Exposures of the predominant circulating metabolite of sofosbuvir (GS-331007) were approximately 6 (rats) and 16 (rabbits) times the exposure in humans at the RHD. In rat pre/postnatal development studies, maternal systemic exposures (AUC) for each component of VOSEVI were approximately 7 (sofosbuvir metabolite GS-331007), 3 (velpatasvir), and 238 (voxilaprevir) times the exposure in humans at the RHD. The background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Data Sofosbuvir: Sofosbuvir was administered orally to pregnant rats (up to 500 mg/kg/day) and rabbits (up to 300 mg/kg/day) on gestation days 6 to 18 and 6 to 19, respectively, and also to rats (oral doses up to 500 mg/kg/day) from gestation day 6 to lactation/post-partum day 20. No significant effects on embryo-fetal (rats and rabbits) or pre/postnatal (rats) development were observed at the highest doses tested.
The systemic exposures (AUC) of the predominant circulating metabolite of sofosbuvir (GS-331007) during gestation were approximately 6 (rats) and 16 (rabbits) times the exposure in humans at the RHD. Velpatasvir: Velpatasvir was administered orally to pregnant mice (up to 1000 mg/kg/day), rats (up to 200 mg/kg/day) and rabbits (up to 300 mg/kg/day) from gestation days 6 to 15, 6 to 17, and 7 to 20, respectively, and also to rats (oral doses up to 200 mg/kg) on gestation day 6 to lactation/post-partum day 20. No significant effects on embryo-fetal (mice, rats, and rabbits) or pre/postnatal (rats) development were observed at the highest doses tested.
The systemic exposures (AUC) of velpatasvir during gestation were approximately 23 (mice), 4 (rats), and 0.5 (rabbits) times the exposure in humans at the RHD. Voxilaprevir: Voxilaprevir was administered orally to pregnant rats (up to 100 mg/kg/day) and rabbits (up to 600 mg/kg/day) from gestation days 6 to 17, and 7 to 19, respectively, and also to rats (oral doses up to 100 mg/kg) on gestation day 6 to lactation/post-partum day 20. No significant effects on embryo-fetal (rats and rabbits) or pre/postnatal (rats) development were observed at the highest doses tested.
The systemic exposures (AUC) of voxilaprevir during gestation were approximately 141 (rats) and 4 (rabbits) times the exposure in humans at the RHD.
8.2Lactation Risk Summary It is not known whether the components of VOSEVI and its metabolites are present in human breast milk, affect human milk production, or have effects on the breastfed infant. When the components of VOSEVI were administered to lactating rats, GS-331007 (the predominant circulating metabolite of sofosbuvir) and velpatasvir were detected in milk, while voxilaprevir was detected in the plasma of nursing pups likely due to the presence of voxilaprevir in milk. No significant effects of any of the drugs were observed in nursing rat pups [see Data ].
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for VOSEVI and any potential adverse effects on the breastfed child from VOSEVI or from the underlyi… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary No adequate human data are available to establish whether or not VOSEVI poses a risk to pregnancy outcomes. In animal reproduction studies, no evidence of adverse developmental outcomes was observed with the components of VOSEVI (sofosbuvir, velpatasvir, or voxilaprevir) at exposures greater than those in humans at the recommended human dose (RHD) [see Data ] . During organogenesis in the mouse, rat, and rabbit, systemic exposures (AUC) of velpatasvir were approximately 23 (mice), 4 (rats), and 0.5 (rabbits) times the exposure in humans at the RHD, while exposures of voxilaprevir were approximately 141 (rats) and 4 (rabbits) times the exposure in humans at the RHD.
Exposures of the predominant circulating metabolite of sofosbuvir (GS-331007) were approximately 6 (rats) and 16 (rabbits) times the exposure in humans at the RHD. In rat pre/postnatal development studies, maternal systemic exposures (AUC) for each component of VOSEVI were approximately 7 (sofosbuvir metabolite GS-331007), 3 (velpatasvir), and 238 (voxilaprevir) times the exposure in humans at the RHD. The background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Data Sofosbuvir: Sofosbuvir was administered orally to pregnant rats (up to 500 mg/kg/day) and rabbits (up to 300 mg/kg/day) on gestation days 6 to 18 and 6 to 19, respectively, and also to rats (oral doses up to 500 mg/kg/day) from gestation day 6 to lactation/post-partum day 20. No significant effects on embryo-fetal (rats and rabbits) or pre/postnatal (rats) development were observed at the highest doses tested.
The systemic exposures (AUC) of the predominant circulating metabolite of sofosbuvir (GS-331007) during gestation were approximately 6 (rats) and 16 (rabbits) times the exposure in humans at the RHD. Velpatasvir: Velpatasvir was administered orally to pregnant mice (up to 1000 mg/kg/day), rats (up to 200 mg/kg/day) and rabbits (up to 300 mg/kg/day) from gestation days 6 to 15, 6 to 17, and 7 to 20, respectively, and also to rats (oral doses up to 200 mg/kg) on gestation day 6 to lactation/post-partum day 20. No significant effects on embryo-fetal (mice, rats, and rabbits) or pre/postnatal (rats) development were observed at the highest doses tested.
The systemic exposures (AUC) of velpatasvir during gestation were approximately 23 (mice), 4 (rats), and 0.5 (rabbits) times the exposure in humans at the RHD. Voxilaprevir: Voxilaprevir was administered orally to pregnant rats (up to 100 mg/kg/day) and rabbits (up to 600 mg/kg/day) from gestation days 6 to 17, and 7 to 19, respectively, and also to rats (oral doses up to 100 mg/kg) on gestation day 6 to lactation/post-partum day 20. No significant effects on embryo-fetal (rats and rabbits) or pre/postnatal (rats) development were observed at the highest doses tested.
The systemic exposures (AUC) of voxilaprevir during gestation were approximately 141 (rats) and 4 (rabbits) times the exposure in humans at the RHD.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of VOSEVI have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of VOSEVI included 74 subjects aged 65 and over (17% of total number of subjects in the POLARIS-1 and POLARIS-4 Phase 3 clinical trials). No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. No dosage adjustment of VOSEVI is warranted in geriatric patients [see Clinical Pharmacology (12.3) ].
🆘 Overdosage ▾
10 OVERDOSAGE No specific antidote is available for overdose with VOSEVI. If overdose occurs the patient must be monitored for evidence of toxicity. Treatment of overdose with VOSEVI consists of general supportive measures including monitoring of vital signs as well as observation of the clinical status of the patient.
Hemodialysis can efficiently remove the predominant circulating metabolite of sofosbuvir, GS-331007, with an extraction ratio of 53%. Hemodialysis is unlikely to result in significant removal of velpatasvir or voxilaprevir since velpatasvir and voxilaprevir are highly bound to plasma protein.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action VOSEVI is a fixed-dose combination of sofosbuvir, velpatasvir, and voxilaprevir which are DAA agents against the hepatitis C virus [see Microbiology (12.4) ].
12.2Pharmacodynamics Cardiac Electrophysiology The effect of sofosbuvir 400 mg (recommended dosage) and 1200 mg (3 times the recommended dosage) on QTc interval was evaluated in an active-controlled (moxifloxacin 400 mg) thorough QT trial. At a dose 3 times the recommended dose, sofosbuvir does not prolong QTc to any clinically relevant extent. The effect of velpatasvir 500 mg (5 times the recommended dosage) was evaluated in an active-controlled (moxifloxacin 400 mg) thorough QT trial.
At a dose 5 times the recommended dose, velpatasvir does not prolong QTc interval to any clinically relevant extent. The effect of voxilaprevir 900 mg (9 times the recommended dosage) was evaluated in an active-controlled (moxifloxacin 400 mg) thorough QT trial. At a dose 9 times the recommended dose, voxilaprevir does not prolong QTc interval to any clinically relevant extent.
12.3Pharmacokinetics The pharmacokinetic properties of the components of VOSEVI are provided in Table 4. The multiple dose pharmacokinetic parameters of sofosbuvir and its metabolite GS-331007, velpatasvir, and voxilaprevir are provided in Table 5. Table 4 Pharmacokinetic Properties of the Components of VOSEVI Sofosbuvir Velpatasvir Voxilaprevir CES1 = carboxylesterase 1; HINT1 = histidine triad nucleotide-binding protein 1.
Absorption T max (h) 2 4 4 Effect of food (relative to fasting) Values refer to geometric mean systemic exposure. VOSEVI should be taken with food. ↑ 64% to 144% ↑ 40% to 166% ↑ 112% to 435% Distribution % Bound to human plasma proteins 61–65 >99 >99 Blood-to-plasma ratio 0.7 0.5–0.7 0.5–0.8 Metabolism Metabolism Cathepsin A CES1 HINT1 CYP2B6 CYP2C8 CYP3A4 CYP3A4 Elimination Major route of elimination SOF: metabolism GS-331007 GS-331007 is the primary circulating nucleotide metabolite of SOF. : glomerular filtration and active tubular secretion Biliary excretion Biliary excretion t 1/2 (h) t 1/2 values refer to median terminal plasma half-life.
SOF:
0.5GS-331007 : 29 17 33 % Of dose excreted in urine Single dose administration of [ 14 C] SOF, [ 14 C] VEL, [ 14 C] VOX in mass balance studies. 80 Predominantly as GS-331007. 0.4 0 % Of dose excreted in feces 14 94 (77% Percent of dose. as parent) 94 (40% as parent) Table 5 Multiple Dose Pharmacokinetic Parameters of Sofosbuvir and its Metabolite, GS-331007, Velpatasvir, and Voxilaprevir Following Oral Administration in HCV-Infected Adults Parameter Mean (%CV) Sofosbuvir From Population PK analysis, N = 1038 GS-331007 From Population PK analysis, N = 1593 Velpatasvir From Population PK analysis, N = 1595 Voxilaprevir From Population PK analysis, N = 1591 CV = coefficient of variation; NA = not applicable.
C max (nanogram per mL) 678 (35.4) 744 (28.3) 311 (56.1) 192 (85.8) AUC tau (nanogram∙hr per mL) 1665 (30.1) 12834 (29.0) 4041 (48.6) 2577 (73.7) C trough (nanogram per mL) NA NA 51 (64.7) 47 (82.0) Sofosbuvir and GS-331007 AUC 0–24 and C max were similar in healthy adult subjects and subjects with HCV infection. Relative to healthy subjects (N=137), velpatasvir AUC 0–24 and C max were 41% lower and 39% lower, respectively, in HCV-infected subjects. Relative to healthy subjects (N=63), voxilaprevir AUC 0–24 and C max were both 260% higher in HCV-infected subjects.
Sofosbuvir and GS-331007 AUCs are near dose-proportional over the dose range of 200 mg to 1200 mg. Velpatasvir AUC increases in a greater than proportional manner from 5 to 50 mg and in a less than proportional manner from 50 to 450 mg in healthy volunteers. However, velpatasvir exhibited near dose-proportional increase in exposures 25 mg to 150 mg in HCV-infected patients.
Voxilaprevir AUC increases in a greater than proportional manner over the dose range of 100 to 900 mg when administered with food. Specific Populations Pediatric Pa… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action VOSEVI is a fixed-dose combination of sofosbuvir, velpatasvir, and voxilaprevir which are DAA agents against the hepatitis C virus [see Microbiology (12.4) ].
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Each VOSEVI tablet contains 400 mg of sofosbuvir, 100 mg of velpatasvir, and 100 mg of voxilaprevir. The tablets are beige, capsule-shaped, film-coated, and debossed with "GSI" on one side and " " on the other side. Each bottle contains 28 tablets (NDC 61958-2401-1), polyester coil, silica gel desiccant, and is closed with a child-resistant closure. Store below 30 °C (86 °F). Dispense only in original container.
📦 Storage and Handling ▾
Store below 30 °C (86 °F). Dispense only in original container.
📋 Description ▾
11 DESCRIPTION VOSEVI is a fixed-dose combination tablet containing sofosbuvir, velpatasvir, and voxilaprevir for oral administration. Sofosbuvir is a nucleotide analog HCV NS5B polymerase inhibitor, velpatasvir is an NS5A inhibitor, and voxilaprevir is an NS3/4A protease inhibitor. Each tablet contains 400 mg sofosbuvir, 100 mg velpatasvir, and 100 mg of voxilaprevir.
The tablets include the following inactive ingredients: colloidal silicon dioxide, copovidone, croscarmellose sodium, lactose monohydrate, magnesium stearate, and microcrystalline cellulose. The tablets are film-coated with a coating material containing the following inactive ingredients: ferrosoferric oxide, iron oxide red, iron oxide yellow, polyethylene glycol, polyvinyl alcohol, talc, and titanium dioxide. Sofosbuvir: The IUPAC name for sofosbuvir is ( S )-Isopropyl 2-(( S )-(((2 R ,3 R ,4 R ,5 R )-5-(2,4-dioxo-3,4-dihydropyrimidin-1(2 H )-yl)-4-fluoro-3-hydroxy-4-methyltetrahydrofuran-2-yl)methoxy)-(phenoxy)phosphorylamino)propanoate.
It has a molecular formula of C 22 H 29 FN 3 O 9 P and a molecular weight of 529.45. It has the following structural formula: Sofosbuvir is a white to off-white crystalline solid with a solubility of at least 2 mg/mL across the pH range of 2–7.7 at 37 °C and is slightly soluble in water. Chemical Structure Velpatasvir: The IUPAC name for velpatasvir is Methyl {(1 R )-2-[(2 S ,4 S )-2-(5-{2-[(2 S ,5 S )-1-{(2 S )-2-[(methoxycarbonyl)amino]-3-methylbutanoyl}-5-methylpyrrolidin-2-yl]-1,11-dihydro[2]benzopyrano[4',3':6,7]naphtho[1,2- d ]imidazol-9-yl}-1 H -imidazol-2-yl)-4-(methoxymethyl)pyrrolidin-1-yl]-2-oxo-1-phenylethyl}carbamate.
It has a molecular formula of C 49 H 54 N 8 O 8 and a molecular weight of 883.0. It has the following structural formula: Velpatasvir is practically insoluble (less than 0.1 mg/mL) above pH 5, slightly soluble (3.6 mg/mL) at pH 2, and soluble (greater than 36 mg/mL) at pH 1.2. Chemical Structure Voxilaprevir: The IUPAC name for voxilaprevir is (1 aR ,5 S ,8 S ,9 S ,10 R ,22a R )-5- tert -butyl- N -{(1 R ,2 R )-2-(difluoromethyl)-1-[(1-methylcyclopropanesulfonyl) carbamoyl]cyclopropyl}-9-ethyl-18,18-difluoro-14-methoxy-3,6-dioxo-1,1 a ,3,4,5,6,9,10,18,19,20,21,22,22 a -tetradecahydro-8 H -7,10-methanocyclopropa[18,19][1,10,3,6]dioxadiazacyclononadecino[11,12- b ]quinoxaline-8-carboxamide.
It has a molecular formula of C 40 H 52 F 4 N 6 O 9 S and a molecular weight of 868.9. It has the following structural formula: Voxilaprevir is a white to light brown solid. It is slightly hygroscopic to hygroscopic.
Voxilaprevir is practically insoluble (less than 0.1 mg/mL) below pH 6.8. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Risk of Hepatitis B Virus Reactivation in Patients Coinfected with HCV and HBV Inform patients that HBV reactivation can occur in patients coinfected with HBV during or after treatment of HCV virus infection. Advise patients to tell their healthcare provider if they have a history of hepatitis B infection [see Warnings and Precautions (5.1) ].
Risk of Hepatic Decompensation/Failure in Patients with Evidence of Advanced Liver Disease Advise patients to seek medical evaluation immediately for symptoms of worsening liver problems such as nausea, tiredness, yellowing of the skin or white part of the eyes, bleeding or bruising more easily than normal, confusion, loss of appetite, diarrhea, dark or brown urine, dark or bloody stool, swelling of the stomach area (abdomen) or pain in the upper right side of the stomach area, sleepiness, or vomiting of blood [see Warnings and Precautions (5.2) ].
Serious Symptomatic Bradycardia When Coadministered with Amiodarone Advise patients to seek medical evaluation immediately for symptoms of bradycardia such as near-fainting or fainting, dizziness or lightheadedness, malaise, weakness, excessive tiredness, shortness of breath, chest pain, confusion, or memory problems [see Warnings and Precautions (5.3) , Adverse Reactions (6.2) , and Drug Interactions (7.3) ]. Drug Interactions Inform patients that VOSEVI may interact with other drugs. Advise patients to report to their healthcare provider the use of any other prescription or nonprescription medication or herbal products including St.
John's wort [see Warnings and Precautions (5.3 , 5.4) and Drug Interactions (7) ]. Administration Advise patients to take VOSEVI once daily on a regular dosing schedule with food. Inform patients that it is important not to miss or skip doses and to take VOSEVI for the duration that is recommended by the physician.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetic properties of the components of VOSEVI are provided in Table 4. The multiple dose pharmacokinetic parameters of sofosbuvir and its metabolite GS-331007, velpatasvir, and voxilaprevir are provided in Table 5. Table 4 Pharmacokinetic Properties of the Components of VOSEVI Sofosbuvir Velpatasvir Voxilaprevir CES1 = carboxylesterase 1; HINT1 = histidine triad nucleotide-binding protein 1.
Absorption T max (h) 2 4 4 Effect of food (relative to fasting) Values refer to geometric mean systemic exposure. VOSEVI should be taken with food. ↑ 64% to 144% ↑ 40% to 166% ↑ 112% to 435% Distribution % Bound to human plasma proteins 61–65 >99 >99 Blood-to-plasma ratio 0.7 0.5–0.7 0.5–0.8 Metabolism Metabolism Cathepsin A CES1 HINT1 CYP2B6 CYP2C8 CYP3A4 CYP3A4 Elimination Major route of elimination SOF: metabolism GS-331007 GS-331007 is the primary circulating nucleotide metabolite of SOF. : glomerular filtration and active tubular secretion Biliary excretion Biliary excretion t 1/2 (h) t 1/2 values refer to median terminal plasma half-life.
SOF:
0.5GS-331007 : 29 17 33 % Of dose excreted in urine Single dose administration of [ 14 C] SOF, [ 14 C] VEL, [ 14 C] VOX in mass balance studies. 80 Predominantly as GS-331007. 0.4 0 % Of dose excreted in feces 14 94 (77% Percent of dose. as parent) 94 (40% as parent) Table 5 Multiple Dose Pharmacokinetic Parameters of Sofosbuvir and its Metabolite, GS-331007, Velpatasvir, and Voxilaprevir Following Oral Administration in HCV-Infected Adults Parameter Mean (%CV) Sofosbuvir From Population PK analysis, N = 1038 GS-331007 From Population PK analysis, N = 1593 Velpatasvir From Population PK analysis, N = 1595 Voxilaprevir From Population PK analysis, N = 1591 CV = coefficient of variation; NA = not applicable.
C max (nanogram per mL) 678 (35.4) 744 (28.3) 311 (56.1) 192 (85.8) AUC tau (nanogram∙hr per mL) 1665 (30.1) 12834 (29.0) 4041 (48.6) 2577 (73.7) C trough (nanogram per mL) NA NA 51 (64.7) 47 (82.0) Sofosbuvir and GS-331007 AUC 0–24 and C max were similar in healthy adult subjects and subjects with HCV infection. Relative to healthy subjects (N=137), velpatasvir AUC 0–24 and C max were 41% lower and 39% lower, respectively, in HCV-infected subjects. Relative to healthy subjects (N=63), voxilaprevir AUC 0–24 and C max were both 260% higher in HCV-infected subjects.
Sofosbuvir and GS-331007 AUCs are near dose-proportional over the dose range of 200 mg to 1200 mg. Velpatasvir AUC increases in a greater than proportional manner from 5 to 50 mg and in a less than proportional manner from 50 to 450 mg in healthy volunteers. However, velpatasvir exhibited near dose-proportional increase in exposures 25 mg to 150 mg in HCV-infected patients.
Voxilaprevir AUC increases in a greater than proportional manner over the dose range of 100 to 900 mg when administered with food. Specific Populations Pediatric Patients: The pharmacokinetics of VOSEVI in pediatric patients has not been established [see Use in Specific Populations (8.4) ]. Geriatric Patients: Population pharmacokinetic analysis in HCV-infected subjects showed that within the age range (18 to 85 years) analyzed, age did not have a clinically relevant effect on the exposure to sofosbuvir, GS-331007, velpatasvir, or voxilaprevir [see Use in Specific Populations (8.5) ].
Patients with Renal Impairment: The pharmacokinetics of sofosbuvir were studied in HCV-negative subjects with mild (eGFR between 50 to less than 80 mL/min/1.73 m 2 ), moderate (eGFR between 30 to less than 50 mL/min/1.73 m 2 ), severe renal impairment (eGFR less than 30 mL/min/1.73 m 2 ), and subjects with ESRD requiring hemodialysis following a single 400 mg dose of sofosbuvir. Relative to subjects with normal renal function (eGFR greater than 80 mL/min/1.73 m 2 ), the sofosbuvir AUC 0–inf was 61%, 107%, and 171% higher in subjects with mild, moderate, and severe renal impairment, while the GS-331007 AUC 0–inf was 55%, 88%, and 451% higher, respe… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Cardiac Electrophysiology The effect of sofosbuvir 400 mg (recommended dosage) and 1200 mg (3 times the recommended dosage) on QTc interval was evaluated in an active-controlled (moxifloxacin 400 mg) thorough QT trial. At a dose 3 times the recommended dose, sofosbuvir does not prolong QTc to any clinically relevant extent. The effect of velpatasvir 500 mg (5 times the recommended dosage) was evaluated in an active-controlled (moxifloxacin 400 mg) thorough QT trial.
At a dose 5 times the recommended dose, velpatasvir does not prolong QTc interval to any clinically relevant extent. The effect of voxilaprevir 900 mg (9 times the recommended dosage) was evaluated in an active-controlled (moxifloxacin 400 mg) thorough QT trial. At a dose 9 times the recommended dose, voxilaprevir does not prolong QTc interval to any clinically relevant extent.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Description of Clinical Trials The efficacy of VOSEVI was evaluated in two Phase 3 trials in DAA-experienced subjects with genotype 1, 2, 3, 4, 5, or 6 HCV infection without cirrhosis or with compensated cirrhosis, as summarized in Table 8. Table 8 Trials Conducted With VOSEVI in DAA-Experienced Subjects With HCV Infection Trial Population Study Arms and Comparator Groups (Number of Subjects Treated) DAA: direct-acting antiviral; SOF: sofosbuvir; VEL: velpatasvir POLARIS-1 Double-blind, placebo-controlled. (NCT02607735) Genotype 1, 2, 3, 4, 5, or 6 NS5A inhibitor-experienced In clinical trials, prior NS5A inhibitor experience included daclatasvir, elbasvir, ledipasvir, ombitasvir, or velpatasvir. , without cirrhosis or with compensated cirrhosis VOSEVI 12 weeks (263) Placebo 12 weeks (152) POLARIS-4 Open-label.
(NCT02639247) Genotype 1, 2, 3, or 4 DAA-experienced In clinical trials, prior treatment experience included sofosbuvir with or without any of the following: peginterferon alfa/ribavirin, ribavirin, HCV NS3/4A protease inhibitor (boceprevir, simeprevir, or telaprevir). who have not received an NS5A inhibitor, without cirrhosis or with compensated cirrhosis VOSEVI 12 weeks (182) SOF/VEL 12 weeks (151) Serum HCV RNA values were measured during the clinical trials using the COBAS AmpliPrep/COBAS Taqman HCV test (version 2.0) with a lower limit of quantification (LLOQ) of 15 IU/mL.
Sustained virologic response (SVR12), defined as HCV RNA less than LLOQ at 12 weeks after the cessation of treatment, was the primary endpoint in both trials. Relapse is defined as HCV RNA greater than or equal to LLOQ after end-of-treatment response among subjects who completed treatment. On-treatment virologic failure is defined as breakthrough, rebound, or non-response.
14.2Clinical Trials in HCV DAA-Experienced Subjects NS5A Inhibitor-Experienced Adults Without Cirrhosis or With Compensated Cirrhosis (POLARIS-1) POLARIS-1 was a randomized, double-blind, placebo-controlled trial that evaluated 12 weeks of treatment with VOSEVI compared with 12 weeks of placebo in DAA-experienced subjects with genotype 1, 2, 3, 4, 5, or 6 HCV infection without cirrhosis or with compensated cirrhosis who previously failed a regimen containing an NS5A inhibitor. Subjects with genotype 1 HCV infection were randomized 1:1 to each group.
Subjects with genotype 2, 3, 4, 5, or 6 HCV infection were enrolled to the VOSEVI group. Randomization was stratified by the presence or absence of cirrhosis. Demographics and baseline characteristics were generally balanced across treatment groups.
Of the 415 treated subjects, the median age was 59 years (range: 27 to 84); 77% of the subjects were male; 81% were White; 14% were Black; 6% were Hispanic or Latino; 33% had a baseline body mass index at least 30 kg/m 2 ; the majority of subjects had genotype 1 (72%) or genotype 3 (19%) HCV infection; 82% had a non-CC IL28B genotype (CT or TT); 74% had baseline HCV RNA levels at least 800,000 IU/mL; and 41% had compensated cirrhosis. In the POLARIS-1 trial, prior DAA regimens contained the following NS5A inhibitors: ledipasvir (51%), daclatasvir (27%), ombitasvir (11%), velpatasvir (7%), and elbasvir (3%).
Table 9 presents the SVR12 by HCV genotype for the POLARIS-1 trial. No subjects in the placebo group achieved SVR12. Table 9 POLARIS-1 Trial: Virologic Outcomes by HCV Genotype in VOSEVI-Treated Subjects Without Cirrhosis or With Compensated Cirrhosis (12 Weeks After Treatment) VOSEVI 12 Weeks (N=263) Total (all GTs) One subject with undetermined genotype achieved SVR12.
(N=263) GT-1 GT-2 (N=5) GT-3 (N=78) GT-4 (N=22) GT-5 (N=1) GT-6 (N=6) GT-1a (N=101) GT-1b (N=45) Total Four subjects had GT-1 subtypes other than GT-1a or GT-1b; all 4 subjects achieved SVR12. (N=150) GT: genotype SVR12 96% (253/263) 96% (97/101) 100% (45/45) 97% (146/150) 100% (5/5) 95% (74/78) 91% (20/22) 100% (1/1) 100% (6/6) Outcome for Subjects without SVR On-Treatment Virologic Failure… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis and Mutagenesis Sofosbuvir: Sofosbuvir was not genotoxic in a battery of in vitro or in vivo assays, including bacterial mutagenicity, chromosome aberration using human peripheral blood lymphocytes, and in vivo mouse micronucleus assays. Sofosbuvir was not carcinogenic in a 2-year mouse study (up to 200 mg/kg/day in males and 600 mg/kg/day in females) and in a 2-year rat study (up to 750 mg/kg/day), resulting in exposures of the predominant circulating metabolite GS-331007 of approximately 4 and 17 times (in male and female mice, respectively) and 9 times (in rats) the exposure in humans at the recommended human dose (RHD).
Velpatasvir: Velpatasvir was not genotoxic in a battery of in vitro or in vivo assays, including bacterial mutagenicity, chromosome aberration using human peripheral blood lymphocytes, and in vivo rat micronucleus assays. Velpatasvir was not carcinogenic in a 6-month rasH2 transgenic mouse study (up to 1000 mg/kg/day) and a 2-year rat carcinogenicity study (up to 200 mg/kg/day). The exposure of VEL in the 2-year rat study was approximately 6 times the exposure in humans at the RHD.
Voxilaprevir: Voxilaprevir was not genotoxic in a battery of in vitro or in vivo assays, including bacterial mutagenicity, chromosome aberration using human peripheral blood lymphocytes, and in vivo rat micronucleus assays. Carcinogenicity studies for voxilaprevir have not been conducted. Impairment of Fertility Sofosbuvir: Sofosbuvir had no effects on embryo-fetal viability or on fertility when evaluated in rats.
At the highest dose tested, AUC exposure to the predominant circulating metabolite GS-331007 was approximately 4 times the exposure in humans at the RHD. Velpatasvir: Velpatasvir had no effects on embryo-fetal viability or on fertility when evaluated in rats. At the highest dose tested, velpatasvir exposure was approximately 4 times the exposure in humans at the RHD.
Voxilaprevir: Voxilaprevir had no effects on embryo-fetal viability or on fertility when evaluated in rats. At the highest dose tested, voxilaprevir exposure was approximately 149 times the exposure in humans at the RHD.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis and Mutagenesis Sofosbuvir: Sofosbuvir was not genotoxic in a battery of in vitro or in vivo assays, including bacterial mutagenicity, chromosome aberration using human peripheral blood lymphocytes, and in vivo mouse micronucleus assays. Sofosbuvir was not carcinogenic in a 2-year mouse study (up to 200 mg/kg/day in males and 600 mg/kg/day in females) and in a 2-year rat study (up to 750 mg/kg/day), resulting in exposures of the predominant circulating metabolite GS-331007 of approximately 4 and 17 times (in male and female mice, respectively) and 9 times (in rats) the exposure in humans at the recommended human dose (RHD).
Velpatasvir: Velpatasvir was not genotoxic in a battery of in vitro or in vivo assays, including bacterial mutagenicity, chromosome aberration using human peripheral blood lymphocytes, and in vivo rat micronucleus assays. Velpatasvir was not carcinogenic in a 6-month rasH2 transgenic mouse study (up to 1000 mg/kg/day) and a 2-year rat carcinogenicity study (up to 200 mg/kg/day). The exposure of VEL in the 2-year rat study was approximately 6 times the exposure in humans at the RHD.
Voxilaprevir: Voxilaprevir was not genotoxic in a battery of in vitro or in vivo assays, including bacterial mutagenicity, chromosome aberration using human peripheral blood lymphocytes, and in vivo rat micronucleus assays. Carcinogenicity studies for voxilaprevir have not been conducted. Impairment of Fertility Sofosbuvir: Sofosbuvir had no effects on embryo-fetal viability or on fertility when evaluated in rats.
At the highest dose tested, AUC exposure to the predominant circulating metabolite GS-331007 was approximately 4 times the exposure in humans at the RHD. Velpatasvir: Velpatasvir had no effects on embryo-fetal viability or on fertility when evaluated in rats. At the highest dose tested, velpatasvir exposure was approximately 4 times the exposure in humans at the RHD.
Voxilaprevir: Voxilaprevir had no effects on embryo-fetal viability or on fertility when evaluated in rats. At the highest dose tested, voxilaprevir exposure was approximately 149 times the exposure in humans at the RHD.
📄 Patient Package Insert ▾
This Patient Information has been approved by the U.S. Food and Drug Administration. Revised: 11/2019 Patient Information VOSEVI ® (voh-SEV-ee) (sofosbuvir, velpatasvir, and voxilaprevir) tablets What is the most important information I should know about VOSEVI?
VOSEVI can cause serious side effects, including, Hepatitis B virus reactivation: Before starting treatment with VOSEVI, your healthcare provider will do blood tests to check for hepatitis B virus infection. If you have ever had hepatitis B virus infection, the hepatitis B virus could become active again during or after treatment of hepatitis C virus with VOSEVI. Hepatitis B virus becoming active again (called reactivation) may cause serious liver problems including liver failure and death.
Your healthcare provider will monitor you if you are at risk for hepatitis B virus reactivation during treatment and after you stop taking VOSEVI. For more information about side effects, see the section " What are the possible side effects of VOSEVI? " What is VOSEVI? VOSEVI is a prescription medicine used to treat adults with chronic (lasting a long time) hepatitis C virus (HCV) infection without cirrhosis or with compensated cirrhosis who have: genotype 1, 2, 3, 4, 5, or 6 infection and have previously been treated with an HCV regimen containing an NS5A inhibitor. genotype 1a or 3 infection and have previously been treated with an HCV regimen containing sofosbuvir without an NS5A inhibitor.
It is not known if VOSEVI is safe and effective in children. Do not take VOSEVI: if you also take any medicines that contain rifampin (Rifater ® , Rifamate ® , Rimactane ® , Rifadin ® ) Before taking VOSEVI, tell your healthcare provider about all your medical conditions, including if you: have ever had hepatitis B infection have liver problems other than hepatitis C infection are pregnant or plan to become pregnant. It is not known if VOSEVI will harm your unborn baby. are breastfeeding or plan to breastfeed.
It is not known if VOSEVI passes into your breast milk. Talk to your healthcare provider about the best way to feed your baby if you take VOSEVI. Tell your healthcare provider about all of the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements.
VOSEVI and other medicines may affect each other. This can cause you to have too much or not enough VOSEVI or other medicines in your body. This may affect the way VOSEVI or your other medicines work or may cause side effects.
Keep a list of your medicines to show your healthcare provider and pharmacist. You can ask your healthcare provider or pharmacist for a list of medicines that interact with VOSEVI. Do not start taking a new medicine without telling your healthcare provider.
Your healthcare provider can tell you if it is safe to take VOSEVI with other medicines. How should I take VOSEVI? Take VOSEVI exactly as your healthcare provider tells you.
Do not change your dose unless your healthcare provider tells you to. Do not stop taking VOSEVI without first talking with your healthcare provider. Take 1 VOSEVI tablet by mouth each day on a regular schedule.
Take VOSEVI with food. If you need to take an antacid medicine that contains aluminum or magnesium, take it either 4 hours before or 4 hours after you take your dose of VOSEVI. It is important that you do not miss or skip doses of VOSEVI during treatment.
If you take too much VOSEVI, call your healthcare provider or go to the nearest hospital emergency room right away. What are the possible side effects of VOSEVI? VOSEVI may cause serious side effects, including: Hepatitis B virus (HBV) reactivation.
See " What is the most important information I should know about VOSEVI? " In people who had or have advanced liver problems before starting treatment with VOSEVI: rare risk of worsening liver problems, liver failure and death. Your healthcare provider will check you for signs and symptoms of worsening liver problems during treatment with VOS… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Dosage and Administration, Renal Impairment ( 2.3 ) 11/2019 Warnings and Precautions, Risk of Hepatic Decompensation/Failure in Patients with Evidence of Advanced Liver Disease ( 5.2 ) 09/2019
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 28 Tablet Bottle Label NDC 61958- 2401 -1 28 tablets Vosevi™ (sofosbuvir, velpatasvir, and voxilaprevir) tablets 400 mg / 100 mg / 100 mg Take 1 tablet once daily Note to pharmacist: Do not cover ALERT box with pharmacy label. ALERT: Find out about medicines that should NOT be taken with Vosevi PRINCIPAL DISPLAY PANEL - 28 Tablet Bottle Label
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |