
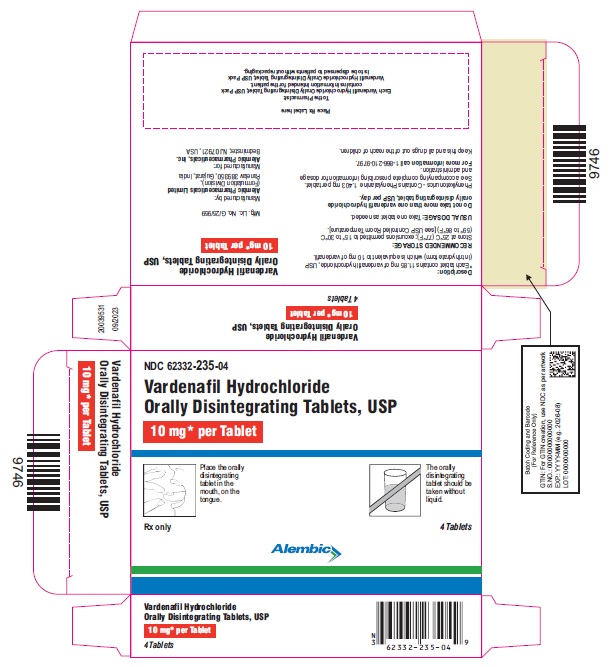
Vardenafil 10 mg Tablet, Orally Disintegrating — NDC 62332-235-04 (Billing 62332-0235-04)
This is a package of Vardenafil 10 mg Tablet, Orally Disintegrating from Alembic Pharmaceuticals Inc., marketed since Nov 2018 and currently FDA-listed; retail pharmacies pay about $23.33 per unit (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 62332-235-04 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 62332 labeler · 235 product · 04 package
- Package marketed since
- Nov 20, 2018
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 6233223504 9
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 067179
- GCN: 29673
- GPI-14 (Medi-Span): 40304090107230
- HICL (First Databank): 025035
- AHFS class code: 24:08.12.00
- RxCUI (RxNorm): 996179
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Phosphodiesterase 5 Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Vardenafil is used to treat erectile dysfunction (impotence; inability to get or keep an erection) in men. Vardenafil is in a class of medications called phosphodiesterase (PDE) inhibitors. It works by increasing blood flow to the penis during sexual stimulation. This increased blood flow can cause an erection. Vardenafil does not cure erectile dysfunction or increase sexual desire. Vardenafil does not prevent pregnancy or the spread of sexually transmitted diseases such as human immunodeficiency virus (HIV).
Read the full MedlinePlus article ↗- Generally, you should take vardenafil about 60 minutes before sexual activity — that's when it tends to work best. For the standard tablet, food doesn't really matter; you can take...
- How long before sex should I take vardenafil, and does it matter if I eat first?
- This is really important to go over with your doctor. If you take any nitrate medications — like nitroglycerin for chest pain — you absolutely cannot take vardenafil. The combinati...
- Can I take vardenafil with my other heart or blood pressure medications?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Vardenafil — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $23.327 | $373.23 / 16 tablets |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 5, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 62332-0235-04 You're viewing this Main listing | 4 BLISTER PACK in 1 CARTON / 4 TABLET, ORALLY DISINTEGRATING in 1 BLISTER PACK | 2018-11-20 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Vardenafil 11.85 mg 33342-0203-37 | Macleods | 4 tablets | $23.327 | AB | Availability likely | — |
| Vardenafil 10 mgthis 62332-0235-04 | Alembic | 4 tablets | $23.327 | AB | Availability likely | — |
| Vardenafil 10 mg 46708-0235-04 | Alembic | 4 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Vardenafil inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII Z0H242BBR1
Aspartame is an artificial sweetener made from amino acids. It's added to medicines to improve taste, making bitter or unpleasant-tasting drugs easier to take.
-
UNII 2968PHW8QP
A weak organic acid derived from citrus fruits or made through fermentation. It works as a buffer to control pH, a preservative to extend shelf life, and a flavoring agent in medications.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII V95R5KMY2B
Peppermint is a flavoring agent derived from the peppermint plant. It's added to medicines to improve taste and mask bitter or unpleasant flavors, making them easier to take.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Alembic Pharmaceuticals Inc. labeler code 62332
- Darifenacin 7.5 mg Tablet, Extended Release NDC 62332-223-08
- Darifenacin 15 mg Tablet, Extended Release NDC 62332-224-08
- Fingolimod .5 mg Capsule NDC 62332-228-10
- Vilazodone Hydrochloride 10 mg Tablet, Film Coated NDC 62332-232-30
- Vilazodone Hydrochloride 20 mg Tablet, Film Coated NDC 62332-233-30
- Vilazodone Hydrochloride 40 mg Tablet, Film Coated NDC 62332-234-30
- Vardenafil Hydrochloride 2.5 mg Tablet, Film Coated NDC 62332-236-30
- Vardenafil Hydrochloride 5 mg Tablet, Film Coated NDC 62332-237-30
- Vardenafil Hydrochloride 10 mg Tablet, Film Coated NDC 62332-238-30
- Vardenafil Hydrochloride 20 mg Tablet, Film Coated NDC 62332-239-30
- RIVAROXABAN Kit NDC 62332-240-51
- Ticagrelor 90 mg Tablet, Film Coated NDC 62332-241-30
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Vardenafil hydrochloride orally disintegrating tablets are indicated for the treatment of erectile dysfunction. • Vardenafil hydrochloride orally disintegrating tablets are phosphodiesterase 5 (PDE5) inhibitor indicated for the treatment of erectile dysfunction. ( 1 ).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Vardenafil hydrochloride orally disintegrating tablets are not interchangeable with vardenafil 10 mg film-coated tablets (LEVITRA). Vardenafil hydrochloride orally disintegrating tablets provide higher systemic exposure compared to vardenafil 10 mg film-coated tablets (LEVITRA). ( 2.1 ) • Vardenafil hydrochloride orally disintegrating tablets are taken as needed, orally, approximately 60 minutes before sexual activity.
( 2.1 ) • The maximum recommended dosing frequency is one tablet per day. ( 2.1 ) • Vardenafil hydrochloride orally disintegrating tablets should be placed on the tongue where it will disintegrate. It should be taken without liquid.
( 2.1 ) • Vardenafil hydrochloride orally disintegrating tablets may be taken with or without food. ( 2.2 )
2.1General Vardenafil hydrochloride orally disintegrating tablets are available in 10 mg orally disintegrating tablets. Vardenafil hydrochloride orally disintegrating tablets are not interchangeable with vardenafil 10 mg film-coated tablets (LEVITRA). Vardenafil hydrochloride orally disintegrating tablets provide higher systemic exposure compared to vardenafil 10 mg film-coated tablets (LEVITRA) [see Clinical Pharmacology (12.3).] Vardenafil hydrochloride orally disintegrating tablets should be taken orally, as needed, approximately 60 minutes before sexual activity.
The maximum dosing frequency is one vardenafil hydrochloride orally disintegrating tablet per day. Sexual stimulation is required for a response to treatment. Vardenafil hydrochloride orally disintegrating tablets should be placed on the tongue where it will disintegrate.
The tablet should be taken without liquid. It should be taken immediately upon removal from the blister. Those patients who require a lower or higher dose of vardenafil need to be prescribed vardenafil film-coated tablets [see Patient Counseling Information (17)] .
2.2Use with Food Vardenafil hydrochloride orally disintegrating tablets can be taken with or without food.
2.3Use in Special Populations Hepatic Impairment: Do not use vardenafil hydrochloride orally disintegrating tablets in patients with moderate (Child-Pugh B) or severe (Child-Pugh C) hepatic impairment [see Warnings and Precautions (5.8) and Clinical Pharmacology (12.3)] . Renal Impairment: Do not use vardenafil hydrochloride orally disintegrating tablets in patients on renal dialysis [see Warnings and Precautions (5.9) and Clinical Pharmacology (12.3)].
2.4Concomitant Medications Nitrates: Concomitant use with nitrates in any form is contraindicated [see Contraindications (4.1)] . Guanylate Cyclase (GC) Stimulators, such as riociguat : Concomitant use is contraindicated [see Contraindications (4.2)]. CYP3A4 Inhibitors: Do not use vardenafil hydrochloride orally disintegrating tablets with strong or moderate CYP3A4 inhibitors such as cobicistat, ketoconazole, itraconazole, ritonavir, indinavir, saquinavir, atazanavir, clarithromycin and erythromycin [see Warnings and Precautions (5.2) and Drug Interactions (7.2)] .
Alpha-Blockers: In those patients who are stable on alpha-blocker therapy, PDE5 inhibitors should be initiated at the lowest recommended starting dose. Stepwise increase in alpha-blocker dose may be associated with further lowering of blood pressure in patients taking a phosphodiesterase (PDE5) inhibitor including vardenafil. In patients taking alpha-blockers, do not initiate vardenafil therapy with vardenafil hydrochloride orally disintegrating tablets.
Lower doses of vardenafil film-coated tablets should be used as initial therapy in these patients [see Dosage and Administration (2.4)] . Patients taking alpha-blockers who have previously used vardenafil film-coated tablets may change to vardenafil hydrochloride orally disintegrating tablets at the advice of their healthcare provider [see Warnings and Precautions (5.6) and Drug Interactions (7.1).] A time interval between dosing should be considered when vardenafil hydrochloride orally d… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Vardenafil hydrochloride orally disintegrating tablets, USP are available in 10 mg white to off white, round, biconvex, debossed with “477”. • Vardenafil hydrochloride orally disintegrating tablets 10 mg: White to off white, round, orally disintegrating tablets (not scored) ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Administration with nitrates and nitric oxide donors ( 2.4 , 4.1 ) Administration with guanylate cyclase (GC) stimulators, such as riociguat ( 2.4 , 4.2 )
4.1Nitrates Administration of vardenafil hydrochloride orally disintegrating tablets with nitrates (either regularly and/or intermittently) and nitric oxide donors is contraindicated [see Clinical Pharmacology (12.2)] . Consistent with the effects of PDE5 inhibition on the nitric oxide/cyclic guanosine monophosphate pathway, PDE5 inhibitors, including vardenafil hydrochloride orally disintegrating tablets, may potentiate the hypotensive effects of nitrates. A suitable time interval following vardenafil hydrochloride orally disintegrating tablets dosing for the safe administration of nitrates or nitric oxide donors has not been determined.
4.2Guanylate Cyclase (GC) Stimulators Do not use vardenafil hydrochloride orally disintegrating tablets in patients who are using a GC stimulator, such as riociguat. PDE5 inhibitors, including vardenafil hydrochloride orally disintegrating tablets may potentiate the hypotensive effects of GC stimulators.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS The evaluation of erectile dysfunction should include a medical assessment, a determination of potential underlying causes and the identification of appropriate treatment. Before prescribing vardenafil hydrochloride orally disintegrating tablets, it is important to note the following: • Cardiovascular Effects: Patients should not use vardenafil hydrochloride orally disintegrating tablets if sex is inadvisable due to cardiovascular status. ( 5.1 ) • Strong and Moderate CYP3A4 Inhibitors: Do not use vardenafil hydrochloride orally disintegrating tablets in patients taking strong or moderate CYP3A4 inhibitors.
( 5.2 , 7.2 ) • Risk of Priapism: In the event that an erection lasts more than 4 hours, the patient should seek immediate medical assistance. ( 5.3 ) • Effects on the Eye: Patients should stop use of vardenafil hydrochloride orally disintegrating tablets and seek medical attention in the event of sudden loss of vision in one or both eyes, which could be a sign of non arteritic anterior ischemic optic neuropathy (NAION). Vardenafil hydrochloride orally disintegrating tablets should be used with caution, and only when the anticipated benefits outweigh the risks, in patients with a history of NAION.
Patients with a “crowded” optic disc may also be at an increased risk of NAION. ( 5.4 , 6.2 ) • Sudden Hearing Loss: Patients should stop vardenafil hydrochloride orally disintegrating tablets and seek medical attention in the event of sudden decrease or loss in hearing. ( 5.5 , 6.2 ) • Alpha-Blockers: Caution is advised when PDE5 inhibitors are coadministered with alpha-blockers.
In some patients, concomitant use of these two drug classes can lower blood pressure significantly leading to symptomatic hypotension (for example, fainting). In patients taking alpha-blockers, do not initiate vardenafil therapy with vardenafil hydrochloride orally disintegrating tablets. ( 2.4 , 5.6 ) • QT Prolongation: Patients with congenital QT syndrome or taking class IA or III antiarrhythmics should avoid using vardenafil hydrochloride orally disintegrating tablets.
( 5.7 , 12.2 ) • Phenylketonurics: Each vardenafil hydrochloride orally disintegrating tablet contain 1.403 mg phenylalanine per tablet, which could be harmful for patients with phenylketonuria. ( 5.12 )
5.1Cardiovascular Effects General Physicians should consider the cardiovascular status of their patients, since there is a degree of cardiac risk associated with sexual activity. Therefore, treatment for erectile dysfunction, including vardenafil hydrochloride orally disintegrating tablets, should not be used in men for whom sexual activity is not recommended because of their underlying cardiovascular status. There are no controlled clinical data on the safety or efficacy of vardenafil in the following patients; and therefore its use is not recommended until further information is available: unstable angina; hypotension (resting systolic blood pressure of <90 mmHg); uncontrolled hypertension (>170/110 mmHg); recent history of stroke, life-threatening arrhythmia, or myocardial infarction (within the last 6 months); severe cardiac failure.
Left Ventricular Outflow Obstruction Patients with left ventricular outflow obstruction (for example, aortic stenosis and idiopathic hypertrophic subaortic stenosis) can be sensitive to the action of vasodilators including PDE5 inhibitors. Blood Pressure Effects Vardenafil has systemic vasodilatory properties that resulted in transient decreases in supine blood pressure in healthy volunteers (mean maximum decrease of 7 mmHg systolic and 8 mmHg diastolic) [see Clinical Pharmacology (12.2)] . While this normally would be expected to be of little consequence in most patients, prior to prescribing vardenafil hydrochloride orally disintegrating tablets, physicians should carefully consider whether their patients with underlying cardiovascular disease could be affected adversely by such vasodilatory effects.
5.2Potential for Drug… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions with the use of vardenafil hydrochloride orally disintegrating tablets are discussed elsewhere in the labeling: · Cardiovascular effects [see Contraindications (4.1) and Warnings and Precautions (5.1)] · Priapism [see Warnings and Precautions (5.3)] · QT Prolongation [see Warnings and Precautions (5.7)] · Effects on eye [see Warnings and Precautions (5.4)] · Sudden hearing loss [see Warnings and Precautions (5.5)] Adverse reactions reported by ≥ 2% of patients treated with vardenafil hydrochloride orally disintegrating tablets : Headache, flushing, nasal congestion, dyspepsia, dizziness, back pain.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Alembic Pharmaceuticals Limited at 1-866-210-9797 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Studies Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Vardenafil Hydrochloride Orally Disintegrating Tablets : Safety of vardenafil hydrochloride orally disintegrating tablets were evaluated in two identical multi-national, randomized, double-blind, placebo-controlled trials. In both pivotal studies, enrollment was stratified so that approximately 50% of patients were ≥65 years old.
Approximately 8% (n=29) were ≥75 years old. An integrated analysis of both studies included a total of 355 subjects that received vardenafil hydrochloride orally disintegrating tablets compared to 340 subjects that received placebo (mean age was 61.7, range 21 to 88; 68% White, 5% Black, 6% Asian, 11% Hispanic and 11% Other). The discontinuation rates due to adverse reactions were 1.4% for vardenafil hydrochloride orally disintegrating tablets compared to 0.6% for placebo.
Table 1 below details the most frequently reported adverse reactions. Table 1: Adverse drug reactions reported by ≥2% of the patients treated with vardenafil hydrochloride orally disintegrating tablets and more frequent on drug than placebo in controlled trials Adverse Drug Reaction Vardenafil hydrochloride orally disintegrating tablets Placebo (n=355) (n=340) Headache 14.4% 1.8% Flushing 7.6% 0.6% Nasal Congestion 3.1% 0.3% Dyspepsia 2.8% 0% Dizziness 2.3% 0% Back Pain 2% 0.3% Adverse drug reactions reported in the vardenafil hydrochloride orally disintegrating tablets placebo controlled trials were comparable to the adverse drug reactions reported in earlier vardenafil film-coated tablets placebo controlled trials.
All Vardenafil Studies: Vardenafil film-coated tablets and vardenafil hydrochloride orally disintegrating tablets have been administered to over 17,000 men (mean age 54.5, range 18 to 89 years; 70% White, 5% Black, 13% Asian, 4% Hispanic and 8% Other) during controlled and uncontrolled clinical trials worldwide. The number of patients treated for 6 months or longer was 3357, and 1350 patients were treated for at least 1 year. In the placebo-controlled clinical trials for vardenafil film-coated tablets and vardenafil hydrochloride orally disintegrating tablets, the discontinuation rate due to adverse events was 1.9% for vardenafil compared to 0.8% for placebo.
Placebo-controlled trials suggested a dose effect in the incidence of some adverse reactions (for example, dizziness, headache, flushing, dyspepsia, nausea, nasal congestion) over the 5 mg, 10 mg, and 20 mg doses of vardenafil film-coated tablets. The following section identifies additional, less frequent adverse reactions (<2%) reported during the clinical development of vardenafil film-coated tablets and vardenafil hydrochloride orally disintegrating tablets. Excluded from this list are those adverse reactions that are infrequent and minor, those events that may be commonly observed in the absence of drug therapy, and those events that are not reasonably associated wit… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS The drug interaction studies described below were conducted using vardenafil film-coated tablets. • Vardenafil hydrochloride orally disintegrating tablets can potentiate the hypotensive effects of nitrates, alpha-blockers, and antihypertensives. ( 7.1 ) • Do not use vardenafil hydrochloride orally disintegrating tablets with moderate or strong CYP3A4 inhibitors as coadministration will result in significant increases in plasma vardenafil concentrations. ( 7.2 )
7.1Potential for Pharmacodynamic Interactions with Vardenafil Hydrochloride Orally Disintegrating Tablets Nitrates: Concomitant use of vardenafil hydrochloride orally disintegrating tablets and nitrates is contraindicated. The blood pressure lowering effects of sublingual nitrates (0.4 mg) taken 1 and 4 hours after vardenafil and increases in heart rate when taken at 1, 4 and 8 hours after vardenafil were potentiated by a 20 mg dose of vardenafil in healthy middle-aged subjects. These effects were not observed when vardenafil 20 mg was taken 24 hours before the nitroglycerin (NTG).
Potentiation of the hypotensive effects of nitrates for patients with ischemic heart disease has not been evaluated, and concomitant use of vardenafil hydrochloride orally disintegrating tablets and nitrates is contraindicated [see Contraindications (4.1) and Clinical Pharmacology (12.2)] . Alpha-Blockers: Patients taking alpha-blockers should not initiate vardenafil therapy with vardenafil hydrochloride orally disintegrating tablets. Patients treated with alpha-blockers who have previously used vardenafil film-coated tablets may be switched to vardenafil hydrochloride orally disintegrating tablets at the advice of their healthcare provider.
Caution is advised when PDE5 inhibitors are co-administered with alpha-blockers. PDE5 inhibitors, including vardenafil hydrochloride orally disintegrating tablets and alpha-adrenergic blocking agents are both vasodilators with blood-pressure-lowering effects. When vasodilators are used in combination, an additive effect on blood pressure may be anticipated.
Clinical pharmacology studies have been conducted with co-administration of vardenafil with alfuzosin, terazosin or tamsulosin [see Dosage and Administration (2.4), Warnings and Precautions (5.6), and Clinical Pharmacology (12.2).] Antihypertensives: Vardenafil hydrochloride orally disintegrating tablets may add to the blood pressure lowering effect of antihypertensive agents. In a clinical pharmacology study of patients with erectile dysfunction, single doses of 20 mg vardenafil caused a mean maximum decrease in supine blood pressure of 7 mmHg systolic and 8 mmHg diastolic (compared to placebo), accompanied by a mean maximum increase of heart rate of 4 beats per minute.
The maximum decrease in blood pressure occurred between 1 and 4 hours after dosing. Following multiple dosing for 31 days, similar blood pressure responses were observed on Day 31 as on Day 1. Alcohol: Vardenafil 20 mg did not potentiate the hypotensive effects of alcohol during the 4-hour observation period in healthy volunteers when administered with alcohol (0.5 g/kg body weight: approximately 40 mL of absolute alcohol in a 70 kg person).
Alcohol and vardenafil plasma levels were not altered when dosed simultaneously.
7.2Effect of Other Drugs on Vardenafil In vitro studies Studies in human liver microsomes showed that vardenafil is metabolized primarily by cytochrome P450 (CYP) isoforms 3A4/5, and to a lesser degree by CYP2C9. Therefore, inhibitors of these enzymes are expected to reduce vardenafil clearance [see Dosage and Administration (2.4) and Warnings and Precautions (5.2)] . In vivo studies Do not use vardenafil hydrochloride orally disintegrating tablets with moderate and strong CYP3A4 inhibitors such as erythromycin, grapefruit juice, clarithromycin, ketoconazole, itraconazole, indinavir, saquinavir, atazanavir, ritonavir as the systemic concentration of vardenafil is increased in their presence [see W… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Do not use vardenafil hydrochloride orally disintegrating tablets in patients with moderate or severe hepatic impairment. ( 8.6 ) • Do not use vardenafil hydrochloride orally disintegrating tablets in patients on renal dialysis. ( 8.7 )
8.1Pregnancy Risk Summary Vardenafil hydrochloride orally disintegrating tablets are not indicated for use in females. There are no data with the use of vardenafil hydrochloride orally disintegrating tablets in pregnant women to inform any drug-associated risks. In animal reproduction studies conducted in pregnant rats and rabbits, no adverse developmental outcomes were observed with oral administration of vardenafil during organogenesis at exposures for unbound vardenafil and its major metabolite at approximately 100 and 29 times, respectively, the maximum recommended human dose (MRHD) of 20 mg based on AUC (see Data) .
Data Animal Data No evidence of specific potential for teratogenicity, embryotoxicity or fetotoxicity was observed in rats and rabbits that received vardenafil at up to 18 mg/kg/day during organogenesis. This dose is approximately 100 fold (rat) and 29 fold (rabbit) greater than the AUC values for unbound vardenafil and its major metabolite in humans given the maximum recommended human dose (MRHD) of 20 mg. In the rat pre-and postnatal development study, the NOAEL (no observed adverse effect level) for maternal toxicity was 8 mg/kg/day.
Retarded physical development of pups in the absence of maternal effects was observed following maternal exposure to 1 and 8 mg/kg possibly due to vasodilatation and/or secretion of the drug into milk. The number of living pups born to rats exposed pre- and postnatally was reduced at 60 mg/kg/day. Based on the results of the pre- and postnatal study, the developmental NOAEL is less than 1 mg/kg/day.
Based on plasma exposures in the rat developmental toxicity study, 1 mg/kg/day in the pregnant rat is estimated to produce total AUC values for unbound vardenafil and its major metabolite comparable to the human AUC at the MRHD of 20 mg.
8.2Lactation Risk Summary Vardenafil hydrochloride orally disintegrating tablets are not indicated for use in females. There is no information on the presence of vardenafil and its major metabolite in human milk, the effects on the breastfed infant, or the effects on milk production. Vardenafil is present in rat milk of lactating rats (see Data) .
Data Vardenafil was secreted into the milk of lactating rats at concentrations approximately 10-fold greater than found in the plasma. Following a single oral dose of 3 mg/kg, 3.3% of the administered dose was excreted into the milk within 24 hours.
8.4Pediatric Use Vardenafil hydrochloride orally disintegrating tablets are not indicated for use in pediatric patients. Safety and efficacy in children has not been established.
8.5Geriatric Use Vardenafil AUC and C max in elderly males 65 years or older taking vardenafil hydrochloride orally disintegrating tablets were increased by 39% and 21%, respectively, in comparison to patients aged 45 years and below. No overall differences in safety or effectiveness were observed between patients ≥65 years old and those < 65 years old in placebo-controlled clinical trials [see Clinical Pharmacology (12.3)].
8.6Hepatic Impairment Do not use vardenafil hydrochloride orally disintegrating tablets in patients with moderate or severe hepatic impairment. In volunteers with mild hepatic impairment (Child-Pugh A), the C max and AUC following a 10 mg vardenafil (film-coated tablets) dose were increased by 22% and 17%, respectively, compared to healthy control subjects. Vardenafil hydrochloride orally disintegrating tablets can be used in patients with mild hepatic impairment.
In volunteers with moderate hepatic impairment (Child-Pugh B), the C max and AUC following a 10 mg vardenafil (film-coated tablets) dose were increased by 130% and 160%, respectively, compared to healthy control subjects. Vardenafil has… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Vardenafil hydrochloride orally disintegrating tablets are not indicated for use in females. There are no data with the use of vardenafil hydrochloride orally disintegrating tablets in pregnant women to inform any drug-associated risks. In animal reproduction studies conducted in pregnant rats and rabbits, no adverse developmental outcomes were observed with oral administration of vardenafil during organogenesis at exposures for unbound vardenafil and its major metabolite at approximately 100 and 29 times, respectively, the maximum recommended human dose (MRHD) of 20 mg based on AUC (see Data) .
Data Animal Data No evidence of specific potential for teratogenicity, embryotoxicity or fetotoxicity was observed in rats and rabbits that received vardenafil at up to 18 mg/kg/day during organogenesis. This dose is approximately 100 fold (rat) and 29 fold (rabbit) greater than the AUC values for unbound vardenafil and its major metabolite in humans given the maximum recommended human dose (MRHD) of 20 mg. In the rat pre-and postnatal development study, the NOAEL (no observed adverse effect level) for maternal toxicity was 8 mg/kg/day.
Retarded physical development of pups in the absence of maternal effects was observed following maternal exposure to 1 and 8 mg/kg possibly due to vasodilatation and/or secretion of the drug into milk. The number of living pups born to rats exposed pre- and postnatally was reduced at 60 mg/kg/day. Based on the results of the pre- and postnatal study, the developmental NOAEL is less than 1 mg/kg/day.
Based on plasma exposures in the rat developmental toxicity study, 1 mg/kg/day in the pregnant rat is estimated to produce total AUC values for unbound vardenafil and its major metabolite comparable to the human AUC at the MRHD of 20 mg.
🧒 Pediatric Use ▾
8.4Pediatric Use Vardenafil hydrochloride orally disintegrating tablets are not indicated for use in pediatric patients. Safety and efficacy in children has not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Vardenafil AUC and C max in elderly males 65 years or older taking vardenafil hydrochloride orally disintegrating tablets were increased by 39% and 21%, respectively, in comparison to patients aged 45 years and below. No overall differences in safety or effectiveness were observed between patients ≥65 years old and those < 65 years old in placebo-controlled clinical trials [see Clinical Pharmacology (12.3)].
🆘 Overdosage ▾
10 OVERDOSAGE The maximum dose of vardenafil for which human data are available is a single 120 mg dose of the film–coated tablets administered to healthy male volunteers. The majority of these subjects experienced reversible back pain/myalgia and/or “abnormal vision.” Single doses up to 80 mg vardenafil and multiple doses up to 40 mg vardenafil administered once daily over 4 weeks were tolerated without producing serious adverse side effects. When 40 mg of vardenafil was administered twice daily, cases of severe back pain were observed.
No muscle or neurological toxicity was identified. In cases of overdose, standard supportive measures should be taken as required. Renal dialysis is not expected to accelerate clearance because vardenafil is highly bound to plasma proteins and is not significantly eliminated in the urine.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Penile erection is a hemodynamic process initiated by the relaxation of smooth muscle in the corpus cavernosum and its associated arterioles. During sexual stimulation, nitric oxide is released from nerve endings and endothelial cells in the corpus cavernosum. Nitric oxide activates the enzyme guanylate cyclase resulting in increased synthesis of cyclic guanosine monophosphate (cGMP) in the smooth muscle cells of the corpus cavernosum.
The cGMP in turn triggers smooth muscle relaxation, allowing increased blood flow into the penis, resulting in erection. The tissue concentration of cGMP is regulated by both the rates of synthesis and degradation via phosphodiesterases (PDEs). The most abundant PDE in the human corpus cavernosum is the cGMP-specific PDE5; therefore, the inhibition of PDE5 enhances erectile function by increasing the amount of cGMP.
Because sexual stimulation is required to initiate the local release of nitric oxide, the inhibition of PDE5 has no effect in the absence of sexual stimulation. In vitro studies have shown that vardenafil is a selective inhibitor of PDE5. The inhibitory effect of vardenafil is more selective on PDE5 than for other known phosphodiesterases (>15-fold relative to PDE6, >130-fold relative to PDE1, >300-fold relative to PDE11, and >1,000-fold relative to PDE2, 3, 4, 7, 8, 9, and 10).
12.2Pharmacodynamics The pharmacodynamic studies described below were conducted using vardenafil film-coated tablets. Effects on Blood Pressure In a clinical pharmacology study of patients with erectile dysfunction, single doses of vardenafil 20 mg film-coated tablets caused a mean maximum decrease in supine blood pressure of 7 mmHg systolic and 8 mmHg diastolic (compared to placebo), accompanied by a mean maximum increase of heart rate of 4 beats per minute. The maximum decrease in blood pressure occurred between 1 and 4 hours after dosing.
Following multiple dosing for 31 days, similar blood pressure responses were observed on Day 31 as on Day 1. Vardenafil may add to the blood pressure lowering effects of antihypertensive agents [see Drug Interactions (7)] . Effects on Blood Pressure and Heart Rate when Vardenafil is Combined with Nitrates A study was conducted in which the blood pressure and heart rate response to 0.4 mg nitroglycerin (NTG) sublingually was evaluated in 18 healthy subjects following pretreatment with vardenafil 20 mg film-coated tablets at various times before NTG administration.
Vardenafil 20 mg caused an additional time-related reduction in blood pressure and increase in heart rate in association with NTG administration. The blood pressure effects were observed when vardenafil 20 mg was dosed 1 or 4 hours before NTG and the heart rate effects were observed when 20 mg was dosed 1, 4, or 8 hours before NTG. Additional blood pressure and heart rate changes were not detected when vardenafil 20 mg film-coated tablet was dosed 24 hours before NTG (see Figure 1).
Figure 1: Placebo-subtracted point estimates (with 90% CI) of mean maximal blood pressure and heart rate effects of pre-dosing with vardenafil 20 mg at 24, 8, 4, and 1 hour before 0.4 mg NTG sublingually Because the disease state of patients requiring nitrate therapy is anticipated to increase the likelihood of hypotension, the use of vardenafil by patients on nitrate therapy or on nitric oxide donors is contraindicated [see Contraindications (4.1)] . Blood Pressure Effects in Patients on Stable Alpha-Blocker Treatment Three clinical pharmacology studies were conducted in patients with benign prostatic hyperplasia (BPH) on stable-dose alpha-blocker treatment , consisting of alfuzosin, tamsulosin or terazosin.
Study 1: This study was designed to evaluate the effect of 5 mg vardenafil film-coated tablets compared to placebo when administered to BPH patients on chronic alpha-blocker therapy in two separate cohorts: tamsulosin 0.4 mg daily (cohort 1, n=21) and terazosin 5 or 10 mg daily (… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Penile erection is a hemodynamic process initiated by the relaxation of smooth muscle in the corpus cavernosum and its associated arterioles. During sexual stimulation, nitric oxide is released from nerve endings and endothelial cells in the corpus cavernosum. Nitric oxide activates the enzyme guanylate cyclase resulting in increased synthesis of cyclic guanosine monophosphate (cGMP) in the smooth muscle cells of the corpus cavernosum.
The cGMP in turn triggers smooth muscle relaxation, allowing increased blood flow into the penis, resulting in erection. The tissue concentration of cGMP is regulated by both the rates of synthesis and degradation via phosphodiesterases (PDEs). The most abundant PDE in the human corpus cavernosum is the cGMP-specific PDE5; therefore, the inhibition of PDE5 enhances erectile function by increasing the amount of cGMP.
Because sexual stimulation is required to initiate the local release of nitric oxide, the inhibition of PDE5 has no effect in the absence of sexual stimulation. In vitro studies have shown that vardenafil is a selective inhibitor of PDE5. The inhibitory effect of vardenafil is more selective on PDE5 than for other known phosphodiesterases (>15-fold relative to PDE6, >130-fold relative to PDE1, >300-fold relative to PDE11, and >1,000-fold relative to PDE2, 3, 4, 7, 8, 9, and 10).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Vardenafil hydrochloride orally disintegrating tablets, USP 10 mg are white to off white, round, biconvex tablet debossed with “477” on one side and plain on other side. Vardenafil hydrochloride orally disintegrating tablets, USP are packaged into blister packs and supplied as a 4 tablet unit. 1 blister card containing 4 tablets NDC 62332-235-04 In addition to the active ingredient, vardenafil, each tablet contains lactose monohydrate, silicified microcrystalline cellulose, crospovidone, colloidal silicon dioxide, aspartame, citric acid monohydrate, NAT Peppermint FL WONF SD #491, sodium stearyl fumarate and magnesium stearate.
16.2Recommended Storage Store vardenafil hydrochloride orally disintegrating tablets, USP at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Vardenafil hydrochloride orally disintegrating tablets, USP are dispensed in blister packs. The patient should be advised to examine the blister pack before use and not use if blisters are torn, broken, or missing.
📋 Description ▾
11 DESCRIPTION Vardenafil hydrochloride orally disintegrating tablets, USP are an oral therapy for the treatment of erectile dysfunction. This monohydrochloride salt of vardenafil is a selective inhibitor of cyclic guanosine monophosphate (cGMP)-specific PDE5. Vardenafil HCl, USP is designated chemically as piperazine, 1-[[3-(1,4-dihydro-5-methyl-4-oxo-7-propylimidazo[5,1-f][1,2,4]triazin-2-yl)-4-ethoxyphenyl]sulfonyl]-4-ethyl-, monohydrochloride and has the following structural formula: Vardenafil HCl, USP is a white or slightly brown or yellow powder with a molecular weight of 579.1.
It is slightly soluble in water, freely soluble in anhydrous Ethanol. Practically insoluble in heptane. Vardenafil hydrochloride orally disintegrating tablets, USP are formulated as white to off white, round, orally disintegrating tablets.
Each tablet contains 11.85 mg vardenafil hydrochloride, USP (in trihydrate form), which is equivalent to 10 mg vardenafil and the following inactive ingredients: lactose monohydrate, silicified microcrystalline cellulose, crospovidone, colloidal silicon dioxide, aspartame, citric acid monohydrate, NAT Peppermint FL WONF SD #491, sodium stearyl fumarate and magnesium stearate. Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-approved patient labeling (Patient Information) Use with Other Formulations of Vardenafil Inform patients that vardenafil hydrochloride orally disintegrating tablets are not interchangeable with vardenafil film-coated tablets (LEVITRA) as it provides higher systemic exposure. They should also discuss that the maximum dosage is one vardenafil hydrochloride orally disintegrating tablets tablet per 24 hours. Nitrates Discuss with patients that vardenafil hydrochloride orally disintegrating tablets are contraindicated with regular and/or intermittent use of organic nitrates.
Patients should be counseled that concomitant use of vardenafil with nitrates could cause blood pressure to suddenly drop to an unsafe level, resulting in dizziness, syncope, or even heart attack or stroke. Guanylate Cyclase (GC) Stimulators Inform patients that vardenafil hydrochloride orally disintegrating tablets are contraindicated in patients who use guanylate cyclase stimulators, such as riociguat. Cardiovascular Discuss with patients the potential cardiac risk of sexual activity for patients with preexisting cardiovascular risk factors.
Concomitant Use with Drugs which Lower Blood Pressure Inform patients that in some patients concomitant use of PDE5 inhibitors, including vardenafil hydrochloride orally disintegrating tablets, with alpha-blockers can lower blood pressure significantly leading to symptomatic hypotension (for example, fainting). Patients who are taking alpha-blockers should only use vardenafil hydrochloride orally disintegrating tablets when previous treatment with vardenafil film-coated tablets has been well tolerated [see Dosage and Administration (2) and Drug Interactions (7)].
Patients should be advised of the possible occurrence of symptoms related to postural hypotension and appropriate countermeasures. Patients should be advised to contact the prescribing physician if other anti-hypertensive drugs or new medications that may interact with vardenafil hydrochloride orally disintegrating tablets are prescribed by another healthcare provider. Recommended Administration Discuss with patients the appropriate use of vardenafil hydrochloride orally disintegrating tablets and its anticipated benefits.
It should be explained that sexual stimulation is required for an erection to occur after taking vardenafil hydrochloride orally disintegrating tablets. Vardenafil hydrochloride orally disintegrating tablets should be taken approximately 60 minutes before sexual activity. Patients should be counseled regarding the dosing of vardenafil hydrochloride orally disintegrating tablets, especially regarding the maximum daily dose.
Patients should be advised to contact their healthcare provider if they are not satisfied with the quality of their sexual performance with vardenafil hydrochloride orally disintegrating tablets or in the case of an unwanted effect. Priapism Inform patients that there have been rare reports of prolonged erections greater than 4 hours and priapism (painful erections greater than 6 hours in duration) for vardenafil and this class of compounds. In the event that an erection persists longer than 4 hours, the patient should seek immediate medical assistance.
If priapism is not treated immediately, penile tissue damage and permanent loss of potency may result. Drug Interactions Advise patients to contact the prescribing physician if new medications that may interact with vardenafil hydrochloride orally disintegrating tablets are prescribed by another healthcare provider. Sudden Loss of Vision Inform patients to stop use of all PDE5 inhibitors, including vardenafil hydrochloride orally disintegrating tablets, and seek medical attention in the event of sudden loss of vision in one or both eyes.
Such an event may be a sign of non-arteritic anterior ischemic optic neuropathy (NAION), a cause of decreased vision, including permanent loss of vision, that has been reported rarely postmarketing in… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of vardenafil and its M1 metabolite from vardenafil hydrochloride orally disintegrating tablets have been evaluated in healthy male volunteers (18 to 50 years) and in young (18 to 45 years) and elderly (≥ 65 years) erectile dysfunction patients. Studies have shown that vardenafil hydrochloride orally disintegrating tablets provides higher systemic exposure of vardenafil compared to vardenafil 10 mg film-coated tablets. Absorption Mean vardenafil plasma concentrations measured after the administration of a single oral dose vardenafil hydrochloride orally disintegrating tablets to patients with erectile dysfunction (18 to 45 years) are depicted in Figure 8 .
Figure 8: Vardenafil Plasma Concentration (Mean ± SD) Profile for Vardenafil Hydrochloride Orally Disintegrating Tablets in men age 18 to 45 years with erectile dysfunction The median time to reach C max (T max ) in patients receiving vardenafil hydrochloride orally disintegrating tablets in the fasted state was 1.5 h [range: 0.75 to 2.5 h]. After administration of vardenafil hydrochloride orally disintegrating tablets to elderly (≥ 65 years) and young (18 to 45 years) patients with erectile dysfunction, mean vardenafil AUC was increased by 21 to 29%, respectively while mean C max was lower by 19% and 8%, respectively, in comparison to 10 mg vardenafil (film-coated tablets).
In a study of healthy male volunteers (18 to 50 years), the mean C max and AUC of vardenafil from vardenafil hydrochloride orally disintegrating tablets were higher by 15% and 44%, respectively compared to 10 mg vardenafil film-coated tablets. Vardenafil was not found to accumulate in plasma when vardenafil hydrochloride orally disintegrating tablets was dosed daily over ten days. Effect of food: A high fat meal had no effect on vardenafil AUC and T max from vardenafil hydrochloride orally disintegrating tablets in healthy volunteers and reduced Cmax by 35%.
Clinical trials for vardenafil hydrochloride orally disintegrating tablets were conducted without regard to meals. Vardenafil hydrochloride orally disintegrating tablets can be taken with or without food. Effect of water: When vardenafil hydrochloride orally disintegrating tablets were swallowed with water, the AUC of vardenafil was reduced by 29% and median T max was shortened by 60 minutes while C max was not affected.
In clinical trials, dosing was done without water. Vardenafil hydrochloride orally disintegrating tablets should be taken without liquid. Distribution The mean steady-state volume of distribution (Vss) for vardenafil is 208 L, indicating extensive tissue distribution.
Vardenafil and its major circulating metabolite, M1, are highly bound to plasma proteins (about 95% for parent drug and M1). This protein binding is reversible and independent of total drug concentrations. Following a single oral dose of 20 mg vardenafil film-coated tablet in healthy volunteers, a mean of 0.00018% of the administered dose was obtained in semen 1.5 hours after dosing.
Metabolism Vardenafil is metabolized predominantly by the hepatic enzyme CYP3A4, with contribution from the CYP3A5 and CYP2C isoforms. The major circulating metabolite, M1, results from desethylation at the piperazine moiety of vardenafil. M1 is subject to further metabolism.
The plasma concentration of M1 is approximately 26% that of the parent compound. This metabolite shows a phosphodiesterase selectivity profile similar to that of vardenafil and an in vitro inhibitory potency for PDE5 28% of that of vardenafil. Therefore, M1 accounts for approximately 7% of total pharmacologic activity.
Excretion The mean terminal half-life of vardenafil in patients receiving vardenafil hydrochloride orally disintegrating tablets varied between about 4 to 6 hours. The elimination half-life of the metabolite M1 is between 3 to 5 hours. After oral administration, vardenafil is excreted as metabolites predominantly in the feces (approximately 91 to 95% of administ… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics The pharmacodynamic studies described below were conducted using vardenafil film-coated tablets. Effects on Blood Pressure In a clinical pharmacology study of patients with erectile dysfunction, single doses of vardenafil 20 mg film-coated tablets caused a mean maximum decrease in supine blood pressure of 7 mmHg systolic and 8 mmHg diastolic (compared to placebo), accompanied by a mean maximum increase of heart rate of 4 beats per minute. The maximum decrease in blood pressure occurred between 1 and 4 hours after dosing.
Following multiple dosing for 31 days, similar blood pressure responses were observed on Day 31 as on Day 1. Vardenafil may add to the blood pressure lowering effects of antihypertensive agents [see Drug Interactions (7)] . Effects on Blood Pressure and Heart Rate when Vardenafil is Combined with Nitrates A study was conducted in which the blood pressure and heart rate response to 0.4 mg nitroglycerin (NTG) sublingually was evaluated in 18 healthy subjects following pretreatment with vardenafil 20 mg film-coated tablets at various times before NTG administration.
Vardenafil 20 mg caused an additional time-related reduction in blood pressure and increase in heart rate in association with NTG administration. The blood pressure effects were observed when vardenafil 20 mg was dosed 1 or 4 hours before NTG and the heart rate effects were observed when 20 mg was dosed 1, 4, or 8 hours before NTG. Additional blood pressure and heart rate changes were not detected when vardenafil 20 mg film-coated tablet was dosed 24 hours before NTG (see Figure 1).
Figure 1: Placebo-subtracted point estimates (with 90% CI) of mean maximal blood pressure and heart rate effects of pre-dosing with vardenafil 20 mg at 24, 8, 4, and 1 hour before 0.4 mg NTG sublingually Because the disease state of patients requiring nitrate therapy is anticipated to increase the likelihood of hypotension, the use of vardenafil by patients on nitrate therapy or on nitric oxide donors is contraindicated [see Contraindications (4.1)] . Blood Pressure Effects in Patients on Stable Alpha-Blocker Treatment Three clinical pharmacology studies were conducted in patients with benign prostatic hyperplasia (BPH) on stable-dose alpha-blocker treatment , consisting of alfuzosin, tamsulosin or terazosin.
Study 1: This study was designed to evaluate the effect of 5 mg vardenafil film-coated tablets compared to placebo when administered to BPH patients on chronic alpha-blocker therapy in two separate cohorts: tamsulosin 0.4 mg daily (cohort 1, n=21) and terazosin 5 or 10 mg daily (cohort 2, n=21). The design was a randomized, double blind, cross-over study with four treatments: vardenafil 5 mg or placebo administered simultaneously with the alpha-blocker and vardenafil 5 mg or placebo administered 6 hours after the alpha-blocker.
Blood pressure and pulse were evaluated over the 6-hour interval after vardenafil dosing. For blood pressure (BP) results, see Table 2 . One patient, after simultaneous treatment with 5 mg vardenafil and 10 mg terazosin, exhibited symptomatic hypotension with standing blood pressure of 80/60 mmHg occurring one hour after administration and subsequent mild dizziness and moderate lightheadedness lasting for 6 hours.
For vardenafil and placebo, five and two patients, respectively, experienced a decrease in standing systolic blood pressure (SBP) of >30 mmHg following simultaneous administration of terazosin. Hypotension was not observed when vardenafil 5 mg and terazosin were administered 6 hours apart. Following simultaneous administration of vardenafil 5 mg and tamsulosin, two patients had a standing SBP of <85 mmHg.
A decrease in standing SBP of >30 mmHg was observed in two patients on tamsulosin receiving simultaneous vardenafil and in one patient receiving simultaneous placebo treatment. When tamsulosin and vardenafil 5 mg were separated by 6 hours, two patients had a standing SBP <85 mmHg and one patient had a decrease i… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy and safety of vardenafil hydrochloride orally disintegrating tablets were evaluated in two identical multi-national, randomized, double-blind, placebo-controlled trials (studies 1 and 2). Vardenafil hydrochloride orally disintegrating tablets were dosed without regard to meals on an as-needed basis in men with erectile dysfunction (ED), many of whom had multiple other medical conditions. In both pivotal studies, randomization was stratified so that approximately 50% of patients were ≥65 years old.
Primary efficacy assessment was by means of the Erectile Function (EF) Domain score of the validated International Index of Erectile Function (IIEF) Questionnaire and two questions from the Sexual Encounter Profile (SEP) dealing with the ability to achieve vaginal penetration (SEP2), and the ability to maintain an erection long enough for successful intercourse (SEP3). The primary endpoints were assessed at 3 months. Study 1 evaluated 355 mainly European (Belgium, France, Germany, Spain, South Africa, and Netherlands) patients (mean age 61.9; 67% White, 4% Black, 3% Asian, 26% Unknown).
The mean baseline EF domain scores were 13 for both placebo and vardenafil hydrochloride orally disintegrating tablets groups. Study 2 evaluated 331 mainly North American (USA, Canada, Mexico, and Australia) patients (mean age 61.7; 69% White, 5% Black, 4% Asian, 22% Hispanic). The mean baseline EF domain scores were 12 for vardenafil hydrochloride orally disintegrating tablets and 13 for placebo.
In both studies vardenafil hydrochloride orally disintegrating tablets demonstrated clinically meaningful and statistically significant improvements over placebo in all 3 primary efficacy variables (see Table 7). Table 7: Change from Baseline for the Primary Efficacy Variables in Studies 1 and 2 Study 1 Study 2 Placebo Vardenafil hydrochloride orally disintegrating tablets p-value Placebo Vardenafil hydrochloride orally disintegrating tablets p-value EF Domain Score (N=172) (N=181) (N=160) (N=167) Endpoint 14 21 14 21 Change from baseline 1.6 8.7 <.0001 1.5 8.5 <.0001 Insertion of Penis (SEP2) (N=169) (N=179) (N=161) (N=168) Endpoint 45% 74% 43% 69% Change from baseline 6.9% 35.9% <.0001 4.8% 30.8% <.0001 Maintenance of Erection (SEP3) (N=164) (N=178) (N=160) (N=168) Endpoint 26% 65% 27% 60% Change from baseline 11.6% 51.6% <.0001 12.4% 45.9% <.0001
14.1Other Vardenafil Clinical Trials Using Film-Coated Tablets Patients with ED and Diabetes Mellitus Vardenafil demonstrated clinically meaningful and statistically significant improvement in erectile function in a prospective, fixed-dose [10 and 20 mg vardenafil film-coated tablets], double-blind, placebo-controlled trial of patients with diabetes mellitus (n=439; mean age 57 years, range 33 to 81; 80% White, 9% Black, 8% Hispanic, and 3% Other). Significant improvements in the EF Domain were shown in this study (EF Domain scores of 17 on 10 mg vardenafil and 19 on 20 mg vardenafil compared to 13 on placebo; p <0.0001).
Vardenafil significantly improved the overall per-patient rate of achieving an erection sufficient for penetration (SEP2) (61% on 10 mg and 64% on 20 mg vardenafil compared to 36% on placebo; p <0.0001). Vardenafil demonstrated a clinically meaningful and statistically significant increase in the overall per-patient rate of maintenance of erection to successful intercourse (SEP3) (49% on 10 mg, 54% on 20 mg vardenafil compared to 23% on placebo; p <0.0001). Patients with ED after Radical Prostatectomy Vardenafil demonstrated clinically meaningful and statistically significant improvement in erectile function in a prospective, fixed-dose 10 and 20 mg vardenafil film-coated tablets, double-blind, placebo-controlled trial in postprostatectomy patients (n=427, mean age 60, range 44 to 77 years; 93% White, 5% Black, 2% Other).
Significant improvements in the EF Domain were shown in this study (EF Domain scores of 15 on 10 mg vardenafil and 15 on 20 mg vardenafil comp… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Vardenafil was not carcinogenic in rats and mice when administered daily for 24 months. In these studies systemic drug exposures (AUCs) for unbound (free) vardenafil and its major metabolite were approximately 400- and 170-fold for male and female rats, respectively, and 21-and 37-fold for male and female mice, respectively, the exposures observed in human males given the maximum recommended human dose (MRHD) of 20 mg. Mutagenesis Vardenafil was not mutagenic as assessed in either the in vitro bacterial Ames assay or the forward mutation assay in Chinese hamster V 79 cells.
Vardenafil was not clastogenic as assessed in either the in vitro chromosomal aberration test or the in vivo mouse micronucleus test. Impairment of Fertility Vardenafil did not impair fertility in male and female rats administered doses up to 100 mg/kg/day for 28 days prior to mating in males, and for 14 days prior to mating and through day 7 of gestation in females. In a corresponding 1-month rat toxicity study, this dose produced an AUC value for unbound vardenafil 200 fold greater than AUC in humans at the MRHD of 20 mg.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Vardenafil was not carcinogenic in rats and mice when administered daily for 24 months. In these studies systemic drug exposures (AUCs) for unbound (free) vardenafil and its major metabolite were approximately 400- and 170-fold for male and female rats, respectively, and 21-and 37-fold for male and female mice, respectively, the exposures observed in human males given the maximum recommended human dose (MRHD) of 20 mg. Mutagenesis Vardenafil was not mutagenic as assessed in either the in vitro bacterial Ames assay or the forward mutation assay in Chinese hamster V 79 cells.
Vardenafil was not clastogenic as assessed in either the in vitro chromosomal aberration test or the in vivo mouse micronucleus test. Impairment of Fertility Vardenafil did not impair fertility in male and female rats administered doses up to 100 mg/kg/day for 28 days prior to mating in males, and for 14 days prior to mating and through day 7 of gestation in females. In a corresponding 1-month rat toxicity study, this dose produced an AUC value for unbound vardenafil 200 fold greater than AUC in humans at the MRHD of 20 mg.
📄 Patient Package Insert ▾
Vardenafil Hydrochloride ( var-DEN-a-fil HYE-droe-KLOR-ide) Orally Disintegrating Tablets, USP Read the Patient Information about vardenafil hydrochloride orally disintegrating tablets before you start taking it and again each time you get a refill. There may be new information. You may also find it helpful to share this information with your partner.
This leaflet does not take the place of talking with your doctor. You and your doctor should talk about vardenafil hydrochloride orally disintegrating tablets when you start taking it and at regular checkups. If you do not understand the information, or have questions, talk with your doctor or pharmacist.
WHAT IMPORTANT INFORMATION SHOULD YOU KNOW ABOUT VARDENAFIL HYDROCHLORIDE ORALLY DISINTEGRATING TABLETS? Vardenafil hydrochloride orally disintegrating tablets are not interchangeable with vardenafil film-coated tablets (LEVITRA). Vardenafil hydrochloride orally disintegrating tablets can cause your blood pressure to drop suddenly to an unsafe level if it is taken with certain other medicines.
With a sudden drop in blood pressure, you could get dizzy, faint, or have a heart attack or stroke. Vardenafil hydrochloride orally disintegrating tablets contain phenylalanine which can be harmful to people who have phenylketonuria. Talk to your doctor if you have phenylketonuria.
Do not take vardenafil hydrochloride orally disintegrating tablets if you: · Take any medicines called “nitrates” (often used to control chest pain, also known as angina) · Use recreational drugs called “poppers” like amyl nitrate and butyl nitrate. · Take riociguat (Adempas ® ), a guanulate cyclase stimulator, a medicine that treats pulmonary arterial hypertension and chronic-thromboembolic pulmonary hypertension. (See “Who Should Not Take Vardenafil Hydrochloride Orally Disintegrating Tablets?” ) Tell all your healthcare providers that you take vardenafil hydrochloride orally disintegrating tablets.
If you need emergency medical care for a heart problem, it will be important for your healthcare provider to know when you last took vardenafil hydrochloride orally disintegrating tablets. WHAT ARE VARDENAFIL HYDROCHLORIDE ORALLY DISINTEGRATING TABLETS? Vardenafil hydrochloride orally disintegrating tablets are a prescription medicine taken by mouth for the treatment of erectile dysfunction (ED) in men.
ED is a condition where the penis does not harden and expand when a man is sexually excited, or when he cannot keep an erection. A man who has trouble getting or keeping an erection should see his doctor for help if the condition bothers him. Vardenafil hydrochloride orally disintegrating tablets may help a man with ED get and keep an erection when he is sexually excited.
Vardenafil hydrochloride orally disintegrating tablets does not: · Cure ED. · Increase a man’s sexual desire. · Protect a man or his partner from sexually transmitted diseases, including HIV. Speak to your doctor about ways to guard against sexually transmitted diseases. · Serve as a male form of birth control. Vardenafil hydrochloride orally disintegrating tablets are only for men with ED.
Vardenafil hydrochloride orally disintegrating tablets are not for women or children. Vardenafil hydrochloride orally disintegrating tablets must be used only under a doctor’s care. HOW DOES VARDENAFIL HYDROCHLORIDE ORALLY DISINTEGRATING TABLETS WORK?
When a man is sexually stimulated, his body’s normal physical response is to increase blood flow to his penis. This results in an erection. Vardenafil hydrochloride orally disintegrating tablets helps increase blood flow to the penis and may help men with ED get and keep an erection satisfactory for sexual activity.
Once a man has completed sexual activity, blood flow to his penis decreases, and his erection goes away. WHO CAN TAKE VARDENAFIL HYDROCHLORIDE ORALLY DISINTEGRATING TABLETS? Talk to your doctor to decide if vardenafil hydrochloride orally disintegrating tablets are right for you.
Vardenafil hydrochlorid… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Warnings and Precautions ( 5.2 ) 4/2023
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 62332-235-04 Vardenafil Hydrochloride Orally Disintegrating Tablets, USP 10 mg* per Tablet Place the orally disintegrating tablet in the mouth, on the tongue. The orally disintegrating tablet should be taken without liquid. Rx only 4 Tablets Alembic vardenafil-10mg.jpg