
Carboplatin 10 mg/mL Injection, Solution — NDC 63323-172-60 (Billing 63323-0172-60)
This is a package of Carboplatin 10 mg/mL Injection, Solution from Fresenius Kabi USA, LLC, marketed since Dec 2009 and currently FDA-listed. It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 038450
- GCN: 09217
- GPI-14 (Medi-Span): 21100015002045
- HICL (First Databank): 003904
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 597195
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Platinum-based Drug class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Carboplatin is used alone or in combination with other medications to treat cancer of the ovaries (cancer that begins in the female reproductive organs where eggs are formed) that has spread to other parts of the body, not improved, or that has worsened after treatment with other medications or radiation therapy. Carboplatin is in a class of medications known as platinum-containing compounds. It works by stopping or slowing the growth of cancer cells.
Read the full MedlinePlus article ↗- It treats ovarian cancer. It is used with other chemotherapy for the first treatment of advanced ovarian cancer, and alone when the cancer has come back after earlier chemotherapy.
- It is given by an infusion into a vein at a treatment center, usually taking 15 minutes or longer. Treatment days are typically about 4 weeks apart. Your team will tell you your ex...
- Nausea and vomiting are common, but you will get anti-nausea medicine before and after treatment. They usually ease within 24 hours. Call if vomiting is severe or will not stop.
- Call for fever or signs of infection, unusual bleeding or bruising, or new numbness or tingling. Get emergency help for rash, hives, wheezing, trouble breathing or faintness, since...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Carboplatin — tap one for details:
Carboplatin may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $3.20 | $191.88 / 60 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9045 | $3.153 / J9045 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 63323-0172-60 You're viewing this Main listing | 1 VIAL in 1 BOX / 60 mL in 1 VIAL | 2009-12-11 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| CARBOplatin 10 mg/mL 00703-4239-81 | Teva | 1 vial | — | AP | FDA listed | — |
| CARBOplatin 10 mg/mL 00703-4244-81 | Teva | 1 vial | — | AP | FDA listed | — |
| CARBOplatin 10 mg/mL 00703-4246-81 | Teva | 1 vial | — | AP | FDA listed | — |
| CARBOplatin 10 mg/mL 00703-4248-91 | Teva | 1 vial | — | AP | Discontinued | — |
| Carboplatin 10 mg/mL 16729-0295-12 | Accord | 1 vial | — | — | FDA listed | — |
| Carboplatin 10 mg/mL 54288-0164-01 | BPI | 1 vial | — | AP | FDA listed | — |
| Carboplatin 10 mg/mL 54288-0165-01 | BPI | 1 vial | — | AP | FDA listed | — |
| Carboplatin 10 mg/mL 54288-0166-01 | BPI | 1 vial | — | AP | FDA listed | — |
| Carboplatin 10 mg/mL 54288-0167-01 | BPI | 1 vial | — | AP | FDA listed | — |
| Carboplatin 50 mg/5mL 55150-0333-01 | Eugia | 1 vial | — | AP | FDA listed | — |
| Carboplatin 150 mg/15mL 55150-0334-01 | Eugia | 1 vial | — | AP | FDA listed | — |
| Carboplatin 450 mg/45mL 55150-0335-01 | Eugia | 1 vial | — | AP | FDA listed | — |
| Carboplatin 600 mg/60mL 55150-0386-01 | Eugia | 1 vial | — | AP | FDA listed | — |
| Carboplatin 10 mg/mL 60505-6282-01 | Apotex | 1 vial | — | AP | FDA listed | — |
| Carboplatin 10 mg/mL 61703-0150-05 | Hospira, | 1 vial | — | AP | FDA listed | — |
| Carboplatin 10 mg/mL 61703-0262-05 | Hospira, | 1 vial | — | AP | FDA listed | — |
| Carboplatin 10 mg/mL 61703-0339-18 | Hospira, | 1 vial | — | AP | FDA listed | — |
| Carboplatin 10 mg/mL 61703-0360-18 | Hospira, | 1 vial | — | AP | Discontinued | — |
| Carboplatin 10 mg/mL 61703-0600-05 | Hospira, | 1 vial | — | AP | FDA listed | — |
| Carboplatin 10 mg/mLthis 63323-0172-60 | Fresenius | 1 vial | — | — | FDA listed | — |
| Carboplatin 10 mg/mL 68083-0190-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Carboplatin 10 mg/mL 68083-0191-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Carboplatin 10 mg/mL 68083-0192-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Carboplatin 10 mg/mL 68083-0193-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Carboplatin 50 mg/5mL 82511-0003-05 | Teyro | 1 vial | — | AP | FDA listed | — |
| Carboplatin 150 mg/15mL 82511-0004-15 | Teyro | 1 vial | — | AP | FDA listed | — |
| Carboplatin 450 mg/45mL 82511-0005-45 | Teyro | 1 vial | — | AP | FDA listed | — |
| Carboplatin 600 mg/60mL 82511-0006-60 | Teyro | 1 vial | — | AP | FDA listed | — |
| Kyxata 80 mg/8mL 83831-0141-08 | Avyxa | 1 vial | — | — | FDA listed | — |
| Kyxata 500 mg/50mL 83831-0142-50 | Avyxa | 1 vial | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING Carboplatin Injection should be administered under the supervision of a qualified physician experienced in the use of cancer chemotherapeutic agents. Appropriate management of therapy and complications is possible only when adequate treatment facilities are readily available. Bone marrow suppression is dose related and may be severe, resulting in infection and/or bleeding.
Anemia may be cumulative and may require transfusion support. Vomiting is another frequent drug-related side effect. Anaphylactic-like reactions to carboplatin have been reported and may occur within minutes of carboplatin administration.
Epinephrine, corticosteroids, and antihistamines have been employed to alleviate symptoms.
🎯 Indications and Usage ▾
INDICATIONS: Initial Treatment of Advanced Ovarian Carcinoma Carboplatin Injection is indicated for the initial treatment of advanced ovarian carcinoma in established combination with other approved chemotherapeutic agents. One established combination regimen consists of carboplatin and cyclophosphamide. Two randomized controlled studies conducted by the NCIC and SWOG with carboplatin versus cisplatin, both in combination with cyclophosphamide, have demonstrated equivalent overall survival between the two groups (see CLINICAL STUDIES ).
There is limited statistical power to demonstrate equivalence in overall pathologic complete response rates and long-term survival (≥3 years) because of the small number of patients with these outcomes: the small number of patients with residual tumor <2 cm after initial surgery also limits the statistical power to demonstrate equivalence in this subgroup. Secondary Treatment of Advanced Ovarian Carcinoma Carboplatin Injection is indicated for the palliative treatment of patients with ovarian carcinoma recurrent after prior chemotherapy, including patients who have been previously treated with cisplatin.
Within the group of patients previously treated with cisplatin, those who have developed progressive disease while receiving cisplatin therapy may have a decreased response rate.
Initial Treatment of Advanced Ovarian Carcinoma Carboplatin Injection is indicated for the initial treatment of advanced ovarian carcinoma in established combination with other approved chemotherapeutic agents. One established combination regimen consists of carboplatin and cyclophosphamide. Two randomized controlled studies conducted by the NCIC and SWOG with carboplatin versus cisplatin, both in combination with cyclophosphamide, have demonstrated equivalent overall survival between the two groups (see CLINICAL STUDIES ).
There is limited statistical power to demonstrate equivalence in overall pathologic complete response rates and long-term survival (≥3 years) because of the small number of patients with these outcomes: the small number of patients with residual tumor <2 cm after initial surgery also limits the statistical power to demonstrate equivalence in this subgroup.
Secondary Treatment of Advanced Ovarian Carcinoma Carboplatin Injection is indicated for the palliative treatment of patients with ovarian carcinoma recurrent after prior chemotherapy, including patients who have been previously treated with cisplatin. Within the group of patients previously treated with cisplatin, those who have developed progressive disease while receiving cisplatin therapy may have a decreased response rate.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION: NOTE: Aluminum reacts with carboplatin causing precipitate formation and loss of potency, therefore, needles or intravenous sets containing aluminum parts that may come in contact with the drug must not be used for the preparation or administration of Carboplatin Injection. Single-Agent Therapy Carboplatin Injection, as a single agent, has been shown to be effective in patients with recurrent ovarian carcinoma at a dosage of 360 mg/m 2 IV on day 1 every 4 weeks (alternatively see Formula Dosing ).
In general, however, single intermittent courses of Carboplatin Injection should not be repeated until the neutrophil count is at least 2,000 and the platelet count is at least 100,000. Combination Therapy with Cyclophosphamide In the chemotherapy of advanced ovarian cancer, an effective combination for previously untreated patients consists of: Carboplatin Injection–300 mg/m 2 IV on day 1 every 4 weeks for 6 cycles (alternatively see Formula Dosing ). Cyclophosphamide–600 mg/m 2 IV on day 1 every 4 weeks for 6 cycles.
For directions regarding the use and administration of cyclophosphamide please refer to its package insert (see CLINICAL STUDIES ). Intermittent courses of Carboplatin Injection in combination with cyclophosphamide should not be repeated until the neutrophil count is at least 2,000 and the platelet count is at least 100,000. Dose Adjustment Recommendations Pretreatment platelet count and performance status are important prognostic factors for severity of myelosuppression in previously treated patients.
The suggested dose adjustments for single agent or combination therapy shown in the table below are modified from controlled trials in previously treated and untreated patients with ovarian carcinoma. Blood counts were done weekly, and the recommendations are based on the lowest post-treatment platelet or neutrophil value. Platelets Neutrophils Adjusted Dose * (From Prior Course) > 100,000 > 2000 125% 50 to 100,000 500 to 2000 No Adjustment < 50,000 <500 75% *Percentages apply to Carboplatin Injection as a single agent or to both carboplatin and cyclophosphamide in combination.
In the controlled studies, dosages were also adjusted at a lower level (50 to 60%) for severe myelosuppression. Escalations above 125% were not recommended for these studies. Carboplatin Injection is usually administered by an infusion lasting 15 minutes or longer.
No pre- or post-treatment hydration or forced diuresis is required. Patients with Impaired Kidney Function Patients with creatinine clearance values below 60 mL/min are at increased risk of severe bone marrow suppression. In renally-impaired patients who received single-agent carboplatin therapy, the incidence of severe leukopenia, neutropenia, or thrombocytopenia has been about 25% when the dosage modifications in the table below have been used.
Baseline Creatinine Clearance Recommended Dose on Day 1 41 to 59 mL/min 250 mg/m 2 16 to 40 mL/min 200 mg/m 2 The data available for patients with severely impaired kidney function (creatinine clearance below 15 mL/min) are too limited to permit a recommendation for treatment. These dosing recommendations apply to the initial course of treatment. Subsequent dosages should be adjusted according to the patient’s tolerance based on the degree of bone marrow suppression.
Formula Dosing Another approach for determining the initial dose of Carboplatin Injection is the use of mathematical formulae, which are based on a patient’s pre-existing renal function or renal function and desired platelet nadir. Renal excretion is the major route of elimination for carboplatin (see CLINICAL PHARMACOLOGY ). The use of dosing formulae, as compared to empirical dose calculation based on body surface area, allows compensation for patient variations in pretreatment renal function that might otherwise result in either underdosing (in patients with above average renal function) or overdosing (in patients with impaired renal function).
A simpl… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS: Carboplatin Injection is contraindicated in patients with a history of severe allergic reactions to cisplatin or other platinum-containing compounds. Carboplatin Injection should not be employed in patients with severe bone marrow depression or significant bleeding.
⚠️ Warnings ▾
WARNINGS: Bone marrow suppression (leukopenia, neutropenia, and thrombocytopenia) is dose-dependent and is also the dose-limiting toxicity. Peripheral blood counts should be frequently monitored during carboplatin treatment and, when appropriate, until recovery is achieved. Median nadir occurs at day 21 in patients receiving single-agent carboplatin.
In general, single intermittent courses of carboplatin should not be repeated until leukocyte, neutrophil, and platelet counts have recovered. Since anemia is cumulative, transfusions may be needed during treatment with carboplatin, particularly in patients receiving prolonged therapy. Bone marrow suppression is increased in patients who have received prior therapy, especially regimens including cisplatin.
Marrow suppression is also increased in patients with impaired kidney function. Initial carboplatin dosages in these patients should be appropriately reduced (see DOSAGE AND ADMINISTRATION ) and blood counts should be carefully monitored between courses. The use of carboplatin in combination with other bone marrow suppressing therapies must be carefully managed with respect to dosage and timing in order to minimize additive effects.
Carboplatin has limited nephrotoxic potential, but concomitant treatment with aminoglycosides has resulted in increased renal and/or audiologic toxicity, and caution must be exercised when a patient receives both drugs. Clinically significant hearing loss has been reported to occur in pediatric patients when carboplatin was administered at higher than recommended doses in combination with other ototoxic agents. Carboplatin can induce emesis, which can be more severe in patients previously receiving emetogenic therapy.
The incidence and intensity of emesis have been reduced by using premedication with antiemetics. Although no conclusive efficacy data exist with the following schedules of carboplatin, lengthening the duration of single intravenous administration to 24 hours or dividing the total dose over 5 consecutive daily pulse doses has resulted in reduced emesis. Although peripheral neurotoxicity is infrequent, its incidence is increased in patients older than 65 years and in patients previously treated with cisplatin.
Pre-existing cisplatin-induced neurotoxicity does not worsen in about 70% of the patients receiving carboplatin as secondary treatment. Loss of vision, which can be complete for light and colors, has been reported after the use of carboplatin with doses higher than those recommended in the package insert. Vision appears to recover totally or to a significant extent within weeks of stopping these high doses.
As in the case of other platinum-coordination compounds, allergic reactions to carboplatin have been reported. These may occur within minutes of administration and should be managed with appropriate supportive therapy. There is increased risk of allergic reactions including anaphylaxis in patients previously exposed to platinum therapy (see CONTRAINDICATIONS and ADVERSE REACTIONS: Allergic Reactions ).
High dosages of carboplatin (more than 4 times the recommended dose) have resulted in severe abnormalities of liver function tests. Carboplatin Injection may cause fetal harm when administered to a pregnant woman. Carboplatin has been shown to be embryotoxic and teratogenic in rats.
There are no adequate and well-controlled studies in pregnant women. If this drug is used during pregnancy, or if the patient becomes pregnant while receiving this drug, the patient should be apprised of the potential hazard to the fetus. Women of childbearing potential should be advised to avoid becoming pregnant.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS: To report SUSPECTED ADVERSE REACTIONS, contact Fresenius Kabi USA, LLC at 1-800-551-7176 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. For a comparison of toxicities when carboplatin or cisplatin was given in combination with cyclophosphamide, see CLINICAL STUDIES , Use with Cyclophosphamide for Initial Treatment of Ovarian Cancer, Comparative Toxicity. ADVERSE EXPERIENCES IN PATIENTS WITH OVARIAN CANCER First Line Combination Therapy * Percent Second Line Single Agent Therapy ** Percent Bone Marrow Thrombocytopenia < 100,000/mm 3 66 62 < 50,000/mm 3 33 35 Neutropenia < 2,000 cells/mm 3 96 67 < 1,000 cells/mm 3 82 21 Leukopenia < 4,000 cells/mm 3 97 85 < 2,000 cells/mm 3 71 26 Anemia < 11/g/dL 90 90 < 8 g/dL 14 21 Infections 16 5 Bleeding 8 5 Transfusions 35 44 Gastrointestinal Nausea and vomiting 93 92 Vomiting 83 81 Other GI side effects 46 21 Neurologic Peripheral neuropathies 15 6 Ototoxicity 12 1 Other sensory side effects 5 1 Central neurotoxicity 26 5 Renal Serum creatinine elevations 6 10 Blood urea elevations 17 22 Hepatic Bilirubin elevations 5 5 SGOT elevations 20 19 Alkaline phosphatase elevations 29 37 Electrolytes loss Sodium 10 47 Potassium 16 28 Calcium 16 31 Magnesium 61 43 Other side effects Pain 44 23 Asthenia 41 11 Cardiovascular 19 6 Respiratory 10 6 Allergic 11 2 Genitourinary 10 2 Alopecia 49 2 Mucositis 8 1 *Use with Cyclophosphamide for Initial Treatment of Ovarian Cancer Data are based on the experience of 393 patients with ovarian cancer (regardless of baseline status) who received initial combination therapy with carboplatin and cyclophosphamide in two randomized controlled studies conducted by SWOG and NCIC (see CLINICAL STUDIES ).
Combination with cyclophosphamide as well as duration of treatment may be responsible for the differences that can be noted in the adverse experience table. **Single Agent Use for the Secondary Treatment of Ovarian Cancer Data are based on the experience of 553 patients with previously treated ovarian carcinoma (regardless of baseline status) who received single-agent carboplatin. In the narrative section that follows, the incidences of adverse events are based on data from 1,893 patients with various types of tumors who received carboplatin as single-agent therapy.
Hematologic Toxicity Bone marrow suppression is the dose-limiting toxicity of carboplatin. Thrombocytopenia with platelet counts below 50,000/mm 3 occurs in 25% of the patients (35% of pretreated ovarian cancer patients); neutropenia with granulocyte counts below 1,000/mm 3 occurs in 16% of the patients (21% of pretreated ovarian cancer patients); leukopenia with WBC counts below 2,000/mm 3 occurs in 15% of the patients (26% of pretreated ovarian cancer patients). The nadir usually occurs about day 21 in patients receiving single-agent therapy.
By day 28, 90% of patients have platelet counts above 100,000/mm 3 ; 74% have neutrophil counts above 2,000/mm 3 ; 67% have leukocyte counts above 4,000/mm 3 . Marrow suppression is usually more severe in patients with impaired kidney function. Patients with poor performance status have also experienced a higher incidence of severe leukopenia and thrombocytopenia.
The hematologic effects, although usually reversible, have resulted in infectious or hemorrhagic complications in 5% of the patients treated with carboplatin, with drug-related death occurring in less than 1% of the patients. Fever has also been reported in patients with neutropenia. Anemia with hemoglobin less than 11 g/dL has been observed in 71% of the patients who started therapy with a baseline above that value.
The incidence of anemia increases with increasing exposure to carboplatin. Transfusions have been administered to 26% of the patients treated with carboplatin (44% of previously treated ovarian cancer patients). Bone marrow depression may be more severe when carboplatin is combined with other bone marrow suppressing drugs or with radiotherapy.
Gastrointestinal Toxicity Vomi… [Excerpted — this section continues on DailyMed.]
🆘 Overdosage ▾
OVERDOSAGE: There is no known antidote for Carboplatin Injection overdosage. The anticipated complications of overdosage would be secondary to bone marrow suppression and/or hepatic toxicity.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY: Carboplatin, like cisplatin, produces predominantly interstrand DNA cross-links rather than DNA-protein cross-links. This effect is apparently cell-cycle nonspecific. The aquation of carboplatin, which is thought to produce the active species, occurs at a slower rate than in the case of cisplatin.
Despite this difference, it appears that both carboplatin and cisplatin induce equal numbers of drug-DNA cross-links, causing equivalent lesions and biological effects. The differences in potencies for carboplatin and cisplatin appear to be directly related to the difference in aquation rates. In patients with creatinine clearances of about 60 mL/min, or greater, plasma levels of intact carboplatin decay in a biphasic manner after a 30-minute intravenous infusion of 300 to 500 mg/m 2 of carboplatin.
The initial plasma half-life (alpha) was found to be 1.1 to 2 hours (n=6), and the post distribution plasma half-life (beta) was found to be 2.6 to 5.9 hours (n=6). The total body clearance, apparent volume of distribution and mean residence time for carboplatin are
4.4L/hour, 16 L and 3.5 hours, respectively. The C max values and areas under the plasma concentration versus time curves from 0 to infinity (AUC inf) increase linearly with dose, although the increase was slightly more than dose proportional. Carboplatin, therefore, exhibits linear pharmacokinetics over the dosing range studied (300 to 500 mg/m 2 ).
Carboplatin is not bound to plasma proteins. No significant quantities of protein-free, ultrafilterable platinum-containing species other than carboplatin are present in plasma. However, platinum from carboplatin becomes irreversibly bound to plasma proteins and is slowly eliminated with a minimum half-life of 5 days.
The major route of elimination of carboplatin is renal excretion. Patients with creatinine clearances of approximately 60 mL/min or greater excrete 65% of the dose in the urine within 12 hours and 71% of the dose within 24 hours. All of the platinum in the 24-hour urine is present as carboplatin.
Only 3% to 5% of the administered platinum is excreted in the urine between 24 and 96 hours. There are insufficient data to determine whether biliary excretion occurs. In patients with creatinine clearances below 60 mL/min, the total body and renal clearances of carboplatin decrease as the creatinine clearance decreases.
Carboplatin dosages should therefore be reduced in these patients (see DOSAGE AND ADMINISTRATION ). The primary determinant of carboplatin clearance is glomerular filtration rate (GFR) and this parameter of renal function is often decreased in elderly patients. Dosing formulas incorporating estimates of GFR (see DOSAGE AND ADMINISTRATION ) to provide predictable carboplatin plasma AUCs should be used in elderly patients to minimize the risk of toxicity.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED: Product No. NDC No. 107260 63323-172-60 CARBOplatin Injection, 600 mg per 60 mL (10 mg per mL), in a 60 mL multiple dose vial packaged individually.
The container closure is not made with natural rubber latex. Storage Unopened vials of Carboplatin Injection are stable to the date indicated on the package when stored at 25°C (77°F); [excursions permitted from 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Protect from light.
Carboplatin Injection multidose vials maintain microbial, chemical, and physical stability for up to 14 days at 25°C following multiple needle entries. Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration. Solutions for infusion should be discarded 8 hours after preparation.
Handling and Disposal Caution should be exercised in handling and preparing carboplatin injection. Several guidelines on this subject have been published. 1-4 To minimize the risk of dermal exposure, always wear impervious gloves when handling vials containing carboplatin injection.
If carboplatin injection contacts the skin, immediately wash the skin thoroughly with soap and water. If carboplatin injection contacts mucous membranes, the membranes should be flushed immediately and thoroughly with water. More information is available in the references listed below.
Storage Unopened vials of Carboplatin Injection are stable to the date indicated on the package when stored at 25°C (77°F); [excursions permitted from 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Protect from light. Carboplatin Injection multidose vials maintain microbial, chemical, and physical stability for up to 14 days at 25°C following multiple needle entries.
Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration. Solutions for infusion should be discarded 8 hours after preparation.
Handling and Disposal Caution should be exercised in handling and preparing carboplatin injection. Several guidelines on this subject have been published. 1-4 To minimize the risk of dermal exposure, always wear impervious gloves when handling vials containing carboplatin injection.
If carboplatin injection contacts the skin, immediately wash the skin thoroughly with soap and water. If carboplatin injection contacts mucous membranes, the membranes should be flushed immediately and thoroughly with water. More information is available in the references listed below.
📋 Description ▾
DESCRIPTION: Carboplatin Injection is supplied as a sterile, pyrogen-free solution available in 10 mg per mL multiple dose vials containing 50 mg, 150 mg, 450 mg or 600 mg of carboplatin for administration by intravenous infusion. Each mL contains: carboplatin 10 mg, and water for injection to volume. Carboplatin is a platinum coordination compound.
The chemical name for carboplatin is platinum, diammine [1,1-cyclobutane-dicarboxylato(2-)-0,0’]-, (SP-4-2), and has the following structural formula: C 6 H 12 N 2 O 4 Pt M.W. 371.25 Carboplatin is a crystalline powder. It is soluble in water at a rate of approximately 14 mg/mL, and the pH of a 1% solution is 5 to 7.
It is virtually insoluble in ethanol, acetone, and dimethylacetamide. structure
⚠️ Precautions ▾
PRECAUTIONS: General Needles or intravenous administration sets containing aluminum parts that may come in contact with Carboplatin Injection should not be used for the preparation or administration of the drug. Aluminum can react with carboplatin causing precipitate formation and loss of potency. Drug Interactions The renal effects of nephrotoxic compounds may be potentiated by carboplatin.
Carcinogenesis, Mutagenesis, Impairment of Fertility The carcinogenic potential of carboplatin has not been studied, but compounds with similar mechanisms of action and mutagenicity profiles have been reported to be carcinogenic. Carboplatin has been shown to be mutagenic both in vitro and in vivo . It has also been shown to be embryotoxic and teratogenic in rats receiving the drug during organogenesis.
Secondary malignancies have been reported in association with multi-drug therapy. Nursing Mothers It is not known whether carboplatin is excreted in human milk. Because there is a possibility of toxicity in nursing infants secondary to carboplatin treatment of the mother, it is recommended that breast-feeding be discontinued if the mother is treated with Carboplatin Injection.
Pediatric Use Safety and effectiveness in pediatric patients have not been established (see WARNINGS; " audiologic toxicity"). Geriatric Use Of the 789 patients in initial treatment combination therapy studies (NCIC and SWOG), 395 patients were treated with carboplatin in combination with cyclophosphamide. Of these, 141 were over 65 years of age and 22 were 75 years or older.
In these trials, age was not a prognostic factor for survival. In terms of safety, elderly patients treated with carboplatin were more likely to develop severe thrombocytopenia than younger patients. In a combined database of 1,942 patients (414 were ≥65 years of age) that received single-agent carboplatin for different tumor types, a similar incidence of adverse events was seen in patients 65 years and older and in patients less than 65.
Other reported clinical experience has not identified differences in responses between elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. Because renal function is often decreased in the elderly, renal function should be considered in the selection of carboplatin dosage (see DOSAGE AND ADMINISTRATION ).
General Needles or intravenous administration sets containing aluminum parts that may come in contact with Carboplatin Injection should not be used for the preparation or administration of the drug. Aluminum can react with carboplatin causing precipitate formation and loss of potency.
Drug Interactions The renal effects of nephrotoxic compounds may be potentiated by carboplatin.
Carcinogenesis, Mutagenesis, Impairment of Fertility The carcinogenic potential of carboplatin has not been studied, but compounds with similar mechanisms of action and mutagenicity profiles have been reported to be carcinogenic. Carboplatin has been shown to be mutagenic both in vitro and in vivo . It has also been shown to be embryotoxic and teratogenic in rats receiving the drug during organogenesis.
Secondary malignancies have been reported in association with multi-drug therapy.
Nursing Mothers It is not known whether carboplatin is excreted in human milk. Because there is a possibility of toxicity in nursing infants secondary to carboplatin treatment of the mother, it is recommended that breast-feeding be discontinued if the mother is treated with Carboplatin Injection.
Pediatric Use Safety and effectiveness in pediatric patients have not been established (see WARNINGS; " audiologic toxicity").
Geriatric Use Of the 789 patients in initial treatment combination therapy studies (NCIC and SWOG), 395 patients were treated with carboplatin in combination with cyclophosphamide. Of these, 141 were over 65 years of age and 22 were 75 years or older. In these trials, age was not a prognostic factor for survival. In terms of safety, elde… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
CLINICAL STUDIES: Use with Cyclophosphamide for Initial Treatment of Ovarian Cancer In two prospectively randomized, controlled studies conducted by the National Cancer Institute of Canada, Clinical Trials Group (NCIC) and the Southwest Oncology Group (SWOG), 789 chemotherapy naive patients with advanced ovarian cancer were treated with carboplatin or cisplatin, both in combination with cyclophos-phamide every 28 days for 6 courses before surgical reevaluation. The following results were obtained from both studies: Comparative Efficacy Overview of Pivotal Trials NCIC SWOG Number of patients randomized 447 342 Median age (years) 60 62 Dose of cisplatin 75 mg/m 2 100 mg/m 2 Dose of carboplatin 300 mg/m 2 300 mg/m 2 Dose of cyclophosphamide 600 mg/m 2 600 mg/m 2 Residual tumor < 2 cm (number of patients) 39% (174/447) 14% (49/342) Clinical Response in Measurable Disease Patients NCIC SWOG Carboplatin (number of patients) 60% (48/80) 58% (48/83) Cisplatin (number of patients) 58% (49/85) 43% (33/76) 95% C.I. of difference (Carboplatin-Cisplatin) (-13.9%, 18.6%) (-2.3%, 31.1%) Pathologic Complete Response * NCIC SWOG Carboplatin (number of patients) 11% (24/224) 10% (17/171) Cisplatin (number of patients) 15% (33/223) 10% (17/171) 95% C.I. of difference (Carboplatin-Cisplatin) (-10.7%, 2.5%) (-6.9%, 6.9%) *114 Carboplatin and 109 Cisplatin patients did not undergo second look surgery in NCIC study.
90 Carboplatin and 106 Cisplatin patients did not undergo second look surgery in SWOG study. Progression-Free Survival (PFS) NCIC SWOG Median Carboplatin 59 weeks 49 weeks Cisplatin 61 weeks 47 weeks 2-year PFS * Carboplatin 31% 21% Cisplatin 31% 21% 95% C.I. of difference (Carboplatin-Cisplatin) (-9.3, 8.7) (-9.0, 9.4) 3-year PFS * Carboplatin 19% 8% Cisplatin 23% 14% 95% C.I. of difference (Carboplatin-Cisplatin) (-11.5, 4.5) (-14.1, 0.3) Hazard Ratio ** 1.10 1.02 95% C.I. (Carboplatin-Cisplatin) (0.89, 1.35) (0.81, 1.29) *Kaplan-Meier Estimates Unrelated deaths occurring in the absence of progression were counted as events (progression) in this analysis. **Analysis adjusted for factors found to be of prognostic significance were consistent with unadjusted analysis.
Survival NCIC SWOG Median Carboplatin 110 weeks 86 weeks Cisplatin 99 weeks 79 weeks 2-year Survival * Carboplatin 51.9% 40.2% Cisplatin 48.4% 39% 95% C.I. of difference (Carboplatin-Cisplatin) (-6.2, 13.2) (-9.8, 12.2) 3-year Survival * Carboplatin 34.6% 18.3% Cisplatin 33.1% 24.9% 95% C.I. of difference (Carboplatin-Cisplatin) (-7.7, 10.7) (-15.9, 2.7) Hazard Ratio** 95% C.I. 0.98 1.01 (Carboplatin-Cisplatin) (0.78, 1.23) (0.78, 1.30) *Kaplan-Meier Estimates **Analysis adjusted for factors found to be of prognostic significance were consistent with unadjusted analysis.
Comparative Toxicity The pattern of toxicity exerted by the carboplatin-containing regimen was significantly different from that of the cisplatin-containing combinations. Differences between the two studies may be explained by different cisplatin dosages and by different supportive care. The carboplatin-containing regimen induced significantly more thrombocytopenia and, in one study, significantly more leukopenia and more need for transfusional support.
The cisplatin-containing regimen produced significantly more anemia in one study. However, no significant differences occurred in incidences of infections and hemorrhagic episodes. Non-hematologic toxicities (emesis, neurotoxicity, ototoxicity, renal toxicity, hypomagnesemia, and alopecia) were significantly more frequent in the cisplatin-containing arms.
ADVERSE EXPERIENCES IN PATIENTS WITH OVARIAN CANCER NCIC STUDY Carboplatin Arm Percent * Cisplatin Arm Percent * P-Values ** Bone Marrow Thrombocytopenia < 100,000/mm 3 70 29 <0.001 < 50,000/mm 3 41 6 <0.001 Neutropenia < 2,000 cells/mm 3 97 96 n.s. < 1,000 cells/mm 3 81 79 n.s. Leukopenia < 4,000 cells/mm 3 98 97 n.s. < 2,000 cells/mm 3 68 52 0.001 Anemia < 11 g/dL 91 91 n.s. < 8 g/dL 18 12 n.s. Infections… [Excerpted — this section continues on DailyMed.]
📚 References ▾
REFERENCES: 1. NIOSH Alert: Preventing occupational exposures to antineoplastic and other hazardous drugs in healthcare settings. 2004.
U.S. Department of Health and Human Services, Public Health Service, Centers for Disease Control and Prevention, National Institute for Occupational Safety and Health, DHHS (NIOSH) Publication No. 2004-165.
2. OSHA Technical Manual, TED 1-0.15A, Section VI: Chapter 2. Controlling occupational exposure to hazardous drugs.
OSHA, 1999. http://www.osha.gov/dts/osta/otm/otm_vi/otm _vi_ 2.html 3. American Society of Health-System Pharmacists. ASHP guidelines on handling hazardous drugs.
Am J Health-Syst Pharm. 2006;63: 1172-1193. 4.
Polovich M, White JM, Kelleher LO, eds. 2005. Chemotherapy and biotherapy guidelines and recommendations for practice.
2nd ed. Pittsburgh, PA: Oncology Nursing Society. www.fresenius-kabi.com/us 451023D Revised: May 2021 logo
📄 Patient Package Insert ▾
Patient Information Read this entire leaflet carefully. Keep it for future reference. CARBOplatin Injection Rx only This information will help you learn more about Carboplatin Injection.
It cannot, however, cover all the possible warnings or side effects relating to Carboplatin Injection, and it does not list all of the benefits and risks of Carboplatin Injection. Your doctor should always be your first choice for detailed information about your medical condition and your treatment. Be sure to ask your doctor about any questions you may have.
What is cancer? Under normal conditions, the cells in your body divide and grow in an orderly, controlled fashion. Cell division and growth are necessary for the human body to perform its functions and to repair itself.
Cancer cells are different from normal cells because they are not able to control their own growth. The reasons for this abnormal growth are not yet fully understood. A tumor is a mass of unhealthy cells that are dividing and growing fast and in an uncontrolled way.
When a tumor invades surrounding healthy body tissue it is known as a malignant tumor. A malignant tumor can spread (metastasize) from its original location to other parts of the body. What is Carboplatin Injection?
Carboplatin Injection is a medicine that is used to treat cancer of the ovaries. It acts by interfering with the division of rapidly multiplying cells, particularly cancer cells. Who should not take Carboplatin Injection?
Treatment with Carboplatin Injection is not recommended if you: • are allergic to carboplatin or other platinum containing products; • have a weakened blood-forming system (bone marrow depression) or significant bleeding; • are pregnant, intend to become pregnant, or are breast feeding a baby. How is Carboplatin Injection used? Only a professional experienced in the use of cancer drugs should give you this medication.
Carboplatin Injection is given by dripping the medicine slowly and directly into a vein (intravenous infusion) for 15 minutes or longer. Your doctor will determine the dose of Carboplatin Injection for you based on your weight, height, and kidney function. Carboplatin Injection may be given alone or with other drugs.
Treatment is usually repeated every four weeks for a number of cycles. Before and after Carboplatin Injection treatment, your doctor may give you medication to lessen the nausea and vomiting associated with this cancer treatment. What should you tell your doctor before starting treatment with Carboplatin Injection?
Discuss the benefits and risks of Carboplatin Injection with your doctor before beginning treatment. Be sure to inform your doctor: • If you are allergic to carboplatin or other platinum-containing products; • If you are or intend to become pregnant, since carboplatin may harm the developing fetus. It is important to use effective birth control while you are being treated with Carboplatin Injection; • If you are breast-feeding, since nursing infants may be exposed to carboplatin in this way; • If you are taking other medicines, including all prescription and non-prescription (over-the-counter) drugs, since carboplatin may affect the action of other medicines; • If you have any other medical problems, especially chicken pox (including recent exposure to adults or children with chicken pox), shingles, hearing problems, infection, or kidney disease, since treatment with Carboplatin Injection increases the risk and severity of these conditions.
What should I avoid while taking Carboplatin Injection? If you are pregnant or think you might be pregnant, or if you are breast feeding, let your doctor know right away. Carboplatin Injection may harm your developing fetus or breast-feeding baby.
If you are a woman of childbearing age, you should use birth control to avoid getting pregnant while you are taking Carboplatin Injection. You should avoid contact with adults and children who have infections, and tell your doctor right away if you show signs of in… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
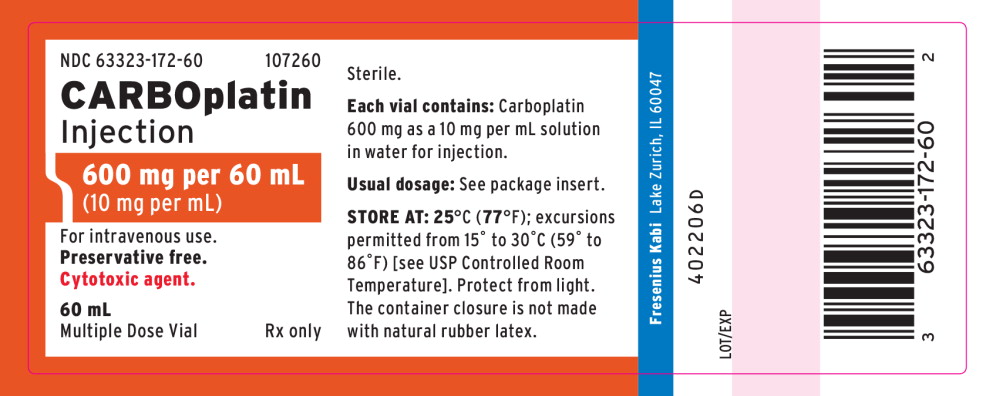
PACKAGE LABEL - PRINCIPAL DISPLAY - Carboplatin 600 mg per 60 mL Multiple Dose Vial Label NDC 63323-172-60 107260 CARBOplatin Injection 600 mg per 60 mL (10 mg per mL) For intravenous use. Preservative free. Cytotoxic agent.
60 mL Multiple Dose Vial Rx only PACKAGE LABEL - PRINCIPAL DISPLAY - Carboplatin 600 mg per 60 mL Multiple Dose Vial Carton Panel NDC 63323-172-60 107260 CARBOplatin Injection 600 mg per 60 mL (10 mg per mL) For intravenous use. Preservative free. Cytotoxic agent.
Rx only 60 mL Multiple Dose Vial vial pbox
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |