
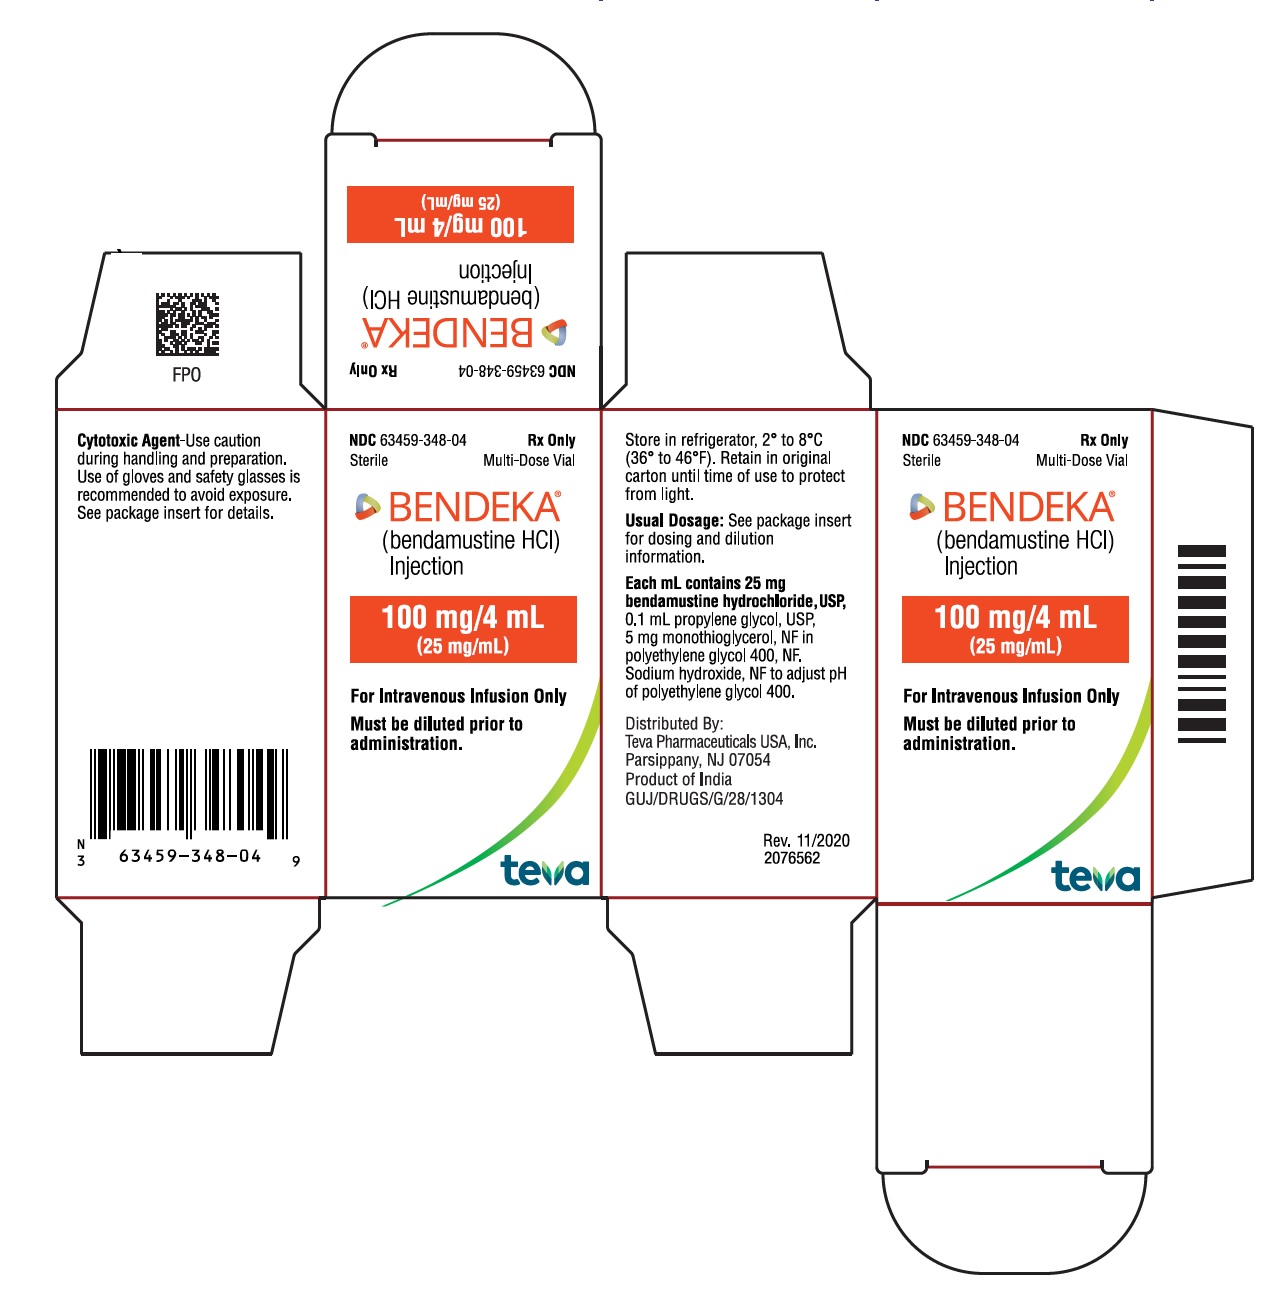
Bendeka bendamustine hydrochloride 25 mg/mL Injection, Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Alkylating Drug class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Bendamustine targets cancer cells in your blood and lymph system. It's approved to treat chronic lymphocytic leukemia (CLL) — a cancer that starts in white blood cells — and a type...
- What exactly is bendamustine treating in my body?
- The most common things people notice are nausea, fatigue, and fever. Because bendamustine lowers your blood counts significantly, you're also at a higher risk for infections. Call...
- What side effects should I actually expect, and which ones mean I need to call someone right away?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Bendamustine Hydrochloride — tap one for details:
Bendamustine Hydrochloride may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII AAO1P0WSXJ
Monothioglycerol is a clear liquid derived from glycerin with a sulfur-containing group added. It works as an antioxidant and reducing agent in medicines, helping prevent degradation of active ingredients during storage.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $350.67 | $1,402.68 / 4 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9034 | $12.532 / J9034 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Bendamustine Hydrochloride 100 mg 10019-0079-01 | Baxter | 1 vial | — | AP | FDA listed | — |
| Vivimusta 25 mg/mL 24338-0270-01 | Azurity | 1 vial | — | — | FDA listed | — |
| Belrapzo 100 mg/4mL 42367-0521-25 | Eagle | 1 vial | — | AP | FDA listed | — |
| Bendamustine Hydrochloride 25 mg/mL 60505-6228-00 | Apotex | 1 vial | — | AP | FDA listed | — |
| Bendeka 25 mg/mLthis 63459-0348-04 | Teva | 1 vial | — | — | FDA listed | — |
| Vivimusta 25 mg/mL 71225-0120-01 | Slayback | 1 vial | — | — | FDA listed | — |
| Bendamustine Hydrochloride 100 mg/4mL 83831-0183-04 | Avyxa | 1 vial | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9144568 ↗ | Method of use | U-1542 | Mar 15, 2033 |
| US 9572797 ↗ | Method of use | U-1971 | Jan 28, 2031 |
| US 10052385 ↗ | Method of use | U-1972 | Mar 15, 2033 |
| US 9597399 ↗ | Method of use | U-1972 | Mar 15, 2033 |
| US 9597399 ↗ | Method of use | U-1971 | Mar 15, 2033 |
| US 9034908 ↗ | Method of use | U-1542 | Mar 15, 2033 |
| US 8609707 ↗ | Method of use | U-1542 | Aug 11, 2031 |
| US 10052385 ↗ | Method of use | U-1971 | Mar 15, 2033 |
| US 9597397 ↗ | Method of use | U-1972 | Mar 15, 2033 |
| US 9572887 ↗ | Method of use | U-1972 | Mar 15, 2033 |
| US 9572887 ↗ | Method of use | U-1971 | Mar 15, 2033 |
| US 9572796 ↗ | Method of use | U-1972 | Jan 28, 2031 |
| US 9572797 ↗ | Method of use | U-1972 | Jan 28, 2031 |
| US 9579384 ↗ | Method of use | U-1971 | Mar 15, 2033 |
| US 9579384 ↗ | Method of use | U-1972 | Mar 15, 2033 |
| US 9000021 ↗ | Method of use | U-1542 | Mar 15, 2033 |
| US 9572796 ↗ | Method of use | U-1971 | Jan 28, 2031 |
| US 9597397 ↗ | Method of use | U-1971 | Mar 15, 2033 |
| US 12350257 ↗ | Method of use | U-1542 | Jan 28, 2031 |
| US 12350257 ↗ | Method of use | U-1971 | Jan 28, 2031 |
| US 12350257 ↗ | Method of use | U-1972 | Jan 28, 2031 |
| US 9597398 ↗ | Method of use | U-1971 | Mar 15, 2033 |
| US 11103483 ↗ | Method of use | U-1971 | Jan 28, 2031 |
| US 11103483 ↗ | Method of use | U-1972 | Jan 28, 2031 |
| US 11844783 ↗ | Method of use | U-1542 | Jan 28, 2031 |
| US 11844783 ↗ | Method of use | U-1972 | Jan 28, 2031 |
| US 11844783 ↗ | Method of use | U-1971 | Jan 28, 2031 |
| US 8791270 ↗ | Method of use | U-1790 | Jan 12, 2026 |
| US 11872214 ↗ | Drug product | — | Jan 28, 2031 |
| US 12138248 ↗ | Drug product | — | Jan 28, 2031 |
| US 10010533 ↗ | Drug product | — | Jan 28, 2031 |
| US 9265831 ↗ | Drug product | — | Jan 28, 2031 |
Is there a generic version of BENDEKA 100 MG/4 ML VIAL?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 63459-0348-04 You're viewing this | 1 VIAL, MULTI-DOSE in 1 CARTON (63459-348-04) / 4 mL in 1 VIAL, MULTI-DOSE | 2015-12-08 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE BENDEKA injection is an alkylating drug indicated for treatment of patients with: Chronic lymphocytic leukemia (CLL). Efficacy relative to first line therapies other than chlorambucil has not been established. ( 1.1 ) Indolent B-cell non-Hodgkin lymphoma (NHL) that has progressed during or within six months of treatment with rituximab or a rituximab-containing regimen. ( 1.2 )
1.1Chronic Lymphocytic Leukemia (CLL) BENDEKA ® is indicated for the treatment of patients with chronic lymphocytic leukemia. Efficacy relative to first line therapies other than chlorambucil has not been established.
1.2Non-Hodgkin Lymphoma (NHL) BENDEKA is indicated for the treatment of patients with indolent B-cell non-Hodgkin lymphoma that has progressed during or within six months of treatment with rituximab or a rituximab-containing regimen.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION For CLL : 100 mg/m 2 infused intravenously over 10 minutes on Days 1 and 2 of a 28-day cycle, up to 6 cycles. ( 2.1 ) For NHL : 120 mg/m 2 infused intravenously over 10 minutes on Days 1 and 2 of a 21-day cycle, up to 8 cycles. ( 2.2 )
2.1Dosing Instructions for CLL Recommended Dosage : The recommended dosage is 100 mg/m 2 administered intravenously over 10 minutes on Days 1 and 2 of a 28-day cycle, up to 6 cycles. Dose Delays, Dosage Modifications and Reinitiation of Therapy for CLL : Delay BENDEKA administration in the event of Grade 4 hematologic toxicity or clinically significant greater than or equal to Grade 2 non-hematologic toxicity. Once non-hematologic toxicity has recovered to less than or equal to Grade 1 and/or the blood counts have improved [Absolute Neutrophil Count (ANC) greater than or equal to 1 x 10 9 /L, platelets greater than or equal to 75 x 10 9 /L], reinitiate BENDEKA (bendamustine hydrochloride) injection at the discretion of the treating physician.
In addition, consider dose reduction. [see Warnings and Precautions (5.1) ] Dosage modifications for hematologic toxicity: for Grade 3 or greater toxicity, reduce the dose to 50 mg/m 2 on Days 1 and 2 of each cycle; if Grade 3 or greater toxicity recurs, reduce the dose to 25 mg/m 2 on Days 1 and 2 of each cycle. Dosage modifications for non-hematologic toxicity: for clinically significant Grade 3 or greater toxicity, reduce the dose to 50 mg/m 2 on Days 1 and 2 of each cycle. Consider dosage re-escalation in subsequent cycles at the discretion of the treating physician.
2.2Dosing Instructions for NHL Recommended Dosage : The recommended dose is 120 mg/m 2 administered intravenously over 10 minutes on Days 1 and 2 of a 21-day cycle, up to 8 cycles. Dose Delays, Dosage Modifications and Reinitiation of Therapy for NHL : Delay BENDEKA administration in the event of a Grade 4 hematologic toxicity or clinically significant greater than or equal to Grade 2 non-hematologic toxicity. Once non-hematologic toxicity has recovered to less than or equal to Grade 1 and/or the blood counts have improved [Absolute Neutrophil Count (ANC) greater than or equal to 1 x 10 9 /L, platelets greater than or equal to 75 x 10 9 /L], reinitiate BENDEKA at the discretion of the treating physician.
In addition, consider dose reduction. [see Warnings and Precautions (5.1) ] Dosage modifications for hematologic toxicity: for Grade 4 toxicity, reduce the dose to 90 mg/m 2 on Days 1 and 2 of each cycle; if Grade 4 toxicity recurs, reduce the dose to 60 mg/m 2 on Days 1 and 2 of each cycle. Dosage modifications for non-hematologic toxicity: for Grade 3 or greater toxicity, reduce the dose to 90 mg/m 2 on Days 1 and 2 of each cycle; if Grade 3 or greater toxicity recurs, reduce the dose to 60 mg/m 2 on Days 1 and 2 of each cycle.
2.3Preparation for Intravenous Administration BENDEKA is a hazardous drug. Follow applicable special handling and disposal procedures. 1 BENDEKA is in a multiple-dose vial.
At room temperature, BENDEKA is a clear, and colorless to yellow ready-to-dilute solution. Store BENDEKA at recommended refrigerated storage conditions (2°C to 8°C or 36°F to 46°F). When refrigerated, the contents may freeze.
Allow the vial to reach room temperature (15°C to 30°C or 59°F to 86°F) prior to use. Do not use the product if particulate matter is observed after achieving room temperature. Intravenous Infusion Aseptically withdraw the volume needed for the required dose from the 25 mg/mL solution as per Table A below and immediately transfer the solution to a 50 mL infusion bag of one of the following diluents: – 0.9% Sodium Chloride Injection, USP; or – 2.5% Dextrose/0.45% Sodium Chloride Injection, USP; or – 5% Dextrose Injection, USP.
The resulting final concentration of bendamustine hydrochloride in the infusion bag should be within 0.49 mg/mL to 5.6 mg/mL. After transferring, thoroughly mix the contents of the infusion bag. The admixture should be a…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 100 mg/4 mL (25 mg/mL) as a clear and colorless to yellow ready-to-dilute solution in a multiple-dose vial. Injection: 100 mg/4 mL (25 mg/mL) in a multiple-dose vial. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS BENDEKA is contraindicated in patients with a known hypersensitivity (e.g., anaphylactic and anaphylactoid reactions) to bendamustine, polyethylene glycol 400, propylene glycol, or monothioglycerol. [see Warnings and Precautions (5.4) ] BENDEKA is contraindicated in patients with a history of a hypersensitivity reaction to bendamustine, polyethylene glycol 400, propylene glycol, or monothioglycerol. Reactions to bendamustine hydrochloride have included anaphylaxis and anaphylactoid reactions ( 4 , 5.4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Myelosuppression: Delay or reduce dose, and restart treatment based on ANC and platelet count recovery. ( 2.1 , 5.1 ) Infections: Monitor for fever and other signs of infection or reactivation of infections and treat promptly. ( 5.2 ) Progressive multifocal leukoencephalopathy (PML): Monitor for new or worsening neurological, cognitive or behavioral signs or symptoms suggestive of PML.
( 5.3 ) Anaphylaxis and Infusion Reactions: Severe anaphylactic reactions have occurred. Monitor clinically and discontinue drug for severe reactions. Pre-medicate in subsequent cycles for milder reactions.
( 5.4 ) Tumor Lysis Syndrome: May lead to acute renal failure and death; anticipate and use supportive measures in patients at high risk. ( 5.5 ) Skin Reactions: Discontinue for severe skin reactions. Cases of SJS, DRESS and TEN, some fatal, have been reported.
( 5.6 ). Hepatotoxicity: Monitor liver chemistry tests prior to and during treatment. ( 5.7 ) Other Malignancies: Pre-malignant and malignant diseases have been reported.
( 5.8 ) Extravasation Injury: Take precautions to avoid extravasation, including monitoring intravenous infusion site during and after administration. ( 5.9 ) Embryo-Fetal Toxicity: Can cause fetal harm. Advise females of reproductive potential and males with female partners of reproductive potential of the potential risk to a fetus and to use an effective method of contraception.
( 5.10 , 8.1 , 8.3 )
5.1Myelosuppression Bendamustine hydrochloride caused severe myelosuppression (Grade 3-4) in 98% of patients in the two NHL studies [see Adverse Reactions (6.1) ] . Three patients (2%) died from myelosuppression-related adverse reactions; one each from neutropenic sepsis, diffuse alveolar hemorrhage with Grade 3 thrombocytopenia, and pneumonia from an opportunistic infection (CMV). BENDEKA causes myelosuppression.
Monitor complete blood counts, including leukocytes, platelets, hemoglobin (Hgb), and neutrophils frequently. In the clinical trials, blood counts were monitored every week initially. Hematologic nadirs occurred predominantly in the third week of therapy.
Myelosuppression may require dose delays and/or subsequent dose reductions if recovery to the recommended values has not occurred by the first day of the next scheduled cycle. Prior to the initiation of the next cycle of therapy, the ANC should be ≥ 1 x 10 9 /L and the platelet count should be ≥ 75 x 10 9 /L. [see Dosage and Administration (2.1) ]
5.2Infections Infection, including pneumonia, sepsis, septic shock, hepatitis and death has occurred in adult and pediatric patients in clinical trials and in postmarketing reports for bendamustine hydrochloride [see Adverse Reactions ( 6.1 , 6.2 )] . Patients with myelosuppression following treatment with bendamustine hydrochloride are more susceptible to infections. Advise patients with myelosuppression following BENDEKA treatment to contact a physician immediately if they have symptoms or signs of infection.
Patients treated with BENDEKA are at risk for reactivation of infections including (but not limited to) hepatitis B, cytomegalovirus, Mycobacterium tuberculosis, and herpes zoster. Patients should undergo appropriate measures (including clinical and laboratory monitoring, prophylaxis, and treatment) for infection and infection reactivation prior to administration.
5.3Progressive Multifocal Leukoencephalopathy (PML) Progressive multifocal leukoencephalopathy (PML), including fatal cases, have occurred following treatment with bendamustine, primarily in combination with rituximab or obinutuzumab [see Adverse Reactions (6.2) ] . Consider PML in the differential diagnosis in patients with new or worsening neurological, cognitive or behavioral signs or symptoms. If PML is suspected, withhold BENDEKA treatment and perform appropriate diagnostic evaluations.
Consider discontinuation or reduction of any concomitant chemotherapy or immunosuppressive therapy in patients who develop PML. 5.4…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions have been associated with bendamustine hydrochloride in clinical trials and are discussed in greater detail in other sections of the prescribing information. Myelosuppression [see Warnings and Precautions (5.1) ] Infections [see Warnings and Precautions (5.2) ] Progressive Multifocal Leukoencephalopathy [see Warnings and Precautions (5.3) ] Anaphylaxis and Infusion Reactions [see Warnings and Precautions (5.4) ] Tumor Lysis Syndrome [see Warnings and Precautions (5.5) ] Skin Reactions [see Warnings and Precautions (5.6) ] Hepatotoxicity [see Warnings and Precautions (5.7) ] Other Malignancies [see Warnings and Precautions (5.8) ] Extravasation Injury [see Warnings and Precautions (5.9) ] Adverse reactions (frequency >5%) during infusion and within 24 hours post-infusion are nausea and fatigue.
( 6.1 ) Most common adverse reactions (≥15%) for CLL are anemia, thrombocytopenia, neutropenia, lymphopenia, leukopenia, hyperbilirubinemia, pyrexia, nausea, vomiting. ( 6.1 , 6.2 ) Most common adverse reactions (≥15%) for NHL are lymphopenia, leukopenia, anemia, neutropenia, thrombocytopenia, nausea, fatigue, vomiting, diarrhea, pyrexia, constipation, anorexia, cough, headache, weight decreased, dyspnea, rash, and stomatitis. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Teva Pharmaceuticals at 1-888-483-8279 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data described below reflect exposure to bendamustine hydrochloride in 329 patients who participated in an actively controlled trial (N=153) for the treatment of CLL and two single arm studies (N=176) for the treatment of indolent B cell NHL.
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety of BENDEKA administered IV as a 50 mL admixture over a 10-minute infusion is supported by clinical trials using bendamustine hydrochloride administered IV as a 500 mL admixture over 30-60 minutes infusion time, as well as an open-label, crossover study in 81 ‘end-of-life’ cancer patients treated with BENDEKA.
In total, safety data from clinical studies are available from over 400 cancer patients exposed to bendamustine hydrochloride at doses in the range used in the treatment of CLL and NHL. No clinically significant differences in the adverse reaction profile were noted among bendamustine hydrochloride administered as a 500 mL admixture over standard infusion time (30-60 minutes) and BENDEKA administered as a 50 mL admixture in a ‘short-time’ infusion over 10 minutes. The safety and tolerability of BENDEKA was evaluated in an 8-week clinical study of BENDEKA in 81 ‘end-of-life’ cancer patients, diagnosed with solid tumors and hematologic malignancies (excluding CLL).
The population was 40-82 years of age, 58% females, 84% white, 12.3% Black, 1.2% Asian and 2.5% were classified as ‘other’. BENDEKA was administered IV at a 120 mg/m 2 dose as a 50 mL admixture over 10 minutes. Patients in the study received BENDEKA (50 mL IV, over 10 minutes) or bendamustine hydrochloride (500 mL IV, over 60 minutes) on Days 1 and 2 every 28 days for two consecutive 2-day cycles.
Adverse reactions (any grade) that occurred with a frequency greater than 5% during BENDEKA infusion and within one hour post-infusion were nausea (8.2%) and fatigue (5.5%). Adverse reactions (any grade) that occurred with a frequency greater than 5% within 24 hours of BENDEKA were nausea (10.9%) and fatigue (8.2%). Adverse reactions leading…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Consider alternative therapies that are not CYP1A2 inducers or inhibitors during treatment with BENDEKA. ( 7.1 )
7.1Effect of Other Drugs on BENDEKA CYP1A2 Inhibitors The coadministration of BENDEKA with CYP1A2 inhibitors may increase bendamustine plasma concentrations and may result in increased incidence of adverse reactions with BENDEKA [see Clinical Pharmacology (12.3) ] . Consider alternative therapies that are not CYP1A2 inhibitors during treatment with BENDEKA. CYP1A2 Inducers The coadministration of BENDEKA with CYP1A2 inducers may decrease bendamustine plasma concentrations and may result in decreased efficacy of BENDEKA [see Clinical Pharmacology (12.3) ] .
Consider alternative therapies that are not CYP1A2 inducers during treatment with BENDEKA.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 ) Infertility: May impair fertility. ( 8.3 ) Renal Impairment: Do not use in patients with creatinine clearance <30 mL/min. ( 8.6 ) Hepatic Impairment: Do not use in patients with total bilirubin 1.5-3 × ULN and AST or ALT 2.5-10 × ULN, or total bilirubin > 3 × ULN. ( 8.7 )
8.1Pregnancy Risk Summary In animal reproduction studies, intraperitoneal administration of bendamustine to pregnant mice and rats during organogenesis at doses 0.6 to 1.8 times the maximum recommended human dose (MRHD) resulted in embryo-fetal and/or infant mortality, structural abnormalities, and alterations to growth (see Data) . There are no available data on bendamustine hydrochloride use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.
Advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Bendamustine hydrochloride was intraperitoneally administered once to mice from 210 mg/m 2 (approximately 1.8 times the MRHD) during organogenesis and caused an increase in resorptions, skeletal and visceral malformations (exencephaly, cleft palates, accessory rib, and spinal deformities) and decreased fetal body weights. This dose did not appear to be maternally toxic and lower doses were not evaluated.
Repeat intraperitoneal administration of bendamustine hydrochloride to mice on gestation days 7 to 11 resulted in an increase in resorptions from 75 mg/m2 (approximately 0.6 times the MRHD) and an increase in abnormalities from 112.5 mg/m 2 (approximately 0.9 times the MRHD), similar to those seen after a single intraperitoneal administration. Bendamustine hydrochloride was intraperitoneally administered once to rats from 120 mg/m 2 (approximately the MRHD) on gestation days 4, 7, 9, 11, or 13 and caused embryo and fetal lethality as indicated by increased resorptions and a decrease in live fetuses.
A significant increase in external (effect on tail, head, and herniation of external organs [exomphalos]) and internal (hydronephrosis and hydrocephalus) malformations were seen in dosed rats.
8.2Lactation Risk Summary There are no data on the presence of bendamustine hydrochloride or its metabolites in either human or animal milk, the effects on the breastfed child, or the effects on milk production. Because of the potential for serious adverse reactions in the breastfed child, advise patients that breastfeeding is not recommended during treatment with BENDEKA, and for 1 week after the last dose.
8.3Females and Males of Reproductive Potential BENDEKA can cause embryo-fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] . Pregnancy Testing Pregnancy testing is recommended for females of reproductive potential prior to initiation of BENDEKA [see Use in Specific Populations (8.1) ] . Contraception Females Advise female patients of reproductive potential to use effective contraception during treatment with BENDEKA and for 6 months after the last dose.
Males Based on genotoxicity findings, advise males with female partners of reproductive potential to use effective contraception during treatment with BENDEKA and for 3 months after the last dose [see Nonclinical Toxicology (13.1) ] . Infertility Males Based on findings from clinical studies, BENDEKA may impair male fertility. Impaired spermatogenesis, azoospermia, and total germinal aplasia have been reported in male patients treated with alkylating agents, especially in combination with other drugs.
In some instances, spermatogenesis may return…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary In animal reproduction studies, intraperitoneal administration of bendamustine to pregnant mice and rats during organogenesis at doses 0.6 to 1.8 times the maximum recommended human dose (MRHD) resulted in embryo-fetal and/or infant mortality, structural abnormalities, and alterations to growth (see Data) . There are no available data on bendamustine hydrochloride use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.
Advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Bendamustine hydrochloride was intraperitoneally administered once to mice from 210 mg/m 2 (approximately 1.8 times the MRHD) during organogenesis and caused an increase in resorptions, skeletal and visceral malformations (exencephaly, cleft palates, accessory rib, and spinal deformities) and decreased fetal body weights. This dose did not appear to be maternally toxic and lower doses were not evaluated.
Repeat intraperitoneal administration of bendamustine hydrochloride to mice on gestation days 7 to 11 resulted in an increase in resorptions from 75 mg/m2 (approximately 0.6 times the MRHD) and an increase in abnormalities from 112.5 mg/m 2 (approximately 0.9 times the MRHD), similar to those seen after a single intraperitoneal administration. Bendamustine hydrochloride was intraperitoneally administered once to rats from 120 mg/m 2 (approximately the MRHD) on gestation days 4, 7, 9, 11, or 13 and caused embryo and fetal lethality as indicated by increased resorptions and a decrease in live fetuses.
A significant increase in external (effect on tail, head, and herniation of external organs [exomphalos]) and internal (hydronephrosis and hydrocephalus) malformations were seen in dosed rats.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. Safety, pharmacokinetics and efficacy were assessed in a single open-label trial (NCT01088984) in patients aged 1 to 19 years with relapsed or refractory acute leukemia, including 27 patients with acute lymphocytic leukemia (ALL) and 16 patients with acute myeloid leukemia (AML). Bendamustine hydrochloride was administered as an intravenous infusion over 60 minutes on Days 1 and 2 of each 21-day cycle.
There was no treatment response (CR+ CRp) in any patient. The safety profile in these patients was consistent with that seen in adults, and no new safety signals were identified. The pharmacokinetics of bendamustine in 43 patients, aged 1 to 19 years (median age of 10 years) were within range of values previously observed in adults given the same dose based on body surface area.
🧓 Geriatric Use ▾
8.5Geriatric Use No overall differences in safety were observed between patients ≥65 years of age and younger patients. Efficacy was lower in patients 65 and over with CLL receiving bendamustine hydrochloride based upon an overall response rate of 47% for patients 65 and over and 70% for younger patients. Progression free survival was also longer in younger patients with CLL receiving bendamustine (19 months vs.
12 months). No overall differences in efficacy in patients with non-Hodgkin Lymphoma were observed between geriatric patients and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE The intravenous LD 50 of bendamustine hydrochloride is 240 mg/m 2 in the mouse and rat. Toxicities included sedation, tremor, ataxia, convulsions and respiratory distress. Across all clinical experience, the reported maximum single dose received was 280 mg/m 2 .
Three of four patients treated at this dose showed ECG changes considered dose-limiting at 7 and 21 days post-dosing. These changes included QT prolongation (one patient), sinus tachycardia (one patient), ST and T wave deviations (two patients) and left anterior fascicular block (one patient). Cardiac enzymes and ejection fractions remained normal in all patients.
No specific antidote for bendamustine hydrochloride overdose is known. Management of overdosage should include general supportive measures, including monitoring of hematologic parameters and ECGs.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Bendamustine is a bifunctional mechlorethamine derivative containing a purine-like benzimidazole ring. Mechlorethamine and its derivatives form electrophilic alkyl groups. These groups form covalent bonds with electron-rich nucleophilic moieties, resulting in interstrand DNA crosslinks.
The bifunctional covalent linkage can lead to cell death via several pathways. Bendamustine is active against both quiescent and dividing cells. The exact mechanism of action of bendamustine remains unknown.
12.2Pharmacodynamics Based on the pharmacokinetics/pharmacodynamics analyses of data from adult patients with NHL, nausea increased with increasing bendamustine C max . Cardiac Electrophysiology The effect of bendamustine on the QTc interval was evaluated in 53 patients with indolent NHL and mantle cell lymphoma on Day 1 of Cycle 1 after administration of rituximab at 375 mg/m 2 intravenous infusion followed by a 30-minute intravenous infusion of bendamustine at 90 mg/m 2 /day. No mean changes greater than 20 milliseconds were detected up to one hour post infusion.
The potential for delayed effects on the QT interval after one hour was not evaluated.
12.3Pharmacokinetics Following a single dose of 120 mg/m 2 of bendamustine hydrochloride over 10-minute infusion, the mean C max achieved was 35 µg/mL (range 6 to 49 µg/mL), occurring typically at the end of infusion. Little or no accumulation in plasma is expected for bendamustine administered on Days 1 and 2 of a 28-day cycle. Distribution The protein binding of bendamustine ranged from 94 to 96% and was concentration independent from 1 to 50 µg/mL.
The blood to plasma concentration ratios in human blood ranged from 0.84 to 0.86 over a concentration range of 10 to 100 µg/mL. The mean steady-state volume of distribution (V SS ) of bendamustine was approximately 20 to 25 L. Elimination After a single intravenous dose of 120 mg/m 2 of bendamustine over 1 hour, the intermediate half-life (t ½ ) of the parent compound is approximately 40 minutes.
The mean terminal elimination t ½ of two active metabolites, γ-hydroxybendamustine (M3) and N desmethylbendamustine (M4) are approximately 3 hours and 30 minutes, respectively. Bendamustine clearance in humans is approximately 700 mL/min. Metabolism Bendamustine is extensively metabolized via hydrolytic, oxidative, and conjugative pathways.
Bendamustine is primarily metabolized via hydrolysis to monohydroxy (HP1) and dihydroxybendamustine (HP2) metabolites with low cytotoxic activity in vitro. Two active minor metabolites, M3 and M4, are primarily formed via CYP1A2 in vitro. M3 and M4 concentrations of these metabolites in plasma are 1/10 th and 1/100 th that of the parent compound, respectively.
Excretion Following IV infusion of radiolabeled bendamustine hydrochloride in cancer patients, approximately 76% of the dose was recovered. Approximately 50% of the dose was recovered in the urine (3.3% unchanged) and approximately 25% of the dose was recovered in the feces. Less than 1% of the dose was recovered in the urine as M3 and M4, and less than 5% of the dose was recovered in the urine as HP2.
Specific Populations No clinically meaningful effects on the pharmacokinetics of bendamustine were observed based on age (31 to 84 years), sex, mild to moderate renal impairment (CLcr ≥ 30 mL/min), or hepatic impairment with total bilirubin 1.5 < ULN and AST or ALT < 2.5 × ULN. The effects of severe renal impairment (CLcr < 30 mL/min), or hepatic impairment with total bilirubin 1.5-3 × ULN and AST or ALT 2.5-10 × ULN or total bilirubin > 3 × ULN on the pharmacokinetics of bendamustine is unknown. Race/Ethnicity Exposures in Japanese subjects (n=6) were 40% higher than that in non-Japanese subjects receiving the same dose.
The clinical importance of this difference on the safety and efficacy of bendamustine hydrochloride in Japanese subjects has not been established. Drug Interaction Studies In Vitro Studies Effect…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Bendamustine is a bifunctional mechlorethamine derivative containing a purine-like benzimidazole ring. Mechlorethamine and its derivatives form electrophilic alkyl groups. These groups form covalent bonds with electron-rich nucleophilic moieties, resulting in interstrand DNA crosslinks.
The bifunctional covalent linkage can lead to cell death via several pathways. Bendamustine is active against both quiescent and dividing cells. The exact mechanism of action of bendamustine remains unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Safe Handling and Disposal BENDEKA (bendamustine hydrochloride) injection is a hazardous drug. Follow applicable special handling and disposal procedures. 1 Care should be exercised in the handling and preparation of solutions prepared from BENDEKA (bendamustine hydrochloride) injection.
The use of gloves and safety glasses is recommended to avoid exposure in case of breakage of the vial or other accidental spillage. If a solution of BENDEKA (bendamustine hydrochloride) injection contacts the skin, wash the skin immediately and thoroughly with soap and water. If BENDEKA (bendamustine hydrochloride) injection contacts the mucous membranes, flush thoroughly with water.
How Supplied BENDEKA (bendamustine hydrochloride) injection is supplied in individual cartons of 5 mL clear multiple-dose vials containing 100 mg of bendamustine hydrochloride as a clear, and colorless to yellow ready-to-dilute solution. NDC 63459-348-04, 100 mg/4 mL (25 mg/mL) Storage Store BENDEKA (bendamustine hydrochloride) injection in refrigerator, 2°C to 8°C (36°F to 46°F). Retain in original carton until time of use to protect from light.
📋 Description ▾
11 DESCRIPTION BENDEKA (bendamustine hydrochloride) injection is an alkylating agent. The chemical name of bendamustine hydrochloride is 1H-benzimidazole-2-butanoic acid, 5-[bis(2-chloroethyl)amino]-1 methyl-, monohydrochloride. Its empirical molecular formula is C 16 H 21 Cl 2 N 3 O 2 · HCl, and the molecular weight is 394.7.
Bendamustine hydrochloride contains a mechlorethamine group and a benzimidazole heterocyclic ring with a butyric acid substituent, and has the following structural formula: BENDEKA (bendamustine hydrochloride) injection for intravenous use is supplied as a sterile, clear, and colorless to yellow ready-to-dilute solution in a multiple-dose clear glass vial. Each milliliter contains 25 mg of bendamustine hydrochloride, USP, 0.1 mL of Propylene Glycol, USP, 5 mg of Monothioglycerol, NF, in Polyethylene Glycol 400, NF. Sodium hydroxide may have been used to adjust the acidity of polyethylene glycol 400.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Myelosuppression Inform patients of the likelihood that BENDEKA (bendamustine hydrochloride) injection will cause a decrease in white blood cells, platelets, and red blood cells. They will need frequent monitoring of these parameters. They should be instructed to report shortness of breath, significant fatigue, bleeding, fever, or other signs of infection [see Warnings and Precautions (5.1) ] .
Progressive Multifocal Leukoencephalopathy (PML) Inform patients to immediately contact their healthcare provider if they experience confusion, memory loss, trouble thinking, difficulty talking or walking, vision loss or other neurological or cognitive symptoms [see Warnings and Precautions (5.3) ] . Anaphylaxis and Infusion Reactions Inform patients of the possibility of serious or mild allergic reactions and to immediately report rash, facial swelling, or difficulty breathing during or soon after infusion [see Warnings and Precautions (5.4) ] .
Skin Reactions Advise patients that a mild rash or itching may occur during treatment with BENDEKA (bendamustine hydrochloride) injection. Advise patients to immediately report severe or worsening rash or itching [see Warnings and Precautions (5.6) ] . Hepatotoxicity Inform patients of the possibility of developing liver function abnormalities and serious hepatic toxicity.
Advise patients to immediately contact their healthcare provider if signs of liver failure occur, including jaundice, anorexia, bleeding or bruising [see Warnings and Precautions (5.7) ] . Fatigue Advise patients that BENDEKA (bendamustine hydrochloride) injection may cause tiredness and to avoid driving any vehicle or operating any dangerous tools or machinery if they experience this side effect [see Adverse Reactions (6.1) ] . Nausea and Vomiting Advise patients that BENDEKA (bendamustine hydrochloride) injection may cause nausea and/or vomiting.
Patients should report nausea and vomiting so that symptomatic treatment may be provided [see Adverse Reactions (6.1) ] . Diarrhea Advise patients that BENDEKA (bendamustine hydrochloride) injection may cause diarrhea. Patients should report diarrhea to the physician so that symptomatic treatment may be provided [see Adverse Reactions (6.1) ] .
Non-melanoma Skin Cancer (NMSC) Advise patients to undergo regular skin cancer screenings, and to report any suspicious skin changes to their healthcare provider [see Warnings and Precautions (5.8) ] . Embryo-Fetal Toxicity Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.10) , Use in Specific Populations (8.2, 8.3) and Nonclinical Toxicology (13.1) ] .
Advise female patients of reproductive potential to use effective contraception during treatment with BENDEKA and for 6 months after the last dose [see Use in Specific Populations (8.1 , 8.3) ] . Advise males with female partners of reproductive potential to use effective contraception during treatment with BENDEKA and for 3 months after the last dose [see Use in Specific Populations (8.3) , and Nonclinical Toxicology (13.1) ] . Lactation Advise females not to breastfeed during treatment with BENDEKA and for 1 week after the last dose [see Use in Specific Populations (8.2) ] .
Infertility Advise males of reproductive potential that BENDEKA may impair fertility [see Use in Specific Populations (8.3) ] . BEN-012 Manufactured For: Teva Pharmaceuticals 400 Interpace Parkway #3, Parsippany, NJ 07054 All rights reserved.