
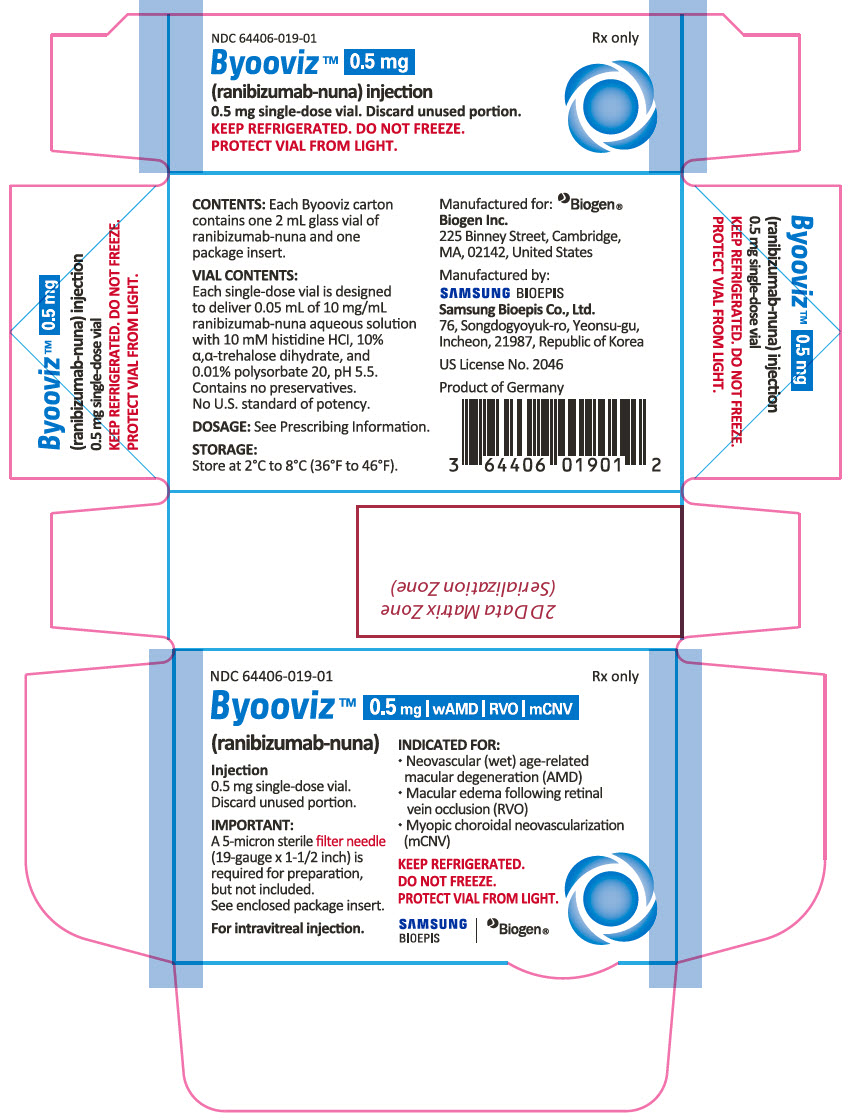
Byooviz ranibizumab-nuna 10 mg/mL Injection, Solution, 1 vial — NDC 64406-019-01 (Billing 64406-0019-01)
This is a package of 1 vial of Byooviz ranibizumab-nuna 10 mg/mL Injection, Solution from BIOGEN INC., marketed since Jun 2022 and currently FDA-listed, this package's marketing is listed to end Jul 2028. It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 64406-019-01 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 64406 labeler · 019 product · 01 package
- Package marketed since
- Jun 1, 2022
- Package marketing ended
- Jul 19, 2028
- Sample package
- No — commercial package
- Barcode (UPC-A, from the NDC)
- 3 6440601901 2
- Medicaid fills, this package
- 419 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 082681
- GCN: 51027
- GPI-14 (Medi-Span): 86655060502020
- HICL (First Databank): 047583
- AHFS class code: 52:92.00.00
- RxCUI (RxNorm): 2602353
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Vascular Endothelial Growth Factor Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Ranibizumab implant is used to treat wet age-related macular degeneration (AMD; an eye disease that causes central vision loss [ability to see straight ahead]), diabetic macular edema (an eye disease caused by diabetes that can lead to vision loss) and diabetic retinopathy (damage to the eyes caused by diabetes). Ranibizumab is in a class of medications called vascular endothelial growth factor A (VEGF-A) antagonists. It works by stopping abnormal blood vessel growth and leakage in the eye(s) that may cause vision loss.
Read the full MedlinePlus article ↗- It treats retinal diseases. Susvimo, the implant form, is used for wet AMD, diabetic macular edema and diabetic retinopathy. It is for people who already responded to at least two...
- An eye specialist gives it inside the eye. With Susvimo, a small implant is surgically placed in your eye and refilled about every 6 months (AMD and DME) or about every 9 months (D...
- Eye effects are most common. These include bleeding on the white of the eye, eye pain, floaters, higher eye pressure and blurred vision. Call right away for worsening pain, redness...
- The implant carries a higher risk of a serious eye infection called endophthalmitis than monthly injections. Many cases involved the eye’s surface covering wearing away or pulling...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $9,934.17 | $496.71 / 0.05 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · Q5124 | $240.972 / Q5124 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Oct 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 64406-0019-01 You're viewing this Main listing | 1 VIAL, SINGLE-DOSE in 1 CARTON / .05 mL in 1 VIAL, SINGLE-DOSE | 2022-06-01 | Jul 19, 2028 | Active |
| 64406-0019-08 64406-019-08 | 1 VIAL, SINGLE-DOSE in 1 CARTON / .05 mL in 1 VIAL, SINGLE-DOSE | 2022-10-03 | Jul 19, 2028 | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 64406-0019-08?
What NDC number is used to bill for this package of Byooviz ranibizumab-nuna 10 mg/mL Injection, Solution?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Byooviz 10 mg/mLthis 64406-0019-01 | BIOGEN | 1 vial | — | — | FDA listed | — |
| Byooviz 10 mg/mL 82667-0018-05 | Harrow | 1 vial | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Purple Book · refreshed Oct 5, 2026
- CMS NADAC weekly file
Availability & biosimilar status
3 interchangeables are FDA-licensed for this reference biologic — see the list below. (Biologics have no small-molecule generics.)
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Sep 17, 2033 |
Is there a biosimilar for BYOOVIZ 0.5 MG/0.05 ML VIAL?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
- FDA Purple Book · refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Ranibizumab Injection inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 4QD397987E
An amino acid used as a buffer and stabilizer in medications. It helps maintain the pH balance and protects the active drug from breaking down during storage and use.
-
UNII 1D5Q932XM6
An amino acid salt used in medicines as a buffer and pH regulator. It helps maintain the proper acidity level in liquid formulations to keep the drug stable and effective.
-
UNII 7T1F30V5YH
A synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together and keeps them from separating in liquid formulations.
-
UNII 7YIN7J07X4
A natural sugar derived from plants and microorganisms. It acts as a filler to give the medication bulk and stability, and helps preserve the active ingredient during storage and manufacturing.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from BIOGEN INC. labeler code 64406
- TYSABRI natalizumab 300 mg/15mL Injection NDC 64406-008-01
- Plegridy Pen peginterferon beta-1a 125 ug/.5mL Injection, Solution NDC 64406-011-01
- Plegridy Pen peginterferon beta-1a Kit NDC 64406-012-01
- Plegridy peginterferon beta-1a 125 ug/.5mL Injection, Solution NDC 64406-015-01
- Plegridy peginterferon beta-1a Kit NDC 64406-016-01
- Plegridy peginterferon beta-1a 125 ug/.5mL Injection, Solution NDC 64406-017-01
- Vumerity diroximel fumarate 231 mg Capsule NDC 64406-020-01
- Tofidence Tocilizumab 20 mg/mL Injection NDC 64406-022-01
- Tofidence Tocilizumab 20 mg/mL Injection NDC 64406-023-01
- Tofidence Tocilizumab 20 mg/mL Injection NDC 64406-024-01
- Zurzuvae zuranolone 20 mg Capsule NDC 64406-029-01
- Zurzuvae zuranolone 25 mg Capsule NDC 64406-030-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE BYOOVIZ is indicated for the treatment of patients with: BYOOVIZ, a vascular endothelial growth factor (VEGF) inhibitor, is indicated for the treatment of patients with: Neovascular (Wet) Age-Related Macular Degeneration (AMD) ( 1.1 ) Macular Edema Following Retinal Vein Occlusion (RVO) ( 1.2 ) Myopic Choroidal Neovascularization (mCNV) ( 1.3 )
1.1 Neovascular (Wet) Age-Related Macular Degeneration (AMD)
1.2 Macular Edema Following Retinal Vein Occlusion (RVO)
1.3 Myopic Choroidal Neovascularization (mCNV)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION For ophthalmic intravitreal injection only ( 2.1 ) Neovascular (Wet) Age-Related Macular Degeneration (AMD) ( 2.2 ) : BYOOVIZ 0.5 mg (0.05 mL) is recommended to be administered by intravitreal injection once a month (approximately 28 days). Although not as effective, patients may be treated with 3 monthly doses followed by less frequent dosing with regular assessment. Although not as effective, patients may also be treated with one dose every 3 months after 4 monthly doses.
Patients should be assessed regularly. Macular Edema Following Retinal Vein Occlusion (RVO) ( 2.3 ) : BYOOVIZ 0.5 mg (0.05 mL) is recommended to be administered by intravitreal injection once a month (approximately 28 days). Myopic Choroidal Neovascularization (mCNV) ( 2.4 ) : BYOOVIZ 0.5 mg (0.05 mL) is recommended to be initially administered by intravitreal injection once a month (approximately 28 days) for up to three months.
Patients may be retreated if needed.
2.1General Dosing Information FOR OPHTHALMIC INTRAVITREAL INJECTION. Vials: A 5-micron sterile filter needle (18-gauge × 1-1/2 inch or 19-gauge × 1-1/2 inch), a 1-mL Luer lock syringe and a 30- gauge × ½ inch sterile injection needle are needed but not included.
2.2Neovascular (Wet) Age-Related Macular Degeneration (AMD) BYOOVIZ 0.5 mg (0.05 mL of 10 mg/mL solution) is recommended to be administered by intravitreal injection once a month (approximately 28 days). Although not as effective, patients may be treated with 3 monthly doses followed by less frequent dosing with regular assessment. In the 9 months after three initial monthly doses, less frequent dosing with 4-5 doses on average is expected to maintain visual acuity while monthly dosing may be expected to result in an additional average 1-2 letter gain.
Patients should be assessed regularly [ see Clinical Studies (14.1) ]. Although not as effective, patients may also be treated with one dose every 3 months after 4 monthly doses. Compared with continued monthly dosing, dosing every 3 months over the next 9 months will lead to an approximate 5-letter (1-line) loss of visual acuity benefit, on average.
Patients should be assessed regularly [ see Clinical Studies (14.1) ].
2.3Macular Edema Following Retinal Vein Occlusion (RVO) BYOOVIZ 0.5 mg (0.05 mL of 10 mg/mL solution) is recommended to be administered by intravitreal injection once a month (approximately 28 days). In Studies RVO-1 and RVO-2, patients received monthly injections of ranibizumab for 6 months. In spite of being guided by optical coherence tomography and visual acuity re-treatment criteria, patients who were then not treated at Month 6 experienced on average, a loss of visual acuity at Month 7, whereas patients who were treated at Month 6 did not.
Patients should be treated monthly [ see Clinical Studies (14.2) ].
2.4Myopic Choroidal Neovascularization (mCNV) BYOOVIZ 0.5 mg (0.05 mL of 10 mg/mL BYOOVIZ solution) is recommended to be initially administered by intravitreal injection once a month (approximately 28 days) for up to 3 months. Patients may be retreated if needed [ see Clinical Studies (14.3) ].
2.5Preparation for Administration Vial: Using aseptic technique, all of the BYOOVIZ vial contents are withdrawn through a 5-micron (19- gauge × 1-1/2 inch), sterile filter needle attached to a 1 mL syringe (not included). The filter needle should be discarded after withdrawal of the vial contents and should not be used for intravitreal injection. The filter needle should be replaced with a sterile 30-gauge × ½ inch needle for the intravitreal injection.
Use aseptic technique to carry out the following preparation steps: Prepare for intravitreal injection with the following medical devices for single use (not included): a 5-micron sterile filter needle (18-gauge × 1-1/2 inch or 19-gauge × 1-1/2 inch) a 1 mL sterile Luer lock syringe (with marking to measure 0.05 mL) a sterile injection needle (30-gauge × 1/2-inch) Before withdrawal, disinfect t… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Single-dose glass vial designed to provide 0.05 mL for intravitreal injection. Clear to slightly opalescent and colorless to pale yellow, 10 mg/mL solution. Single-dose glass vial designed to provide 0.05 mL for intravitreal injections: 10 mg/mL solution. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Ocular or periocular infections ( 4.1 ) Hypersensitivity ( 4.2 )
4.1Ocular or Periocular Infections BYOOVIZ is contraindicated in patients with ocular or periocular infections.
4.2Hypersensitivity BYOOVIZ is contraindicated in patients with known hypersensitivity to ranibizumab products or any of the excipients in BYOOVIZ. Hypersensitivity reactions may manifest as severe intraocular inflammation.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Endophthalmitis and retinal detachments may occur following intravitreal injections. Patients should be monitored following the injection ( 5.1 ). Increases in intraocular pressure (IOP) have been noted both pre- and post-intravitreal injection ( 5.2 ). There is a potential risk of arterial thromboembolic events following intravitreal use of VEGF inhibitors ( 5.3 ).
5.1Endophthalmitis and Retinal Detachments Intravitreal injections, including those with ranibizumab products, have been associated with endophthalmitis and retinal detachments. Proper aseptic injection technique should always be used when administering BYOOVIZ. In addition, patients should be monitored following the injection to permit early treatment should an infection occur [ see Dosage and Administration (2.5 , 2.6) and Patient Counseling Information (17) ].
5.2Increases in Intraocular Pressure Increases in intraocular pressure have been noted both pre-injection and post-injection (at 60 minutes) while being treated with ranibizumab products. Monitor intraocular pressure prior to and following intravitreal injection with BYOOVIZ and manage appropriately [ see Dosage and Administration (2.6) ].
5.3Thromboembolic Events Although there was a low rate of arterial thromboembolic events (ATEs) observed in the ranibizumab clinical trials, there is a potential risk of ATEs following intravitreal use of VEGF inhibitors. Arterial thromboembolic events are defined as nonfatal stroke, nonfatal myocardial infarction, or vascular death (including deaths of unknown cause). Neovascular (Wet) Age-Related Macular Degeneration The ATE rate in the three controlled neovascular AMD studies (AMD-1, AMD-2, AMD-3) during the first year was 1.9% (17 of 874) in the combined group of patients treated with 0.3 mg or 0.5 mg ranibizumab compared with 1.1% (5 of 441) in patients from the control arms [ see Clinical Studies (14.1) ].
In the second year of Studies AMD-1 and AMD-2, the ATE rate was 2.6% (19 of 721) in the combined group of ranibizumab-treated patients compared with 2.9% (10 of 344) in patients from the control arms. In Study AMD-4, the ATE rates observed in the 0.5 mg arms during the first and second year were similar to rates observed in Studies AMD-1, AMD-2, and AMD-3. In a pooled analysis of 2-year controlled studies [AMD-1, AMD-2, and a study of ranibizumab used adjunctively with verteporfin photodynamic therapy (PDT)], the stroke rate (including both ischemic and hemorrhagic stroke) was 2.7% (13 of 484) in patients treated with 0.5 mg ranibizumab compared to 1.1% (5 of 435) in patients in the control arms [odds ratio 2.2 (95% confidence interval (0.8-7.1)].
Macular Edema Following Retinal Vein Occlusion The ATE rate in the two controlled RVO studies during the first 6 months was 0.8% in both the ranibizumab and control arms of the studies (4 of 525 in the combined group of patients treated with 0.3 mg or 0.5 mg ranibizumab and 2 of 260 in the control arms) [ see Clinical Studies (14.2) ]. The stroke rate was 0.2% (1 of 525) in the combined group of ranibizumab -treated patients compared to 0.4% (1 of 260) in the control arms.
5.4Retinal Vasculitis with or without Occlusion Retinal vasculitis with or without occlusion, typically in the presence of preexisting intraocular inflammation or post-treatment with other intravitreal agents, have been reported with the use of ranibizumab products. Discontinue treatment with BYOOVIZ in patients who develop these events. Patients should be instructed to report any change in vision without delay [ see Patient Counseling Information (17) ].
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the label: Endophthalmitis and Retinal Detachments [ see Warnings and Precautions (5.1) ] Increases in Intraocular Pressure [ see Warnings and Precautions (5.2) ] Thromboembolic Events [ see Warnings and Precautions (5.3) ] The most common adverse reactions (reported more frequently in ranibizumab treated subjects than control subjects) are conjunctival hemorrhage, eye pain, vitreous floaters, and increased IOP ( 6.2 ).
To report SUSPECTED ADVERSE REACTIONS, contact Biogen Inc. at 1-877-422-8360 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Injection Procedure Serious adverse reactions related to the injection procedure have occurred in < 0.1% of intravitreal injections, including endophthalmitis [ see Warnings and Precautions (5.1) ], rhegmatogenous retinal detachment, and iatrogenic traumatic cataract.
6.2Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of the same or another drug and may not reflect the rates observed in practice. The data below reflect exposure to 0.5 mg ranibizumab in 440 patients with neovascular AMD in Studies AMD-1, AMD-2, and AMD-3; in 259 patients with macular edema following RVO. Safety data observed in 224 patients with mCNV, as well as Studies AMD-4 and D-3, were consistent with these results.
On average, the rates and types of adverse reactions in patients were not significantly affected by dosing regimen. Ocular Reactions Table 1 shows frequently reported ocular adverse reactions in ranibizumab-treated patients compared with the control group. Table 1 Ocular Reactions in the AMD, and RVO Studies Adverse Reaction AMD 2-year AMD 1-year RVO 6-month Ranibizumab 0.5 mg Control Ranibizumab 0.5 mg Control Ranibizumab 0.5 mg Control n=379 n=379 n=440 n=441 n=259 n=260 Conjunctival hemorrhage 74% 60% 64% 50% 48% 37% Eye pain 35% 30% 26% 20% 17% 12% Vitreous floaters 27% 8% 19% 5% 7% 2% Intraocular pressure increased 24% 7% 17% 5% 7% 2% Vitreous detachment 21% 19% 15% 15% 4% 2% Intraocular inflammation 18% 8% 13% 7% 1% 3% Cataract 17% 14% 11% 9% 2% 2% Foreign body sensation in eyes 16% 14% 13% 10% 7% 5% Eye irritation 15% 15% 13% 12% 7% 6% Lacrimation increased 14% 12% 8% 8% 2% 3% Blepharitis 12% 8% 8% 5% 0% 1% Dry eye 12% 7% 7% 7% 3% 3% Visual disturbance or vision blurred 18% 15% 13% 10% 5% 3% Eye pruritis 12% 11% 9% 7% 1% 2% Ocular hyperemia 11% 8% 7% 4% 5% 3% Retinal disorder 10% 7% 8% 4% 2% 1% Maculopathy 9% 9% 6% 6% 11% 7% Retinal degeneration 8% 6% 5% 3% 1% 0% Ocular discomfort 7% 4% 5% 2% 2% 2% Conjunctival hyperemia 7% 6% 5% 4% 0% 0% Posterior capsule opacification 7% 4% 2% 2% 0% 1% Injection site hemorrhage 5% 2% 3% 1% 0% 0% Non-Ocular Reactions Non-ocular adverse reactions with an incidence of ≥ 5% in patients receiving ranibizumab for AMD, and/or RVO and which occurred at a ≥ 1% higher frequency in patients treated with ranibizumab compared to control are shown in Table 2.
Though less common, wound healing complications were also observed in some studies. Table 2 Non-Ocular Reactions in the AMD, and RVO Studies Adverse Reaction AMD 2-year AMD 1-year RVO 6-month Ranibizumab 0.5 mg Control Ranibizumab 0.5 mg Control Ranibizumab 0.5 mg Control n=379 n=379 n=440 n=441 n=259 n=260 Nasopharyngitis 16% 13% 8% 9% 5% 4% Anemia 8% 7% 4% 3% 1% 1% Nausea 9% 6% 5% 5% 1% 2% Cough 9% 8% 5% 4% 1% 2% Constipation 5% 7% 3% 4% 0% 1% Seasonal allergy 4% 4% 2% 2% 0% 2% Hypercholesterolemia 5% 5% 3% 2% 1% 1% Influenza 7% 5% 3% 2% 3% 2% Renal failure 1% 1% 0% 0% 0% 0% Upper respiratory tract infection 9% 8% 5% 5% 2% 2% Gastroesophageal reflux disease 4% 6% 3% 4% 1% 0% Headache 12% 9% 6% 5% 3% 3% Edema peripheral 3% 5% 2% 3% 0% 1% Renal failure chronic 0% 1% 0% 0% 0% 0% Neuropathy peripheral 1% 1% 1% 0% 0% 0% Sinusitis 8% 7% 5% 5% 3%… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Drug interaction studies have not been conducted with ranibizumab products. Ranibizumab intravitreal injection has been used adjunctively with Photodynamic Therapy (PDT). Twelve of 105 (11%) patients with neovascular AMD developed serious intraocular inflammation; in 10 of the 12 patients, this occurred when ranibizumab was administered 7 days (± 2 days) after PDT.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies of ranibizumab products administered in pregnant women. Administration of ranibizumab to pregnant monkeys throughout the period of organogenesis resulted in a low incidence of skeletal abnormalities at intravitreal doses 13-times the predicted human exposure (based on maximal serum trough levels [C max ]) after a single eye treatment at the recommended clinical dose. No skeletal abnormalities were observed at serum trough levels equivalent to the predicted human exposure after a single eye treatment at the recommended clinical dose [ see Animal Data ].
Animal reproduction studies are not always predictive of human response, and it is not known whether ranibizumab products can cause fetal harm when administered to a pregnant woman. Based on the anti-VEGF mechanism of action for ranibizumab products [ see Clinical Pharmacology (12.1) ], treatment with ranibizumab products may pose a risk to human embryofetal development. BYOOVIZ should be given to a pregnant woman only if clearly needed.
Data Animal Data An embryo-fetal developmental toxicity study was performed on pregnant cynomolgus monkeys. Pregnant animals received intravitreal injections of ranibizumab every 14 days starting on Day 20 of gestation, until Day 62 at doses of 0, 0.125, and 1 mg/eye. Skeletal abnormalities including incomplete and/or irregular ossification of bones in the skull, vertebral column, and hindlimbs and shortened supernumerary ribs were seen at a low incidence in fetuses from animals treated with 1 mg/eye of ranibizumab.
The 1 mg/eye dose resulted in trough serum ranibizumab levels up to 13 times higher than predicted Cmax levels with single eye treatment in humans. No skeletal abnormalities were seen at the lower dose of 0.125 mg/eye, a dose which resulted in trough exposures equivalent to single eye treatment in humans. No effect on the weight or structure of the placenta, maternal toxicity, or embryotoxicity was observed.
8.2Lactation Risk Summary There are no data available on the presence of ranibizumab products in human milk, the effects of ranibizumab products on the breastfed infant or the effects of ranibizumab products on milk production/excretion. Because many drugs are excreted in human milk, and because the potential for absorption and harm to infant growth and development exists, caution should be exercised when BYOOVIZ is administered to a nursing woman. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for BYOOVIZ and any potential adverse effects on the breastfed child from BYOOVIZ.
8.3Females and Males of Reproductive Potential Infertility No studies on the effects of ranibizumab products on fertility have been conducted and it is not known whether ranibizumab products can affect reproduction capacity. Based on the anti-VEGF mechanism of action for ranibizumab products, treatment with ranibizumab products may pose a risk to reproductive capacity.
8.4Pediatric Use The safety and effectiveness of BYOOVIZ in pediatric patients have not been established.
8.5Geriatric Use In the clinical studies, approximately 76% (2449 of 3227) of patients randomized to treatment with ranibizumab were ≥ 65 years of age and approximately 51% (1644 of 3227) were ≥ 75 years of age [ see Clinical Studies (14) ]. No notable differences in efficacy or safety were seen with increasing age in these studies. Age did not have a significant effect on systemic exposure.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies of ranibizumab products administered in pregnant women. Administration of ranibizumab to pregnant monkeys throughout the period of organogenesis resulted in a low incidence of skeletal abnormalities at intravitreal doses 13-times the predicted human exposure (based on maximal serum trough levels [C max ]) after a single eye treatment at the recommended clinical dose. No skeletal abnormalities were observed at serum trough levels equivalent to the predicted human exposure after a single eye treatment at the recommended clinical dose [ see Animal Data ].
Animal reproduction studies are not always predictive of human response, and it is not known whether ranibizumab products can cause fetal harm when administered to a pregnant woman. Based on the anti-VEGF mechanism of action for ranibizumab products [ see Clinical Pharmacology (12.1) ], treatment with ranibizumab products may pose a risk to human embryofetal development. BYOOVIZ should be given to a pregnant woman only if clearly needed.
Data Animal Data An embryo-fetal developmental toxicity study was performed on pregnant cynomolgus monkeys. Pregnant animals received intravitreal injections of ranibizumab every 14 days starting on Day 20 of gestation, until Day 62 at doses of 0, 0.125, and 1 mg/eye. Skeletal abnormalities including incomplete and/or irregular ossification of bones in the skull, vertebral column, and hindlimbs and shortened supernumerary ribs were seen at a low incidence in fetuses from animals treated with 1 mg/eye of ranibizumab.
The 1 mg/eye dose resulted in trough serum ranibizumab levels up to 13 times higher than predicted Cmax levels with single eye treatment in humans. No skeletal abnormalities were seen at the lower dose of 0.125 mg/eye, a dose which resulted in trough exposures equivalent to single eye treatment in humans. No effect on the weight or structure of the placenta, maternal toxicity, or embryotoxicity was observed.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of BYOOVIZ in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use In the clinical studies, approximately 76% (2449 of 3227) of patients randomized to treatment with ranibizumab were ≥ 65 years of age and approximately 51% (1644 of 3227) were ≥ 75 years of age [ see Clinical Studies (14) ]. No notable differences in efficacy or safety were seen with increasing age in these studies. Age did not have a significant effect on systemic exposure.
🆘 Overdosage ▾
10 OVERDOSAGE More concentrated doses as high as 2 mg ranibizumab in 0.05 mL have been administered to patients. No additional unexpected adverse reactions were seen.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ranibizumab products bind to the receptor binding site of active forms of VEGF-A, including the biologically active, cleaved form of this molecule, VEGF 110 . VEGF-A has been shown to cause neovascularization and leakage in models of ocular angiogenesis and vascular occlusion and is thought to contribute to pathophysiology of neovascular AMD, mCNV, and macular edema following RVO. The binding of ranibizumab products to VEGF-A prevents the interaction of VEGF-A with its receptors (VEGFR1 and VEGFR2) on the surface of endothelial cells, reducing endothelial cell proliferation, vascular leakage, and new blood vessel formation.
12.2Pharmacodynamics Increased retinal thickness (i.e., center point thickness (CPT) or central foveal thickness (CFT)), as assessed by optical coherence tomography (OCT) is associated with neovascular AMD, mCNV, and macular edema following RVO. Leakage from choroidal neovascularization (CNV) as assessed by fluorescein angiography (FA) is associated with neovascular AMD and mCNV. Neovascular (Wet) Age-Related Macular Degeneration In Study AMD-3, CPT was assessed by time domain (TD)-OCT in 118 of 184 patients.
TD-OCT measurements were collected at baseline, Months 1, 2, 3, 5, 8, and 12. In patients treated with ranibizumab, CPT decreased, on average, more than in the sham group from baseline through Month 12. CPT decreased by Month 1 and decreased further at Month 3, on average.
In this study, CPT data did not provide information useful in influencing treatment decisions [ see Clinical Studies (14.1) ]. In Study AMD-4, CFT was assessed by spectral domain (SD)-OCT in all patients; on average, CFT reductions were observed beginning at Day 7 following the first ranibizumab injection through Month 24. CFT data did not provide information capable of predicting final visual acuity results [ see Clinical Studies (14.1) ].
In patients treated with ranibizumab, the area of CNV leakage, on average, decreased by Month 3 as assessed by FA. The area of CNV leakage for an individual patient was not correlated with visual acuity. Macular Edema Following Retinal Vein Occlusion On average, CPT reductions were observed in Studies RVO-1 and RVO-2 beginning at Day 7 following the first ranibizumab injection through Month 6.
CPT was not evaluated as a means to guide treatment decisions [ see Clinical Studies (14.2) ]. Myopic Choroidal Neovascularization On average CFT reductions were observed as early as Month 1, and were greater in the ranibizumab groups compared to PDT [ see Clinical Studies (14.3) ].
12.3Pharmacokinetics In patients with neovascular AMD, following monthly intravitreal administration of 0.5 mg ranibizumab, mean (±SD) maximum ranibizumab serum concentrations were 1.7 (± 1.1) ng/mL. These concentrations were below the concentration range of ranibizumab (11 to 27 ng/mL) that was necessary to inhibit the biological activity of VEGF-A by 50%, as measured in an in vitro cellular proliferation assay (based on human umbilical vein endothelial cells (HUVEC)). No significant change from baseline was observed in the mean plasma VEGF concentrations following three monthly 0.5 mg intravitreal injections.
The maximum observed serum concentration was dose proportional over the dose range of 0.05 to 2 mg/eye. Serum ranibizumab concentrations in RVO patients were similar to those observed in neovascular AMD patients. Based on a population pharmacokinetic analysis of patients with neovascular AMD, maximum serum concentrations are predicted to be reached at approximately 1 day after monthly intravitreal administration of ranibizumab 0.5 mg/eye.
Based on the disappearance of ranibizumab from serum, the estimated average vitreous elimination half-life was approximately 9 days. Steady-state minimum concentration is predicted to be 0.22 ng/mL with a monthly dosing regimen. In humans, serum ranibizumab concentrations are predicted to be approximately 90,000-fold lower than vitreal c… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ranibizumab products bind to the receptor binding site of active forms of VEGF-A, including the biologically active, cleaved form of this molecule, VEGF 110 . VEGF-A has been shown to cause neovascularization and leakage in models of ocular angiogenesis and vascular occlusion and is thought to contribute to pathophysiology of neovascular AMD, mCNV, and macular edema following RVO. The binding of ranibizumab products to VEGF-A prevents the interaction of VEGF-A with its receptors (VEGFR1 and VEGFR2) on the surface of endothelial cells, reducing endothelial cell proliferation, vascular leakage, and new blood vessel formation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Each BYOOVIZ 0.5 mg carton (NDC 64406-019-01) contains a single-dose, 2-mL glass vial designed to deliver 0.05 mL of 10 mg/mL ranibizumab-nuna solution that is clear to slightly opalescent and colorless to pale yellow. EACH CARTON IS FOR SINGLE-EYE USE ONLY. BYOOVIZ should be refrigerated at 2°C to 8°C (36°F to 46°F).
DO NOT FREEZE. Do not use beyond the date stamped on the label. Protect BYOOVIZ vials from light and store in the original carton until time of use.
Prior to use, the unopened vial can be stored at temperatures up to 86°F (30°C) for up to 72 hours.
📦 Storage and Handling ▾
BYOOVIZ should be refrigerated at 2°C to 8°C (36°F to 46°F). DO NOT FREEZE. Do not use beyond the date stamped on the label. Protect BYOOVIZ vials from light and store in the original carton until time of use. Prior to use, the unopened vial can be stored at temperatures up to 86°F (30°C) for up to 72 hours.
📋 Description ▾
11 DESCRIPTION BYOOVIZ (ranibizumab-nuna) is a recombinant humanized IgG1 kappa isotype monoclonal antibody fragment designed for intraocular use. Ranibizumab-nuna binds to and inhibits the biologic activity of human vascular endothelial growth factor A (VEGF-A). Ranibizumab-nuna, which lacks an Fc region, has a molecular weight of approximately 48 kilodaltons and is produced by an E. coli expression system in a nutrient medium containing the antibiotic tetracycline.
Tetracycline is not detectable in the final product. BYOOVIZ (ranibizumab-nuna) injection is a sterile, clear to slightly opalescent and colorless to pale yellow solution in a single-dose glass vial for intravitreal use. BYOOVIZ is supplied as a preservative-free, sterile solution in a single-dose container designed to deliver 0.05 mL of 10 mg/mL BYOOVIZ (0.5 mg dose vial) aqueous solution with 10 mM histidine HCl, 10% α,α-trehalose dihydrate, 0.01% polysorbate 20, pH 5.5.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients that in the days following BYOOVIZ administration, patients are at risk of developing endophthalmitis and retinal vasculitis with or without occlusion. If the eye becomes red, sensitive to light, painful, or develops a change in vision, advise the patient to seek immediate care from an ophthalmologist [ see Warnings and Precautions (5.1 , 5.4) ].
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics In patients with neovascular AMD, following monthly intravitreal administration of 0.5 mg ranibizumab, mean (±SD) maximum ranibizumab serum concentrations were 1.7 (± 1.1) ng/mL. These concentrations were below the concentration range of ranibizumab (11 to 27 ng/mL) that was necessary to inhibit the biological activity of VEGF-A by 50%, as measured in an in vitro cellular proliferation assay (based on human umbilical vein endothelial cells (HUVEC)). No significant change from baseline was observed in the mean plasma VEGF concentrations following three monthly 0.5 mg intravitreal injections.
The maximum observed serum concentration was dose proportional over the dose range of 0.05 to 2 mg/eye. Serum ranibizumab concentrations in RVO patients were similar to those observed in neovascular AMD patients. Based on a population pharmacokinetic analysis of patients with neovascular AMD, maximum serum concentrations are predicted to be reached at approximately 1 day after monthly intravitreal administration of ranibizumab 0.5 mg/eye.
Based on the disappearance of ranibizumab from serum, the estimated average vitreous elimination half-life was approximately 9 days. Steady-state minimum concentration is predicted to be 0.22 ng/mL with a monthly dosing regimen. In humans, serum ranibizumab concentrations are predicted to be approximately 90,000-fold lower than vitreal concentrations.
In pharmacokinetic covariate analyses, 48% (520/1091) of patients had renal impairment (35% mild, 11% moderate, and 2% severe). Because the increases in plasma ranibizumab exposures in these patients are not considered clinically significant, no dosage adjustment is needed based on renal impairment status.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Increased retinal thickness (i.e., center point thickness (CPT) or central foveal thickness (CFT)), as assessed by optical coherence tomography (OCT) is associated with neovascular AMD, mCNV, and macular edema following RVO. Leakage from choroidal neovascularization (CNV) as assessed by fluorescein angiography (FA) is associated with neovascular AMD and mCNV. Neovascular (Wet) Age-Related Macular Degeneration In Study AMD-3, CPT was assessed by time domain (TD)-OCT in 118 of 184 patients.
TD-OCT measurements were collected at baseline, Months 1, 2, 3, 5, 8, and 12. In patients treated with ranibizumab, CPT decreased, on average, more than in the sham group from baseline through Month 12. CPT decreased by Month 1 and decreased further at Month 3, on average.
In this study, CPT data did not provide information useful in influencing treatment decisions [ see Clinical Studies (14.1) ]. In Study AMD-4, CFT was assessed by spectral domain (SD)-OCT in all patients; on average, CFT reductions were observed beginning at Day 7 following the first ranibizumab injection through Month 24. CFT data did not provide information capable of predicting final visual acuity results [ see Clinical Studies (14.1) ].
In patients treated with ranibizumab, the area of CNV leakage, on average, decreased by Month 3 as assessed by FA. The area of CNV leakage for an individual patient was not correlated with visual acuity. Macular Edema Following Retinal Vein Occlusion On average, CPT reductions were observed in Studies RVO-1 and RVO-2 beginning at Day 7 following the first ranibizumab injection through Month 6.
CPT was not evaluated as a means to guide treatment decisions [ see Clinical Studies (14.2) ]. Myopic Choroidal Neovascularization On average CFT reductions were observed as early as Month 1, and were greater in the ranibizumab groups compared to PDT [ see Clinical Studies (14.3) ].
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Unless otherwise noted, visual acuity was measured at a distance of 4 meters.
14.1Neovascular (Wet) Age-Related Macular Degeneration (AMD) The safety and efficacy of ranibizumab were assessed in three randomized, double-masked, sham- or active-controlled studies in patients with neovascular AMD. A total of 1323 patients (ranibizumab 879, control 444) were enrolled in the three studies. Studies AMD-1 and AMD-2 In Study AMD-1, patients with minimally classic or occult (without classic) CNV lesions received monthly ranibizumab 0.3 mg or 0.5 mg intravitreal injections or monthly sham injections.
Data are available through Month 24. Patients treated with ranibizumab in Study AMD-1 received a mean of 22 total treatments out of a possible 24 from Day 0 to Month 24. In Study AMD-2, patients with predominantly classic CNV lesions received one of the following: 1) monthly ranibizumab 0.3 mg intravitreal injections and sham PDT; 2) monthly ranibizumab 0.5 mg intravitreal injections and sham PDT; or 3) sham intravitreal injections and active PDT.
Sham PDT (or active PDT) was given with the initial ranibizumab (or sham) intravitreal injection and every 3 months thereafter if FA showed persistence or recurrence of leakage. Data are available through Month 24. Patients treated with ranibizumab in Study AMD-2 received a mean of 21 total treatments out of a possible 24 from Day 0 through Month 24.
In both studies, the primary efficacy endpoint was the proportion of patients who maintained vision, defined as losing fewer than 15 letters of visual acuity at 12 months compared with baseline. Almost all ranibizumab--treated patients (approximately 95%) maintained their visual acuity. Among ranibizumab--treated patients, 31% to 37% experienced a clinically significant improvement in vision, defined as gaining 15 or more letters at 12 months.
The size of the lesion did not significantly affect the results. Detailed results are shown in Table 3, Table 4, and Figure 1 below. Table 3 Visual Acuity Outcomes at Month 12 and Month 24 in Study AMD-1 Outcome Measure Month Sham n=229 Ranibizumab 0.5 mg n=230 Estimated Difference (95% CI) Adjusted estimate based on the stratified model; p <
0.01Loss of <15 letters in visual acuity (%) 12 60% 91% 30% (23%, 37%) 24 56% 89% 33% (26%, 41%) Gain of ≥15 letters in visual acuity (%) 12 6% 31% 25% (18%, 31%) 24 4% 30% 25% (18%, 31%) Mean change in visual acuity (letters) (SD) 12 -11.0 (17.9) +6.3 (14.1) 17.1 (14.2, 20.0) 24 -15.0 (19.7) +5.5 (15.9) 20.1 (16.9, 23.4) Table 4 Visual Acuity Outcomes at Month 12 and Month 24 in Study AMD-2 Outcome Measure Month PDT n=141 Ranibizumab 0.5 mg n=139 Estimated Difference (95% CI) Adjusted estimate based on the stratified model; p <
0.01Loss of <15 letters in visual acuity (%) 12 66% 98% 32% (24%, 40%) 24 65% 93% 28% (19%, 37%) Gain of ≥15 letters in visual acuity (%) 12 11% 37% 26% (17%, 36%) 24 9% 37% 29% (20%, 39%) Mean change in visual acuity (letters) (SD) 12 -8.5 (17.8) +11.0 (15.8) 19.8 (15.9, 23.7) 24 -9.1 (18.7) +10.9 (17.3) 20 (16.0, 24.4) Figure 1 Mean Change in Visual Acuity Visual acuity was measured at a distance of 2 meters from Baseline to Month 24 in Study AMD-1 and Study AMD-2 AMD-1 AMD-2 Ranibizumab 0.5 mg (n=240) Ranibizumab 0.5 mg (n=139) Sham (n=238) Verteporfin PDT (n=143) Patients in the group treated with ranibizumab had minimal observable CNV lesion growth, on average.
At Month 12, the mean change in the total area of the CNV lesion was 0.1-0.3 disc areas (DA) for ranibizumab versus 2.3-2.6 DA for the control arms. At Month 24, the mean change in the total area of the CNV lesion was 0.3-0.4 DA for ranibizumab versus 2.9-3.1 DA for the control arms. Figure 1 Figure Figure Figure Figure Study AMD-3 Study AMD-3 was a randomized, double-masked, sham-controlled, 2-year study designed to assess the safety and efficacy of ranibizumab in patients with neovascular AMD (with or without a classic CNV component).
Data are available through… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Animal studies have not been conducted to determine the carcinogenic potential of ranibizumab products. Based on the anti-VEGF mechanism of action of ranibizumab products, treatment with ranibizumab products may pose a risk to reproductive capacity [ see Females and Males of Reproductive Potential (8.3) ].
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Animal studies have not been conducted to determine the carcinogenic potential of ranibizumab products. Based on the anti-VEGF mechanism of action of ranibizumab products, treatment with ranibizumab products may pose a risk to reproductive capacity [ see Females and Males of Reproductive Potential (8.3) ].
📄 Recent Major Changes ▾
Warnings and Precautions, Retinal Vasculitis with or without Occlusion ( 5.4 ) 8/2025
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 0.5 mg Vial Carton NDC 64406-019-01 Rx only Byooviz™ 0.5mg wAMD RVO mCNO (ranibizumab-nuna) Injection 0.5 mg single-dose vial. Discard unused portion. IMPORTANT: A 5-micron sterile filter needle (19-gauge x 1-1/2 inch) is required for preparation, but not included.
See enclosed package insert. For intravitreal injection. INDICATED FOR: Neovascular (wet) age-related macular degeneration (AMD) Macular edema following retinal vein occlusion (RVO) Myopic choroidal neovascularization (mCNV) KEEP REFRIGERATED.
DO NOT FREEZE. PROTECT VIAL FROM LIGHT. SAMSUNG BIOEPIS, Biogen ® PRINCIPAL DISPLAY PANEL - 0.5 mg Vial Carton
Medicaid utilization & spend
Medicaid utilization by pack size
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |