
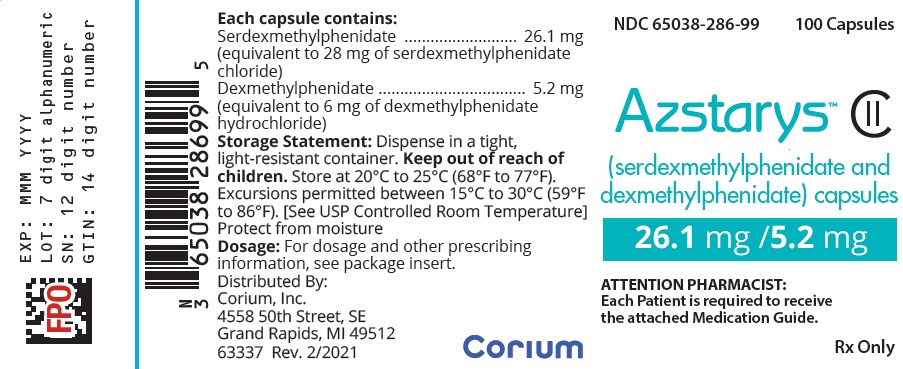
AZSTARYS Serdexmethylphenidate and Dexmethylphenidate 26.1 mg; 5.2 mg Capsule, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Centrally acting sympathomimetics class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
The combination of serdexmethylphenidate and dexmethylphenidate is used as part of a treatment program to control symptoms of attention deficit hyperactivity disorder (ADHD; more difficulty focusing, controlling actions, and remaining still or quiet than other people who are the same age) in adults and children 6 years of age and older. The combination of serdexmethylphenidate and dexmethylphenidate is in a class of medications called central nervous system stimulants. These medications work by changing the amounts of certain natural substances in the brain.
Read the full MedlinePlus article ↗- Azstarys is a prescription stimulant used to treat ADHD — Attention Deficit Hyperactivity Disorder — in people 6 years of age and older. It contains two ingredients: serdexmethylph...
- What exactly is Azstarys and what does it treat?
- Take Azstarys once every morning. You can take it with or without food — food doesn't change how much of the drug you absorb, it just delays the peak effect by a couple of hours. I...
- How should I take Azstarys — does it matter if I take it with food?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
3.34 mg
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
0.68 mg
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
27.35 mg
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
0.67 mg
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
0.67 mg
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $14.402 | $1,440.19 / 100 capsules |
| Medicaid paysCMS SDUD · 12 mo | $13.97 | $1,396.88 / 100 capsules |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Azstarys 26.1 mg/1; 5.2 mgthis 65038-0286-99 | Commave | 100 capsules | $14.402 | — | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 10858341 ↗ | Method of use | U-3094 | Dec 9, 2037 |
| US 10954213 ↗ | Method of use | U-3094 | Dec 9, 2037 |
| US 10858341 ↗ | Method of use | U-3094 | Dec 9, 2037 |
| US 10954213 ↗ | Method of use | U-3094 | Dec 9, 2037 |
| US 10954213 ↗ | Method of use | U-3094 | Dec 9, 2037 |
| US 10858341 ↗ | Method of use | U-3094 | Dec 9, 2037 |
| US 10584112 ↗ | Drug substance | — | Dec 9, 2037 |
| US 10584112 ↗ | Drug substance | — | Dec 9, 2037 |
| US 10584113 ↗ | Drug product | — | Dec 9, 2037 |
| US 10759778 ↗ | Drug product | — | Dec 9, 2037 |
| US 9079928 ↗ | Drug product | — | May 7, 2035 |
| US 9079928 ↗ | Drug product | — | May 7, 2035 |
| US 10759778 ↗ | Drug product | — | Dec 9, 2037 |
| US 10584113 ↗ | Drug product | — | Dec 9, 2037 |
| US 9079928 ↗ | Drug product | — | May 7, 2035 |
| US 10759778 ↗ | Drug product | — | Dec 9, 2037 |
| US 10584113 ↗ | Drug product | — | Dec 9, 2037 |
| US 10584112 ↗ | Drug substance | — | Dec 9, 2037 |
| Code | What it grants | Expires |
|---|---|---|
| NCE | New Chemical Entity (5-year) | May 7, 2026 |
| NCE | New Chemical Entity (5-year) | May 7, 2026 |
| NCE | New Chemical Entity (5-year) | May 7, 2026 |
Is there a generic version of AZSTARYS 26.1 MG-5.2 MG CAP?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 65038-0286-99 You're viewing this | 100 CAPSULE in 1 BOTTLE, PLASTIC (65038-286-99) | 2021-07-16 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: ABUSE, MISUSE, AND ADDICTION AZSTARYS has a high potential for abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Misuse and abuse of CNS stimulants, including AZSTARYS, can result in overdose and death [see Overdosage ( 10 )], and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection. Before prescribing AZSTARYS, assess each patient’s risk for abuse, misuse, and addiction.
Educate patients and their families about these risks, proper storage of the drug, and proper disposal of any unused drug. Throughout AZSTARYS treatment, reassess each patient’s risk of abuse, misuse, and addiction and frequently monitor for signs and symptoms of abuse, misuse, and addiction [see Warnings and Precautions ( 5.1 ) and Drug Abuse and Dependence ( 9.2 )]. WARNING: ABUSE, MISUSE, AND ADDICTION See full prescribing information for complete boxed warning.
AZSTARYS has a high potential for abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Misuse and abuse of CNS stimulants, including AZSTARYS, can result in overdose and death ( 5.1 , 9.2 , 10 ): Before prescribing AZSTARYS, assess each patient’s risk for abuse, misuse, and addiction. Educate patients and their families about these risks, proper storage of the drug, and proper disposal of any unused drug.
Throughout treatment, reassess each patient’s risk and frequently monitor for signs and symptoms of abuse, misuse, and addiction.
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE AZSTARYS is indicated for the treatment of Attention Deficit Hyperactivity Disorder (ADHD) in patients 6 years of age and older. Limitations of Use The use of AZSTARYS is not recommended in pediatric patients younger than 6 years of age because they had higher plasma exposure and a higher incidence of adverse reactions (e.g., weight loss) than patients 6 years and older at the same dosage [see Warnings and Precautions ( 5.7 ), Use in Specific Populations ( 8.4 )]. AZSTARYS is a central nervous system (CNS) stimulant indicated for the treatment of Attention Deficit Hyperactivity Disorder (ADHD) in patients 6 years of age and older.
( 1 ) Limitations of Use The use of AZSTARYS is not recommended in pediatric patients younger than 6 years of age because they had higher plasma exposure and a higher incidence of adverse reactions (e.g., weight loss) than patients 6 years and older at the same dosage (5.7, 8.4).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Pediatric Patients 6 to 12 years : Recommended starting dosage is 39.2 mg/7.8 mg orally once daily in the morning. Dosage may be increased to 52.3 mg/10.4 mg daily or decreased to 26.1 mg/5.2 mg daily after one week. Maximum recommended dosage is 52.3 mg/10.4 mg once daily.
( 2.2 ) Adults and Pediatric Patients 13 to 17 years: Recommended starting dosage is 39.2 mg/7.8 mg orally once daily in the morning. Increase the dosage after one week to 52.3 mg/10.4 mg once daily depending on response and tolerability. ( 2.2 ) Administer with or without food.
( 2.3 ) Swallow capsules whole or open and sprinkle onto applesauce or add to water. ( 2.3 ) To avoid substitution errors and overdosage, do not substitute for other methylphenidate products on a milligram-per-milligram basis. ( 2.4 )
2.1Pretreatment Screening Prior to treating patients with AZSTARYS, assess: for the presence of cardiac disease (i.e., perform a careful history, family history of sudden death or ventricular arrhythmia, and physical exam) [see Warnings and Precautions ( 5.2 )]. the family history and clinically evaluate patients for motor or verbal tics or Tourette’s syndrome before initiating AZSTARYS [see Warnings and Precautions ( 5.10 )].
2.2Recommended Dosage Pediatric Patients 6 to 12 years of age The recommended starting dosage of AZSTARYS is 39.2 mg serdexmethylphenidate/7.8 mg dexmethylphenidate once daily in the morning. The dosage may be increased after one week to a dosage of 52.3 mg serdexmethylphenidate/10.4 mg dexmethylphenidate per day, or decreased after one week to a dosage of 26.1 mg serdexmethylphenidate/5.2 mg dexmethylphenidate per day, depending on response and tolerability. Maximum recommended dosage is 52.3 mg serdexmethylphendiate/10.4 mg dexmethyphenidate once daily.
Adults and Pediatric Patients 13 to 17 years of age The recommended starting dosage of AZSTARYS is 39.2 mg serdexmethylphenidate/7.8 mg dexmethylphenidate once daily in the morning. Increase the dosage after one week to a dosage of 52.3 mg serdexmethylphenidate/10.4 mg dexmethylphenidate per day, depending on response and tolerability. Maximum recommended dosage is 52.3 mg serdexmethylphenidate/10.4 mg dexmethylphenidate once daily.
2.3Administration Instructions Administer AZSTARYS orally once daily in the morning with or without food [see Clinical Pharmacology ( 12.3 )] . AZSTARYS capsules may be taken whole, or opened and the entire contents sprinkled into 50 mL of water or over 2 tablespoons of applesauce. Consume all the drug/food mixture immediately or within 10 minutes of mixing; do not store for future use [see Clinical Pharmacology ( 12.3 )] .
2.4Switching from Other Methylphenidate Products If switching from other methylphenidate products, discontinue that treatment, and titrate with AZSTARYS using the titration schedule described above. Do not substitute AZSTARYS for other methylphenidate products on a milligram-per-milligram basis because these products have different pharmacokinetic profiles from AZSTARYS and may have different methylphenidate base composition [see Description ( 11 ), Clinical Pharmacology ( 12.3 )] .
2.5Dosage Reduction and Discontinuation If paradoxical aggravation of symptoms or other adverse reactions occur, reduce dosage or, if necessary, discontinue AZSTARYS. If improvement is not observed after appropriate dosage adjustment over a one-month period, discontinue AZSTARYS.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS AZSTARYS capsules are available as: 26.1 mg/5.2 mg (serdexmethylphenidate/dexmethylphenidate) – blue cap/grey body, imprinted with "286" on cap and "KP415" on the body 39.2 mg/7.8 mg (serdexmethylphenidate/dexmethylphenidate) – dark blue cap/grey body, imprinted with "429" on cap and "KP415" on the body 52.3 mg/10.4 mg (serdexmethylphenidate/dexmethylphenidate) – orange cap/grey body, imprinted with "5612" on cap and "KP415" on the body Capsules (serdexmethylphenidate/dexmethylphenidate): 26.1 mg/5.2 mg, 39.2 mg/7.8 mg, 52.3 mg/10.4 mg.
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS AZSTARYS is contraindicated in patients: with known hypersensitivity to serdexmethylphenidate, methylphenidate, or other components of AZSTARYS. Bronchospasm, rash, and pruritus have been reported in patients who received AZSTARYS. Hypersensitivity reactions such as angioedema and anaphylactic reactions have been reported in patients treated with other methylphenidate products [see Adverse Reactions ( 6.2 )] . receiving concomitant treatment with monoamine oxidase inhibitors (MAOIs), or within 14 days following discontinuation of treatment with an MAOI, because of the risk of hypertensive crisis [see Drug Interactions ( 7.1 )] .
Known hypersensitivity to serdexmethylphenidate, methylphenidate, or product components. ( 4 ) Concurrent treatment with a monoamine oxidase inhibitor (MAOI), or use of an MAOI within the preceding 14 days. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Risks to Patients with Serious Cardiac Disease : Avoid use in patients with known structural cardiac abnormalities, cardiomyopathy, serious cardiac arrhythmias, coronary artery disease, or other serious cardiac disease. (5.2) Increased Blood Pressure and Heart Rate : Monitor blood pressure and pulse. (5.3) Psychiatric Adverse Reactions : Prior to initiating AZSTARYS, screen patients for risk factors for developing a manic episode.
If new psychotic or manic symptoms occur, consider discontinuing AZSTARYS. (5.4) Priapism : If abnormally sustained or frequent and painful erections occur, patients should seek immediate medical attention. (5.5) Peripheral Vasculopathy, including Raynaud's Phenomenon : Careful observation for digital changes is necessary during AZSTARYS treatment with ADHD stimulants.
Further clinical evaluation (e.g., rheumatology referral) may be appropriate for patients who develop signs or symptoms of peripheral vasculopathy. (5.6) Long-Term Suppression of Growth in Pediatric Patients : Monitor height and weight at appropriate intervals in pediatric patients. (5.7) Acute Angle Closure Glaucoma : AZSTARYS-treated patients considered at risk for acute angle closure glaucoma (e.g., patients with significant hyperopia) should be evaluated by an ophthalmologist.
(5.8) Increased Intraocular Pressure (IOP) and Glaucoma : Prescribe AZSTARYS to patients with open-angle glaucoma or abnormally increased IOP only if the benefit of treatment is considered to outweigh the risk. Closely monitor patients with a history of increased IOP or open angle glaucoma. (5.9) Motor and Verbal Tics, and Worsening of Tourette’s Syndrome: Before initiating AZSTARYS, assess the family history and clinically evaluate patients for tics or Tourette’s syndrome.
Regularly monitor patients for the emergence or worsening of tics or Tourette’s syndrome. Discontinue treatment if clinically appropriate. (5.10)
5.1Abuse, Misuse, and Addiction AZSTARYS has a high potential for abuse and misuse. The use of AZSTARYS exposes individuals to the risks of abuse and misuse, which can lead to the development of a substance use disorder, including addiction. AZSTARYS can be diverted for non-medical use into illicit channels or distribution [see Drug Abuse and Dependence (9.2) ] .
Misuse and abuse of CNS stimulants, including AZSTARYS, can result in overdose and death [see Overdosage ( 10 )], and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection. Before prescribing AZSTARYS, assess each patient’s risk for abuse, misuse, and addiction. Educate patients and their families about these risks and proper disposal of any unused drug.
Advise patients to store AZSTARYS in a safe place, preferably locked, and instruct patients to not give AZSTARYS to anyone else. Throughout AZSTARYS treatment, reassess each patient’s risk of abuse, misuse, and addiction and frequently monitor for signs and symptoms of abuse, misuse, and addiction.
5.2Risks to Patients with Serious Cardiac Disease Sudden death has been reported in patients with structural cardiac abnormalities or other serious cardiac disease who were treated with CNS stimulants at the recommended ADHD dosage. Avoid AZSTARYS use in patients with known structural cardiac abnormalities, cardiomyopathy, serious cardiac arrhythmia, coronary artery disease, or other serious cardiac disease.
5.3Increased Blood Pressure and Heart Rate CNS stimulants cause an increase in blood pressure (mean increase approximately 2 to 4 mmHg) and heart rate (mean increase approximately 3 to 6 beats per minute). Some patients may have larger increases. Monitor all AZSTARYS-treated patients for hypertension and tachycardia.
5.4Psychiatric Adverse Reactions Exacerbation of Pre-Existing Psychosis CNS stimulants may exacerbate symptoms of behavior disturbance and thought disorder in patients with a pre-existing psychotic disorder. Induction of a Manic Episode in…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following are discussed in more detail in other sections of the labeling: Abuse, Misuse, and Addiction [see Boxed Warning, Warnings and Precautions (5.1) , and Drug Abuse and Dependence (9.2 , 9.3) ] Known hypersensitivity to methylphenidate or other ingredients of AZSTARYS [see Contraindications (4) ] Hypertensive Crisis with Concomitant Use of Monoamine Oxidase Inhibitors [see Contraindications (4) ] Risks to Patients with Serious Cardiac Disease [see Warnings and Precautions (5.2) ] Increased Blood Pressure and Heart Rate [see Warnings and Precautions (5.3) ] Psychiatric Adverse Reactions [see Warnings and Precautions (5.4) ] Priapism [see Warnings and Precautions (5.5) ] Peripheral Vasculopathy, including Raynaud's Phenomenon [see Warnings and Precautions (5.6) ] Long-Term Suppression of Growth in Pediatric Patients [see Warnings and Precautions (5.7) ] Acute Angle Closure Glaucoma [see Warnings and Precautions (5.8) ] Increased Intraocular Pressure and Glaucoma [see Warnings and Precautions (5.9) ] Motor and Verbal Tics, and Worsening of Tourette’s Syndrome [see Warnings and Precautions (5.10) ] Based on accumulated data from other methylphenidate products, the most common (>5% and twice the rate of placebo) adverse reactions are appetite decreased, insomnia, nausea, vomiting, dyspepsia, abdominal pain, weight decreased, anxiety, dizziness, irritability, affect lability, tachycardia, and blood pressure increased.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Corium, LLC at 1-855-253-2407 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Adverse Reactions in Studies with Other Methylphenidate Products in Pediatric Patients and Adults with ADHD Commonly reported (≥ 5% of the methylphenidate group and at least twice the rate of the placebo group) adverse reactions from placebo-controlled trials of methylphenidate products include: decreased appetite, decreased weight, nausea, abdominal pain, dyspepsia, vomiting, insomnia, anxiety, affect lability, irritability, dizziness, increased blood pressure, and tachycardia.
Adverse Reactions in Studies with AZSTARYS in Pediatric Patients (6 to 12 years) with ADHD Short-Term Study A short-term study conducted in pediatric patients 6 to 12 years of age with ADHD was comprised of a 3-week, open-label, dose optimization phase in which all patients received AZSTARYS (n=155), followed by a 1-week, double-blind, controlled phase in which patients were randomized to continue AZSTARYS (n=74) or switch to placebo (n=76). Because of the study design, the reported adverse reaction rates cannot be used to predict the rates that may be expected in clinical practice.
Long-Term Study A long-term, open-label safety study was conducted in pediatric patients 6 to 12 years of age with ADHD who either completed the short-term study or were de novo patients. This study was comprised of a 3-week dose optimization phase for patients not recently treated with AZSTARYS followed by a 12-month treatment phase for all patients during which 238 patients received open- label AZSTARYS and had evaluable safety data. A total of 154 patients were treated for 12 months.
Because of the open-label, uncontrolled design of this study, the reported adverse reaction rates cannot be assessed in terms of a causal relationship to AZSTARYS treatment. To adjust for normal growth, z-scores were derived (measured in standard deviations [SD]); z- scores normalize for the natural growth of children and adolescents by comparisons to age- and sex-matched population standards. A z-score change less than
0.5SD is considered not clinically significant. In this study, the mean increase in weight from baseline t…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Antihypertensive Drugs: Monitor blood pressure. Adjust dosage of antihypertensive drug as needed. ( 7.1 )
7.1Clinically Important Interactions with AZSTARYS Table 1 presents clinically important drug interactions with AZSTARYS. Table 1: Clinically Important Drug Interactions with AZSTARYS Monoamine Oxidase Inhibitors (MAOIs) Clinical Impact Concomitant use of MAOIs and CNS stimulants, including AZSTARYS, can cause hypertensive crisis. Potential outcomes include death, stroke, myocardial infarction, aortic dissection, ophthalmological complications, eclampsia, pulmonary edema, and renal failure [see Contraindications ( 4 )] .
Intervention Do not administer AZSTARYS concomitantly with MAOIs or within 14 days after discontinuing MAOI treatment [see Contraindications ( 4 )] Antihypertensive Drugs Clinical Impact AZSTARYS may decrease the effectiveness of drugs used to treat hypertension [see Warnings and Precautions ( 5.3 )] . Intervention Monitor blood pressure and adjust the dosage of the antihypertensive drug, as needed. Halogenated Anesthetics Clinical Impact Concomitant use of halogenated anesthetics and AZSTARYS may increase the risk of sudden blood pressure and heart rate increase during surgery.
Intervention Avoid use of AZSTARYS in patients being treated with anesthetics on the day of surgery. Risperidone Clinical Impact Combined use of methylphenidate with risperidone when there is a change, whether an increase or decrease, in dosage of either or both medications, may increase the risk of extrapyramidal symptoms (EPS). Intervention Monitor for signs of EPS.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ADHD medications, including AZSTARYS, during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Psychostimulants at 1-866-961-2388. Risk Summary There are no available data on AZSTARYS use in pregnant women to evaluate for a drug- associated risk of major birth defects, miscarriage or other adverse maternal or fetal outcomes; however, AZSTARYS contains dexmethylphenidate and serdexmethylphenidate, a prodrug of dexmethylphenidate.
Dexmethylphenidate is the d-threo enantiomer of racemic methylphenidate. Published studies and postmarketing reports on methylphenidate use during pregnancy have not identified a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. There may be risks to the fetus associated with the use of CNS stimulants use during pregnancy ( see Clinical Considerations ).
Embryo-fetal development studies in rats showed delayed fetal skeletal ossification at doses up to 3 times the maximum recommended human dose (MRHD) of 40 mg/day dexmethylphenidate hydrochloride given to adults based on plasma levels. A decrease in pup weight in males was observed in a pre- and post-natal development study with oral administration of dexmethylphenidate to rats throughout pregnancy and lactation at doses 3 times the MRHD of 40 mg/day dexmethylphenidate hydrochloride given to adults based on plasma levels ( see Data ).
No evidence of developmental effects were found in an embryo-fetal development study with oral administration of serdexmethylphenidate to rabbits during organogenesis at doses up to approximately 49 times the MRHD of 52 mg/day serdexmethylphenidate given to adults based on plasma levels ( see Data ). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions CNS stimulants, such as AZSTARYS, can cause vasoconstriction and thereby decrease placental perfusion. No fetal and/or neonatal adverse reactions have been reported with the use of therapeutic doses of methylphenidate during pregnancy; however, premature delivery and low birth weight infants have been reported in amphetamine-dependent mothers.
Data Animal Data In embryo-fetal development studies conducted in rats and rabbits, dexmethylphenidate hydrochloride was administered orally at doses of up to 20 and 100 mg/kg/day, respectively, during the period of organogenesis. No evidence of malformations was found in either the rat or rabbit study; however, delayed fetal skeletal ossification was observed at the highest dose level in rats. When dexmethylphenidate hydrochloride was administered to rats throughout pregnancy and lactation at doses of up to 20 mg/kg/day, post-weaning body weight gain was decreased in male offspring at the highest dose, but no other effects on postnatal development were observed.
At the highest doses tested, plasma levels [area under the curves (AUCs)] of dexmethylphenidate in pregnant rats and rabbits were approximately 3 and 1 times, respectively, those in adults dosed with 40 mg/day dexmethylphenidate hydrochloride. Racemic methylphenidate hydrochloride has been shown to cause malformations (increased incidence of fetal spina bifida) in rabbits when given in doses of 200 mg/kg/day throughout organogenesis. No evidence of developmental effects were found in an embryo-fetal development study with oral administration of serdexmethylphenidate in rabbits during organogenesis at doses of up to 374 mg/kg/day.
At…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ADHD medications, including AZSTARYS, during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Psychostimulants at 1-866-961-2388. Risk Summary There are no available data on AZSTARYS use in pregnant women to evaluate for a drug- associated risk of major birth defects, miscarriage or other adverse maternal or fetal outcomes; however, AZSTARYS contains dexmethylphenidate and serdexmethylphenidate, a prodrug of dexmethylphenidate.
Dexmethylphenidate is the d-threo enantiomer of racemic methylphenidate. Published studies and postmarketing reports on methylphenidate use during pregnancy have not identified a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. There may be risks to the fetus associated with the use of CNS stimulants use during pregnancy ( see Clinical Considerations ).
Embryo-fetal development studies in rats showed delayed fetal skeletal ossification at doses up to 3 times the maximum recommended human dose (MRHD) of 40 mg/day dexmethylphenidate hydrochloride given to adults based on plasma levels. A decrease in pup weight in males was observed in a pre- and post-natal development study with oral administration of dexmethylphenidate to rats throughout pregnancy and lactation at doses 3 times the MRHD of 40 mg/day dexmethylphenidate hydrochloride given to adults based on plasma levels ( see Data ).
No evidence of developmental effects were found in an embryo-fetal development study with oral administration of serdexmethylphenidate to rabbits during organogenesis at doses up to approximately 49 times the MRHD of 52 mg/day serdexmethylphenidate given to adults based on plasma levels ( see Data ). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions CNS stimulants, such as AZSTARYS, can cause vasoconstriction and thereby decrease placental perfusion. No fetal and/or neonatal adverse reactions have been reported with the use of therapeutic doses of methylphenidate during pregnancy; however, premature delivery and low birth weight infants have been reported in amphetamine-dependent mothers.
Data Animal Data In embryo-fetal development studies conducted in rats and rabbits, dexmethylphenidate hydrochloride was administered orally at doses of up to 20 and 100 mg/kg/day, respectively, during the period of organogenesis. No evidence of malformations was found in either the rat or rabbit study; however, delayed fetal skeletal ossification was observed at the highest dose level in rats. When dexmethylphenidate hydrochloride was administered to rats throughout pregnancy and lactation at doses of up to 20 mg/kg/day, post-weaning body weight gain was decreased in male offspring at the highest dose, but no other effects on postnatal development were observed.
At the highest doses tested, plasma levels [area under the curves (AUCs)] of dexmethylphenidate in pregnant rats and rabbits were approximately 3 and 1 times, respectively, those in adults dosed with 40 mg/day dexmethylphenidate hydrochloride. Racemic methylphenidate hydrochloride has been shown to cause malformations (increased incidence of fetal spina bifida) in rabbits when given in doses of 200 mg/kg/day throughout organogenesis. No evidence of developmental effects were found in an embryo-fetal development study with oral administration of serdexmethylphenidate in rabbits during organogenesis at doses of up to 374 mg/kg/day.
At the highest dose tested, the p…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of AZSTARYS have not been established in pediatric patients below the age of 6 years. In studies evaluating extended-release methylphenidate products, patients 4 to <6 years of age had higher systemic methylphenidate exposures than those observed in older pediatric patients at the same dosage. Pediatric patients 4 to <6 years of age also had a higher incidence of adverse reactions, including weight loss.
The safety and effectiveness of AZSTARYS have been established in pediatric patients ages 6 to 17 years of age for the treatment of ADHD. Use of AZSTARYS in patients 6 to 12 years of age is supported by a randomized, double-blind, placebo-controlled, parallel group trial in 155 pediatric patients with ADHD and a 12-month open-label long term safety trial in 238 patients [see Adverse Reactions ( 6.1 ), Clinical Studies ( 14 )]. Use of AZSTARYS in pediatric patients 13 to 17 years of age is supported by additional pharmacokinetics analysis showing similar plasma concentration-time profiles of dexmethylphenidate in adolescents and adults after administration of the same dose of AZSTARYS [see Clinical Studies ( 14 )].
Long Term Suppression of Growth Growth should be monitored during treatment with stimulants, including AZSTARYS. Pediatric patients who are not growing or gaining weight as expected may need to have their treatment interrupted [see Warnings and Precautions ( 5.7 ) and Adverse Reactions ( 6.1 )] . Juvenile Animal Toxicity Data Rats treated with racemic methylphenidate early in the postnatal period through sexual maturation demonstrated a decrease in spontaneous locomotor activity in adulthood.
A deficit in acquisition of a specific learning task was observed in females only. The doses at which these findings were observed are at least 3 times the MRHD of 40 mg/day dexmethylphenidate hydrochloride given to children on a mg/m 2 basis. In a study conducted in young rats, racemic methylphenidate hydrochloride was administered orally at doses of up to 100 mg/kg/day for 9 weeks, starting early in the postnatal period (postnatal Day 7) and continuing through sexual maturity (postnatal Week 10).
When these animals were tested as adults (postnatal Weeks 13 to 14), decreased spontaneous locomotor activity was observed in males and females previously treated with 50 mg/kg/day racemic methylphenidate hydrochloride [approximately 3 times the maximum recommended human dose (MRHD) of 40 mg of dexmethylphenidate hydrochloride given to children on a mg/m 2 basis] or greater, and a deficit in the acquisition of a specific learning task was seen in females exposed to the highest dose (6 times the MRHD of 40 mg of dexmethylphenidate hydrochloride given to children on a mg/m 2 basis).
The no effect level for juvenile neurobehavioral development in rats was 5 mg/kg/day racemic methylphenidate hydrochloride (less than the MRHD of 40 mg of dexmethylphenidate hydrochloride given to children on a mg/m 2 basis). The clinical significance of the long-term behavioral effects observed in rats is unknown. Serdexmethylphenidate was administered orally to juvenile rabbits at doses up to 280 mg/kg/day (approximately 50 times the MRHD of 52 mg/day serdexmethylphenidate given to children on a mg/m 2 basis), respectively, for 6 months, starting at postnatal Day 28 and continuing through sexual maturity (postnatal Day 196).
No adverse findings were observed at the highest dose of serdexmethylphenidate.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of AZSTARYS did not include any patients aged 65 years and over.
🆘 Overdosage ▾
10 OVERDOSAGE Clinical Effects of Overdose Overdose of CNS stimulants is characterized by the following sympathomimetic effects: Cardiovascular effects including tachyarrhythmias, and hypertension or hypotension. Vasospasm, myocardial infarction, or aortic dissection may precipitate sudden cardiac death. Takotsubo cardiomyopathy may develop.
CNS effects including psychomotor agitation, confusion, and hallucinations. Serotonin syndrome, seizures, cerebral vascular accidents, and coma may occur. Life-threatening hyperthermia (temperatures greater than 104°F) and rhabdomyolysis may develop.
Overdose Management Consider the possibility of multiple drug ingestion. The pharmacokinetic profile of AZSTARYS should be considered when treating patients with overdose. Because methylphenidate has a large volume of distribution and is rapidly metabolized, dialysis is not useful.
Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Serdexmethylphenidate is a prodrug of dexmethylphenidate. Dexmethylphenidate HCl is a central nervous system (CNS) stimulant. The mode of therapeutic action in ADHD is not known.
12.2Pharmacodynamics Dexmethylphenidate Dexmethylphenidate is the more pharmacologically active d-enantiomer of racemic d,l- methylphenidate. Methylphenidate blocks the reuptake of norepinephrine and dopamine into the presynaptic neuron and increase the release of these monoamines into the extraneuronal space. In vitro studies with serdexmethylphenidate showed little or no binding of the prodrug to monoaminergic reuptake transporters.
Cardiac Electrophysiology The effect of serdexmethylphenidate on QTc interval was evaluated in a randomized, double-blind, placebo-controlled, human abuse potential study (intranasal administration) in 46 healthy subjects. At a mean concentration 40 times the C max for the highest dose of AZSTARYS (52.3/10.4 mg base equivalent), serdexmethylphenidate does not prolong the QT interval to any clinically relevant extent.
12.3Pharmacokinetics Serdexmethylphenidate is a prodrug of dexmethylphenidate. Following a single dose administration of 52.3 mg/10.4 mg AZSTARYS and 40 mg of an dexmethylphenidate hydrochloride extended-release (ER) capsule in healthy volunteers under fasted conditions: The mean peak plasma concentration (C max ) of dexmethylphenidate was 14.0 ng/mL and 28.2 ng/mL, respectively; The mean area under concentration curve (AUC) of dexmethylphenidate was 186 hour*ng/mL and 248 hour*ng/mL, respectively. The plasma PK profiles of dexmethylphenidate following administration of AZSTARYS or dexmethylphenidate hydrochloride extended-release (ER) capsule are presented in Figure 1 .
Figure 1: Mean Dexmethylphenidate Plasma Concentration-Time Profiles After A Single Dose Administration of AZSTARYS or Dexmethylphenidate Hydrochloride Extended-Release (ER) Capsule in Healthy Adults Under Fasted Conditions Approximate linear PK was demonstrated for dexmethylphenidate following single dose administration of AZSTARYS in the dose range of 26.1 mg/5.2 mg to 52.3 mg/10.4 mg. Steady state of dexmethylphenidate was approached after the third once-daily dose. At steady-state, dexmethylphenidate mean exposures (C max and AUC 0-24h ) were approximately 37% higher relative to a single-dose administration of AZSTARYS.
No accumulation of serdexmethylphenidate was observed after once-daily administration of AZSTARYS. The mean relative exposure of serdexmethylphenidate to dexmethylphenidate based on molar concentrations for C max , C min , and AUC 0-24hr was about 101%, 8.5%, and 55.7%, respectively, following multiple once-daily oral dosing under fasted conditions. Absorption Cross-study calculation estimated an absolute oral bioavailability for serdexmethylphenidate of less than 3%.
The median time to reach C max of serdexmethylphenidate and dexmethylphenidate (T max ) is about 2 hours following a single dose administration of AZSTARYS under fasted conditions. Following oral administration of serdexmethylphenidate single moiety alone, dexmethylphenidate T max is reached at about 8 hours post dose. Effect of Food No clinically meaningful differences in the exposure of dexmethylphenidate were observed when administered after an overnight fast, with a high-fat, high-caloric meal, or sprinkled onto applesauce or water.
The median time to peak plasma concentration (T max ) was lengthened from 2 to 4-4.5 hours in the presence of food. Distribution Plasma protein binding of serdexmethylphenidate and dexmethylphenidate is approximately 56% and 47%, respectively, at 5 µM (about 60-fold higher than the therapeutic concentrations at the highest recommended dose). The mean apparent volume of distribution for serdexmethylphenidate was about
29.3L/kg after AZSTARYS administration. Dexmethylphenidate shows a mean volume of distribution of
2.65L/kg after intravenous administration. Elimination The m…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Serdexmethylphenidate is a prodrug of dexmethylphenidate. Dexmethylphenidate HCl is a central nervous system (CNS) stimulant. The mode of therapeutic action in ADHD is not known.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING AZSTARYS (serdexmethylphenidate/dexmethylphenidate) capsules are available as follows: 26.1 mg/5.2 mg Capsules – blue cap/grey body, imprinted with "286" on cap and "KP415" on the body Bottles of 100 ................................................................... NDC 65038-0286-99 39.2 mg/7.8 mg Capsules – dark blue cap/grey body, imprinted with "429" on cap and "KP415" on the body Bottles of 100 ................................................................... NDC 65038-0429-99 52.3 mg/10.4 mg Capsules – orange cap/grey body, imprinted with "5612" on cap and "KP415" on the body Bottles of 100 ...................................................................
NDC 65038-0561-99 Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F). [See USP Controlled Room Temperature]. Protect from moisture. Dispense in tight container (USP).
📋 Description ▾
11 DESCRIPTION AZSTARYS (serdexmethylphenidate and dexmethylphenidate) capsules contain dexmethylphenidate, a CNS stimulant, and serdexmethylphenidate, a prodrug of dexmethylphenidate. AZSTARYS capsules are intended for oral administration and each capsule contains a fixed molar ratio of 30% dexmethylphenidate and 70% serdexmethylphenidate. AZSTARYS contains 26.1/5.2, 39.2/7.8, or 52.3/10.4 mg of serdexmethylphenidate/ dexmethylphenidate (equivalent to 28/6, 42/9, or 56/12 mg of serdexmethylphenidate chloride/ dexmethylphenidate hydrochloride, respectively.
The combined molar dose of serdexmethylphenidate and dexmethylphenidate in each dosage strength of AZSTARYS is equivalent to 20, 30, or 40 mg dexmethylphenidate hydrochloride, respectively (equivalent to 17.3, 25.9 or 34.6 mg dexmethylphenidate free base, respectively). The chemical name of serdexmethylphenidate chloride is 3-((( 1S )-1-carboxy-2-hydroxyethyl)carbamoyl)-1-(((( 2R )-2-(2-( 1R )-methoxy-2-oxo-1-phenylethyl)piperidine-1-carbonyl)oxy)methyl)pyridinium chloride. Its molecular formula is C 25 H 30 N 3 O 8 + •Cl - , and its structural formula is: Serdexmethylphenidate chloride is a white to off-white crystalline powder.
Its solutions are acid to litmus. It is freely soluble in water, soluble in methanol, and slightly soluble in alcohol and acetone. Its molecular weight is 535.98 g/mol.
Dexmethylphenidate is the d-threo enantiomer of racemic d,l -methylphenidate hydrochloride. The chemical name of dexmethylphenidate hydrochloride is methyl ( R )-2-phenyl-2-(( R )-piperidin-2-yl)acetate hydrochloride. Its molecular formula is C 14 H 19 NO 2 •HCl, and its structural formula is: Dexmethylphenidate hydrochloride is a white to off-white powder.
Its solutions are acid to litmus. It is freely soluble in water and in methanol, soluble in alcohol, and slightly soluble in chloroform and in acetone. Its molecular weight is 269.77 g/mol.
Inactive ingredients: colloidal silicon dioxide, crospovidone, hypromellose, magnesium stearate, microcrystalline cellulose, and talc. Each strength capsule also contains colorant ingredients in the capsule shell as follows: 26.1/5.2 mg: Black Iron Oxide, FD&C Blue No. 1, Titanium Dioxide 39.2/7.8 mg: Black Iron Oxide, FD&C Blue No.
1, FD&C Red No. 40, Titanium Dioxide 52.3/10.4 mg: Black Iron Oxide, FD&C Red No. 40, FD&C Yellow No.
6, Titanium Dioxide chemical structure-1 chemical structure-2
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Abuse, Misuse, and Addiction Educate patients and their families about the risks of abuse, misuse, and addiction of AZSTARYS, which can lead to overdose and death, and proper disposal of any unused drug [see Warnings and Precautions (5.1) , Drug Abuse and Dependence (9.2) , Overdosage (10) ]. Advise patients to store AZSTARYS in a safe place, preferably locked, and instruct patients to not give AZSTARYS to anyone else.
Risk to Patients with Serious Cardiac Disease Advise patients that there are potential risks to patients with serious cardiac disease, including sudden death, with AZSTARYS use. Instruct patients to contact a healthcare provider immediately if they develop symptoms such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease [see Warnings and Precautions (5.2) ] . Increased Blood Pressure and Heart Rate Advise patients and their caregivers that AZSTARYS can elevate blood pressure and heart rate [see Warnings and Precautions ( 5.3 )] .
Psychiatric Adverse Reactions Advise patients and their caregivers that AZSTARYS, at recommended doses, can cause psychotic or manic symptoms, even in patients without a prior history or psychotic symptoms or mania [see Warnings and Precautions ( 5.4 )] . Priapism Advise patients and their caregivers of the possibility of painful or prolonged penile erections (priapism). Instruct the patient to seek immediate medical attention in the event of priapism [see Warnings and Precautions ( 5.5 )] .
Circulation Problems in Fingers and Toes [Peripheral vasculopathy, including Raynaud's phenomenon] Instruct patients about the risk of peripheral vasculopathy, including Raynaud's phenomenon, and associated signs and symptoms: fingers or toes may feel numb, cool, painful, and/or may change color from pale, to blue, to red. Instruct patients to report to their physician any new numbness, pain, skin color change, or sensitivity to temperature in fingers or toes. Instruct patients to call their physician immediately with any signs of unexplained wounds appearing on fingers or toes while taking AZSTARYS.
Further clinical evaluation (e.g., rheumatology referral) may be appropriate for certain patients [see Warnings and Precautions ( 5.6 )] . Long-Term Suppression of Growth in Pediatric Patients Advise patients and their caregivers that AZSTARYS can cause slowing of growth and weight loss [see Warnings and Precautions ( 5.7 )] . Increased Intraocular Pressure (IOP) and Glaucoma Advise patients that IOP and glaucoma may occur during treatment with AZSTARYS [see Warnings and Precautions ( 5.9 )] .
Motor and Verbal Tics, and Worsening of Tourette’s Syndrome Advise patients that motor and verbal tics and worsening of Tourette’s Syndrome may occur during treatment with AZSTARYS. Instruct patients to notify their healthcare provider if emergence of new tics or worsening of tics or Tourette’s syndrome occurs [see Warnings and Precautions ( 5.10 )] . Administration Instructions Advise patients and their caregivers to administer AZSTARYS capsules whole or opened and sprinkled over applesauce or added to water.
If sprinkled, advise patients and their caregivers to consume all the drug/food mixture immediately or within 10 minutes of mixing and not to store for future use [see Dosage and Administration ( 2.3 )]. Pregnancy Registry Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in females exposed to AZSTARYS during pregnancy [see Use in Specific Populations ( 8.1 )] . Lactation Advise nursing mother to monitor infants exposed to AZSTARYS through breastmilk for agitation, poor feeding, and reduced weight gain [see Use in Specific Populations ( 8.2 )] .
Distributed by: Corium, LLC 55 Cambridge Parkway, Suite 401 Cambridge, MA 02142 Corium Logo
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: 09/2025 REF-02399 09/2025 Medication Guide AZSTARYS® (az star’ is) (serdexmethylphenidate and dexmethylphenidate) capsules, CII What is the most important information I should know about AZSTARYS?
AZSTARYS can cause serious side effects, including: Abuse misuse, and addiction. AZSTARYS has a high chance for abuse and misuse and may lead to substance use problems, including addiction. Misuse and abuse of AZSTARYS, other methylphenidate containing medicines, and amphetamine containing medicines, can lead to overdose and death.
The risk of overdose and death is increased with higher doses of AZSTARYS or when it is used in ways that are not approved, such as snorting or injection. Your healthcare provider should check you or your child’s risk for abuse, misuse, and addiction before starting treatment with AZSTARYS and will monitor you or your child during treatment. AZSTARYS may lead to physical dependence after prolonged use, even if taken as directed by your healthcare provider.
Do not give AZSTARYS to anyone else. See “What is AZSTARYS?” for more information. Keep AZSTARYS in a safe place and properly dispose of any unused medicine.
See “How should I store AZSTARYS?” for more information. Tell your healthcare provider if you or your child have ever abused or been dependent on alcohol, prescription medicines, or street drugs. Risks for people with serious heart disease.
Sudden death has happened in people who have heart defects or other serious heart disease. Your healthcare provider should check you or your child carefully for heart problems before starting treatment with AZSTARYS. Tell your healthcare provider if you or your child have any heart problems, heart disease, or heart defects.
Call your healthcare provider or go to the nearest hospital emergency room right away if you or your child have any signs of heart problems such as chest pain, shortness of breath, or fainting during treatment with AZSTARYS. Increased blood pressure and heart rate. Your healthcare provider should check you or your child’s blood pressure and heart rate regularly during treatment with AZSTARYS.
Mental (psychiatric) problems, including: new or worse behavior and thought problems new or worse bipolar illness new psychotic symptoms (such as hearing voices, or seeing or believing things that are not real) or new manic symptoms Tell your healthcare provider about any mental problems you or your child have, or about a family history of suicide, bipolar illness, or depression. Call your healthcare provider right away if you or your child have any new or worsening mental symptoms or problems during treatment with AZSTARYS, especially hearing voices, seeing or believing things that are not real, or new manic symptoms.
What is AZSTARYS? AZSTARYS is a central nervous system stimulant prescription medicine used for the treatment of Attention-Deficit Hyperactivity Disorder (ADHD) in people 6 years of age and older. AZSTARYS may help increase attention and decrease impulsiveness and hyperactivity in people 6 years of age and older with ADHD.
AZSTARYS is not recommended for use in children under 6 years of age with ADHD. AZSTARYS is a federally controlled substance (CII) because it contains dexmethylphenidate that can be a target for people who abuse prescription medicines or street drugs. Keep AZSTARYS in a safe place to protect it from theft.
Never give AZSTARYS to anyone else because it may cause death or harm them. Selling or giving away AZSTARYS may harm others and is against the law. Do not take AZSTARYS if you or your child are: allergic to serdexmethylphenidate, methylphenidate, or any of the ingredients in AZSTARYS.
See the end of this Medication Guide for a complete list of ingredients in AZSTARYS. taking or have stopped taking within the past 14 days a medicine used to treat depression called a monoamine oxidase inhibitor (MAOI). Before taking AZSTARYS, tell y…