
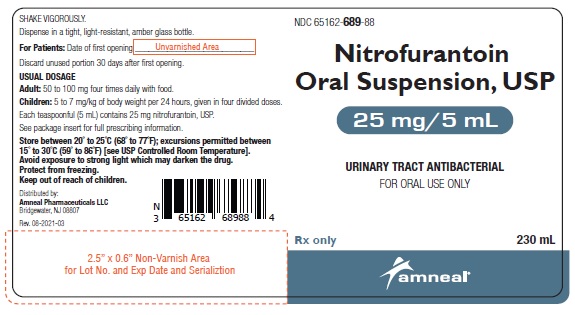
Nitrofurantoin 25 mg/5mL Suspension, 230 mL
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Nitrofuran Antibacterial class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Nitrofurantoin is used to treat urinary tract infections. Nitrofurantoin is in a class of medications called antibiotics. It works by killing bacteria that cause infection. Antibiotics such as nitrofurantoin will not work for colds, flu, or other viral infections. Using antibiotics when they are not needed increases your risk of getting an infection later that resists antibiotic treatment.
Read the full MedlinePlus article ↗- Nitrofurantoin is an antibiotic specifically for urinary tract infections — think bladder infections, not kidney infections. It works by concentrating in your urine where it kills...
- What exactly is nitrofurantoin used for?
- Yes, every time. Taking nitrofurantoin with food isn't just about avoiding an upset stomach — food actually helps your body absorb more of the medication, so it works better. Even...
- Do I really need to take it with food every single time?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Nitrofurantoin — tap one for details:
Nitrofurantoin may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $6.08 | $1,399.11 / 230 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nitrofurantoin 25 mg/5mL 59651-0206-23 | Aurobindo | 1 bottle | $1.718 | AB | Availability likely | — |
| Nitrofurantoin 25 mg/5mL 64980-0593-24 | Rising | 1 bottle | $1.718 | AB | Availability likely | — |
| Nitrofurantoin 25 mg/5mL 69238-2512-09 | Amneal | 1 bottle | $1.718 | — | Availability likely | — |
| Nitrofurantoin 25 mg/5mL 70069-0829-01 | Somerset | 1 bottle | $1.718 | AB | Availability likely | — |
| Nitrofurantoin 25 mg/5mL 70377-0118-31 | Biocon | 1 bottle | $1.718 | AB | Availability likely | — |
| Nitrofurantoin 25 mg/5mL 70954-0496-10 | ANI | 230 ml | $1.718 | AB | Availability likely | — |
| Nitrofurantoin 25 mg/5mL 72603-0176-01 | NorthStar | 1 bottle | $1.718 | AB | Availability likely | — |
| Nitrofurantoin 25 mg/5mL 31722-0491-23 | Camber | 1 bottle | — | AB | FDA listed | — |
| Nitrofurantoin 25 mg/5mL 40032-0450-11 | Novel | 1 bottle | — | AB | FDA listed | — |
| Nitrofurantoin 25 mg/5mL 43386-0450-11 | Lupin | 1 bottle | — | AB | FDA listed | — |
| Nitrofurantoin 25 mg/5mLthis 65162-0689-88 | Amneal | 230 ml | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 65162-0689-88 You're viewing this | 230 mL in 1 BOTTLE, GLASS (65162-689-88) | 2011-03-24 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Nitrofurantoin oral suspension is specifically indicated for the treatment of urinary tract infections when due to susceptible strains of Escherichia coli, enterococci , Staphylococcus aureus , and certain susceptible strains of Klebsiella and Enterobacter species. Nitrofurantoin oral suspension is not indicated for the treatment of pyelonephritis or perinephric abscesses. Nitrofurantoins lack the broader tissue distribution of other therapeutic agents approved for urinary tract infections.
Consequently, many patients who are treated with nitrofurantoin oral suspension are predisposed to persistence or reappearance of bacteriuria. Urine specimens for culture and susceptibility testing should be obtained before and after completion of therapy. If persistence or reappearance of bacteriuria occurs after treatment with nitrofurantoin oral suspension, other therapeutic agents with broader tissue distribution should be selected.
In considering the use of nitrofurantoin oral suspension, lower eradication rates should be balanced against the increased potential for systemic toxicity and for the development of antimicrobial resistance when agents with broader tissue distribution are utilized.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Nitrofurantoin oral suspension should be given with food to improve drug absorption and, in some patients, tolerance. Adults 50 to 100 mg four times a day - the lower dosage level is recommended for uncomplicated urinary tract infections. Pediatric Patients 5 to 7 mg/kg of body weight per 24 hours, given in four divided doses (contraindicated under one month of age).
The following table is based on an average weight in each range receiving 5 to 6 mg/kg of body weight per 24 hours, given in four divided doses. It can be used to calculate an average dose of nitrofurantoin oral suspension (25 mg/5 mL) for pediatric patients. Table 3: Pediatric Dosing Table Weight in Kilograms (kg) Pediatric Doses (milliliters) and Frequency 7 kg to 11 kg 2.5 mL Four times Daily 12 kg to 21 kg 5 mL Four times Daily 22 kg to 30 kg 7.5 mL Four times Daily 31 kg to 41 kg 10 mL Four times Daily 42 kg or greater See Adult Dose Therapy should be continued for one week or for at least 3 days after sterility of the urine is obtained.
Continued infection indicates the need for reevaluation. For long-term suppressive therapy in adults, a reduction of dosage to 50 to 100 mg at bedtime may be adequate. For long-term suppressive therapy in pediatric patients, doses as low as 1 mg/kg per 24 hours, given in a single dose or in two divided doses, may be adequate.
SEE WARNINGS SECTION REGARDING RISKS ASSOCIATED WITH LONG TERM THERAPY .
⛔ Contraindications ▾
CONTRAINDICATIONS Anuria, oliguria, or significant impairment of renal function (creatinine clearance under 60 mL per minute or clinically significant elevated serum creatinine) are contraindications. Treatment of this type of patient carries an increased risk of toxicity because of impaired excretion of the drug. Because of the possibility of hemolytic anemia due to immature erythrocyte enzyme systems (glutathione instability), the drug is contraindicated in pregnant patients at term (38 to 42 weeks gestation), during labor and delivery, or when the onset of labor is imminent.
For the same reason, the drug is contraindicated in neonates under one month of age. Nitrofurantoin oral suspension is contraindicated in patients with a previous history of cholestatic jaundice/hepatic dysfunction associated with nitrofurantoin. Nitrofurantoin oral suspension is also contraindicated in those patients with known hypersensitivity to nitrofurantoin.
⚠️ Warnings ▾
WARNINGS Pulmonary reactions ACUTE, SUBACUTE, OR CHRONIC PULMONARY REACTIONS HAVE BEEN OBSERVED IN PATIENTS TREATED WITH NITROFURANTOIN. IF THESE REACTIONS OCCUR, NITROFURANTOIN ORAL SUSPENSION SHOULD BE DISCONTINUED AND APPROPRIATE MEASURES TAKEN. REPORTS HAVE CITED PULMONARY REACTIONS AS A CONTRIBUTING CAUSE OF DEATH.
CHRONIC PULMONARY REACTIONS (DIFFUSE INTERSTITIAL PNEUMONITIS OR PULMONARY FIBROSIS, OR BOTH) CAN DEVELOP INSIDIOUSLY. THESE REACTIONS OCCUR RARELY AND GENERALLY IN PATIENTS RECEIVING THERAPY FOR SIX MONTHS OR LONGER. CLOSE MONITORING OF THE PULMONARY CONDITION OF PATIENTS RECEIVING LONG-TERM THERAPY IS WARRANTED AND REQUIRES THAT THE BENEFITS OF THERAPY BE WEIGHED AGAINST POTENTIAL RISKS (see RESPIRATORY REACTIONS ).
Hepatotoxicity Hepatic reactions, including hepatitis, cholestatic jaundice, chronic active hepatitis, and hepatic necrosis, occur rarely. Fatalities have been reported. The onset of chronic active hepatitis may be insidious, and patients should be monitored periodically for changes in biochemical tests that would indicate liver injury.
If hepatitis occurs, the drug should be withdrawn immediately and appropriate measures should be taken. Neuropathy Peripheral neuropathy, which may become severe or irreversible, has occurred. Fatalities have been reported.
Conditions such as renal impairment (creatinine clearance under 60 mL per minute or clinically significant elevated serum creatinine), anemia, diabetes mellitus, electrolyte imbalance, vitamin B deficiency, and debilitating disease may enhance the occurrence of peripheral neuropathy. Patients receiving long-term therapy should be monitored periodically for changes in renal function. Optic neuritis has been reported rarely in postmarketing experience with nitrofurantoin formulations.
Hemolytic anemia Cases of hemolytic anemia of the primaquine-sensitivity type have been induced by nitrofurantoin. Hemolysis appears to be linked to a glucose-6-phosphate dehydrogenase deficiency in the red blood cells of the affected patients. This deficiency is found in 10 percent of Blacks and a small percentage of ethnic groups of Mediterranean and Near-Eastern origin.
Hemolysis is an indication for discontinuing Nitrofurantoin oral suspension; hemolysis ceases when the drug is withdrawn. Clostridium difficile -associated diarrhea Clostridium difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including nitrofurantoin oral suspension, and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile.
C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibiotic use.
Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibiotic use not directed against C. difficile may need to be discontinued. Appropriate fluid and electrolyte management, protein supplementation, antibiotic treatment of C. difficile , and surgical evaluation should be instituted as clinically indicated.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Respiratory CHRONIC, SUBACUTE, OR ACUTE PULMONARY HYPERSENSITIVITY REACTIONS MAY OCCUR. CHRONIC PULMONARY REACTIONS MAY OCCUR GENERALLY IN PATIENTS WHO HAVE RECEIVED CONTINUOUS TREATMENT FOR SIX MONTHS OR LONGER. MALAISE, DYSPNEA ON EXERTION, COUGH, AND ALTERED PULMONARY FUNCTION ARE COMMON MANIFESTATIONS WHICH CAN OCCUR INSIDIOUSLY.
RADIOLOGIC AND HISTOLOGIC FINDINGS OF DIFFUSE INTERSTITIAL PNEUMONITIS OR FIBROSIS, OR BOTH, ARE ALSO COMMON MANIFESTATIONS OF THE CHRONIC PULMONARY REACTION. FEVER IS RARELY PROMINENT. THE SEVERITY OF CHRONIC PULMONARY REACTIONS AND THEIR DEGREES OF RESOLUTION APPEAR TO BE RELATED TO THE DURATION OF THERAPY AFTER THE FIRST CLINICAL SIGNS APPEAR.
PULMONARY FUNCTION MAY BE IMPAIRED PERMANENTLY, EVEN AFTER CESSATION OF THERAPY. THE RISK IS GREATER WHEN CHRONIC PULMONARY REACTIONS ARE NOT RECOGNIZED EARLY. In subacute pulmonary reactions, fever and eosinophilia occur less often than in the acute form.
Upon cessation of therapy, recovery may require several months. If the symptoms are not recognized as being drug-related and nitrofurantoin therapy is not stopped, the symptoms may become more severe. Acute pulmonary reactions are commonly manifested by fever, chills, cough, chest pain, dyspnea, pulmonary infiltration with consolidation of pleural effusion on x-ray, and eosinophilia.
Acute reactions usually occur within the first week of treatment and are reversible with cessation of therapy. Resolution often is dramatic (see WARNINGS ). Changes in EKG (e.g., non-specific ST/T wave changes, bundle branch block) have been reported in association with pulmonary reactions.
Cyanosis has been reported rarely. Hepatic Hepatic reactions, including hepatitis, cholestatic jaundice, chronic active hepatitis, and hepatic neurosis, occur rarely (see WARNINGS ). Neurologic Peripheral neuropathy, which may become severe or irreversible, has occurred.
Fatalities have been reported. Conditions such as renal impairment (creatinine clearance under 60 mL per minute or clinically significant elevated serum creatinine), anemia, diabetes mellitus, electrolyte imbalance, vitamin B deficiency, and debilitating diseases may increase the possibility of peripheral neuropathy (see WARNINGS ). Asthenia, vertigo, nystagmus, dizziness, headache, and drowsiness have also been reported with the use of nitrofurantoin.
Benign intracranial hypertension (pseudotumor cerebri), confusion, depression, optic neuritis, and psychotic reactions have been reported rarely. Bulging fontanels, as a sign of benign intracranial hypertension in infants, have been reported rarely. Dermatologic Exfoliative dermatitis and erythema multiforme (including Stevens-Johnson syndrome) have been reported rarely.
Transient alopecia also has been reported. Allergic A lupus-like syndrome associated with pulmonary reactions to nitrofurantoin has been reported. Also, angioedema; maculopapular, erythematous, or eczematous eruptions; pruritus; urticaria; anaphylaxis; arthralgia; myalgia; drug fever; and vasculitis (sometimes associated with pulmonary reactions) have been reported.
Hypersensitivity reactions present the most frequent spontaneously-reported adverse events in world-wide postmarketing experience with nitrofurantoin formulations. Gastrointestinal Nausea, emesis, and anorexia occur most often. Abdominal pain and diarrhea are less common gastrointestinal reactions.
These dose-related reactions can be minimized by reduction of dosage. Sialadenitis and pancreatitis have been reported. There have been sporadic reports of pseudomembranous colitis with the use of nitrofurantoin.
The onset of pseudomembranous colitis symptoms may occur during or after antimicrobial treatment (see WARNINGS ). Hematologic Cyanosis secondary to methemoglobinemia has been reported rarely. Miscellaneous As with other antimicrobial agents, superinfections caused by resistant organisms, e.g., Pseudomonas species or Candida species, can occur.
There are sporadic reports of…
🆘 Overdosage ▾
OVERDOSAGE Occasional incidents of acute overdosage of nitrofurantoin oral suspension have not resulted in any specific symptoms other than vomiting. Induction of emesis is recommended. There is no specific antidote, but a high fluid intake should be maintained to promote urinary excretion of the drug. It is dialyzable.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Orally administered nitrofurantoin oral suspension is readily absorbed and rapidly excreted in urine. Blood concentrations at therapeutic dosage are usually low. It is highly soluble in urine, to which it may impart a brown color.
Following a dose regimen of 100 mg q.i.d. for 7 days, average urinary drug recoveries (0 to 24 hours) on day 1 and day 7 were 42.7% and 43.6%. Unlike many drugs, the presence of food or agents delaying gastric emptying can increase the bioavailability of nitrofurantoin oral suspension, presumably by allowing better dissolution in gastric juices. Microbiology Mode of Action Nitrofurantoin is reduced by a wide range of enzymes including bacterial flavoproteins to reactive intermediates which are damaging to macromolecules such as DNA and proteins.
Cross-Resistance Although cross-resistance with other antimicrobials may occur, cross-resistance with sulfonamides has not been observed. Interaction with Other Antimicrobials Antagonism has been demonstrated in vitro between nitrofurantoin and quinolone antimicrobial agents. Nitrofurantoin, in the form of nitrofurantoin oral suspension, has been shown to be active against most of the following bacteria both in vitro and in clinical infections: (see INDICATIONS AND USAGE ).
Gram-positive Aerobes Staphylococcus aureus Enterococcus species Gram-Negative Aerobes Escherichia coli NOTE: Some strains of Enterobacter species and Klebsiella species are resistant to nitrofurantoin. The following in vitro data are available, but their clinical significance is unknown. Nitrofurantoin exhibits in vitro activity against the following bacteria; however, the safety and effectiveness of nitrofurantoin in treating clinical infections due to these bacteria have not been established in adequate and well controlled clinical trials.
Gram-Positive Aerobes Coagulase-negative staphylococci (including Staphylococcus epidermidis and Staphylococcus saprophyticus ) Streptococcus agalactiae Viridans group streptococci Gram-Negative Aerobes Citrobacter koseri Citrobacter freundii Klebsiella oxytoca Nitrofurantoin is not active against most strains of Proteus species or Serratia species. It has no activity against Pseudomonas species. Susceptibility Testing For specific information regarding susceptibility test interpretive criteria, and associated test methods and quality control standards recognized by FDA for this drug, please see: http://www.fda.gov/STIC.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Nitrofurantoin oral suspension, USP (a clear, yellow colored, tutti frutti flavored suspension) containing 25 mg nitrofurantoin, USP in each teaspoonful (5 mL) is available as follows: 230 mL in an 8 oz amber bottle. NDC 65162-689-88 Avoid exposure to strong light which may darken the drug. It is stable when stored between 20° to 25°C (68° to 77°F); excursions permitted between 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
Protect from freezing. Shake vigorously. Dispense in tight, light-resistant, amber glass bottles.
Use within 30 days. Keep out of reach of children. Rx only Distributed by: Amneal Pharmaceuticals LLC Bridgewater, NJ 08807 Rev.
08-2021-04
📋 Description ▾
DESCRIPTION Nitrofurantoin oral suspension USP, a synthetic chemical, is a stable, yellow, crystalline compound. Nitrofurantoin oral suspension, USP is an antibacterial agent for specific urinary tract infections. Nitrofurantoin oral suspension, USP is available in 25 mg/5 mL liquid suspension for oral administration.
Inactive Ingredients Nitrofurantoin oral suspension, USP contains anhydrous citric acid, artificial fruit flavor, carboxymethylcellulose sodium, glycerin, magnesium aluminum silicate, methylparaben, propylparaben, purified water, saccharin insoluble, sodium citrate, and sorbitol solution 52ae3bb2-figure-01