
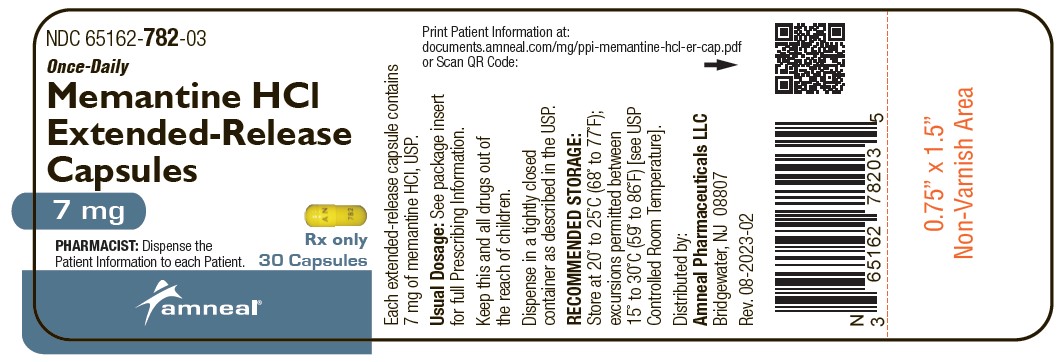
Memantine Hydrochloride 7 mg Capsule, Extended Release, 30-count — NDC 65162-782-03 (Billing 65162-0782-03)
This is a package of 30 capsules of Memantine Hydrochloride 7 mg Capsule, Extended Release from Amneal Pharmaceuticals LLC, marketed since Dec 2017 and currently FDA-listed; retail pharmacies pay about $0.3123 per capsule (NADAC). It is the main listing for this product, which comes in 3 package sizes.
NDC database record
One package, one record: these facts belong to NDC 65162-782-03 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 65162 labeler · 782 product · 03 package
- Package marketed since
- Dec 22, 2017
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 30 EA per package
- Barcode (UPC)
- 0365162784091, 0365162783094, 0365162785098, 0365162782097
- Medicaid fills, this package
- 57 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Other active recalls for Memantine Hydrochloride (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 070867
- GCN: 34524
- GPI-14 (Medi-Span): 62053550107020
- HICL (First Databank): 013778
- AHFS class code: 28:92.00.00
- RxCUI (RxNorm): 996594
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the N-methyl-D-aspartate Receptor Antagonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Memantine is used to treat the symptoms of Alzheimer's disease (AD; a brain disease that affects memory, thinking, and behavior). Memantine is in a class of medications called NMDA receptor antagonists. It works by changing the activity of certain natural substances in the brain.
Read the full MedlinePlus article ↗- Memantine treats moderate to severe dementia of the Alzheimer’s type. It helps manage symptoms, but it has not been shown to prevent or slow the underlying nerve damage.
- Take it by mouth as your prescriber directs. The dose usually starts low and goes up over several weeks. Tablets and oral solution can be taken with or without food. If you miss a...
- The most common are dizziness, headache, confusion and constipation. Tell your doctor if they bother you or don’t settle. Seek help quickly for a seizure, a severe skin reaction, u...
- Many people take it with donepezil, which showed no interaction in studies. Be careful with amantadine, ketamine and dextromethorphan, and with sodium bicarbonate or carbonic anhyd...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Memantine Hydrochloride — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.312 | $9.37 / 30 capsules |
| Medicaid paysCMS SDUD · 12 mo | $0.5242 | $15.73 / 30 capsules |
| Medicare drug plans payPart D · Q2 2026 | $1.09 | $32.78 / 30 capsules |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 65162-0782-03 You're viewing this Main listing | 30 CAPSULE, EXTENDED RELEASE in 1 BOTTLE | $0.3123 / ea | $9.37 | 2017-12-22 | — | Active |
| 65162-0782-09 65162-782-09 | 90 CAPSULE, EXTENDED RELEASE in 1 BOTTLE | — | — | 2017-12-22 | — | Active |
| 65162-0782-50 65162-782-50 | 500 CAPSULE, EXTENDED RELEASE in 1 BOTTLE | — | — | 2017-12-22 | — | Active |
You're viewing the smallest of 3 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 65162-0782-09?
What NDC number is used to bill for this package of Memantine Hydrochloride 7 mg Capsule, Extended Release?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| memantine hydrochloride 7 mg 00904-6734-61 | Major | 1 capsule | $0.312 | AB | Availability likely | — |
| Memantine Hydrochloride 7 mg 16571-0852-03 | Rising | 30 capsules | $0.312 | AB | Availability likely | — |
| Memantine Hydrochloride 7 mg 59651-0404-30 | Aurobindo | 30 capsules | $0.312 | AB | Availability likely | — |
| Memantine Hydrochloride 7 mgthis 65162-0782-03 | Amneal | 30 capsules | $0.312 | AB | Availability likely | — |
| Memantine hydrochloride 7 mg 68382-0546-06 | Zydus | 30 capsules | $0.312 | AB | Availability likely | — |
| Memantine Hydrochloride 7 mg 69680-0161-30 | Vitruvias | 30 capsules | $0.312 | AB | Availability likely | — |
| Memantine Hydrochloride 7 mg 70436-0054-04 | Slate | 30 capsules | $0.312 | AB | Availability likely | — |
| Memantine hydrochloride 7 mg 33342-0219-07 | Macleods | 30 capsules | — | AB | FDA listed | — |
| memantine hydrochloride 7 mg 68180-0246-02 | Lupin | 500 capsules | — | AB | FDA listed | — |
| Memantine hydrochloride 7 mg 70771-1321-03 | Zydus | 30 capsules | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 8PJ61P6TS3
Butyl alcohol is a clear liquid organic solvent derived from petroleum or natural sources. In medicines, it helps dissolve active ingredients and serves as a solvent in liquid formulations and some topical products.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII 7Z8S9VYZ4B
Ethylcellulose is a plant-derived thickener and film-former made by chemically modifying cellulose. It's used as a binder to hold tablet ingredients together, a coating to control how quickly medicine is released, or a thickener in liquid formulations.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 8Z96QXD6UM
Triethyl citrate is a clear liquid derived from citric acid. It acts as a plasticizer and solvent in tablet coatings and film formulations, helping the coating remain flexible and adhere properly to the medicine.
18 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Amneal Pharmaceuticals LLC labeler code 65162
- Warfarin Sodium 7.5 mg Tablet NDC 65162-768-10
- Warfarin Sodium 10 mg Tablet NDC 65162-769-10
- Ibuprofen Pain Reliever/Fever Reducer 200 mg Capsule, Liquid Filled NDC 65162-770-02
- Montelukast Sodium 4 mg Tablet, Chewable NDC 65162-771-03
- Montelukast Sodium 5 mg Tablet, Chewable NDC 65162-772-03
- Budesonide 3 mg Capsule, Delayed Release NDC 65162-778-10
- Memantine Hydrochloride 14 mg Capsule, Extended Release NDC 65162-783-03
- Memantine Hydrochloride 21 mg Capsule, Extended Release NDC 65162-784-03
- Memantine Hydrochloride 28 mg Capsule, Extended Release NDC 65162-785-03
- Lidocaine 700 mg Patch NDC 65162-791-08
- Dextromethorphan Polistirex Extended-Release 30 mg/5mL Suspension NDC 65162-799-76
- Temozolomide 5 mg Capsule NDC 65162-801-14
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Memantine hydrochloride extended-release capsules are indicated for the treatment of moderate to severe dementia of the Alzheimer’s type. Memantine hydrochloride extended-release capsules are a N-methyl-D-aspartate (NMDA) receptor antagonist indicated for the treatment of moderate to severe dementia of the Alzheimer’s type. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended starting dose of memantine hydrochloride extended-release capsules is 7 mg once daily; the dose should be increased in 7 mg increments to the recommended maintenance dose of 28 mg once daily; the minimum recommended interval between dose increases is one week. ( 2.1 ) Patients with severe renal impairment: the recommended maintenance dose of memantine hydrochloride extended-release capsules is 14 mg once daily. ( 2.3 )
2.1Recommended Dosing The dosage of memantine hydrochloride extended-release capsules shown to be effective in a controlled clinical trial is 28 mg once daily. The recommended starting dose of memantine hydrochloride extended-release capsules is 7 mg once daily. The dose should be increased in 7 mg increments to the recommended maintenance dose of 28 mg once daily.
The minimum recommended interval between dose increases is one week. The dose should only be increased if the previous dose has been well tolerated. The maximum recommended dose is 28 mg once daily.
Memantine hydrochloride extended-release capsules can be taken with or without food. Memantine hydrochloride extended-release capsules can be taken intact or may be opened, sprinkled on applesauce, and thereby swallowed. The entire contents of each memantine hydrochloride extended-release capsule should be consumed; the dose should not be divided.
Except when opened and sprinkled on applesauce, as described above, memantine hydrochloride extended-release capsules should be swallowed whole. Memantine hydrochloride extended-release capsules should not be divided, chewed, or crushed. If a patient misses a single dose of memantine hydrochloride extended-release capsules, that patient should not double up on the next dose.
The next dose should be taken as scheduled. If a patient fails to take memantine hydrochloride extended-release capsules for several days, dosing may need to be resumed at lower doses and retitrated as described above.
2.2Switching from NAMENDA to Memantine hydrochloride Extended-release Capsules Patients treated with NAMENDA may be switched to memantine hydrochloride extended-release capsules as follows: It is recommended that a patient who is on a regimen of 10 mg twice daily of NAMENDA be switched to memantine hydrochloride extended-release 28 mg once daily capsules the day following the last dose of 10 mg NAMENDA. There is no study addressing the comparative efficacy of these 2 regimens. In a patient with severe renal impairment, it is recommended that a patient who is on a regimen of 5 mg twice daily of NAMENDA be switched to memantine hydrochloride extended-release 14 mg once daily capsules the day following the last dose of 5 mg NAMENDA.
2.3Dosing in Patients with Renal Impairment In patients with severe renal impairment (creatinine clearance of 5 to 29 mL/min, based on the Cockcroft-Gault equation), the recommended maintenance dose (and maximum recommended dose) is 14 mg/day [see Clinical Pharmacology (12.3) ] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Each capsule contains 7 mg, 14 mg, 21 mg, or 28 mg of memantine hydrochloride, USP. The 7 mg capsules are a standard yellow opaque capsule, imprinted with “AN” on the cap and “782” on the body in black ink. The 14 mg capsules are a standard yellow opaque cap and dark green opaque body capsule, imprinted with “AN” on the cap and “783” on the body in black ink.
The 21 mg capsules are a white opaque cap and dark green opaque body capsule, imprinted with “AN” on the cap and “784” on the body in black ink. The 28 mg capsules are a dark green opaque capsule, imprinted with “AN” on the cap and “785” on the body in white ink. Memantine hydrochloride extended-release capsules are available as an extended-release capsule in the following strengths: 7 mg, 14 mg, 21 mg, 28 mg.
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Memantine hydrochloride extended-release capsules are contraindicated in patients with known hypersensitivity to memantine hydrochloride or to any excipients used in the formulation. Memantine hydrochloride extended-release capsules are contraindicated in patients with known hypersensitivity to memantine hydrochloride or to any excipients used in the formulation. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Conditions that raise urine pH may decrease the urinary elimination of memantine resulting in increased plasma levels of memantine. (5.1 , 7.1 )
5.1Genitourinary Conditions Conditions that raise urine pH may decrease the urinary elimination of memantine resulting in increased plasma levels of memantine [see Drug Interactions (7.1) ] .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most commonly observed adverse reactions occurring at a frequency of at least 5% and greater than placebo with administration of memantine hydrochloride extended-release capsules 28 mg/day were headache, diarrhea and dizziness. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Amneal Pharmaceuticals at 1-877-835-5472 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Memantine hydrochloride extended-release capsules were evaluated in a double-blind placebo-controlled trial in which a total of 676 patients with moderate to severe dementia of the Alzheimer’s type (341 patients on memantine hydrochloride extended-release capsules 28 mg/day and 335 patients on placebo) were treated for up to 24 weeks. Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
Adverse Reactions Leading to Discontinuation In the placebo-controlled clinical trial of memantine hydrochloride extended-release capsules, the proportion of patients in the memantine hydrochloride extended-release capsules group and the placebo group who discontinued treatment due to adverse reactions was 10% and 6%, respectively. The most common adverse reaction that led to treatment discontinuation in the memantine hydrochloride extended-release capsules group was dizziness, at a rate of 1.5%. Most Common Adverse Reactions The most commonly observed adverse reactions seen in patients administered memantine hydrochloride extended-release capsules in the controlled clinical trial, defined as those occurring at a frequency of at least 5% in the memantine hydrochloride extended-release capsules group and at a frequency higher than placebo, were headache, diarrhea and dizziness.
Table 1 lists adverse reactions that were observed at an incidence of ≥ 2% in the memantine hydrochloride extended-release capsules group and occurred at a rate greater than placebo. Table 1: Adverse Reactions Observed with a Frequency of ≥ 2% in the Memantine Hydrochloride Extended-release Capsules Group and at a Rate Greater than Placebo Adverse Reaction Placebo (n = 335) % Memantine Hydrochloride Extended-release Capsules 28 mg (n = 341) % Gastrointestinal Disorders Diarrhea 4 5 Constipation 1 3 Abdominal pain 1 2 Vomiting 1 2 Infections and Infestations Influenza 3 4 Investigations Weight, increased 1 3 Musculoskeletal and Connective Tissue Disorders Back pain 1 3 Nervous System Disorders Headache 5 6 Dizziness 1 5 Somnolence 1 3 Psychiatric Disorders Anxiety 3 4 Depression 1 3 Aggression 1 2 Renal and Urinary Disorders Urinary incontinence 1 2 Vascular Disorders Hypertension 2 4 Hypotension 1 2 Seizure Memantine has not been systematically evaluated in patients with a seizure disorder.
In clinical trials of memantine, seizures occurred in 0.3% of patients treated with memantine and 0.6% of patients treated with placebo.
6.2Postmarketing Experience The following adverse reactions have been identified during post-approval use of memantine. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. These reactions include: Blood and Lymphatic System Disorders: agranulocytosis, leukopenia (including neutropenia), pancytopenia, thrombocytopenia, thrombotic thrombocytopenic purpura.
Cardiac Disorders: cardiac failure congestive. Gastrointestinal Disorders: pancreatitis. Hepatobiliary Disorders: hepatitis.
Psychiatric Disorders: suicidal ideation. Renal and Urinary Disorders: acute renal failure (including increased creatinine and renal insufficiency). Skin Disorders: Stevens Johnson syndrome.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Drugs That Make the Urine Alkaline The clearance of memantine was reduced by about 80% under alkaline urine conditions at pH 8. Therefore, alterations of urine pH towards the alkaline condition may lead to an accumulation of the drug with a possible increase in adverse effects. Urine pH is altered by diet, drugs (e.g. carbonic anhydrase inhibitors, sodium bicarbonate) and clinical state of the patient (e.g. renal tubular acidosis or severe infections of the urinary tract).
Hence, memantine should be used with caution under these conditions.
7.2Use with Other N-methyl-D-aspartate (NMDA) Antagonists The combined use of memantine hydrochloride extended-release capsules with other NMDA antagonists (amantadine, ketamine, and dextromethorphan) has not been systematically evaluated and such use should be approached with caution.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with the use of memantine hydrochloride extended-release capsules in pregnant women. Adverse developmental effects (decreased body weight and skeletal ossification) were observed in the offspring of rats administered memantine during pregnancy at doses associated with minimal maternal toxicity. These doses are higher than those used in humans at the maximum recommended daily dose of memantine hydrochloride extended-release capsules [see Data].
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown. Data Animal Data Oral administration of memantine (0, 2, 6, or 18 mg/kg/day) to rats during the period of organogenesis resulted in decreased skeletal ossification in fetuses at the highest dose tested.
The higher no-effect dose for adverse developmental effects (6 mg/kg) is 2 times the maximum recommended human daily dose (MRHD) of memantine hydrochloride extended-release capsules (28 mg) on a body surface area (mg/m 2 ) basis. Oral administration of memantine to rabbits (0, 3, 10, or 30 mg/kg/day) during the period of organogenesis resulted in no adverse developmental effects. The highest dose tested is approximately 20 times the MRHD of memantine hydrochloride extended-release capsules on a mg/m 2 basis.
In rats, memantine (0, 2, 6, or 18 mg/kg/day) was administered orally prior to and throughout mating and, in females, through the period of organogenesis or continuing throughout lactation to weaning. Decreased skeletal ossification in fetuses and decreased body weight in pups were observed at the highest dose tested. The higher no-effect dose for adverse developmental effects (6 mg/kg/day) is 2 times the MRHD of memantine hydrochloride extended-release capsules on a mg/m 2 basis.
Oral administration of memantine (0, 2, 6, or 18 mg/kg/day) to rats from late gestation throughout lactation to weaning, resulted in decreased pup weights at the highest dose tested. The higher no-effect dose (6 mg/kg/day) is approximately 2 times the MRHD of memantine hydrochloride extended-release capsules on a mg/m 2 basis.
8.2Lactation Risk Summary There are no data on the presence of memantine in human milk, the effects on the breastfed infant, or the effects of memantine hydrochloride extended-release capsules on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for memantine hydrochloride extended-release capsules and any potential adverse effects on the breastfed infant from memantine hydrochloride extended-release capsules or from the underlying maternal condition.
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. Memantine failed to demonstrate efficacy in two 12-week controlled clinical studies of 578 pediatric patients aged 6 to 12 years with autism spectrum disorders (ASD), including autism, Asperger’s disorder and Pervasive Development Disorder - Not Otherwise Specified (PDD-NOS). Memantine has not been studied in pediatric patients under 6 years of age or over 12 years of age.
Memantine treatment was initiated at 3 mg/day and the dose was escalated to the target dose (weight-based) by week 6. Oral doses of memantine 3 mg, 6 mg, 9 mg, or 15 mg extended-release capsules were administered once daily to patients with weights < 20 kg, 20 to 39 kg, 40 to 59 kg and ≥ 60 kg, respectively. In a randomized, 12-week double-blind, placebo-controlled parallel study (Study A) in patients with autism, there was no statistically significant difference in the Social Responsiveness Scale (SRS) total raw score between patients randomized to memantine (n=54) and those randomized to placebo (n=53).… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with the use of memantine hydrochloride extended-release capsules in pregnant women. Adverse developmental effects (decreased body weight and skeletal ossification) were observed in the offspring of rats administered memantine during pregnancy at doses associated with minimal maternal toxicity. These doses are higher than those used in humans at the maximum recommended daily dose of memantine hydrochloride extended-release capsules [see Data].
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown. Data Animal Data Oral administration of memantine (0, 2, 6, or 18 mg/kg/day) to rats during the period of organogenesis resulted in decreased skeletal ossification in fetuses at the highest dose tested.
The higher no-effect dose for adverse developmental effects (6 mg/kg) is 2 times the maximum recommended human daily dose (MRHD) of memantine hydrochloride extended-release capsules (28 mg) on a body surface area (mg/m 2 ) basis. Oral administration of memantine to rabbits (0, 3, 10, or 30 mg/kg/day) during the period of organogenesis resulted in no adverse developmental effects. The highest dose tested is approximately 20 times the MRHD of memantine hydrochloride extended-release capsules on a mg/m 2 basis.
In rats, memantine (0, 2, 6, or 18 mg/kg/day) was administered orally prior to and throughout mating and, in females, through the period of organogenesis or continuing throughout lactation to weaning. Decreased skeletal ossification in fetuses and decreased body weight in pups were observed at the highest dose tested. The higher no-effect dose for adverse developmental effects (6 mg/kg/day) is 2 times the MRHD of memantine hydrochloride extended-release capsules on a mg/m 2 basis.
Oral administration of memantine (0, 2, 6, or 18 mg/kg/day) to rats from late gestation throughout lactation to weaning, resulted in decreased pup weights at the highest dose tested. The higher no-effect dose (6 mg/kg/day) is approximately 2 times the MRHD of memantine hydrochloride extended-release capsules on a mg/m 2 basis.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. Memantine failed to demonstrate efficacy in two 12-week controlled clinical studies of 578 pediatric patients aged 6 to 12 years with autism spectrum disorders (ASD), including autism, Asperger’s disorder and Pervasive Development Disorder - Not Otherwise Specified (PDD-NOS). Memantine has not been studied in pediatric patients under 6 years of age or over 12 years of age.
Memantine treatment was initiated at 3 mg/day and the dose was escalated to the target dose (weight-based) by week 6. Oral doses of memantine 3 mg, 6 mg, 9 mg, or 15 mg extended-release capsules were administered once daily to patients with weights < 20 kg, 20 to 39 kg, 40 to 59 kg and ≥ 60 kg, respectively. In a randomized, 12-week double-blind, placebo-controlled parallel study (Study A) in patients with autism, there was no statistically significant difference in the Social Responsiveness Scale (SRS) total raw score between patients randomized to memantine (n=54) and those randomized to placebo (n=53).
In a 12-week responder-enriched randomized withdrawal study (Study B) in 471 patients with ASD, there was no statistically significant difference in the loss of therapeutic response rates between patients randomized to remain on full-dose memantine (n=153) and those randomized to switch to placebo (n=158). The overall safety profile of memantine in pediatric patients was generally consistent with the known safety profile in adults [see Adverse Reactions (6.1) ] . In Study A, the adverse reactions in the memantine group (n=56) that were reported in at least 5% of patients and at least twice the frequency of the placebo group (N=58) are listed in Table 2.
Table 2: Study A Commonly Reported Adverse Reactions with a Frequency ≥ 5% and Twice That of Placebo Adverse Reaction Memantine N=56 Placebo N=58 Cough 8.9% 3.4% Influenza 7.1% 3.4% Rhinorrhea 5.4% 0% Agitation 5.4% 1.7% Discontinuations due to Adverse Reactions a Aggression 3.6% 1.7% Irritability 1.8% 3.4% a Reported adverse reactions leading to discontinuation in more than one patient in either treatment group. The adverse reactions that were reported in at least 5% of patients in the 12 to 48 week open-label study to identify responders to enroll in Study B are listed in Table 3.
Table 3: 12 to 48 Week Open Label Lead-In Study to Study B Commonly Reported Adverse Reactions with a Frequency ≥ 5% Adverse Reaction Memantine N=903 Headache 8.0% Nasopharyngitis 6.3% Pyrexia 5.8% Irritability 5.4% Discontinuations due to Adverse Reactions a Irritability 1.2% Aggression 1.0% a At least 1% incidence of adverse reactions leading to premature discontinuation. In the randomized withdrawal study (Study B), the adverse reaction in patients randomized to placebo (n=160) and reported in at least 5% of patients and twice that of the full-dose memantine treatment group (n=157) was irritability (5.0% vs 2.5%).
Juvenile Animal Study In a juvenile animal study, male and female juvenile rats were administered memantine (15, 30, and 45 mg/kg/day) starting on postnatal day (PND) 14 through PND 70. Body weights were reduced at 45 mg/kg/day. Delays in sexual maturation were noted in male and female rats at doses ≥ 30 mg/kg/day.
Memantine induced neuronal lesions in several areas of the brain on PND 15 and 17 at doses ≥ 30 mg/kg/day. Behavioral toxicity (decrease percent of auditory startle habituation) was noted for animals in the 45 mg/kg/day dose group. The 15 mg/kg/day dose was considered the No-Observed-Adverse-Effect-Level (NOAEL) for this study.
In a second juvenile rat toxicity study, male and female juvenile rats were administered memantine (1, 3, 8, 15, 30, and 45 mg/kg/day) starting on postnatal day (PND) 7 through PND 70. Due to early memantine-related mortality, the 30 and 45 mg/kg/day dose groups were terminated without further evaluation. Memantine induced apoptosis or neuronal degeneration in several areas of the brain on PN… [Excerpted — this section continues on DailyMed.]
🆘 Overdosage ▾
10 OVERDOSAGE Signs and symptoms most often accompanying overdosage with other formulations of memantine in clinical trials and from worldwide marketing experience, alone or in combination with other drugs and/or alcohol, include agitation, asthenia, bradycardia, confusion, coma, dizziness, ECG changes, increased blood pressure, lethargy, loss of consciousness, psychosis, restlessness, slowed movement, somnolence, stupor, unsteady gait, visual hallucinations, vertigo, vomiting, and weakness. The largest known ingestion of memantine worldwide was 2 grams in a patient who took memantine in conjunction with unspecified antidiabetic medications.
This patient experienced coma, diplopia, and agitation, but subsequently recovered. One patient participating in a memantine hydrochloride extended-release capsules clinical trial unintentionally took 112 mg of memantine hydrochloride extended-release capsules daily for 31 days and experienced an elevated serum uric acid, elevated serum alkaline phosphatase, and low platelet count. Fatal outcome has been very rarely reported with memantine, and the relationship to memantine was unclear.
Because strategies for the management of overdose are continually evolving, it is advisable to contact a poison control center to determine the latest recommendations for the management of an overdose of any drug. As in any cases of overdose, general supportive measures should be utilized, and treatment should be symptomatic. Elimination of memantine can be enhanced by acidification of urine.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Persistent activation of central nervous system N-methyl-D-aspartate (NMDA) receptors by the excitatory amino acid glutamate has been hypothesized to contribute to the symptomatology of Alzheimer’s disease. Memantine is postulated to exert its therapeutic effect through its action as a low to moderate affinity uncompetitive (open-channel) NMDA receptor antagonist which binds preferentially to the NMDA receptor-operated cation channels. There is no evidence that memantine prevents or slows neurodegeneration in patients with Alzheimer’s disease.
12.2Pharmacodynamics Memantine showed low to negligible affinity for GABA, benzodiazepine, dopamine, adrenergic, histamine and glycine receptors and for voltage-dependent Ca 2+ , Na+, or K + channels. Memantine also showed antagonistic effects at the 5HT 3 receptor with a potency similar to that for the NMDA receptor and blocked nicotinic acetylcholine receptors with one-sixth to one-tenth the potency. In vitro studies have shown that memantine does not affect the reversible inhibition of acetylcholinesterase by donepezil, galantamine, or tacrine.
12.3Pharmacokinetics Memantine is well absorbed after oral administration and has linear pharmacokinetics over the therapeutic dose range. It is excreted predominantly unchanged in urine and has a terminal elimination half-life of about 60-80 hours. In a study comparing 28 mg once daily memantine hydrochloride extended-release capsules to 10 mg twice daily NAMENDA, the C max and AUC 0-24 values were 48% and 33% higher for the XR dosage regimen, respectively.
Absorption After multiple dose administration of memantine hydrochloride extended-release capsules, memantine peak concentrations occur around 9 to 12 hours post-dose. There is no difference in the absorption of memantine hydrochloride extended-release capsules when the capsule is taken intact or when the contents are sprinkled on applesauce. There is no difference in memantine exposure, based on C max or AUC, for memantine hydrochloride extended-release capsules whether that drug product is administered with food or on an empty stomach.
However, peak plasma concentrations are achieved about 18 hours after administration with food versus approximately 25 hours after administration on an empty stomach. Distribution The mean volume of distribution of memantine is 9 to 11 L/kg and the plasma protein binding is low (45%). Elimination Metabolism Memantine undergoes partial hepatic metabolism.
The hepatic microsomal CYP450 enzyme system does not play a significant role in the metabolism of memantine. Excretion Memantine is excreted predominantly unchanged in the urine and has a terminal elimination half-life of about 60 to 80 hours. About 48% of administered drug is excreted unchanged in urine; the remainder is converted primarily to three polar metabolites which possess minimal NMDA receptor antagonistic activity: the N-glucuronide conjugate, 6-hydroxy-memantine, and 1-nitroso-deaminated memantine.
A total of 74% of the administered dose is excreted as the sum of the parent drug and the N-glucuronide conjugate. Renal clearance involves active tubular secretion moderated by pH dependent tubular reabsorption. Specific Populations Elderly The pharmacokinetics of memantine in young and elderly subjects are similar.
Gender Following multiple dose administration of memantine hydrochloride 20 mg daily, females had about 45% higher exposure than males, but there was no difference in exposure when body weight was taken into account. Renal Impairment Memantine pharmacokinetics were evaluated following single oral administration of 20 mg memantine hydrochloride in 8 subjects with mild renal impairment (creatinine clearance, CLcr, > 50 to 80 mL/min), 8 subjects with moderate renal impairment (CLcr 30 to 49 mL/min), 7 subjects with severe renal impairment (CLcr 5 to 29 mL/min) and 8 healthy subjects (CLcr > 80 mL/min) matched as closely as possible by age,… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Persistent activation of central nervous system N-methyl-D-aspartate (NMDA) receptors by the excitatory amino acid glutamate has been hypothesized to contribute to the symptomatology of Alzheimer’s disease. Memantine is postulated to exert its therapeutic effect through its action as a low to moderate affinity uncompetitive (open-channel) NMDA receptor antagonist which binds preferentially to the NMDA receptor-operated cation channels. There is no evidence that memantine prevents or slows neurodegeneration in patients with Alzheimer’s disease.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Memantine hydrochloride extended-release capsules, 7 mg, are supplied as a two-piece hard gelatin capsule with standard yellow opaque cap and standard yellow opaque body filled with white to off-white pellets. Imprinted in black ink “AN” on the cap and imprinted in black ink “782” on the body. They are available as follows: Bottles of 30: NDC 65162-782-03 Bottles of 90: NDC 65162-782-09 Bottles of 500: NDC 65162-782-50 Memantine hydrochloride extended-release capsules, 14 mg, are supplied as a two-piece hard gelatin capsule with standard yellow opaque cap and dark green opaque body filled with white to off-white pellets.
Imprinted in black ink “AN” on the cap and imprinted in black ink “783”on the body. They are available as follows: Bottles of 30: NDC 65162-783-03 Bottles of 90: NDC 65162-783-09 Bottles of 500: NDC 65162-783-50 Memantine hydrochloride extended-release capsules, 21 mg, are supplied as a two-piece hard gelatin capsule with white opaque cap and dark green opaque body filled with white to off-white pellets. Imprinted in black ink “AN” on the cap and imprinted in black ink “784” on the body.
They are available as follows: Bottles of 30: NDC 65162-784-03 Bottles of 90: NDC 65162-784-09 Bottles of 500: NDC 65162-784-50 Memantine hydrochloride extended-release capsules, 28 mg, are supplied as a two-piece hard gelatin capsule with dark green opaque cap and dark green opaque body filled with white to off-white pellets. Imprinted in white ink “AN” on the cap and imprinted in white ink “785” on the body. They are available as follows: Bottles of 30: NDC 65162-785-03 Bottles of 90: NDC 65162-785-09 Bottles of 500: NDC 65162-785-50 Store at 20° to 25°C (68° to 77°F); excursions permitted between 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Memantine hydrochloride extended-release capsules are an orally active NMDA receptor antagonist. The chemical name for memantine hydrochloride, USP is 1-amino-3,5-dimethyladamantane hydrochloride with the following structural formula: The molecular formula is C 12 H 21 N•HCl and the molecular weight is 215.76. Memantine hydrochloride, USP occurs as a fine white to off-white powder and is soluble in water.
Memantine hydrochloride extended-release capsules are supplied for oral administration as 7 mg, 14 mg, 21 mg, and 28 mg capsules. Each capsule contains extended-release beads with the labeled amount of memantine hydrochloride, USP and the following inactive ingredients: colloidal silicon dioxide, ethylcellulose, hypromellose, sugar spheres (sucrose, corn starch), talc, and triethyl citrate in hard gelatin capsules. Each capsule shell contains the following inactive ingredients: D&C Yellow No.
10, gelatin, iron oxide yellow and titanium dioxide. The 14 mg, 21 mg and 28 mg capsule shells also contain FD&C Blue No. 1.
The 7 mg, 14 mg and 21 mg imprinting ink contains the following inactive ingredients: D&C Yellow No. 10, FD&C Blue No. 1, FD&C Blue No.
2, FD&C Red No. 40, iron oxide black, N-butyl alcohol, propylene glycol and shellac glaze. The 28 mg imprinting ink contains the following inactive ingredients: ammonium hydroxide, isopropyl alcohol, N-butyl alcohol, propylene glycol, simethicone, shellac glaze and titanium dioxide.
Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information ). To assure safe and effective use of memantine hydrochloride extended-release capsules, the information and instructions provided in the patient information section should be discussed with patients and caregivers. Instruct patients and caregivers to take memantine hydrochloride extended-release capsules only once per day, as prescribed.
Instruct patients and caregivers that memantine hydrochloride extended-release capsules be swallowed whole. Alternatively, memantine hydrochloride extended-release capsules may be opened and sprinkled on applesauce and the entire contents should be consumed. The capsules should not be divided, chewed or crushed.
Warn patients not to use any capsules of memantine hydrochloride extended-release capsules that are damaged or show signs of tampering. If a patient misses a single dose of memantine hydrochloride extended-release capsules, that patient should not double up on the next dose. The next dose should be taken as scheduled.
If a patient fails to take memantine hydrochloride extended-release capsules for several days, dosing should not be resumed without consulting that patient’s healthcare professional. Advise patients and caregivers that memantine hydrochloride extended-release capsules may cause headache, diarrhea, and dizziness. *Brands listed are the trademarks of their respective owners. Distributed by: Amneal Pharmaceuticals LLC Bridgewater, NJ 08807 Rev.
04-2025-05
🍼 Nursing Mothers ▾
8.2Lactation Risk Summary There are no data on the presence of memantine in human milk, the effects on the breastfed infant, or the effects of memantine hydrochloride extended-release capsules on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for memantine hydrochloride extended-release capsules and any potential adverse effects on the breastfed infant from memantine hydrochloride extended-release capsules or from the underlying maternal condition.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Memantine is well absorbed after oral administration and has linear pharmacokinetics over the therapeutic dose range. It is excreted predominantly unchanged in urine and has a terminal elimination half-life of about 60-80 hours. In a study comparing 28 mg once daily memantine hydrochloride extended-release capsules to 10 mg twice daily NAMENDA, the C max and AUC 0-24 values were 48% and 33% higher for the XR dosage regimen, respectively.
Absorption After multiple dose administration of memantine hydrochloride extended-release capsules, memantine peak concentrations occur around 9 to 12 hours post-dose. There is no difference in the absorption of memantine hydrochloride extended-release capsules when the capsule is taken intact or when the contents are sprinkled on applesauce. There is no difference in memantine exposure, based on C max or AUC, for memantine hydrochloride extended-release capsules whether that drug product is administered with food or on an empty stomach.
However, peak plasma concentrations are achieved about 18 hours after administration with food versus approximately 25 hours after administration on an empty stomach. Distribution The mean volume of distribution of memantine is 9 to 11 L/kg and the plasma protein binding is low (45%). Elimination Metabolism Memantine undergoes partial hepatic metabolism.
The hepatic microsomal CYP450 enzyme system does not play a significant role in the metabolism of memantine. Excretion Memantine is excreted predominantly unchanged in the urine and has a terminal elimination half-life of about 60 to 80 hours. About 48% of administered drug is excreted unchanged in urine; the remainder is converted primarily to three polar metabolites which possess minimal NMDA receptor antagonistic activity: the N-glucuronide conjugate, 6-hydroxy-memantine, and 1-nitroso-deaminated memantine.
A total of 74% of the administered dose is excreted as the sum of the parent drug and the N-glucuronide conjugate. Renal clearance involves active tubular secretion moderated by pH dependent tubular reabsorption. Specific Populations Elderly The pharmacokinetics of memantine in young and elderly subjects are similar.
Gender Following multiple dose administration of memantine hydrochloride 20 mg daily, females had about 45% higher exposure than males, but there was no difference in exposure when body weight was taken into account. Renal Impairment Memantine pharmacokinetics were evaluated following single oral administration of 20 mg memantine hydrochloride in 8 subjects with mild renal impairment (creatinine clearance, CLcr, > 50 to 80 mL/min), 8 subjects with moderate renal impairment (CLcr 30 to 49 mL/min), 7 subjects with severe renal impairment (CLcr 5 to 29 mL/min) and 8 healthy subjects (CLcr > 80 mL/min) matched as closely as possible by age, weight and gender to the subjects with renal impairment.
Mean AUC 0-∞ increased by 4%, 60%, and 115% in subjects with mild, moderate, and severe renal impairment, respectively, compared to healthy subjects. The terminal elimination half-life increased by 18%, 41%, and 95% in subjects with mild, moderate, and severe renal impairment, respectively, compared to healthy subjects. Hepatic Impairment Memantine pharmacokinetics were evaluated following the administration of single oral doses of 20 mg in 8 subjects with moderate hepatic impairment (Child-Pugh Class B, score 7-9) and 8 subjects who were age-, gender-, and weight-matched to the hepatically-impaired subjects.
There was no change in memantine exposure (based on C max and AUC) in subjects with moderate hepatic impairment as compared with healthy subjects. However, terminal elimination half-life increased by about 16% in subjects with moderate hepatic impairment as compared with healthy subjects. Drug-Drug Interactions Use with Cholinesterase Inhibitors Co-administration of memantine with the AChE inhibitor donepezil did not affect the pharmacokinetics of either compound.
Furthermore,… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Memantine showed low to negligible affinity for GABA, benzodiazepine, dopamine, adrenergic, histamine and glycine receptors and for voltage-dependent Ca 2+ , Na+, or K + channels. Memantine also showed antagonistic effects at the 5HT 3 receptor with a potency similar to that for the NMDA receptor and blocked nicotinic acetylcholine receptors with one-sixth to one-tenth the potency. In vitro studies have shown that memantine does not affect the reversible inhibition of acetylcholinesterase by donepezil, galantamine, or tacrine.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The effectiveness of memantine hydrochloride extended-release capsules as a treatment for patients with moderate to severe Alzheimer’s disease was based on the results of a double-blind, placebo-controlled trial. 24-week Study of Memantine Hydrochloride Extended-release Capsules This was a randomized double-blind clinical investigation in outpatients with moderate to severe Alzheimer’s disease (diagnosed by DSM-IV criteria and NINCDS-ADRDA criteria for AD with a Mini Mental State Examination (MMSE) score ≥ 3 and ≤ 14 at Screening and Baseline) receiving acetylcholinesterase inhibitor (AChEI) therapy at a stable dose for 3 months prior to screening.
The mean age of patients participating in this trial was 76.5 years with a range of 49-97 years. Approximately 72% of patients were female and 94% were Caucasian. Study Outcome Measures The effectiveness of memantine hydrochloride extended-release capsules was evaluated in this study using the co-primary efficacy parameters of Severe Impairment Battery (SIB) and the Clinician’s Interview-Based Impression of Change (CIBIC-Plus).
The ability of memantine hydrochloride extended-release capsules to improve cognitive performance was assessed with the Severe Impairment Battery (SIB), a multi-item instrument that has been validated for the evaluation of cognitive function in patients with moderate to severe dementia. The SIB examines selected aspects of cognitive performance, including elements of attention, orientation, language, memory, visuospatial ability, construction, praxis, and social interaction. The SIB scoring range is from 0 to 100, with lower scores indicating greater cognitive impairment.
The ability of memantine hydrochloride extended-release capsules to produce an overall clinical effect was assessed using a Clinician’s Interview Based Impression of Change that required the use of caregiver information, the CIBIC-Plus. The CIBIC-Plus is not a single instrument and is not a standardized instrument like the ADCS-ADL or SIB. Clinical trials for investigational drugs have used a variety of CIBIC formats, each different in terms of depth and structure.
As such, results from a CIBIC-Plus reflect clinical experience from the trial or trials in which it was used and cannot be compared directly with the results of CIBIC-Plus evaluations from other clinical trials. The CIBIC-Plus used in this trial was a structured instrument based on a comprehensive evaluation at baseline and subsequent time-points of four domains: general (overall clinical status), functional (including activities of daily living), cognitive, and behavioral. It represents the assessment of a skilled clinician using validated scales based on his/her observation during an interview with the patient, in combination with information supplied by a caregiver familiar with the behavior of the patient over the interval rated.
The CIBIC-Plus is scored as a seven point categorical rating, ranging from a score of 1, indicating “marked improvement” to a score of 4, indicating “no change” to a score of 7, indicating “marked worsening.” The CIBIC-Plus has not been systematically compared directly to assessments not using information from caregivers (CIBIC) or other global methods. Study Results In this study, 677 patients were randomized to one of the following 2 treatments: Memantine hydrochloride extended-release capsules 28 mg/day or placebo while still receiving an AChEI (either donepezil, galantamine, or rivastigmine).
Effects on Severe Impairment Battery (SIB) Figure 1 shows the time course for the change from baseline in SIB score for the two treatment groups completing the 24 weeks of the study. At 24 weeks of treatment, the mean difference in the SIB change scores for the memantine hydrochloride extended-release capsules 28 mg/AChEI-treated (combination therapy) patients compared to the patients on placebo/AChEI (monotherapy) was 2.6 units. Using an LOCF analysis, memantine hydrochloride extended-rel… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis There was no evidence of carcinogenicity in a 113-week oral study in mice at doses up to 40 mg/kg/day (7 times the maximum recommended human dose [MRHD] on a mg/m 2 basis). There was also no evidence of carcinogenicity in rats orally dosed at up to 40 mg/kg/day for 71 weeks followed by 20 mg/kg/day (14 and 7 times the MRHD on a mg/m 2 basis, respectively) through 128 weeks. Mutagenesis Memantine produced no evidence of genotoxic potential when evaluated in the in vitro S. typhimurium or E. coli reverse mutation assay, an in vitro chromosomal aberration test in human lymphocytes, an in vivo cytogenetics assay for chromosome damage in rats, and the in vivo mouse micronucleus assay.
The results were equivocal in an in vitro gene mutation assay using Chinese hamster V79 cells. Impairment of Fertility No impairment of fertility or reproductive performance was seen in rats administered up to 18 mg/kg/day (6 times the MRHD on a mg/m 2 basis) orally from 14 days prior to mating through gestation and lactation in females, or for 60 days prior to mating in males.
13.2Animal Toxicology and/or Pharmacology Memantine induced neuronal lesions (vacuolation and necrosis) in the multipolar and pyramidal cells in cortical layers III and IV of the posterior cingulate and retrosplenial neocortices in rats, similar to those which are known to occur in rodents administered other NMDA receptor antagonists. Lesions were seen after a single dose of memantine. In a study in which rats were given daily oral doses of memantine for 14 days, the no-effect dose for neuronal necrosis was 4 times the maximum recommended human dose (MRHD of 28 mg/day) on a mg/m 2 basis.
In acute and repeat-dose neurotoxicity studies in female rats, oral administration of memantine and donepezil in combination resulted in increased incidence, severity, and distribution of neurodegeneration compared with memantine alone. The no-effect levels of the combination were associated with clinically relevant plasma memantine and donepezil exposures. The relevance of these findings to humans is unknown.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis There was no evidence of carcinogenicity in a 113-week oral study in mice at doses up to 40 mg/kg/day (7 times the maximum recommended human dose [MRHD] on a mg/m 2 basis). There was also no evidence of carcinogenicity in rats orally dosed at up to 40 mg/kg/day for 71 weeks followed by 20 mg/kg/day (14 and 7 times the MRHD on a mg/m 2 basis, respectively) through 128 weeks. Mutagenesis Memantine produced no evidence of genotoxic potential when evaluated in the in vitro S. typhimurium or E. coli reverse mutation assay, an in vitro chromosomal aberration test in human lymphocytes, an in vivo cytogenetics assay for chromosome damage in rats, and the in vivo mouse micronucleus assay.
The results were equivocal in an in vitro gene mutation assay using Chinese hamster V79 cells. Impairment of Fertility No impairment of fertility or reproductive performance was seen in rats administered up to 18 mg/kg/day (6 times the MRHD on a mg/m 2 basis) orally from 14 days prior to mating through gestation and lactation in females, or for 60 days prior to mating in males.
📄 Patient Package Insert ▾
Patient Information Memantine Hydrochloride (mem’ an teen hye” droe klor’ ide) Extended-release Capsules Read this Patient Information that comes with memantine hydrochloride extended-release capsules before you start taking it and each time you get a refill. There may be new information. This information does not take the place of talking to your doctor about your medical condition or your treatment.
What are memantine hydrochloride extended-release capsules? Memantine hydrochloride extended-release capsules are a prescription medicine used for the treatment of moderate to severe dementia in people with Alzheimer’s disease. Memantine hydrochloride extended-release capsules belong to a class of medicines called N-methyl-D-aspartate (NMDA) inhibitors.
It is not known if memantine hydrochloride extended-release capsules are safe and effective in children. Who should not take memantine hydrochloride extended-release capsules? Do not take memantine hydrochloride extended-release capsules if you are allergic to memantine or any of the other ingredients in memantine hydrochloride extended-release capsules.
See the end of this leaflet for a complete list of ingredients in memantine hydrochloride extended-release capsules. What should I tell my doctor before taking memantine hydrochloride extended-release capsules? Before you take memantine hydrochloride extended-release capsules, tell your doctor if you: have or have had seizures have or have had problems passing urine have or have had bladder or kidney problems have liver problems have any other medical conditions are pregnant or plan to become pregnant.
It is not known if memantine hydrochloride extended-release capsules will harm your unborn baby. are breastfeeding or plan to breastfeed. It is not known if memantine hydrochloride passes into your breast milk. Talk to your doctor about the best way to feed your baby if you take memantine hydrochloride extended-release capsules.
Tell your doctor about all the medicines you take, including prescription and non-prescription medicines, vitamins, and herbal supplements. Taking memantine hydrochloride extended-release capsules with certain other medicines may affect each other. Taking memantine hydrochloride extended-release capsules with other medicines can cause serious side effects.
Especially tell your doctor if you take: other NMDA antagonists such as amantadine, ketamine, and dextromethorphan medicines that make your urine alkaline such as carbonic anhydrase inhibitors and sodium bicarbonate Ask your doctor or pharmacist for a list of these medicines, if you are not sure. Know the medicines you take. Keep a list of them to show your doctor and pharmacist when you get a new medicine.
How should I take memantine hydrochloride extended-release capsules? Your doctor will tell you how much memantine hydrochloride extended-release capsules to take and when to take it. Your doctor may change your dose if needed.
Memantine hydrochloride extended-release capsules may be taken with food or without food. Memantine hydrochloride extended-release capsules may be opened and sprinkled on applesauce before swallowing, but the contents of the entire capsule should be taken and the dose should not be divided. Except when opened and sprinkled on applesauce, memantine hydrochloride extended-release capsules must be swallowed whole and never crushed, divided or chewed.
Do not use any capsules of memantine hydrochloride extended-release capsules that are damaged or show signs of tampering. If you are currently taking another formulation of memantine, talk to your healthcare professional about how to switch to memantine hydrochloride extended-release capsules. If you forget to take one dose of memantine hydrochloride extended-release capsules, do not double up on the next dose.
You should take only the next dose as scheduled. If you have forgotten to take memantine hydrochloride extended-release capsules for several days, you should not take the next dos… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL 7mg-90ct label
14mg-90ct label
21mg-90ct label
28mg-90ct label