
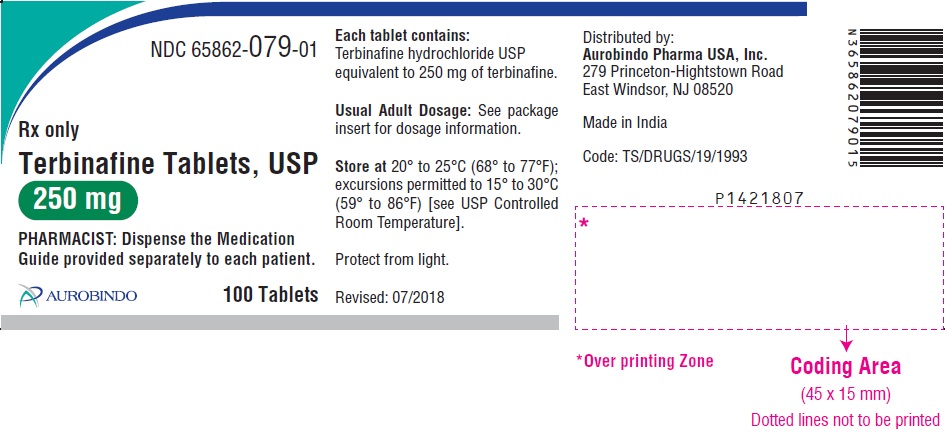
Terbinafine Hydrochloride 250 mg Tablet, 30-count
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- That's one of the most common questions I get with this medication. The tablets clear the fungus, but your nail has to physically grow out before it looks healthy — and that can ta...
- How long will it take for my nail to look normal after I finish the tablets?
- Yes — and the big one is your liver. If you notice yellowing of your skin or eyes, dark urine, pale-colored stools, or you feel unusually tired and nauseous, stop the tablets and c...
- Are there any side effects I should actually call my doctor about?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII R75537T0T4
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. It serves as a binder that holds tablet ingredients together, a film-coating for pills, and a viscosity controller in liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.136 | $4.07 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.4048 | $12.14 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.3660 | $10.98 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Terbinafine 250 mg 16714-0795-01 | NorthStar | 30 tablets | $0.136 | AB | Availability likely | — |
| Terbinafine Hydrochloride 250 mg 51991-0526-01 | Breckenridge | 100 tablets | $0.136 | — | Availability likely | — |
| Terbinafine 250 mg 60687-0909-21 | American | 30 tablets | $0.136 | AB | Availability likely | — |
| Terbinafine 250 mg 62135-0572-30 | Chartwell | 30 tablets | $0.136 | AB | Availability likely | — |
| Terbinafine Hydrochloride 250 mgthis 65862-0079-30 | Aurobindo | 30 tablets | $0.136 | — | Availability likely | — |
| Terbinafine 250 mg 69097-0859-02 | Cipla | 30 tablets | $0.136 | — | Availability likely | — |
| Terbinafine Hydrochloride 250 mg 69292-0225-01 | Amici | 100 tablets | $0.136 | AB | Availability likely | — |
| terbinafine hydrochloride 250 mg 69452-0351-13 | Bionpharma | 30 tablets | $0.136 | AB | Availability likely | — |
| Terbinafine Hydrochloride 250 mg 69097-0731-02 | Cipla | 30 tablets | $0.154 | AB | FDA listed | +14% |
| Terbinafine Hydrochloride 250 mg 43063-0906-20 | PD-Rx | 20 tablets | — | — | FDA listed | — |
| Terbinafine Hydrochloride 250 mg 43353-0893-16 | Aphena | 6000 tablets | — | — | FDA listed | — |
| Terbinafine Hydrochloride 250 mg 50090-1048-00 | A-S | 30 tablets | — | — | FDA listed | — |
| Terbinafine 250 mg 50090-3575-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Terbinafine 250 mg 50090-3654-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| terbinafine hydrochloride 250 mg 50090-7300-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Terbinafine Hydrochloride 250 mg 51407-0995-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Terbinafine Hydrochloride 250 mg 51655-0364-26 | Northwind | 90 tablets | — | — | FDA listed | — |
| Terbinafine Hydrochloride 250 mg 55111-0250-01 | Dr.Reddys | 100 tablets | — | AB | FDA listed | — |
| Terbinafine Hydrochloride 250 mg 60429-0222-30 | Golden | 30 tablets | — | — | FDA listed | — |
| Terbinafine Hydrochloride 250 mg 63629-1993-01 | Bryant | 100 tablets | — | — | Discontinued | — |
| Terbinafine Hydrochloride 250 mg 68071-1640-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Terbinafine Hydrochloride 250 mg 68071-2381-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Terbinafine Hydrochloride 250 mg 68071-4500-01 | NuCare | 100 tablets | — | — | FDA listed | — |
| Terbinafine 250 mg 68071-4873-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Terbinafine 250 mg 68788-7450-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Terbinafine 250 mg 70518-2941-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| terbinafine hydrochloride 250 mg 70518-3907-00 | REMEDYREPACK | 90 tablets | — | AB | Discontinued | — |
| Terbinafine 250 mg 70518-4323-00 | REMEDYREPACK | 30 tablets | — | — | FDA listed | — |
| Terbinafine 250 mg 70518-4421-00 | REMEDYREPACK | 90 tablets | — | — | FDA listed | — |
| Terbinafine 250 mg 71205-0061-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Terbinafine Hydrochloride 250 mg 71205-0127-14 | Proficient | 14 tablets | — | — | FDA listed | — |
| Terbinafine 250 1 71205-0152-15 | Proficient | 15 tablets | — | — | FDA listed | — |
| Terbinafine 250 mg 71205-0492-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Terbinafine Hydrochloride 250 mg 71335-0918-01 | Bryant | 30 tablets | — | — | FDA listed | — |
| Terbinafine 250 mg 71335-1124-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| terbinafine hydrochloride 250 mg 71335-9677-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Terbinafine Hydrochloride 250 mg 72162-1595-01 | Bryant | 100 tablets | — | — | FDA listed | — |
| Terbinafine 250 mg 72162-2539-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Terbinafine 250 mg 72189-0243-30 | direct | 30 tablets | — | AB | FDA listed | — |
| Terbinafine 250 mg 72789-0394-42 | PD-Rx | 42 tablets | — | AB | FDA listed | — |
| Terbinafine 250 mg 76282-0209-01 | Exelan | 100 tablets | — | — | FDA listed | — |
| terbinafine hydrochloride 250 mg 82804-0220-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Terbinafine Hydrochloride 250 mg 45201-0526-00 | Laboratorios | 26600 tablets | — | — | FDA listed | — |
| Terbinafine Hydrochloride 250 mg 51991-0001-00 | Breckenridge | 26600 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 65862-0079-01 | 100 TABLET in 1 BOTTLE (65862-079-01) | — | — | 2007-07-02 | Active |
| 65862-0079-30 You're viewing this | 30 TABLET in 1 BOTTLE (65862-079-30) | $0.1356 / ea | $4.07 | 2007-07-02 | Active |
| 65862-0079-99 | 1000 TABLET in 1 BOTTLE (65862-079-99) | — | — | 2007-07-02 | Active |
| 65862-0079-39 | 3000 TABLET in 1 BAG (65862-079-39) | — | — | — | Active |
You're viewing the smallest of 4 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 65862-0079-30?
What is the difference between NDC 65862-0079-30 and NDC 65862-0079-01?
What NDC number is used to bill for this package of Terbinafine Hydrochloride 250 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What "drug for further processing" means
FDA lists this package under the "drug for further processing" marketing category: Aurobindo Pharma Limited supplies it to other companies for further processing or repackaging (blister cards that are later repackaged or co-packaged are a common example). The units themselves are a finished dosage form — which is why pricing or Medicaid data can still appear — but this exact package code may not be the presentation a retail pharmacy dispenses.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Is this NDC FDA-approved?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Where does this data come from?
📄 Full FDA label FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Terbinafine tablets are indicated for the treatment of onychomycosis of the toenail or fingernail due to dermatophytes (tinea unguium). Prior to initiating treatment, appropriate nail specimens for laboratory testing [potassium hydroxide (KOH) preparation, fungal culture, or nail biopsy] should be obtained to confirm the diagnosis of onychomycosis. Terbinafine tablets are an allylamine antifungal indicated for the treatment of onychomycosis of the toenail or fingernail due to dermatophytes (tinea unguium).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Prior to administering, evaluate patients for evidence of chronic or active liver disease. (2.1) Fingernail onychomycosis: One tablet, once daily for 6 weeks. (2.2) Toenail onychomycosis: One tablet, once daily for 12 weeks. (2.2)
2.1Assessment Prior to Initiation Before administering terbinafine tablets, evaluate patients for evidence of chronic or active liver disease [see Contraindications (4) and Warnings and Precautions (5.1) ].
2.2Dosage Fingernail onychomycosis: One 250 mg tablet once daily for 6 weeks. Toenail onychomycosis: One 250 mg tablet once daily for 12 weeks. The optimal clinical effect is seen some months after mycological cure and cessation of treatment. This is related to the period required for outgrowth of healthy nail.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablet, 250 mg white to off-white, round uncoated, biconvex beveled edge tablets having ‘D’ debossed on one side and ‘74’ on the other side. Tablet, 250 mg
⛔ Contraindications ▾
4 CONTRAINDICATIONS Terbinafine tablets are contraindicated in patients with: Chronic or active liver disease [see Warnings and Precautions (5.1) ] History of allergic reaction to oral terbinafine because of the risk of anaphylaxis [see Adverse Reactions (6.2) ] Chronic or active liver disease. (4) History of allergic reaction to oral terbinafine because of the risk of anaphylaxis. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Liver failure, sometimes leading to liver transplant or death, has occurred with the use of oral terbinafine. Obtain pretreatment serum transaminases. Prior to initiating treatment and periodically during therapy, assess liver function tests.
Discontinue terbinafine tablets if liver injury develops. (5.1) Taste disturbance, including taste loss, has been reported with the use of terbinafine tablets. Taste disturbance can be severe, may be prolonged, or may be permanent.
Discontinue terbinafine tablets if taste disturbance occurs. (5.2) Smell disturbance, including loss of smell, has been reported with the use of terbinafine tablets. Smell disturbance may be prolonged, or may be permanent.
Discontinue terbinafine tablets if smell disturbance occurs. (5.3) Depressive symptoms have been reported with terbinafine use. Prescribers should be alert to the development of depressive symptoms.
(5.4) Severe neutropenia has been reported. If the neutrophil count is less than or equal to 1000 cells/mm 3 , terbinafine tablets should be discontinued. (5.5) Stevens-Johnson syndrome, toxic epidermal necrolysis, erythema multiforme, exfoliative dermatitis, bullous dermatitis, and drug reaction with eosinophilia and systemic symptoms (DRESS) syndrome have been reported with oral terbinafine use.
If signs or symptoms of drug reaction occur, treatment with terbinafine tablets should be discontinued. (5.6)
5.1Hepatotoxicity Terbinafine tablets are contraindicated for patients with chronic or active liver disease. Before prescribing terbinafine tablets, perform liver function tests because hepatotoxicity may occur in patients with and without preexisting liver disease. Cases of liver failure, some leading to liver transplant or death, have occurred with the use of terbinafine tablets in individuals with and without preexisting liver disease.
In the majority of liver cases reported in association with use of terbinafine tablets, the patients had serious underlying systemic conditions. The severity of hepatic events and/or their outcome may be worse in patients with active or chronic liver disease. Periodic monitoring of liver function tests is recommended.
Discontinue terbinafine tablets if biochemical or clinical evidence of liver injury develops. Warn patients prescribed terbinafine tablets and/or their caregivers to report immediately to their healthcare providers any symptoms or signs of persistent nausea, anorexia, fatigue, vomiting, right upper abdominal pain or jaundice, dark urine, or pale stools. Advise patients with these symptoms to discontinue taking oral terbinafine, and immediately evaluate the patient’s liver function.
5.2Taste Disturbance Including Loss of Taste Taste disturbance, including taste loss, has been reported with the use of terbinafine tablets. It can be severe enough to result in decreased food intake, weight loss, anxiety, and depressive symptoms. Taste disturbance may resolve within several weeks after discontinuation of treatment, but may be prolonged (greater than 1 year), or may be permanent.
If symptoms of a taste disturbance occur, terbinafine tablets should be discontinued.
5.3Smell Disturbance Including Loss of Smell Smell disturbance, including loss of smell, has been reported with the use of terbinafine tablets. Smell disturbance may resolve after discontinuation of treatment, but may be prolonged (greater than 1 year), or may be permanent. If symptoms of a smell disturbance occur, terbinafine tablets should be discontinued.
5.4Depressive Symptoms Depressive symptoms have occurred during postmarketing use of terbinafine tablets. Prescribers should be alert to the development of depressive symptoms, and patients should be instructed to report depressive symptoms to their physician.
5.5Hematologic Effects Transient decreases in absolute lymphocyte counts (ALCs) have been observed in controlled clinical trials. In placebo-controlled trials, 8/465 subjects receiving terbinafine table…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Common (greater than 2% of patients treated with terbinafine tablets) reported adverse events include headache, diarrhea, rash, dyspepsia, liver enzyme abnormalities, pruritus, taste disturbance, nausea, abdominal pain, and flatulence. (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The most frequently reported adverse events observed in the 3 U.S./Canadian placebo-controlled trials are listed in the Table 1. The adverse events reported encompass gastrointestinal symptoms (including diarrhea, dyspepsia, and abdominal pain), liver test abnormalities, rashes, urticaria, pruritus, and taste disturbances.
Changes in the ocular lens and retina have been reported following the use of terbinafine tablets in controlled trials. The clinical significance of these changes is unknown. In general, the adverse events were mild, transient, and did not lead to discontinuation from study participation.
Table 1. Most frequently reported adverse events observed in the 3 U.S./Canadian placebo-controlled trials Adverse Event Discontinuation Terbinafine Tablets (%) n=465 Placebo (%) n=137 Terbinafine Tablets (%) n=465 Placebo (%) n=137 * Liver enzyme abnormalities greater than or equal to 2 times the upper limit of normal range. Headache 12.9 9.5 0.2 0 Gastrointestinal Symptoms: Diarrhea Dyspepsia Abdominal Pain Nausea Flatulence 5.6 4.3 2.4 2.6 2.2 2.9 2.9 1.5 2.9 2.2 0.6 0.4 0.4 0.2 0 0 0 0 0 0 Dermatological Symptoms: Rash Pruritus Urticaria 5.6 2.8 1.1 2.2 1.5 0 0.9 0.2 0 0.7 0 0 Liver Enzyme Abnormalities* 3.3 1.4 0.2 0 Taste Disturbance 2.8 0.7 0.2 0 Visual Disturbance 1.1 1.5 0.9 0
6.2Postmarketing Experience The following adverse events have been identified during post-approval use of terbinafine tablets. Because these events are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Blood and lymphatic system disorders: Pancytopenia, agranulocytosis, severe neutropenia, thrombocytopenia, anemia, thrombotic microangiopathy (TMA), including thrombotic thrombocytopenic purpura and hemolytic uremic syndrome [see Warnings and Precautions (5.5 , 5.8) ] Immune system disorders: Serious hypersensitivity reactions e.g., angioedema and allergic reactions (including anaphylaxis), precipitation and exacerbation of cutaneous and systemic lupus erythematosus [see Warnings and Precautions (5.7) ], serum sickness-like reaction Psychiatric disorders: Anxiety and depressive symptoms independent of taste disturbance have been reported with use of terbinafine tablets.
In some cases, depressive symptoms have been reported to subside with discontinuance of therapy and to recur with reinstitution of therapy [see Warnings and Precautions (5.4) ] . Nervous system disorders: Cases of taste disturbance, including taste loss, have been reported with the use of terbinafine tablets. It can be severe enough to result in decreased food intake, weight loss, anxiety, and depressive symptoms.
Cases of smell disturbance, including smell loss, have been reported with the use of terbinafine tablets [see Warnings and Precautions (5.2 , 5.3) ] . Cases of paresthesia and hypoesthesia have been reported with the use of terbinafine tablets. Eye disorders: Visual field defects, reduced visual acuity Ear and labyrinth disorders: Hearing impairment, vertigo, tinnitus Vascular disorders: Vasculitis Gastrointestinal disorders: Pancreatitis, vomiting Hepatobiliary disorders: Cases of liver failure some leading to liver transplant or death [see Warnings and Precautions (5.…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Terbinafine is an inhibitor of CYP450 2D6 isozyme and has an effect on metabolism of desipramine. Drug interactions have also been noted with cimetidine, fluconazole, cyclosporine, rifampin, and caffeine. (7.1)
7.1Drug-Drug Interactions In vivo studies have shown that terbinafine is an inhibitor of the CYP450 2D6 isozyme. Drugs predominantly metabolized by the CYP450 2D6 isozyme include the following drug classes: tricyclic antidepressants, selective serotonin reuptake inhibitors, beta-blockers, antiarrhythmics class 1C (e.g., flecainide and propafenone) and monoamine oxidase inhibitors Type B. Coadministration of terbinafine tablets should be done with careful monitoring and may require a reduction in dose of the 2D6-metabolized drug.
In a study to assess the effects of terbinafine on desipramine in healthy volunteers characterized as normal metabolizers, the administration of terbinafine resulted in a 2-fold increase in C max and a 5-fold increase in area under the curve (AUC). In this study, these effects were shown to persist at the last observation at 4 weeks after discontinuation of terbinafine tablets. In studies in healthy subjects characterized as extensive metabolizers of dextromethorphan (antitussive drug and CYP2D6 probe substrate), terbinafine increases the dextromethorphan/dextrorphan metabolite ratio in urine by 16- to 97-fold on average.
Thus, terbinafine may convert extensive CYP2D6 metabolizers to poor metabolizer status. In vitro studies with human liver microsomes showed that terbinafine does not inhibit the metabolism of tolbutamide, ethinylestradiol, ethoxycoumarin, cyclosporine, cisapride and fluvastatin. In vivo drug-drug interaction studies conducted in healthy volunteer subjects showed that terbinafine does not affect the clearance of antipyrine or digoxin.
Terbinafine decreases the clearance of caffeine by 19%. Terbinafine increases the clearance of cyclosporine by 15%. The influence of terbinafine on the pharmacokinetics of fluconazole, cotrimoxazole (trimethoprim and sulfamethoxazole), zidovudine or theophylline was not considered to be clinically significant.
Coadministration of a single dose of fluconazole (100 mg) with a single dose of terbinafine resulted in a 52% and 69% increase in terbinafine C max and AUC, respectively. Fluconazole is an inhibitor of CYP2C9 and CYP3A enzymes. Based on this finding, it is likely that other inhibitors of both CYP2C9 and CYP3A4 (e.g., ketoconazole, amiodarone) may also lead to a substantial increase in the systemic exposure (C max and AUC) of terbinafine when concomitantly administered.
There have been spontaneous reports of increase or decrease in prothrombin times in patients concomitantly taking oral terbinafine and warfarin, however, a causal relationship between terbinafine tablets and these changes has not been established. Terbinafine clearance is increased 100% by rifampin, a CYP450 enzyme inducer, and decreased 33% by cimetidine, a CYP450 enzyme inhibitor. Terbinafine clearance is unaffected by cyclosporine.
There is no information available from adequate drug-drug interaction studies with the following classes of drugs: oral contraceptives, hormone replacement therapies, hypoglycemics, phenytoins, thiazide diuretics, and calcium channel blockers.
7.2Food Interactions An evaluation of the effect of food on terbinafine tablets was conducted. An increase of less than 20% of the AUC of terbinafine was observed when terbinafine tablets were administered with food. Terbinafine tablets can be taken with or without food.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Available data from postmarketing cases on the use of terbinafine tablets in pregnant women are insufficient to evaluate a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, terbinafine did not cause malformations or any harm to the fetus when administered to pregnant rabbits and rats during the period of organogenesis at oral doses up to 12 and 23 times the maximum recommended human dose (MRHD) of 250 mg/day, respectively (see data) .
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The background risk of major birth defects and miscarriage for the indicated population is unknown; however, in the U.S. general population, the estimated background risk of major birth defects is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies. Data Animal Data In embryo-fetal development studies in rats and rabbits, pregnant animals received orally (by gavage) doses of terbinafine up to 300 mg/kg/day, during the period of organogenesis.
There were no maternal or embryo-fetal effects in either species up to the maximum dose tested. The 300 mg/kg/day dose level in rats and rabbits corresponds to 23 and 12 times the MRHD [based on body surface area (BSA) comparisons], respectively. In a rat peri- and postnatal development study, terbinafine doses of up to 300 mg/kg/day (12 times the MRHD based on BSA comparisons) given by oral gavage during late pregnancy and lactation (Day 15 of gestation to day 20 post-partum) had no adverse effects on parturition and lactation.
8.2Lactation Risk Summary After oral administration, terbinafine is present in human milk. However, there are no data on the effects on the breastfed child or on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for terbinafine tablets and any potential adverse effects on the breastfed child from terbinafine tablets or from the underlying maternal condition.
8.4Pediatric Use The safety and efficacy of terbinafine tablets have not been established in pediatric patients with onychomycosis.
8.5Geriatric Use Clinical studies of terbinafine tablets did not include sufficient numbers of subjects aged 65 years and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
8.6Renal Impairment In patients with renal impairment (creatinine clearance less than or equal to 50 mL/min), the use of terbinafine tablets has not been adequately studied.
8.7Hepatic Impairment Terbinafine tablets are contraindicated for patients with chronic or active liver disease [see Contraindications (4) and Warnings and Precautions (5.1) ] . Cases of liver failure, some leading to liver transplant or death, have occurred with the use of terbinafine tablets in individuals with and without preexisting liver disease. The severity of hepatic events and/or their outcome may be worse in patients with active or chronic liver disease.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from postmarketing cases on the use of terbinafine tablets in pregnant women are insufficient to evaluate a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, terbinafine did not cause malformations or any harm to the fetus when administered to pregnant rabbits and rats during the period of organogenesis at oral doses up to 12 and 23 times the maximum recommended human dose (MRHD) of 250 mg/day, respectively (see data) .
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The background risk of major birth defects and miscarriage for the indicated population is unknown; however, in the U.S. general population, the estimated background risk of major birth defects is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies. Data Animal Data In embryo-fetal development studies in rats and rabbits, pregnant animals received orally (by gavage) doses of terbinafine up to 300 mg/kg/day, during the period of organogenesis.
There were no maternal or embryo-fetal effects in either species up to the maximum dose tested. The 300 mg/kg/day dose level in rats and rabbits corresponds to 23 and 12 times the MRHD [based on body surface area (BSA) comparisons], respectively. In a rat peri- and postnatal development study, terbinafine doses of up to 300 mg/kg/day (12 times the MRHD based on BSA comparisons) given by oral gavage during late pregnancy and lactation (Day 15 of gestation to day 20 post-partum) had no adverse effects on parturition and lactation.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and efficacy of terbinafine tablets have not been established in pediatric patients with onychomycosis.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of terbinafine tablets did not include sufficient numbers of subjects aged 65 years and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Clinical experience regarding overdose with oral terbinafine is limited. Doses up to 5 grams (20 times the therapeutic daily dose) have been taken without inducing serious adverse reactions. The symptoms of overdose included nausea, vomiting, abdominal pain, dizziness, rash, frequent urination, and headache.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Terbinafine is an allylamine antifungal [see Clinical Pharmacology (12.4) ] .
12.2Pharmacodynamics The pharmacodynamics of terbinafine tablets is unknown.
12.3Pharmacokinetics Following oral administration, terbinafine is well absorbed (greater than 70%) and the bioavailability of terbinafine tablets as a result of first-pass metabolism is approximately 40%. Peak plasma concentrations of 1 mcg/mL appear within 2 hours after a single 250 mg dose; the AUC is approximately 4.56 mcg•h/mL. An increase in the AUC of terbinafine of less than 20% is observed when terbinafine tablets are administered with food.
In plasma, terbinafine is greater than 99% bound to plasma proteins and there are no specific binding sites. At steady-state, in comparison to a single dose, the peak concentration of terbinafine is 25% higher and plasma AUC increases by a factor of 2.5; the increase in plasma AUC is consistent with an effective half-life of ~36 hours. Terbinafine is distributed to the sebum and skin.
A terminal half-life of 200 to 400 hours may represent the slow elimination of terbinafine from tissues such as skin and adipose. Prior to excretion, terbinafine is extensively metabolized by at least 7 CYP isoenzymes with major contributions from CYP2C9, CYP1A2, CYP3A4, CYP2C8, and CYP2C19. No metabolites have been identified that have antifungal activity similar to terbinafine.
Approximately 70% of the administered dose is eliminated in the urine. In patients with renal impairment (creatinine clearance less than or equal to 50 mL/min) or hepatic cirrhosis, the clearance of terbinafine is decreased by approximately 50% compared to normal volunteers. No effect of gender on the blood levels of terbinafine was detected in clinical trials.
No clinically relevant age-dependent changes in steady-state plasma concentrations of terbinafine have been reported.
12.4Microbiology Terbinafine, an allylamine antifungal, inhibits biosynthesis of ergosterol, an essential component of fungal cell membrane, via inhibition of squalene epoxidase enzyme. This results in fungal cell death primarily due to the increased membrane permeability mediated by the accumulation of high concentrations of squalene but not due to ergosterol deficiency. Depending on the concentration of the drug and the fungal species test in vitro , terbinafine hydrochloride may be fungicidal.
However, the clinical significance of in vitro data is unknown. Terbinafine has been shown to be active against most strains of the following microorganisms both in vitro and in clinical infections: Trichophyton mentagrophytes Trichophyton rubrum The following in vitro data are available, but their clinical significance is unknown. In vitro , terbinafine exhibits satisfactory MIC’s against most strains of the following microorganisms; however, the safety and efficacy of terbinafine in treating clinical infections due to these microorganisms have not been established in adequate and well-controlled clinical trials: Candida albicans Epidermophyton floccosum Scopulariopsis brevicaulis Susceptibility Testing For specific information regarding susceptibility test interpretive criteria and associated test methods and quality control standards recognized by FDA for this drug, please see: https://www.fda.gov/STIC.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Terbinafine is an allylamine antifungal [see Clinical Pharmacology (12.4) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Terbinafine Tablets USP, 250 mg are supplied as white to off-white, round uncoated, biconvex beveled edge tablets having ‘D’ debossed on one side and ‘74’ on the other side. Bottles of 30 NDC 65862-079-30 Bottles of 100 NDC 65862-079-01 Bottles of 1,000 NDC 65862-079-99 Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Protect from light.
📋 Description ▾
11 DESCRIPTION Terbinafine tablets, USP contain the synthetic allylamine antifungal compound terbinafine hydrochloride USP. Chemically, terbinafine hydrochloride is (E)- N -(6,6-dimethyl-2-hepten-4-ynyl)- N -methyl-1-naphthalenemethanamine hydrochloride. The molecular formula C 21 H 26 ClN with a molecular weight of 327.90, and the following structural formula: Terbinafine hydrochloride USP is a white to off-white fine crystalline powder.
It is freely soluble in methanol and methylene chloride, soluble in ethanol, and slightly soluble in water. Each tablet contains : Active Ingredient: Terbinafine hydrochloride USP (equivalent to 250 mg of terbinafine) Inactive Ingredients: Microcrystalline cellulose, sodium starch glycolate, colloidal silicon dioxide, hypromellose, and magnesium stearate. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-Approved Medication Guide. Patients taking terbinafine tablets should receive the following information and instructions: Advise patients to immediately report to their physician or get emergency help if they experience any of the following symptoms: hives, mouth sores, blistering and peeling of skin, swelling of face, lips, tongue, or throat, difficulty swallowing or breathing. Terbinafine tablets treatment should be discontinued.
Advise patients to immediately report to their physician any symptoms of persistent nausea, anorexia, fatigue, vomiting, right upper abdominal pain, jaundice, dark urine, or pale stools. Terbinafine tablets treatment should be discontinued. Advise patients to report to their physician any signs of taste disturbance, smell disturbance and/or depressive symptoms, fever, skin eruption, lymph node enlargement, erythema, scaling, loss of pigment, and unusual photosensitivity that can result in a rash.
Terbinafine tablets treatment should be discontinued. Advise patients to minimize exposure to natural and artificial sunlight (tanning beds or UVA/B treatment) while using terbinafine tablets. Advise patients that if they forget to take terbinafine tablets, to take their tablets as soon as they remember, unless it is less than 4 hours before the next dose is due.
Advise patients to call their physician if they take too many terbinafine tablets. Advise patients to call their physician if they become pregnant during treatment with terbinafine tablets. Dispense with Medication Guide available at: www.aurobindousa.com/medication-guides Distributed by: Aurobindo Pharma USA, Inc.
279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Revised: 01/2022
💬 Medication Guide ▾
Medication Guide Terbinafine Tablets, USP [Terbinafine (ter BIN na feen)] What is the most important information I should know about terbinafine tablets? Terbinafine tablets may cause serious side effects, including: Liver problems that can lead to the need for a liver transplant or death . This can happen in people who have liver problems and in people who have never had liver problems.
Tell your doctor right away if you get any of these symptoms of liver problems: nausea poor appetite tiredness vomiting upper right stomach-area (abdomen) pain yellowing of your skin or eyes (jaundice) dark (tea-colored) urine pale or light colored stools Your doctor should do a blood test to check you for liver problems before you start treatment with terbinafine tablets. Your doctor may also check you for liver problems during treatment, and tell you to stop taking terbinafine tablets if you develop liver problems.
What are terbinafine tablets? Terbinafine tablets are a prescription medicine used to treat fungal infections of the fingernails and toenails (onychomycosis). Your doctor should do tests to check you for fungal infection of your nails before you start terbinafine tablets.
It is not known if terbinafine tablets are safe and effective in children for the treatment of onychomycosis. Who should not take terbinafine tablets? Do not take terbinafine tablets if you: have had a severe allergic reaction to terbinafine hydrochloride when taken by mouth. have had liver disease for a long time (chronic) or have active liver disease.
What should I tell my doctor before taking terbinafine tablets? Before taking terbinafine tablets, tell your doctor about all of your medical conditions, including if you: have or had liver problems have a weakened immune system (immunocompromised) have lupus (an autoimmune disease) are pregnant or plan to become pregnant. It is not known if terbinafine tablets may harm your unborn baby.
Tell your doctor right away if you become pregnant during treatment with terbinafine tablets. are breastfeeding or plan to breastfeed. Terbinafine hydrochloride passes into your breast milk and may harm your baby. Talk to your doctor about the best way to feed your baby if you take terbinafine tablets.
Tell your doctor about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. Terbinafine tablets may affect the way other medicines work and other medicines may affect how terbinafine tablets work. How should I take terbinafine tablets?
Take terbinafine tablets exactly as your doctor tells you to take them. Terbinafine hydrochloride comes as a tablet that you take by mouth. Terbinafine tablets are usually taken: 1 time each day for 6 weeks to treat fungal infections of your fingernail, or 1 time each day for 12 weeks to treat fungal infections of your toenail Terbinafine tablets can be taken with or without food.
If you miss a dose of terbinafine tablets, take it as soon as you remember. If it is less than 4 hours before your next dose, skip the missed dose. Just take the next dose at your regular time.
If you take too many terbinafine tablets, call your doctor. You may have the following symptoms: nausea vomiting stomach-area (abdomen) pain dizziness rash frequent urination headache What should I avoid while taking terbinafine tablets? Avoid sunlight.
Terbinafine tablets can make your skin sensitive to the sun and the light from sunlamps and tanning beds. You can get a severe sunburn. Use sunscreen and wear a hat and clothes that cover your skin if you have to be in sunlight.
Talk to your doctor if you get sunburn. What are the possible side effects of terbinafine tablets? Terbinafine tablets may cause serious side effects, including: See “What is the most important information I should know about terbinafine tablets?” Change in your sense of taste or loss of taste is common with terbinafine tablets, but can also be severe.
This may improve within several weeks after yo…