
Abacavir and Lamivudine 600 mg; 300 mg Tablet, Film Coated — NDC 65862-335-10 (Billing 65862-0335-10)
This is a package of Abacavir and Lamivudine 600 mg; 300 mg Tablet, Film Coated from Aurobindo Pharma Limited, marketed since Nov 2018 and currently FDA-listed.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 057896
- GCN: 23167
- GPI-14 (Medi-Span): 12109902200340
- HICL (First Databank): 026524
- AHFS class code: 08:18.08.20
- RxCUI (RxNorm): 602393
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Human Immunodeficiency Virus Nucleoside Analog Reverse Transcriptase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Abacavir is used to treat human immunodeficiency virus (HIV) infection. Abacavir is in a class of medications called nucleoside reverse transcriptase inhibitors (NRTIs). It works by decreasing the amount of HIV in the blood. Although abacavir does not cure HIV, it may decrease your chance of developing acquired immunodeficiency syndrome (AIDS) and HIV-related illnesses. Taking these medications and making other lifestyle changes may decrease the risk of giving the HIV virus to other people.
Read the full MedlinePlus article ↗This is a film-coated tablet combining two antiviral medications: abacavir and lamivudine. Both are nucleoside reverse transcriptase inhibitors typically used as part of combination therapy to treat HIV infection. The tablet contains 600 mg of abacavir and 300 mg of lamivudine per dose. This product is listed as a drug for further processing, meaning it is intended for use in manufacturing or repackaging rather than direct dispensing to patients.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $4.88 | $488.21 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 65862-0335-10 You're viewing this | 10 BLISTER PACK in 1 CARTON / 10 TABLET, FILM COATED in 1 BLISTER PACK | — | — | 2018-11-15 | — | Active |
| 65862-0335-30 65862-335-30 Main listing | 1 BOTTLE in 1 CARTON / 30 TABLET, FILM COATED in 1 BOTTLE | $1.48 / ea | $44.51 | 2018-11-15 | — | Active |
| 65862-0335-99 65862-335-99 | 1000 TABLET, FILM COATED in 1 BAG | — | — | — | — | Active |
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Abacavir and Lamivudine 600 mg; 300 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Abacavir and Lamivudine 600 mg/1; 300 mg 68180-0288-06 | Lupin | 30 tablets | $1.209 | AB | Discontinued | — |
| ABACAVIR and LAMIVUDINE 600 mg/1; 300 mg 31722-0838-30 | Camber | 30 tablets | $1.484 | AB | Availability likely | — |
| Abacavir and Lamivudine 600 mg/1; 300 mg 69097-0362-02 | Cipla | 30 tablets | $1.484 | AB | Availability likely | — |
| Abacavir and Lamivudine 600 mg/1; 300 mg 33342-0440-07 | Macleods | 30 tablets | — | — | FDA listed | — |
| Abacavir and Lamivudine 600 mg/1; 300 mg 42385-0962-18 | Laurus | 180 tablets | — | AB | FDA listed | — |
| Abacavir and Lamivudine 600 mg/1; 300 mgthis 65862-0335-10 | Aurobindo | 10 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII 0VUT3PMY82
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. In medicines, it forms protective coatings on tablets or capsules, controls how fast the drug releases, and thickens liquid formulations.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: HYPERSENSITIVITY REACTIONS and EXACERBATIONS OF HEPATITIS B Hypersensitivity Reactions Serious and sometimes fatal hypersensitivity reactions, with multiple organ involvement, have occurred with abacavir, a component of abacavir and lamivudine. Patients who carry the HLA-B*5701 allele are at a higher risk of a hypersensitivity reaction to abacavir; although, hypersensitivity reactions have occurred in patients who do not carry the HLA-B*5701 allele [see Warnings and Precautions (5.1) ] . Abacavir and lamivudine is contraindicated in patients with a prior hypersensitivity reaction to abacavir and in HLA-B*5701-positive patients [see Contraindications (4) , Warnings and Precautions (5.1) ].
All patients should be screened for the HLA-B*5701 allele prior to initiating therapy with abacavir and lamivudine or reinitiation of therapy with abacavir and lamivudine, unless patients have a previously documented HLA-B*5701 allele assessment. Discontinue abacavir and lamivudine immediately if a hypersensitivity reaction is suspected, regardless of HLA-B*5701 status and even when other diagnoses are possible [see Contraindications (4) , Warnings and Precautions (5.1) ]. Following a hypersensitivity reaction to abacavir and lamivudine, NEVER restart abacavir and lamivudine or any other abacavir-containing product because more severe symptoms, including death, can occur within hours.
Similar severe reactions have also occurred rarely following the reintroduction of abacavir-containing products in patients who have no history of abacavir hypersensitivity [see Warnings and Precautions (5.1) ]. Exacerbations of Hepatitis B Severe acute exacerbations of hepatitis B have been reported in patients who are co-infected with hepatitis B virus (HBV) and human immunodeficiency virus (HIV-1) and have discontinued lamivudine, which is a component of abacavir and lamivudine. Hepatic function should be monitored closely with both clinical and laboratory follow-up for at least several months in patients who discontinue abacavir and lamivudine and are co-infected with HIV-1 and HBV.
If appropriate, initiation of anti-hepatitis B therapy may be warranted [see Warnings and Precautions (5.2) ]. WARNING: HYPERSENSITIVITY REACTIONS and EXACERBATIONS OF HEPATITIS B See full prescribing information for complete boxed warning. Hypersensitivity Reactions • Serious and sometimes fatal hypersensitivity reactions have occurred with abacavir-containing products.
( 5.1 ) • Hypersensitivity to abacavir is a multi-organ clinical syndrome. ( 5.1 ) • Patients who carry the HLA-B*5701 allele are at a higher risk of experiencing a hypersensitivity reaction to abacavir. ( 5.1 ) • Abacavir and lamivudine is contraindicated in patients with a prior hypersensitivity reaction to abacavir and in HLA-B*5701-positive patients.
( 4 ) • Discontinue abacavir and lamivudine as soon as a hypersensitivity reaction is suspected. Regardless of HLA-B*5701 status, permanently discontinue abacavir and lamivudine if hypersensitivity cannot be ruled out, even when other diagnoses are possible. ( 5.1 ) • Following a hypersensitivity reaction to abacavir and lamivudine, NEVER restart abacavir and lamivudine or any other abacavir-containing product.
( 5.1 ) Exacerbations of Hepatitis B • Severe acute exacerbations of hepatitis B have been reported in patients who are co-infected with hepatitis B virus (HBV) and human immunodeficiency virus (HIV-1) and have discontinued lamivudine, a component of abacavir and lamivudine. Monitor hepatic function closely in these patients and, if appropriate, initiate anti-hepatitis B treatment. ( 5.2)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Abacavir and lamivudine tablets, in combination with other antiretroviral agents, are indicated for the treatment of human immunodeficiency virus type 1 (HIV-1) infection. Abacavir and lamivudine tablets, a combination of abacavir and lamivudine, both nucleoside analogue HIV-1 reverse transcriptase inhibitors, are indicated in combination with other antiretroviral agents for the treatment of HIV-1 infection. (1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Before initiating abacavir and lamivudine tablets, screen for the HLA-B*5701 allele because abacavir and lamivudine tablets contains abacavir. ( 2.1 ) Adults: One tablet orally once daily. ( 2.2 ) Pediatric patients weighing at least 25 kg: One tablet daily.
( 2.3 ) Because abacavir and lamivudine tablet is a fixed-dose tablet and cannot be dose adjusted, abacavir and lamivudine tablets are not recommended in patients with creatinine clearance less than 30 mL per minute or patients with hepatic impairment. ( 2.4 , 4 )
2.1Screening for HLA-B*5701 Allele Prior to Starting Abacavir and Lamivudine Tablets Screen for the HLA-B*5701 allele prior to initiating therapy with abacavir and lamivudine [see Boxed Warning , Warnings and Precautions (5.1) ].
2.2Recommended Dosage for Adult Patients The recommended dosage of abacavir and lamivudine tablets for adults is one tablet taken orally once daily, in combination with other antiretroviral agents, with or without food.
2.3Recommended Dosage for Pediatric Patients The recommended oral dose of abacavir and lamivudine for pediatric patients weighing at least 25 kg is one tablet daily in combination with other antiretroviral agents [see Clinical Studies (14.2) ]. Before prescribing abacavir and lamivudine tablets, pediatric patients should be assessed for the ability to swallow tablets.
2.4Not Recommended Due to Lack of Dosage Adjustment Because abacavir and lamivudine is a fixed-dose tablet and cannot be dose adjusted, abacavir and lamivudine tablets are not recommended for: patients with creatinine clearance less than 30 mL per minute [see Use in Specific Populations (8.6) ]. patients with mild hepatic impairment. Abacavir and lamivudine tablets are contraindicated in patients with moderate or severe hepatic impairment [see Contraindications (4) , Use in Specific Populations (8.7) ] . Use of EPIVIR (lamivudine) oral solution or tablets and ZIAGEN (abacavir) oral solution may be considered.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Abacavir and lamivudine tablets USP 600 mg/300 mg contain 600 mg of abacavir as abacavir sulfate and 300 mg of lamivudine. The tablets are orange colored, modified capsule shaped, film-coated tablets debossed with ‘H’ on one side and ‘27’ on other side. Tablets: 600 mg of abacavir and 300 mg of lamivudine. (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Abacavir and lamivudine tablets are contraindicated in patients: • who have the HLA-B*5701 allele [see Warnings and Precautions (5.1) ]. • with prior hypersensitivity reaction to abacavir [see Warnings and Precautions (5.1) ] or lamivudine. • with moderate or severe hepatic impairment [see Use in Specific Populations (8.7) ]. Presence of HLA-B*5701 allele. ( 4 ) Prior hypersensitivity reaction to abacavir or lamivudine.
( 4 ) Moderate or severe hepatic impairment. ( 4 , 8.7 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogues. ( 5.3 ) Immune reconstitution syndrome has been reported in patients treated with combination antiretroviral therapy. ( 5.4 )
5.1Hypersensitivity Reactions Serious and sometimes fatal hypersensitivity reactions have occurred with abacavir, a component of abacavir and lamivudine. These hypersensitivity reactions have included multi-organ failure and anaphylaxis and typically occurred within the first 6 weeks of treatment with abacavir (median time to onset was 9 days); although abacavir hypersensitivity reactions have occurred any time during treatment [see Adverse Reactions (6.1) ] . Patients who carry the HLA-B*5701 allele are at a higher risk of abacavir hypersensitivity reactions; although, patients who do not carry the HLA-B*5701 allele have developed hypersensitivity reactions.
Hypersensitivity to abacavir was reported in approximately 206 (8%) of 2,670 patients in 9 clinical trials with abacavir-containing products where HLA-B*5701 screening was not performed. The incidence of suspected abacavir hypersensitivity reactions in clinical trials was 1% when subjects carrying the HLA-B*5701 allele were excluded. In any patient treated with abacavir, the clinical diagnosis of hypersensitivity reaction must remain the basis of clinical decision making.
Due to the potential for severe, serious, and possibly fatal hypersensitivity reactions with abacavir: All patients should be screened for the HLA-B*5701 allele prior to initiating therapy with abacavir and lamivudine or reinitiation of therapy with abacavir and lamivudine, unless patients have a previously documented HLA-B*5701 allele assessment. Abacavir and lamivudine is contraindicated in patients with a prior hypersensitivity reaction to abacavir and in HLA-B*5701-positive patients. Before starting abacavir and lamivudine, review medical history for prior exposure to any abacavir-containing product.
NEVER restart abacavir and lamivudine or any other abacavir-containing product following a hypersensitivity reaction to abacavir, regardless of HLA-B*5701 status. To reduce the risk of a life-threatening hypersensitivity reaction, regardless of HLA-B*5701 status, discontinue abacavir and lamivudine immediately if a hypersensitivity reaction is suspected, even when other diagnoses are possible (e.g., acute onset respiratory diseases such as pneumonia, bronchitis, pharyngitis, or influenza; gastroenteritis; or reactions to other medications).
If a hypersensitivity reaction cannot be ruled out, do not restart abacavir and lamivudine or any other abacavir-containing products because more severe symptoms, which may include life-threatening hypotension and death, can occur within hours. If a hypersensitivity reaction is ruled out, patients may restart abacavir and lamivudine. Rarely, patients who have stopped abacavir for reasons other than symptoms of hypersensitivity have also experienced life-threatening reactions within hours of reinitiating abacavir therapy.
Therefore, reintroduction of abacavir and lamivudine or any other abacavir-containing product is recommended only if medical care can be readily accessed. A Medication Guide and Warning Card that provide information about recognition of hypersensitivity reactions should be dispensed with each new prescription and refill.
5.2Patients with Hepatitis B Virus Co-infection Posttreatment Exacerbations of Hepatitis Clinical and laboratory evidence of exacerbations of hepatitis have occurred after discontinuation of lamivudine. See full prescribing information for EPIVIR (lamivudine). Patients should be closely monitored with both clinical and laboratory follow-up for at least several months after stopping treatment.
Emergence of Lamivudine-Resistant HBV Safety and efficacy of lamivudine have not been established for treatment of chronic hepatitis B in subjects dually infe… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in other sections of the labeling: Serious and sometimes fatal hypersensitivity reactions [see Boxed Warning , Warnings and Precautions (5.1) ] . Exacerbations of hepatitis B [see Boxed Warning , Warnings and Precautions (5.2) ]. Lactic acidosis and severe hepatomegaly with steatosis [see Warnings and Precautions (5.3) ] .
Immune reconstitution syndrome [see Warnings and Precautions (5.4) ]. Myocardial infarction [see Warnings and Precautions (5.5) ]. The most commonly reported adverse reactions of at least moderate intensity (incidence greater than 5%) in an adult HIV-1 clinical trial were drug hypersensitivity, insomnia, depression/depressed mood, headache/migraine, fatigue/malaise, dizziness/vertigo, nausea, and diarrhea.
(6.1) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience in Adult Subjects Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Serious and Fatal Abacavir-Associated Hypersensitivity Reactions In clinical trials, serious and sometimes fatal hypersensitivity reactions have occurred with abacavir, a component of abacavir and lamivudine [see Boxed Warning, Warnings and Precautions (5.1) ] .
These reactions have been characterized by 2 or more of the following signs or symptoms: (1) fever; (2) rash; (3) gastrointestinal symptoms (including nausea, vomiting, diarrhea, or abdominal pain); (4) constitutional symptoms (including generalized malaise, fatigue, or achiness); (5) respiratory symptoms (including dyspnea, cough, or pharyngitis). Almost all abacavir hypersensitivity reactions include fever and/or rash as part of the syndrome. Other signs and symptoms have included lethargy, headache, myalgia, edema, arthralgia, and paresthesia.
Anaphylaxis, liver failure, renal failure, hypotension, adult respiratory distress syndrome, respiratory failure, myolysis, and death have occurred in association with these hypersensitivity reactions. Physical findings have included lymphadenopathy, mucous membrane lesions (conjunctivitis and mouth ulcerations), and maculopapular or urticarial rash (although some patients had other types of rashes and others did not have a rash). There were reports of erythema multiforme.
Laboratory abnormalities included elevated liver chemistries, elevated creatine phosphokinase, elevated creatinine, and lymphopenia and abnormal chest x-ray findings (predominantly infiltrates, which were localized). Additional Adverse Reactions with Use of abacavir and lamivudine Therapy-Naive Adults : Treatment-emergent clinical adverse reactions (rated by the investigator as moderate or severe) with greater than or equal to 5% frequency during therapy with ZIAGEN 600 mg once daily or ZIAGEN 300 mg twice daily, both in combination with lamivudine 300 mg once daily and efavirenz 600 mg once daily, are listed in Table 1.
Table 1. Treatment-Emergent (All Causality) Adverse Reactions of at Least Moderate Intensity (Grades 2 to 4, Greater than or Equal to 5% Frequency) in Therapy-Naive Adults (CNA30021) through 48 Weeks of Treatment a Subjects receiving ZIAGEN 600 mg once daily, experienced a significantly higher incidence of severe drug hypersensitivity reactions and severe diarrhea compared with subjects who received ZIAGEN 300 mg twice daily. Five percent (5%) of subjects receiving ZIAGEN 600 mg once daily had severe drug hypersensitivity reactions compared with 2% of subjects receiving ZIAGEN 300 mg twice daily.
Two percent (2%) of subjects receiving ZIAGEN 600 mg once daily had severe diarrhea while none of the subjects receiving ZIAGEN 300 mg twice daily had this event. b CNA30024 was a multi-center, double… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Methadone: An increased methadone dose may be required in a small number of patients. ( 7.1 ) Sorbitol: Coadministration of lamivudine and sorbitol may decrease lamivudine concentrations; when possible, avoid chronic coadministration. ( 7.2 ) Riociguat: The riociguat dose may need to be reduced. ( 7.3 )
7.1Methadone In a trial of 11 HIV-1-infected subjects receiving methadone-maintenance therapy with 600 mg of ZIAGEN twice daily (twice the currently recommended dose), oral methadone clearance increased [see Clinical Pharmacology (12.3) ] . This alteration will not result in a methadone dose modification in the majority of patients; however, an increased methadone dose may be required in a small number of patients.
7.2Sorbitol Coadministration of single doses of lamivudine and sorbitol resulted in a sorbitol dose-dependent reduction in lamivudine exposures. When possible, avoid use of sorbitol-containing medicines with lamivudine-containing medicines [see Clinical Pharmacology (12.3) ] .
7.3Riociguat Coadministration with fixed-dose abacavir/dolutegravir/lamivudine resulted in increased riociguat exposure, which may increase the risk of riociguat adverse reactions [see Clinical Pharmacology (12.3) ] . The riociguat dose may need to be reduced. See full prescribing information for ADEMPAS (riociguat).
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Women infected with HIV should be instructed not to breastfeed due to potential for HIV transmission. ( 8.2 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to abacavir and lamivudine during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the APR show no difference in the overall risk of birth defects for abacavir or lamivudine compared with the background rate for birth defects of 2.7% in the Metropolitan Atlanta Congenital Defects Program (MACDP) reference population (see Data).
The APR uses the MACDP as the U.S. reference population for birth defects in the general population. The MACDP evaluates women and infants from a limited geographic area and does not include outcomes for births that occurred at less than 20 weeks’ gestation. The rate of miscarriage is not reported in the APR.
The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15% to 20%. The background risk for major birth defects and miscarriage for the indicated population is unknown. In animal reproduction studies, oral administration of abacavir to pregnant rats during organogenesis resulted in fetal malformations and other embryonic and fetal toxicities at exposures 35 times the human exposure (AUC) at the recommended clinical daily dose.
However, no adverse developmental effects were observed following oral administration of abacavir to pregnant rabbits during organogenesis, at exposures approximately 9 times the human exposure (AUC) at the recommended clinical dose. Oral administration of lamivudine to pregnant rabbits during organogenesis resulted in embryolethality at systemic exposure (AUC) similar to the recommended clinical dose; however, no adverse development effects were observed with oral administration of lamivudine to pregnant rats during organogenesis at plasma concentrations (C max ) 35 times the recommended clinical dose (see Data).
Data Human Data: Abacavir: Based on prospective reports to the APR of exposures to abacavir during pregnancy resulting in live births (including over 1,300 exposed in the first trimester and over 1,300 exposed in the second/third trimester), there was no difference between the overall risk of birth defects for abacavir compared with the background birth defect rate of 2.7% in the U.S. reference population of the MACDP. The prevalence of defects in live births was 3.2% (95% CI: 2.3% to 4.3%) following first trimester exposure to abacavir-containing regimens and 2.9% (95% CI: 2.1% to 4.0%) following second/third trimester exposure to abacavir-containing regimens.
Abacavir has been shown to cross the placenta and concentrations in neonatal plasma at birth were essentially equal to those in maternal plasma at delivery [see Clinical Pharmacology (12.3) ] . Lamivudine: Based on prospective reports to the APR of exposures to lamivudine during pregnancy resulting in live births (including over 5,300 exposed in the first trimester and over 7,400 exposed in the second/third trimester), there was no difference between the overall risk of birth defects for lamivudine compared with the background birth defect rate of 2.7% in the U.S. reference population of the MACDP.
The prevalence of birth defects in live births was 3.1% (95% CI: 2.7% to 3.6%) following first trimester exposure to lamivudine-containing regimens and 2.9% (95% CI: 2.5%, 3.3%) following second/third trimester exposure to lamivudine-containing regimens. Lamivudine pharmacokinetics were studied in pregnant women during 2 clinical trials conducted in South Africa. The trials assessed pharmacokinetics in 16 women at 36 weeks’ gestation using 150 mg lamivudine twice daily with zidovudine, 10 women at 38 weeks’ gestation using 150 mg lamivudine twice daily wit… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to abacavir and lamivudine during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the APR show no difference in the overall risk of birth defects for abacavir or lamivudine compared with the background rate for birth defects of 2.7% in the Metropolitan Atlanta Congenital Defects Program (MACDP) reference population (see Data).
The APR uses the MACDP as the U.S. reference population for birth defects in the general population. The MACDP evaluates women and infants from a limited geographic area and does not include outcomes for births that occurred at less than 20 weeks’ gestation. The rate of miscarriage is not reported in the APR.
The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15% to 20%. The background risk for major birth defects and miscarriage for the indicated population is unknown. In animal reproduction studies, oral administration of abacavir to pregnant rats during organogenesis resulted in fetal malformations and other embryonic and fetal toxicities at exposures 35 times the human exposure (AUC) at the recommended clinical daily dose.
However, no adverse developmental effects were observed following oral administration of abacavir to pregnant rabbits during organogenesis, at exposures approximately 9 times the human exposure (AUC) at the recommended clinical dose. Oral administration of lamivudine to pregnant rabbits during organogenesis resulted in embryolethality at systemic exposure (AUC) similar to the recommended clinical dose; however, no adverse development effects were observed with oral administration of lamivudine to pregnant rats during organogenesis at plasma concentrations (C max ) 35 times the recommended clinical dose (see Data).
Data Human Data: Abacavir: Based on prospective reports to the APR of exposures to abacavir during pregnancy resulting in live births (including over 1,300 exposed in the first trimester and over 1,300 exposed in the second/third trimester), there was no difference between the overall risk of birth defects for abacavir compared with the background birth defect rate of 2.7% in the U.S. reference population of the MACDP. The prevalence of defects in live births was 3.2% (95% CI: 2.3% to 4.3%) following first trimester exposure to abacavir-containing regimens and 2.9% (95% CI: 2.1% to 4.0%) following second/third trimester exposure to abacavir-containing regimens.
Abacavir has been shown to cross the placenta and concentrations in neonatal plasma at birth were essentially equal to those in maternal plasma at delivery [see Clinical Pharmacology (12.3) ] . Lamivudine: Based on prospective reports to the APR of exposures to lamivudine during pregnancy resulting in live births (including over 5,300 exposed in the first trimester and over 7,400 exposed in the second/third trimester), there was no difference between the overall risk of birth defects for lamivudine compared with the background birth defect rate of 2.7% in the U.S. reference population of the MACDP.
The prevalence of birth defects in live births was 3.1% (95% CI: 2.7% to 3.6%) following first trimester exposure to lamivudine-containing regimens and 2.9% (95% CI: 2.5%, 3.3%) following second/third trimester exposure to lamivudine-containing regimens. Lamivudine pharmacokinetics were studied in pregnant women during 2 clinical trials conducted in South Africa. The trials assessed pharmacokinetics in 16 women at 36 weeks’ gestation using 150 mg lamivudine twice daily with zidovudine, 10 women at 38 weeks’ gestation using 150 mg lamivudine twice daily with zidovudine, and 10 women at 38 weeks’ gestation using lamivudine 300 mg twice daily without other antiretrovirals.
These trials were not designed or… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use The dosing recommendations in this population are based on the safety and efficacy established in a controlled trial conducted using either the combination of EPIVIR and ZIAGEN or abacavir and lamivudine [see Dosage and Administration (2.3) , Adverse Reactions (6.2) , Clinical Studies (14.2) ]. In pediatric patients weighing less than 25 kg, use of abacavir and lamivudine as single products is recommended to achieve appropriate dosing.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of abacavir and lamivudine did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In general, caution should be exercised in the administration of abacavir and lamivudine in elderly patients reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy [see Dosage and Administration (2.4) , Use in Specific Populations (8.6 , 8.7) ] .
🆘 Overdosage ▾
10 OVERDOSAGE There is no known specific treatment for overdose with abacavir and lamivudine. If overdose occurs, the patient should be monitored, and standard supportive treatment applied as required. Abacavir: It is not known whether abacavir can be removed by peritoneal dialysis or hemodialysis.
Lamivudine: Because a negligible amount of lamivudine was removed via (4-hour) hemodialysis, continuous ambulatory peritoneal dialysis, and automated peritoneal dialysis, it is not known if continuous hemodialysis would provide clinical benefit in a lamivudine overdose event.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Abacavir and lamivudine is an antiretroviral agent with activity against HIV-1 [see Microbiology (12.4) ] .
12.3Pharmacokinetics Pharmacokinetics in Adults In a single-dose, 3-way crossover bioavailability trial of 1 abacavir and lamivudine tablet versus 2 ZIAGEN tablets (2 x 300 mg) and 2 EPIVIR tablets (2 x 150 mg) administered simultaneously in healthy subjects (n = 25), there was no difference in the extent of absorption, as measured by the area under the plasma concentration-time curve (AUC) and maximal peak concentration (C max ), of each component. Abacavir: Following oral administration, abacavir is rapidly absorbed and extensively distributed.
After oral administration of a single dose of 600 mg of abacavir in 20 subjects, C max was 4.26 ± 1.19 mcg per mL (mean ± SD) and AUC ∞ was 11.95 ± 2.51 mcg•hour per mL. Binding of abacavir to human plasma proteins is approximately 50% and was independent of concentration. Total blood and plasma drug-related radioactivity concentrations are identical, demonstrating that abacavir readily distributes into erythrocytes.
The primary routes of elimination of abacavir are metabolism by alcohol dehydrogenase to form the 5’-carboxylic acid and glucuronyl transferase to form the 5’-glucuronide. Lamivudine: Following oral administration, lamivudine is rapidly absorbed and extensively distributed. After multiple-dose oral administration of lamivudine 300 mg once daily for 7 days to 60 healthy subjects, steady-state C max (C max,ss ) was 2.04 ± 0.54 mcg per mL (mean ± SD) and the 24-hour steady-state AUC (AUC 24,ss ) was 8.87 ± 1.83 mcg•hour per mL.
Binding to plasma protein is low. Approximately 70% of an intravenous dose of lamivudine is recovered as unchanged drug in the urine. Metabolism of lamivudine is a minor route of elimination.
In humans, the only known metabolite is the trans-sulfoxide metabolite (approximately 5% of an oral dose after 12 hours). In humans, abacavir and lamivudine are not significantly metabolized by cytochrome P450 (CYP) enzymes. The pharmacokinetic properties of abacavir and lamivudine in fasting subjects are summarized in Table 2.
Table 2. Pharmacokinetic Parameters a for Abacavir and Lamivudine in Adults a Data presented as mean ± standard deviation except where noted. b Approximate range. Parameter Abacavir Lamivudine Oral bioavailability (%) 86 ± 25 n = 6 86 ± 16 n = 12 Apparent volume of distribution (L/kg) 0.86 ± 0.15 n = 6 1.3 ± 0.4 n = 20 Systemic clearance (L/h/kg) 0.80 ± 0.24 n = 6 0.33 ± 0.06 n = 20 Renal clearance (L/h/kg) 0.007 ± 0.008 n = 6 0.22 ± 0.06 n = 20 Elimination half-life (h) 1.45 ± 0.32 n = 20 13 to 19 b Effect of Food on Absorption of Abacavir and Lamivudine Abacavir and lamivudine may be administered with or without food.
Administration with a high-fat meal in a single-dose bioavailability trial resulted in no change in AUC last , AUC ∞ , and C max for lamivudine. Food did not alter the extent of systemic exposure to abacavir (AUC ∞ ), but the rate of absorption (C max ) was decreased approximately 24% compared with fasted conditions (n = 25). These results are similar to those from previous trials of the effect of food on abacavir and lamivudine tablets administered separately.
Specific Populations Patients with Renal Impairment: The pharmacokinetics for the individual lamivudine component of abacavir and lamivudine tablets has been evaluated in patients with renal impairment (see the U.S. prescribing information for the individual lamivudine component). Patients with Hepatic Impairment: The pharmacokinetics for the individual components of abacavir and lamivudine tablets have been evaluated in patients with varying degrees of hepatic impairment (see the U.S. prescribing information for the individual abacavir and lamivudine components).
Pregnant Women: Abacavir: Abacavir pharmacokinetics were studied in 25 pregnant women during the last trimester of pregnancy receiving abacavir 300 m… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Abacavir and lamivudine is an antiretroviral agent with activity against HIV-1 [see Microbiology (12.4) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Abacavir and Lamivudine Tablets USP contain 600 mg of abacavir as abacavir sulfate and 300 mg of lamivudine. The tablets are orange colored, modified capsule shaped, film-coated tablets debossed with ‘H’ on one side and ‘27’ on other side. Bottles of 30 NDC 65862-335-30 Cartons of 100 (10 x 10) Unit-dose Tablets NDC 65862-335-10 Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Abacavir and lamivudine Abacavir and lamivudine tablets USP contain the following 2 synthetic nucleoside analogues: abacavir (ZIAGEN, also a component of TRIZIVIR) and lamivudine (also known as EPIVIR or 3TC) with inhibitory activity against HIV-1. Abacavir and lamivudine tablets USP are for oral administration. Each orange, film-coated tablet contains the active ingredients 600 mg of abacavir as abacavir sulfate USP and 300 mg of lamivudine USP, and the inactive ingredients magnesium stearate, microcrystalline cellulose and sodium starch glycolate.
The tablets are coated with a film (opadry orange YS-1-13065-A) that is made of FD&C yellow #6 aluminum lake, hypromellose, polyethylene glycol 400, polysorbate 80, and titanium dioxide. Abacavir Sulfate The chemical name of abacavir sulfate is ( 1 S,cis) -4-[2-amino-6-(cyclopropylamino)-9 H -purin-9-yl]-2-cyclopentene-1-methanol sulfate (salt) (2:1). Abacavir sulfate is the enantiomer with 1S, 4R absolute configuration on the cyclopentene ring.
It has a molecular formula of (C 14 H 18 N 6 O) 2 •H 2 SO 4 and a molecular weight of 670.76 g per mol. It has the following structural formula: Abacavir sulfate USP is a white to off-white powder and soluble in water, slightly soluble in methanol and practically insoluble in ethyl acetate and in absolute alcohol. In vivo , abacavir sulfate dissociates to its free base, abacavir.
Dosages are expressed in terms of abacavir. Lamivudine The chemical name of lamivudine is (2R,cis)-4-amino-1-(2-hydroxymethyl-1,3-oxathiolan-5-yl)-(1H)-pyrimidin-2-one. Lamivudine is the (-)enantiomer of a dideoxy analogue of cytidine.
Lamivudine has also been referred to as (-)2´,3´-dideoxy, 3´-thiacytidine. It has a molecular formula of C 8 H 11 N 3 O 3 S and a molecular weight of 229.3 g per mol. It has the following structural formula: Lamivudine USP is a white to off-white solid and is soluble in water.
Abacavir Sulfate Structure Lamivudine Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Hypersensitivity Reactions Inform patients: that a Medication Guide and Warning Card summarizing the symptoms of the abacavir hypersensitivity reaction and other product information will be dispensed by the pharmacist with each new prescription and refill of abacavir and lamivudine and instruct the patient to read the Medication Guide and Warning Card every time to obtain any new information that may be present about abacavir and lamivudine.
The complete text of the Medication Guide is reprinted at the end of this document. to carry the Warning Card with them. how to identify a hypersensitivity reaction [see Warnings and Precautions (5.1) , Medication Guide ]. that if they develop symptoms consistent with a hypersensitivity reaction they should call their healthcare provider right away to determine if they should stop taking abacavir and lamivudine. that a hypersensitivity reaction can worsen and lead to hospitalization or death if abacavir and lamivudine is not immediately discontinued. to not restart abacavir and lamivudine or any other abacavir-containing product following a hypersensitivity reaction because more severe symptoms can occur within hours and may include life-threatening hypotension and death. that if they have a hypersensitivity reaction, they should dispose of any unused abacavir and lamivudine to avoid restarting abacavir. that a hypersensitivity reaction is usually reversible if it is detected promptly and abacavir and lamivudine is stopped right away. that if they have interrupted abacavir and lamivudine for reasons other than symptoms of hypersensitivity (for example, those who have an interruption in drug supply), a serious or fatal hypersensitivity reaction may occur with reintroduction of abacavir. to not restart abacavir and lamivudine or any other abacavir-containing product without medical consultation and only if medical care can be readily accessed by the patient or others.
Patients with Hepatitis B or C Co-infection Advise patients co-infected with HIV-1 and HBV that worsening of liver disease has occurred in some cases when treatment with lamivudine was discontinued. Advise patients to discuss any changes in regimen with their physician [see Warnings and Precautions (5.2) ]. Lactic Acidosis/Hepatomegaly with Steatosis Advise patients that lactic acidosis and severe hepatomegaly with steatosis have been reported with use of nucleoside analogues and other antiretrovirals.
Advise patients to stop taking abacavir and lamivudine if they develop clinical symptoms suggestive of lactic acidosis or pronounced hepatotoxicity [see Warnings and Precautions (5.3) ]. Immune Reconstitution Syndrome Advise patients to inform their healthcare provider immediately of any signs and symptoms of infection as inflammation from previous infection may occur soon after combination antiretroviral therapy, including when abacavir and lamivudine is started [see Warnings and Precautions (5.4) ]. Pregnancy Registry Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to abacavir and lamivudine during pregnancy [see Use in Specific Populations (8.1) ] .
Lactation Instruct women with HIV-1 infection not to breastfeed because HIV-1 can be passed to the baby in the breast milk [see Use in Specific Populations (8.2) ] . Missed Dose Instruct patients that if they miss a dose of abacavir and lamivudine, to take it as soon as they remember. Advise patients not to double their next dose or take more than the prescribed dose [see Dosage and Administration (2) ] .
Availability of Medication Guide Instruct patients to read the Medication Guide before starting abacavir and lamivudine and to re-read it each time the prescription is renewed. Instruct patients to inform their physician or pharmacist if they develop any unusual symptom, or if any known symptom persists or… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
MEDICATION GUIDE Abacavir and Lamivudine Tablets USP (a bak' a vir and la miv' ue deen) What is the most important information I should know about abacavir and lamivudine tablets? Abacavir and lamivudine tablets can cause serious side effects, including: Serious allergic reactions (hypersensitivity reaction) that can cause death have happened with abacavir and lamivudine tablets and other abacavir-containing products. Your risk of this allergic reaction is much higher if you have a gene variation called HLA-B*5701.
Your healthcare provider can determine with a blood test if you have this gene variation. If you get a symptom from 2 or more of the following groups while taking abacavir and lamivudine tablets, call your healthcare provider right away to find out if you should stop taking abacavir and lamivudine tablets. Symptom(s) Group 1 Fever Group 2 Rash Group 3 Nausea, vomiting, diarrhea, abdominal (stomach area) pain Group 4 Generally ill feeling, extreme tiredness, or achiness Group 5 Shortness of breath, cough, sore throat A list of these symptoms is on the Warning Card your pharmacist gives you.
Carry this Warning Card with you at all times. If you stop abacavir and lamivudine tablets because of an allergic reaction, never take abacavir and lamivudine tablets or any other abacavir-containing medicine (TRIUMEQ, TRIZIVIR, or ZIAGEN) again. If you have an allergic reaction, dispose of any unused abacavir and lamivudine tablets.
Ask your pharmacist how to properly dispose of medicines. If you take abacavir and lamivudine tablets or any other abacavir-containing medicine again after you have had an allergic reaction, within hours you may get life-threatening symptoms that may include very low blood pressure or death. If you stop abacavir and lamivudine tablets for any other reason, even for a few days, and you are not allergic to abacavir and lamivudine tablets, talk with your healthcare provider before taking them again.
Taking abacavir and lamivudine tablets again can cause a serious allergic or life-threatening reaction, even if you never had an allergic reaction to them before. If your healthcare provider tells you that you can take abacavir and lamivudine tablets again, start taking them when you are around medical help or people who can call a healthcare provider if you need one. Worsening of hepatitis B virus (HBV) infection.
If you have HBV infection and take abacavir and lamivudine tablets, your HBV may get worse (flare-up) if you stop taking abacavir and lamivudine tablets. A “flare-up” is when your HBV infection suddenly returns in a worse way than before. Do not run out of abacavir and lamivudine tablets.
Refill your prescription or talk to your healthcare provider before your abacavir and lamivudine tablets is all gone Do not stop abacavir and lamivudine tablets without first talking to your healthcare provider. If you stop taking abacavir and lamivudine tablets, your healthcare provider will need to check your health often and do blood tests regularly for several months to check your liver function and monitor your HBV infection. It may be necessary to give you a medicine to treat HBV.
Tell your healthcare provider about any new or unusual symptoms you may have after you stop taking abacavir and lamivudine tablets. Resistant HBV. If you have human immunodeficiency virus-1 (HIV-1) and HBV, the HBV can change (mutate) during your treatment with abacavir and lamivudine tablets and become harder to treat (resistant).
For more information about side effects, see “What are the possible side effects of abacavir and lamivudine tablets?” What are abacavir and lamivudine tablets? Abacavir and lamivudine tablets are a prescription medicine used with other HIV-1 medicines to treat HIV-1 infection. HIV-1 is the virus that causes Acquired Immune Deficiency Syndrome (AIDS).
Abacavir and lamivudine tablets contain the prescription medicines abacavir and lamivudine. Abacavir and lamivudine tablets should not be used in children w… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Pharmacokinetics in Adults In a single-dose, 3-way crossover bioavailability trial of 1 abacavir and lamivudine tablet versus 2 ZIAGEN tablets (2 x 300 mg) and 2 EPIVIR tablets (2 x 150 mg) administered simultaneously in healthy subjects (n = 25), there was no difference in the extent of absorption, as measured by the area under the plasma concentration-time curve (AUC) and maximal peak concentration (C max ), of each component. Abacavir: Following oral administration, abacavir is rapidly absorbed and extensively distributed.
After oral administration of a single dose of 600 mg of abacavir in 20 subjects, C max was 4.26 ± 1.19 mcg per mL (mean ± SD) and AUC ∞ was 11.95 ± 2.51 mcg•hour per mL. Binding of abacavir to human plasma proteins is approximately 50% and was independent of concentration. Total blood and plasma drug-related radioactivity concentrations are identical, demonstrating that abacavir readily distributes into erythrocytes.
The primary routes of elimination of abacavir are metabolism by alcohol dehydrogenase to form the 5’-carboxylic acid and glucuronyl transferase to form the 5’-glucuronide. Lamivudine: Following oral administration, lamivudine is rapidly absorbed and extensively distributed. After multiple-dose oral administration of lamivudine 300 mg once daily for 7 days to 60 healthy subjects, steady-state C max (C max,ss ) was 2.04 ± 0.54 mcg per mL (mean ± SD) and the 24-hour steady-state AUC (AUC 24,ss ) was 8.87 ± 1.83 mcg•hour per mL.
Binding to plasma protein is low. Approximately 70% of an intravenous dose of lamivudine is recovered as unchanged drug in the urine. Metabolism of lamivudine is a minor route of elimination.
In humans, the only known metabolite is the trans-sulfoxide metabolite (approximately 5% of an oral dose after 12 hours). In humans, abacavir and lamivudine are not significantly metabolized by cytochrome P450 (CYP) enzymes. The pharmacokinetic properties of abacavir and lamivudine in fasting subjects are summarized in Table 2.
Table 2. Pharmacokinetic Parameters a for Abacavir and Lamivudine in Adults a Data presented as mean ± standard deviation except where noted. b Approximate range. Parameter Abacavir Lamivudine Oral bioavailability (%) 86 ± 25 n = 6 86 ± 16 n = 12 Apparent volume of distribution (L/kg) 0.86 ± 0.15 n = 6 1.3 ± 0.4 n = 20 Systemic clearance (L/h/kg) 0.80 ± 0.24 n = 6 0.33 ± 0.06 n = 20 Renal clearance (L/h/kg) 0.007 ± 0.008 n = 6 0.22 ± 0.06 n = 20 Elimination half-life (h) 1.45 ± 0.32 n = 20 13 to 19 b Effect of Food on Absorption of Abacavir and Lamivudine Abacavir and lamivudine may be administered with or without food.
Administration with a high-fat meal in a single-dose bioavailability trial resulted in no change in AUC last , AUC ∞ , and C max for lamivudine. Food did not alter the extent of systemic exposure to abacavir (AUC ∞ ), but the rate of absorption (C max ) was decreased approximately 24% compared with fasted conditions (n = 25). These results are similar to those from previous trials of the effect of food on abacavir and lamivudine tablets administered separately.
Specific Populations Patients with Renal Impairment: The pharmacokinetics for the individual lamivudine component of abacavir and lamivudine tablets has been evaluated in patients with renal impairment (see the U.S. prescribing information for the individual lamivudine component). Patients with Hepatic Impairment: The pharmacokinetics for the individual components of abacavir and lamivudine tablets have been evaluated in patients with varying degrees of hepatic impairment (see the U.S. prescribing information for the individual abacavir and lamivudine components).
Pregnant Women: Abacavir: Abacavir pharmacokinetics were studied in 25 pregnant women during the last trimester of pregnancy receiving abacavir 300 mg twice daily. Abacavir exposure (AUC) during pregnancy was similar to those in postpartum and in HIV-infected non-pregnant historical controls. Consistent wi… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Adults One abacavir and lamivudine tablet given once daily is an alternative regimen to EPIVIR tablets 300 mg once daily plus ZIAGEN tablets 2 x 300 mg once daily as a component of antiretroviral therapy. The following trial was conducted with the individual components of abacavir and lamivudine. Therapy-Naive Adults CNA30021 was an international, multicenter, double-blind, controlled trial in which 770 HIV-1-infected, therapy-naive adults were randomized and received either ZIAGEN 600 mg once daily or ZIAGEN 300 mg twice daily, both in combination with EPIVIR 300 mg once daily and efavirenz 600 mg once daily.
The double-blind treatment duration was at least 48 weeks. Trial participants had a mean age of 37 years; were male (81%), white (54%), black (27%), and American Hispanic (15%). The median baseline CD4+ cell count was 262 cells per mm 3 (range: 21 to 918 cells per mm 3 ) and the median baseline plasma HIV-1 RNA was 4.89 log 10 copies per mL (range: 2.60 to 6.99 log 10 copies per mL).
The outcomes of randomized treatment are provided in Table 4. Table 4. Outcomes of Randomized Treatment through Week 48 (CNA30021) a Subjects achieved and maintained confirmed HIV-1 RNA less than 50 copies per mL (less than 400 copies per mL) through Week 48 (Roche AMPLICOR Ultrasensitive HIV-1 MONITOR standard test version 1.0). b Includes viral rebound, failure to achieve confirmed less than 50 copies per mL (less than 400 copies per mL) by Week 48, and insufficient viral load response. c Includes consent withdrawn, lost to follow-up, protocol violations, clinical progression, and other.
Outcome ZIAGEN 600 mg q.d. plus EPIVIR plus Efavirenz (n = 384) ZIAGEN 300 mg b.i.d. plus EPIVIR plus Efavirenz (n = 386) Responder a Virologic failure b Discontinued due to adverse reactions Discontinued due to other reasons c 64% (71%) 11% (5%) 13% 11% 65% (72%) 11% (5%) 11% 13% After 48 weeks of therapy, the median CD4+ cell count increases from baseline were 188 cells per mm 3 in the group receiving ZIAGEN 600 mg once daily and 200 cells per mm 3 in the group receiving ZIAGEN 300 mg twice daily. Through Week 48, 6 subjects (2%) in the group receiving ZIAGEN 600 mg once daily (4 CDC classification C events and 2 deaths) and 10 subjects (3%) in the group receiving ZIAGEN 300 mg twice daily (7 CDC classification C events and 3 deaths) experienced clinical disease progression.
None of the deaths were attributed to trial medications.
14.2Pediatric Subjects ARROW (COL105677) was a 5-year, randomized, multicenter trial which evaluated multiple aspects of clinical management of HIV-1 infection in pediatric subjects. HIV-1–infected, treatment-naïve subjects aged 3 months to 17 years were enrolled and treated with a first-line regimen containing abacavir and lamivudine, dosed twice daily according to World Health Organization recommendations. After a minimum of 36 weeks of treatment, subjects were given the option to participate in Randomization 3 of the ARROW trial, comparing the safety and efficacy of once-daily dosing with twice-daily dosing of abacavir and lamivudine, in combination with a third antiretroviral drug, for an additional 96 weeks.
Virologic suppression was not a requirement for participation at baseline for Randomization 3. At baseline for Randomization 3 (following a minimum of 36 weeks of twice-daily treatment), 75% of subjects in the twice-daily cohort were virologically suppressed, compared with 71% of subjects in the once-daily cohort. Of the 1,206 original ARROW subjects, 669 participated in Randomization 3.
Subjects randomized to receive once-daily dosing (n = 336) and who weighed at least 25 kg received abacavir 600 mg and lamivudine 300 mg, as either the single entities or as abacavir and lamivudine. The proportions of subjects with HIV-1 RNA less than 80 copies per mL through 96 weeks are shown in Table 5. The differences between virologic responses in the two treatment arms were comparable across baseline cha… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity Abacavir: Abacavir was administered orally at 3 dosage levels to separate groups of mice and rats in 2-year carcinogenicity studies. Results showed an increase in the incidence of malignant and non-malignant tumors. Malignant tumors occurred in the preputial gland of males and the clitoral gland of females of both species, and in the liver of female rats.
In addition, non-malignant tumors also occurred in the liver and thyroid gland of female rats. These observations were made at systemic exposures in the range of 6 to 32 times the human exposure at the recommended dose of 600 mg. Lamivudine: Long-term carcinogenicity studies with lamivudine in mice and rats showed no evidence of carcinogenic potential at exposures up to 10 times (mice) and 58 times (rats) the human exposures at the recommended dose of 300 mg.
Mutagenicity Abacavir: Abacavir induced chromosomal aberrations both in the presence and absence of metabolic activation in an in vitro cytogenetic study in human lymphocytes. Abacavir was mutagenic in the absence of metabolic activation, although it was not mutagenic in the presence of metabolic activation in an L5178Y mouse lymphoma assay. Abacavir was clastogenic in males and not clastogenic in females in an in vivo mouse bone marrow micronucleus assay.
Abacavir was not mutagenic in bacterial mutagenicity assays in the presence and absence of metabolic activation. Lamivudine: Lamivudine was mutagenic in an L5178Y mouse lymphoma assay and clastogenic in a cytogenetic assay using cultured human lymphocytes. Lamivudine was not mutagenic in a microbial mutagenicity assay, in an in vitro cell transformation assay, in a rat micronucleus test, in a rat bone marrow cytogenetic assay, and in an assay for unscheduled DNA synthesis in rat liver.
Impairment of Fertility Abacavir: Abacavir did not affect male or female fertility in rats at a dose associated with exposures (AUC) approximately 3.3 times (male) or 4.1 times (female) those in humans at the clinically recommended dose. Lamivudine: Lamivudine did not affect male or female fertility in rats at doses up to 4,000 mg per kg per day, associated with concentrations approximately 42 times (male) or 63 times (female) higher than the concentrations (C max ) in humans at the dose of 300 mg.
13.2Animal Toxicology and/or Pharmacology Myocardial degeneration was found in mice and rats following administration of abacavir for 2 years. The systemic exposures were equivalent to 7 to 24 times the expected systemic exposure in humans at a dose of 600 mg. The clinical relevance of this finding has not been determined.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity Abacavir: Abacavir was administered orally at 3 dosage levels to separate groups of mice and rats in 2-year carcinogenicity studies. Results showed an increase in the incidence of malignant and non-malignant tumors. Malignant tumors occurred in the preputial gland of males and the clitoral gland of females of both species, and in the liver of female rats.
In addition, non-malignant tumors also occurred in the liver and thyroid gland of female rats. These observations were made at systemic exposures in the range of 6 to 32 times the human exposure at the recommended dose of 600 mg. Lamivudine: Long-term carcinogenicity studies with lamivudine in mice and rats showed no evidence of carcinogenic potential at exposures up to 10 times (mice) and 58 times (rats) the human exposures at the recommended dose of 300 mg.
Mutagenicity Abacavir: Abacavir induced chromosomal aberrations both in the presence and absence of metabolic activation in an in vitro cytogenetic study in human lymphocytes. Abacavir was mutagenic in the absence of metabolic activation, although it was not mutagenic in the presence of metabolic activation in an L5178Y mouse lymphoma assay. Abacavir was clastogenic in males and not clastogenic in females in an in vivo mouse bone marrow micronucleus assay.
Abacavir was not mutagenic in bacterial mutagenicity assays in the presence and absence of metabolic activation. Lamivudine: Lamivudine was mutagenic in an L5178Y mouse lymphoma assay and clastogenic in a cytogenetic assay using cultured human lymphocytes. Lamivudine was not mutagenic in a microbial mutagenicity assay, in an in vitro cell transformation assay, in a rat micronucleus test, in a rat bone marrow cytogenetic assay, and in an assay for unscheduled DNA synthesis in rat liver.
Impairment of Fertility Abacavir: Abacavir did not affect male or female fertility in rats at a dose associated with exposures (AUC) approximately 3.3 times (male) or 4.1 times (female) those in humans at the clinically recommended dose. Lamivudine: Lamivudine did not affect male or female fertility in rats at doses up to 4,000 mg per kg per day, associated with concentrations approximately 42 times (male) or 63 times (female) higher than the concentrations (C max ) in humans at the dose of 300 mg.
📄 Recent Major Changes ▾
Dosage and Administration, Not Recommended Due to 12/2021 Lack of Dosage Adjustment ( 2.4 )
📄 Package Label / Principal Display Panel ▾
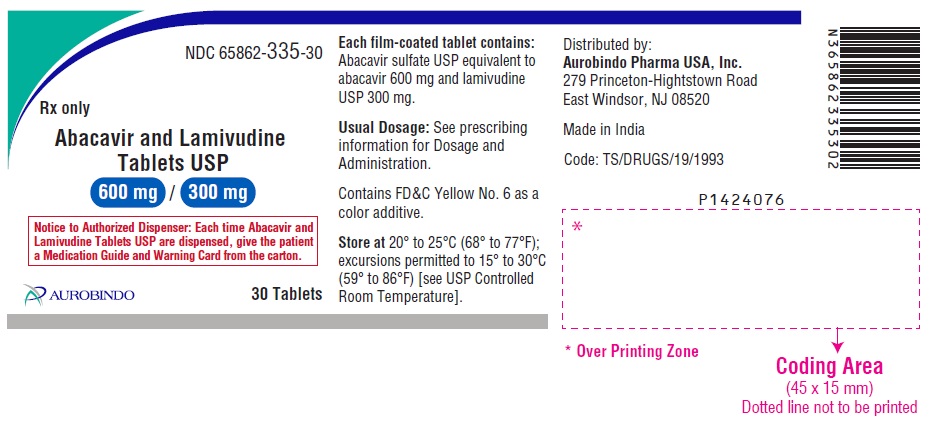
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 600 mg/300 mg (30 Tablets Container) NDC 65862-335-30 Rx only Abacavir and Lamivudine Tablets USP 600 mg / 300 mg Notice to Authorized Dispenser: Each time Abacavir and Lamivudine Tablets USP are dispensed, give the patient a Medication Guide and Warning Card from the carton. AUROBINDO 30 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 600 mg/300 mg (30 Tablets Container)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 600 mg/300 mg (30 Tablets Container Carton) NDC 65862-335-30 Abacavir and Lamivudine Tablets USP 600 mg / 300 mg Notice to Authorized Dispenser: Each time Abacavir and Lamivudine Tablets USP are dispensed, give the patient a Medication Guide and Warning Card from the carton. Rx only 30 Tablets AUROBINDO fig2
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL – 600 mg/300 mg (100 Unit-dose Tablets (10 x 10s)) NDC 65862-335-30 Rx only Abacavir and Lamivudine Tablets USP 600 mg / 300 mg Notice to Authorized Dispenser: Each time Abacavir and Lamivudine Tablets USP are dispensed, give the patient a Medication Guide and Warning Card from the carton. AUROBINDO 100 Unit-dose Tablets (10 x 10s) PACKAGE LABEL-PRINCIPAL DISPLAY PANEL – 600 mg/300 mg (100 Unit-dose Tablets (10 x 10s))
Medicaid utilization by pack size
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |