
Arixtra fondaparinux sodium 7.5 mg/.6mL Injection, Solution, 10 syringes
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Factor Xa Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Fondaparinux injection is used to: prevent deep vein thrombosis (DVT; a blood clot, usually in the leg) in certain conditions. treat DVT and pulmonary embolism (PE; a blood clot in the lung). Fondaparinux injection is in a class of medications called factor Xa inhibitors. It works by slowing down and stopping blood from clotting.
Read the full MedlinePlus article ↗- Fondaparinux is a blood thinner — it lowers the chance of dangerous clots forming in your veins. Doctors use it after certain surgeries (like hip or knee replacement) to prevent de...
- Yes — fondaparinux is only available as an injection given just under the skin (subcutaneous injection), usually in the abdomen. It's given once a day. It cannot be taken by mouth,...
- How do I take fondaparinux, and does it have to be a shot?
- The biggest risk with fondaparinux is bleeding, since it's a blood thinner. Common signs to look out for include unusual bruising, bleeding that takes longer than normal to stop, b...
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J1652 | $0.925 / J1652 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Fondaparinux Sodium 7.5 mg/.6mL 55111-0680-02 | Dr. | 2 syringes | $20.923 | AP | FDA listed | — |
| Fondaparinux Sodium 7.5 mg/.6mL 67457-0584-06 | Mylan | 10 syringes | $42.712 | AP | Availability likely | — |
| fondaparinux sodium 7.5 mg/.6mL 70710-1516-06 | Zydus | 10 syringes | $42.712 | AP | Availability likely | — |
| Fondaparinux Sodium 7.5 mg/.6mL 00781-3465-12 | Sandoz | 2 syringes | — | — | FDA listed | — |
| fondaparinux sodium 7.5 mg/.6mL 11797-0156-06 | Italfarmaco | 10 syringes | — | AP | FDA listed | — |
| Fondaparinux Sodium 7.5 mg/.6mL 55150-0232-02 | Eugia | 2 syringes | — | AP | FDA listed | — |
| Arixtra 7.5 mg/.6mLthis 67457-0594-06 | Mylan | 10 syringes | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 67457-0594-06 You're viewing this | 10 SYRINGE, PLASTIC in 1 CARTON (67457-594-06) / .6 mL in 1 SYRINGE, PLASTIC (67457-594-00) | 2016-02-11 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SPINAL/EPIDURAL HEMATOMAS Epidural or spinal hematomas may occur in patients who are anticoagulated with low molecular weight heparins (LMWH), heparinoids, or fondaparinux sodium and are receiving neuraxial anesthesia or undergoing spinal puncture. These hematomas may result in long-term or permanent paralysis. Consider these risks when scheduling patients for spinal procedures.
Factors that can increase the risk of developing epidural or spinal hematomas in these patients include: • use of indwelling epidural catheters • concomitant use of other drugs that affect hemostasis, such as non-steroidal anti- inflammatory drugs (NSAIDs), platelet inhibitors, or other anticoagulants • a history of traumatic or repeated epidural or spinal puncture • a history of spinal deformity or spinal surgery • Optimal timing between the administration of ARIXTRA and neuraxial procedures is not known. Monitor patients frequently for signs and symptoms of neurologic impairment.
If neurologic compromise is noted, urgent treatment is necessary. Consider the benefit and risks before neuraxial intervention in patients anticoagulated or to be anticoagulated for thromboprophylaxis [see Warnings and Precautions (5.1) and Drug Interactions (7) ] . WARNING: SPINAL/EPIDURAL HEMATOMAS See full prescribing information for complete boxed warning.
Epidural or spinal hematomas may occur in patients who are anticoagulated with low molecular weight heparins (LMWH), heparinoids, or fondaparinux sodium and are receiving neuraxial anesthesia or undergoing spinal puncture. These hematomas may result in long-term or permanent paralysis. Consider these risks when scheduling patients for spinal procedures.
Factors that can increase the risk of developing epidural or spinal hematomas in these patients include: • use of indwelling epidural catheters • concomitant use of other drugs that affect hemostasis, such as non-steroidal anti-inflammatory drugs (NSAIDs), platelet inhibitors, or other anticoagulants • a history of traumatic or repeated epidural or spinal puncture • a history of spinal deformity or spinal surgery Monitor patients frequently for signs and symptoms of neurologic impairment. If neurologic compromise is noted, urgent treatment is necessary.
Consider the benefit and risks before neuraxial intervention in patients anticoagulated or to be anticoagulated for thromboprophylaxis [see Warnings and Precautions (5.1) and Drug Interactions (7) ] .
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ARIXTRA is a Factor Xa inhibitor (anticoagulant) indicated for: • Prophylaxis of deep vein thrombosis (DVT) in adult patients undergoing hip fracture surgery (including extended prophylaxis), hip replacement surgery, knee replacement surgery, or abdominal surgery. ( 1.1 ) • Treatment of DVT or acute pulmonary embolism (PE) in adult patients when administered in conjunction with warfarin sodium. ( 1.2 , 1.3 ) • Treatment of venous thromboembolism (VTE) in pediatric patients aged 1 year or older weighing at least 10 kg.
( 1.4 )
1.1Prophylaxis of Deep Vein Thrombosis in Adult Patients ARIXTRA ® is indicated for the prophylaxis of deep vein thrombosis (DVT) in adults, which may lead to pulmonary embolism (PE): • in patients undergoing hip fracture surgery, including extended prophylaxis; • in patients undergoing hip replacement surgery; • in patients undergoing knee replacement surgery; • in patients undergoing abdominal surgery who are at risk for thromboembolic complications.
1.2Treatment of Acute Deep Vein Thrombosis in Adult Patients ARIXTRA is indicated for the treatment of acute deep vein thrombosis in adults when administered in conjunction with warfarin sodium.
1.3Treatment of Acute Pulmonary Embolism in Adult Patients ARIXTRA is indicated for the treatment of acute pulmonary embolism in adults when administered in conjunction with warfarin sodium when initial therapy is administered in the hospital.
1.4Treatment of Venous Thromboembolism in Pediatric Patients ARIXTRA is indicated for the treatment of venous thromboembolism (VTE) in pediatric patients aged 1 year or older weighing at least 10 kg.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • For subcutaneous use, do not mix with other injections or infusions. ( 2.1 ) • Prophylaxis of deep vein thrombosis in adults: ARIXTRA 2.5 mg subcutaneously once daily after hemostasis has been established. The initial dose should be given no earlier than 6 hours to 8 hours after surgery and continued for 5 days to 9 days.
For patients undergoing hip fracture surgery, extended prophylaxis up to 24 additional days is recommended. ( 2.2 , 2.3 ) • Treatment of deep vein thrombosis and pulmonary embolism in adults: ARIXTRA 5 mg (body weight less than 50 kg), 7.5 mg (50 kg to 100 kg), or 10 mg (greater than 100 kg) subcutaneously once daily. Treatment should continue for at least 5 days until INR 2 to 3 is achieved with warfarin sodium.
( 2.4 ) • Treatment of venous thromboembolism in pediatric patients weighing at least 10 kg: ARIXTRA 0.1 mg/kg subcutaneously once daily. ( 2.5 )
2.1Important Dosing Information Do not mix other medications or solutions with ARIXTRA. Administer ARIXTRA only subcutaneously. Discard unused portion. Monitor routine complete blood counts (including platelet count), serum creatinine level, and stool occult blood periodically [see Warnings and Precautions (5.6) ] .
2.2Deep Vein Thrombosis Prophylaxis Following Hip Fracture, Hip Replacement, and Knee Replacement Surgery in Adults In adult patients undergoing hip fracture, hip replacement, or knee replacement surgery, the recommended dose of ARIXTRA is 2.5 mg administered by subcutaneous injection once daily after hemostasis has been established. Administer the initial dose no earlier than 6 hours to 8 hours after surgery. Administration of ARIXTRA earlier than 6 hours after surgery increases the risk of major bleeding.
The usual duration of therapy is 5 days to 9 days; up to 11 days of therapy was administered in clinical trials. In patients undergoing hip fracture surgery, an extended prophylaxis course of up to 24 additional days is recommended. In patients undergoing hip fracture surgery, a total of 32 days (peri-operative and extended prophylaxis) was administered in clinical trials [see Warnings and Precautions (5.6) , Adverse Reactions (6) , and Clinical Studies (14) ] .
2.3Deep Vein Thrombosis Prophylaxis Following Abdominal Surgery in Adults In adult patients undergoing abdominal surgery, the recommended dose of ARIXTRA is 2.5 mg administered by subcutaneous injection once daily after hemostasis has been established. Administer the initial dose no earlier than 6 hours to 8 hours after surgery. Administration of ARIXTRA earlier than 6 hours after surgery increases the risk of major bleeding.
The usual duration of administration is 5 days to 9 days, and up to 10 days of ARIXTRA was administered in clinical trials.
2.4Deep Vein Thrombosis and Pulmonary Embolism Treatment in Adults In adult patients with acute symptomatic DVT and in patients with acute symptomatic PE, the recommended dose of ARIXTRA is 5 mg (body weight less than 50 kg), 7.5 mg (body weight 50 kg to 100 kg), or 10 mg (body weight greater than 100 kg) by subcutaneous injection once daily (ARIXTRA treatment regimen). Initiate concomitant treatment with warfarin sodium as soon as possible, usually within 72 hours. Continue treatment with ARIXTRA for at least 5 days and until a therapeutic oral anticoagulant effect is established (INR 2 to 3).
The usual duration of administration of ARIXTRA is 5 days to 9 days; up to 26 days of ARIXTRA injection was administered in clinical trials [see Warnings and Precautions (5.6) , Adverse Reactions (6) , and Clinical Studies (14) ] .
2.5Venous Thromboembolism Treatment in Pediatric Patients Aged 1 Year or Older Weighing at Least 10 kg For patients weighing 10 kg to 20 kg, the recommended initial dose is 0.1 mg/kg subcutaneously once daily. There is no available prefilled syringe for patients in this weight range, and a patient specific dose should be prepared ( see section
2.8 Instructions for Preparation of Individual…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: Single-dose, prefilled syringes containing clear to practically clear and colorless liquid containing either 2.5 mg/0.5 mL, 5 mg/0.4 mL, 7.5 mg/0.6 mL, or 10 mg/0.8 mL of fondaparinux sodium. Single-dose, prefilled syringes containing 2.5 mg/0.5 mL, 5 mg/0.4 mL, 7.5 mg/0.6 mL, or 10 mg/0.8 mL of fondaparinux sodium. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS ARIXTRA is contraindicated in the following conditions: • Severe renal impairment (creatinine clearance [CrCl] less than 30 mL/min) [see Warnings and Precautions (5.3) and Use in Specific Populations (8.6) ] . • Active major bleeding. • Bacterial endocarditis. • Thrombocytopenia associated with a positive in vitro test for anti-platelet antibody in the presence of fondaparinux sodium. • Body weight less than 50 kg (venous thromboembolism [VTE] prophylaxis in adults only) [see Warnings and Precautions (5.4) ] . • History of serious hypersensitivity reaction (e.g., angioedema, anaphylactoid/anaphylactic reactions) to ARIXTRA.
ARIXTRA is contraindicated in the following conditions: ( 4 ) • Severe renal impairment (creatinine clearance less than 30 mL/min) in prophylaxis or treatment of venous thromboembolism. • Active major bleeding. • Bacterial endocarditis. • Thrombocytopenia associated with a positive in vitro test for anti-platelet antibody in the presence of fondaparinux sodium. • Body weight less than 50 kg (venous thromboembolism prophylaxis in adults only). • History of serious hypersensitivity reaction (e.g., angioedema, anaphylactoid/anaphylactic reactions) to ARIXTRA.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Spinal or epidural hematomas, which may result in long-term or permanent paralysis, can occur. ( 5.1 ) • Patients taking ARIXTRA with risk factors for bleeding are at increased risk of hemorrhage. ( 5.2 ) • Bleeding risk is increased in renal impairment and in adult patients with low body weight less than 50 kg.
( 5.3 , 5.4 ) • Thrombocytopenia can occur with administration of ARIXTRA. ( 5.5 ) • Periodic routine complete blood counts (including platelet counts), serum creatinine level, and stool occult blood tests are recommended. ( 5.6 ) • The packaging (needle guard) contains dry natural rubber and may cause allergic reactions in latex sensitive individuals.
( 5.7 )
5.1Neuraxial Anesthesia and Post-operative Indwelling Epidural Catheter Use Spinal or epidural hematomas, which may result in long-term or permanent paralysis, can occur with the use of anticoagulants and neuraxial (spinal/epidural) anesthesia or spinal puncture. The risk of these events may be higher with post-operative use of indwelling epidural catheters or concomitant use of other drugs affecting hemostasis such as NSAIDs [see Boxed Warning ] . In the postmarketing experience, epidural or spinal hematoma has been reported in association with the use of ARIXTRA by subcutaneous (SC) injection.
Optimal timing between the administration of ARIXTRA and neuraxial procedures is not known. Monitor patients undergoing these procedures for signs and symptoms of neurologic impairment such as midline back pain, sensory and motor deficits (numbness, tingling, or weakness in lower limbs), and bowel or bladder dysfunction. Consider the potential risks and benefits before neuraxial intervention in patients anticoagulated or who may be anticoagulated for thromboprophylaxis.
5.2Hemorrhage ARIXTRA increases the risk of hemorrhage in patients at risk for bleeding, including conditions such as congenital or acquired bleeding disorders, active ulcerative and angiodysplastic gastrointestinal disease, hemorrhagic stroke, uncontrolled arterial hypertension, diabetic retinopathy, or shortly after brain, spinal, or ophthalmological surgery. Cases of elevated aPTT temporally associated with bleeding events have been reported following administration of ARIXTRA (with or without concomitant administration of other anticoagulants) [see Adverse Reactions (6.2) ] .
Conditions associated with increased bleeding in pediatric patients include systemic lupus erythematosus, Wilms tumor, antiphospholipid syndrome, antithrombin III deficiency, Factor V Leiden, malignancy, pancytopenia, indwelling chest tubes, thoracotomy, invasive infections, hypertensive encephalopathy, intestinal lymphangiectasia and von Willebrand disease. Do not administer agents that enhance the risk of hemorrhage with ARIXTRA unless essential for the management of the underlying condition, such as vitamin K antagonists for the treatment of VTE.
If co-administration is essential, closely monitor patients for signs and symptoms of bleeding. Do not administer the initial dose of ARIXTRA earlier than 6 to 8 hours after surgery. Administration earlier than 6 hours after surgery increases risk of major bleeding [see Dosage and Administration (2) and Adverse Reactions (6.1) ] .
5.3Renal Impairment and Bleeding Risk in Adult Patients ARIXTRA increases the risk of bleeding in adult patients with impaired renal function due to reduced clearance [see Clinical Pharmacology (12.4) ] . The incidence of major bleeding by renal function status reported in clinical trials of adult patients receiving ARIXTRA for VTE surgical prophylaxis is provided in Table 4. In these patient populations, the following is recommended: • Do not use ARIXTRA for VTE prophylaxis and treatment in patients with CrCl less than 30 mL/min [see Contraindications (4) ] . • ARIXTRA may cause prolonged anticoagulation in patients with CrCl 30 mL/min to 50 mL/min.
Table 4. Incidence of Major Bleeding in Adult Patients Treated with ARIXTRA by…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: • Spinal or epidural hematomas [see Warnings and Precautions (5.1) ] • Hemorrhage [see Warnings and Precautions (5.2) ] • Renal impairment and bleeding risk [see Warnings and Precautions (5.3) ] • Body weight less than 50 kg and bleeding risk [see Warnings and Precautions (5.4) ] • Thrombocytopenia [see Warnings and Precautions (5.5) ] The most serious adverse reactions associated with the use of ARIXTRA are bleeding complications.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Mylan at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Clinical Trials Experience in Adults The adverse reaction information below is based on data from 8,877 patients exposed to ARIXTRA in controlled trials of hip fracture, hip replacement, major knee, or abdominal surgeries, and DVT and PE treatment.
Hemorrhage During administration of ARIXTRA, the most common adverse reactions were bleeding complications [see Warnings and Precautions (5.2) ] . Hip Fracture, Hip Replacement, and Knee Replacement Surgery The rates of major bleeding events reported during 3 active-controlled peri-operative VTE prophylaxis trials with enoxaparin sodium in hip fracture, hip replacement, or knee replacement surgery (N = 3,616) and in an extended VTE prophylaxis trial (n = 327) with ARIXTRA 2.5 mg are provided in Table 5. Table 5.
Bleeding Across Randomized, Controlled Hip Fracture, Hip Replacement, and Knee Replacement Surgery Studies Peri-Operative Prophylaxis (Day 1 to Day 7 ± 1 post-surgery) Extended Prophylaxis (Day 8 to Day 28 ± 2 post-surgery) ARIXTRA 2.5 mg subcutaneously once daily N = 3,616 Enoxaparin Sodium Enoxaparin sodium dosing regimen: 30 mg every 12 hours or 40 mg once daily. , Not approved for use in patients undergoing hip fracture surgery. N = 3,956 ARIXTRA 2.5 mg subcutaneously once daily N = 327 Placebo subcutaneously once daily N = 329 Major bleeding Major bleeding was defined as clinically overt bleeding that was (1) fatal, (2) bleeding at critical site (e.g., intracranial, retroperitoneal, intraocular, pericardial, spinal, or into adrenal gland), (3) associated with re-operation at operative site, or (4) with a bleeding index (BI) greater than or equal to 2.
96 (2.7%) 75 (1.9%) 8 (2.4%) 2 (0.6%) Hip fracture 18/831 (2.2%) 19/842 (2.3%) 8/327 (2.4%) 2/329 (0.6%) Hip replacement 67/2,268 (3.0%) 55/2,597 (2.1%) — — Knee replacement 11/517 (2.1%) 1/517 (0.2%) — — Fatal bleeding 0 (0%) 1 (less than 0.1%) 0 (0%) 0 (0%) Non-fatal bleeding at critical site 0 (0%) 1 (less than 0.1%) 0 (0%) 0 (0%) Re-operation due to bleeding 12 (0.3%) 10 (0.3%) 2 (0.6%) 2 (0.6%) BI greater than or equal to 2 BI greater than or equal to 2: Overt bleeding associated only with a bleeding index (BI) greater than or equal to 2 calculated as [number of whole blood or packed red blood cell units transfused + [(pre-bleeding) – (post-bleeding)] hemoglobin (g/dL) values].
84 (2.3%) 63 (1.6%) 6 (1.8%) 0 (0%) Minor bleeding Minor bleeding was defined as clinically overt bleeding that was not major. 109 (3%) 116 (2.9%) 5 (1.5%) 2 (0.6%) A separate analysis of major bleeding across all randomized, controlled, peri-operative, prophylaxis clinical studies of hip fracture, hip replacement, or knee replacement surgery according to the time of the first injection of ARIXTRA after surgical closure was performed in patients who received ARIXTRA only post-operatively. In this analysis, the incidences of major bleeding were as follows: less than 4 hours was 4.8% (5/104), 4 to 6 hours was 2.3% (28/1,196), 6 to 8 hours was 1.9% (38/1,965).
In all studi…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS In clinical studies performed with ARIXTRA, the concomitant use of oral anticoagulants (warfarin sodium), platelet inhibitors (acetylsalicylic acid), NSAIDs (piroxicam), and digoxin did not significantly affect the pharmacokinetics/pharmacodynamics of fondaparinux sodium. In addition, ARIXTRA neither influenced the pharmacodynamics of warfarin sodium, acetylsalicylic acid, piroxicam, and digoxin, nor the pharmacokinetics of digoxin at steady state. Agents that may enhance the risk of hemorrhage should be discontinued prior to initiation of therapy with ARIXTRA unless these agents are essential.
If co-administration is necessary, monitor patients closely for hemorrhage [see Warnings and Precautions (5.2) ] . In an in vitro study in human liver microsomes, inhibition of CYP2A6 hydroxylation of coumarin by fondaparinux (200 micromolar i.e., 350 mg/L) was 17% to 28%. Inhibition of the other isozymes evaluated (CYPs 1A2, 2C9, 2C19, 2D6, 3A4, and 3E1) was 0% to 16%.
Since fondaparinux does not markedly inhibit CYP450s (CYP1A2, CYP2A6, CYP2C9, CYP2C19, CYP2D6, CYP2E1, or CYP3A4) in vitro , fondaparinux sodium is not expected to significantly interact with other drugs in vivo by inhibition of metabolism mediated by these isozymes. Since fondaparinux sodium does not bind significantly to plasma proteins other than ATIII, no drug interactions by protein-binding displacement are expected. Discontinue agents that may enhance the risk of hemorrhage prior to initiation of therapy with ARIXTRA unless essential.
If co-administration is necessary, monitor patients closely for hemorrhage. ( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Because elderly patients are more likely to have reduced renal function, ARIXTRA should be used with caution in these patients. ( 8.5 ) • The risk of bleeding is increased with reduced renal or hepatic function. ( 8.6 , 8.7 )
8.1Pregnancy Risk Summary Available data from published literature and postmarketing reports have not reported a clear association with fondaparinux sodium and adverse developmental outcomes. Fondaparinux sodium plasma concentrations obtained from four women treated with ARIXTRA during pregnancy and their newborn infants demonstrated low placental transfer of fondaparinux sodium (see Data ) . There are risks to the mother associated with untreated venous thromboembolism in pregnancy and a risk of hemorrhage in the mother and fetus associated with use of anticoagulants (see Clinical Considerations ) .
In animal reproduction studies, there was no evidence of adverse developmental outcomes when fondaparinux sodium was administered to pregnant rats and rabbits during organogenesis at doses 32 times and 65 times, respectively, the recommended human dose based on body surface area. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Pregnancy confers an increased risk for thromboembolism that is higher for women with underlying thromboembolic disease and certain high-risk pregnancy conditions. Published data describe that women with a previous history of venous thrombosis are at high risk for recurrence during pregnancy.
Fetal/Neonatal Adverse Reactions Fondaparinux sodium has been demonstrated to cross the placenta in humans (see Data ) . Use of anticoagulants, including fondaparinux sodium, may increase the risk of bleeding in the fetus and neonate. Monitor neonates for bleeding [see Warnings and Precautions (5.2 , 5.4 , 5.6) ] .
Labor or Delivery All patients receiving anticoagulants, including pregnant women, are at risk for bleeding. Fondaparinux sodium use during labor or delivery in women who are receiving neuraxial anesthesia may result in epidural or spinal hematomas. Pregnant women receiving fondaparinux sodium should be carefully monitored for evidence of bleeding or unexpected changes in coagulation parameters.
Consideration for use of a shorter acting anticoagulant should be specifically addressed as delivery approaches [see Warnings and Precautions (5.1 , 5.6) ] . Data Human Data In a study of five pregnant women treated with fondaparinux sodium during the third trimester of pregnancy at a dose of 2.5 mg/day, four of the women had elevated anti-factor Xa activity noted in the cord blood. Anti-factor Xa clotting times in these four cases were between 37.5 seconds and 50.9 seconds.
The patient who did not have elevated anti-factor Xa activity had received only one dose of fondaparinux sodium 22 hours prior to delivery. The concentration of fondaparinux sodium in umbilical cord plasma was approximately 1/10 th the level of fondaparinux sodium in maternal plasma. None of the infants experienced adverse effects.
Animal Data Embryo-fetal development studies have been conducted with fondaparinux sodium in pregnant rats at subcutaneous doses up to 10 mg/kg/day (about 32 times the recommended human dose based on body surface area) administered from days 6 to 17 of gestation and pregnant rabbits at subcutaneous doses up to 10 mg/kg/day (about 65 times the recommended human dose based on body surface area) administered from days 6 to 18 of gestation. These studies have revealed no evidence of adverse developmental outcomes when fondaparinux sodium was administered to pregnant rat…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from published literature and postmarketing reports have not reported a clear association with fondaparinux sodium and adverse developmental outcomes. Fondaparinux sodium plasma concentrations obtained from four women treated with ARIXTRA during pregnancy and their newborn infants demonstrated low placental transfer of fondaparinux sodium (see Data ) . There are risks to the mother associated with untreated venous thromboembolism in pregnancy and a risk of hemorrhage in the mother and fetus associated with use of anticoagulants (see Clinical Considerations ) .
In animal reproduction studies, there was no evidence of adverse developmental outcomes when fondaparinux sodium was administered to pregnant rats and rabbits during organogenesis at doses 32 times and 65 times, respectively, the recommended human dose based on body surface area. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Pregnancy confers an increased risk for thromboembolism that is higher for women with underlying thromboembolic disease and certain high-risk pregnancy conditions. Published data describe that women with a previous history of venous thrombosis are at high risk for recurrence during pregnancy.
Fetal/Neonatal Adverse Reactions Fondaparinux sodium has been demonstrated to cross the placenta in humans (see Data ) . Use of anticoagulants, including fondaparinux sodium, may increase the risk of bleeding in the fetus and neonate. Monitor neonates for bleeding [see Warnings and Precautions (5.2 , 5.4 , 5.6) ] .
Labor or Delivery All patients receiving anticoagulants, including pregnant women, are at risk for bleeding. Fondaparinux sodium use during labor or delivery in women who are receiving neuraxial anesthesia may result in epidural or spinal hematomas. Pregnant women receiving fondaparinux sodium should be carefully monitored for evidence of bleeding or unexpected changes in coagulation parameters.
Consideration for use of a shorter acting anticoagulant should be specifically addressed as delivery approaches [see Warnings and Precautions (5.1 , 5.6) ] . Data Human Data In a study of five pregnant women treated with fondaparinux sodium during the third trimester of pregnancy at a dose of 2.5 mg/day, four of the women had elevated anti-factor Xa activity noted in the cord blood. Anti-factor Xa clotting times in these four cases were between 37.5 seconds and 50.9 seconds.
The patient who did not have elevated anti-factor Xa activity had received only one dose of fondaparinux sodium 22 hours prior to delivery. The concentration of fondaparinux sodium in umbilical cord plasma was approximately 1/10 th the level of fondaparinux sodium in maternal plasma. None of the infants experienced adverse effects.
Animal Data Embryo-fetal development studies have been conducted with fondaparinux sodium in pregnant rats at subcutaneous doses up to 10 mg/kg/day (about 32 times the recommended human dose based on body surface area) administered from days 6 to 17 of gestation and pregnant rabbits at subcutaneous doses up to 10 mg/kg/day (about 65 times the recommended human dose based on body surface area) administered from days 6 to 18 of gestation. These studies have revealed no evidence of adverse developmental outcomes when fondaparinux sodium was administered to pregnant rats and rabbits during organogenesis.
Additionally, there were no effects on pre- and postnatal development in a study conducted in rats at subcutaneous doses up to 10 mg/kg/day (about 32 times the recommended human dose based on body surface area).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of ARIXTRA for the treatment of venous thromboembolism have been established in pediatric patients aged 1 year and older weighing at least 10 kg. Use of ARIXTRA for this indication is supported by evidence from adequate and well-controlled studies in adults with additional pharmacokinetic, pharmacodynamic, safety, and efficacy data in pediatric patients aged 0.3 years and older [see Adverse Reactions (6.1) , Clinical Pharmacology (12.4) , and Clinical Studies (14.8) ] .
The frequency, type, and severity of adverse reactions observed were generally consistent with those observed in adults. The safety and effectiveness of ARIXTRA have not been established in pediatric patients for the treatment of venous thromboembolism who are younger than 1 year old, weigh less than 10 kg, or with any category of renal or hepatic impairment. The safety and effectiveness of ARIXTRA have not been established in pediatric patients for the prophylaxis of DVT and treatment of DVT or PE in conjunction with warfarin sodium.
🧓 Geriatric Use ▾
8.5Geriatric Use Over 3,000 patients 65 years and older have received ARIXTRA in randomized clinical trials for the treatment or prophylaxis of DVT and PE. There were over 2,000 patients 65 years of age and older in the orthopedic surgery clinical studies for prophylaxis of DVT and PE [see Clinical Studies (14) ] . Of the total number of ARIXTRA-treated patients in these orthopedic surgery studies, 1,111 (30.9%) were 65 years of age to 74 years of age, while 1,227 (34.2%) were 75 years of age and older.
No overall differences in effectiveness of ARIXTRA have been observed between patients 65 years of age and older and younger adult patients. Serious adverse events were more frequent in patients 65 years of age and older. When using ARIXTRA in elderly patients, pay particular attention to dosing directions and concomitant medications (especially anti-platelet medication) [see Warnings and Precautions (5.2) ] .
Fondaparinux sodium is substantially excreted by the kidney, and the risk of adverse reactions to ARIXTRA may be greater in patients with impaired renal function. Because geriatric patients are more likely to have decreased renal function, assess renal function prior to ARIXTRA administration [see Contraindications (4) , Warnings and Precautions (5.3) , and Clinical Pharmacology (12.4) ] . In the peri-operative hip fracture, hip replacement, or knee replacement surgery clinical trials with patients receiving ARIXTRA 2.5 mg, serious adverse events increased with age for patients receiving ARIXTRA.
The incidence of major bleeding in clinical trials of ARIXTRA by age is provided in Table 9. Table 9. Incidence of Major Bleeding in Patients Treated with ARIXTRA by Age Age Less than 65 years % (n/N) 65 years to 74 years % (n/N) Greater than or equal to 75 years % (n/N) Orthopedic surgery Includes hip fracture, hip replacement, and knee replacement surgery prophylaxis.
1.8% (23/1,253) 2.2% (24/1,111) 2.7% (33/1,277) Extended prophylaxis 1.9% (1/52) 1.4% (1/71) 2.9% (6/204) Abdominal surgery 3% (19/644) 3.2% (16/507) 5% (14/282) DVT and PE treatment 0.6% (7/1,151) 1.6% (9/560) 2.1% (12/583)
🆘 Overdosage ▾
10 OVERDOSAGE Overdose of ARIXTRA may lead to hemorrhagic complications. Discontinue treatment and initiate appropriate therapy if bleeding complications associated with overdosage occur. There is no known antidote for ARIXTRA. Data obtained in patients undergoing chronic intermittent hemodialysis suggest that clearance of ARIXTRA can increase by 20% during hemodialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The antithrombotic activity of fondaparinux sodium is the result of antithrombin III (ATIII)-mediated selective inhibition of Factor Xa. By selectively binding to ATIII, fondaparinux sodium potentiates (about 300 times) the innate neutralization of Factor Xa by ATIII. Neutralization of Factor Xa interrupts the blood coagulation cascade and thus inhibits thrombin formation and thrombus development.
Fondaparinux sodium does not inactivate thrombin (activated Factor II) and has no known effect on platelet function. At the recommended dose, fondaparinux sodium does not affect fibrinolytic activity or bleeding time.
12.2Pharmacodynamics Anti-Xa Activity The pharmacodynamics/pharmacokinetics of fondaparinux sodium are derived from fondaparinux plasma concentrations quantified via anti-Factor Xa activity. Only fondaparinux can be used to calibrate the anti-Xa assay. (The international standards of heparin or LMWH are not appropriate for this use.) As a result, the activity of fondaparinux sodium is expressed as milligrams (mg) of the fondaparinux calibrator.
The anti-Xa activity of the drug increases with increasing drug concentration, reaching maximum values in approximately three hours.
12.3Pharmacokinetics Absorption Fondaparinux sodium administered by subcutaneous injection is rapidly and completely absorbed (absolute bioavailability is 100%). Following a single subcutaneous dose of fondaparinux sodium 2.5 mg in young male subjects, C max of 0.34 mg/L is reached in approximately 2 hours. In patients undergoing treatment with fondaparinux sodium injection 2.5 mg, once daily, the peak steady-state plasma concentration is, on average, 0.39 mg/L to 0.5 mg/L and is reached approximately 3 hours post-dose.
In these patients, the minimum steady-state plasma concentration is 0.14 mg/L to 0.19 mg/L. In patients with symptomatic deep vein thrombosis and pulmonary embolism undergoing treatment with fondaparinux sodium injection 5 mg (body weight less than 50 kg), 7.5 mg (body weight 50 kg to 100 kg), and 10 mg (body weight greater than 100 kg) once daily, the body-weight-adjusted doses provide similar mean steady-state peaks and minimum plasma concentrations across all body weight categories. The mean peak steady-state plasma concentration is in the range of 1.20 mg/L to 1.26 mg/L.
In these patients, the mean minimum steady-state plasma concentration is in the range of 0.46 mg/L to 0.62 mg/L. Distribution In healthy adults, intravenously or subcutaneously administered fondaparinux sodium distributes mainly in blood and only to a minor extent in extravascular fluid as evidenced by steady state and non-steady state apparent volume of distribution of 7 L to 11 L. Similar fondaparinux distribution occurs in patients undergoing elective hip surgery or hip fracture surgery.
In vitro , fondaparinux sodium is highly (at least 94%) and specifically bound to antithrombin III (ATIII) and does not bind significantly to other plasma proteins (including platelet Factor 4 [PF4]) or red blood cells. Metabolism In vivo metabolism of fondaparinux has not been investigated since the majority of the administered dose is eliminated unchanged in urine in individuals with normal kidney function. Elimination In individuals with normal kidney function, fondaparinux is eliminated in urine mainly as unchanged drug.
In healthy individuals up to 75 years of age, up to 77% of a single subcutaneous or intravenous fondaparinux dose is eliminated in urine as unchanged drug in 72 hours. The elimination half-life is 17 hours to 21 hours.
12.4Special Populations Renal Impairment Fondaparinux elimination is prolonged in patients with renal impairment since the major route of elimination is urinary excretion of unchanged drug. In patients undergoing prophylaxis following elective hip surgery or hip fracture surgery, the total clearance of fondaparinux is approximately 25% lower in patients with mild renal impairment (CrCl 50…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The antithrombotic activity of fondaparinux sodium is the result of antithrombin III (ATIII)-mediated selective inhibition of Factor Xa. By selectively binding to ATIII, fondaparinux sodium potentiates (about 300 times) the innate neutralization of Factor Xa by ATIII. Neutralization of Factor Xa interrupts the blood coagulation cascade and thus inhibits thrombin formation and thrombus development.
Fondaparinux sodium does not inactivate thrombin (activated Factor II) and has no known effect on platelet function. At the recommended dose, fondaparinux sodium does not affect fibrinolytic activity or bleeding time.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING ARIXTRA (fondaparinux sodium injection, USP) is available in single-dose, prefilled syringes containing clear to practically clear and colorless liquid in the following strengths: 2.5 mg/0.5 mL ARIXTRA in single-dose prefilled syringe, affixed with a 27-gauge x ½-inch needle and an automatic needle protection system with white plunger rod. NDC 67457-592-10 10 Single Unit Syringes 5 mg/0.4 mL ARIXTRA in single-dose prefilled syringe, affixed with a 27-gauge x ½-inch needle and an automatic needle protection system with white plunger rod.
NDC 67457-593-04 10 Single Unit Syringes 7.5 mg/0.6 mL ARIXTRA in single-dose prefilled syringe, affixed with a 27-gauge x ½-inch needle and an automatic needle protection system with white plunger rod. NDC 67457-594-06 10 Single Unit Syringes 10 mg/0.8 mL ARIXTRA in single-dose prefilled syringe, affixed with a 27-gauge x ½-inch needle and an automatic needle protection system with white plunger rod. NDC 67457-595-08 10 Single Unit Syringes Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [See USP Controlled Room Temperature].
Discard unused portion. PHARMACIST: Dispense a Patient Information Leaflet with each prescription.
📋 Description ▾
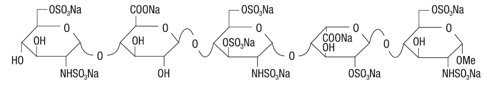
11 DESCRIPTION ARIXTRA (fondaparinux sodium injection, USP) is a sterile solution containing fondaparinux sodium. It is a synthetic and specific inhibitor of activated Factor X (Xa). Fondaparinux sodium is methyl O -2-deoxy-6- O -sulfo-2-(sulfoamino)-α-D-glucopyranosyl-(1→4)- O -β-D-glucopyra-nuronosyl-(1→4)- O -2-deoxy-3,6-di- O -sulfo-2-(sulfoamino)-α-D-glucopyranosyl-(1→4)- O -2- O -sulfo-α-L-idopyranuronosyl-(1→4)-2-deoxy-6- O -sulfo-2-(sulfoamino)-α-D-glucopyranoside, decasodium salt.
The molecular formula of fondaparinux sodium is C 31 H 43 N 3 Na 10 O 49 S 8 and its molecular weight is 1728. The structural formula is provided below: ARIXTRA is supplied as a sterile, preservative-free injectable solution for subcutaneous use. Each single-dose, prefilled syringe of ARIXTRA, affixed with an automatic needle protection system, contains 2.5 mg of fondaparinux sodium in 0.5 mL, 5 mg of fondaparinux sodium in 0.4 mL, 7.5 mg of fondaparinux sodium in 0.6 mL, or 10 mg of fondaparinux sodium in 0.8 mL of an isotonic solution of sodium chloride and water for injection.
May also contain sodium hydroxide and/or hydrochloric acid as pH adjusters. The final drug product is a clear and colorless to slightly yellow liquid with a pH between 5 and 8. fondaparinux sodium structural formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information and Instructions for Use ) .
17.1Patient Advice If the patients have had neuraxial anesthesia or spinal puncture, and particularly, if they are taking concomitant NSAIDS, platelet inhibitors, or other anticoagulants, inform patients to watch for signs and symptoms of spinal or epidural hematomas, such as back pain, tingling, numbness (especially in the lower limbs), muscular weakness, and stool or urine incontinence. If any of these symptoms occur, advise patients to contact his or her physician immediately. The use of aspirin and other NSAIDS may enhance the risk of hemorrhage.
Advise patients to discontinue use prior to ARIXTRA therapy whenever possible; if co-administration is essential, the patient’s clinical and laboratory status should be closely monitored [see Drug Interactions (7) ] . If patients must self-administer ARIXTRA or if administered by a caregiver, (e.g., if ARIXTRA is used at home), advise patients of the following: • Advise patients that ARIXTRA should be given by subcutaneous injection. Instruct patients in the proper technique for administration. • Instruct patients that if they miss a dose of ARIXTRA, to inject the dose as soon as they remember.
Advise patients not to inject two doses at the same time. • The most important risk with ARIXTRA administration is bleeding. Counsel patients on signs and symptoms of possible bleeding. • Advise patients that it may take them longer than usual to stop bleeding. • Advise patients that they may bruise and/or bleed more easily when they are treated with ARIXTRA. • Advise patients to report any unusual bleeding, bruising, or signs of thrombocytopenia (such as a rash of dark red spots under the skin) to their physician [see Warnings and Precautions (5.2 , 5.5) ] . • Advise patients to tell their physicians and dentists they are taking ARIXTRA and/or any other product known to affect bleeding before any surgery is scheduled and before any new drug is taken [see Warnings and Precautions (5.2) ] . • Advise patients to tell their physicians and dentists of all medications they are taking, including those obtained without a prescription, such as aspirin or other NSAIDs [see Drug Interactions (7) ] .
Manufactured for: Mylan Institutional LLC Morgantown, WV 26505 U.S.A. Manufactured by: Aspen Notre Dame de Bondeville Notre Dame de Bondeville, France MI:ARXTIJ:R7p