
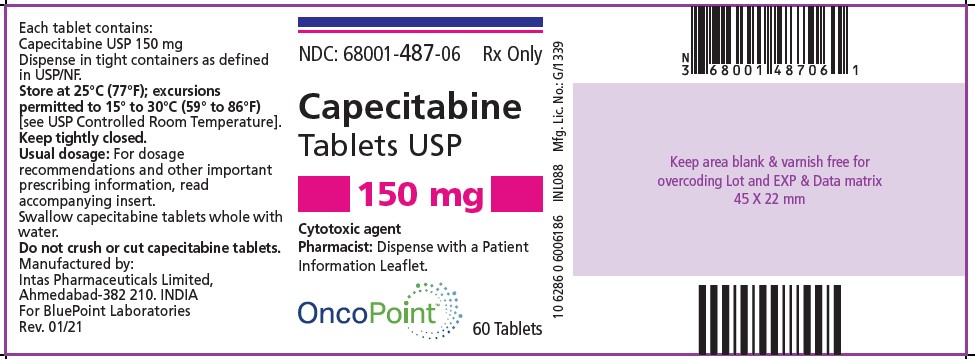
CAPECITABINE 150 mg Tablet, Film Coated, 60-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Nucleoside Metabolic Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Taking capecitabine with food helps slow down absorption in a way that's actually built into how your dosing is set up. Studies show that eating a meal before your dose affects how...
- Why do I need to take capecitabine with food?
- Hand-and-foot syndrome — also called palmar-plantar erythrodysesthesia — is one of the most common side effects of capecitabine. It causes redness, tenderness, swelling, or peeling...
- What is hand-and-foot syndrome and what should I do if it happens?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Capecitabine — tap one for details:
Capecitabine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII R75537T0T4
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. It serves as a binder that holds tablet ingredients together, a film-coating for pills, and a viscosity controller in liquids.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.362 | $21.69 / 60 tablets |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · NONE | No ASP payment limit on file for NONE this quarter. | |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Capecitabine 150 mg 00093-7473-06 | Teva | 60 tablets | $0.362 | AB | Availability likely | — |
| Capecitabine 150 mg 16729-0072-12 | Accord | 60 tablets | $0.362 | AB | Availability likely | — |
| capecitabine 150 mg 31722-0774-60 | Camber | 60 tablets | $0.362 | AB | Availability likely | — |
| Capecitabine 150 mgthis 68001-0487-06 | BluePoint | 60 tablets | $0.362 | AB | Availability likely | — |
| Capecitabine 150 mg 68001-0643-06 | BluePoint | 60 tablets | $0.362 | AB | Availability likely | — |
| Capecitabine 150 mg 69097-0949-03 | Cipla | 60 tablets | $0.362 | AB | Availability likely | — |
| Capecitabine 150 mg 70756-0815-60 | Lifestar | 60 tablets | $0.362 | AB | Availability likely | — |
| Capecitabine 150 mg 72205-0006-60 | Novadoz | 60 tablets | $0.362 | AB | Availability likely | — |
| Capecitabine 150 mg 82249-0207-60 | CivicaScript | 60 tablets | $0.362 | AB | Availability likely | — |
| Capecitabine 150 mg 51407-0639-60 | Golden | 60 tablets | — | AB | FDA listed | — |
| capecitabine 150 mg 55111-0496-05 | Dr. | 500 tablets | — | AB | FDA listed | — |
| Capecitabine 150 mg 59651-0204-10 | Aurobindo | 10 tablets | — | AB | FDA listed | — |
| Capecitabine 150 mg 62756-0238-18 | Sun | 1000 tablets | — | — | FDA listed | — |
| Capecitabine 150 mg 67877-0458-12 | Ascend | 120 tablets | — | AB | FDA listed | — |
| Capecitabine 150mg 150 mg 72485-0204-60 | Armas | 60 tablets | — | AB | FDA listed | — |
| Capecitabine 150 mg 82511-0001-15 | Teyro | 60 tablets | — | BX | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 68001-0487-06 You're viewing this | 60 TABLET, FILM COATED in 1 BOTTLE, PLASTIC (68001-487-06) | 2021-02-22 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
Clinically significant increases in prothrombin time (PT) and international normalized ratio (INR) have been reported in patients who were on stable doses of a vitamin K antagonist at the time capecitabine was introduced. These events occurred within several days and up to several months after initiating capecitabine and, in a few cases, within 1 month after stopping capecitabine. These events occurred in patients with and without liver metastases.
Monitor INR more frequently and adjust the dose of the vitamin K antagonist as appropriate [see Drug Interactions (7.2)]. WARNING: INCREASED RISK OF BLEEDING WITH CONCOMITANT USE OF VITAMIN K ANTAGONISTS See full prescribing information for complete boxed warning. Altered coagulation parameters and/or bleeding, including death, have been reported in patients taking capecitabine concomitantly with oral vitamin K antagonists.
(5.1, 7.2) Monitor international normalized ratio (INR) more frequently and adjust the dose of the vitamin K antagonist as appropriate. (7.2)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Capecitabine is a nucleoside metabolic inhibitor indicated for: Colorectal Cancer ● adjuvant treatment of patients with Stage III colon cancer as a single agent or as a component of a combination chemotherapy regimen. ( 1.1 ) ● perioperative treatment of adults with locally advanced rectal cancer as a component of chemoradiotherapy.( 1.1 ) ● treatment of patients with unresectable or metastatic colorectal cancer as a single agent or as a component of a combination chemotherapy regimen. ( 1.1 ) Breast Cancer ● treatment of patients with advanced or metastatic breast cancer as a single agent if an anthracycline- or taxane-containing chemotherapy is not indicated.
( 1.2 ) ● treatment of patients with advanced or metastatic breast cancer in combination with docetaxel after disease progression on prior anthracycline-containing chemotherapy. ( 1.2 ) Gastric, Esophageal, or Gastroesophageal Junction Cancer ● treatment of adults with unresectable or metastatic gastric, esophageal, or gastroesophageal junction cancer as a component of a combination chemotherapy regimen. ( 1.3 ) ● treatment of adults with HER2-overexpressing metastatic gastric or gastroesophageal junction adenocarcinoma who have not received prior treatment for metastatic disease as a component of a combination regimen.
( 1.3 ) Pancreatic Cancer ● adjuvant treatment of adults with pancreatic adenocarcinoma as a component of a combination chemotherapy regimen. ( 1.4 )
1.1Colorectal Cancer Capecitabine tablets, USP are indicated for the: ● adjuvant treatment of patients with Stage III colon cancer as a single agent or as a component of a combination chemotherapy regimen. ● perioperative treatment of adults with locally advanced rectal cancer as a component of chemoradiotherapy. ● treatment of patients with unresectable or metastatic colorectal cancer as a single agent or as a component of a combination chemotherapy regimen.
1.2Breast Cancer Capecitabine tablets USP are indicated for the: ● treatment of patients with advanced or metastatic breast cancer as a single agent if an anthracycline- or taxane-containing chemotherapy is not indicated. ● treatment of patients with advanced or metastatic breast cancer in combination with docetaxel after disease progression on prior anthracycline-containing chemotherapy.
1.3Gastric, Esophageal, or Gastroesophageal Junction Cancer Capecitabine tablets USP are indicated for the: ● treatment of adults with unresectable or metastatic gastric, esophageal, or gastroesophageal junction cancer as a component of a combination chemotherapy regimen. ● treatment of adults with HER2-overexpressing metastatic gastric or gastroesophageal junction adenocarcinoma who have not received prior treatment for metastatic disease as a component of a combination regimen.
1.4Pancreatic Cancer Capecitabine tablets USP are indicated for the adjuvant treatment of adults with pancreatic adenocarcinoma as a component of a combination chemotherapy regimen.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Adjuvant Treatment of Colon Cancer ● Single agent: 1,250 mg/m 2 twice daily orally for the first 14 days of each 21-day cycle for a maximum of 8 cycles. (2.1) In combination with Oxaliplatin-Containing Regimens: 1,000 mg/m 2 orally twice daily for the first 14 days of each 21-day cycle for a maximum of 8 cycles in combination with oxaliplatin 130 mg/m 2 administered intravenously on day 1 of each cycle. ( 2.1 ) Perioperative Treatment of Rectal Cancer ● With Concomitant Radiation Therapy: 825 mg/m 2 orally twice daily ( 2.1 ) ● Without Radiation Therapy: 1,250 mg/m 2 orally twice daily ( 2.1 ) Unresectable or Metastatic Colorectal Cancer: ● Single agent: 1,250 mg/m 2 twice daily orally for the first 14 days of each 21-day cycle until disease progression or unacceptable toxicity.
( 2.1 ) ● In Combination with Oxaliplatin: 1,000 mg/m 2 orally twice daily for the first 14 days of each 21-day cycle until disease progression or unacceptable toxicity in combination with oxaliplatin 130 mg/m 2 administered intravenously on day 1 of each cycle. ( 2.1 ) Advanced or Metastatic Breast Cancer: ● Single agent: 1,000 mg/m 2 or 1,250 mg/m2 twice daily orally for the first 14 days of each 21-day cycle until disease progression or unacceptable toxicity. ( 2.2 ) ● In combination with docetaxel: 1,000 mg/m 2 or 1,250 mg/m2 orally twice daily for the first 14 days of a 21-day cycle, until disease progression or unacceptable toxicity in combination with docetaxel at 75 mg/m 2 administered intravenously on day 1 of each cycle ( 2.2 ) Unresectable or Metastatic Gastric, Esophageal, or Gastroesophageal Junction Cancer ● 625 mg/m 2 orally twice daily on days 1 to 21 of each 21-day cycle for a maximum of 8 cycles in combination with platinum-containing chemotherapy.
( 2.3 ) OR ● 850 mg/m 2 or 1,000 mg/m 2 orally twice daily for the first 14 days of each 21-day cycle until disease progression or unacceptable toxicity in combination with oxaliplatin 130 mg/m 2 administered intravenously on day 1 of each cycle. ( 2.3 ) HER2-overexpressing metastatic adenocarcinoma of the gastroesophageal junction or stomach ● 1,000 mg/m 2 orally twice daily for the first 14 days of each 21-day cycle until disease progression or unacceptable toxicity in combination with cisplatin and trastuzumab. ( 2.3 ) Pancreatic cancer ● 830 mg/m 2 orally twice daily for the first 21 days of each 28-day cycle for maximum of 6 cycles in combination with gemcitabine 1,000 mg/m 2 administered intravenously on days 1, 8, and 15 of each cycle.
( 2.4 ) Refer to Sections 2.5 and 2.6 for information related to dosage modifications for adverse reactions and renal impairment ( 2.5 and 2.6 ).
2.1Recommended Dosage for Colorectal Cancer Adjuvant Treatment of Colon Cancer Single Agent The recommended dosage of capecitabine tablets are 1,250 mg/m2 orally twice daily for the first 14 days of each 21-day cycle for a maximum of 8 cycles. In Combination with Oxaliplatin-Containing Regimens The recommended dosage of capecitabine tablets are 1,000 mg/m2 orally twice daily for the first 14 days of each 21-day cycle for a maximum of 8 cycles in combination with oxaliplatin 130 mg/m2 administered intravenously on day 1 of each cycle.
Refer to the oxaliplatin prescribing information for additional dosing information as appropriate. Perioperative Treatment of Rectal Cancer The recommended dosage of capecitabine is 825 mg/m2 orally twice daily when administered with concomitant radiation therapy and 1,250 mg/m2 orally twice daily when administered without radiation therapy as part of a peri-operative combination regimen. Unresectable or Metastatic Colorectal Cancer Single Agent The recommended dosage of capecitabine tablets are 1,250 mg/m2 orally twice daily for the first 14 days of a 21-day cycle until disease progression or unacceptable toxicity.
In Combination with Oxaliplatin The recommended dosage of capecitabine tablets are 1,000 mg/m2 orally twice daily for the first 14 days o…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capecitabine tablets, USP film-coated: ● 150 mg: biconvex, oblong shaped, light peach colored, debossed with ‘150’ on one side and plain on other side. ● 500 mg: biconvex, oblong shaped, peach colored, debossed with '500' on one side and plain on other side. Tablets: 150 mg and 500 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Capecitabine is contraindicated in patients with history of severe hypersensitivity reaction to fluorouracil or capecitabine [see Adverse Reactions ( 6.1 )] . History of severe hypersensitivity reactions to fluorouracil or capecitabine ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS ● Serious Adverse Reactions from Dihydropyrimidine Dehydrogenase (DPD) Deficiency: Patients with certain homozygous or compound heterozygous variants in the DPYD gene are at increased risk for acute early-onset toxicity and serious, including fatal, adverse reactions due to capecitabine (e.g., mucositis, diarrhea, neutropenia, and neurotoxicity). Capecitabine is not recommended for use in patients known to have certain homozygous or compound heterozygous DPYD variants that result in complete absence of DPD activity.
Withhold or permanently discontinue based on clinical assessment. No capecitabine dose has been proven safe in patients with complete absence of DPD activity. ( 5.2 ) ● Cardiotoxicity: May be more common in patients with a prior history of coronary artery disease.
Withhold capecitabine for cardiotoxicity as appropriate. The safety of resumption of capecitabine in patients with cardiotoxicity that has resolved has not been established. (2.5 , 5.3 ) ● Diarrhea: Withhold capecitabine and then resume at same or reduced dose, or permanently discontinue, based on severity and occurrence.
( 2.5 , 5.4 ) ● Dehydration: Optimize hydration before starting capecitabine. Monitor hydration status and kidney function at baseline and as clinically indicated. Withhold capecitabine and then resume at same or reduced dose, or permanently discontinue, based on severity and occurrence.
( 2.5 , 5.5 ) ● Renal Toxicity: Monitor renal function at baseline and as clinically indicated. Optimize hydration before starting capecitabine. Withhold capecitabine and then resume at same or reduced dose, or permanently discontinue, based on severity and occurrence.
( 2.5 , 5.6 ) ● Serious Skin Toxicities: Monitor for new or worsening serious skin reactions. Permanently discontinue capecitabine in patients who experience a severe cutaneous adverse reaction. ( 5.7 ) ● Palmar-Plantar Erythrodysesthesia Syndrome: Withhold capecitabine then resume at same or reduced dose, or permanently discontinue, based on severity and occurrence.
( 2.5 , 5.8 ) ● Myelosuppression: Monitor complete blood count at baseline and before each cycle. Capecitabine is not recommended in patients with baseline neutrophil counts <1.5 x 10⁹/L or platelet counts <100 x 109/L. For grade 3 or 4 myelosuppression, withhold capecitabine and then resume at same or reduced dose, or permanently discontinue, based on occurrence.
( 2.5 , 5.9 ) ● Hyperbilirubinemia: Patients with Grade 3 to 4 hyperbilirubinemia may resume treatment once the event isGrade 2 or less (≤3 x ULN), using the percent of current dose as shown in column 3 of Table 1 ( 2.5 , 5.10 ) ● Embryo-Fetal Toxicity: Can cause fetal harm. Advise patients of the potential risk to a fetus and to use effective contraception. ( 5.11 , 8.1 , 8.3 )
5.1Increased Risk of Bleeding With Concomitant Use of Vitamin K Antagonists Altered coagulation parameters and/or bleeding, including death, have been reported in patients taking capecitabine concomitantly with vitamin K antagonists, such as warfarin. Clinically significant increases in PT and INR have been reported in patients who were on stable doses of oral vitamin K antagonists at the time capecitabine was introduced. These events occurred within several days and up to several months after initiating capecitabine and, in a few cases, within 1 month after stopping capecitabine.
These events occurred in patients with and without liver metastases. Monitor INR more frequently and adjust the dose of the vitamin K antagonist as appropriate [see Drug Interactions ( 7.1 )].
5.2Serious Adverse Reactions from Dihydropyrimidine Dehydrogenase (DPD) Deficiency Patients with certain homozygous or compound heterozygous variants in the DPYD gene known to result in complete or near complete absence of DPD activity (complete DPD deficiency) are at increased risk for acute early-onset toxicity and serious, including fatal, adverse reactions due to capecitabine (e.g., mucositis,…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: • Cardiotoxicity [see Warnings and Precautions ( 5.3 )] • Diarrhea [see Warnings and Precautions ( 5.4 )] • Dehydration [see Warnings and Precautions ( 5.5 )] • Renal Toxicity [see Warnings and Precautions ( 5.6 )] • Serious Skin Toxicities [see Warnings and Precautions ( 5.7 )] • Palmar-Plantar Erythrodysesthesia Syndrome [see Warnings and Precautions ( 5.8 )] • Myelosuppression [see Warnings and Precautions ( 5.9 )] • Hyperbilirubinemia [see Warnings and Precautions ( 5.10 )] ● Most common adverse reactions in patients who received capecitabine as a single agent for the adjuvant treatment for colon cancer (≥30%) were palmar-plantar erythrodysesthesia syndrome, diarrhea, and nausea.
( 6.1 ) ● Most common adverse reactions (≥30%) in patients with metastatic colorectal cancer who received capecitabine as a single agent were anemia, diarrhea, palmar-plantar erythrodysesthesia syndrome, hyperbilirubinemia, nausea, fatigue, and abdominal pain. ( 6.1 ) ● Most common adverse reactions (≥30%) in patients with metastatic breast cancer who received capecitabine with docetaxel were diarrhea, stomatitis, palmar-plantar erythrodysesthesia syndrome, nausea, alopecia, vomiting, edema, and abdominal pain. ( 6.1 ) ● Most common adverse reactions (≥30%) in patients with metastatic breast cancer who received capecitabine as a single agent were lymphopenia, anemia, diarrhea, hand-and-foot syndrome, nausea,fatigue, vomiting, and dermatitis.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Accord Healthcare Inc. at 1-866-941-7875 or www.accordhealthcare.us or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch To report SUSPECTED ADVERSE REACTIONS, contact Accord Healthcare Inc. at 1-866-941-7875 or www.accordhealthcare.us or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adjuvant Treatment of Colon Cancer Single Agent The safety of capecitabine as a single agent was evaluated in patients with Stage III colon cancer in X-ACT [see Clinical Studies ( 14.1 )]. Patients received capecitabine 1,250 mg/m 2 orally twice daily for the first 14 days of a 21-day cycle (N=995) or leucovorin 20 mg/m 2 intravenously followed by fluorouracil 425 mg/m 2 as an intravenous bolus on days 1 to 5 of each 28-day cycle (N=974).
Among patients who received capecitabine, the median duration of treatment was 5.4 months. Deaths due to all causes occurred in 0.8% of patients who received capecitabine on study or within 28 days of receiving study drug. Permanent discontinuation due to an adverse reaction occurred in 11% of patients who received capecitabine.
Most common adverse reactions (>30%) were palmar-plantar erythrodysesthesia syndrome, diarrhea, and nausea. Tables 2 and 3 summarize the adverse reactions and laboratory abnormalities in X-ACT. Table 2 Adverse Reactions (≥ 10%) in Patients Who Received Capecitabine for Adjuvant Treatment of Colon Cancer in X-ACT Adverse Reaction Capecitabine (N=995) Fluorouracil + Leucovorin (N=974) All Grades (%) Grade 3 or 4 (%) All Grades (%) Grade3 or 4 (%) Skin and Subcutaneous Tissue Palmar-plantar erythrodysesthesia syndrome 60 17 9 <1 Gastrointestinal Diarrhea 47 12 65 14 Nausea 34 2 47 2 Stomatitis 22 2 60 14 Vomiting 15 2 21 2 Abdominal Pain 14 3 16 2 General Fatigue 16 <1 16 1 Asthenia 10 <1 10 1 Lethargy 10 <1 9 <1 Clinically relevant adverse reactions in <10% of patients are presented below: Eye: conjunctivitis Gastrointestinal: constipation, upper abdominal pain, dyspepsia General: pyrexia Metabolism and Nutrition: anorexia Nervous System: dizziness, dysgeusia, headache Skin & Subcutaneous Tissue: rash, alopecia, erythema…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS ● Allopurinol: Avoid concomitant use of allopurinol with capecitabine. ( 7.1 ) ● Leucovorin: Closely monitor for toxicities when capecitabine is coadministered with leucovorin. ( 7.1 ) ● CYP2C9 substrates: Closely monitor for adverse reactions when CYP2C9 substrates are coadministered with capecitabine.
( 7.2 ) ● Vitamin K antagonists: Monitor INR more frequently and dose adjust oral vitamin K antagonist as appropriate ● Phenytoin: Closely monitor phenytoin levels in patients taking capecitabine concomitantly with phenytoin and adjust the phenytoin dose as appropriate. ( 7.2 ) ● Nephrotoxic drugs: Closely monitor for signs of renal toxicity when capecitabine is used concomitantly with nephrotoxic drugs. ( 7.3 )
7.1Effect of Other Drugs on Capecitabine Allopurinol Concomitant use with allopurinol may decrease concentration of capecitabine’s active metabolites [see Clinical Pharmacology ( 12.3 )], which may decrease efficacy. Avoid concomitant use of allopurinol with capecitabine. Leucovorin The concentration of fluorouracil is increased and its toxicity may be enhanced by leucovorin, folic acid, or folate analog products.
Deaths from severe enterocolitis, diarrhea, and dehydration have been reported in elderly patients receiving weekly leucovorin and fluorouracil. Instruct patients not to take products containing folic acid or folate analog products unless directed to do so by their healthcare provider.
7.2Effect of Capecitabine on Other Drugs CYP2C9 Substrates Capecitabine increased exposure of CYP2C9 substrates [see Clinical Pharmacology ( 12.3 )], which may increase the risk of adverse reactions related to these substrates. Closely monitor for adverse reactions of CYP2C9 substrates where minimal concentration changes may lead to serious adverse reactions when used concomitantly with capecitabine (e.g., anticoagulants, antidiabetic drugs). Vitamin K Antagonists Capecitabine increases exposure of vitamin K antagonist [see Clinical Pharmacology ( 12.3 )], which may alter coagulation parameters and/or bleeding and could result in death [see Warning and Precautions ( 5.1 )] .
These events may occur within days of treatment initiation and up to 1 month after discontinuation of capecitabine. Monitor INR more frequently and refer to the prescribing information of oral vitamin K antagonist for dosage adjustment, as appropriate, when capecitabine is used concomitantly with vitamin K antagonist. Phenytoin Capecitabine may increases exposure of phenytoin, which may increase the risk of adverse reactions related to phenytoin.
Closely monitor phenytoin levels and refer to the prescribing information of phenytoin for dosage adjustment, as appropriate, when capecitabine is used concomitantly with phenytoin.
7.3Nephrotoxic Drugs Due of the additive pharmacologic effect, concomitant use of capecitabine with other drugs known to cause renal toxicity may increase the risk of renal toxicity [see Warnings and Precautions ( 5.6 )]. Closely monitor for signs of renal toxicity when capecitabine is used concomitantly with nephrotoxic drugs (e.g. platinum salts, irinotecan, methotrexate, intravenous bisphosphonates).
For full Taxotere prescribing information, please refer to Taxotere Package Insert. All trade names drug products are the property of their respective owners. Manufactured By: Intas Pharmaceuticals Limited, Ahmedabad – 380 054, India. For BluePoint Laboratories Issued 03/23
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS ● Lactation: Advise not to breastfeed. ( 8.2 ) ● Hepatic Impairment: Monitor patients with hepatic impairment more frequently for adverse reactions. ( 8.7 )
8.1Pregnancy Risk Summary Based on findings in animal reproduction studies and its mechanism of action [see Clinical Pharmacology ( 12.1 )], capecitabine can cause fetal harm when administered to a pregnant woman. Available human data with capecitabine use in pregnant women is not sufficient to inform the drug-associated risk. In animal reproduction studies, administration of capecitabine to pregnant animals during the period of organogenesis caused embryolethality and teratogenicity in mice and embryolethality in monkeys at 0.2 and 0.6 times the exposure (AUC) in patients receiving the recommended dose of 1,250 mg/m2 twice daily, respectively (see Data).
Advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Oral administration of capecitabine to pregnant mice during the period of organogenesis at a dose of 198 mg/kg/day caused malformations and embryo lethality. In separate pharmacokinetic studies, this dose in mice produced 5’-DFUR AUC values that were approximately 0.2 times the AUC values in patients administered the recommended daily dose.
Malformations in mice included cleft palate, anophthalmia, microphthalmia, oligodactyly, polydactyly, syndactyly, kinky tail and dilation of cerebral ventricles. Oral administration of capecitabine to pregnant monkeys during the period of organogenesis at a dose of 90 mg/kg/day, caused fetal lethality. This dose produced 5’-DFUR AUC values that were approximately 0.6 times the AUC values in patients administered the recommended daily dose.
8.2Lactation Risk Summary There is no information regarding the presence of capecitabine or its metabolites in human milk, or on its effects on milk production or the breast-fed infant. Capecitabine metabolites were present in the milk of lactating mice [see Data ]. Because of the potential for serious adverse reactions in a breastfed child, advise women not to breastfeed during treatment with capecitabine and for 1 weeks after the final dose.
Data Lactating mice given a single oral dose of capecitabine excreted significant amounts of capecitabine metabolites into the milk.
8.3Females and Males of Reproductive Potential Capecitabine can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations ( 8.1 )]. Pregnancy Testing Verify pregnancy status in females of reproductive potential prior to initiating capecitabine. Contraception Females Advise females of reproductive potential to use effective contraception during treatment with capecitabine and for 6 months after the last dose.
Males Based on genotoxicity findings, advise males with female partners of reproductive potential to use effective contraception during treatment with capecitabine and for 3 months after the last dos [see Nonclinical Toxicology (13.1) ] . Infertility Based on animal studies, capecitabine may impair fertility in females and males of reproductive potential [see Nonclinical Toxicology (13.1) ] .
8.4Pediatric Use The safety and effectiveness of capecitabine in pediatric patients have not been established. Safety and effectiveness were assessed, but not established in two single arm studies in 56 pediatric patients aged 3 months to <17 years with newly diagnosed gliomas. In both trials, pediatric patients received an investigational pediatric formulation of capecitabine concomitantly with and following completion of radiation therapy (total dose of 5580 cGy in 180 cGy fractio…
🤰 Pregnancy ▾
5.6Renal Toxicity Serious renal failure, sometimes fatal, can occur with capecitabine. Renal impairment or coadministration of capecitabine with other products known to cause renal toxicity may increase the risk of renal toxicity [see Drug Interactions (7.3)]. Monitor renal function at baseline and as clinically indicated.
Optimize hydration before starting capecitabine. Withhold capecitabine and then resume at same or reduced dose, or permanently discontinue, based on severity and occurrence [see Dosage and Administration ( 2.5 )].
8.1Pregnancy Risk Summary Based on findings in animal reproduction studies and its mechanism of action [see Clinical Pharmacology ( 12.1 )], capecitabine can cause fetal harm when administered to a pregnant woman. Available human data with capecitabine use in pregnant women is not sufficient to inform the drug-associated risk. In animal reproduction studies, administration of capecitabine to pregnant animals during the period of organogenesis caused embryolethality and teratogenicity in mice and embryolethality in monkeys at 0.2 and 0.6 times the exposure (AUC) in patients receiving the recommended dose of 1,250 mg/m2 twice daily, respectively (see Data).
Advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Oral administration of capecitabine to pregnant mice during the period of organogenesis at a dose of 198 mg/kg/day caused malformations and embryo lethality. In separate pharmacokinetic studies, this dose in mice produced 5’-DFUR AUC values that were approximately 0.2 times the AUC values in patients administered the recommended daily dose.
Malformations in mice included cleft palate, anophthalmia, microphthalmia, oligodactyly, polydactyly, syndactyly, kinky tail and dilation of cerebral ventricles. Oral administration of capecitabine to pregnant monkeys during the period of organogenesis at a dose of 90 mg/kg/day, caused fetal lethality. This dose produced 5’-DFUR AUC values that were approximately 0.6 times the AUC values in patients administered the recommended daily dose.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of capecitabine in pediatric patients have not been established. Safety and effectiveness were assessed, but not established in two single arm studies in 56 pediatric patients aged 3 months to <17 years with newly diagnosed gliomas. In both trials, pediatric patients received an investigational pediatric formulation of capecitabine concomitantly with and following completion of radiation therapy (total dose of 5580 cGy in 180 cGy fractions).
The relative bioavailability of the investigational formulation to capecitabine was similar. The adverse reaction profile was consistent with that of adults, with the exception of laboratory abnormalities which occurred more commonly in pediatric patients. The most frequently reported laboratory abnormalities (per-patient incidence ≥ 40%) were increased ALT (75%), lymphocytopenia (73%), hypokalemia (68%), thrombocytopenia (57%), hypoalbuminemia (55%), neutropenia (50%), low hematocrit (50%), hypocalcemia(48%), hypophosphatemia (45%) and hyponatremia (45%).
🧓 Geriatric Use ▾
5.10Hyperbilirubinemia Hyperbilirubinemia can occur with capecitabine. In the 875 patients with metastatic breast or colorectal cancer who received capecitabine as a single agent, grade 3 hyperbilirubinemia occurred in 15% of patients and grade 4 hyperbilirubinemia occurred in 3.9%. Of the 566 patients who had hepatic metastases at baseline and the 309 patients without hepatic metastases at baseline, grade 3 or 4 hyperbilirubinemia occurred in 23% and 12%, respectively.
Of these 167 patients with grade 3 or 4 hyperbilirubinemia, 19% had postbaseline increased alkaline phosphatase and 28% had postbaseline increased transaminases at any time (not necessarily concurrent). The majority of these patients with increased transaminases or alkaline phosphatase had liver metastases at baseline. In addition, 58% and 35% of the 167 patients with grade 3 or 4 hyperbilirubinemia had pre- and postbaseline increased alkaline phosphatase or transaminases (grades 1 to 4), respectively.
Only 8% (n=13) and 3% (n=5) had grade 3 or 4 increased alkaline phosphatase or transaminases. In the 596 patients who received capecitabine for metastatic colorectal cancer, the incidence of grade 3 or 4 hyperbilirubinemia was similar to that observed for the pooled population of patients with metastatic breast and colorectal cancer. The median time to onset for grade 3 or 4 hyperbilirubinemia was 64 days and median total bilirubin increased from 8 μm/L at baseline to 13 μm/L during treatment with capecitabine.
Of the 136 patients with grade 3 or 4 hyperbilirubinemia, 49 patients had grade 3 or 4 hyperbilirubinemia as their last measured value, of which 46 had liver metastases at baseline. In the 251 patients with metastatic breast cancer who received capecitabine with docetaxel, grade 3 hyperbilirubinemia occurred in 7% and grade 4 hyperbilirubinemia occurred in 2%. Withhold capecitabine and then resume at a same or reduced dose, or permanently discontinue, based on occurrence [see Dosage and Administration ( 2.5 )].
Patients with Grade 3 to 4 hyperbilirubinemia may resume treatment once the event is Grade 2 or less than three times the upper limit of normal, using the percent of current dose as shown in Table 1 [see Dosage and Administration ( 2.5 )].
8.5Geriatric Use Of 7938 patients with colorectal cancer who were treated with capecitabine, 33% were older than 65 years. Of the 4536 patients with metastatic breast cancer who were treated with capecitabine, 18% were older than 65 years. Of 1951 patients with gastric, esophageal, or gastrointestinal junction cancer who were treated with capecitabine, 26% were older than 65 years.
Of 364 patients with pancreatic cancer who received adjuvant treatment with capecitabine, 47% were 65 years or older. No overall differences in efficacy were observed comparing older versus younger patients with colorectal cancer, gastric, esophageal or gastrointestinal junction cancer, or pancreatic cancer using the approved recommended dosages and treatment regimens. Older patients experience increased gastrointestinal toxicity due to capecitabine compared to younger patients.
Deaths from severe enterocolitis, diarrhea, and dehydration have been reported in elderly patients receiving weekly leucovorin and fluorouracil [see Drug Interactions ( 7.1 )].
🆘 Overdosage ▾
10 OVERDOSAGE Administer uridine triacetate within 96 hours for management of capecitabine overdose. Although no clinical experience using dialysis as a treatment for capecitabine overdose has been reported, dialysis may be of benefit in reducing circulating concentrations of 5’-DFUR, a low– molecular-weight metabolite of the parent compound.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Capecitabine is metabolized to fluorouracil in vivo. Both normal and tumor cells metabolize fluorouracil to 5-fluoro-2’-deoxyuridine monophosphate (FdUMP) and 5-fluorouridine triphosphate (FUTP). These metabolites cause cell injury by two different mechanisms.
First, FdUMP and the folate cofactor, N 5-10 -methylenetetrahydrofolate, bind to thymidylate synthase (TS) to form a covalently bound ternary complex. This binding inhibits the formation of thymidylate from 2’-deoxyuridylate. Thymidylate is the necessary precursor of thymidine triphosphate, which is essential for the synthesis of DNA, so that a deficiency of this compound can inhibit cell division.
Second, nuclear transcriptional enzymes can mistakenly incorporate FUTP in place of uridine triphosphate (UTP) during the synthesis of RNA. This metabolic error can interfere with RNA processing and protein synthesis.
12.2Pharmacodynamics Population-based exposure-effect analyses demonstrated a positive association between AUC of fluorouracil and grade 3 to 4 hyperbilirubinemia.
12.3Pharmacokinetics The AUC of capecitabine and its metabolite 5’-DFCR increases proportionally over a dosage range of 500 mg/m 2 /day to 3,500 mg/m2/day (0.2 to 1.4 times the approved recommended dosage). The AUC of capecitabine’s metabolites 5’-DFUR and fluorouracil increased greater than proportional to the dose. The interpatient variability in the C max and AUC of fluorouracil was greater than 85%.
Absorption Following oral administration of capecitabine 1,255 mg/m 2 orally twice daily (the recommended dosage when used as single agent), the median T max of capecitabine and its metabolite fluorouracil was approximately 1.5 hours and 2 hours, respectively. Effect of Food Following administration of a meal (breakfast medium-rich in fat and carbohydrates), the mean C max and AUC 0 to INF of capecitabine was decreased by 60% and 34%, respectively. The mean C max and AUC 0 to INF of fluorouracil were also decreased by 37 % and 12%, respectively.
The T max of both capecitabine and fluorouracil was delayed by 1.5 hours. Distribution Plasma protein binding of capecitabine and its metabolites is less than 60% and is not concentration-dependent. Capecitabine was primarily bound to human albumin (approximately 35%).
Following oral administration of capecitabine 7 days before surgery in patients with colorectal cancer, the median ratio of concentration for the active metabolite fluorouracil in colorectal tumors to adjacent tissues was 2.9 (range: 0.9 to 8.0). Elimination The elimination half-lives of capecitabine and fluorouracil were approximately 0.75 hour. Metabolism Capecitabine undergoes metabolism by carboxylesterase and is hydrolyzed to 5’-DFCR.
5’- DFCR is subsequently converted to 5’-DFUR by cytidine deaminase. 5’-DFUR is then hydrolized by thymidine phosphorylase (dThdPase) enzymes to the active metabolite fluorouracil. Fluorouracil is subsequently metabolized by dihydropyrimidine dehydrogenase to 5-fluoro-5, 6- dihydro-fluorouracil (FUH2).
The pyrimidine ring of FUH2 is cleaved by dihydropyrimidinase to yield 5-fluoro-ureido-propionic acid (FUPA). Finally, FUPA is cleaved by β-ureido-propionase to α-fluoro-β-alanine (FBAL). Excretion Following administration of radiolabeled capecitabine, 96% of the administered capecitabine dose was recovered in urine (3% unchanged and 57% as metabolite FBAL) and 2.6% in feces.
Specific Populations Following therapeutic doses of capecitabine, no clinically meaningful difference in the pharmacokinetics of 5’-DFUR, fluorouracil or FBAL were observed based on sex (202 females and 303 males) and race (455 White, 22 Black, and 28 Other). No clinically meaningful difference on the pharmacokinetics of 5’-DFUR and fluorouracil were observed based on age (range: 27 to 86 years); however, the AUC of FBAL increased by 15% following a 20% increase in age. Racial or Ethnic Groups Following administration of capecitabine 825 mg/…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Capecitabine is metabolized to fluorouracil in vivo. Both normal and tumor cells metabolize fluorouracil to 5-fluoro-2’-deoxyuridine monophosphate (FdUMP) and 5-fluorouridine triphosphate (FUTP). These metabolites cause cell injury by two different mechanisms.
First, FdUMP and the folate cofactor, N 5-10 -methylenetetrahydrofolate, bind to thymidylate synthase (TS) to form a covalently bound ternary complex. This binding inhibits the formation of thymidylate from 2’-deoxyuridylate. Thymidylate is the necessary precursor of thymidine triphosphate, which is essential for the synthesis of DNA, so that a deficiency of this compound can inhibit cell division.
Second, nuclear transcriptional enzymes can mistakenly incorporate FUTP in place of uridine triphosphate (UTP) during the synthesis of RNA. This metabolic error can interfere with RNA processing and protein synthesis.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Capecitabine tablets, USP 150 mg and 500 mg are supplied as follows: ● NDC 68001-487-06: 150 mg: biconvex, oblong shaped, light peach colored, film coated tablets, debossed with ‘150’ on one side and plain on other side; available in bottles of 60 with child-resistant closure. ● NDC 68001-488-07: 500 mg: biconvex, oblong shaped, peach colored, film coated tablets, debossed with '500' on one side and plain on other side; available in bottles of 120 with child-resistant closure. Storage and Handling Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature] .
KEEP TIGHTLY CLOSED. Capecitabine is a hazardous drug. Follow applicable special handling and disposal procedures.
1
📋 Description ▾
11 DESCRIPTION Capecitabine is a nucleoside metabolic inhibitor. The chemical name is 5’-deoxy-5-fluoro-N- [(pentyloxy) carbonyl]-cytidine and has a molecular formula of C 15 H 22 FN 3 O 6 and a molecular weight of 359.35. Capecitabine has the following structural formula: Capecitabine is a white to off-white crystalline powder with an aqueous solubility of 26 mg/mL at 20°C.
Capecitabine tablets, USP are supplied as biconvex, oblong film-coated tablets for oral administration. Each light peach-colored tablet contains 150 mg capecitabine and each peach-colored tablet contains 500 mg capecitabine. The inactive ingredients in capecitabine tablets include: anhydrous lactose, croscarmellose sodium, hypromellose, microcrystalline cellulose and magnesium stearate.
The peach or light peach film coating contains hypromellose, purified talc, titanium dioxide and ferric oxide red and ferric oxide yellow. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Increased Risk of Bleeding with Concomitant Use of Vitamin K Antagonists Advise patients on vitamin K antagonists, such as warfarin, that they are at an increased risk of severe bleeding while taking capecitabine. Advise these patients that INR should be monitored more frequently, and dosage modifications of the vitamin K antagonist may be required, while taking and after discontinuation of capecitabine.
Advise these patients to immediately contact their healthcare provider if signs or symptoms of bleeding occur [see Warnings and Precautions ( 5.1 )]. Serious Adverse Reactions from Dihydropyrimidine Dehydrogenase (DPD) Deficiency Inform patients of the potential for serious and life-threatening adverse reactions due to DPD deficiency and discuss with your patient whether they should be tested for genetic variants of DPYD that are associated with an increased risk of serious adverse reactions from the use of capecitabine.
Advise patients to immediately contact their healthcare provider if symptoms of severe mucositis, diarrhea, neutropenia, and neurotoxicity occur [see Warnings and Precautions ( 5.2 ) and Clinical Pharmacology ( 12.5 )] . Cardiotoxicity Advise patients of the risk of cardiotoxicity and to immediately contact their healthcare provider for new onset of chest pain, shortness of breath, dizziness, or lightheadedness [see Warnings and Precautions ( 5.3 )] . Diarrhea Inform patients experiencing grade 2 diarrhea (an increase of 4 to 6 stools/day or nocturnal stools) or greater or experiencing severe bloody diarrhea with severe abdominal pain and fever to stop taking capecitabine.
Advise patients on the use of antidiarrheal treatments (e.g., loperamide) to manage diarrhea [see Warnings and Precautions ( 5.4 )] . Dehydration Instruct patients experiencing grade 2 or higher dehydration to stop taking capecitabine immediately and to contact their healthcare provider. Advise patients to not restart capecitabine until rehydrated and any precipitating causes have been corrected or controlled [see Warnings and Precautions ( 5.5 )] .
Renal Toxicity Instruct patients experiencing decreased urinary output or other signs and symptoms of renal toxicity to immediately contact their healthcare provider [see Warnings and Precautions ( 5.6 )] . Serious Skin Toxicities Instruct patients skin rash, blistering, or peeling to immediately contact their healthcare provider [see Warnings and Precautions ( 5.7 )] . Palmar-Plantar Erythrodysesthesia Syndrome Instruct patients experiencing grade 2 palmar-plantar erythrodysesthesia syndrome or greater to stop taking capecitabine immediately and to contact their healthcare provider.
Inform patients that initiation of symptomatic treatment is recommended and hand-and-foot syndrome can lead to loss of fingerprints which could impact personal identification [see Warnings and Precautions ( 5.8 )] . Myelosuppression Inform patients who develop a fever of 100.5°F or greater or other evidence of potential infection to immediately contact their healthcare provider [see Warnings and Precautions ( 5.9 )] . Hyperbilirubinemia Inform patients who develop jaundice or icterus to immediately contact their healthcare provider [see Warnings and Precautions ( 5.10 )] .
Embryo-Fetal Toxicity Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females of reproductive potential to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions ( 5.11 ), Use in Specific Populations ( 8.1 )] . Advise females of reproductive potential to use effective contraception during treatment with capecitabine and for 6 months after the last dose [see Use in Specific Populations ( 8.3 )] .
Advise males with female partners of reproductive potential to use effective contraception during treatment with capecitabine and for 3 months aft…