
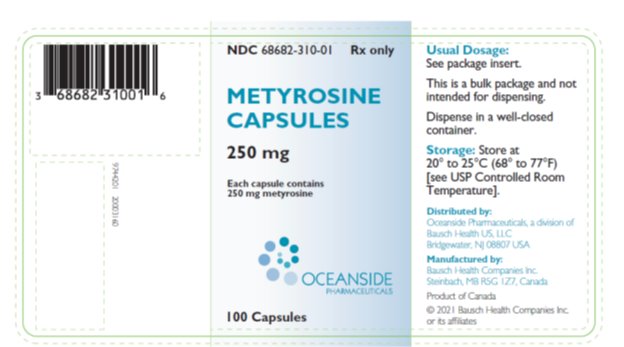
Metyrosine 250 mg Capsule, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Catecholamine Synthesis Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 9XZ8H6N6OH
A plant-based cellulose derivative used as a binder to hold tablet ingredients together, a thickener in liquids, and a coating agent to control how fast the medicine dissolves.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $236.16 | $23,615.78 / 100 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Demser 250 mg 25010-0305-15 | Bausch | 100 capsules | — | AB | FDA listed | — |
| Metyrosine 250 mgthis 68682-0310-01 | Oceanside | 100 capsules | — | AB | FDA listed | — |
| metyrosine 250 mg 69238-1621-01 | Amneal | 100 capsules | — | AB | FDA listed | — |
| Metyrosine 250 mg 75907-0166-01 | Dr. | 100 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 68682-0310-01 You're viewing this | 100 CAPSULE in 1 BOTTLE (68682-310-01) | 2020-09-07 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Metyrosine is indicated in the treatment of patients with pheochromocytoma for: 1. Preoperative preparation of patients for surgery 2. Management of patients when surgery is contraindicated 3. Chronic treatment of patients with malignant pheochromocytoma Metyrosine is not recommended for the control of essential hypertension.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The recommended initial dosage of Metyrosine for adults and children 12 years of age and older is 250 mg orally four times daily. This may be increased by 250 mg to 500 mg every day to a maximum of 4 g/day in divided doses. When used for preoperative preparation, the optimally effective dosage of Metyrosine should be given for at least five to seven days.
Optimally effective dosages of Metyrosine usually are between 2 and 3 g/day, and the dose should be titrated by monitoring clinical symptoms and catecholamine excretion. In patients who are hypertensive, dosage should be titrated to achieve normalization of blood pressure and control of clinical symptoms. In patients who are usually normotensive, dosage should be titrated to the amount that will reduce urinary metanephrines and/or vanillylmandelic acid by 50% or more.
If patients are not adequately controlled by the use of Metyrosine, an alpha-adrenergic blocking agent (phenoxybenzamine) should be added. Use of Metyrosine in children under 12 years of age has been limited and a dosage schedule for this age group cannot be given.
⛔ Contraindications ▾
CONTRAINDICATIONS Metyrosine is contraindicated in persons known to be hypersensitive to this compound.
⚠️ Warnings ▾
WARNINGS Maintain Fluid Volume During and After Surgery When Metyrosine is used preoperatively, alone or especially in combination with alpha-adrenergic blocking drugs, adequate intravascular volume must be maintained intraoperatively (especially after tumor removal) and postoperatively to avoid hypotension and decreased perfusion of vital organs resulting from vasodilatation and expanded volume capacity. Following tumor removal, large volumes of plasma may be needed to maintain blood pressure and central venous pressure within the normal range.
In addition, life-threatening arrhythmias may occur during anesthesia and surgery, and may require treatment with a beta-blocker or lidocaine. During surgery, patients should have continuous monitoring of blood pressure and electrocardiogram. Intraoperative Effects While the preoperative use of Metyrosine in patients with pheochromocytoma is thought to decrease intraoperative problems with blood pressure control, Metyrosine does not eliminate the danger of hypertensive crises or arrhythmias during manipulation of the tumor, and the alpha-adrenergic blocking drug, phentolamine, may be needed.
Interaction with Alcohol Metyrosine may add to the sedative effects of alcohol and other CNS depressants, e.g., hypnotics, sedatives, and tranquilizers. (See PRECAUTIONS , Information for Patients and Drug Interactions .)
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Central Nervous System Sedation: The most common adverse reaction to Metyrosine is moderate to severe sedation, which has been observed in almost all patients. It occurs at both low and high dosages. Sedative effects begin within the first 24 hours of therapy, are maximal after two to three days, and tend to wane during the next few days.
Sedation usually is not obvious after one week unless the dosage is increased, but at dosages greater than 2000 mg/day some degree of sedation or fatigue may persist. In most patients who experience sedation, temporary changes in sleep pattern occur following withdrawal of the drug. Changes consist of insomnia that may last for two or three days and feelings of increased alertness and ambition.
Even patients who do not experience sedation while on Metyrosine may report symptoms of psychic stimulation when the drug is discontinued. Extrapyramidal Signs: Extrapyramidal signs such as drooling, speech difficulty, and tremor have been reported in approximately 10% of patients. These occasionally have been accompanied by trismus and frank parkinsonism.
Anxiety and Psychic Disturbances: Anxiety and psychic disturbances such as depression, hallucinations, disorientation, and confusion may occur. These effects seem to be dose-dependent and may disappear with reduction of dosage. Diarrhea Diarrhea occurs in about 10% of patients and may be severe.
Anti-diarrheal agents may be required if continuation of Metyrosine is necessary. Miscellaneous Infrequently, slight swelling of the breast, galactorrhea, nasal stuffiness, decreased salivation, dry mouth, headache, nausea, vomiting, abdominal pain, and impotence or failure of ejaculation may occur. Crystalluria (see PRECAUTIONS ) and transient dysuria and hematuria have been observed in a few patients.
Hematologic disorders (including eosinophilia, anemia, thrombocytopenia, and thrombocytosis), increased SGOT levels, peripheral edema, and hypersensitivity reactions such as urticaria and pharyngeal edema have been reported rarely. To report SUSPECTED ADVERSE REACTIONS, contact Oceanside Pharmaceuticals at 1-800-321-4576 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🆘 Overdosage ▾
OVERDOSAGE Signs of metyrosine overdosage include those central nervous system effects observed in some patients even at low dosages. At doses exceeding 2000 mg/day, some degree of sedation or feeling of fatigue may persist. Doses of 2000-4000 mg/day can result in anxiety or agitated depression, neuromuscular effects (including fine tremor of the hands, gross tremor of the trunk, tightening of the jaw with trismus), diarrhea, and decreased salivation with dry mouth.
Reduction of drug dose or cessation of treatment results in the disappearance of these symptoms. The acute toxicity of metyrosine was 442 mg/kg and 752 mg/kg in the female mouse and rat, respectively.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Metyrosine inhibits tyrosine hydroxylase, which catalyzes the first transformation in catecholamine biosynthesis, i.e., the conversion of tyrosine to dihydroxyphenylalanine (DOPA). Because the first step is also the rate-limiting step, blockade of tyrosine hydroxylase activity results in decreased endogenous levels of catecholamines, usually measured as decreased urinary excretion of catecholamines and their metabolites. In patients with pheochromocytoma, who produce excessive amounts of norepinephrine and epinephrine, administration of 1 to 4 grams of Metyrosine per day has reduced catecholamine biosynthesis from about 35% to 80% as measured by the total excretion of catecholamines and their metabolites (metanephrine and vanillylmandelic acid).
The maximum biochemical effect usually occurs within two to three days, and the urinary concentration of catecholamines and their metabolites usually returns to pretreatment levels within three to four days after Metyrosine is discontinued. In some patients the total excretion of catecholamines and catecholamine metabolites may be lowered to normal or near normal levels (less than 10 mg/24 hours). In most patients, the duration of treatment has been two to eight weeks, but several patients have received Metyrosine for periods of 1 to 10 years.
Most patients with pheochromocytoma treated with Metyrosine experience decreased frequency and severity of hypertensive attacks with their associated headache, nausea, sweating, and tachycardia. In patients who respond, blood pressure decreases progressively during the first two days of therapy with Metyrosine; after withdrawal, blood pressure usually increases gradually to pretreatment values within two to three days. Metyrosine is well absorbed from the gastrointestinal tract.
From 53% to 88% (mean 69%) was recovered in the urine as unchanged drug following maintenance oral doses of 600 to 4000 mg/24 hours in patients with pheochromocytoma or essential hypertension. Less than 1% of the dose was recovered as catechol metabolites. These metabolites are probably not present in sufficient amounts to contribute to the biochemical effects of metyrosine.
The quantities excreted, however, are sufficient to interfere with accurate determination of urinary catecholamines determined by routine techniques. Plasma half-life of metyrosine determined over an 8-hour period after single oral doses was 3-3.7 hours in three patients. For further information, refer to: Sjoerdsma A, Engelman K, Waldman TA, Cooperman LH, Hammond WG.
Pheochromocytoma: Current Concepts of Diagnosis and Treatment: Combined Clinical Staff Conference at the National Institutes of Health. Ann Intern Med . 1966;65:1302-1326.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Metyrosine Capsules 250 mg are blue opaque capsules imprinted with “ATON/305” on body, and “DEMSER” on cap, filled with white to off-white granular free-flowing powder. They are supplied as follows: NDC 68682-310-01 bottles of 100 Storage: Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. Dispense in a well-closed container.
Distributed by: Oceanside Pharmaceuticals, a division of Bausch Health US, LLC Bridgewater, NJ 08807 USA Manufactured by: Bausch Health Companies Inc. Steinbach, MB R5G 1Z7, Canada DEMSER is a trademark of Bausch Health Companies Inc. or its affiliates. © 2021 Bausch Health Companies Inc. or its affiliates Rev. 07/2021 9744301 20003161
📋 Description ▾
DESCRIPTION Metyrosine is (–)-α-methyl- L -tyrosine or (α-MPT). It has the following structural formula: Metyrosine is a white to off-white, crystalline compound of molecular weight 195.22. It is very slightly soluble in water, acetone, and methanol, and insoluble in chloroform and benzene.
It is soluble in acidic aqueous solutions. It is also soluble in alkaline aqueous solutions, but is subject to oxidative degradation under these conditions. Metyrosine is supplied as capsules for oral administration.
Each capsule contains 250 mg metyrosine. Inactive ingredients are colloidal silicon dioxide, gelatin, hydroxypropyl cellulose, magnesium stearate, titanium dioxide, FD&C Blue 2 and edible black ink. image