
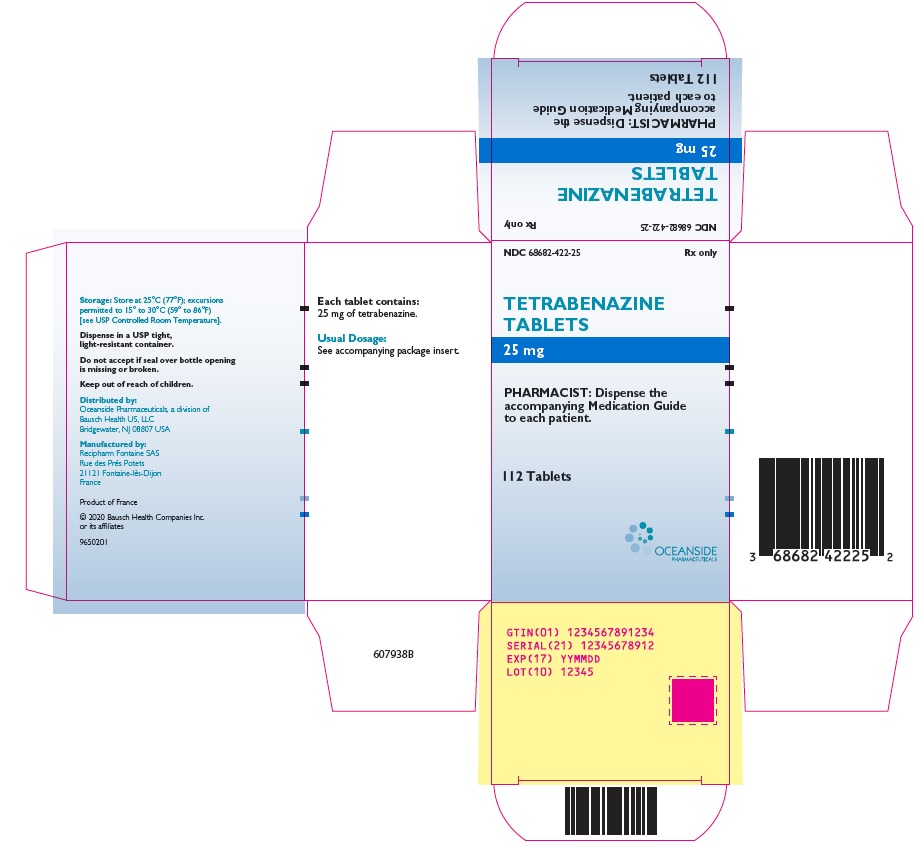
tetrabenazine 25 mg Tablet, 112-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Vesicular Monoamine Transporter 2 Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Tetrabenazine is used to treat chorea (sudden movements that you cannot control) caused by Huntington's disease (an inherited disease that causes the progressive breakdown of nerve cells in the brain). Tetrabenazine is in a class of medications called vesicular monoamine transporter 2 (VMAT2) inhibitors. It works by changing the activity of certain natural substances in the brain that affect nerves and muscles.
Read the full MedlinePlus article ↗- Tetrabenazine doesn't treat the disease itself — it specifically targets the involuntary, jerky movements called chorea that are a major symptom of Huntington's disease. By reducin...
- What exactly does tetrabenazine do for Huntington's disease?
- It's a very real concern — serious enough that the FDA requires a boxed warning on the label. Tetrabenazine can increase the risk of depression and suicidal thoughts, especially si...
- I heard this medication can cause depression. How serious is that risk?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Tetrabenazine — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII J2B2A4N98G
Lactose is a natural sugar derived from milk. In medications, it serves as a filler and binder to add bulk and help hold tablet or capsule ingredients together during manufacturing.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.598 | $179.02 / 112 tablets |
| Medicaid paysCMS SDUD · 12 mo | $1.55 | $173.40 / 112 tablets |
| Medicare drug plans payPart D · Q2 2026 | $10.00 | $1,119.94 / 112 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tetrabenazine 25 mg 47335-0179-23 | Sun | 112 tablets | $1.204 | — | FDA listed | save 25% |
| tetrabenazine 25 mg 70436-0102-09 | Slate | 112 tablets | $1.287 | AB | Availability likely | save 19% |
| Tetrabenazine 25 mg 23155-0939-63 | Heritage | 112 tablets | $1.340 | AB | Availability likely | save 16% |
| Tetrabenazine 25 mg 31722-0822-11 | Camber | 112 tablets | $1.340 | AB | Availability likely | save 16% |
| Tetrabenazine 25 mg 60505-3883-07 | Apotex | 112 tablets | $1.340 | AB | Availability likely | save 16% |
| Tetrabenazine 25 mg 68094-0805-10 | Precision | 112 tablets | $1.340 | AB | Availability likely | save 16% |
| Tetrabenazine 25 mg 69452-0118-21 | Bionpharma | 112 tablets | $1.340 | AB | Availability likely | save 16% |
| tetrabenazine 25 mgthis 68682-0422-25 | Oceanside | 112 tablets | $1.598 | AB | FDA listed | — |
| Tetrabenazine 25 mg 27241-0177-13 | Ajanta | 112 tablets | — | — | FDA listed | — |
| Tetrabenazine 25 mg 43598-0395-05 | Dr. | 500 tablets | — | AB | FDA listed | — |
| Tetrabenazine 25 mg 51407-0481-12 | Golden | 112 tablets | — | AB | FDA listed | — |
| Xenazine 25 mg 67386-0422-01 | Lundbeck | 112 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 68682-0422-25 You're viewing this | 112 TABLET in 1 BOTTLE (68682-422-25) | 2015-07-20 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: DEPRESSION AND SUICIDALITY Tetrabenazine tablets can increase the risk of depression and suicidal thoughts and behavior (suicidality) in patients with Huntington's disease. Anyone considering the use of tetrabenazine tablets must balance the risks of depression and suicidality with the clinical need for control of chorea. Close observation of patients for the emergence or worsening of depression, suicidality, or unusual changes in behavior should accompany therapy.
Patients, their caregivers, and families should be informed of the risk of depression and suicidality and should be instructed to report behaviors of concern promptly to the treating physician. Particular caution should be exercised in treating patients with a history of depression or prior suicide attempts or ideation, which are increased in frequency in Huntington's disease. Tetrabenazine tablets are contraindicated in patients who are actively suicidal, and in patients with untreated or inadequately treated depression [see Contraindications (4) , ] .
WARNING: DEPRESSION AND SUICIDALITY See full prescribing information for complete boxed warning . • Increases the risk of depression and suicidal thoughts and behavior (suicidality) in patients with Huntington's disease ( 5.1 ) • Balance risks of depression and suicidality with the clinical need for control of chorea when considering the use of tetrabenazine tablets ( 5.2 ) • Monitor patients for the emergence or worsening of depression, suicidality, or unusual changes in behavior ( 5.1 ) • Inform patients, caregivers and families of the risk of depression and suicidality and instruct to report behaviors of concern promptly to the treating physician (5.1 ) • Exercise caution when treating patients with a history of depression or prior suicide attempts or ideation (5.1) • Tetrabenazine tablets are contraindicated in patients who are actively suicidal, and in patients with untreated or inadequately treated depression ( 4 , 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Tetrabenazine tablets are indicated for the treatment of chorea associated with Huntington's disease. Tetrabenazine tablets are a vesicular monoamine transporter 2 (VMAT) inhibitor indicated for the treatment of chorea associated with Huntington's disease. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Individualization of dose with careful weekly titration is required. The 1 st week's starting dose is 12.5 mg daily; 2 nd week, 25 mg (12.5 mg twice daily); then slowly titrate at weekly intervals by 12.5 mg to a tolerated dose that reduces chorea. ( 2.1 , 2.2 ) • Doses of 37.5 mg and up to 50 mg/day should be administered in three divided doses per day with a maximum recommended single dose not to exceed 25 mg.
( 2.2 ) • Patients requiring doses above 50 mg/day should be genotyped for the drug metabolizing enzyme CYP2D6 to determine if the patient is a poor metabolizer (PM) or an extensive metabolizer (EM). ( 2.2 , 5.3 ) • Maximum daily dose in PMs: 50 mg with a maximum single dose of 25 mg ( 2.2 ) • Maximum daily dose in EMs and intermediate metabolizers (IMs): 100 mg with a maximum single dose of 37.5 mg ( 2.2 ) • If serious adverse reactions occur, titration should be stopped and the dose should be reduced. If the adverse reaction(s) do not resolve, consider withdrawal of tetrabenazine tablets.
( 2.2 )
2.1General Dosing Considerations The chronic daily dose of tetrabenazine tablets used to treat chorea associated with Huntington's disease (HD) is determined individually for each patient. When first prescribed, tetrabenazine tablets therapy should be titrated slowly over several weeks to identify a dose of tetrabenazine tablets that reduces chorea and is tolerated. Tetrabenazine tablets can be administered without regard to food [see Clinical Pharmacology (12.3) ].
2.2Individualization of Dose The dose of tetrabenazine tablets should be individualized. Dosing Recommendations Up to 50 mg/day The starting dose should be 12.5 mg/day given once in the morning. After 1 week, the dose should be increased to 25 mg/ day given as 12.5 mg twice a day.
Tetrabenazine tablets should be titrated up slowly at weekly intervals by 12.5 mg daily, to allow the identification of a tolerated dose that reduces chorea. If a dose of 37.5 to 50 mg/day is needed, it should be given in a three times a day regimen. The maximum recommended single dose is 25 mg.
If adverse reactions such as akathisia, restlessness, parkinsonism, depression, insomnia, anxiety or sedation occur, titration should be stopped and the dose should be reduced. If the adverse reaction does not resolve, consideration should be given to withdrawing tetrabenazine tablets treatment or initiating other specific treatment (e.g., antidepressants) [see Adverse Reactions ( 6.1 )] . Dosing Recommendations Above 50 mg/day Patients who require doses of tetrabenazine tablets greater than 50 mg/day should be first tested and genotyped to determine if they are poor metabolizers (PMs) or extensive metabolizers (EMs) by their ability to express the drug metabolizing enzyme, CYP2D6.
The dose of tetrabenazine tablets should then be individualized accordingly to their status as PMs or EMs [see Warnings and Precautions (5.3) , Use in Specific Populations ( 8.7 ), Clinical Pharmacology (12.3) ]. Extensive and Intermediate CYP2D6 Metabolizers Genotyped patients who are identified as extensive (EMs) or intermediate metabolizers (IMs) of CYP2D6, who need doses of tetrabenazine above 50 mg/day, should be titrated up slowly at weekly intervals by 12.5 mg daily, to allow the identification of a tolerated dose that reduces chorea.
Doses above 50 mg/day should be given in a three times a day regimen. The maximum recommended daily dose is 100 mg and the maximum recommended single dose is 37.5 mg. If adverse reactions such as akathisia, parkinsonism, depression, insomnia, anxiety or sedation occur, titration should be stopped and the dose should be reduced.
If the adverse reaction does not resolve, consideration should be given to withdrawing tetrabenazine tablets treatment or initiating other specific treatment (e.g., antidepressants) [see Warnings and Precautions (5.3) , Use in Specific Populations ( 8.7 ), Clinical Pharmacology (12.3) ]. Poor CYP2D6 Metabolizers In PMs, the i…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tetrabenazine tablets are available in the following strengths and packages: The 12.5 mg tetrabenazine tablets are white, cylindrical, biplanar tablets with beveled edges, non-scored, embossed on one side with “CL” and “12.5.” The 25 mg tetrabenazine tablets are yellowish-buff, cylindrical, biplanar tablets with beveled edges, scored, embossed on one side with “CL” and “25.” Tablets: 12.5 mg non-scored and 25 mg scored ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Tetrabenazine tablets are contraindicated in patients: • Who are actively suicidal, or in patients with untreated or inadequately treated depression [see Warnings and Precautions (5.1) ]. • With hepatic impairment [see Use in Specific Populations (8.6) , Clinical Pharmacology (12.3) ]. • Taking monoamine oxidase inhibitors (MAOIs). Tetrabenazine tablets should not be used in combination with an MAOI, or within a minimum of 14 days of discontinuing therapy with an MAOI [see Drug Interactions ( 7.3 )]. • Taking reserpine.
At least 20 days should elapse after stopping reserpine before starting tetrabenazine tablets [see Drug Interactions (7.2) ] . • Taking deutetrabenazine or valbenazine [see Drug Interactions ( 7.7 )] . • Actively suicidal, or who have depression which is untreated or undertreated ( 4 , 5.1 ) • Hepatic impairment ( 4 , 8.6 , 12.3 ) • Taking monoamine oxidase inhibitors (MAOIs) or reserpine ( 4 , 7.2 , 7.3 ) • Taking deutetrabenazine or valbenazine ( 4 , 7.7 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Periodically reevaluate the benefit and potential for adverse effects such as worsening mood, cognition, rigidity, and functional capacity. ( 5.2 ) • Do not exceed 50 mg/day and the maximum single dose should not exceed 25 mg if administered in conjunction with a strong CYP2D6 inhibitor (e.g., fluoxetine, paroxetine). ( 5.3 , 7.1 ) • Neuroleptic Malignant Syndrome (NMS): Discontinue if this occurs.
( 5.4 , 7.6 ) • Restlessness, agitation, akathisia and parkinsonism: Reduce dose or discontinue if occurs. ( 5.5 , 5.6 ) • Sedation/Somnolence: May impair patient's ability to drive or operate complex machinery ( 5.7) • QTc prolongation: Not recommended in combination with other drugs that prolong QTc ( 5.8 )
5.1Depression and Suicidality Patients with Huntington’s disease are at increased risk for depression, suicidal ideation or behaviors (suicidality). Tetrabenazine tablets increase the risk for suicidality in patients with HD. In a 12-week, double-blind, placebo-controlled study in patients with chorea associated with Huntington’s disease, 10 of 54 patients (19%) treated with tetrabenazine were reported to have an adverse event of depression or worsening depression compared to none of the 30 placebo-treated patients.
In two open-label studies (in one study, 29 patients received tetrabenazine tablets for up to 48 weeks; in the second study, 75 patients received tetrabenazine tablets for up to 80 weeks), the rate of depression/worsening depression was 35%. In all of the HD chorea studies of tetrabenazine tablets (n=187), one patient committed suicide, one attempted suicide, and six had suicidal ideation. When considering the use of tetrabenazine tablets, the risk of suicidality should be balanced against the need for treatment of chorea.
All patients treated with tetrabenazine tablets should be observed for new or worsening depression or suicidality. If depression or suicidality does not resolve, consider discontinuing treatment with tetrabenazine tablets. Patients, their caregivers, and families should be informed of the risks of depression, worsening depression, and suicidality associated with tetrabenazine tablets, and should be instructed to report behaviors of concern promptly to the treating physician.
Patients with HD who express suicidal ideation should be evaluated immediately.
5.2Clinical Worsening and Adverse Effects Huntington’s disease is a progressive disorder characterized by changes in mood, cognition, chorea, rigidity, and functional capacity over time. In a 12-week controlled trial, tetrabenazine was also shown to cause slight worsening in mood, cognition, rigidity, and functional capacity. Whether these effects persist, resolve, or worsen with continued treatment is unknown.
Prescribers should periodically re-evaluate the need for tetrabenazine in their patients by assessing the effect on chorea and possible adverse effects, including depression and suicidality, cognitive decline, parkinsonism, dysphagia, sedation/somnolence, akathisia, restlessness, and disability. It may be difficult to distinguish between adverse reactions and progression of the underlying disease; decreasing the dose or stopping the drug may help the clinician distinguish between the two possibilities. In some patients, underlying chorea itself may improve over time, decreasing the need for tetrabenazine.
5.3Laboratory Tests Before prescribing a daily dose of tetrabenazine tablets that is greater than 50 mg/day, patients should be genotyped to determine if they express the drug metabolizing enzyme, CYP2D6. CYP2D6 testing is necessary to determine whether patients are poor metabolizers (PMs), extensive (EMs) or intermediate metabolizers (IMs) of tetrabenazine tablets. Patients who are PMs of tetrabenazine tablets will have substantially higher levels of the primary drug metabolites (about 3-fold for α-HTBZ and 9-fold for β-HTBZ) than patients who are EMs.
The dosage should be adjusted according to a patient’s C…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described below and elsewhere in the labeling: • Depression and Suicidality [see Warnings and Precautions (5.1) ] • Neuroleptic Malignant Syndrome (NMS) [see Warnings and Precautions (5.4) ] • Akathisia, Restlessness, and Agitation [see Warnings and Precautions (5.5) ] • Parkinsonism [see Warnings and Precautions (5.6) ] • Sedation and Somnolence [see Warnings and Precautions (5.7) ] • QTc Prolongation [see Warnings and Precautions (5.8) ] • Hypotension and Orthostatic Hypotension [see Warnings and Precautions (5.9) ] • Hyperprolactinemia [see Warnings and Precautions (5.10) ] • Binding to Melanin-Containing Tissues [see Warnings and Precautions (5.11) ] Most common adverse reactions (greater than 10% and at least 5% greater than placebo) were: sedation/somnolence, fatigue, insomnia, depression, akathisia, anxiety/anxiety aggravated, nausea.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Oceanside Pharmaceuticals at 1-800-321-4576 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. During its development, tetrabenazine tablets were administered to 773 unique subjects and patients. The conditions and duration of exposure to tetrabenazine varied greatly, and included single-dose and multiple-dose clinical pharmacology studies in healthy volunteers (n=259) and open-label (n=529) and double-blind studies (n=84) in patients.
In a randomized, 12-week, placebo-controlled clinical trial of HD patients, adverse reactions were more common in the tetrabenazine tablets group than in the placebo group. Forty-nine of 54 (91%) patients who received tetrabenazine tablets experienced one or more adverse reactions at any time during the study. The most common adverse reactions (over 10%, and at least 5% greater than placebo) were sedation/somnolence, fatigue, insomnia, depression, akathisia, anxiety/anxiety aggravated, and nausea.
Adverse Reactions Occurring in Greater Than or Equal to 4% of Patients The number and percentage of the most common adverse reactions that occurred at any time during the study in greater than or equal to 4% of tetrabenazine tablet-treated patients, and with a greater frequency than in placebo-treated patients, are presented in Table 1. Table 1: Adverse Reactions in a 12-Week, Double-Blind, Placebo-Controlled Trial in Patients with Huntington’s Disease Adverse Reaction Tetrabenazine Tablets n=54 % Placebo n=30 % Sedation/somnolence 31 3 Insomnia 22 0 Fatigue 22 13 Depression 19 0 Akathisia 19 0 Anxiety/anxiety aggravated 15 3 Fall 15 13 Nausea 13 7 Upper respiratory tract infection 11 7 Irritability 9 3 Balance difficulty 9 0 Parkinsonism/bradykinesia 9 0 Vomiting 6 3 Laceration (head) 6 0 Ecchymosis 6 0 Decreased appetite 4 0 Obsessive reaction 4 0 Dizziness 4 0 Dysarthria 4 0 Unsteady gait 4 0 Headache 4 3 Shortness of breath 4 0 Bronchitis 4 0 Dysuria 4 0 Dose escalation was discontinued or dosage of study drug was reduced because of one or more adverse reactions in 28 of 54 (52%) patients randomized to tetrabenazine tablets.
These adverse reactions consisted of sedation (15), akathisia (7), parkinsonism (4), depression (3), anxiety (2), fatigue (1) and diarrhea (1). Some patients had more than one AR and are, therefore, counted more than once. Adverse Reactions Due to Extrapyramidal Symptoms Table 2 describes the incidence of events considered to be extrapyramidal adverse reactions which occurred at a greater frequency in tetrabenazine tablet-treated patients compared to placebo-treated patients.
Table 2: Adverse Reactions Due to Extrapyramidal Symptoms in a 12-Week, Double-Blind, Placebo-Controlled Trial in Patients with Huntington’s Disease Tetrabenazine…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Strong CYP2D6 Inhibitors In vitro studies indicate that α-HTBZ and β-HTBZ are substrates for CYP2D6. Strong CYP2D6 inhibitors (e.g., paroxetine, fluoxetine, quinidine) markedly increase exposure to these metabolites. A reduction in tetrabenazine tablets dose may be necessary when adding a strong CYP2D6 inhibitor (e.g., fluoxetine, paroxetine, quinidine) in patients maintained on a stable dose of tetrabenazine tablets.
The daily dose of tetrabenazine should not exceed 50 mg/day and the maximum single dose of tetrabenazine tablets should not exceed 25 mg in patients taking strong CYP2D6 inhibitors [see Dosage and Administration (2.3) , Warnings and Precautions (5.3) , Use in Specific Populations ( 8.7 ), Clinical Pharmacology (12.3) ].
7.2Reserpine Reserpine binds irreversibly to VMAT2, and the duration of its effect is several days. Prescribers should wait for chorea to re-emerge before administering tetrabenazine tablets to avoid overdosage and major depletion of serotonin and norepinephrine in the CNS. At least 20 days should elapse after stopping reserpine before starting tetrabenazine tablets.
Tetrabenazine tablets and reserpine should not be used concomitantly [see Contraindications (4) ].
7.3Monoamine Oxidase Inhibitors (MAOIs) Tetrabenazine tablets are contraindicated in patients taking MAOIs. Tetrabenazine tablets should not be used in combination with an MAOI, or within a minimum of 14 days of discontinuing therapy with an MAOI [see Contraindications (4) ].
7.4Alcohol or Other Sedating Drugs Concomitant use of alcohol or other sedating drugs may have additive effects and worsen sedation and somnolence [see Warnings and Precautions (5.7) ] .
7.5Drugs That Cause QTc Prolongation Tetrabenazine tablets cause a small prolongation of QTc (about 8 msec), concomitant use with other drugs that are known to cause QTc prolongation should be avoided, these including antipsychotic medications (e.g., chlorpromazine, haloperidol, thioridazine, ziprasidone), antibiotics (e.g., moxifloxacin), Class 1A (e.g., quinidine, procainamide) and Class III (e.g., amiodarone, sotalol) antiarrhythmic medications or any other medications known to prolong the QTc interval. Tetrabenazine tablets should be avoided in patients with congenital long QT syndrome and in patients with a history of cardiac arrhythmias.
Certain conditions may increase the risk for torsade de pointes or sudden death such as (1) bradycardia; (2) hypokalemia or hypomagnesemia; (3) concomitant use of other drugs that prolong the QTc interval; and (4) presence of congenital prolongation of the QT interval [see Warnings and Precautions ( 5.8 ), Clinical Pharmacology (12.2) ].
7.6Neuroleptic Drugs The risk for Parkinsonism, NMS, and akathisia may be increased by concomitant use of tetrabenazine tablets and dopamine antagonists or antipsychotics (e.g., chlorpromazine, haloperidol, olanzapine, risperidone, thioridazine, ziprasidone) [see Warnings and Precautions ( 5.4 , 5.5 , 5.6 )] .
7.7Concomitant Deutetrabenazine or Valbenazine Tetrabenazine tablets are contraindicated in patients currently taking deutetrabenazine or valbenazine.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm. ( 8.1 )
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with the use of tetrabenazine tablets in pregnant women. Administration of tetrabenazine to rats throughout pregnancy and lactation resulted in an increase in stillbirths and postnatal offspring mortality. Administration of a major human metabolite of tetrabenazine to rats during pregnancy or during pregnancy and lactation produced adverse effects on the developing fetus and offspring (increased mortality, decreased growth, and neurobehavioral and reproductive impairment).
The adverse developmental effects of tetrabenazine and a major human metabolite of tetrabenazine in rats occurred at clinically relevant doses [see Data] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
Data Animal Data Tetrabenazine had no clear effects on embryofetal development when administered to pregnant rats throughout the period of organogenesis at oral doses up to 30 mg/kg/day (or 3 times the maximum recommended human dose [MRHD] of 100 mg/day on a mg/m 2 basis). Tetrabenazine had no effects on embryofetal development when administered to pregnant rabbits during the period of organogenesis at oral doses up to 60 mg/kg/day (or 12 times the MRHD on a mg/m 2 basis). When tetrabenazine (5, 15, and 30 mg/kg/day) was orally administered to pregnant rats from the beginning of organogenesis through the lactation period, an increase in stillbirths and offspring postnatal mortality was observed at 15 and 30 mg/kg/day and delayed pup maturation was observed at all doses.
A no-effect dose for pre- and postnatal developmental toxicity in rats was not identified. The lowest dose tested (5 mg/kg/day) was less than the MRHD on a mg/m 2 basis. Because rats dosed orally with tetrabenazine do not produce 9-desmethyl-β-DHTBZ, a major human metabolite of tetrabenazine, the metabolite was directly administered to pregnant and lactating rats.
Oral administration of 9-desmethyl-β-DHTBZ (8, 15, and 40 mg/kg/day) throughout the period of organogenesis produced increases in embryofetal mortality at 15 and 40 mg/kg/day and reductions in fetal body weights at 40 mg/kg/day, which was also maternally toxic. When 9-desmethyl-β-DHTBZ (8, 15, and 40 mg/kg/day) was orally administered to pregnant rats from the beginning of organogenesis through the lactation period, increases in gestation duration, stillbirths, and offspring postnatal mortality (40 mg/kg/day); decreases in pup weights (40 mg/kg/day); and neurobehavioral (increased activity, learning and memory deficits) and reproductive (decreased litter size) impairment (15 and 40 mg/kg/day) were observed.
Maternal toxicity was seen at the highest dose. The no-effect dose for developmental toxicity in rats (8 mg/kg/day) was associated with plasma exposures (AUC) of 9-desmethyl-β-DHTBZ in pregnant rats lower than that in humans at the MRHD.
8.2Lactation Risk Summary There are no data on the presence of tetrabenazine or its metabolites in human milk, the effects on the breastfed infant, or the effects of the drug on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for tetrabenazine and any potential adverse effects on the breastfed infant from tetrabenazine tablets or from the underlying maternal condition.
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
8.5Geriatric Use The pharmacokinetics of tetrabenazine tablets and its primary metabolites have not been formally studied in geriatric subjects.
8.6Hepatic Impairment Because the safety and efficacy of the increased exposure to tetrabenazine tablets a…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with the use of tetrabenazine tablets in pregnant women. Administration of tetrabenazine to rats throughout pregnancy and lactation resulted in an increase in stillbirths and postnatal offspring mortality. Administration of a major human metabolite of tetrabenazine to rats during pregnancy or during pregnancy and lactation produced adverse effects on the developing fetus and offspring (increased mortality, decreased growth, and neurobehavioral and reproductive impairment).
The adverse developmental effects of tetrabenazine and a major human metabolite of tetrabenazine in rats occurred at clinically relevant doses [see Data] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
Data Animal Data Tetrabenazine had no clear effects on embryofetal development when administered to pregnant rats throughout the period of organogenesis at oral doses up to 30 mg/kg/day (or 3 times the maximum recommended human dose [MRHD] of 100 mg/day on a mg/m 2 basis). Tetrabenazine had no effects on embryofetal development when administered to pregnant rabbits during the period of organogenesis at oral doses up to 60 mg/kg/day (or 12 times the MRHD on a mg/m 2 basis). When tetrabenazine (5, 15, and 30 mg/kg/day) was orally administered to pregnant rats from the beginning of organogenesis through the lactation period, an increase in stillbirths and offspring postnatal mortality was observed at 15 and 30 mg/kg/day and delayed pup maturation was observed at all doses.
A no-effect dose for pre- and postnatal developmental toxicity in rats was not identified. The lowest dose tested (5 mg/kg/day) was less than the MRHD on a mg/m 2 basis. Because rats dosed orally with tetrabenazine do not produce 9-desmethyl-β-DHTBZ, a major human metabolite of tetrabenazine, the metabolite was directly administered to pregnant and lactating rats.
Oral administration of 9-desmethyl-β-DHTBZ (8, 15, and 40 mg/kg/day) throughout the period of organogenesis produced increases in embryofetal mortality at 15 and 40 mg/kg/day and reductions in fetal body weights at 40 mg/kg/day, which was also maternally toxic. When 9-desmethyl-β-DHTBZ (8, 15, and 40 mg/kg/day) was orally administered to pregnant rats from the beginning of organogenesis through the lactation period, increases in gestation duration, stillbirths, and offspring postnatal mortality (40 mg/kg/day); decreases in pup weights (40 mg/kg/day); and neurobehavioral (increased activity, learning and memory deficits) and reproductive (decreased litter size) impairment (15 and 40 mg/kg/day) were observed.
Maternal toxicity was seen at the highest dose. The no-effect dose for developmental toxicity in rats (8 mg/kg/day) was associated with plasma exposures (AUC) of 9-desmethyl-β-DHTBZ in pregnant rats lower than that in humans at the MRHD.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use The pharmacokinetics of tetrabenazine tablets and its primary metabolites have not been formally studied in geriatric subjects.
🆘 Overdosage ▾
10 OVERDOSAGE Three episodes of overdose occurred in the open-label trials performed in support of registration. Eight cases of overdose with tetrabenazine tablets have been reported in the literature. The dose of tetrabenazine tablets in these patients ranged from 100 mg to 1 g.
Adverse reactions associated with tetrabenazine tablets overdose include acute dystonia, oculogyric crisis, nausea and vomiting, sweating, sedation, hypotension, confusion, diarrhea, hallucinations, rubor, and tremor. Treatment should consist of those general measures employed in the management of overdosage with any CNS-active drug. General supportive and symptomatic measures are recommended.
Cardiac rhythm and vital signs should be monitored. In managing overdosage, the possibility of multiple drug involvement should always be considered. The physician should consider contacting a poison control center on the treatment of any overdose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The precise mechanism by which tetrabenazine tablets exert its anti-chorea effects is unknown but is believed to be related to its effect as a reversible depletor of monoamines (such as dopamine, serotonin, norepinephrine, and histamine) from nerve terminals. Tetrabenazine reversibly inhibits the human vesicular monoamine transporter type 2 (VMAT2) (K i ≈ 100 nM), resulting in decreased uptake of monoamines into synaptic vesicles and depletion of monoamine stores. Human VMAT2 is also inhibited by dihydrotetrabenazine (HTBZ), a mixture of α-HTBZ and β-HTBZ. α- and β-HTBZ, major circulating metabolites in humans, exhibit high in vitro binding affinity to bovine VMAT2.
Tetrabenazine exhibits weak in vitro binding affinity at the dopamine D2 receptor (K i = 2100 nM).
12.2Pharmacodynamics QTc Prolongation The effect of a single 25 or 50 mg dose of tetrabenazine tablets on the QT interval was studied in a randomized, double-blind, placebo-controlled crossover study in healthy male and female subjects with moxifloxacin as a positive control. At 50 mg, tetrabenazine caused an approximately 8 msec mean increase in QTc (90% CI: 5.0, 10.4 msec). Additional data suggest that inhibition of CYP2D6 in healthy subjects given a single 50 mg dose of tetrabenazine does not further increase the effect on the QTc interval.
Effects at higher exposures to either tetrabenazine tablets or its metabolites have not been evaluated [see Warnings and Precautions (5.8) , Drug Interactions (7.5) ]. Melanin Binding Tetrabenazine or its metabolites bind to melanin-containing tissues (i.e., eye, skin, fur) in pigmented rats. After a single oral dose of radiolabeled tetrabenazine, radioactivity was still detected in eye and fur at 21 days post dosing [see Warnings and Precautions (5.11) ].
12.3Pharmacokinetics Absorption Following oral administration of tetrabenazine, the extent of absorption is at least 75%. After single oral doses ranging from 12.5 to 50 mg, plasma concentrations of tetrabenazine are generally below the limit of detection because of the rapid and extensive hepatic metabolism of tetrabenazine by carbonyl reductase to the active metabolites α-HTBZ and β-HTBZ. α-HTBZ and β-HTBZ are metabolized principally by CYP2D6. Peak plasma concentrations (C max ) of α-HTBZ and β-HTBZ are reached within 1 to 1½ hours post-dosing. α-HTBZ is subsequently metabolized to a minor metabolite, 9-desmethyl-α-DHTBZ. β-HTBZ is subsequently metabolized to another major circulating metabolite, 9-desmethyl-β-DHTBZ, for which C max is reached approximately 2 hours post-dosing.
Food Effects The effects of food on the bioavailability of tetrabenazine tablets were studied in subjects administered a single dose with and without food. Food had no effect on mean plasma concentrations, C max , or the area under the concentration time course (AUC) of α-HTBZ or β-HTBZ [see Dosage and Administration (2.1) ]. Distribution Results of PET-scan studies in humans show that radioactivity is rapidly distributed to the brain following intravenous injection of 11 C-labeled tetrabenazine or α-HTBZ, with the highest binding in the striatum and lowest binding in the cortex.
The in vitro protein binding of tetrabenazine, α-HTBZ, and β-HTBZ was examined in human plasma for concentrations ranging from 50 to 200 ng/mL. Tetrabenazine binding ranged from 82% to 85%, α-HTBZ binding ranged from 60% to 68%, and β-HTBZ binding ranged from 59% to 63%. Metabolism After oral administration in humans, at least 19 metabolites of tetrabenazine have been identified. α-HTBZ, β-HTBZ and 9-desmethyl-β-DHTBZ are the major circulating metabolites and are subsequently metabolized to sulfate or glucuronide conjugates. α-HTBZ and β-HTBZ are formed by carbonyl reductase that occurs mainly in the liver. α-HTBZ is O-dealkylated by CYP450 enzymes, principally CYP2D6, with some contribution of CYP1A2 to form 9-desmethyl-α-DHTBZ, a minor metabolite. β-HTBZ is O-dealkylated…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The precise mechanism by which tetrabenazine tablets exert its anti-chorea effects is unknown but is believed to be related to its effect as a reversible depletor of monoamines (such as dopamine, serotonin, norepinephrine, and histamine) from nerve terminals. Tetrabenazine reversibly inhibits the human vesicular monoamine transporter type 2 (VMAT2) (K i ≈ 100 nM), resulting in decreased uptake of monoamines into synaptic vesicles and depletion of monoamine stores. Human VMAT2 is also inhibited by dihydrotetrabenazine (HTBZ), a mixture of α-HTBZ and β-HTBZ. α- and β-HTBZ, major circulating metabolites in humans, exhibit high in vitro binding affinity to bovine VMAT2.
Tetrabenazine exhibits weak in vitro binding affinity at the dopamine D2 receptor (K i = 2100 nM).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Tetrabenazine tablets are available in the following strengths and packages: The 12.5 mg tetrabenazine tablets are white, cylindrical, biplanar tablets with beveled edges, non-scored, embossed on one side with “CL” and “12.5”. NDC 68682-421-12 12.5 mg 112-count bottle The 25 mg tetrabenazine tablets are yellowish-buff, cylindrical, biplanar tablets with beveled edges, scored, embossed on one side with “CL” and “25”. NDC 68682-422-25 25 mg 112-count bottle
16.2Storage Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
📦 Storage and Handling ▾
16.2Storage Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Tetrabenazine tablets are a monoamine depletor for oral administration. The molecular weight of tetrabenazine is 317.43; the pKa is 6.51. Tetrabenazine is a hexahydro-dimethoxy-benzoquinolizine derivative and has the following chemical name: cis rac –1,3,4,6,7,11b-hexahydro-9,10-dimethoxy-3-(2-methylpropyl)-2H-benzo[a]quinolizin-2-one.
The empirical formula C 19 H 27 NO 3 is represented by the following structural formula: Tetrabenazine is a white to slightly yellow crystalline powder that is sparingly soluble in water and soluble in ethanol. Each tetrabenazine tablet contains either 12.5 or 25 mg of tetrabenazine as the active ingredient. Tetrabenazine tablets contain tetrabenazine as the active ingredient and the following inactive ingredients: lactose, magnesium stearate, maize starch, and talc.
The 25 mg strength tablet also contains yellow iron oxide as an inactive ingredient. Tetrabenazine tablets are supplied as a yellowish-buff, scored tablet containing 25 mg of tetrabenazine or as a white, non-scored tablet containing 12.5 mg of tetrabenazine. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Risk of Suicidality Inform patients and their families that tetrabenazine tablets may increase the risk of suicidal thinking and behaviors. Counsel patients and their families to remain alert to the emergence of suicidal ideation and to report it immediately to the patient’s physician [see Contraindications ( 4 ), Warnings and Precautions ( 5.1 )] .
Risk of Depression Inform patients and their families that tetrabenazine tablets may cause depression or may worsen pre-existing depression. Encourage patients and their families to be alert to the emergence of sadness, worsening of depression, withdrawal, insomnia, irritability, hostility (aggressiveness), akathisia (psychomotor restlessness), anxiety, agitation, or panic attacks and to report such symptoms promptly to the patient’s physician [see Contraindications ( 4 ), Warnings and Precautions ( 5.1 )] . Dosing of Tetrabenazine Tablets Inform patients and their families that the dose of tetrabenazine tablets will be increased slowly to the dose that is best for each patient.
Sedation, akathisia, parkinsonism, depression, and difficulty swallowing may occur. Such symptoms should be promptly reported to the physician, and the tetrabenazine tablets dose may need to be reduced or discontinued [see Dosage and Administration ( 2.2 )] . Risk of Sedation and Somnolence Inform patients that tetrabenazine tablets may induce sedation and somnolence and may impair the ability to perform tasks that require complex motor and mental skills.
Advise patients that until they learn how they respond to tetrabenazine tablets, they should be careful doing activities that require them to be alert, such as driving a car or operating machinery [see Warnings and Precautions (5.7) ] . Interaction with Alcohol Advise patients and their families that alcohol may potentiate the sedation induced by tetrabenazine tablets [see Drug Interactions ( 7.4 )] . Usage in Pregnancy Advise patients and their families to notify the physician if the patient becomes pregnant or intends to become pregnant during tetrabenazine tablets therapy, or is breastfeeding or intending to breastfeed an infant during therapy [see Use in Specific Populations ( 8.1 )].
Distributed by: Oceanside Pharmaceuticals, a division of Bausch Health US, LLC Bridgewater, NJ 08807 USA Manufactured by: Recipharm Fontaine SAS Rue des Prés Potets 21121 Fontaine-lés-Dijon France All other product/brand names and/or logos are trademarks of the respective owners. © 2020 Bausch Health Companies Inc. or its affiliates 9443704
💬 Medication Guide ▾
MEDICATION GUIDE Tetrabenazine Tablets Read the Medication Guide that comes with tetrabenazine tablets before you start taking it and each time you refill the prescription. There may be new information. This information does not take the place of talking with your doctor about your medical condition or your treatment.
You should share this information with your family members and caregivers. What is the most important information I should know about tetrabenazine tablets? • Tetrabenazine tablets can cause serious side effects, including: o depression o suicidal thoughts o suicidal actions • You should not start taking tetrabenazine tablets if you are depressed (have untreated depression or depression that is not well controlled by medicine) or have suicidal thoughts. • Pay close attention to any changes, especially sudden changes, in mood, behaviors, thoughts or feelings.
This is especially important when tetrabenazine tablets are started and when the dose is changed. Call the doctor right away if you become depressed or have any of the following symptoms, especially if they are new, worse, or worry you: • feel sad or have crying spells • lose interest in seeing your friends or doing things you used to enjoy • sleep a lot more or a lot less than usual • feel unimportant • feel guilty • feel hopeless or helpless • more irritable, angry or aggressive than usual • more or less hungry than usual or notice a big change in your body weight • have trouble paying attention • feel tired or sleepy all the time • have thoughts about hurting yourself or ending your life What are tetrabenazine tablets?
Tetrabenazine tablets are a medicine that is used to treat the involuntary movements (chorea) of Huntington’s disease. Tetrabenazine tablets do not cure the cause of the involuntary movements, and it does not treat other symptoms of Huntington’s disease, such as problems with thinking or emotions. It is not known whether tetrabenazine tablets are safe and effective in children.
Who should not take tetrabenazine tablets? Do not take tetrabenazine tablets if you: • are depressed or have thoughts of suicide. See “What is the most important information I should know about tetrabenazine tablets?” • have liver problems. • are taking a monoamine oxidase inhibitor (MAOI) medicine.
Ask your doctor or pharmacist if you are not sure. • are taking reserpine. Do not take medicines that contain reserpine (such as Serpalan and Renese-R) with tetrabenazine tablets. If your doctor plans to switch you from taking reserpine to tetrabenazine tablets, you must wait at least 20 days after your last dose of reserpine before you start taking tetrabenazine tablets.
What should I tell my doctor before taking tetrabenazine tablets? Tell your doctor about all your medical conditions, including if you: • have emotional or mental problems (for example, depression, nervousness, anxiety, anger, agitation, psychosis, previous suicidal thoughts or suicide attempts). • have liver disease. • have any allergies. See the end of this Medication Guide for a complete list of the ingredients in tetrabenazine tablets. • have breast cancer or a history of breast cancer. • have heart disease that is not stable, have heart failure or recently had a heart attack. • have an irregular heartbeat (cardiac arrhythmia). • are pregnant or plan to become pregnant.
It is not known if tetrabenazine tablets can harm your unborn baby. • are breastfeeding. It is not known if tetrabenazine tablets passes into breast milk. Tell your doctor about all the medicines you take, including prescription medicines and nonprescription medicines, vitamins and herbal products.
Using tetrabenazine tablets with certain other medicines may cause serious side effects . Do not start any new medicines while taking tetrabenazine tablets without talking to your doctor first. How should I take tetrabenazine tablets? • Tetrabenazine is a tablet that you take by mouth. • Take tetrabenazine tablets exactly as prescribed by yo…