
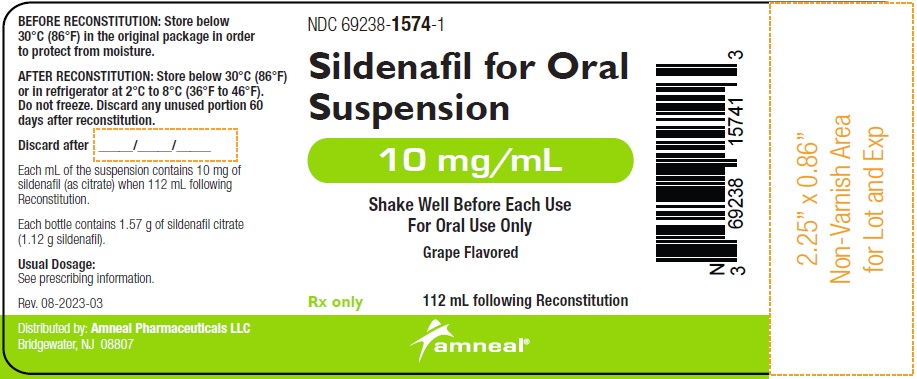
Sildenafil 10 mg/mL Powder, For Suspension
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Phosphodiesterase 5 Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Sildenafil (Viagra) is used to treat erectile dysfunction (impotence; inability to get or keep an erection) in men. Sildenafil (Liqrev, Revatio) is used to improve the ability to exercise in adults (Liqrev, Revatio) and children 1 year of age and older (Revatio) with pulmonary arterial hypertension (PAH; high blood pressure in the vessels carrying blood to the lungs, causing shortness of breath, dizziness, and tiredness). Sildenafil is in a class of medications called phosphodiesterase (PDE) inhibitors. Sildenafil treats erectile dysfunction by increasing blood flow to the penis during sexual...
Read the full MedlinePlus article ↗- For erectile dysfunction, you take sildenafil only when you need it — about 30 minutes to 1 hour before sexual activity works best, though anywhere from 30 minutes to 4 hours ahead...
- Can I take Viagra or generic sildenafil just before sex, or do I need to take it every day?
- Both sildenafil and nitrates lower blood pressure, and together their effect on blood pressure can be dangerously large — we're talking about a drop severe enough to cause fainting...
- Why can't I take sildenafil with nitroglycerin or other nitrate medicines?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Sildenafil — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII OJ245FE5EU
Sodium benzoate is a salt derived from benzoic acid, a preservative. It's added to medicines to prevent growth of bacteria, fungi, and other microorganisms that could spoil the product.
-
UNII 1Q73Q2JULR
Sodium citrate is a salt derived from citric acid. It works as a buffer to maintain the medicine's pH level and may also help improve taste or act as a preservative in the formulation.
-
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 96K6UQ3ZD4
Sucralose is a synthetic sweetener made from sugar. It's added to medicines to improve taste without adding calories, helping make bitter or unpleasant-tasting drugs easier to take.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII TTV12P4NEE
Xanthan gum is a thickening and stabilizing ingredient made from fermented corn or other sugars. It's added to medicines to improve texture, prevent separation of liquids and solids, and help the product stay consistent.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.273 | $30.54 / 112 ml |
| Medicaid paysCMS SDUD · 12 mo | $3.79 | $424.21 / 112 ml |
| Medicare drug plans payPart D · Q2 2026 | $3.32 | $372.05 / 112 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Sildenafil 10 mg/mL 00591-4050-94 | Actavis | 1 bottle | $0.273 | AB | Availability likely | — |
| Sildenafil 10 mg/mL 27241-0175-29 | Ajanta | 1 pouch | $0.273 | AB | Availability likely | — |
| Sildenafil 10 mg/mL 31722-0136-31 | Camber | 1 bottle | $0.273 | AB | Availability likely | — |
| sildenafil CITRATE 10 mg/mL 59651-0420-11 | Aurobindo | 1 bottle | $0.273 | AB | Availability likely | — |
| Sildenafil 10 mg/mL 60219-2651-01 | Amneal | 1 bottle | $0.273 | AB | Availability likely | — |
| Sildenafil 10 mg/mLthis 69238-1574-01 | Amneal | 1 bottle | $0.273 | AB | Availability likely | — |
| Sildenafil Citrate 10 mg/mL 70710-1716-04 | Zydus | 1 bottle | $0.273 | AB | Availability likely | — |
| Sildenafil 10 mg/mL 70954-0168-10 | ANI | 1 bottle | $0.273 | AB | Availability likely | — |
| sildenafil citrate 10 mg/mL 72205-0059-76 | Novadoz | 1 bottle | $0.273 | AB | Availability likely | — |
| Sildenafil Citrate 10 mg/mL 67877-0648-11 | Ascend | 1 bottle | — | AB | FDA listed | — |
| Sildenafil 10 mg/mL 68180-0283-01 | Lupin | 1 bottle | — | — | FDA listed | — |
| sildenafil 10 mg/mL 69543-0419-72 | Virtus | 1 bottle | — | AB | FDA listed | — |
| Sildenafil Citrate 10 mg/mL 70771-1668-04 | Zydus | 1 bottle | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 69238-1574-01 You're viewing this | 1 BOTTLE, GLASS in 1 CARTON (69238-1574-1) / 112 mL in 1 BOTTLE, GLASS | 2019-12-06 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Adults Sildenafil for oral suspension is indicated for the treatment of pulmonary arterial hypertension (PAH) (World Health Organization [WHO] Group I) in adults to improve exercise ability and delay clinical worsening [see Clinical Studies (14) ] . Pediatric use information is approved for Viatris Specialty LLC’s, REVATIO (sildenafil) oral suspension. However, due to Viatris Specialty LLC’s marketing exclusivity rights, this drug product is not labeled with that information.
Adults Sildenafil for oral suspension is a phosphodiesterase-5 (PDE-5) inhibitor indicated for the treatment of pulmonary arterial hypertension (PAH) (World Health Organization [WHO] Group I) in adults to improve exercise ability and delay clinical worsening. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Adults: 20 mg three times a day. ( 2.1 )
2.1Recommended Dosage in Adults Oral Dosage The recommended dosage of sildenafil for oral suspension is 20 mg three times a day [see Clinical Studies (14) ] . Pediatric use information is approved for Viatris Specialty LLC’s, REVATIO (sildenafil) oral suspension. However, due to Viatris Specialty LLC’s marketing exclusivity rights, this drug product is not labeled with that information.
2.3Reconstitution of the Powder for Oral Suspension Note: Reconstitute the contents of the bottle with a total volume of 90 mL (60 mL followed by 30 mL) . Refer to the detailed instructions below. Tap the bottle to loosen the powder.
Add 60 mL of water to the bottle. Replace the cap and shake the bottle vigorously for a minimum of 30 seconds. Add another 30 mL of water to the bottle.
Replace the cap and shake the bottle vigorously for a minimum of 30 seconds. Remove the cap and press the bottle adaptor into the neck of the bottle. Replace the cap on the bottle.
Write the expiration date of the reconstituted oral suspension on the bottle label (the expiration date of the reconstituted oral suspension is 60 days from the date of reconstitution). Incompatibilities Do not mix with any other medication or additional flavoring agent.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Sildenafil for Oral Suspension White to off-white powder containing 1.57 g of sildenafil citrate, USP (equivalent to 1.12 g of sildenafil) in a bottle for reconstitution to 10 mg/mL. Following reconstitution with 90 mL of water, the total volume of the oral suspension is 112 mL. A 2 mL oral dosing syringe (with 0.5 mL and 2 mL dose markings) and a press-in bottle adaptor are also provided.
For Oral Suspension: 10 mg/mL (when reconstituted) ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Sildenafil for oral suspension is contraindicated in patients with: Concomitant use of organic nitrates in any form, either regularly or intermittently, because of the greater risk of hypotension [see Warnings and Precautions (5.1) ] . Concomitant use of riociguat, a guanylate cyclase stimulator. Phosphodiesterase-5 (PDE-5) inhibitors, including sildenafil, may potentiate the hypotensive effects of riociguat.
Known hypersensitivity to sildenafil or any component of the oral suspension. Hypersensitivity, including anaphylactic reaction, anaphylactic shock and anaphylactoid reaction, has been reported in association with the use of sildenafil. Use with organic nitrates or riociguat.
( 4 ) History of hypersensitivity reaction to sildenafil or any component of the oral suspension. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Vasodilation effects may be more common in patients with hypotension or on antihypertensive therapy. ( 5.1 ) Use in pulmonary veno-occlusive disease (PVOD) may cause pulmonary edema and is not recommended. ( 5.2 ) Hearing or visual impairment: Seek medical attention if sudden decrease or loss of vision or hearing occurs.
( 5.4 , 5.5 ) Pulmonary hypertension (PH) secondary to sickle cell disease: Sildenafil may cause serious vaso-occlusive crises. ( 5.8 )
5.1Hypotension Sildenafil has vasodilatory properties, resulting in mild and transient decreases in blood pressure. Before prescribing sildenafil, carefully consider whether patients with certain underlying conditions could be adversely affected by such vasodilatory effects (e.g., patients on antihypertensive therapy or with resting hypotension [blood pressure less than 90/50], fluid depletion, severe left ventricular outflow obstruction, or autonomic dysfunction). Monitor blood pressure when co-administering blood pressure lowering drugs with sildenafil.
5.2Worsening Pulmonary Vascular Occlusive Disease Pulmonary vasodilators may significantly worsen the cardiovascular status of patients with pulmonary veno-occlusive disease (PVOD). Since there are no clinical data on administration of sildenafil to patients with veno-occlusive disease, administration of sildenafil to such patients is not recommended. Should signs of pulmonary edema occur when sildenafil is administered, consider the possibility of associated PVOD.
5.3Epistaxis The incidence of epistaxis was 13% in patients taking sildenafil with PAH secondary to CTD. This effect was not seen in idiopathic PAH (sildenafil 3%, placebo 2%) patients. The incidence of epistaxis was also higher in sildenafil-treated patients with a concomitant oral vitamin K antagonist (9% versus 2% in those not treated with concomitant vitamin K antagonist).
The safety of sildenafil is unknown in patients with bleeding disorders or active peptic ulceration.
5.4Visual Loss When used to treat erectile dysfunction, non-arteritic anterior ischemic optic neuropathy (NAION), a cause of decreased vision including permanent loss of vision, has been reported post-marketing in temporal association with the use of PDE-5 inhibitors, including sildenafil. Most patients had underlying anatomic or vascular risk factors for developing NAION, including low cup to disc ratio (“crowded disc”). Advise patients to seek immediate medical attention in the event of a sudden loss of vision in one or both eyes while taking sildenafil.
There are no controlled clinical data on the safety or efficacy of sildenafil in patients with retinitis pigmentosa, a minority of whom have genetic disorders of retinal phosphodiesterases. Therefore, use of sildenafil in patients with retinitis pigmentosa is not recommended.
5.5Hearing Loss Cases of sudden decrease or loss of hearing, which may be accompanied by tinnitus and dizziness, have been reported in temporal association with the use of PDE-5 inhibitors, including sildenafil. In some of the cases, medical conditions and other factors were reported that may have played a role. In many cases, medical follow-up information was limited.
It is not possible to determine whether these reported events are related directly to the use of sildenafil, to the patient’s underlying risk factors for hearing loss, a combination of these factors, or to other factors. Advise patients to seek prompt medical attention in the event of sudden decrease or loss of hearing while taking PDE-5 inhibitors, including sildenafil.
5.6Combination with Other PDE-5 Inhibitors Sildenafil is also marketed as VIAGRA ® . The safety and efficacy of combinations of sildenafil for oral suspension with VIAGRA or other PDE-5 inhibitors have not been studied. Inform patients taking sildenafil for oral suspension not to take VIAGRA or other PDE-5 inhibitors.
5.7 Priapism Use sildenafil with caution in patients with anatomical deformation of the p…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse events are discussed elsewhere in the labeling: Hypotension [see Warnings and Precautions (5.1) ] Vision Loss [see Warnings and Precautions (5.4) ] Hearing Loss [see Warnings and Precautions (5.5) ] Priapism [see Warnings and Precautions (5.7) ] Vaso-occlusive Crisis in Patients with Pulmonary Hypertension Secondary to Sickle Cell Disease [see Warnings and Precautions (5.8) ] Adults: Headache, dyspepsia, flushing, pain in limb, myalgia, back pain and diarrhea. ( 6.1 , 6.2 ) To report SUSPECTED ADVERSE REACTIONS, contact Amneal Pharmaceuticals at 1-877-835-5472 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In a 12-week, placebo-controlled clinical study and an open-label extension study (SUPER-1) in 277 sildenafil-treated adults with PAH (WHO Group I) [see Clinical Studies (14) ] the adverse reactions that were reported by at least 10% of sildenafil-treated patients in any dosing group, and were more frequent in sildenafil-treated patients than in placebo-treated patients are shown in Table 1.
Adverse reactions were generally transient and mild to moderate in nature. The overall frequency of discontinuation in sildenafil-treated patients was 3% (20 mg three times a day). The overall frequency of discontinuation for placebo was 3%.
Table 1: Most Common Adverse Reactions in Patients Treated with Sildenafil 20 mg and Placebo three times per day in SUPER-1 (More Frequent in Sildenafil-Treated Patients than Placebo-Treated Patients) Sildenafil 20 mg (n = 69) Placebo (n = 70) Headache 46% 39% Flushing 10% 4% Pain in Limb 7% 6% Myalgia 7% 4% Back Pain 13% 11% Dyspepsia 13% 7% Diarrhea 9% 6% In a placebo-controlled fixed dose titration study (PACES-1) of sildenafil (starting with recommended dose of 20 mg and increased to 40 mg and then 80 mg all three times a day) as an adjunct to intravenous epoprostenol in patients with PAH, no new safety issues were identified except for edema, which occurred in 25% of subjects in the combined sildenafil + epoprostenol group compared with 13% of subjects in the epoprostenol group [see Clinical Studies (14) ] .
Pediatric use information is approved for Viatris Specialty LLC’s, REVATIO (sildenafil) oral suspension. However, due to Viatris Specialty LLC’s marketing exclusivity rights, this drug product is not labeled with that information.
6.2Post-marketing Experience The following adverse reactions have been identified during post approval use of sildenafil (marketed for both PAH and erectile dysfunction). Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Cardiovascular Events In post-marketing experience with sildenafil at doses indicated for erectile dysfunction, serious cardiovascular, cerebrovascular, and vascular events, including myocardial infarction, sudden cardiac death, ventricular arrhythmia, cerebrovascular hemorrhage, transient ischemic attack, hypertension, pulmonary hemorrhage, and subarachnoid and intracerebral hemorrhages have been reported in temporal association with the use of the drug.
Most, but not all, of these patients had preexisting cardiovascular risk factors. Many of these events were reported to occur during or shortly after sexual activity, and a few were reported to occur shortly after the use of sildenafil without sexual activity. Others were reported to have occurred hours to days after use concurrent with sexual activity.
It is not possible to determine whether these events are related directly to sildenafil, to sexual activity, to the patient’s underlying cardiovascular dis…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Nitrates Concomitant use of sildenafil with nitrates in any form is contraindicated [see Contraindications (4) ] . Strong CYP3A Inhibitors Concomitant use of sildenafil with strong CYP3A inhibitors is not recommended [see Clinical Pharmacology (12.3) ] . Moderate-to-Strong CYP3A Inducers Concomitant use of sildenafil with moderate-to-strong CYP3A inducers (such as bosentan) decreases the sildenafil exposure.
Dose up-titration of sildenafil may be needed when initiating treatment with moderate-to-strong CYP3A inducers. Reduce the dose of sildenafil to 20 mg three times a day when discontinuing treatment with moderate-to-strong CYP3A inducers [see Clinical Pharmacology (12.3) and Clinical Studies (14) ] . Use with strong CYP3A inhibitors: Not recommended.
( 7 , 12.3 ) Concomitant PDE-5 inhibitors: Avoid use with Viagra ® or other PDE-5 inhibitors. ( 5.6 ) Pediatric use information is approved for Viatris Specialty LLC’s, REVATIO (sildenafil) oral suspension. However, due to Viatris Specialty LLC’s marketing exclusivity rights, this drug product is not labeled with that information.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Limited published data from randomized controlled trials, case-controlled trials, and case series do not report a clear association with sildenafil and major birth defects, miscarriage, or adverse maternal or fetal outcomes when sildenafil is used during pregnancy. There are risks to the mother and fetus from untreated pulmonary arterial hypertension (see Clinical Considerations ) . Animal reproduction studies conducted with sildenafil showed no evidence of embryo-fetal toxicity or teratogenicity at doses up to 32- and 65-times the recommended human dose (RHD) of 20 mg three times a day in rats and rabbits, respectively (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Pregnant women with untreated pulmonary arterial hypertension are at risk for heart failure, stroke, preterm delivery, and maternal and fetal death. Data Animal Data No evidence of teratogenicity, embryotoxicity, or fetotoxicity was observed in pregnant rats or rabbits dosed with sildenafil 200 mg/kg/day during organogenesis, a level that is, on a mg/m 2 basis, 32- and 65-times, respectively, the recommended human dose (RHD) of 20 mg three times a day.
In a rat pre- and postnatal development study, the no-observed-adverse-effect dose was 30 mg/kg/day (equivalent to 5-times the RHD on a mg/m 2 basis).
8.2Lactation Risk Summary Limited published data from a case report describe the presence of sildenafil and its active metabolite in human milk. There is insufficient information about the effects of sildenafil on the breastfed infant and no information on the effects of sildenafil on milk production. Limited clinical data during lactation preclude a clear determination of the risk of sildenafil to an infant during lactation.
8.4Pediatric Use The safety and effectiveness of sildenafil has not been established in pediatric patients younger than 1 year of age. Pediatric use information is approved for Viatris Specialty LLC’s, REVATIO (sildenafil) oral suspension. However, due to Viatris Specialty LLC’s marketing exclusivity rights, this drug product is not labeled with that information.
8.5Geriatric Use Clinical studies of sildenafil did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy [see Clinical Pharmacology (12.3) ] .
8.6Patients with Hepatic Impairment No dose adjustment for mild to moderate impairment is required. Severe impairment has not been studied [see Clinical Pharmacology (12.3) ] .
8.7Patients with Renal Impairment No dose adjustment is required (including severe impairment CLcr < 30 mL/min) [see Clinical Pharmacology (12.3) ] .
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Limited published data from randomized controlled trials, case-controlled trials, and case series do not report a clear association with sildenafil and major birth defects, miscarriage, or adverse maternal or fetal outcomes when sildenafil is used during pregnancy. There are risks to the mother and fetus from untreated pulmonary arterial hypertension (see Clinical Considerations ) . Animal reproduction studies conducted with sildenafil showed no evidence of embryo-fetal toxicity or teratogenicity at doses up to 32- and 65-times the recommended human dose (RHD) of 20 mg three times a day in rats and rabbits, respectively (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Pregnant women with untreated pulmonary arterial hypertension are at risk for heart failure, stroke, preterm delivery, and maternal and fetal death. Data Animal Data No evidence of teratogenicity, embryotoxicity, or fetotoxicity was observed in pregnant rats or rabbits dosed with sildenafil 200 mg/kg/day during organogenesis, a level that is, on a mg/m 2 basis, 32- and 65-times, respectively, the recommended human dose (RHD) of 20 mg three times a day.
In a rat pre- and postnatal development study, the no-observed-adverse-effect dose was 30 mg/kg/day (equivalent to 5-times the RHD on a mg/m 2 basis).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of sildenafil has not been established in pediatric patients younger than 1 year of age. Pediatric use information is approved for Viatris Specialty LLC’s, REVATIO (sildenafil) oral suspension. However, due to Viatris Specialty LLC’s marketing exclusivity rights, this drug product is not labeled with that information.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of sildenafil did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy [see Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE In studies with healthy volunteers of single doses up to 800 mg, adverse events were similar to those seen at lower doses but rates and severities were increased. In cases of overdose, standard supportive measures should be adopted as required. Renal dialysis is not expected to accelerate clearance as sildenafil is highly bound to plasma proteins and it is not eliminated in the urine.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Sildenafil is an inhibitor of cGMP specific PDE-5 in the smooth muscle of the pulmonary vasculature, where PDE-5 is responsible for degradation of cGMP. Sildenafil, therefore, increases cGMP within pulmonary vascular smooth muscle cells resulting in relaxation. In patients with PAH, this can lead to vasodilation of the pulmonary vascular bed and, to a lesser degree, vasodilatation in the systemic circulation.
Studies in vitro have shown that sildenafil is selective for PDE-5. Its effect is more potent on PDE-5 than on other known phosphodiesterases (10-fold for PDE6, greater than 80-fold for PDE1, greater than 700-fold for PDE2, PDE3, PDE4, PDE7, PDE8, PDE9, PDE10, and PDE11). The approximately 4,000-fold selectivity for PDE-5 versus PDE3 is important because PDE3 is involved in control of cardiac contractility.
Sildenafil is only about 10 times as potent for PDE5 compared to PDE6, an enzyme found in the retina and involved in the phototransduction pathway of the retina. This lower selectivity is thought to be the basis for abnormalities related to color vision observed with higher doses or plasma levels [see Clinical Pharmacology (12.2) ] . In addition to pulmonary vascular smooth muscle and the corpus cavernosum, PDE5 is also found in other tissues including vascular and visceral smooth muscle and in platelets.
The inhibition of PDE5 in these tissues by sildenafil may be the basis for the enhanced platelet anti-aggregatory activity of nitric oxide observed in vitro , and the mild peripheral arterial-venous dilatation in vivo .
12.2Pharmacodynamics Effects of Sildenafil on Hemodynamic Measures Adults Patients on all sildenafil doses achieved a statistically significant reduction in mean pulmonary arterial pressure (mPAP) compared to those on placebo in a study with no background vasodilators [see SUPER-1 in Clinical Studies (14) ] . Data on other hemodynamic measures for the sildenafil 20 mg three times a day and placebo dosing regimens is displayed in Table 2. The relationship between these effects and improvements in 6-minute walk distance is unknown.
Table 2: Changes from Baseline in Hemodynamic Parameters at Week 12 [mean (95% CI)] for the Sildenafil 20 mg Three Times a Day and Placebo Group Placebo (n = 65) * Sildenafil 20 mg (n = 65) * mPAP (mmHg) 0.6 (-0.8, 2) -2.1 (-4.3, 0) PVR (dyn•s/cm 5 ) 49 (-54, 153) -122 (-217, -27) SVR (dyn•s/cm 5 ) -78 (-197, 41) -167 (-307, -26) RAP (mmHg) 0.3 (-0.9, 1.5) -0.8 (-1.9, 0.3) CO (L/min) -0.1 (-0.4, 0.2) 0.4 (0.1, 0.7) HR (beats/min) -1.3 (-4.1, 1.4) -3.7 (-5.9, -1.4) mPAP = mean pulmonary arterial pressure; PVR = pulmonary vascular resistance; SVR = systemic vascular resistance; RAP = right atrial pressure; CO = cardiac output; HR = heart rate. * The number of patients per treatment group varied slightly for each parameter due to missing assessments.
Effects of Sildenafil on Blood Pressure Single oral doses of sildenafil 100 mg administered to healthy volunteers produced decreases in supine blood pressure (mean maximum decrease in systolic/diastolic blood pressure of 8/5 mmHg). The decrease in blood pressure was most notable approximately 1 hour to 2 hours after dosing and was not different from placebo at 8 hours. Similar effects on blood pressure were noted with 25 mg, 50 mg, and 100 mg doses of sildenafil, therefore the effects are not related to dose or plasma levels within this dosage range.
Larger effects were recorded among patients receiving concomitant nitrates [see Contraindications (4) ] . Single oral doses of sildenafil up to 100 mg in healthy volunteers produced no clinically relevant effects on electrocardiogram (ECG). After chronic dosing of 80 mg three times a day to patients with PAH, no clinically relevant effects on ECG were reported.
After chronic dosing of 80 mg three times a day sildenafil to healthy volunteers, the largest mean change from baseline in supine systolic and supine diastolic blood pressures was…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Sildenafil is an inhibitor of cGMP specific PDE-5 in the smooth muscle of the pulmonary vasculature, where PDE-5 is responsible for degradation of cGMP. Sildenafil, therefore, increases cGMP within pulmonary vascular smooth muscle cells resulting in relaxation. In patients with PAH, this can lead to vasodilation of the pulmonary vascular bed and, to a lesser degree, vasodilatation in the systemic circulation.
Studies in vitro have shown that sildenafil is selective for PDE-5. Its effect is more potent on PDE-5 than on other known phosphodiesterases (10-fold for PDE6, greater than 80-fold for PDE1, greater than 700-fold for PDE2, PDE3, PDE4, PDE7, PDE8, PDE9, PDE10, and PDE11). The approximately 4,000-fold selectivity for PDE-5 versus PDE3 is important because PDE3 is involved in control of cardiac contractility.
Sildenafil is only about 10 times as potent for PDE5 compared to PDE6, an enzyme found in the retina and involved in the phototransduction pathway of the retina. This lower selectivity is thought to be the basis for abnormalities related to color vision observed with higher doses or plasma levels [see Clinical Pharmacology (12.2) ] . In addition to pulmonary vascular smooth muscle and the corpus cavernosum, PDE5 is also found in other tissues including vascular and visceral smooth muscle and in platelets.
The inhibition of PDE5 in these tissues by sildenafil may be the basis for the enhanced platelet anti-aggregatory activity of nitric oxide observed in vitro , and the mild peripheral arterial-venous dilatation in vivo .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Sildenafil powder for oral suspension, 10 mg/mL is available as a white to off-white powder in amber glass bottles. Each bottle contains 1.57 g of sildenafil citrate, USP (equivalent to 1.12 g sildenafil). Following reconstitution, the volume of the oral suspension is 112 mL (10 mg sildenafil/mL).
A 2 mL oral dosing syringe (with 0.5 mL and 2 mL dose markings) and a press-in bottle adaptor are also provided. It is supplied as follows: 10 mg/mL: NDC 69238-1574-1 (when reconstituted) Recommended storage for sildenafil for oral suspension: Store below 30°C (86°F) in the original package in order to protect from moisture. Reconstituted Oral Suspension Store below 30°C (86°F) or in refrigerator at 2°C to 8°C (36°F to 46°F).
Do not freeze. The shelf-life of the reconstituted oral suspension is 60 days. Any remaining oral suspension should be discarded 60 days after reconstitution.
📋 Description ▾
11 DESCRIPTION Sildenafil citrate, USP phosphodiesterase-5 (PDE-5) inhibitor, is the citrate salt of sildenafil, a selective inhibitor of cyclic guanosine monophosphate (cGMP)-specific phosphodiesterase type-5 (PDE-5). Sildenafil is also marketed as VIAGRA ® for erectile dysfunction. Sildenafil citrate, USP is designated chemically as 1-[[3-(6,7-dihydro-1-methyl-7-oxo-3-propyl-1 H -pyrazolo [4,3- d ] pyrimidin-5-yl)-4-ethoxyphenyl] sulfonyl]-4-methylpiperazine citrate and has the following structural formula: Sildenafil citrate, USP is a white to off-white crystalline powder with a solubility of 3.5 mg/mL in water and a molecular weight of 666.7.
Sildenafil for Oral Suspension: Sildenafil for oral suspension is supplied as white to off-white powder containing 1.57 g of sildenafil citrate, USP (equivalent to 1.12 g sildenafil) in an amber glass bottle intended for reconstitution. Following reconstitution with 90 mL water, the total volume of the oral suspension is 112 mL and the oral suspension contains 10 mg/mL sildenafil. The inactive ingredients include anhydrous citric acid, colloidal silicon dioxide, grape flavor, sodium benzoate, sodium citrate dihydrate, sorbitol, sucralose, titanium dioxide, and xanthan gum.
In addition to the bottle, a press-in bottle adapter and an oral dosing syringe (with 0.5 mL and 2 mL dose markings) are provided. Structural formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information and Instructions for Use ). Inform patients of contraindication of sildenafil with regular and/or intermittent use of organic nitrates. Inform patients that sildenafil is also marketed as VIAGRA for erectile dysfunction.
Advise patients taking sildenafil for oral suspension not to take VIAGRA or other PDE-5 inhibitors. Advise patients to seek immediate medical attention for a sudden loss of vision in one or both eyes while taking sildenafil. Such an event may be a sign of NAION.
Advise patients to seek prompt medical attention in the event of sudden decrease or loss of hearing while taking sildenafil. These events may be accompanied by tinnitus and dizziness. Trademarks are the property of their respective owner.
Distributed by: Amneal Pharmaceuticals LLC Bridgewater, NJ 08807 Rev. 11-2023-04