
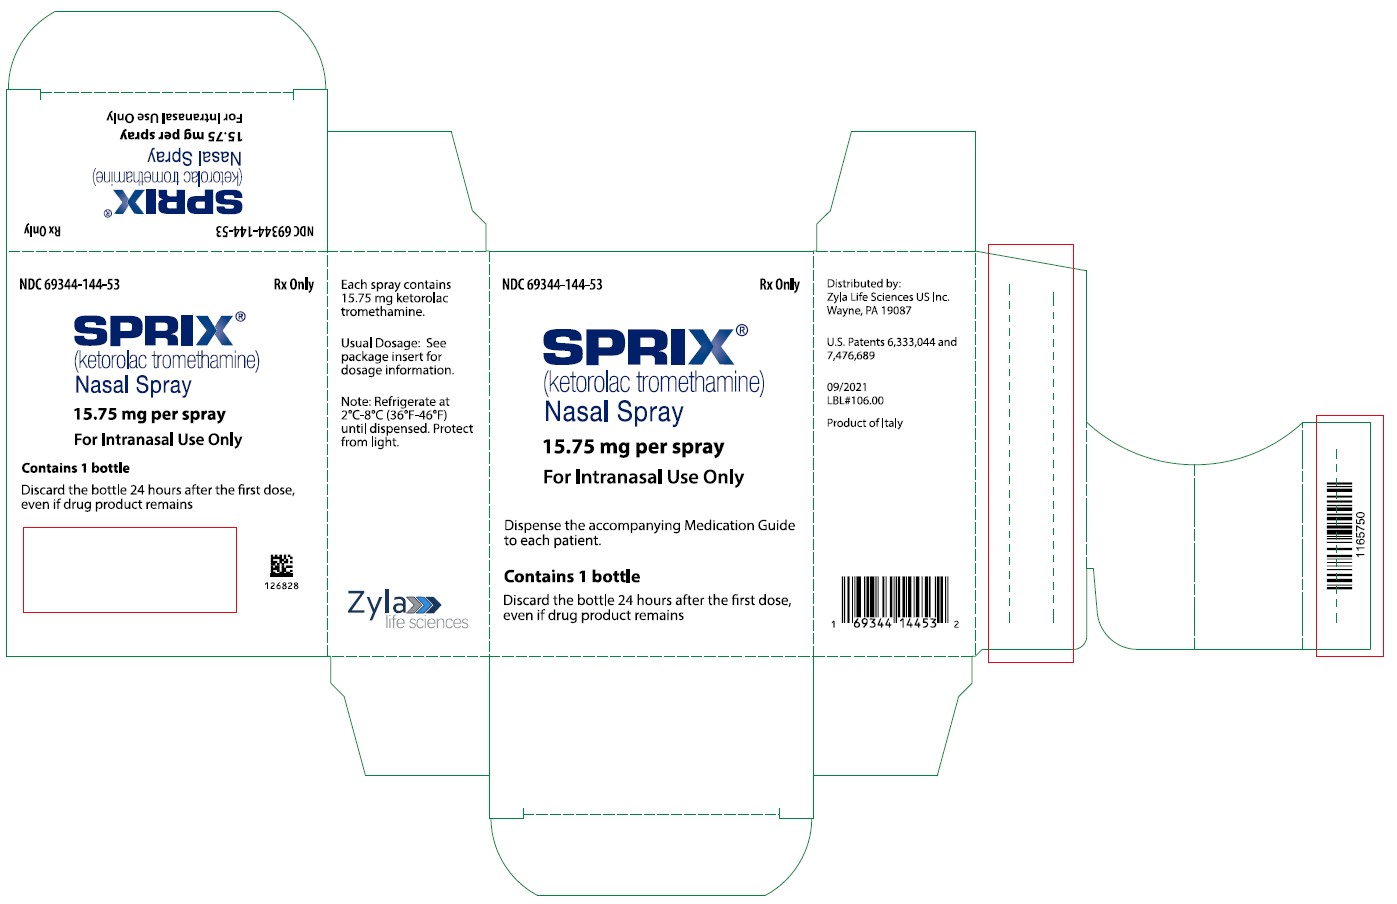
Sprix ketorolac tromethamine 15.75 mg Spray, Metered — NDC 69344-144-53 (Billing 69344-0144-53)
This is a package of Sprix ketorolac tromethamine 15.75 mg Spray, Metered from Zyla Life Sciences US LLC, marketed since Apr 2011 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 69344-144-53 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 69344 labeler · 144 product · 53 package
- Package marketed since
- Mar 2, 2022
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 6934414453 6
- FDA record last changed
- Jul 24, 2026
Other active recalls for Ketorolac Tromethamine (different manufacturers) — 3 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 067386
- GCN: 29928
- GPI-14 (Medi-Span): 66100037102090
- HICL (First Databank): 005175
- AHFS class code: 28:08.04.04
- RxCUI (RxNorm): 1797855
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Nonsteroidal Anti-inflammatory Drug class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Ketorolac nasal spray is used for the short-term relief of moderate to moderately severe pain. Ketorolac is in a class of medications called nonsteroidal anti-inflammatory drugs (NSAIDs). It works by stopping the body's production of a substance that causes pain, fever, and inflammation.
Read the full MedlinePlus article ↗- Sprix is for short-term relief of moderate to moderately severe pain in adults, pain strong enough to need opioid-level relief. You can use it for up to 5 days in total. It is not...
- Prime the new bottle with 5 pumps first. Blow your nose, tilt your head slightly forward, and spray without sniffing in. Breathe through your mouth right after, and pinch your nose...
- Throw the bottle away within 24 hours of your first dose, even if liquid is left. After 24 hours it will not deliver the right amount. Keep it capped, cool, dry and away from child...
- Nose and throat irritation is most common, along with watery eyes, a runny nose and nose pain. These are usually mild. Call your doctor for black stools, chest pain, rash, yellow s...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Ketorolac Tromethamine — tap one for details:
Ketorolac Tromethamine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 5, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 69344-0144-43 69344-144-43 Main listing | 5 CARTON in 1 CARTON / 1 BOTTLE, SPRAY in 1 CARTON / 8 SPRAY, METERED in 1 BOTTLE, SPRAY | 2011-04-26 | — | Active |
| 69344-0144-53 You're viewing this | 1 BOTTLE, SPRAY in 1 CARTON / 8 SPRAY, METERED in 1 BOTTLE, SPRAY | 2022-03-02 | — | Active |
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Sprix ketorolac tromethamine 15.75 mg Spray, Metered?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Sprix 15.75 mgthis 69344-0144-53 | Zyla | 1 bottle | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Ketorolac Nasal Spray inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII 4J9FJ0HL51
Potassium phosphate, monobasic is a salt compound used in medicines as a pH buffer and electrolyte source. It helps stabilize the acidity level of liquid and powdered formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Zyla Life Sciences US LLC labeler code 69344
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RISK OF SERIOUS CARDIOVASCULAR AND GASTROINTESTINAL EVENTS Cardiovascular Thrombotic Events Nonsteroidal anti-inflammatory drugs (NSAIDs) cause an increased risk of serious cardiovascular thrombotic events, including myocardial infarction and stroke, which can be fatal. This risk may occur early in treatment and may increase with duration of use [ see Warnings and Precautions ( 5.1 ) ]. SPRIX ® is contraindicated in the setting of coronary artery bypass graft (CABG) surgery [ see Contraindications ( 4 ) and Warnings and Precautions ( 5.1 ) ].
Gastrointestinal Bleeding, Ulceration, and Perforation NSAIDs cause an increased risk of serious gastrointestinal (GI) adverse events including bleeding, ulceration, and perforation of the stomach or intestines, which can be fatal. These events can occur at any time during use and without warning symptoms. Elderly patients and patients with a prior history of peptic ulcer disease and/or GI bleeding are at greater risk for serious GI events [ see Warnings and Precautions ( 5.2 ) ].
WARNING: RISK OF SERIOUS CARDIOVASCULAR AND GASTROINTESTINAL EVENTS See full prescribing information for complete boxed warning. Nonsteroidal anti-inflammatory drugs (NSAIDS) cause an increased risk of serious cardiovascular thrombotic events, including myocardial infarction and stroke, which can be fatal. This risk may occur early in treatment and may increase with duration of use ( 5.1 ) SPRIX ® is contraindicated in the setting of coronary artery bypass graft (CABG) surgery ( 4 , 5.1 ) NSAIDS cause an increased risk of serious gastrointestinal (GI) adverse events including bleeding, ulceration, and perforation of the stomach or intestines, which can be fatal.
These events can occur at any time during use and without warning symptoms. Elderly patients and patients with a prior history of peptic ulcer disease and/or GI bleeding are at greater risk for serious GI events ( 5.2 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE SPRIX is indicated in adult patients for the short term (up to 5 days) management of moderate to moderately severe pain that requires analgesia at the opioid level. Limitations of Use Sprix is not for use in pediatric patients less than 2 years of age. SPRIX is a nonsteroidal anti-inflammatory drug indicated in adult patients for the short term (up to 5 days) management of moderate to moderately severe pain that requires analgesia at the opioid level.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Use the lowest effective dosage for shortest duration consistent with individual patient treatment goals. ( 2.1 ) SPRIX is not an inhaled product. For adult patients < 65 years of age: 31.5 mg (one 15.75 mg spray in each nostril) every 6 to 8 hours.
The maximum daily dose is 126 mg. ( 2.2 , 2.3 ) For patients ≥ 65 years of age, renally impaired patients, and patients less than 50 kg (110 lbs): 15.75 mg (one 15.75 mg spray in only one nostril) every 6 to 8 hours. The maximum daily dose is 63 mg.
( 2.4 ) SPRIX nasal spray should be discarded within 24 hours of taking the first dose, even if the bottle still contains some medication. ( 2.5 )
2.1General Dosing Instructions Use the lowest effective dosage for the shortest duration consistent with individual patient treatment goals [ see Warnings and Precautions ( 5 ) ]. The total duration of use of SPRIX alone or sequentially with other formulations of ketorolac (IM/IV or oral) must not exceed 5 days because of the potential for increasing the frequency and severity of adverse reactions associated with the recommended doses [ see Warnings and Precautions ( 5.15 ) ]. Do not use SPRIX concomitantly with other formulations of ketorolac or other NSAIDs [ see Warnings and Precautions ( 5.15 ) ].
2.2Administration SPRIX is not an inhaled product. Do not inhale when administering this product. Instruct patients to administer as follows: 1.
First hold the finger flange with fingers, and remove the clear plastic cover with opposite hand; then remove the blue plastic safety clip. Keep the clear plastic cover; and throw away the blue plastic safety clip. 2.
Before using the bottle for the FIRST time, activate the pump. To activate the pump, hold the bottle at arm’s length away from the body with index finger and middle finger resting on the top of the finger flange and thumb supporting the base. Press down evenly and release the pump 5 times.
Patient may not see a spray the first few times he/she presses down. The bottle is now ready to use. There is no need to activate the pump again if more doses are used from the bottle.
3. It’s important to get the medication to the correct place in the nose so it will be most effective. - Blow nose gently to clear nostrils. - Sit up straight or stand. Tilt head slightly forward. - Insert the tip of the container into your right nostril. - Point the container away from the center of your nose. - Hold your breath and spray once into your right nostril, pressing down evenly on both sides. - Immediately after administration, resume breathing through mouth to reduce expelling the product.
Also pinch the nose to help retain the spray if it starts to drip. If only one spray per dose is prescribed, administration is complete; skip to Step 5 below. 4.
If a dose of 2 sprays is prescribed, repeat the process in Step 3 for the left nostril. Again, be sure to point the spray away from the center of nose. Spray once into the left nostril.
5. Replace the clear plastic cover and place the bottle in a cool, dry location out of direct sunlight, such as inside a medication cabinet. Keep out of reach of children.
2.3Adult Patients < 65 Years of Age The recommended dose is 31.5 mg SPRIX (one 15.75 mg spray in each nostril) every 6 to 8 hours. The maximum daily dose is 126 mg (four doses).
2.4Reduced Doses for Special Populations For patients ≥ 65 years of age, renally impaired patients, and adult patients less than 50 kg (110 lbs), the recommended dose is 15.75 mg SPRIX ( one 15.75 mg spray in only one nostril) every 6 to 8 hours. The maximum daily dose is 63 mg (four doses) [ see Warnings and Precautions ( 5.2 , 5.6 ) ].
2.5Discard Used SPRIX Bottle after 24 Hours Do not use any single SPRIX bottle for more than one day as it will not deliver the intended dose after 24 hours. Therefore, the bottle must be discarded no more than 24 hours after taking the first dose, even if the bottle still contains some liquid.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS SPRIX (ketorolac tromethamine) Nasal spray: 15.75 mg of ketorolac tromethamine in each 100 μL spray. Each 1.7 g bottle contains 8 sprays. SPRIX (ketorolac tromethamine) Nasal Spray: 15.75 mg of ketorolac tromethamine in each 100 μL spray. Each 1.7 g bottle contains 8 sprays. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS SPRIX is contraindicated in the following patients: Known hypersensitivity (e.g., anaphylactic reactions and serious skin reactions) to ketorolac or any components of the drug product [ see Warnings and Precautions ( 5.7 , 5.9 ) ] History of asthma, urticaria, or other allergic-type reactions after taking aspirin or other NSAIDs. Severe, sometimes fatal, anaphylactic reactions to NSAIDs have been reported in such patients [ see Warnings and Precautions ( 5.7 , 5.8 ) ] In the setting of coronary artery bypass graft (CABG) surgery [ see Warnings and Precautions ( 5.1 ) ] Use in patients with active peptic ulcer disease and in patients with recent gastrointestinal bleeding or perforation [ see Warnings and Precautions ( 5.2 ) ] Use as a prophylactic analgesic before any major surgery [ see Warnings and Precautions ( 5.11 ) ] Use in patients with advanced renal disease or patients at risk for renal failure due to volume depletion [ see Warnings and Precautions ( 5.6 ) ] Use in labor and delivery.
Through its prostaglandin synthesis inhibitory effect, ketorolac may adversely affect fetal circulation and inhibit uterine contractions, thus increasing the risk of uterine hemorrhage [ see Use in Specific Populations ( 8.1 ) ] Use in patients with suspected or confirmed cerebrovascular bleeding, hemorrhagic diathesis, incomplete hemostasis, or those for whom hemostasis is critical [ see Warnings and Precautions ( 5.11 ), Drug Interactions ( 7 ) ] Concomitant use with probenecid [ see Drug Interactions ( 7 ) ] Concomitant use with pentoxifylline [ see Drug Interactions ( 7 ) ] Known hypersensitivity to ketorolac or any components of the drug product ( 4 ) History of asthma, urticaria, or other allergic-type reactions after taking aspirin or other NSAIDs ( 4 ) In the setting of CABG surgery ( 4 ) Use in patients with active peptic ulcer disease or with recent GI bleeding or perforation ( 4 ) Use as a prophylactic analgesic before any major surgery ( 4 ) Use in patients with advanced renal disease or patients at risk for renal failure due to volume depletion ( 4 ) Use in patients with suspected or confirmed cerebrovascular bleeding, patients with hemorrhagic diathesis, incomplete hemostasis, and those at high risk of bleeding ( 4 ) Use in labor and delivery ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hepatotoxicity : Inform patients of warning signs and symptoms of hepatotoxicity. Discontinue if abnormal liver tests persist or worsen or if clinical signs and symptoms of liver disease develop. ( 5.3 ) Hypertension : Patients taking some antihypertensive medications may have impaired response to these therapies when taking NSAIDs.
Monitor blood pressure. ( 5.4 , 7 ) Heart Failure and Edema : Avoid use of SPRIX in patients with severe heart failure unless benefits are expected to outweigh risk of worsening heart failure. ( 5.5 ) Renal Toxicity : Monitor renal function in patients with renal or hepatic impairment, heart failure, dehydration, or hypovolemia.
Avoid use of SPRIX in patients with advanced renal disease unless benefits are expected to outweigh risk of worsening renal function. ( 5.6 ) Anaphylactic Reactions : Seek emergency help if an anaphylactic reaction occurs. ( 5.7 ) Exacerbation of Asthma Related to Aspirin Sensitivity : SPRIX is contraindicated in patients with aspirin-sensitive asthma.
Monitor patients with preexisting asthma (without aspirin sensitivity). ( 5.8 ) Serious Skin Reactions : Discontinue SPRIX at first appearance of skin rash or other signs of hypersensitivity. ( 5.9 ) Fetal Toxicity : Limit use of NSAIDs, including SPRIX, between about 20 to 30 weeks in pregnancy due to the risk of oligohydramnios/fetal renal dysfunction.
Avoid use of NSAIDs in women at about 30 weeks gestation and later in pregnancy due to the risks of oligohydramnios/fetal dysfunction and premature closure of the fetal ductus arteriosus ( 5.10 , 8.1 ) Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS) : Discontinue and evaluate clinically ( 5.11 ) Hematologic Toxicity : Monitor hemoglobin or hematocrit in patients with any signs or symptoms of anemia. Do not use SPRIX in patients for whom hemostasis is critical. ( 5.12 , 7 ) Limitations of Use : SPRIX should not be used concomitantly with IM/IV or oral ketorolac, aspirin, or other NSAIDs.
( 5.16 )
5.1Cardiovascular Thrombotic Events Clinical trials of several COX-2 selective and nonselective NSAIDs of up to three years duration have shown an increased risk of serious cardiovascular (CV) thrombotic events, including myocardial infarction (MI) and stroke, which can be fatal. Based on available data, it is unclear that the risk for CV thrombotic events is similar for all NSAIDs. The relative increase in serious CV thrombotic events over baseline conferred by NSAID use appears to be similar in those with and without known CV disease or risk factors for CV disease.
However, patients with known CV disease or risk factors had a higher absolute incidence of excess serious CV thrombotic events, due to their increased baseline rate. Some observational studies found that this increased risk of serious CV thrombotic events began as early as the first weeks of treatment. The increase in CV thrombotic risk has been observed most consistently at higher doses.
To minimize the potential risk for an adverse CV event in NSAID-treated patients, use the lowest effective dose for the shortest duration possible. Physicians and patients should remain alert for the development of such events, throughout the entire treatment course, even in the absence of previous CV symptoms. Patients should be informed about the symptoms of serious CV events and the steps to take if they occur.
There is no consistent evidence that concurrent use of aspirin mitigates the increased risk of serious CV thrombotic events associated with NSAID use. The concurrent use of aspirin and an NSAID, such as ketorolac, increases the risk of serious gastrointestinal (GI) events [ see Warnings and Precautions ( 5.2 ) ]. Status Post Coronary Artery Bypass Graft (CABG) Surgery Two large, controlled clinical trials of a COX-2 selective NSAID for the treatment of pain in the first 10–14 days following CABG surgery found an increased incidence of myocardial infarction and stroke.
NSAIDs are contrai… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: Cardiovascular Thrombotic Events [ see Warnings and Precautions ( 5.1 ) ] GI Bleeding, Ulceration and Perforation [ see Warnings and Precautions ( 5.2 ) ] Hepatotoxicity [ see Warnings and Precautions ( 5.3 ) ] Hypertension [ see Warnings and Precautions ( 5.4 ) ] Heart Failure and Edema [ see Warnings and Precautions ( 5.5 ) ] Renal Toxicity and Hyperkalemia [ see Warnings and Precautions ( 5.6 ) ] Anaphylactic Reactions [ see Warnings and Precautions ( 5.7 ) ] Serious Skin Reactions [ see Warnings and Precautions ( 5.9 ) ] Hematologic Toxicity [ see Warnings and Precautions ( 5.12 ) ] Most common adverse reactions (incidence ≥2%) in patients treated with SPRIX and occurring at a rate at least twice that of placebo are nasal discomfort, rhinalgia, increased lacrimation, throat irritation, oliguria, rash, bradycardia, decreased urine output, increased ALT and/or AST, hypertension, and rhinitis.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Zyla Life Sciences US Inc. at 1-800-518-1084 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data described below reflect exposure to SPRIX in patients enrolled in placebo-controlled efficacy studies of acute pain following major surgery. The studies enrolled 828 patients (183 men, 645 women) ranging from 18 years to over 75 years of age.
The patients in the postoperative pain studies had undergone major abdominal, orthopedic, gynecologic, or other surgery; 455 patients received SPRIX (31.5 mg) three or four times a day for up to 5 days, and 245 patients received placebo. Most patients were receiving concomitant opioids, primarily PCA morphine. The most frequently reported adverse reactions were related to local symptoms, i.e., nasal discomfort or irritation.
These reactions were generally mild and transient in nature. The most common drug-related adverse events leading to premature discontinuation were nasal discomfort or nasal pain (rhinalgia). Table 1: Post-Operative Patients with Adverse Reactions Observed at a Rate of 2% or More and at Least Twice the Incidence of the Placebo Group.
SPRIX (N = 455) Placebo (N = 245) Nasal discomfort 15% 2% Rhinalgia 13% <1% Lacrimation increased 5% 0% Throat irritation 4% <1% Oliguria 3% 1% Rash 3% <1% Bradycardia 2% <1% Urine output decreased 2% <1% ALT and/or AST increased 2% 1% Hypertension 2% 1% Rhinitis 2% <1% In controlled clinical trials in major surgery, primarily knee and hip replacements and abdominal hysterectomies, seven patients (N=455, 1.5%) treated with SPRIX experienced serious adverse events of bleeding (4 patients) or hematoma (3 patients) at the operative site versus one patient (N=245, 0.4%) treated with placebo (hematoma).
Six of the seven patients treated with SPRIX underwent a surgical procedure and/or blood transfusion and the placebo patient subsequently required a blood transfusion. Adverse Reactions Reported in Clinical Trials with Other Dosage Forms of Ketorolac or Other NSAIDs Adverse reaction rates increase with higher doses of ketorolac. It is necessary to remain alert for the severe complications of treatment with ketorolac, such as GI ulceration, bleeding, and perforation, postoperative bleeding, acute renal failure, anaphylactic and anaphylactoid reactions, and liver failure.
These complications can be serious in certain patients for whom ketorolac is indicated, especially when the drug is used inappropriately. In patients taking ketorolac or other NSAIDs in clinical trials, the most frequently reported adverse experiences in approximately 1% to 10% of patients are: * Incidence greater than 10% Gas… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS See Table 2 for clinically significant drug interactions with ketorolac. Table 2: Clinically Significant Drug Interactions with Ketorolac Drugs that Interfere with Hemostasis Clinical Impact: Ketorolac and anticoagulants such as warfarin have a synergistic effect on bleeding. The concomitant use of ketorolac and anticoagulants have an increased risk of serious bleeding compared to the use of either drug alone [ see Clinical Pharmacology ( 12.3 ) ].
Serotonin release by platelets plays an important role in hemostasis. Case-control and cohort epidemiological studies showed that concomitant use of drugs that interfere with serotonin reuptake and an NSAID may potentiate the risk of bleeding more than an NSAID alone. When ketorolac is administered concurrently with pentoxifylline, there is an increased risk of bleeding.
Intervention: Monitor patients with concomitant use of SPRIX with anticoagulants (e.g., warfarin), antiplatelet agents (e.g., aspirin), selective serotonin reuptake inhibitors (SSRIs), and serotonin norepinephrine reuptake inhibitors (SNRIs) for signs of bleeding [ see Warnings and Precautions ( 5.12 ) ]. Concomitant use of SPRIX and pentoxifylline is contraindicated [ see Contraindications ( 4 ) and Warnings and Precautions ( 5.12 ) ]. Aspirin Clinical Impact: Controlled clinical studies showed that the concomitant use of NSAIDs and analgesic doses of aspirin does not produce any greater therapeutic effect than the use of NSAIDs alone.
In a clinical study, the concomitant use of an NSAID and aspirin was associated with a significantly increased incidence of GI adverse reactions as compared to use of the NSAID alone [ see Warnings and Precautions ( 5.2 ) ]. Intervention: Concomitant use of SPRIX and analgesic doses of aspirin is not generally recommended because of the increased risk of bleeding [ see Warnings and Precautions ( 5.12 ) ]. SPRIX is not a substitute for low dose aspirin for cardiovascular protection.
ACE Inhibitors, Angiotensin Receptor Blockers, and Beta-blockers Clinical Impact: NSAIDs may diminish the antihypertensive effect of angiotensin converting enzyme (ACE) inhibitors, angiotensin receptor blockers (ARBs), or beta-blockers (including propranolol). In patients who are elderly, volume-depleted (including those on diuretic therapy), or have renal impairment, co-administration of an NSAID with ACE inhibitors or ARBs may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible.
Intervention: During concomitant use of SPRIX and ACE-inhibitors, ARBs, or beta-blockers, monitor blood pressure to ensure that the desired blood pressure is obtained. During concomitant use of SPRIX and ACE-inhibitors or ARBs in patients who are elderly, volume-depleted, or have impaired renal function, monitor for signs of worsening renal function [ see Warnings and Precautions ( 5.6 ) ]. When these drugs are administered concomitantly, patients should be adequately hydrated.
Assess renal function at the beginning of the concomitant treatment and periodically thereafter. Diuretics Clinical Impact: Clinical studies, as well as post-marketing observations, showed that NSAIDs reduced the natriuretic effect of loop diuretics (e.g., furosemide) and thiazide diuretics in some patients. This effect has been attributed to the NSAID inhibition of renal prostaglandin synthesis Intervention: During concomitant use of SPRIX with diuretics, observe patients for signs of worsening renal function, in addition to assuring diuretic efficacy including antihypertensive effects [ see Warnings and Precautions ( 5.6 ) ].
Digoxin Clinical Impact: The concomitant use of ketorolac with digoxin has been reported to increase the serum concentration and prolong the half-life of digoxin. Intervention: During concomitant use of SPRIX and digoxin, monitor serum digoxin levels. Lithium Clinical Impact: NSAIDs have produced elevations in plasma lithium levels and reductions… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Infertility : NSAIDs are associated with reversible infertility. Consider withdrawal of SPRIX in women who have difficulties conceiving. ( 8.3 )
8.1Pregnancy Risk Summary Use of NSAIDs, including SPRIX, can cause premature closure of the fetal ductus arteriosus and fetal renal dysfunction leading to oligohydramnios and, in some cases, neonatal renal impairment. Because of these risks, limit dose and duration of SPRIX use between about 20 and 30 weeks of gestation, and avoid SPRIX use at about 30 weeks of gestation and later in pregnancy ( see Clinical Considerations, Data ). Premature Closure of Fetal Ductus Arteriosus Use of NSAIDs, including SPRIX, at about 30 weeks gestation or later in pregnancy increases the risk of premature closure of the fetal ductus arteriosus.
Oligohydramnios/Neonatal Renal Impairment Use of NSAIDs at about 20 weeks gestation or later in pregnancy has been associated with cases of fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment. Data from observational studies regarding other potential embryofetal risks of NSAID use in women in the first or second trimesters of pregnancy are inconclusive. In animal reproduction studies in rabbits and rats tested at 0.6 and 1.5 times the human systemic exposure, respectively, at the recommended maximum IN dose of 31.5 mg four times a day, there was no evidence of teratogenicity or other adverse developmental outcomes ( see Data ).
Based on animal data, prostaglandins have been shown to have an important role in endometrial vascular permeability, blastocyst implantation, and decidualization. In animal studies, administration of prostaglandin synthesis inhibitors such as ketorolac, resulted in increased pre- and post-implantation loss. Prostaglandins also have been shown to have an important role in fetal kidney development.
In published animal studies, prostaglandin synthesis inhibitors have been reported to impair kidney development when administered at clinically relevant doses. The estimated background risk of major birth defects and miscarriage for the indicated population(s) is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Premature Closure of Fetal Ductus Arteriosus: Avoid use of NSAIDs in women at about 30 weeks gestation and later in pregnancy, because NSAIDs, including SPRIX, can cause premature closure of the fetal ductus arteriosus ( see Data ). Oligohydramnios/Neonatal Renal Impairment: If an NSAID is necessary at about 20 weeks gestation or later in pregnancy, limit the use to the lowest effective dose and shortest duration possible.
If SPRIX treatment extends beyond 48 hours, consider monitoring with ultrasound for oligohydramnios. If oligohydramnios occurs, discontinue SPRIX and follow up according to clinical practice ( see Data ). Data Human Data Premature Closure of Fetal Ductus Arteriosus: Published literature reports that the use of NSAIDs at about 30 weeks of gestation and later in pregnancy may cause premature closure of the fetal ductus arteriosus.
Oligohydramnios/Neonatal Renal Impairment: Published studies and postmarketing reports describe maternal NSAID use at about 20 weeks gestation or later in pregnancy associated with fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment. These adverse outcomes are seen, on average, after days to weeks of treatment, although oligohydramnios has been infrequently reported as soon as 48 hours after NSAID initiation. In many cases, but not all, the decrease in amniotic fluid was transient and reversible with cessation of the drug.
There have been a limited number of case reports of maternal NSAID use and… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Use of NSAIDs, including SPRIX, can cause premature closure of the fetal ductus arteriosus and fetal renal dysfunction leading to oligohydramnios and, in some cases, neonatal renal impairment. Because of these risks, limit dose and duration of SPRIX use between about 20 and 30 weeks of gestation, and avoid SPRIX use at about 30 weeks of gestation and later in pregnancy ( see Clinical Considerations, Data ). Premature Closure of Fetal Ductus Arteriosus Use of NSAIDs, including SPRIX, at about 30 weeks gestation or later in pregnancy increases the risk of premature closure of the fetal ductus arteriosus.
Oligohydramnios/Neonatal Renal Impairment Use of NSAIDs at about 20 weeks gestation or later in pregnancy has been associated with cases of fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment. Data from observational studies regarding other potential embryofetal risks of NSAID use in women in the first or second trimesters of pregnancy are inconclusive. In animal reproduction studies in rabbits and rats tested at 0.6 and 1.5 times the human systemic exposure, respectively, at the recommended maximum IN dose of 31.5 mg four times a day, there was no evidence of teratogenicity or other adverse developmental outcomes ( see Data ).
Based on animal data, prostaglandins have been shown to have an important role in endometrial vascular permeability, blastocyst implantation, and decidualization. In animal studies, administration of prostaglandin synthesis inhibitors such as ketorolac, resulted in increased pre- and post-implantation loss. Prostaglandins also have been shown to have an important role in fetal kidney development.
In published animal studies, prostaglandin synthesis inhibitors have been reported to impair kidney development when administered at clinically relevant doses. The estimated background risk of major birth defects and miscarriage for the indicated population(s) is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Premature Closure of Fetal Ductus Arteriosus: Avoid use of NSAIDs in women at about 30 weeks gestation and later in pregnancy, because NSAIDs, including SPRIX, can cause premature closure of the fetal ductus arteriosus ( see Data ). Oligohydramnios/Neonatal Renal Impairment: If an NSAID is necessary at about 20 weeks gestation or later in pregnancy, limit the use to the lowest effective dose and shortest duration possible.
If SPRIX treatment extends beyond 48 hours, consider monitoring with ultrasound for oligohydramnios. If oligohydramnios occurs, discontinue SPRIX and follow up according to clinical practice ( see Data ). Data Human Data Premature Closure of Fetal Ductus Arteriosus: Published literature reports that the use of NSAIDs at about 30 weeks of gestation and later in pregnancy may cause premature closure of the fetal ductus arteriosus.
Oligohydramnios/Neonatal Renal Impairment: Published studies and postmarketing reports describe maternal NSAID use at about 20 weeks gestation or later in pregnancy associated with fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment. These adverse outcomes are seen, on average, after days to weeks of treatment, although oligohydramnios has been infrequently reported as soon as 48 hours after NSAID initiation. In many cases, but not all, the decrease in amniotic fluid was transient and reversible with cessation of the drug.
There have been a limited number of case reports of maternal NSAID use and neonatal renal dysfunction without oligohydramnios, some of which were irreversible. Some cases of neonatal renal dysfunction required treatment with invasive procedures, suc… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use Sprix is not for use in pediatric patients less than 2 years of age. The safety and effectiveness of ketorolac in pediatric patients 17 years of age and younger have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Exercise caution when treating the elderly (65 years and older) with SPRIX. Elderly patients, compared to younger patients, are at greater risk for NSAID-associated serious cardiovascular, gastrointestinal, and/or renal adverse reactions. If the anticipated benefit for the elderly patient outweighs these potential risks, start dosing at the low end of the dosing range, and monitor patients for adverse effects [ see Dosage and Administration ( 2.4 ), Warnings and Precautions ( 5.1 , 5.2 , 5.3 , 5.6, 5.14 ), Clinical Pharmacology ( 12.3 ) ].
After observing the response to initial therapy with SPRIX, adjust the dose and frequency to suit an individual patient’s needs. Ketorolac and its metabolites are known to be substantially excreted by the kidneys, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, use caution in this patient population, and it may be useful to monitor renal function [ see Clinical Pharmacology ( 12.3 ) ].
🆘 Overdosage ▾
10 OVERDOSAGE Symptoms following acute NSAID overdosages have been typically limited to lethargy, drowsiness, nausea, vomiting, and epigastric pain, which have been generally reversible with supportive care. Gastrointestinal bleeding has occurred. Hypertension, acute renal failure, respiratory depression, and coma have occurred, but were rare [ see Warnings and Precautions ( 5.1 , 5.2 , 5.4 , 5.6 ) ].
There has been no experience with overdosage of SPRIX. In controlled overdosage studies with IM ketorolac injection, daily doses of 360 mg given for five days (approximately 3 times the maximum daily dose of SPRIX) caused abdominal pain and peptic ulcers, which healed after discontinuation of dosing. Single overdoses of ketorolac tromethamine have been variously associated with abdominal pain, nausea, vomiting, hyperventilation, peptic ulcers and/or erosive gastritis, and renal dysfunction.
Manage patients with symptomatic and supportive care following an NSAID overdosage. There are no specific antidotes. Consider emesis and/or activated charcoal (60 to 100 grams in adults, 1 to 2 grams per kg of body weight in pediatric patients) and/or osmotic cathartic in symptomatic patients seen within four hours of ingestion or in patients with a large overdosage (5 to 10 times the recommended dosage).
Forced diuresis, alkalinization of urine, hemodialysis, or hemoperfusion may not be useful due to high protein binding. For additional information about overdosage treatment contact a poison control center (1-800-222-1222).
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ketorolac has analgesic, anti-inflammatory, and antipyretic properties. The mechanism of action of SPRIX, like that of other NSAIDs, is not completely understood but involves inhibition of cyclooxygenase (COX-1 and COX-2), an early component of the arachidonic acid cascade, resulting in the reduced synthesis of prostaglandins, thromboxanes, and prostacyclin. Ketorolac is a potent inhibitor of prostaglandin synthesis in vitro .
Ketorolac concentrations reached during therapy have produced in vivo effects. Prostaglandins sensitize afferent nerves and potentiate the action of bradykinin in inducing pain in animal models. Prostaglandins are mediators of inflammation.
Because ketorolac is an inhibitor of prostaglandin synthesis, its mode of action may be due to a decrease of prostaglandins in peripheral tissues.
12.3Pharmacokinetics The half-lives of ketorolac by the IN and IM routes were similar. The bioavailability of ketorolac by the IN route of administration of a 31.5 mg dose was approximately 60% compared to IM administration. (See Table 3 ).
Table 3: Pharmacokinetic Parameters of Ketorolac Tromethamine after Intramuscular (IM) and Intranasal (IN) Administration C max = maximum plasma concentration; t max = time of C max ; AUC 0-∞ = complete area under the concentration-time curve; T ½ = half-life; SD = standard deviation. All values are means, except t max , for which medians are reported. Ketorolac Tromethamine C max (SD) ng/mL t max (range) hours AUC 0-∞ (SD) ng•h/mL T ½ (SD) hours 30 mg IM (1.0 mL of a 30 mg/mL solution) 2382.2 (432.7) 0.75 (0.25-1.03) 11152.8 (4260.1) 4.80 (1.18) 31.5 mg IN (SPRIX) (2 x 100 μL of a 15% w/w solution) 1805.8 (882.8) 0.75 (0.50-2.00) 7477.3 (3654.4) 5.24 (1.33) 15 mg IM (0.5 mL of a 30 mg/mL solution) 1163.4 (279.9) 0.75 (0.25-1.50) 5196.3 (2076.7) 5.00 (1.72) Absorption In a study in which SPRIX (31.5 mg) was administered to healthy volunteers four times daily for 5 days, the C max , t max , and AUC values following the final dose were comparable to those obtained in the single-dose study.
Accumulation of ketorolac has not been studied in special populations, geriatric, pediatric, renal failure or hepatic disease patients. Distribution Scintigraphic assessment of drug disposition of ketorolac following SPRIX intranasal dosing demonstrated that most of the ketorolac was deposited in the nasal cavity and pharynx, with less than 20% deposited in the esophagus and stomach, and zero or negligible deposition in the lungs (<0.5%). The mean apparent volume (Vβ) of ketorolac tromethamine following complete distribution was approximately 13 liters.
This parameter was determined from single-dose data. The ketorolac tromethamine racemate has been shown to be highly protein bound (99.2%). Nevertheless, plasma concentrations as high as 10 mcg/mL will only occupy approximately 5% of the albumin binding sites.
Thus, the unbound fraction for each enantiomer will be constant over the therapeutic range. A decrease in serum albumin, however, will result in increased free drug concentrations. Therapeutic concentrations of digoxin, warfarin, ibuprofen, naproxen, piroxicam, acetaminophen, phenytoin, and tolbutamide did not alter ketorolac protein binding.
In vitro studies indicate that, at therapeutic concentrations of salicylate (300 mcg/mL), the binding of ketorolac was reduced from approximately 99.2% to 97.5%, representing a potential twofold increase in unbound ketorolac plasma levels. The in vitro binding of warfarin to plasma proteins is only slightly reduced by ketorolac (99.5% control vs. 99.3%) when ketorolac plasma concentrations reach 5 to 10 mcg/mL.
Ketorolac tromethamine is excreted in human milk. Elimination Metabolism Ketorolac tromethamine is largely metabolized in the liver. The metabolic products are hydroxylated and conjugated forms of the parent drug.
The products of metabolism, and some unchanged drug, are excreted in the urine. There is no… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ketorolac has analgesic, anti-inflammatory, and antipyretic properties. The mechanism of action of SPRIX, like that of other NSAIDs, is not completely understood but involves inhibition of cyclooxygenase (COX-1 and COX-2), an early component of the arachidonic acid cascade, resulting in the reduced synthesis of prostaglandins, thromboxanes, and prostacyclin. Ketorolac is a potent inhibitor of prostaglandin synthesis in vitro .
Ketorolac concentrations reached during therapy have produced in vivo effects. Prostaglandins sensitize afferent nerves and potentiate the action of bradykinin in inducing pain in animal models. Prostaglandins are mediators of inflammation.
Because ketorolac is an inhibitor of prostaglandin synthesis, its mode of action may be due to a decrease of prostaglandins in peripheral tissues.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING SPRIX (ketorolac tromethamine) Nasal Spray, 15.75 mg/spray, are single-day preservative-free spray bottles, supplied as: NDC 69344-144-43 Carton containing 5 single-day nasal spray bottles NDC 69344-144-53 Carton containing 1 single-day nasal spray bottle Each single-day nasal spray bottle contains a sufficient quantity of solution to deliver 8 sprays for a total of 126 mg of ketorolac tromethamine. Each spray delivers 15.75 mg of ketorolac tromethamine. The delivery system is designed to administer precisely metered doses of 100 µL per spray.
Storage Protect from light and freezing. Store unopened SPRIX between 2°C to 8°C (36°F to 46°F). During use, keep containers of SPRIX Nasal Spray at controlled room temperature, between 15°C to 30°C (59°F to 86°F), out of direct sunlight.
Bottles of SPRIX should be discarded within 24 hours of priming.
📋 Description ▾
11 DESCRIPTION SPRIX (ketorolac tromethamine) Nasal Spray is a member of the pyrrolo-pyrrole group of nonsteroidal anti-inflammatory drugs, available as a clear, colorless to yellow solution packaged in a glass vial with a snap on spray pump that delivers 15.75 mg ketorolac tromethamine per spray and is intended for intranasal administration. The chemical name is (±)-5-benzoyl-2,3-dihydro-1H-pyrrolizine-1-carboxylic acid, compound with 2-amino-2-(hydroxymethyl)-1,3-propanediol (1:1). The molecular weight is 376.41.
Its molecular formula is C 19 H 24 N 2 O 6 (C 15 H 13 NO 3 •C 4 H 11 NO 3 ), and it has the following chemical structure. Ketorolac tromethamine is highly water-soluble, allowing its formulation in an aqueous nasal spray product at pH 7.2. The inactive ingredients in SPRIX include: edetate disodium (EDTA), monobasic potassium phosphate, sodium hydroxide, and water for injection.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide and Instructions for Use ) that accompanies each prescription dispensed. Instruct all patients to read and closely follow the FDA-approved SPRIX Patient Instructions to ensure proper administration of SPRIX. When prescribing SPRIX, inform patients or their caregivers of the potential risks of ketorolac treatment, instruct patients to seek medical advice if they develop treatment-related adverse events, advise patients not to give SPRIX to other family members, and advise patients to discard any unused drug.
Inform patients, families, or their caregivers of the following information before initiating therapy with SPRIX and periodically during the course of ongoing therapy. Cardiovascular Thrombotic Events Advise patients to be alert for the symptoms of cardiovascular thrombotic events, including chest pain, shortness of breath, weakness, or slurring of speech, and to report any of these symptoms to their health care provider immediately [ see Warnings and Precautions ( 5.1 ) ]. Gastrointestinal Bleeding, Ulceration, and Perforation Advise patients to report symptoms of ulcerations and bleeding, including epigastric pain, dyspepsia, melena, and hematemesis to their health care provider.
In the setting of concomitant use of low-dose aspirin for cardiac prophylaxis, inform patients of the increased risk for and the signs and symptoms of GI bleeding [ see Contraindications ( 4 ), Warnings and Precautions ( 5.2 ) ]. Hepatotoxicity Inform patients of the warning signs and symptoms of hepatotoxicity (e.g., nausea, fatigue, lethargy, pruritus, diarrhea, jaundice, right upper quadrant tenderness, and “flu-like” symptoms). If these occur, instruct patients to stop SPRIX and seek immediate medical therapy [ see Warnings and Precautions ( 5.3 ) ].
Heart Failure and Edema Advise patients to be alert for the symptoms of congestive heart failure including shortness of breath, unexplained weight gain, or edema and to contact their healthcare provider if such symptoms occur [ see Warnings and Precautions ( 5.5 ) ]. Anaphylactic Reactions Inform patients of the signs of an anaphylactic reaction (e.g., difficulty breathing, swelling of the face or throat). Instruct patients to seek immediate emergency help if these occur [ see Contraindications ( 4 ) and Warnings and Precautions ( 5.7 ) ].
Serious Skin Reactions, including DRESS Advise patients to stop taking SPRIX immediately if they develop any type of rash or fever and to contact their healthcare provider as soon as possible [ see Warnings and Precautions ( 5.9 , 5.10 ) ]. Female Fertility Advise females of reproductive potential who desire pregnancy that NSAIDs, including SPRIX, may be associated with a reversible delay in ovulation [ see Use in Specific Populations ( 8.3 ) ]. Fetal Toxicity Inform pregnant women to avoid use of SPRIX and other NSAIDs starting at 30 weeks gestation because of the risk of the premature closing of the fetal ductus arteriosus.
If treatment with SPRIX is needed for a pregnant woman between about 20 to 30 weeks gestation, advise her that she may need to be monitored for oligohydramnios, if treatment continues for longer than 48 hours [ see Warnings and Precautions ( 5.10 ) and Use in Specific Populations ( 8.1 ) ]. Avoid Concomitant Use of NSAIDs Inform patients that the concomitant use of SPRIX with other NSAIDs or salicylates (e.g., diflunisal, salsalate) is not recommended due to the increased risk of gastrointestinal toxicity, and little or no increase in efficacy [ see Warnings and Precautions ( 5.2 ) and Drug Interactions ( 7 ) ].
Alert patients that NSAIDs may be present in “over the counter” medications for treatment of colds, fever, or insomnia. Use of NSAIDS and Low-Dose Aspirin Inform patients not to use low-dose aspirin concomitantly with SPRIX until they talk to their healthcare provider [ see Drug Interactions ( 7 ) ]. Renal Effects SPRIX… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
Medication Guide for Nonsteroidal Anti-inflammatory Drugs (NSAIDs) What is the most important information I should know about medicines called Nonsteroidal Anti-inflammatory Drugs (NSAIDs)? NSAIDs can cause serious side effects, including: Increased risk of a heart attack or stroke that can lead to death. This risk may happen early in treatment and may increase: with increasing doses of NSAIDs with longer use of NSAIDs Do not take NSAIDs right before or after a heart surgery called a “coronary artery bypass graft (CABG)." Avoid taking NSAIDs after a recent heart attack, unless your healthcare provider tells you to.
You may have an increased risk of another heart attack if you take NSAIDs after a recent heart attack. Increased risk of bleeding, ulcers, and tears (perforation) of the esophagus (tube leading from the mouth to the stomach), stomach and intestines: anytime during use without warning symptoms that may cause death The risk of getting an ulcer or bleeding increases with: past history of stomach ulcers, or stomach or intestinal bleeding with use of NSAIDs taking medicines called “corticosteroids”, “anticoagulants”, “SSRIs”, or “SNRIs” increasing doses of NSAIDs longer use of NSAIDs smoking drinking alcohol older age poor health advanced liver disease bleeding problems NSAIDs should only be used: exactly as prescribed at the lowest dose possible for your treatment for the shortest time needed What are NSAIDs?
NSAIDs are used to treat pain and redness, swelling, and heat (inflammation) from medical conditions such as different types of arthritis, menstrual cramps, and other types of short-term pain. Who should not take NSAIDs? Do not take NSAIDs: if you have had an asthma attack, hives, or other allergic reaction with aspirin or any other NSAIDs. right before or after heart bypass surgery.
Before taking NSAIDs, tell your healthcare provider about all of your medical conditions, including if you: have liver or kidney problems have high blood pressure have asthma are pregnant or plan to become pregnant. Taking NSAIDs at about 20 weeks of pregnancy or later may harm your unborn baby. If you need to NSAIDs for more than 2 days when you are between 20 and 30 weeks of pregnancy, your healthcare provider may need to monitor the amount of fluid in your womb around your baby.
You should not take NSAIDs after about 30 weeks of pregnancy. are breastfeeding or plan to breast feed. Tell your healthcare provider about all of the medicines you take, including prescription or over-the-counter medicines, vitamins or herbal supplements. NSAIDs and some other medicines can interact with each other and cause serious side effects.
Do not start taking any new medicine without talking to your healthcare provider first. What are the possible side effects of NSAIDs? NSAIDs can cause serious side effects, including: See “ What is the most important information I should know about medicines called Nonsteroidal Anti-inflammatory Drugs (NSAIDs)? ” new or worse high blood pressure heart failure liver problems including liver failure kidney problems including kidney failure low red blood cells (anemia) life-threatening skin reactions life-threatening allergic reactions Other side effects of NSAIDs include: stomach pain, constipation, diarrhea, gas, heartburn, nausea, vomiting, and dizziness.
Get emergency help right away if you get any of the following symptoms: shortness of breath or trouble breathing chest pain weakness in one part or side of your body slurred speech swelling of the face or throat Stop taking your NSAID and call your healthcare provider right away if you get any of the following symptoms: nausea more tired or weaker than usual diarrhea itching your skin or eyes look yellow indigestion or stomach pain flu-like symptoms vomit blood there is blood in your bowel movement or it is black and sticky like tar unusual weight gain skin rash or blisters with fever swelling of the arms, legs, hands and feet If you take too much of your NSAID, c… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
8.3Females and Males of Reproductive Potential Infertility Females Based on the mechanism of action, the use of prostaglandin-mediated NSAIDs, including SPRIX, may delay or prevent rupture of ovarian follicles, which has been associated with reversible infertility in some women. Published animal studies have shown that administration of prostaglandin synthesis inhibitors has the potential to disrupt prostaglandin-mediated follicular rupture required for ovulation. Small studies in women treated with NSAIDs have also shown a reversible delay in ovulation.
Consider withdrawal of NSAIDs, including SPRIX, in women who have difficulties conceiving or who are undergoing investigation of infertility.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The half-lives of ketorolac by the IN and IM routes were similar. The bioavailability of ketorolac by the IN route of administration of a 31.5 mg dose was approximately 60% compared to IM administration. (See Table 3 ).
Table 3: Pharmacokinetic Parameters of Ketorolac Tromethamine after Intramuscular (IM) and Intranasal (IN) Administration C max = maximum plasma concentration; t max = time of C max ; AUC 0-∞ = complete area under the concentration-time curve; T ½ = half-life; SD = standard deviation. All values are means, except t max , for which medians are reported. Ketorolac Tromethamine C max (SD) ng/mL t max (range) hours AUC 0-∞ (SD) ng•h/mL T ½ (SD) hours 30 mg IM (1.0 mL of a 30 mg/mL solution) 2382.2 (432.7) 0.75 (0.25-1.03) 11152.8 (4260.1) 4.80 (1.18) 31.5 mg IN (SPRIX) (2 x 100 μL of a 15% w/w solution) 1805.8 (882.8) 0.75 (0.50-2.00) 7477.3 (3654.4) 5.24 (1.33) 15 mg IM (0.5 mL of a 30 mg/mL solution) 1163.4 (279.9) 0.75 (0.25-1.50) 5196.3 (2076.7) 5.00 (1.72) Absorption In a study in which SPRIX (31.5 mg) was administered to healthy volunteers four times daily for 5 days, the C max , t max , and AUC values following the final dose were comparable to those obtained in the single-dose study.
Accumulation of ketorolac has not been studied in special populations, geriatric, pediatric, renal failure or hepatic disease patients. Distribution Scintigraphic assessment of drug disposition of ketorolac following SPRIX intranasal dosing demonstrated that most of the ketorolac was deposited in the nasal cavity and pharynx, with less than 20% deposited in the esophagus and stomach, and zero or negligible deposition in the lungs (<0.5%). The mean apparent volume (Vβ) of ketorolac tromethamine following complete distribution was approximately 13 liters.
This parameter was determined from single-dose data. The ketorolac tromethamine racemate has been shown to be highly protein bound (99.2%). Nevertheless, plasma concentrations as high as 10 mcg/mL will only occupy approximately 5% of the albumin binding sites.
Thus, the unbound fraction for each enantiomer will be constant over the therapeutic range. A decrease in serum albumin, however, will result in increased free drug concentrations. Therapeutic concentrations of digoxin, warfarin, ibuprofen, naproxen, piroxicam, acetaminophen, phenytoin, and tolbutamide did not alter ketorolac protein binding.
In vitro studies indicate that, at therapeutic concentrations of salicylate (300 mcg/mL), the binding of ketorolac was reduced from approximately 99.2% to 97.5%, representing a potential twofold increase in unbound ketorolac plasma levels. The in vitro binding of warfarin to plasma proteins is only slightly reduced by ketorolac (99.5% control vs. 99.3%) when ketorolac plasma concentrations reach 5 to 10 mcg/mL.
Ketorolac tromethamine is excreted in human milk. Elimination Metabolism Ketorolac tromethamine is largely metabolized in the liver. The metabolic products are hydroxylated and conjugated forms of the parent drug.
The products of metabolism, and some unchanged drug, are excreted in the urine. There is no evidence in animal or human studies that ketorolac induces or inhibits hepatic enzymes capable of metabolizing itself or other drugs. Excretion The principal route of elimination of ketorolac and its metabolites is renal.
About 92% of a given dose is found in the urine, approximately 40% as metabolites and 60% as unchanged ketorolac. Approximately 6% of a dose is excreted in the feces. A single-dose study with 10 mg ketorolac tromethamine (n = 9) demonstrated that the S-enantiomer is cleared approximately two times faster than the R-enantiomer and that the clearance was independent of the route of administration.
This means that the ratio of S/R plasma concentrations decreases with time after each dose. There is little or no inversion of the R- to S- form in humans. The half-life of the ketorolac tromethamine S-enantiomer was approximately 2.5 hours (SD ±… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Postoperative Pain The effect of SPRIX on acute pain was evaluated in two multi-center, randomized, double-blind, placebo-controlled studies. In a study of adults who had undergone elective abdominal or orthopedic surgery, 300 patients were randomized and treated with SPRIX or placebo administered every 8 hours and morphine administered via patient controlled analgesia on an as needed basis. Efficacy was demonstrated as a statistically significant greater reduction in the summed pain intensity difference over 48 hours in patients who received SPRIX as compared to those receiving placebo.
The clinical relevance of this is reflected in the finding that patients treated with SPRIX required 36% less morphine over 48 hours than patients treated with placebo. In a study of adults who had undergone elective abdominal surgery, 321 patients were randomized and treated with SPRIX or placebo administered every 6 hours and morphine administered via patient controlled analgesia on an as needed basis. Efficacy was demonstrated as a statistically significant greater reduction in the summed pain intensity difference over 48 hours in patients who received SPRIX as compared to those receiving placebo.
The clinical relevance of this is reflected in the finding that patients treated with SPRIX required 26% less morphine over 48 hours than patients treated with placebo.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis An 18-month study in mice with oral doses of ketorolac at 2 mg/kg/day (approximately 1.3 times the human systemic exposure at the recommended maximum IN dose of 31.5 mg four times a day, based on area-under-the-plasma-concentration curve [AUC]), and a 24-month study in rats at 5 mg/kg/day (approximately 0.8 times the human AUC) showed no evidence of tumorigenicity. Mutagenesis Ketorolac was not mutagenic in the Ames test, unscheduled DNA synthesis and repair, or in forward mutation assays.
Ketorolac did not cause chromosome breakage in the in vivo mouse micronucleus assay. At 1590 μg/mL and at higher concentrations, ketorolac increased the incidence of chromosomal aberrations in Chinese hamster ovarian cells. Impairment of fertility Impairment of fertility did not occur in male or female rats at oral doses of 9 mg/kg (approximately 1.3 times the human AUC) and 16 mg/kg (approximately 2.4 times the human AUC) of ketorolac, respectively.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis An 18-month study in mice with oral doses of ketorolac at 2 mg/kg/day (approximately 1.3 times the human systemic exposure at the recommended maximum IN dose of 31.5 mg four times a day, based on area-under-the-plasma-concentration curve [AUC]), and a 24-month study in rats at 5 mg/kg/day (approximately 0.8 times the human AUC) showed no evidence of tumorigenicity. Mutagenesis Ketorolac was not mutagenic in the Ames test, unscheduled DNA synthesis and repair, or in forward mutation assays.
Ketorolac did not cause chromosome breakage in the in vivo mouse micronucleus assay. At 1590 μg/mL and at higher concentrations, ketorolac increased the incidence of chromosomal aberrations in Chinese hamster ovarian cells. Impairment of fertility Impairment of fertility did not occur in male or female rats at oral doses of 9 mg/kg (approximately 1.3 times the human AUC) and 16 mg/kg (approximately 2.4 times the human AUC) of ketorolac, respectively.
📖 Instructions for Use ▾
Instructions for Use SPRIX ® (spriks) (ketorolac tromethamine) Nasal Spray Read this Instructions for Use before you start using SPRIX and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or your treatment.
Important information: SPRIX is for use in your nose only. Do not breathe in (inhale) SPRIX. Each SPRIX bottle has enough pain medicine for 1 day.
Throw away each SPRIX bottle within 24 hours of taking your first dose, even if the bottle still contains unused medicine. Your healthcare provider has prescribed SPRIX to treat moderate to severe pain. Use SPRIX exactly as your healthcare provider tells you to use it.
Your healthcare provider will tell you how many sprays you should use each time you use SPRIX. Do not use SPRIX for more than 5 days. If you still have pain after 5 days, contact your healthcare provider.
Do not use SPRIX more than every 6 hours. It is important that you drink plenty of fluids while you are using SPRIX. Tell your healthcare provider if you urinate less while using SPRIX.
You may have discomfort or irritation in your nose when using SPRIX. This usually lasts for a short time. Do not breathe in (inhale) SPRIX while spraying.
Using SPRIX Nasal Spray Parts of your SPRIX bottle Follow the instructions below to use SPRIX. Before you use SPRIX for the first time, you will need to prime the bottle. Priming SPRIX: Step 1.
Hold the finger flange with your fingers (see Figure A ) , and remove the clear plastic cover with your opposite hand. Keep the clear plastic cover for later. Remove and throw away the blue plastic safety clip.
If the clear plastic cover is improperly removed, the tip of the bottle may be pulled off of the glass vial. If this happens, place the tip back onto the glass vial by lining it up carefully and gently pushing it back on until it is back in the correct position (see Figure B ) . The SPRIX bottle should work properly again.
Step 2. Hold the SPRIX bottle upright at arm’s length away from you with your index finger and middle finger resting on the top of the finger flange and your thumb supporting the base (see Figure C ) . Press down on the finger flange and release the pump 5 times.
You may not see a spray the first few times you press down. Now the pump is primed and ready to use. You do not need to prime the pump again if you use more doses from this bottle.
Step 3. Blow your nose to clear your nostrils. Step 4.
Sit up straight or stand. Step 5. Keep your head tilted downward toward your toes.
Step 6. Place the tip of the SPRIX bottle into your right nostril. Step 7.
Hold the SPRIX bottle upright and aim the tip toward the back of your nose (see Figure D ) . Step 8. Hold your breath and spray 1 time into your right nostril, pressing down on both sides of the finger flange (see Figure D ) .
Step 9. Breathe in gently through your mouth after you use SPRIX. You may also pinch your nose to help keep the medicine in your nose.
Step 10. If your healthcare provider has prescribed only 1 spray per dose for you, you have now finished your dose, skip to Step 12 below. Step 11.
If your healthcare provider has prescribed 2 sprays for you, repeat steps 3 - 9 above for your left nostril. Be sure to point the spray away from the center of your nose. Spray 1 time into your left nostril.
Step 12. When you are finished using SPRIX, put the clear plastic cover back on the SPRIX bottle. How should I store SPRIX?
Store unopened SPRIX bottles between 36°F to 46°F (2°C to 8°C). Keep opened bottles of SPRIX at room temperature. Keep SPRIX out of direct sunlight.
Do not freeze SPRIX. SPRIX does not contain a preservative. Throw away each SPRIX bottle within 24 hours of taking your first dose, even if the bottle still contains unused medicine.
Keep SPRIX and all medicines out of the reach of children. General information about the safe and effective use of SPRIX. Medicines are sometimes pres… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Warnings and Precautions ( 5.9 ) 11/2024
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - NDC 69344-144-63 - Vial Label Vial Label
PRINCIPAL DISPLAY PANEL - NDC 69344-144-43 - Carton Label Carton Label
PRINCIPAL DISPLAY PANEL - NDC 69344-144-53 - Carton Label Carton Label
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |