
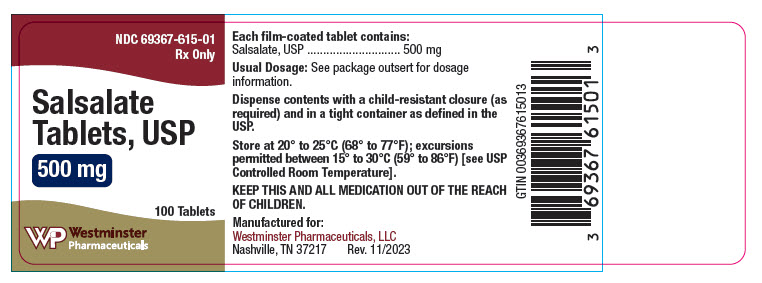
Salsalate 500 mg Tablet, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Salicylic acid and derivatives class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Salsalate is a close cousin of aspirin — both belong to the salicylate family and work by reducing inflammation in your body. The main practical difference is that salsalate isn't...
- What exactly is salsalate and how is it different from aspirin?
- Don't be discouraged if you don't feel better right away — salsalate works gradually. It can take 3 to 4 days of regular use before salicylate levels in your blood reach a steady,...
- How long does it take for salsalate to start working?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Salsalate — tap one for details:
Salsalate may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII H8AV0SQX4D
A modified starch derived from potato or corn starch. It absorbs water quickly and helps tablets or capsules break apart and dissolve in the stomach, acting as a disintegrant to ensure the medicine releases its active ingredients properly.
-
UNII 4ELV7Z65AP
Stearic acid is a fatty acid derived from plant or animal sources. It acts as a binder and lubricant in tablets and capsules, helping them hold together and flow smoothly during manufacturing.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.235 | $23.46 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.3967 | $39.67 / 100 tablets |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Salsalate 500 mg 65162-0512-10 | Amneal | 100 tablets | $0.235 | — | Availability likely | — |
| Salsalate 500 mgthis 69367-0615-01 | Westminster | 100 tablets | $0.235 | — | Availability likely | — |
| Salsalate 500 mg 63629-9247-01 | Bryant | 100 tablets | — | — | Discontinued | — |
| Salsalate 500 mg 63629-9248-01 | Bryant | 500 tablets | — | — | Discontinued | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 69367-0615-01 You're viewing this | 100 TABLET in 1 BOTTLE (69367-615-01) | 2023-11-15 | Active |
🧭 About this NDC listing & data coverage
Listed without an FDA application
This product's marketing category indicates it is marketed without an approved FDA application (no NDA, ANDA, or BLA on file). Having an NDC does not by itself establish FDA approval — the NDC Directory is a listing system, not an approval decision. Approval-linked data such as Orange Book therapeutic-equivalence ratings therefore does not apply.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Is this NDC FDA-approved?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
Cardiovascular Risk NSAIDs may cause an increased risk of serious cardiovascular thrombotic events, myocardial infarction, and stroke, which can be fatal. This risk may increase with duration of use. Patients with cardiovascular disease or risk factors for cardiovascular disease may be at greater risk (see WARNINGS and CLINICAL TRIALS).
Salsalate tablets, USP are contraindicated for the treatment of perioperative pain in the setting of coronary artery bypass graft (CABG) surgery (see WARNINGS ). Gastrointestinal Risk NSAIDs cause an increased risk of serious gastrointestinal adverse events including bleeding, ulceration, and perforation of the stomach or intestines, which can be fatal. These events can occur at any time during use and without warning symptoms.
Elderly patients are at greater risk for serious gastrointestinal events (see WARNINGS ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Carefully consider the potential benefits and risks of Salsalate tablets, USP and other treatment options before deciding to use Salsalate tablets, USP. Use the lowest effective dose for the shortest duration consistent with individual patient treatment goals (see WARNINGS ). Salsalate, USP is indicated for relief of the signs and symptoms of rheumatoid arthritis, osteoarthritis and related rheumatic disorder.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Carefully consider the potential benefits and risks of Salsalate tablets, USP and other treatment options before deciding to use Salsalate tablets, USP. Use the lowest effective dose for the shortest duration consistent with individual patient treatment goals (see WARNINGS ). After observing the response to initial therapy with Salsalate tablets, USP, the dose and frequency should be adjusted to suit an individual patient's needs.
Salsalate, USP is indicated for relief of the signs and symptoms of rheumatoid arthritis, osteoarthritis and related rheumatic disorder. Adults The usual dosage is 3000 mg daily, given in divided doses as follows: 1) two doses of two 750 mg tablets; 2) two doses of three 500 mg tablets; or 3) three doses of two 500 mg tablets. Some patients, e.g., the elderly, may require a lower dosage to achieve therapeutic blood concentrations and to avoid the more common side effects such as auditory.
Alleviation of symptoms is gradual, and full benefit may not be evident for 3 to 4 days, when plasma salicylate levels have achieved steady-state. There is no evidence for development of tissue tolerance (tachyphylaxis), but salicylate therapy may induce increased activity of metabolizing liver enzymes, causing a greater rate of salicyluric acid production and excretion, with a resultant increase in dosage requirement for maintenance of therapeutic serum salicylate levels. Children Dosage recommendations and indications for salsalate, USP use in children have not been established.
⛔ Contraindications ▾
CONTRAINDICATIONS Salsalate tablets, USP are contraindicated in patients with known hypersensitivity to salsalate, USP. Salsalate tablets, USP should not be given to patients who have experienced asthma, urticaria, or allergic-type reactions after taking aspirin or other NSAIDs. Severe, rarely fatal, anaphylactic-like reactions to NSAIDs have been reported in such patients (see WARNINGS – Anaphylactoid Reactions , and PRECAUTIONS - Preexisting Asthma ).
Salsalate tablets, USP are contraindicated for the treatment of peri-operative pain in the setting of coronary artery bypass graft (CABG) surgery (see WARNINGS ).
⚠️ Warnings ▾
WARNINGS Reye's Syndrome may develop in individuals who have chicken pox, influenza, or flu symptoms. Some studies suggest a possible association between the development of Reye's Syndrome and the use of medicines containing salicylate or aspirin. Salsalate contains a salicylate and therefore is not recommended for use in patients with chicken pox, influenza, or flu symptoms.
CARDIOVASCULAR EFFECTS Cardiovascular Thrombotic Events Clinical trials of several COX-2 selective and nonselective NSAIDs of up to three years duration have shown an increased risk of serious cardiovascular (CV) thrombotic events, myocardial infarction, and stroke, which can be fatal. All NSAIDs, both COX-2 selective and nonselective, may have a similar risk. Patients with known CV disease or risk factors for CV disease may be at greater risk.
To minimize the potential risk for an adverse CV event in patients treated with an NSAID, the lowest effective dose should be used for the shortest duration possible. Physicians and patients should remain alert for the development of such events, even in the absence of previous CV symptoms. Patients should be informed about the signs and/or symptoms of serious CV events and the steps to take if they occur.
There is no consistent evidence that concurrent use of aspirin mitigates the increased risk of serious CV thrombotic events associated with NSAID use. The concurrent use of aspirin and an NSAID does increase the risk of serious GI events (see GI WARNINGS ). Two large, controlled, clinical trials of a COX-2 selective NSAID for the treatment of pain in the first 10 to 14 days following CABG surgery found an increased incidence of myocardial infarction and stroke (see CONTRAINDICATIONS ).
Hypertension NSAIDs, including Salsalate tablets, can lead to onset of new hypertension or worsening of pre-existing hypertension, either of which may contribute to the increased incidence of CV events. Patients taking thiazides or loop diuretics may have impaired response to these therapies when taking NSAIDs. NSAIDs, including Salsalate tablets, should be used with caution in patients with hypertension.
Blood pressure (BP) should be monitored closely during the initiation of NSAID treatment and throughout the course of therapy. Congestive Heart Failure and Edema Fluid retention and edema have been observed in some patients taking NSAIDs. Salsalate tablets should be used with caution in patients with fluid retention or heart failure.
Gastrointestinal Effects Risk of Ulceration, Bleeding, and Perforation NSAIDs, including Salsalate tablets, can cause serious gastrointestinal (GI) adverse events including inflammation, bleeding, ulceration, and perforation of the stomach, small intestine, or large intestine, which can be fatal. These serious adverse events can occur at any time, with or without warning symptoms, in patients treated with NSAIDs. Only one in five patients, who develop a serious upper GI adverse event on NSAID therapy, is symptomatic.
Upper GI ulcers, gross bleeding, or perforation caused by NSAIDs occur in approximately 1% of patients treated for 3 to 6 months, and in about 2% to 4% of patients treated for one year. These trends continue with longer duration of use, increasing the likelihood of developing a serious GI event at some time during the course of therapy. However, even short-term therapy is not without risk.
NSAIDs should be prescribed with extreme caution in those with a prior history of ulcer disease or gastrointestinal bleeding. Patients with a prior history of peptic ulcer disease and/or gastrointestinal bleeding who use NSAIDs have a greater than 10-fold increased risk for developing a GI bleed compared to patients with neither of these risk factors. Other factors that increase the risk for GI bleeding in patients treated with NSAIDs include concomitant use of oral corticosteroids or anticoagulants, longer duration of NSAID therapy, smoking, use of alcohol, older age, and poor general health status.
Mo…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS In two well-controlled clinical trials, the following reversible adverse experiences characteristic of salicylates were most commonly reported with salsalate (n-280 pts; listed in descending order of frequency): tinnitus, nausea, hearing impairment, rash, and vertigo. These common symptoms of salicylates, i.e., tinnitus or reversible hearing impairment, are often used as a guide to therapy. Although cause-and-effect relationships have not been established, spontaneous reports over a ten-year period have included the following additional medically significant adverse experiences: abdominal pain, abnormal hepatic function, anaphylactic shock, angioedema, bronchospasm, decreased creatinine clearance, diarrhea, G.I. bleeding, hepatitis, hypotension, nephritis and urticaria.
To report SUSPECTED ADVERSE REACTIONS, contact Westminster Pharmaceuticals, LLC at 1-844-221-7294 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
DRUG INTERACTIONS ACE-inhibitors Reports suggest that NSAIDs may diminish the antihypertensive effect of ACE-inhibitors. This interaction should be given consideration in patients taking NSAIDs concomitantly with ACE-inhibitors. Aspirin Salicylates antagonize the uricosuric action of drugs used to treat gout.
ASPIRIN AND OTHER SALICYLATE DRUGS WILL BE ADDITIVE TO SALSALATE AND MAY INCREASE PLASMA CONCENTRATIONS OF SALICYLIC ACID TO TOXIC LEVELS. Drugs and foods that raise urine pH will increase renal clearance and urinary excretion of salicylic acid, thus lowering plasma levels: acidifying drugs or foods will decrease urinary excretion and increase plasma levels. Salicylates given concomitantly with anticoagulant drugs may predispose to systemic bleeding.
Salicylates may enhance the hypoglycemic effect of oral antidiabetic drugs of the sulfonylurea class. Salicylate competes with a number of drugs for protein binding sites, notably penicillin, thiopental, thyroxine, triiodothyronine, phenytoin, sulfinpyrazone, naproxen, warfarin, methotrexate, and possibly corticosteroids. [When Salsalate tablets, USP are administered with aspirin, its protein binding is reduced, although the clearance of free Salsalate tablets, USP are not altered. The clinical significance of this interaction is not known; however,] as with other NSAIDs, concomitant administration of salsalate and aspirin is not generally recommended because of the potential of increased adverse effects.
Furosemide Clinical studies, as well as post marketing observations, have shown that Salsalate tablets, USP can reduce the natriuretic effect-of furosemide and thiazides in some patients. This response has been attributed to inhibition of renal prostaglandin synthesis. During concomitant therapy with NSAIDs, the patient should be observed closely for signs of renal failure (see PRECAUTIONS, Renal Effects ), as well as to assure diuretic efficacy.
Lithium NSAIDs have produced an elevation of plasma lithium levels and a reduction in renal lithium clearance. The mean minimum lithium concentration increased 15% and the renal clearance was decreased by approximately 20%. These effects have been attributed to inhibition of renal prostaglandin synthesis by the NSAID.
Thus, when NSAIDs and lithium are administered concurrently, subjects should be observed carefully for signs of lithium toxicity. Methotrexate NSAIDs have been reported to competitively inhibit methotrexate accumulation in rabbit kidney slices. This may indicate that they could enhance the toxicity of methotrexate.
Caution should be used when NSAIDs are administered concomitantly with methotrexate. Warfarin The effects of warfarin and NSAIDs on GI bleeding are synergistic, such that users of both drugs together have a risk of serious GI bleeding higher than users of either drug alone.
🔄 Drug / Laboratory Test Interactions ▾
Drug/Laboratory Test Interactions Salicylate competes with thyroid hormone for binding to plasma proteins, which may be reflected in a depressed plasma T4 value in some patients; thyroid function and basal metabolism are unaffected.
🤰 Pregnancy ▾
Pregnancy Category C Risk Summary Use of NSAIDs, including Salsalate tablets, USP, can cause premature closure of the fetal ductus arteriosus and fetal renal dysfunction leading to oligohydramnios and, in some cases, neonatal renal impairment. Because of these risks, limit dose and duration of Salsalate tablets, USP use between about 20 and 30 weeks of gestation, and avoid Salsalate tablets, USP use at about 30 weeks of gestation and later in pregnancy. Premature Closure of Fetal Ductus Arteriosus Use of NSAIDs, including Salsalate tablets, USP, at about 30 weeks gestation or later in pregnancy increases the risk of premature closure of the fetal ductus arteriosus.
Oligohydramnios/Neonatal Renal Impairment Use of NSAIDs at about 20 weeks gestation or later in pregnancy has been associated with cases of fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment. Data from observational studies regarding other potential embryofetal risks of NSAID use in women in the first or second trimesters of pregnancy are inconclusive. In the general U.S. population, all clinically recognized pregnancies, regardless of drug exposure, have a background rate of 2-4% for major malformations, and 15-20% for pregnancy loss.
Animal reproduction studies conducted in rats and rabbits have not demonstrated evidence of developmental abnormalities. However, animal reproduction studies are not always predictive of human response. There are no adequate and well-controlled studies in pregnant women.
Because of the known effects of nonsteroidal anti-inflammatory drugs on the fetal cardiovascular system (closure of ductus arteriosus), use during pregnancy (particularly late pregnancy) should be avoided. Based on animal data, prostaglandins have been shown to have an important role in endometrial vascular permeability, blastocyst implantation, and decidualization. In animal studies, administration of prostaglandin synthesis inhibitors such as [active moiety], resulted in increased pre- and post-implantation loss.
Prostaglandins also have been shown to have an important role in fetal kidney development. In published animal studies, prostaglandin synthesis inhibitors have been reported to impair kidney development when administered at clinically relevant doses. Clinical Considerations Fetal/Neonatal Adverse Reactions Premature Closure of Fetal Ductus Arteriosus Avoid use of NSAIDs in women at about 30 weeks gestation and later in pregnancy, because NSAIDs, including Salsalate tablets, USP, can cause premature closure of the fetal ductus arteriosus (see Data ).
Oligohydramnios/Neonatal Renal Impairment If an NSAID is necessary at about 20 weeks gestation or later in pregnancy, limit the use to the lowest effective dose and shortest duration possible. If Salsalate tablets, USP treatment extends beyond 48 hours, consider monitoring with ultrasound for oligohydramnios. If oligohydramnios occurs, discontinue Salsalate tablets, USP and follow up according to clinical practice (see Data ).
Data Human Data Premature Closure of Fetal Ductus Arteriosus Published literature reports that the use of NSAIDs at about 30 weeks of gestation and later in pregnancy may cause premature closure of the fetal ductus arteriosus. Oligohydramnios/Neonatal Renal Impairment Published studies and postmarketing reports describe maternal NSAID use at about 20 weeks gestation or later in pregnancy associated with fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment. These adverse outcomes are seen, on average, after days to weeks of treatment, although oligohydramnios has been infrequently reported as soon as 48 hours after NSAID initiation.
In many cases, but not all, the decrease in amniotic fluid was transient and reversible with cessation of the drug. There have been a limited number of case reports of maternal NSAID use and neonatal renal dysfunction without oligohydramnios, some of which were irreversible…
🆘 Overdosage ▾
OVERDOSAGE Death has followed ingestion of 10 to 30 g of salicylates in adults, but much larger amounts have been ingested without fatal outcome. Symptoms The usual symptoms of salicylism - tinnitus, vertigo, headache, confusion, drowsiness, sweating, hyperventilation, vomiting and diarrhea - will occur. More severe intoxication will lead to disruption of electrolyte balance and blood pH, and hyperthermia and dehydration.
Treatment Further absorption of salsalate from the G.I. tract should be prevented by emesis (syrup of ipecac), and, if necessary, by gastric lavage. Fluid and electrolyte imbalance should be corrected by the administration of appropriate I.V. therapy. Adequate renal function should be maintained.
Hemodialysis or peritoneal dialysis may be required in extreme cases.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Salsalate is insoluble in acid gastric fluids (<0.1 mg/ml at pH 1.0), but readily soluble in the small intestine where it is partially hydrolyzed to two molecules of salicylic acid. A significant portion of the parent compound is absorbed unchanged and undergoes rapid esterase hydrolysis in the body: its half-life is about one hour. About 13% is excreted through the kidneys as a glucuronide conjugate of the parent compound, the remainder as salicylic acid and its metabolites.
Thus, the amount of salicylic acid available from salsalate is about 15% less than from aspirin, when the two drugs are administered on a salicylic acid molar equivalent basis (3.6 g salsalate/5 g aspirin). Salicylic acid biotransformation is saturated at anti-inflammatory doses of salsalate. Such capacity-limited biotransformation results in an increase in the half-life of salicylic acid from 3.5 to 16 or more hours.
Thus, dosing with salsalate twice a day will satisfactorily maintain blood levels within the desired therapeutic range (10 to 30 mg/100 mL) throughout the 12-hour intervals. Therapeutic blood levels continue for up to 16 hours after the last dose. The parent compound does not show capacity-limited biotransformation, nor does it accumulate in the plasma on multiple dosing.
Food slows the absorption of all salicylates including salsalate. The mode of anti-inflammatory action of salsalate and other nonsteroidal anti-inflammatory drugs is not fully defined. Although salicylic acid (the primary metabolite of salsalate) is a weak inhibitor of prostaglandin synthesis in vitro , salsalate appears to selectively inhibit prostaglandin synthesis in vivo 1 , providing anti-inflammatory activity equivalent to aspirin 2 and indomethacin 3 .
Unlike aspirin, salsalate does not inhibit platelet aggregation 4 . The usefulness of salicylic acid, the active in vivo product of salsalate, in the treatment of arthritic disorders has been established 5,6 . In contrast to aspirin, salsalate causes no greater fecal gastrointestinal blood loss than placebo 7 .
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED 500 mg Tablets: Supplied in bottles of 100ct (NDC 69367-615-01) Appearance: Yellow, round, Biconvex tablet, debossed "615" on one side and plain on the other side. 750 mg Tablets: Supplied in bottles of 100ct (NDC 69367-616-01) Appearance: Yellow, capsule-shaped, Biconvex tablet, debossed "616" on one side and plain on the other side. Dispense contents with a child-resistant closure (as required) and in a tight container as defined in the USP.
Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Rx only
📦 Storage and Handling ▾
Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Rx only
📋 Description ▾
DESCRIPTION Salsalate USP, is a nonsteroidal anti-inflammatory agent for oral administration. Chemically, salsalate, USP (salicylsalicylic acid or 2-hydroxy-benzoic acid, 2-carboxyphenyl ester) is a dimer of salicylic acid; its structural formula is shown below. Chemical Structure: Tablets: Inactive Ingredients: Colloidal Silicon Dioxide, D&C Yellow #10, Hypromellose, Microcrystalline Cellulose, Sodium Starch Glycolate, Stearic Acid, Titanium Dioxide, Triacetin.
Chemical Structure
💬 Information for Patients ▾
INFORMATION FOR PATIENTS Patients should be informed of the following information before initiating therapy with an NSAID and periodically during the course of ongoing therapy. Patients should also be encouraged to read the NSAID Medication Guide that accompanies each prescription dispensed. 1.
Salsalate tablets, USP, like other NSAIDs, may cause serious CV side effects, such as MI or stroke, which may result in hospitalization and even death. Although serious CV events can occur without warning symptoms, patients should be alert for the signs and symptoms of chest pain, shortness of breath, weakness, slurring of speech, and should ask for medical advice when observing any indicative sign or symptoms. Patients should be apprised of the importance of this follow-up (see WARNINGS, Cardiovascular Effects ).
2. Salsalate tablets, USP, like other NSAIDs, can cause GI discomfort and, rarely, serious GI side effects, such as ulcers and bleeding, which may result in hospitalization and even death. Although serious GI tract ulcerations and bleeding can occur without warning symptoms, patients should be alert for the signs and symptoms of ulcerations and bleeding, and should ask for medical advice when observing any indicative sign or symptoms including epigastric pain, dyspepsia, melena, and hematemesis.
Patients should be apprised of the importance of this follow-up (see WARNINGS, Gastrointestinal Effects: Risk of Ulceration, Bleeding, and Perforation ). 3. Salsalate tablets, USP like other NSAIDs, can cause serious skin side effects such as exfoliative dermatitis, SJS, and TEN, which may result in hospitalizations and even death.
Although serious skin reactions may occur without warning, patients should be alert for the signs and symptoms of skin rash and blisters, fever, or other signs of hypersensitivity such as itching, and should ask for medical advice when observing any indicative signs or symptoms. Patients should be advised to stop the drug immediately if they develop any type of rash and contact their physicians as soon as possible. 4.
Patients should promptly report signs or symptoms of unexplained weight gain or edema to their physicians. 5. Patients should be informed of the warning signs and symptoms of hepatotoxicity (e.g., nausea, fatigue, lethargy, pruritus, jaundice, right upper quadrant tenderness, and "flu-like" symptoms).
If these occur, patients should be instructed to stop therapy and seek immediate medical therapy. 6. Patients should be informed of the signs of an anaphylactoid reaction (e.g. difficulty breathing, swelling of the face or throat).
If these occur, patients should be instructed to seek immediate emergency help (see WARNINGS ). 7. In late pregnancy, as with other NSAIDs, Salsalate tablets, USP should be avoided because it will cause premature closure of the ductus arteriosus.