
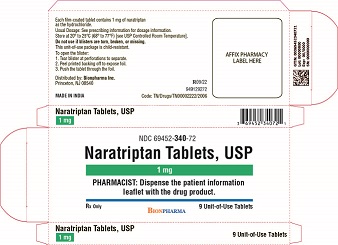
Naratriptan 1 mg Tablet, Film Coated, 9-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Serotonin-1b and Serotonin-1d Receptor Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Naratriptan is used to treat the symptoms of migraine headaches (severe, throbbing headaches that sometimes come with nausea and a strong reaction to sound or light). Naratriptan is in a class of medications called selective serotonin receptor agonists. It works by narrowing blood vessels around the brain, stopping pain signals from being sent to the brain, which stops the release of certain natural substances that cause pain, nausea, and other symptoms of migraines. Naratriptan does not stop migraine attacks from coming or reduce the number of headaches you have.
Read the full MedlinePlus article ↗- Naratriptan is specifically designed to treat migraine attacks — it targets the biological processes that cause migraine pain, including blood vessel changes and the release of pai...
- What exactly is naratriptan for, and how is it different from everyday pain relievers?
- You can take naratriptan at the onset of a migraine. There's no need to wait until the pain becomes severe — in fact, taking it early during an attack tends to work better. If your...
- When should I take it during a migraine — right away, or should I wait to see if it gets bad?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Naratriptan — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $2.94 | $26.50 / 9 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Naratriptan 1 mg 00054-0278-03 | Hikma | 9 tablets | $1.981 | AB | Availability likely | — |
| naratriptan 1 mg 23155-0054-03 | Heritage | 30 tablets | — | AB | FDA listed | — |
| Naratriptan 1 mgthis 69452-0340-72 | Bionpharma | 9 tablets | — | AB | FDA listed | — |
| naratriptan 1 mg 87063-0287-09 | ASCLEMED | 9 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 69452-0340-72 You're viewing this | 1 BLISTER PACK in 1 CARTON (69452-340-72) / 9 TABLET, FILM COATED in 1 BLISTER PACK (69452-340-60) | 2022-04-11 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Naratriptan tablets are indicated for the acute treatment of migraine with or without aura in adults. Limitations of Use Use only if a clear diagnosis of migraine has been established. If a patient has no response to the first migraine attack treated with naratriptan tablets, reconsider the diagnosis of migraine before naratriptan tablets are administered to treat any subsequent attacks.
Naratriptan tablets are not indicated for the prevention of migraine attacks. Safety and effectiveness of naratriptan tablets have not been established for cluster headache. Naratriptan tablets are a serotonin (5-HT 1B/1D ) receptor agonist (triptan) indicated for the acute treatment of migraine with or without aura in adults.
(1) Limitations of Use: Use only if a clear diagnosis of migraine has been established. (1) Not indicated for the prophylactic therapy of migraine attacks. (1) Not indicated for the treatment of cluster headache.
(1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended dose: 1 mg or 2.5 mg. (2.1) May repeat dose after 4 hours if needed; not to exceed 5 mg in any 24 hour period. (2.1) Mild or moderate renal or hepatic impairment: recommended starting dose is 1 mg not to exceed 2.5 mg in any 24 hour period. (2.2, 2.3)
2.1Dosing Information The recommended dose of naratriptan tablets is 1 mg or 2.5 mg. If the migraine returns or if the patient has only partial response, the dose may be repeated once after 4 hours, for a maximum dose of 5 mg in a 24 hour period. The safety of treating an average of more than 4 migraine attacks in a 30 day period has not been established.
2.2Dosage Adjustment in Patients with Renal Impairment Naratriptan tablets are contraindicated in patients with severe renal impairment (creatinine clearance: <15 mL/min) because of decreased clearance of the drug [see Contraindications (4), Use in Specific Populations (8.6), Clinical Pharmacology (12.3)]. In patients with mild to moderate renal impairment, the maximum daily dose should not exceed 2.5 mg over a 24‑hour period and a 1 mg starting dose is recommended [see Use in Specific Populations (8.6), Clinical Pharmacology (12.3)] .
2.3Dosage Adjustment in Patients with Hepatic Impairment Naratriptan tablets are contraindicated in patients with severe hepatic impairment (Child-Pugh Grade C) because of decreased clearance [see Contraindications (4), Use in Specific Populations (8.7), Clinical Pharmacology (12.3)]. In patients with mild or moderate hepatic impairment (Child-Pugh Grade A or B), the maximum daily dose should not exceed 2.5 mg over a 24 hour period and a 1 mg starting dose is recommended [see Use in Specific Populations (8.7), Clinical Pharmacology (12.3)] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 1 mg white to off-white tablets, capsule shaped, film-coated, and debossed with "N" on one side and "1" on the other side 2.5 mg green tablets, capsule shaped, film-coated, and debossed with "N" on one side and "2.5" on the other side Tablets: 1 mg and 2.5 mg (3, 16)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Naratriptan tablets are contraindicated in patients with: Ischemic coronary artery disease (CAD) (angina pectoris, history of myocardial infarction, or documented silent ischemia) or coronary artery vasospasm, including Prinzmetal’s angina [see Warnings and Precautions (5.1)] Wolff-Parkinson-White syndrome or arrhythmias associated with other cardiac accessory conduction pathway disorders [see Warnings and Precautions (5.2)] History of stroke or transient ischemic attack (TIA) or history of hemiplegic or basilar migraine because such patients are at a higher risk of stroke [s ee Warnings and Precautions (5.4)] Peripheral vascular disease [see Warnings and Precautions (5.5)] Ischemic bowel disease [see Warnings and Precautions (5.5)] Uncontrolled hypertension [see Warnings and Precautions (5.8)] Recent use (i.e., within 24 hours) of another 5-HT 1 agonist, ergotamine-containing medication, ergot-type medication (such as dihydroergotamine or methysergide) [see Drug Interactions (7.1, 7.2)] Hypersensitivity to naratriptan tablets (angioedema and anaphylaxis seen) [see Warnings and Precautions (5.9)] Severe renal or hepatic impairment [see Use in Specific Populations (8.6, 8.7), Clinical Pharmacology (12.3)] History of coronary artery disease or coronary artery vasospasm (4) Wolff-Parkinson-White syndrome or other cardiac accessory conduction pathway disorders (4) History of stroke, transient ischemic attack, or hemiplegic or basilar migraine (4) Peripheral vascular disease (4) Ischemic bowel disease (4) Uncontrolled hypertension (4) Recent (within 24 hours) use of another 5-HT 1 agonist (e.g., another triptan) or an ergotamine-containing medication (4) Hypersensitivity to naratriptan tablets (angioedema and anaphylaxis seen) (4) Severe renal or hepatic impairment (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Myocardial ischemia/infarction and Prinzmetal’s angina: Perform cardiac evaluation in patients with multiple cardiovascular risk factors. (5.1) Arrhythmias: Discontinue naratriptan tablets if occurs. (5.2) Chest/throat/neck/jaw pain, tightness, pressure, or heaviness: Generally not associated with myocardial ischemia; evaluate for CAD in patients at high risk.
(5.3) Cerebral hemorrhage, subarachnoid hemorrhage, and stroke: Discontinue naratriptan tablets if occurs. (5.4) Gastrointestinal ischemic reactions and peripheral vasospastic reactions: Discontinue naratriptan tablets if occurs. (5.5) Medication overuse headache: Detoxification may be necessary.
(5.6) Serotonin syndrome: Discontinue naratriptan tablets if occurs. (5.7)
5.1Myocardial Ischemia, Myocardial Infarction, and Prinzmetal’s Angina Naratriptan tablets are contraindicated in patients with ischemic or vasospastic CAD. There have been rare reports of serious cardiac adverse reactions, including acute myocardial infarction, occurring within a few hours following administration of naratriptan tablets. Some of these reactions occurred in patients without known CAD.
Naratriptan tablets may cause coronary artery vasospasm (Prinzmetal’s angina), even in patients without a history of CAD. Perform a cardiovascular evaluation in triptan-naive patients who have multiple cardiovascular risk factors (e.g., increased age, diabetes, hypertension, smoking, obesity, strong family history of CAD) prior to receiving naratriptan tablets. If there is evidence of CAD or coronary artery vasospasm, naratriptan tablets are contraindicated.
For patients with multiple cardiovascular risk factors who have a negative cardiovascular evaluation, consider administering the first dose of naratriptan tablets in a medically supervised setting and performing an electrocardiogram (ECG) immediately following administration of naratriptan tablets. For such patients, consider periodic cardiovascular evaluation in intermittent long-term users of naratriptan tablets.
5.2Arrhythmias Life-threatening disturbances of cardiac rhythm, including ventricular tachycardia and ventricular fibrillation leading to death, have been reported within a few hours following the administration of 5-HT 1 agonists. Discontinue naratriptan tablets if these disturbances occur. Naratriptan tablets are contraindicated in patients with Wolff-Parkinson-White syndrome or arrhythmias associated with other cardiac accessory conduction pathway disorders.
5.3Chest, Throat, Neck, and/or Jaw Pain/Tightness/Pressure Sensations of tightness, pain, and pressure in the chest, throat, neck, and jaw commonly occur after treatment with naratriptan tablets and are usually non-cardiac in origin. However, perform a cardiac evaluation if these patients are at high cardiac risk. 5-HT 1 agonists, including naratriptan tablets, are contraindicated in patients with CAD and those with Prinzmetal’s variant angina.
5.4Cerebrovascular Events Cerebral hemorrhage, subarachnoid hemorrhage, and stroke have occurred in patients treated with 5-HT 1 agonists, and some have resulted in fatalities. In a number of cases, it appears possible that the cerebrovascular events were primary, the 5-HT 1 agonist having been administered in the incorrect belief that the symptoms experienced were a consequence of migraine when they were not. Also, patients with migraine may be at increased risk of certain cerebrovascular events (e.g., stroke, hemorrhage, TIA).
Discontinue naratriptan tablets if a cerebrovascular event occurs. Before treating headaches in patients not previously diagnosed as migraineurs, and in migraineurs who present with symptoms atypical for migraine, exclude other potentially serious neurological conditions. Naratriptan tablets are contraindicated in patients with a history of stroke or TIA.
5.5Other Vasospasm Reactions Naratriptan tablets may cause non-coronary vasospastic reactions, such as peripheral vascular ischemia, gast…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in more detail in other sections of the prescribing information: Myocardial ischemia, myocardial infarction, and Prinzmetal’s angina [see Warnings and Precautions (5.1)] Arrhythmias [see Warnings and Precautions (5.2)] Chest, throat, neck, and/or jaw pain/tightness/pressure [see Warnings and Precautions (5.3)] Cerebrovascular events [see Warnings and Precautions (5.4)] Other vasospasm reactions [see Warnings and Precautions (5.5)] Medication overuse headache [see Warnings and Precautions (5.6)] Serotonin syndrome [see Warnings and Precautions (5.7)] Increase in blood pressure [see Warnings and Precautions (5.8)] Hypersensitivity reactions [see Contraindications (4), Warnings and Precautions (5.9)] Most common adverse reactions (≥2 % and > placebo) were paresthesias, nausea, dizziness, drowsiness, malaise/fatigue, and throat/neck symptoms.
(6.1) To report SUSPECTED ADVERSE REACTIONS, contact Bionpharma Inc. at 1-888-235-BION or 1-888-235-2466 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. In a long-term open-label trial where patients were allowed to treat multiple migraine attacks for up to 1 year, 15 patients (3.6%) discontinued treatment due to adverse reactions. In controlled clinical trials, the most common adverse reactions were paresthesias, dizziness, drowsiness, malaise/fatigue, and throat/neck symptoms, which occurred at a rate of 2% and at least 2 times placebo rate.
Table 1 lists the adverse reactions that occurred in 5 placebo-controlled clinical trials of approximately 1,752 exposures to placebo and naratriptan tablets in adult patients with migraine. Only reactions that occurred at a frequency of 2% or more in groups treated with naratriptan tablets 2.5 mg and that occurred at a frequency greater than the placebo group in the 5 pooled trials are included in Table 1. Table 1.
Adverse Reactions Reported by at Least 2% of Patients Treated with Naratriptan Tablets and at a Frequency Greater than Placebo Adverse Reaction Percent of Patients Reporting Naratriptan Tablets 1 mg (n = 627) Naratriptan Tablets 2.5 mg (n = 627) Placebo (n = 498) Atypical sensation 2 4 1 Paresthesias (all types) 1 2 <1 Gastrointestinal 6 7 5 Nausea 4 5 4 Neurological 4 7 3 Dizziness 1 2 1 Drowsiness 1 2 <1 Malaise/fatigue 2 2 1 Pain and pressure sensation 2 4 2 Throat/neck symptoms 1 2 1 The incidence of adverse reactions in controlled clinical trials was not affected by age or weight of the patients, duration of headache prior to treatment, presence of aura, use of prophylactic medications, or tobacco use.
There were insufficient data to assess the impact of race on the incidence of adverse reactions.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Ergot-Containing Drugs Ergot-containing drugs have been reported to cause prolonged vasospastic reactions. Because these effects may be additive, use of ergotamine-containing or ergot-type medications (like dihydroergotamine or methysergide) and naratriptan tablets within 24 hours of each other is contraindicated.
7.2Other 5-HT 1 Agonists Concomitant use of other 5-HT 1B/1D agonists (including triptans) within 24 hours of treatment with naratriptan tablets is contraindicated because the risk of vasospastic reactions may be additive.
7.3Selective Serotonin Reuptake Inhibitors/Serotonin Norepinephrine Reuptake Inhibitors and Serotonin Syndrome Cases of serotonin syndrome have been reported during co-administration of triptans and SSRIs, SNRIs, TCAs, and MAO inhibitors [see Warnings and Precautions (5.7)] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm (8.1)
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with use of naratriptan tablets in pregnant women. Data from a prospective pregnancy exposure registry and epidemiological studies of pregnant women have documented outcomes in women exposed to naratriptan during pregnancy; however, due to small sample sizes, no definitive conclusions can be drawn regarding the risk of birth defects following exposure to naratriptan [see Data] . In animal studies, naratriptan produced developmental toxicity (including embryolethality and fetal abnormalities) when administered to pregnant rats and rabbits.
The lowest doses producing evidence of developmental toxicity in animals were associated with plasma exposures 2.5 (rabbit) to 11 (rat) times that in humans at the maximum recommended daily dose (MRDD) [see Data] . In the U.S. general population, the estimated background risk of major birth defects and of miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. The reported rate of major birth defects among deliveries to women with migraine ranged from 2.2% to 2.9% and of miscarriage was 17%, which were similar to rates reported in women without migraine.
Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Several studies have suggested that women with migraine may be at increased risk of preeclampsia during pregnancy. Data Human Data : The numbers of exposed pregnancy outcomes accumulated during the Sumatriptan/Naratriptan/Treximet ® (sumatriptan and naproxen sodium) Pregnancy Registry, a population-based international prospective study that collected data from October 1997 to September 2012, and smaller observational studies, were insufficient to define a level of risk for naratriptan in pregnant women.
The Registry documented outcomes of 57 infants and fetuses exposed to naratriptan during pregnancy (52 exposed during the first trimester and 5 exposed during the second trimester). The occurrence of major birth defects (excluding fetal deaths and induced abortions without reported defects and all spontaneous pregnancy losses) during first-trimester exposure to naratriptan was 2.2% (1/46 [95% CI: 0.1% to 13%]) and during any trimester of exposure was 2% (1/51 [95% CI: 0.1% to 11.8%]). Seven infants were exposed to both naratriptan and sumatriptan in utero, and one of these infants with first-trimester exposure was born with a major birth defect (ventricular septal defect).
The sample size in this study had 80% power to detect at least a 3.8 to 4.6 fold increase in the rate of major malformations. In a study using data from the Swedish Medical Birth Register, women who used triptans or ergots during pregnancy were compared with women who did not. Of the 22 births with first-trimester exposure to naratriptan, one infant was born with a malformation (congenital deformity of the hand).
Animal Data : When naratriptan was administered to pregnant rats during the period of organogenesis at doses of 10, 60, or 340 mg/kg/day, there was a dose-related increase in embryonic death; incidences of fetal structural variations (incomplete/irregular ossification of skull bones, sternebrae, ribs) were increased at all doses. The maternal plasma exposures (AUC) at these doses were approximately 11, 70, and 470 times the exposure in humans at the MRDD. The high dose was maternally toxic, as evidenced by decreased maternal body weight gain during gestation.
A no-effect dose for developmental toxicity in rats exposed during organogenesis was not established. When naratriptan was administered orally (1, 5, or 30 mg/kg/day) to pregnant Dutch rabbits throughout organogenesis, the incidence of a specific fetal skeletal malformation (fused sternebrae) was increased at the high dose, the incidence of fetal variations (major blood vessel variations, supernumerary ribs, incomplete skel…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with use of naratriptan tablets in pregnant women. Data from a prospective pregnancy exposure registry and epidemiological studies of pregnant women have documented outcomes in women exposed to naratriptan during pregnancy; however, due to small sample sizes, no definitive conclusions can be drawn regarding the risk of birth defects following exposure to naratriptan [see Data] . In animal studies, naratriptan produced developmental toxicity (including embryolethality and fetal abnormalities) when administered to pregnant rats and rabbits.
The lowest doses producing evidence of developmental toxicity in animals were associated with plasma exposures 2.5 (rabbit) to 11 (rat) times that in humans at the maximum recommended daily dose (MRDD) [see Data] . In the U.S. general population, the estimated background risk of major birth defects and of miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. The reported rate of major birth defects among deliveries to women with migraine ranged from 2.2% to 2.9% and of miscarriage was 17%, which were similar to rates reported in women without migraine.
Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Several studies have suggested that women with migraine may be at increased risk of preeclampsia during pregnancy. Data Human Data : The numbers of exposed pregnancy outcomes accumulated during the Sumatriptan/Naratriptan/Treximet ® (sumatriptan and naproxen sodium) Pregnancy Registry, a population-based international prospective study that collected data from October 1997 to September 2012, and smaller observational studies, were insufficient to define a level of risk for naratriptan in pregnant women.
The Registry documented outcomes of 57 infants and fetuses exposed to naratriptan during pregnancy (52 exposed during the first trimester and 5 exposed during the second trimester). The occurrence of major birth defects (excluding fetal deaths and induced abortions without reported defects and all spontaneous pregnancy losses) during first-trimester exposure to naratriptan was 2.2% (1/46 [95% CI: 0.1% to 13%]) and during any trimester of exposure was 2% (1/51 [95% CI: 0.1% to 11.8%]). Seven infants were exposed to both naratriptan and sumatriptan in utero, and one of these infants with first-trimester exposure was born with a major birth defect (ventricular septal defect).
The sample size in this study had 80% power to detect at least a 3.8 to 4.6 fold increase in the rate of major malformations. In a study using data from the Swedish Medical Birth Register, women who used triptans or ergots during pregnancy were compared with women who did not. Of the 22 births with first-trimester exposure to naratriptan, one infant was born with a malformation (congenital deformity of the hand).
Animal Data : When naratriptan was administered to pregnant rats during the period of organogenesis at doses of 10, 60, or 340 mg/kg/day, there was a dose-related increase in embryonic death; incidences of fetal structural variations (incomplete/irregular ossification of skull bones, sternebrae, ribs) were increased at all doses. The maternal plasma exposures (AUC) at these doses were approximately 11, 70, and 470 times the exposure in humans at the MRDD. The high dose was maternally toxic, as evidenced by decreased maternal body weight gain during gestation.
A no-effect dose for developmental toxicity in rats exposed during organogenesis was not established. When naratriptan was administered orally (1, 5, or 30 mg/kg/day) to pregnant Dutch rabbits throughout organogenesis, the incidence of a specific fetal skeletal malformation (fused sternebrae) was increased at the high dose, the incidence of fetal variations (major blood vessel variations, supernumerary ribs, incomplete skeletal ossification) was increased at the mid and high doses, and embryonic death was increa…
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. Therefore, naratriptan tablets are not recommended for use in patients younger than 18 years of age. One controlled clinical trial evaluated naratriptan tablets (0.25 to 2.5 mg) in 300 adolescent migraineurs aged 12 to 17 years who received at least 1 dose of naratriptan tablets for an acute migraine.
In this study, 54% of the patients were female and 89% were Caucasian. There were no statistically significant differences between any of the treatment groups. The headache response rates at 4 hours (n) were 65% (n = 74), 67% (n = 78), and 64% (n = 70) for placebo, 1 mg, and 2.5 mg groups, respectively.
This trial did not establish the efficacy of naratriptan tablets compared with placebo in the treatment of migraine in adolescents. Adverse reactions observed in this clinical trial were similar in nature to those reported in clinical trials in adults.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of naratriptan tablets did not include sufficient numbers of patients aged 65 and older to determine whether they respond differently from younger patients. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy.
Naratriptan is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in elderly patients who have reduced renal function. In addition, elderly patients are more likely to have decreased hepatic function, they are at higher risk for CAD, and blood pressure increases may be more pronounced in the elderly. A cardiovascular evaluation is recommended for geriatric patients who have other cardiovascular risk factors (e.g., diabetes, hypertension, smoking, obesity, strong family history of CAD) prior to receiving naratriptan tablets [see Warnings and Precautions (5.1)].
🆘 Overdosage ▾
10 OVERDOSAGE Adverse reactions observed after overdoses of up to 25 mg included increases in blood pressure resulting in lightheadedness, neck tension, tiredness, and loss of coordination. Also, ischemic ECG changes likely due to coronary artery vasospasm have been reported. The elimination half-life of naratriptan is about 6 hours [see Clinical Pharmacology (12.3)] , therefore monitoring of patients after overdose with naratriptan tablets should continue for at least 24 hours or while symptoms or signs persist.
There is no specific antidote to naratriptan. It is unknown what effect hemodialysis or peritoneal dialysis has on the serum concentrations of naratriptan.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Naratriptan binds with high affinity to human cloned 5-HT 1B/1D receptors. Migraines are likely due to local cranial vasodilatation and/or to the release of sensory neuropeptides (including substance P and calcitonin gene-related peptide) through nerve endings in the trigeminal system. The therapeutic activity of naratriptan tablets for the treatment of migraine headache is thought to be due to the agonist effects at the 5-HT 1B/1D receptors on intracranial blood vessels (including the arterio-venous anastomoses) and sensory nerves of the trigeminal system, which result in cranial vessel constriction and inhibition of pro-inflammatory neuropeptide release.
12.2Pharmacodynamics In the anesthetized dog, naratriptan has been shown to reduce the carotid arterial blood flow with little or no effect on arterial blood pressure or total peripheral resistance. While the effect on blood flow was selective for the carotid arterial bed, increases in vascular resistance of up to 30% were seen in the coronary arterial bed. Naratriptan has also been shown to inhibit trigeminal nerve activity in rat and cat.
In 10 subjects with suspected CAD undergoing coronary artery catheterization, there was a 1% to 10% reduction in coronary artery diameter following subcutaneous injection of 1.5 mg of naratriptan [see Contraindications (4)] .
12.3Pharmacokinetics Absorption Naratriptan is well absorbed, with about 70% oral bioavailability. Following administration of a 2.5 mg tablet, the peak concentrations are obtained in 2 to 3 hours. After administration of 1 or 2.5 mg tablets, the C max is somewhat (about 50%) higher in women (not corrected for milligram-per-kilogram dose) than in men.
During a migraine attack, absorption is slower, with a T max of 3 to 4 hours. Food does not affect the pharmacokinetics of naratriptan. Naratriptan displays linear kinetics over the therapeutic dose range.
Distribution The steady-state volume of distribution of naratriptan is 170 L. Plasma protein binding is 28% to 31% over the concentration range of 50 to 1,000 ng/mL. Metabolism In vitro , naratriptan is metabolized by a wide range of cytochrome P450 isoenzymes into a number of inactive metabolites.
Elimination Naratriptan is predominantly eliminated in urine, with 50% of the dose recovered unchanged and 30% as metabolites in urine. The mean elimination half-life of naratriptan is 6 hours. The systemic clearance of naratriptan is 6.6 mL/min/kg.
The renal clearance (220 mL/min) exceeds glomerular filtration rate, indicating active tubular secretion. Repeat administration of naratriptan tablets does not result in drug accumulation. Special Populations Age: A small decrease in clearance (approximately 26%) was observed in healthy elderly subjects (65 to 77 years) compared with younger subjects, resulting in slightly higher exposure [see Use in Specific Populations (8.5)] .
Race: The effect of race on the pharmacokinetics of naratriptan has not been examined. Renal Impairment: Clearance of naratriptan was reduced by 50% in subjects with moderate renal impairment (creatinine clearance: 18 to 39 mL/min) compared with the normal group. Decrease in clearances resulted in an increase of mean half-life from 6 hours (healthy) to 11 hours (range: 7 to 20 hours).
The mean C max increased by approximately 40%. The effects of severe renal impairment (creatinine clearance:≤15 mL/min) on the pharmacokinetics of naratriptan have not been assessed [see Contraindications (4)] . Hepatic Impairment: Clearance of naratriptan was decreased by 30% in subjects with moderate hepatic impairment (Child-Pugh Grade A or B).
This resulted in an approximately 40% increase in the half-life (range: 8 to 16 hours). The effects of severe hepatic impairment (Child-Pugh Grade C) on the pharmacokinetics of naratriptan have not been assessed [see Contraindications (4)] . Drug Interaction Studies From population pharmacokinetic analyses, co-administration of…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Naratriptan binds with high affinity to human cloned 5-HT 1B/1D receptors. Migraines are likely due to local cranial vasodilatation and/or to the release of sensory neuropeptides (including substance P and calcitonin gene-related peptide) through nerve endings in the trigeminal system. The therapeutic activity of naratriptan tablets for the treatment of migraine headache is thought to be due to the agonist effects at the 5-HT 1B/1D receptors on intracranial blood vessels (including the arterio-venous anastomoses) and sensory nerves of the trigeminal system, which result in cranial vessel constriction and inhibition of pro-inflammatory neuropeptide release.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Naratriptan tablets, USP containing 1 mg and 2.5 mg of naratriptan (base) as the hydrochloride salt. Naratriptan Tablets USP, 1 mg, are white to off-white colored, capsule shaped, film-coated tablets debossed with “N” on one side and “1” on the other side are supplied as: Carton of 9 Unit-of-Use tablets each with cross perforation and individually labeled NDC 69452-340-72 Naratriptan Tablets USP, 2.5 mg, are green colored, capsule shaped, film-coated tablets debossed with “N” on one side and “2.5” on the other side are supplied as: Carton of 9 Unit-of-Use tablets each with cross perforation and individually labeled NDC 69452-341-72 Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Naratriptan tablets, USP contain naratriptan hydrochloride USP, a selective 5-HT 1B/1D receptor agonist. Naratriptan hydrochloride, USP is chemically designated as N-methyl-3-(1-methyl-4-piperidinyl)-1H-indole-5-ethanesulfonamide monohydrochloride, and it has the following structure: The empirical formula is C 17 H 25 N 3 O 2 S•HCl, representing a molecular weight of 371.93. Naratriptan hydrochloride, USP is a white to pale yellow powder that is sparingly soluble in water.
Each naratriptan tablet, USP for oral administration contains 1.11 or 2.78 mg of naratriptan hydrochloride USP, equivalent to 1 or 2.5 mg of naratriptan, respectively. Each tablet also contains the inactive ingredients croscarmellose sodium, anhydrous lactose, magnesium stearate, microcrystalline cellulose, opadry white (1 mg tablet) and opadry green (2.5 mg tablet). The components of opadry white are hypromellose, triacetin, and titanium dioxide.
The components of opadry green are hypromellose, triacetin, titanium dioxide, iron oxide yellow, and FD&C Blue No. 2. molecular structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Risk of Myocardial Ischemia and/or Infarction, Prinzmetal’s Angina, Other Vasospasm-Related Events, Arrhythmias, and Cerebrovascular Events Inform patients that naratriptan tablets may cause serious cardiovascular side effects such as myocardial infarction or stroke. Although serious cardiovascular events can occur without warning symptoms, patients should be alert for the signs and symptoms of chest pain, shortness of breath, irregular heartbeat, significant rise in blood pressure, weakness, and slurring of speech and should ask for medical advice if any indicative sign or symptoms are observed.
Apprise patients of the importance of this follow-up [see Warnings and Precautions (5.1, 5.2, 5.4, 5.5, 5.8)] . Anaphylactic Reactions Inform patients that anaphylactic reactions have occurred in patients receiving naratriptan tablets. Such reactions can be life threatening or fatal.
In general, anaphylactic reactions to drugs are more likely to occur in individuals with a history of sensitivity to multiple allergens [see Contraindications (4), Warnings and Precautions (5.9)] . Concomitant Use with Other Triptans or Ergot Medications Inform patients that use of naratriptan tablets within 24 hours of another triptan or an ergot-type medication (including dihydroergotamine or methysergide) is contraindicated [see Contraindications (4), Drug Interactions (7.1, 7.2)] . Serotonin Syndrome Caution patients about the risk of serotonin syndrome with the use of naratriptan tablets or other triptans, particularly during combined use with SSRIs, SNRIs, TCAs, and MAO inhibitors [see Warnings and Precautions (5.7), Drug Interactions (7.3)].
Medication Overuse Headache Inform patients that use of acute migraine drugs for 10 or more days per month may lead to an exacerbation of headache and encourage patients to record headache frequency and drug use (e.g., by keeping a headache diary) [see Warnings and Precautions (5.6)] . Pregnancy Advise patients to notify their healthcare provider if they become pregnant during treatment or intend to become pregnant [see Use in Specific Populations (8.1)]. Lactation Advise patients to notify their healthcare provider if they are breastfeeding or plan to breastfeed [see Use in Specific Populations (8.2)].
Ability to Perform Complex Tasks Treatment with naratriptan tablets may cause somnolence and dizziness; instruct patients to evaluate their ability to perform complex tasks after administration of naratriptan tablets.