
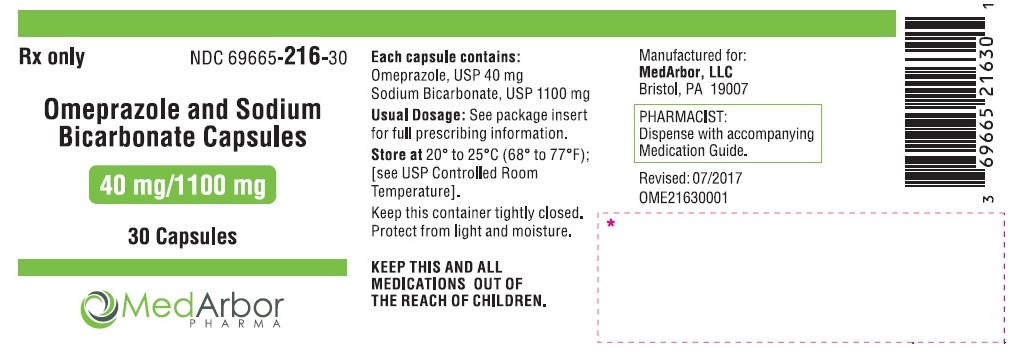
Omeprazole and Sodium Bicarbonate 40; 1100 mg; mg Capsule, 30-count
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Prescription omeprazole is used alone or with other medications to treat the symptoms of gastroesophageal reflux disease (GERD), a condition in which backward flow of acid from the stomach causes heartburn and possible injury of the esophagus (the tube between the throat and stomach) in adults and children 1 year of age and older. Prescription omeprazole is used to treat damage from GERD in adults and children 1 month of age and older. Prescription omeprazole is used to allow the esophagus to heal and prevent further damage to the esophagus in adults and children 1 year of age and older with G...
Read the full MedlinePlus article ↗- It's blocking the pump in your stomach lining that produces acid — pretty much turning it off at the source. Less acid means ulcers can heal, acid reflux symptoms ease up, and the...
- What exactly is this medication doing for my stomach?
- Yes, timing really does matter here. Take it at least 1 hour before your first meal of the day. If you take it with or after food, your body absorbs significantly less of it, so it...
- When should I take it, and does it matter if I eat first?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII 5138Q19F1X
Ammonia is a colorless gas made from nitrogen and hydrogen. It's used in medicines as a pH buffer to maintain the correct acidity level and help keep the product stable.
-
UNII 8PJ61P6TS3
Butyl alcohol is a clear liquid organic solvent derived from petroleum or natural sources. In medicines, it helps dissolve active ingredients and serves as a solvent in liquid formulations and some topical products.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII ND2M416302
Isopropyl alcohol is a clear liquid solvent derived from petroleum. In medicines, it dissolves active ingredients and other components, helps the product flow smoothly, and aids in sterilization during manufacturing.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
14 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Omeprazole and Sodium Bicarbonate 40 mg/1; 1100 mg 27241-0032-03 | Ajanta | 30 capsules | $0.562 | AB | Availability likely | — |
| omeprazole sodium bicarbonate 40 mg/1; 1100 mg 69097-0914-02 | Cipla | 30 capsules | $0.562 | AB | Availability likely | — |
| Omeprazole/Bicarbonate 40 mg/1; 1100 mg 69367-0196-30 | Westminster | 30 capsules | $0.562 | AB | Availability likely | — |
| Omeprazole and Sodium Bicarbonate 40 mg/1; 1100 mg 68682-0104-30 | Oceanside | 30 capsules | $0.643 | — | FDA listed | — |
| Omeprazole and Sodium Bicarbonate 40 mg/1; 1100 mg 50228-0364-05 | ScieGen | 500 capsules | — | AB | FDA listed | — |
| Omeprazole, Sodium bicarbonate 40 mg/1; 1100 mg 53041-0663-77 | Guardian | 30 capsules | — | AB | FDA listed | — |
| Zegerid 40 mg/1; 1100 mg 68012-0104-05 | Santarus, | 5 capsules | — | — | FDA listed | — |
| Omeprazole/Bicarbonate 40 mg/1; 1100 mg 71205-0985-30 | Proficient | 30 capsules | — | AB | FDA listed | — |
| Omeprazole/Sodiium Bicarbonate 40 mg/1; 1100 mg 72189-0568-30 | Direct_rx | 30 capsules | — | AB | FDA listed | — |
| Omeprazole and Sodium Bicarbonate 40 mg/1; 1100 mg 85509-1032-01 | PHOENIX | 15 capsules | — | AB | FDA listed | — |
| Omeprazole and Sodium Bicarbonate 40; 1100 mg/1; mgthis 69665-0216-30 | Medarbor | 30 capsules | — | AB | Discontinued | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 69665-0216-30 You're viewing this | 30 CAPSULE in 1 BOTTLE (69665-216-30) | 2017-07-01 | Inactivated by FDA |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Omeprazole and sodium bicarbonate capsules is a proton pump inhibitor indicated for: Short-term treatment of active duodenal ulcer (1.1) Short-term treatment of active benign gastric ulcer (1.2) Treatment of gastroesophageal reflux disease (GERD) (1.3) Maintenance of healing of erosive esophagitis (1.4) The safety and effectiveness of omeprazole and sodium bicarbonate capsules in pediatric patients (<18 years of age) have not been established. (8.4)
1.1Duodenal Ulcer Omeprazole and sodium bicarbonate capsules is indicated for short-term treatment of active duodenal ulcer. Most patients heal within four weeks. Some patients may require an additional four weeks of therapy. [ See Clinical Studies (14.1) ]
1.2Gastric Ulcer Omeprazole and sodium bicarbonate capsules is indicated for short-term treatment (4-8 weeks) of active benign gastric ulcer. [ See Clinical Studies (14.2) ]
1.3Treatment of Gastroesophageal Reflux Disease (GERD) Symptomatic GERD Omeprazole and sodium bicarbonate capsules is indicated for the treatment of heartburn and other symptoms associated with GERD for up to 4 weeks. [ See Clinical Studies (14.3) ] Erosive Esophagitis Omeprazole and sodium bicarbonate capsules is indicated for the short-term treatment (4-8 weeks) of erosive esophagitis which has been diagnosed by endoscopy. The efficacy of omeprazole and sodium bicarbonate capsules used for longer than 8 weeks in these patients has not been established.
If a patient does not respond to 8 weeks of treatment, it may be helpful to give up to an additional 4 weeks of treatment. If there is recurrence of erosive esophagitis or GERD symptoms (e.g., heartburn), additional 4-8 week courses of omeprazole and sodium bicarbonate capsules may be considered. [ See Clinical Studies (14.3) ]
1.4Maintenance of Healing of Erosive Esophagitis Omeprazole and sodium bicarbonate capsules is indicated to maintain healing of erosive esophagitis. Controlled studies do not extend beyond 12 months. [ See Clinical Studies (14.4) ]
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Omeprazole and sodium bicarbonate is available as a capsule in 20 mg and 40 mg strengths of omeprazole for adult use. Directions for use for each indication are summarized in Table 1. All recommended doses throughout the labeling are based upon omeprazole.
Since both the 20 mg and 40 mg capsules contain the same amount of sodium bicarbonate (1100 mg), two capsules of 20 mg are not equivalent to one capsule of omeprazole and sodium bicarbonate 40 mg; therefore, two 20 mg capsules of omeprazole and sodium bicarbonate should not be substituted for one capsule of omeprazole and sodium bicarbonate 40 mg. Omeprazole and sodium bicarbonate capsules should be taken on an empty stomach at least one hour before a meal. Table 1: Recommended Doses of Omeprazole and sodium bicarbonate by Indication for Adults 18 Years and Older Indication Recommended Dose Frequency Short-Term Treatment of Active Duodenal Ulcer 20 mg Once daily for 4 weeks *,+ Benign Gastric Ulcer 40 mg Once daily for 4-8 weeks **,+ Gastroesophageal Reflux Disease (GERD) Symptomatic GERD (with no esophageal erosions) 20 mg Once daily for up to 4 weeks * Erosive Esophagitis 20 mg Once daily for 4-8 weeks * Maintenance of Healing of Erosive Esophagitis 20 mg Once daily ** * Most patients heal within 4 weeks.
Some patients may require an additional 4 weeks of therapy. [See Clinical Studies (14.1)] ** Controlled studies do not extend beyond 12 months. [See Clinical Studies (14)] + For additional information, [See Indications and Usage (1)] Special Populations Hepatic Insufficiency Consider dose reduction, particularly for maintenance of healing of erosive esophagitis. [See Clinical Pharmacology (12.3)] Administration of Capsules Omeprazole and sodium bicarbonate capsules should be swallowed intact with water. DO NOT USE OTHER LIQUIDS.
DO NOT OPEN CAPSULE AND SPRINKLE CONTENTS INTO FOOD. Short-Term Treatment of Active Duodenal Ulcer: 20 mg once daily for 4 weeks (some patients may require an additional 4 weeks of therapy (14.1)) (2) Gastric Ulcer: 40 mg once daily for 4-8 weeks (2) Gastroesophageal Reflux Disease (GERD) (2) - Symptomatic GERD (with no esophageal erosions): 20 mg once daily for up to 4 weeks - Erosive Esophagitis: 20 mg once daily for 4-8 weeks • Maintenance of Healing of Erosive Esophagitis: 20 mg once daily* *studied for 12 months
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Omeprazole and Sodium Bicarbonate Capsules, 20 mg/1100 mg: each hard gelatin capsule has a light blue opaque cap and white opaque body, imprinted in black ink with 'U' on the cap, '88' on the body and contains 20 mg omeprazole, USP and 1100 mg sodium bicarbonate, USP. Omeprazole and Sodium Bicarbonate Capsules, 40 mg/1100 mg: each hard gelatin capsule has a dark blue opaque cap and white opaque body, imprinted in black ink with 'U' on the cap, '89' on the body and contains 40 mg omeprazole, USP and 1100 mg sodium bicarbonate, USP.
Omeprazole and sodium bicarbonate is available as a capsule in 20 mg and 40 mg strengths
⛔ Contraindications ▾
4 CONTRAINDICATIONS Omeprazole and sodium bicarbonate capsules is contraindicated in patients with known hypersensitivity to any components of the formulation. Hypersensitivity reactions may include anaphylaxis, anaphylactic shock, angioedema, bronchospasm, acute interstitial nephritis, and urticaria. [See Adverse Reactions (6)] Known hypersensitivity to any components of the formulation
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Concomitant Gastric Malignancy: Symptomatic response to therapy with omeprazole and sodium bicarbonate does not preclude the presence of gastric malignancy (5.1) Atrophic Gastritis: Has been observed in gastric corpus biopsies from patients treated long-term with omeprazole (5.2) Acute interstitial nephritis has been observed in patients taking PPIs. (5.3) Cyanocobalamin (vitamin B-12) Deficiency: Daily long-term use (e.g., longer than 3 years) may lead to malabsorption or a deficiency of cyanocobalamin.
(5.4) Buffer Content: contains sodium bicarbonate (5.5) PPI therapy may be associated with increased risk of Clostridium difficile associated diarrhea. (5.6) Avoid concomitant use of omeprazole and sodium bicarbonate with clopidogrel (5.7) Bone Fracture: Long-term and multiple daily dose PPI therapy may be associated with an increased risk for osteoporosis-related fractures of the hip, wrist, or spine. (5.8) Hypomagnesemia has been reported rarely with prolonged treatment with PPIs (5.9) Avoid concomitant use of omeprazole and sodium bicarbonate with St John's Wort or rifampin due to the potential reduction in omeprazole concentrations (5.10, 7.2) Interactions with diagnostic investigations for Neuroendocrine Tumors: Increases in intragastric pH may result in hypergastrinemia and enterochromaffin-like cell hyperplasia and increased Choromogranin A levels which may interfere with diagnostic investigations for neuroendocrine tumors.
(5.11, 12.2)
5.1Concomitant Gastric Malignancy Symptomatic response to therapy with omeprazole does not preclude the presence of gastric malignancy.
5.2Atrophic gastritis Atrophic gastritis has been noted occasionally in gastric corpus biopsies from patients treated long-term with omeprazole.
5.3Acute Interstitial Nephritis Acute interstitial nephritis has been observed in patients taking PPIs including omeprazole and sodium bicarbonate. Acute interstitial nephritis may occur at any point during PPI therapy and is generally attributed to an idiopathic hypersensitivity reaction. Discontinue omeprazole and sodium bicarbonate if acute interstitial nephritis develops. [See Contraindications (4)].
5.4Cyanocobalamin (vitamin B-12) Deficiency Daily treatment with any acid-suppressing medications over a long period of time (e.g., longer than 3 years) may lead to malabsorption of cyanocobalamin (vitamin B-12) caused by hypo- or achlorhydria. Rare reports of cyanocobalamin deficiency occurring with acid-suppressing therapy have been reported in the literature. This diagnosis should be considered if clinical symptoms consistent with cyanocobalamin deficiency are observed.
5.5Buffer Content Each omeprazole and sodium bicarbonate capsule contains 1100 mg (13 mEq) of sodium bicarbonate. The total content of sodium in each capsule is 304 mg. The sodium content of omeprazole and sodium bicarbonate capsules should be taken into consideration when administering to patients on a sodium restricted diet.
Because omeprazole and sodium bicarbonate capsules contain sodium bicarbonate, they should be used with caution in patients with Bartter's syndrome, hypokalemia, hypocalcemia, and problems with acid-base balance. Long-term administration of bicarbonate with calcium or milk can cause milk-alkali syndrome. Chronic use of sodium bicarbonate may lead to systemic alkalosis and increased sodium intake can produce edema and weight increase.
5.6Clostridium difficile Associated Diarrhea Published observational studies suggest that PPI therapy like omeprazole and sodium bicarbonate may be associated with an increased risk of Clostridium difficile associated diarrhea, especially in hospitalized patients. This diagnosis should be considered for diarrhea that does not improve. [See Adverse Reactions (6.2)] Patients should use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated.
5.7 Interaction with Clopidogrel Avoid concomitant use of omeprazole and sodium b…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (incidence ≥ 2%) are: Headache, abdominal pain, nausea, diarrhea, vomiting, and flatulence To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. In the U.S. clinical trial population of 465 patients, the adverse reactions summarized in Table 2 were reported to occur in 1% or more of patients on therapy with omeprazole. Numbers in parentheses indicate percentages of the adverse reactions considered by investigators as possibly, probably or definitely related to the drug.
Table 2: Adverse Reactions Occurring In 1% or More of Patients on Omeprazole Therapy Omeprazole (n = 465) Placebo (n = 64) Ranitidine (n = 195) Headache 6.9 (2.4) 6.3 7.7 (2.6) Diarrhea 3.0 (1.9) 3.1 (1.6) 2.1 (0.5) Abdominal Pain 2.4 (0.4) 3.1
2.1Nausea 2.2 (0.9) 3.1 4.1 (0.5) URI 1.9 1.6
2.6Dizziness 1.5 (0.6) 0.0 2.6 (1.0) Vomiting 1.5 (0.4) 4.7 1.5 (0.5) Rash 1.5 (1.1) 0.0
0.0Constipation 1.1 (0.9) 0.0
0.0Cough 1.1 0.0
1.5Asthenia 1.1 (0.2) 1.6 (1.6) 1.5 (1.0) Back Pain 1.1 0.0
0.5Table 3 summarizes the adverse reactions that occurred in 1% or more of omeprazole-treated patients from international double-blind, and open-label clinical trials in which 2,631 patients and subjects received omeprazole. Table 3: Incidence of Adverse Reactions > 1% Causal Relationship not Assessed Omeprazole (n = 2631) Placebo (n = 120) Body as a Whole, site unspecified Abdominal pain 5.2
3.3Asthenia 1.3
0.8Digestive System Constipation 1.5
0.8Diarrhea 3.7
2.5Flatulence 2.7
5.8Nausea 4.0
6.7Vomiting 3.2
10.0Acid regurgitation 1.9
3.3Nervous System/Psychiatric Headache 2.9 2.5
6.2Postmarketing Experience The following adverse reactions have been identified during post-approval use of omeprazole. Because these reactions are voluntarily reported from a population of uncertain size, it is not always possible to reliably estimate their actual frequency or establish a causal relationship to drug exposure. Body as a Whole: Hypersensitivity reactions, including anaphylaxis, anaphylactic shock, angioedema, bronchospasm, interstitial nephritis, urticaria (see also Skin below), fever, pain, fatigue, malaise.
Cardiovascular: Chest pain or angina, tachycardia, bradycardia, palpitation, elevated blood pressure, and peripheral edema. Gastrointestinal: Pancreatitis (some fatal), anorexia, irritable colon, flatulence, fecal discoloration, esophagealcandidiasis, mucosal atrophy of the tongue, dry mouth, stomatitis and abdominal swelling. During treatment with omeprazole, astric fundic gland polyps have been noted rarely.
These polyps are benign and appear to be reversible when treatment is discontinued. Gastroduodenal carcinoids have been reported in patients with Zollinger- Ellison syndrome on long-term treatment with omeprazole. This finding is believed to be a manifestation of the underlying condition, which is known to be associated with such tumors.
Hepatic: Mild and, rarely, marked elevations of liver function tests [ALT (SGPT), AST (SGOT), γ-glutamyl transpeptidase, alkaline phosphatase, and bilirubin (jaundice)]. In rare instances, overt liver disease has occurred, including hepatocellular, cholestatic, or mixed hepatitis, liver necrosis (some fatal), hepatic failure (some fatal), and hepatic encephalopathy. Infections and Infestations: Clostridium difficile associated diarrhea.
Metabolism and Nutritional Disorders: Hyponatremia, hypoglycemia, hypomagnesemia, and weight gain. Musculoskeletal: Muscle cramps, myalgia, muscle weakness, joint pain, bone fracture, and leg pain. Nervous System/Psychiatric: Psychic disturbances including depression…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS May interfere with drugs for which gastric pH can affect bioavailability (e.g., ketoconazole, ampicillin esters, iron salts, erlotinib, digoxin, and mycophenolate mofetil) (7.1) Drugs metabolized by cytochrome P450 (e.g., diazepam, warfarin, phenytoin, cyclosporine, disulfiram, benzodiazepines): Omeprazole and sodium bicarbonate can prolong their elimination. Monitor to determine the need for possible dose adjustments when taken with omeprazole and sodium bicarbonate capsules (7.2) Patients treated with proton pump inhibitors and warfarin concomitantly may need to be monitored for increases in INR and prothrombin time (7.2) Voriconazole: May increase plasma levels of omeprazole (7.2) Saquinavir: Omeprazole and sodium bicarbonate increases plasma levels of saquinavir (7.3) Omeprazole and sodium bicarbonate may reduce plasma levels of atazanavir and nelfinavir (7.3) Clopidogrel: Omeprazole and sodium bicarbonate decreases exposure to the active metabolite of clopidogrel (7.5) Tacrolimus: Omeprazole and sodium bicarbonate may increase serum levels of tacrolimus (7.6) Methotrexate: Omeprazole and sodium bicarbonate may increase serum level of methotrexate (7.8)
7.1Drugs for Which Gastric pH Can Affect Bioavailability Due to its effects on gastric acid secretion, omeprazole can reduce the absorption of drugs where gastric pH is an important determinant of their bioavailability. Like with other drugs that decrease the intragastric acidity, the absorption of drugs such as ketoconazole, atazanavir, iron salts, erlotinib, and mycophenolate mofetil (MMF) can decrease, while the absorption of drugs such as digoxin can increase during treatment with omeprazole. Concomitant treatment with omeprazole (20 mg daily) and digoxin in healthy subjects increased the bioavailability of digoxin by 10% (30% in two subjects).
Co-administration of digoxin with omeprazole and sodium bicarbonate is expected to increase the systemic exposure of digoxin. Therefore, patients may need to be monitored when digoxin is taken concomitantly with omeprazole and sodium bicarbonate. Co-administration of omeprazole in healthy subjects and in transplant patients receiving MMF has been reported to reduce the exposure to the active metabolite, mycophenolic acid (MPA), possibly due to a decrease in MMF solubility at an increased gastric pH.
The clinical relevance of reduced MPA exposure on organ rejection has not been established in transplant patients receiving omeprazole and sodium bicarbonate and MMF. Use omeprazole and sodium bicarbonate with caution in transplant patients receiving MMF. [See Clinical Pharmacology (12.3)]
7.2Drugs Metabolized by Cytochrome P450 (CYP) Omeprazole can prolong the elimination of diazepam, warfarin and phenytoin, drugs that are metabolized by oxidation in the liver. There have been reports of increased INR and prothrombin time in patients receiving proton pump inhibitors, including omeprazole, and warfarin concomitantly. Increases in INR and prothrombin time may lead to abnormal bleeding and even death.
Patients treated with proton pump inhibitors and warfarin may need to be monitored for increases in INR and prothrombin time. Although in normal subjects no interaction with theophylline or propranolol was found, there have been clinical reports of interaction with other drugs metabolized via the cytochrome P-450 system (e.g., cyclosporine, disulfiram, benzodiazepines). Patients should be monitored to determine if it is necessary to adjust the dosage of these drugs when taken concomitantly with omeprazole and sodium bicarbonate.
Concomitant administration of omeprazole and voriconazole (a combined inhibitor of CYP2C19 and CYP3A4) resulted in more than doubling of the omeprazole exposure. Dose adjustment of omeprazole is not normally required. When voriconazole (400 mg every 12 hours for one day, then 200 mg for 6 days) was given with omeprazole (40 mg once daily for 7 days) to healthy subjects, it significantly increa…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based upon animal data, may cause fetal harm (8.1) The safety and effectiveness of omeprazole and sodium bicarbonate in pediatric patients less than 18 years of age have not been established. (8.4) Hepatic Impairment: Consider dose reduction, particularly for maintenance of healing of erosive esophagitis (12.3)
8.1Pregnancy Pregnancy Category C Risk Summary There are no adequate and well-controlled studies on the use of omeprazole and sodium bicarbonate in pregnant women. Available epidemiologic data fail to demonstrate an increased risk of major congenital malformations or other adverse pregnancy outcomes with first trimester omeprazole use. Teratogenicity was not observed in animal reproduction studies with administration of oral esomeprazole magnesium in rats and rabbits with doses about68 times and 42 times, respectively, an oral human dose of 40 mg (based on a body surface area basis for a 60 kg person).
However, changes in bone morphology were observed in offspring of rats dosed through most of pregnancy and lactation at doses equal to or greater than approximately 33.6 times an oral human dose of 40 mg ( see Animal Data ). Because of the observed effect at high doses of esomeprazole magnesium on developing bone in rat studies, omeprazole and sodium bicarbonate should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Human Data Four published epidemiological studies compared the frequency of congenital abnormalities among infants born to women who used omeprazole during pregnancy with the frequency of abnormalities among infants of women exposed to H 2 -receptor antagonists or other controls.
A population-based retrospective cohort epidemiological study from the Swedish Medical Birth Registry, covering approximately 99% of pregnancies, from 1995-99, reported on 955 infants (824 exposed during the first trimester with 39 of these exposed beyond first trimester, and 131 exposed after the first trimester) whose mothers used omeprazole during pregnancy. The number of infants exposed in utero to omeprazole that had any malformation, low birth weight, low Apgar score, or hospitalization was similar to the number observed in this population.
The number of infants born with ventricular septal defects and the number of stillborn infants was slightly higher in the omeprazole-exposed infants than the expected number in this population. A population-based retrospective cohort study covering all live births in Denmark from 1996-2009, reported on 1,800 live births whose mothers used omeprazole during the first trimester of pregnancy and 837, 317 live births whose mothers did not use any proton pump inhibitor. The overall rate of birth defects in infants born to mothers with first trimester exposure to omeprazole was 2.9% and 2.6% in infants born to mothers not exposed to any proton pump inhibitor during the first trimester.
A retrospective cohort study reported on 689 pregnant women exposed to either H 2 -blockers or omeprazole in the first trimester (134 exposed to omeprazole) and 1,572 pregnant women unexposed to either during the first trimester. The overall malformation rate in offspring born to mothers with first trimester exposure to omeprazole, an H 2 -blocker, or were unexposed was 3.6%, 5.5%, and 4.1% respectively. A small prospective observational cohort study followed 113 women exposed to omeprazole during pregnancy (89% first trimester exposures).
The reported rate of major congenital malformations was 4% in the omeprazole group, 2% in controls exposed to non-teratogens, and 2.8% in disease-paired controls. Rates of spontaneous and elective abortions, preterm deliveries, gestational age at delivery, and mean birth weight were similar among the groups. Several studies have reported no apparent adverse short-term effects on the infant when single dose oral or intravenous omeprazole was administered to over 200 pregnant women as premedic…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Category C Risk Summary There are no adequate and well-controlled studies on the use of omeprazole and sodium bicarbonate in pregnant women. Available epidemiologic data fail to demonstrate an increased risk of major congenital malformations or other adverse pregnancy outcomes with first trimester omeprazole use. Teratogenicity was not observed in animal reproduction studies with administration of oral esomeprazole magnesium in rats and rabbits with doses about68 times and 42 times, respectively, an oral human dose of 40 mg (based on a body surface area basis for a 60 kg person).
However, changes in bone morphology were observed in offspring of rats dosed through most of pregnancy and lactation at doses equal to or greater than approximately 33.6 times an oral human dose of 40 mg ( see Animal Data ). Because of the observed effect at high doses of esomeprazole magnesium on developing bone in rat studies, omeprazole and sodium bicarbonate should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Human Data Four published epidemiological studies compared the frequency of congenital abnormalities among infants born to women who used omeprazole during pregnancy with the frequency of abnormalities among infants of women exposed to H 2 -receptor antagonists or other controls.
A population-based retrospective cohort epidemiological study from the Swedish Medical Birth Registry, covering approximately 99% of pregnancies, from 1995-99, reported on 955 infants (824 exposed during the first trimester with 39 of these exposed beyond first trimester, and 131 exposed after the first trimester) whose mothers used omeprazole during pregnancy. The number of infants exposed in utero to omeprazole that had any malformation, low birth weight, low Apgar score, or hospitalization was similar to the number observed in this population.
The number of infants born with ventricular septal defects and the number of stillborn infants was slightly higher in the omeprazole-exposed infants than the expected number in this population. A population-based retrospective cohort study covering all live births in Denmark from 1996-2009, reported on 1,800 live births whose mothers used omeprazole during the first trimester of pregnancy and 837, 317 live births whose mothers did not use any proton pump inhibitor. The overall rate of birth defects in infants born to mothers with first trimester exposure to omeprazole was 2.9% and 2.6% in infants born to mothers not exposed to any proton pump inhibitor during the first trimester.
A retrospective cohort study reported on 689 pregnant women exposed to either H 2 -blockers or omeprazole in the first trimester (134 exposed to omeprazole) and 1,572 pregnant women unexposed to either during the first trimester. The overall malformation rate in offspring born to mothers with first trimester exposure to omeprazole, an H 2 -blocker, or were unexposed was 3.6%, 5.5%, and 4.1% respectively. A small prospective observational cohort study followed 113 women exposed to omeprazole during pregnancy (89% first trimester exposures).
The reported rate of major congenital malformations was 4% in the omeprazole group, 2% in controls exposed to non-teratogens, and 2.8% in disease-paired controls. Rates of spontaneous and elective abortions, preterm deliveries, gestational age at delivery, and mean birth weight were similar among the groups. Several studies have reported no apparent adverse short-term effects on the infant when single dose oral or intravenous omeprazole was administered to over 200 pregnant women as premedication for cesarean section under general anesthesia.
Animal Data Reproductive studies conducted with omeprazole in rats at oral doses up to 138 mg/kg/day (about 33.6 times an oral human dose of 40 mg on a body surface area basis) and in rabbits at doses up to 69 mg/kg/day (about 33.6times an oral human dose of 40 mg on a body surface area basis) did no…
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of omeprazole and sodium bicarbonate have not been established in pediatric patients less than 18 years of age. Juvenile Animal Data In a juvenile rat toxicity study, esomeprazole was administered with both magnesium and strontium salts at oral doses about 34 to 68 times a daily human dose of 40 mg on a body surface area basis. Increases in death were seen at the high dose, and at all doses of esomeprazole, there were decreases in body weight, body weight gain, femur weight and femur length, and decreases in overall growth. [ See Nonclinical Toxicology (13.2) ]
🧓 Geriatric Use ▾
8.5Geriatric Use Omeprazole was administered to over 2000 elderly individuals (≥ 65 years of age) in clinical trials in the U.S. and Europe. There were no differences in safety and effectiveness between the elderly and younger subjects. Other reported clinical experience has not identified differences in response between the elderly and younger subjects, but greater sensitivity of some older individuals cannot be ruled out.
Pharmacokinetic studies with buffered omeprazole have shown the elimination rate was somewhat decreased in the elderly and bioavailability was increased. The plasma clearance of omeprazole was 250 mL/min (about half that of young subjects). The plasma half-life averaged one hour, about twice that in nonelderly, healthy subjects taking omeprazole and sodium bicarbonate.
However, no dosage adjustment is necessary in the elderly. [ See Clinical Pharmacology (12.3) ]
🆘 Overdosage ▾
10 OVERDOSAGE Reports have been received of overdosage with omeprazole in humans. Doses ranged up to 2400 mg (120 times the usual recommended clinical dose). Manifestations were variable, but included confusion, drowsiness, blurred vision, tachycardia, nausea, vomiting, diaphoresis, flushing, headache, dry mouth, and other adverse reactions similar to those seen in normal clinical experience [See Adverse Reactions (6)].
Symptoms were transient, and no serious clinical outcome has been reported when omeprazole was taken alone. No specific antidote for omeprazole overdosage is known. Omeprazole is extensively protein bound and is, therefore, not readily dialyzable.
In the event of overdosage, treatment should be symptomatic and supportive. As with the management of any overdose, the possibility of multiple drug ingestion should be considered. For current information on treatment of any drug overdose, a certified Regional Poison Control Center should be contacted.
Telephone numbers are listed in the Physicians' Desk Reference (PDR) or local telephone book. Single oral doses of omeprazole at 1350, 1339, and 1200 mg/kg were lethal to mice, rats, and dogs, respectively. Animals given these doses showed sedation, ptosis, tremors, convulsions, and decreased activity, body temperature, and respiratory rate and increased depth of respiration.
In addition, a sodium bicarbonate overdose may cause hypocalcemia, hypokalemia, hypernatremia, and seizures.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Omeprazole belongs to a class of antisecretory compounds, the substituted benzimidazoles, that do not exhibit anticholinergic or H 2 histamine antagonistic properties, but that suppress gastric acid secretion by specific inhibition of the H + /K + ATPase enzyme system at the secretory surface of the gastric parietal cell. Because this enzyme system is regarded as the acid (proton) pump within the gastric mucosa, omeprazole has been characterized as a gastric acid-pump inhibitor, in that it blocks the final step of acid production.
This effect is dose related and leads to inhibition of both basal and stimulated acid secretion irrespective of the stimulus. Animal studies indicate that after rapid disappearance from plasma, omeprazole can be found within the gastric mucosa for a day or more. Omeprazole is acid labile and thus rapidly degraded by gastric acid.
Omeprazole and sodium bicarbonate capsules is an immediate-release formulations that contain sodium bicarbonate which raises the gastric pH and thus protects omeprazole from acid degradation.
12.2Pharmacodynamics Enterochromaffin-like (ECL) Cell Effects In 24-month carcinogenicity studies in rats, a dose-related significant increase in gastric carcinoid tumors and ECL cell hyperplasia was observed in both male and female animals [See Nonclinical Toxicology (13.1)] . Carcinoid tumors have also been observed in rats subjected to fundectomy or long-term treatment with other proton pump inhibitors or high doses of H2-receptor antagonists. Human gastric biopsy specimens have been obtained from more than 3000 patients treated with omeprazole in long-term clinical trials.
The incidence of ECL cell hyperplasia in these studies increased with time; however, no case of ECL cell carcinoids, dysplasia, or neoplasia has been found in these patients. These studies are of insufficient durationand size torule out the possible influence of long-term administration of omeprazole on the development of any premalignant or malignant conditions. Serum Gastrin Effects In studies involving more than 200 patients, serum gastrin levels increased during the first 1 to 2 weeks of once-daily administration of therapeutic doses of omeprazole in parallel with inhibition of acid secretion.
No further increase in serum gastrin occurred with continued treatment. In comparison with histamine H2-receptor antagonists, the median increases produced by 20 mg doses of omeprazole were higher (1.3 to 3.6 fold vs. 1.1 to 1.8 fold increase).
Gastrin values returned to pretreatment levels, usually within 1 to 2 weeks after discontinuation of therapy. Increased gastrin causes enterochromaffin-like cell hyperplasia and increased serum Chromogranin A (CgA) levels. The increased CgA levels may cause false positive results in diagnostic investigations for neuroendocrine tumors.
Other Effects Systemic effects of omeprazole in the CNS, cardiovascular and respiratory systems have not been found to date. Omeprazole, given in oral doses of 30 or 40 mg for 2 to 4 weeks, had no effect on thyroid function, carbohydrate metabolism, or circulating levels of parathyroid hormone, cortisol, estradiol, testosterone, prolactin, cholecystokinin or secretin. No effect on gastric emptying of the solid and liquid components of a test meal was demonstrated after a single dose of omeprazole 90 mg.
In healthy subjects, a single I.V. dose of omeprazole (0.35 mg/kg) had no effect on intrinsic factor secretion. No systematic dose-dependent effect has been observed on basal or stimulated pepsin output in humans. However, when intragastric pH is maintained at 4.0 or above, basal pepsin output is low, and pepsin activity is decreased.
As do other agents that elevate intragastric pH, omeprazole administered for 14 days in healthy subjects produced a significant increase in the intragastric concentrations of viable bacteria. The pattern of the bacterial species was unchanged from that commonly found in…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Omeprazole belongs to a class of antisecretory compounds, the substituted benzimidazoles, that do not exhibit anticholinergic or H 2 histamine antagonistic properties, but that suppress gastric acid secretion by specific inhibition of the H + /K + ATPase enzyme system at the secretory surface of the gastric parietal cell. Because this enzyme system is regarded as the acid (proton) pump within the gastric mucosa, omeprazole has been characterized as a gastric acid-pump inhibitor, in that it blocks the final step of acid production.
This effect is dose related and leads to inhibition of both basal and stimulated acid secretion irrespective of the stimulus. Animal studies indicate that after rapid disappearance from plasma, omeprazole can be found within the gastric mucosa for a day or more. Omeprazole is acid labile and thus rapidly degraded by gastric acid.
Omeprazole and sodium bicarbonate capsules is an immediate-release formulations that contain sodium bicarbonate which raises the gastric pH and thus protects omeprazole from acid degradation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Omeprazole and Sodium Bicarbonate Capsules, 20 mg/1100 mg are hard gelatin capsules with a light blue opaque cap and white opaque body, imprinted in black ink with 'U' on the cap, '88' on the body and filled with white to off-white powder. Bottles of 30 NDC 69665-215-30 Omeprazole and Sodium Bicarbonate Capsules, 40 mg/1100 mg are hard gelatin capsules with a dark blue opaque cap and white opaque body, imprinted in black ink with 'U' on the cap, '89' on the body and filled with white to off-white powder.
Bottles of 30 NDC 69665-216-30 Storage Store at 20° to 25°C (68° to 77°F); [See USP Controlled Room Temperature]. Keep this medication out of the hands of children. Keep container tightly closed.
Protect from light and moisture.
📋 Description ▾
11 DESCRIPTION Omeprazole and sodium bicarbonate capsules is a combination of omeprazole, a proton-pump inhibitor, and sodium bicarbonate, an antacid. Omeprazole is a substituted benzimidazole, 5-methoxy-2-[[(4-methoxy-3,5- dimethyl-2-pyridinyl)methyl]sulfinyl]-1 H- benzimidazole, a racemic mixture of two enantiomers that inhibits gastric acid secretion. Its molecular formula is C 17 H 19 N 3 O 3 S, with a molecular weight of 345.42.
The structural formula is: Omeprazole is a white to off-white crystalline powder which melts with decomposition at about 155°C. It is a weak base, freely soluble in ethanol and methanol, and slightly soluble in acetone and isopropanol and very slightly soluble in water. The stability of omeprazole is a function of pH; it is rapidly degraded in acid media, but has acceptable stability under alkaline conditions.
Omeprazole and sodium bicarbonate is supplied as immediate-release capsules. Each capsule contains either 40 mg or 20 mg of omeprazole and 1100 mg of sodium bicarbonate with the following excipients: croscarmellose sodium and magnesium stearate. The capsule shell contains gelatin, titanium dioxide, sodium lauryl sulfate, NF and the colorants FD&C Blue #1 (40 mg and 20 mg), FD&C Red# 3 (20 mg) and the components of ink, Edible ink type TekPrintTM SW-9008 Black Ink (Shellac, NF; Dehydrated Alcohol, USP; Isopropyl Alcohol, USP; Butyl Alcohol, NF; Propylene Glycol, USP; Strong Ammonia Solution, NF; Black Iron Oxide, NF, E172; Potassium Hydroxide, NF) or Opacode ® Monogramming ink S-1-17823 Black (Shellac, NF; Isopropyl Alcohol, USP; Iron Oxide Black, NF; N-Butyl Alcohol, NF; Propylene Glycol, USP; Ammonium Hydroxide, NF).
Descrp-1
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-Approved Medication Guide. Instruct patients that omeprazole and sodium bicarbonate capsules should be taken on an empty stomach at least one hour prior to a meal. [See Dosage and Administration (2)] Instruct patients in Directions for Use as follows: Capsules: Swallow intact capsule with water. DO NOT USE OTHER LIQUIDS.
DO NOT OPEN CAPSULE AND SPRINKLE CONTENTS INTO FOOD. Omeprazole and sodium bicarbonate is available either as 40 mg or 20 mg capsules with 1100 mg sodium bicarbonate. Patients should be instructed not to substitute omeprazole and sodium bicarbonate capsules for other omeprazole and sodium bicarbonate dosage forms because different dosage forms contain different amounts of sodium bicarbonate and magnesium hydroxide. [See Dosage and Administration (2)] Patients should be advised that since both the 20 mg and 40 mg capsules contain the same amount of sodium bicarbonate (1100 mg), two capsules of 20 mg are not equivalent to one capsule of omeprazole and sodium bicarbonate 40 mg; therefore, two 20 mg capsules of omeprazole and sodium bicarbonate should not be substituted for one capsule of omeprazole and sodium bicarbonate 40 mg. [See Dosage and Administration (2)] Patients should be advised that this drug is not approved for use in patients less than 18 years of age. [See Pediatric Use (8.4)] Patients on a sodium-restricted diet or patients at risk of developing congestive heart failure (CHF) should be informed of the sodium content of omeprazole and sodium bicarbonate capsules (304 mg per capsule).
Patients should be informed that chronic use of sodium bicarbonate may cause problems and increased sodium intake can cause swelling and weight gain. If this occurs, they should contact their healthcare provider. [See Warnings and Precautions (5.5)] Patients should be informed that the most frequent adverse reactions associated with omeprazole and sodium bicarbonate capsules include headache, abdominal pain, nausea, diarrhea, vomiting and flatulence. [See Adverse Reactions (6)] Pregnant women should be advised that a harmful effect of omeprazole and sodium bicarbonate on the fetus can not be ruled out and that the drug should be used with caution during pregnancy. [See Pregnancy (8.1)] Patients should be advised to use this drug with caution if they are regularly taking calcium supplements. [See Warnings and Precautions (5.3)] Advise patients to immediately report and seek care for diarrhea that does not improve.
This may be a sign of Clostridium difficile associated diarrhea. [See Warnings and Precautions (5.6)] Advise patients to immediately report and seek care for any cardiovascular or neurological symptoms including palpitations, dizziness, seizures and tetany as these may be signs of hypomagnesemia. [See Warnings and Precautions (5.9)] Manufactured for: MedArbor, LLC Bristol, PA 19007 Revised: 07/2017
💬 Medication Guide ▾
MEDICATION GUIDE Omeprazole and Sodium Bicarbonate Capsules (oh mep' ra zole and soe' dee um bye kar' bo nate) Read this Medication Guide before you start taking omeprazole and sodium bicarbonate capsules and each time you get a refill. There may be new information. This information does not take the place of talking to your doctor about your medical condition or treatment.
What is the most important information I should know about omeprazole and sodium bicarbonate capsules? Omeprazole and sodium bicarbonate capsules may help with your acid-related symptoms, but you could still have serious stomach problems. Talk with your doctor.
Omeprazole and sodium bicarbonate capsules can cause serious side effects, including: • Omeprazole and sodium bicarbonate capsules contains sodium bicarbonate. Tell your doctor if you are on a sodium restricted diet or if you have Bartter's Syndrome (a rare kidney disorder). Tell your doctor right away if you have confusion, shaking hands, dizziness, muscle twitching, nausea, vomiting, and numbness or tingling in the face, arms, or legs. • Diarrhea.
Omeprazole and sodium bicarbonate capsules may increase your risk of getting severe diarrhea. This diarrhea may be caused by an infection ( Clostridium difficile ) in your intestines. Call your doctor right away if you have watery stool, stomach pain, and fever that does not go away. • Bone fractures.
People who take multiple daily doses of proton pump inhibitor medicines for a long period of time (a year or longer) may have an increased risk of fractures of the hip, wrist or spine. You should take omeprazole and sodium bicarbonate capsules exactly as prescribed, at the lowest dose possible for your treatment and for the shortest time needed. Talk to your doctor about your risk of bone fracture if you take omeprazole and sodium bicarbonate capsules.
Omeprazole and sodium bicarbonate capsules can have other serious side effects. See “What are the possible side effects of omeprazole and sodium bicarbonate capsules?" What is omeprazole and sodium bicarbonate capsule? Omeprazole and sodium bicarbonate capsule is a prescription medicine called a proton pump inhibitor (PPI).
Omeprazole and sodium bicarbonate capsule reduces the amount of acid in your stomach. Omeprazole and sodium bicarbonate capsule is used in adults: for 4 weeks to heal ulcers in the first part of the small bowel (duodenal ulcers). Your doctor may prescribe another 4 weeks of omeprazole and sodium bicarbonate capsules. for up to 8 weeks for healing stomach ulcers. for up to 4 weeks to treat heartburn and other symptoms that happen with gastro-esophageal reflux disease (GERD).
GERD happens when acid from the stomach backs up into the tube (esophagus) that connects your mouth to your stomach. This may cause a burning feeling in your chest or throat, sour taste, or burping. for up to 8 weeks to heal acid-related damage to the lining of the esophagus (called erosive esophagitis or EE). to maintain healing of the esophagus. It is not known if omeprazole and sodium bicarbonate capsule is safe and effective if used longer than 12 months (1 year).
It is not known if omeprazole and sodium bicarbonate capsule is safe and effective in children less than 18 years of age. Who should not take omeprazole and sodium bicarbonate capsules? Do not take omeprazole and sodium bicarbonate capsules if you: • are allergic to omeprazole or any of the other ingredients in omeprazole and sodium bicarbonate capsules.
See the end of this Medication Guide for a complete list of ingredients in omeprazole and sodium bicarbonate capsules. • are allergic to any other proton pump inhibitor (PPI) medicine. What should I tell my doctor before I take omeprazole and sodium bicarbonate capsules? Before you take omeprazole and sodium bicarbonate capsules, tell your doctor if you: • have been told that you have low magnesium, calcium, or potassium levels in your blood • have liver problems • have heart failure • have Bartter's syndro…