
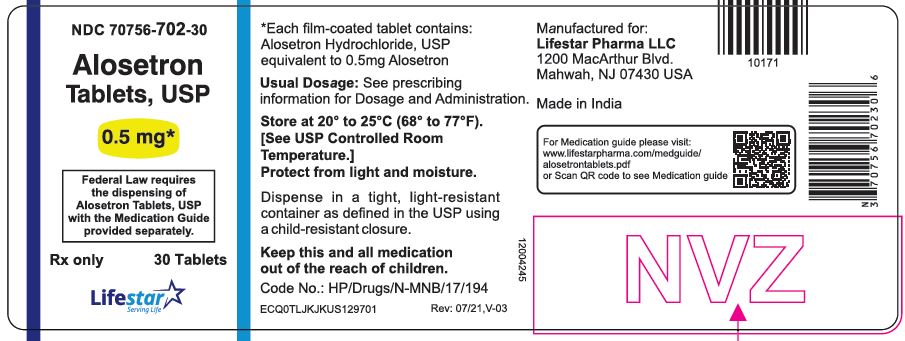
Alosetron .5 mg Tablet, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Serotonin-3 Receptor Antagonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Alosetron is used to treat diarrhea, pain, cramps, and the feeling of an urgent need to have bowel movements caused by irritable bowel syndrome (IBS; a condition that causes stomach pain, bloating, constipation, and diarrhea) in women who have diarrhea as their main symptom and have not been helped by other treatments. Alosetron is in a class of medications called 5-HT3 receptor antagonists. Alosetron works by slowing the movement of stool (bowel movements) through the intestines.
Read the full MedlinePlus article ↗- Alosetron is approved specifically for women with severe diarrhea-predominant IBS — that means IBS where diarrhea is the main problem, symptoms have been going on for at least 6 mo...
- What exactly is alosetron used for — and can my husband take it too?
- Constipation is the big one — it's actually the most common reason people stop taking alosetron. If you become constipated, stop the medication right away and call your prescriber...
- What side effect should I watch out for most closely?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Alosetron — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII Q662QK8M3B
Polyethylene glycol 8000 is a synthetic polymer made from ethylene oxide. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and add bulk to the medicine.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.949 | $58.47 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $2.50 | $74.94 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $6.41 | $192.34 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Alosetron Hydrochloride .5 mg 53746-0248-30 | Amneal | 30 tablets | $1.949 | AB | Availability likely | — |
| Alosetron Hydrochloride .5 mg 65162-0248-03 | Amneal | 30 tablets | $1.949 | AB | Availability likely | — |
| Alosetron .5 mgthis 70756-0702-30 | Lifestar | 30 tablets | $1.949 | AB | Availability likely | — |
| Alosetron Hydrochloride .5 mg 71930-0010-30 | Eywa | 30 tablets | $1.949 | AB | Availability likely | — |
| Lotronex .5 mg 54766-0894-03 | Sebela | 30 tablets | — | AB | FDA listed | — |
| Alosetron .5 mg 63629-2517-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Alosetron Hydrochloride .5 mg 73190-0035-30 | AvKARE | 30 tablets | — | AB | FDA listed | — |
| Lotronex .5 mg 83107-0013-30 | Legacy | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 70756-0702-30 You're viewing this | 30 TABLET in 1 BOTTLE (70756-702-30) | 2020-09-14 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SERIOUS GASTROINTESTINAL ADVERSE REACTIONS Infrequent but serious gastrointestinal adverse reactions have been reported with the use of alosetron tablets. These events, including ischemic colitis and serious complications of constipation, have resulted in hospitalization, and rarely, blood transfusion, surgery, and death. Alosetron tablets are indicated only for women with severe diarrhea-predominant irritable bowel syndrome (IBS) who have not responded adequately to conventional therapy [see Indications and Usage (1)] .
Alosetron tablets should be discontinued immediately in patients who develop constipation or symptoms of ischemic colitis. Patients should immediately report constipation or symptoms of ischemic colitis to their prescriber. Alosetron tablets should not be resumed in patients who develop ischemic colitis.
Patients who have constipation should immediately contact their prescriber if the constipation does not resolve after alosetron tablets is discontinued. Patients with resolved constipation should resume alosetron tablets only on the advice of their treating prescriber [see Dosage and Administration (2.1) , Warnings and Precautions (5.1) , (5.2)]. WARNING: SERIOUS GASTROINTESTINAL ADVERSE REACTIONS See full prescribing information for complete boxed warning.
Infrequent but serious gastrointestinal adverse reactions have been reported with the use of alosetron tablets. These events, including ischemic colitis and serious complications of constipation, have resulted in hospitalization and, rarely, blood transfusion, surgery, and death. Alosetron tablets are indicated only for women with severe diarrhea-predominant irritable bowel syndrome (IBS) who have not responded adequately to conventional therapy.
( 1 ) Discontinue alosetron tablets immediately in patients who develop constipation or symptoms of ischemic colitis. Do not resume alosetron tablets in patients who develop ischemic colitis. ( 2.1 , 5.1 , 5.2 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Alosetron tablets are indicated only for women with severe diarrhea-predominant irritable bowel syndrome (IBS) who have: chronic IBS symptoms (generally lasting 6 months or longer), had anatomic or biochemical abnormalities of the gastrointestinal tract excluded, and not responded adequately to conventional therapy. Diarrhea-predominant IBS is severe if it includes diarrhea and one or more of the following: frequent and severe abdominal pain/discomfort, frequent bowel urgency or fecal incontinence, disability or restriction of daily activities due to IBS.
Because of infrequent but serious gastrointestinal adverse reactions associated with alosetron tablets, the indication is restricted to those patients for whom the benefit-to-risk balance is most favorable. Clinical studies have not been performed to adequately confirm the benefits of alosetron tablets in men. Alosetron tablets are selective serotonin 5-HT 3 antagonist indicated only for women with severe diarrhea-predominant irritable bowel syndrome (IBS) who have: chronic IBS symptoms (generally lasting 6 months or longer), had anatomic or biochemical abnormalities of the gastrointestinal tract excluded and not responded adequately to conventional therapy.
( 1 ) Severe IBS includes diarrhea and 1 or more of the following: frequent and severe abdominal pain/discomfort, frequent bowel urgency or fecal incontinence, disability or restriction of daily activities due to IBS. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Starting dose is 0.5 mg twice a day ( 2.1 ) May increase dose to 1 mg twice a day after 4 weeks if starting dosage is well tolerated but does not adequately control IBS symptoms ( 2.1 ) Discontinue alosetron tablets in patients who have not had adequate control of IBS symptoms after 4 weeks of treatment with 1 mg twice a day. ( 2.1 )
2.1Adult Patients To lower the risk of constipation, alosetron tablets should be started at a dosage of 0.5 mg twice a day. Patients who become constipated at this dosage should stop taking alosetron tablets until the constipation resolves. They may be restarted at 0.5 mg once a day.
If constipation recurs at the lower dose, Alosetron tablets should be discontinued immediately. Patients well controlled on 0.5 mg once or twice a day may be maintained on this regimen. If after 4 weeks the dosage is well tolerated but does not adequately control IBS symptoms, then the dosage can be increased to up to 1 mg twice a day.
Alosetron tablets should be discontinued in patients who have not had adequate control of IBS symptoms after 4 weeks of treatment with 1 mg twice a day. Alosetron tablets can be taken with or without food [see Clinical Pharmacology (12.3) ] . Alosetron tablets should be discontinued immediately in patients who develop constipation or signs of ischemic colitis.
Alosetron tablets should not be restarted in patients who develop ischemic colitis. Clinical trial and postmarketing experience suggest that debilitated patients or patients taking additional medications that decrease gastrointestinal motility may be at greater risk of serious complications of constipation. Therefore, appropriate caution and follow-up should be exercised if alosetron tablets are prescribed for these patients.
Postmarketing experience suggests that elderly patients may be at greater risk for complications of constipation; therefore, appropriate caution and follow-up should be exercised if alosetron tablets are prescribed for these patients [see Warnings and Precautions (5.1) ] .
2.2Patients with Hepatic Impairment Alosetron tablets are extensively metabolized by the liver, and increased exposure to alosetron tablets is likely to occur in patients with hepatic impairment. Increased drug exposure may increase the risk of serious adverse reactions. Alosetron tablets should be used with caution in patients with mild or moderate hepatic impairment and is contraindicated in patients with severe hepatic impairment [see Contraindications (4) , Use in Specific Populations (8.6) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 0.5 mg and 1 mg tablets Alosetron Tablets USP, 0.5 mg (0.562 mg alosetron HCl equivalent to 0.5 mg alosetron), are round, film-coated, white colored biconvex tablets debossed with "LS 702" on one side and plain on other side. Alosetron Tablets USP, 1 mg (1.124 mg alosetron HCl equivalent to 1 mg alosetron), are round, film-coated, blue colored biconvex tablets debossed with "LS 701" on one side and plain on other side. Tablets: 0.5 and 1 mg
⛔ Contraindications ▾
4 CONTRAINDICATIONS Do not initiate in patients with constipation ( 4.1 ) History of chronic or severe constipation or sequelae from constipation; intestinal obstruction, stricture, toxic megacolon, gastrointestinal perforation, and/or adhesions; ischemic colitis; impaired intestinal circulation, thrombophlebitis, or hypercoagulable state; Crohn's disease or ulcerative colitis; diverticulitis; severe hepatic impairment ( 4.2 ) Concomitant use of fluvoxamine ( 4.3 )
4.1Constipation Alosetron tablets should not be initiated in patients with constipation [see Warnings and Precautions (5.1) ] .
4.2History of Severe Bowel or Hepatic Disorders Alosetron tablets are contraindicated in patients with a history of the following: chronic or severe constipation or sequelae from constipation intestinal obstruction, stricture, toxic megacolon, gastrointestinal perforation and/or adhesions ischemic colitis, impaired intestinal circulation, thrombophlebitis, or hypercoagulable state Crohn's disease or ulcerative colitis diverticulitis severe hepatic impairment
4.3Concomitant Use of Fluvoxamine Concomitant administration of alosetron tablets with fluvoxamine is contraindicated. Fluvoxamine, a known strong inhibitor of CYP1A2, has been shown to increase mean alosetron plasma concentrations (AUC) approximately 6-fold and prolong the half-life by approximately 3-fold [see Drug Interactions (7.1) ] .
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Serious Complications of Constipation: May occur in some patients without warning. Includes obstruction, ileus, impaction, toxic megacolon, and secondary bowel ischemia and in rare cases perforation and death have been reported. Risk is increased in patients who are elderly, debilitated, or taking medications that decrease bowel motility.
( 5.1 ) Discontinue alosetron tablets immediately if constipation occurs. ( 5.1 ) Ischemic colitis: May occur in some patients without warning. Promptly evaluate patients with signs of ischemic colitis (e.g., rectal bleeding, bloody diarrhea, new or worsening abdominal pain).
( 5.2 ) Discontinue alosetron tablets immediately if signs of ischemic colitis occur, such as rectal bleeding, bloody diarrhea, or new or worsening abdominal pain. ( 5.2 )
5.1Serious Complications of Constipation Some patients have experienced serious complications of constipation without warning. Serious complications of constipation, including obstruction, ileus, impaction, toxic megacolon, and secondary bowel ischemia, have been reported with use of alosetron tablets during clinical trials. Complications of constipation have been reported with use of 1 mg twice daily and with lower doses.
A dose response relationship has not been established for serious complications of constipation. The incidence of serious complications of constipation was approximately 0.1% (1 per 1,000 patients) in women receiving either alosetron tablets or placebo. In addition, rare cases of perforation and death have been reported from postmarketing clinical practice.
In some cases, complications of constipation required intestinal surgery, including colectomy. Patients who are elderly, debilitated, or taking additional medications that decrease gastrointestinal motility may be at greater risk for complications of constipation. Alosetron tablets should be discontinued immediately in patients who develop constipation [see Boxed Warning ].
5.2Ischemic Colitis Some patients have experienced ischemic colitis without warning. Ischemic colitis has been reported in patients receiving alosetron tablets in clinical trials as well as during marketed use of the drug. In IBS clinical trials, the cumulative incidence of ischemic colitis in women receiving alosetron tablets was 0.2% (2 per 1,000 patients, 95% confidence interval 1 to 3) through 3 months and was 0.3% (3 per 1,000 patients, 95% confidence interval 1 to 4) through 6 months.
Ischemic colitis has been reported with use of 1 mg twice daily and with lower doses. A dose-response relationship has not been established. Ischemic colitis was reported in one patient receiving placebo.
The patient experience in controlled clinical trials is insufficient to estimate the incidence of ischemic colitis in patients taking alosetron tablets for longer than 6 months. Alosetron tablets should be discontinued immediately in patients with signs of ischemic colitis such as rectal bleeding, bloody diarrhea, or new or worsening abdominal pain. Because ischemic colitis can be life-threatening, patients with signs or symptoms of ischemic colitis should be evaluated promptly and have appropriate diagnostic testing performed.
Treatment with alosetron tablets should not be resumed in patients who develop ischemic colitis.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described in more detail in other sections of the label: Complications of constipation [see Boxed Warning , Warnings and Precautions ( 5.1 )] Ischemic colitis [see Boxed Warning , Warnings and Precautions ( 5.2 )] Most common adverse reactions (incidence >2% and >placebo) in clinical studies were constipation, abdominal discomfort and pain, nausea and gastrointestinal discomfort and pain. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Lifestar Pharma LLC at 1-888-995-4337 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Patients with Irritable Bowel Syndrome: Table 1 summarizes adverse reactions from 22 repeat-dose studies in patients with IBS who were treated with 1 mg of alosetron tablets twice daily for 8 to 24 weeks. The adverse reactions in Table 1 were reported in 1% or more of patients who received alosetron tablets and occurred more frequently on alosetron tablets than on placebo.
A statistically significant difference was observed for constipation in patients treated with alosetron tablets compared to placebo (p<0.0001). Table 1. Adverse Reactions Reported in ≥1% of Patients with Irritable Bowel Syndrome and More Frequently on Alosetron Tablets 1 mg Twice Daily Than Placebo Body System Adverse Reaction Placebo (n = 2,363) Alosetron Tablets 1 mg twice daily (n = 8,328) Gastrointestinal Constipation 6% 29% Abdominal discomfort and pain 4% 7% Nausea 5% 6% Gastrointestinal discomfort and pain 3% 5% Abdominal distention 1% 2% Regurgitation and reflux 2% 2% Hemorrhoids 1% 2% Gastrointestinal: Constipation is a frequent and dose-related side effect of treatment with alosetron tablets [see Warnings and Precautions ( 5.1 )] .
In clinical studies constipation was reported in approximately 29% of patients with IBS treated with alosetron tablets 1 mg twice daily (n = 9,316). This effect was statistically significant compared to placebo (p<0.0001). Eleven percent (11%) of patients treated with alosetron tablets 1 mg twice daily withdrew from the studies due to constipation.
Although the number of patients with IBS treated with alosetron tablets 0.5 mg twice daily is relatively small (n = 243), only 11% of those patients reported constipation and 4% withdrew from clinical studies due to constipation. Among the patients treated with alosetron tablets 1 mg twice daily who reported constipation, 75% reported a single episode and most reports of constipation (70%) occurred during the first month of treatment, with the median time to first report of constipation onset of 8 days. Occurrences of constipation in clinical trials were generally mild to moderate in intensity, transient in nature, and resolved either spontaneously with continued treatment or with an interruption of treatment.
However, serious complications of constipation have been reported in clinical studies and in postmarketing experience [see Boxed Warning and Warnings and Precautions (5.1) ] . In Studies 1 and 2, 9% of patients treated with alosetron tablets reported constipation and 4 consecutive days with no bowel movement [see Clinical Studies (14.2) ] . Following interruption of treatment, 78% of the affected patients resumed bowel movements within a 2-day period and were able to re-initiate treatment with alosetron tablets.
Hepatic: A similar incidence in elevation of ALT (>2-fold) was seen in patients receiving alosetron tablets or placebo (1.0% vs. 1.2%). A single case of hepatitis (elevated ALT, AST, alkaline phosphatase, and bilirubin) without jaundice in a patient receiving alosetron tablets was reported in a 12-week study.
A causal association with alosetron tablets has not been established. Long-Term Safety…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS In vivo data suggest that alosetron is primarily metabolized by cytochrome P450 (CYP) 1A2, with minor contributions from CYP3A4 and CYP2C9. Therefore, inducers or inhibitors of these enzymes may change the clearance of alosetron. CYP1A2 inhibitors: Avoid concomitant uses because of increased exposure and half-life of alosetron.
Use with fluvoxamine is contraindicated. ( 4.3 , 7.1) CYP3A4 inhibitors: Use with caution in combination due to increased exposure of alosetron. ( 7.2 )
7.1CYP1A2 Inhibitors Fluvoxamine is a known strong inhibitor of CYP1A2 and also inhibits CYP3A4, CYP2C9, and CYP2C19. In a pharmacokinetic study, 40 healthy female subjects received fluvoxamine in escalating doses from 50 to 200 mg/day for 16 days, with coadministration of alosetron 1 mg on the last day. Fluvoxamine increased mean alosetron plasma concentrations (AUC) approximately 6-fold and prolonged the half-life by approximately 3-fold.
Concomitant administration of alosetron and fluvoxamine is contraindicated [see Contraindications (4.3) ] . Concomitant administration of alosetron and moderate CYP1A2 inhibitors, including quinolone antibiotics and cimetidine, has not been evaluated, but should be avoided unless clinically necessary because of similar potential drug interactions.
7.2CYP3A4 Inhibitors Ketoconazole is a known strong inhibitor of CYP3A4. In a pharmacokinetic study, 38 healthy female subjects received ketoconazole 200 mg twice daily for 7 days, with coadministration of alosetron 1 mg on the last day. Ketoconazole increased mean alosetron plasma concentrations (AUC) by 29%.
Caution should be used when alosetron and ketoconazole are administered concomitantly. Coadministration of alosetron and strong CYP3A4 inhibitors such as clarithromycin, telithromycin, protease inhibitors, voriconazole, and itraconazole has not been evaluated but should be undertaken with caution because of similar potential drug interactions. The effect of induction or inhibition of other pathways on exposure to alosetron and its metabolites is not known.
7.3Other CYP Enzymes In vitro human liver microsome studies and an in vivo metabolic probe study demonstrated that alosetron did not inhibit CYP enzymes 3A4, 2C9, or 2C19. In vitro at total drug concentrations 27-fold higher than peak plasma concentrations observed with the 1 mg dose, alosetron inhibited CYP enzymes 1A2 (60%) and 2E1 (50%). In an in vivo metabolic probe study, alosetron did not inhibit CYP2E1 but did produce 30% inhibition of both CYP1A2 and N-acetyltransferase.
Although not studied with alosetron, inhibition of N-acetyltransferase may have clinically relevant consequences for drugs such as isoniazid, procainamide, and hydralazine. The effect on CYP1A2 was explored further in a clinical interaction study with theophylline and no effect on metabolism was observed. Another study showed that alosetron had no clinically significant effect on plasma concentrations of the oral contraceptive agents ethinyl estradiol and levonorgestrel (CYP3A4 substrates).
A clinical interaction study was also conducted with alosetron and the CYP3A4 substrate cisapride. No significant effects on cisapride metabolism or QT interval were noted. The effects of alosetron on monoamine oxidases and on intestinal first pass secondary to high intraluminal concentrations have not been examined.
Based on the above data from in vitro and in vivo studies, it is unlikely that alosetron will inhibit the hepatic metabolic clearance of drugs metabolized by the CYP enzymes 2C9, 2C19, or 2E1. Alosetron does not appear to induce the major cytochrome P450 drug-metabolizing enzyme 3A. Alosetron also does not appear to induce CYP enzymes 2E1 or 2C19.
It is not known whether alosetron might induce other enzymes.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Hepatic impairment: Contraindicated in severe hepatic impairment. Use with caution in patients with mild or moderate hepatic impairment. ( 4.2 , 8.6 ) Geriatric use: Elderly patients may be at greater risk for complications of constipation. ( 8.5 )
8.1Pregnancy Risk Summary The available data with alosetron tablets use in pregnant women are insufficient to draw conclusions about any drug-associated risks for major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, no adverse developmental effects were observed with oral administration of alosetron in rats and rabbits during organogenesis at doses 160 to 240 times, respectively, the recommended human dosage (see Data). The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and miscarriage is 15 to 20%, respectively. Data Animal Data No adverse developmental effects were observed with oral administration of alosetron during the period of organogenesis to pregnant rats at doses up to 40 mg/kg/day (about 160 times the recommended human dose based on body surface area) or to pregnant rabbits at doses up to 30 mg/kg/day (about 240 times the recommended daily human dose based on body surface area).
8.2Lactation Risk Summary There are no data regarding the presence of alosetron in human milk, the effects on the breastfed infant, or the effects on milk production. Alosetron and/or metabolites of alosetron are present in the breast milk of lactating rats. When a drug is present in animal milk, it is likely that the drug will be present in human milk.
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for alosetron tablets and any potential adverse effects on the breastfed infant from alosetron tablets or from the underlying maternal condition. Clinical Considerations Monitor infants exposed to alosetron through breast milk for severe constipation and blood in stools.
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. Use of alosetron tablets are not recommended in the pediatric population, based upon the risk of serious complications of constipation and ischemic colitis in adults.
8.5Geriatric Use In some studies, in healthy men or women, plasma concentrations were elevated by approximately 40% in individuals 65 years and older compared to young adults [see Warnings and Precautions (5.1) ] . However, this effect was not consistently observed in men. Postmarketing experience suggests that elderly patients may be at greater risk for complications of constipation therefore, appropriate caution and follow-up should be exercised if alosetron tablets are prescribed for these patients [see Warnings and Precautions (5.1) ] .
8.6Hepatic Impairment Due to the extensive hepatic metabolism of alosetron, increased exposure to alosetron and/or its metabolites is likely to occur in patients with hepatic impairment. Alosetron should not be used in patients with severe hepatic impairment and should be used with caution in patients with mild or moderate hepatic impairment. A single 1 mg oral dose of alosetron was administered to 1 female and 5 male patients with moderate hepatic impairment (Child-Pugh score of 7 to 9) and to 1 female and 2 male patients with severe hepatic impairment (Child-Pugh score of >9).
In comparison with historical data from healthy subjects, patients with severe hepatic impairment displayed higher systemic exposure to alosetron. The female with severe hepatic impairment displayed approximately 14-fold higher exposure, while the female with moderate hepatic impairment displayed approximately 1.6-fold higher ex…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The available data with alosetron tablets use in pregnant women are insufficient to draw conclusions about any drug-associated risks for major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, no adverse developmental effects were observed with oral administration of alosetron in rats and rabbits during organogenesis at doses 160 to 240 times, respectively, the recommended human dosage (see Data). The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and miscarriage is 15 to 20%, respectively. Data Animal Data No adverse developmental effects were observed with oral administration of alosetron during the period of organogenesis to pregnant rats at doses up to 40 mg/kg/day (about 160 times the recommended human dose based on body surface area) or to pregnant rabbits at doses up to 30 mg/kg/day (about 240 times the recommended daily human dose based on body surface area).
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. Use of alosetron tablets are not recommended in the pediatric population, based upon the risk of serious complications of constipation and ischemic colitis in adults.
🧓 Geriatric Use ▾
8.5Geriatric Use In some studies, in healthy men or women, plasma concentrations were elevated by approximately 40% in individuals 65 years and older compared to young adults [see Warnings and Precautions (5.1) ] . However, this effect was not consistently observed in men. Postmarketing experience suggests that elderly patients may be at greater risk for complications of constipation therefore, appropriate caution and follow-up should be exercised if alosetron tablets are prescribed for these patients [see Warnings and Precautions (5.1) ] .
🆘 Overdosage ▾
10 OVERDOSAGE There is no specific antidote for overdose of alosetron tablets. Patients should be managed with appropriate supportive therapy. Individual oral doses as large as 16 mg have been administered in clinical studies without significant adverse reactions.
This dose is 8 times higher than the recommended total daily dose. Inhibition of the metabolic elimination and reduced first pass of other drugs might occur with overdoses of alosetron hydrochloride [see Drug Interactions (7) ].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Alosetron is a potent and selective 5-HT 3 receptor antagonist. 5-HT 3 receptors are ligand-gated cation channels that are extensively distributed on enteric neurons in the human gastrointestinal tract, as well as other peripheral and central locations. Activation of these channels and the resulting neuronal depolarization affect the regulation of visceral pain, colonic transit, and gastrointestinal secretions, processes that relate to the pathophysiology of IBS.
5-HT 3 receptor antagonists such as alosetron inhibit activation of non-selective cation channels, which results in the modulation of the enteric nervous system. The cause of IBS is unknown. IBS is characterized by visceral hypersensitivity and hyperactivity of the gastrointestinal tract, which lead to abnormal sensations of pain and motor activity.
Following distention of the rectum, patients with IBS exhibit pain and discomfort at lower volumes than healthy volunteers. Following such distention, alosetron reduced pain and exaggerated motor responses, possibly due to blockade of 5-HT 3 receptors.
12.2Pharmacodynamics In healthy volunteers and patients with IBS, alosetron (2 mg orally, twice daily for 8 days) increased colonic transit time without affecting orocecal transit time. In healthy volunteers, alosetron also increased basal jejunal water and sodium absorption after a single 4 mg dose. In patients with IBS, multiple oral dosages of alosetron (4 mg twice daily for 6.5 days) significantly increased colonic compliance.
Single oral doses of alosetron administered to healthy men produced a dose-dependent reduction in the flare response seen after intradermal injection of serotonin. Urinary 6-β-hydroxycortisol excretion decreased by 52% in elderly subjects after 27.5 days of alosetron 2 mg administered orally twice daily. This decrease was not statistically significant.
In another study utilizing alosetron 1 mg administered orally twice daily for 4 days, there was a significant decrease in urinary 6-β-hydroxycortisol excretion. However, there was no change in the ratio of 6-β-hydroxycortisol to cortisol, indicating a possible decrease in cortisol production. The clinical significance of these findings is unknown.
12.3Pharmacokinetics The pharmacokinetics of alosetron have been studied after single oral doses ranging from 0.05 to 16 mg in healthy men. The pharmacokinetics of alosetron have also been evaluated in healthy women and men and in patients with IBS after repeated oral dosages ranging from 1 mg twice daily to 8 mg twice daily. Absorption: Alosetron was rapidly absorbed after oral administration with a mean absolute bioavailability of approximately 50% to 60% (approximate range, 30% to >90%).
After administration of radiolabeled alosetron, only 1% of the dose was recovered in the feces as unchanged drug. Following oral administration of a 1 mg alosetron dose to young men, a peak plasma concentration of approximately 5 ng/mL occurred at 1 hour. In young women, the mean peak plasma concentration was approximately 9 ng/mL, with a similar time to peak.
Plasma concentrations were 30% to 50% lower and less variable in men compared to women given the same oral dose. Population pharmacokinetic analysis in IBS patients confirmed that alosetron concentrations were influenced by gender (27% lower in men). Food Effects: Alosetron absorption is decreased by approximately 25% by co-administration with food, with a mean delay in time to peak concentration of 15 minutes [see Dosage and Administration (2.1) ] .
Distribution: Alosetron demonstrates a volume of distribution of approximately 65 to 95 L. Plasma protein binding is 82% over a concentration range of 20 to 4,000 ng/mL. Metabolism and Elimination: Plasma concentrations of alosetron increase proportionately with increasing single oral doses up to 8 mg and more than proportionately at a single oral dose of 16 mg.
Twice-daily oral dosing of alosetron does not result in…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Alosetron is a potent and selective 5-HT 3 receptor antagonist. 5-HT 3 receptors are ligand-gated cation channels that are extensively distributed on enteric neurons in the human gastrointestinal tract, as well as other peripheral and central locations. Activation of these channels and the resulting neuronal depolarization affect the regulation of visceral pain, colonic transit, and gastrointestinal secretions, processes that relate to the pathophysiology of IBS.
5-HT 3 receptor antagonists such as alosetron inhibit activation of non-selective cation channels, which results in the modulation of the enteric nervous system. The cause of IBS is unknown. IBS is characterized by visceral hypersensitivity and hyperactivity of the gastrointestinal tract, which lead to abnormal sensations of pain and motor activity.
Following distention of the rectum, patients with IBS exhibit pain and discomfort at lower volumes than healthy volunteers. Following such distention, alosetron reduced pain and exaggerated motor responses, possibly due to blockade of 5-HT 3 receptors.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Alosetron Tablets USP, 0.5 mg (0.562 mg alosetron HCl equivalent to 0.5 mg alosetron), are round, film coated, white colored biconvex tablets debossed with "LS 702" on one side and plain on other side. Bottles of 30 (NDC 70756-702-30) with child-resistant closures. Alosetron Tablets USP, 1 mg (1.124 mg alosetron HCl equivalent to 1 mg alosetron), are round, film coated, blue colored biconvex tablets debossed with "LS 701" on one side and plain on other side.
Bottles of 30 (NDC 70756-701-30) with child-resistant closures. Store at 20-25°C (68-77°F) (See USP Controlled Room Temperature). Protect from light and moisture.
Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure.
📋 Description ▾
11 DESCRIPTION The active ingredient in alosetron tablets USP, is alosetron hydrochloride (HCl) USP, a potent and selective antagonist of the serotonin 5-HT 3 receptor type. Chemically, alosetron is designated as 2,3,4,5-tetrahydro-5-methyl-2-[(5-methyl-1H-imidazol-4-yl)methyl]-1H-pyrido[4,3-b]indol-1-one, monohydrochloride. Alosetron is achiral and has the empirical formula C 17 H 18 N 4 O•HCl, representing a molecular weight of 330.8.
Alosetron is a white to beige solid that has a solubility of 61 mg/mL in water, 42 mg/mL in 0.1M hydrochloric acid, 0.3 mg/mL in pH 6 phosphate buffer, and <0.1 mg/mL in pH 8 phosphate buffer. The chemical structure of alosetron is: Alosetron Tablets USP, are supplied for oral administration as 0.5 mg (white) and 1 mg (blue) tablets. The 0.5 mg tablet contains 0.562 mg alosetron HCl equivalent to 0.5 mg alosetron, and the 1 mg tablet contains 1.124 mg alosetron HCl equivalent to 1 mg of alosetron.
Each tablet also contains the inactive ingredients lactose monohydrate, magnesium stearate, microcrystalline cellulose, and pregelatinized starch (maize). The white film coat for the 0.5 mg tablet contains hypromellose, polyethylene glycol, and titanium dioxide. The blue film coat for the 1 mg tablet contains hypromellose, polyethylene glycol, titanium dioxide, FD&C Blue #2 - Aluminum Lake and Iron Oxide Yellow.
Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labelling (Medication Guide). Prescriber and Patient Responsibilities Patients should be fully counseled on and understand the risks and benefits of alosetron tablets before an initial prescription is written. The patient may be educated by the prescriber or a healthcare provider under a prescriber's direction.
Prescribers must: counsel patients for whom alosetron tablets are appropriate about the benefits and risks of alosetron tablets and discuss the impact of IBS symptoms on the patient's life. review the Medication Guide, which outlines the benefits and risks of alosetron tablets, and instruct the patient to read it carefully. Answer all questions the patient may have about alosetron tablets. The complete text of the Medication Guide is printed at the end of this document. provide each patient with appropriate instructions for taking alosetron tablets.
Additional copies of the Medication Guide are available by contacting Lifestar Pharma LLC at 1-888-995-4337. Patients who are prescribed alosetron tablets should be instructed to: read the Medication Guide before starting alosetron tablets and each time they refill their prescription. not start taking alosetron tablets if they are constipated. immediately discontinue alosetron tablets and contact their prescriber if they become constipated, or have symptoms of ischemic colitis such as new or worsening abdominal pain, bloody diarrhea, or blood in the stool.
Contact their prescriber again if their constipation does not resolve after discontinuation of alosetron tablets. Resume alosetron tablets only if their constipation has resolved and after discussion with and the agreement of their treating prescriber. stop taking alosetron tablets and contact their prescriber if alosetron tablets does not adequately control IBS symptoms after 4 weeks of taking 1 mg twice a day. Manufactured for: Lifestar Pharma LLC 1200 MacArthur Blvd Mahwah, NJ 07430 USA Made in India Rev.
September 2025, V-04
💬 Medication Guide ▾
MEDICATION GUIDE Alosetron (a-LOE-se-tron) Tablets, USP Read the Medication Guide you get with each refill for alosetron tablets. There may be new information. This Medication Guide does not take the place of talking with your doctor.
What is the most important information I should know about alosetron tablets? Alosetron tablets is a medicine only for some women with severe chronic irritable bowel syndrome (IBS) whose: ● main problem is diarrhea and ● IBS symptoms have not been helped enough by other treatments. Some people have developed serious bowel side effects while taking alosetron tablets.
Serious bowel (intestine) side effects can happen suddenly, including the following: ● Serious complications of constipation: These complications may lead to a hospital stay and, in rare cases, blood transfusions, surgery, and death. People who are older, who are weak from illness, or who take other constipating medicines may be more likely to have serious complications of constipation with alosetron tablets. ● To lower your chances of getting serious complications of constipation, do the following: ○ If you are constipated, do not start taking alosetron tablets ○ If you get constipated while taking alosetron tablets, stop taking it right away and call your doctor. ○ If your constipation does not get better after stopping alosetron tablets, call your doctor again. ○ If you stopped taking alosetron tablets, do not start taking alosetron tablets again unless your doctor tells you to do so. ● Inflammation and injury of the intestines caused by reduced blood flow (ischemic colitis: Ischemic colitis is caused by reduced blood flow to parts of the large bowel.
The chance of getting ischemic colitis when you take alosetron tablets for more than 6 months is not known. Ischemic colitis may lead to a hospital stay and, in rare cases, blood transfusions, surgery, and death. Stop taking alosetron tablets and call your doctor or get medical help if you have symptoms of ischemic colitis such as new or worsening stomach-area (abdominal) pain, bloody diarrhea or blood in the stool.
What are alosetron tablets? Alosetron tablets are prescription medicine used only for some women with severe chronic IBS whose: ● main problem is diarrhea and ● IBS symptoms have not been helped enough by other treatments. Alosetron tablets do not cure IBS, and it may not help every person who takes it.
For those who are helped alosetron tablets reduces lower stomach area (abdominal) pain and discomfort, the sudden need to have a bowel movement (bowel urgency), and diarrhea from IBS. If you stop taking alosetron tablets, your IBS symptoms may return within 1 or 2 weeks to what they were before you started taking alosetron tablets. It is not known if alosetron tablets are safe and effective in men with IBS.
It is not known if alosetron tablets are safe and effective in children. Who should not take alosetron tablets? Do not take alosetron tablets if you: ● have constipation or you are constipated most of the time. ● have had a serious problem from constipation.
If you are constipated now, do not start taking alosetron tablets. ● have had serious bowel blockages. ● have had blood flow problems to your bowels, such as ischemic colitis. ● have had blood clots. ● have had Crohn's disease, ulcerative colitis, diverticulitis, or severe liver disease. ● are taking fluvoxamine (LUVOX). What should I talk about with my doctor before taking alosetron tablets? Talk with your doctor: ● about the possible benefits and risks of alosetron tablets. ● about how much of a problem IBS is in your life and what treatments you have tried. ● about any other illnesses you have and medicines you take or plan to take.
These include prescription and non-prescription medicines, supplements, and herbal remedies. Certain illnesses and medicines can increase your chance of getting serious side effects while taking alosetron tablets. Other medicines may interact with how the body handles alosetron tablets…