
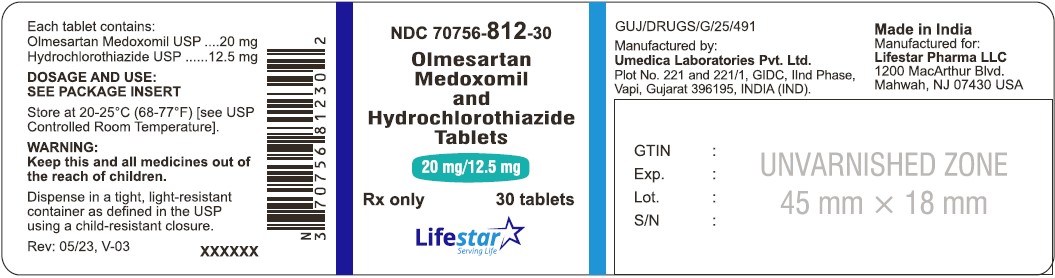
Olmesartan Medoxomil and Hydrochlorothiazide 20 mg; 12.5 mg Tablet, 30-count — NDC 70756-812-30 (Billing 70756-0812-30)
This is a package of 30 tablets of Olmesartan Medoxomil and Hydrochlorothiazide 20 mg; 12.5 mg Tablet from Lifestar Pharma LLC, marketed since Oct 2020 and currently FDA-listed; retail pharmacies pay about $0.1650 per tablet (NADAC).
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 052833
- GCN: 20074
- GPI-14 (Medi-Span): 36994002500320
- HICL (First Databank): 025446
- AHFS class code: 24:32.08.00
- RxCUI (RxNorm): 403853
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Angiotensin 2 Receptor Blocker class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.165 | $4.95 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.3308 | $9.92 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.3606 | $10.82 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 70756-0812-12 70756-812-12 | 1000 TABLET in 1 BOTTLE | — | — | 2020-10-01 | — | Active |
| 70756-0812-30 You're viewing this | 30 TABLET in 1 BOTTLE | $0.1650 / ea | $4.95 | 2020-10-01 | — | Active |
| 70756-0812-90 70756-812-90 Main listing | 90 TABLET in 1 BOTTLE | $0.1650 / ea | $14.85 | 2020-10-01 | — | Active |
| 70756-0812-51 70756-812-51 | 500 TABLET in 1 BOTTLE | — | — | 2020-10-01 | — | Active |
You're viewing the smallest of 4 pack sizes for this product.
This pack has the lowest per-ea cost of the 2 priced pack sizes ($0.1650 NADAC).
This pack accounts for about 32% of this product's recent Medicaid fills; most go to the 90 tablets pack. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 70756-0812-90?
What NDC number is used to bill for this package of Olmesartan Medoxomil and Hydrochlorothiazide 20 mg; 12.5 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Olmesartan medoxomil and hydrochlorothiazide 20 mg/1; 12.5 mg 31722-0886-30 | Camber | 30 tablets | $0.165 | AB | Availability likely | — |
| OLMESARTAN MEDOXOMIL and HYDROCHLOROTHIAZIDE 20 mg/1; 12.5 mg 33342-0173-07 | Macleods | 30 tablets | $0.165 | AB | Availability likely | — |
| OLMESARTAN MEDOXOMIL and HYDROCHLOROTHIAZIDE 20 mg/1; 12.5 mg 43547-0391-03 | Solco | 30 tablets | $0.165 | AB | Availability likely | — |
| Olmesartan Medoxomil and Hydrochlorothiazide 20 mg/1; 12.5 mg 65862-0779-30 | Aurobindo | 30 tablets | $0.165 | — | Availability likely | — |
| Olmesartan Medoxomil And Hydrochlorothiazide 20 mg/1; 12.5 mg 67877-0453-30 | Ascend | 30 tablets | $0.165 | AB | Availability likely | — |
| Olmesartan Medoxomil and Hydrochlorothiazide 20 mg/1; 12.5 mgthis 70756-0812-30 | Lifestar | 30 tablets | $0.165 | AB | Availability likely | — |
| olmesartan medoxomil-hydrochlorothiazide 20 mg/1; 12.5 mg 72205-0147-30 | Novadoz | 30 tablets | $0.165 | AB | Availability likely | — |
| OLMESARTAN MEDOXOMIL and HYDROCHLOROTHIAZIDE 20 mg/1; 12.5 mg 72603-0290-01 | NorthStar | 30 tablets | $0.165 | AB | Availability likely | — |
| Olmesartan Medoxomil And Hydrochlorothiazide 20 mg/1; 12.5 mg 16729-0366-15 | Accord | 90 tablets | $0.175 | AB | Availability likely | +6% |
| Benicar HCT 20 mg/1; 12.5 mg 00713-0863-30 | Cosette | 30 tablets | $11.317 | AB | Availability likely | +6758% |
| Benicar HCT 20 mg/1; 12.5 mg 00713-0943-30 | Cosette | 30 tablets | — | AB | FDA listed | — |
| olmesartan medoxomil-hydrochlorothiazide 20 mg/1; 12.5 mg 42291-0924-90 | AvKARE | 90 tablets | — | AB | FDA listed | — |
| Olmesartan Medoxomil and Hydrochlorothiazide 20 mg/1; 12.5 mg 46708-0149-08 | Alembic | 80 tablets | — | AB | FDA listed | — |
| Olmesartan Medoxomil and Hydrochlorothiazide 20 mg/1; 12.5 mg 50090-3701-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| OLMESARTAN MEDOXOMIL and HYDROCHLOROTHIAZIDE 20 mg/1; 12.5 mg 50090-6836-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| OLMESARTAN MEDOXOMIL and HYDROCHLOROTHIAZIDE 20 mg/1; 12.5 mg 50090-7478-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| OLMESARTAN MEDOXOMIL and HYDROCHLOROTHIAZIDE 20 mg/1; 12.5 mg 50228-0342-10 | ScieGen | 1000 tablets | — | AB | FDA listed | — |
| Olmesartan Medoxomil and Hydrochlorothiazide 20 mg/1; 12.5 mg 62332-0149-08 | Alembic | 80 tablets | — | AB | FDA listed | — |
| OLMESARTAN MEDOXOMIL and HYDROCHLOROTHIAZIDE 20 mg/1; 12.5 mg 71335-2424-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| OLMESARTAN MEDOXOMIL and HYDROCHLOROTHIAZIDE 20 mg/1; 12.5 mg 71335-3029-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| OLMESARTAN MEDOXOMIL and HYDROCHLOROTHIAZIDE 20 mg/1; 12.5 mg 84677-0056-10 | Golden | 1000 tablets | — | AB | FDA listed | — |
| Olmesartan Medoxomil and Hydrochlorothiazide 20 mg/1; 12.5 mg 60290-0102-01 | Umedica | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII UKE75GEA7F
Hydroxypropyl cellulose is a plant-based polymer used as a binder and thickener. It helps hold tablet ingredients together, controls how fast the medicine dissolves, and improves the texture of liquid formulations.
-
UNII 2165RE0K14
A plant-based thickener made from cellulose that helps control how quickly the medicine dissolves and releases its active ingredient. It also binds ingredients together and improves the tablet's texture and handling during manufacturing.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY When pregnancy is detected, discontinue olmesartan medoxomil and hydrochlorothiazide tablets as soon as possible [see Warnings and Precautions ( 5.1 ), use in specific populations ( 8.1 )] . Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus [see Warnings and Precautions ( 5.1 ), use in specific populations ( 8.1 )]. WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning.
When pregnancy is detected, discontinue olmesartan medoxomil and hydrochlorothiazide tablets as soon as possible ( 5.1 , 8.1 ). Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus ( 5.1 , 8.1 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Olmesartan medoxomil and hydrochlorothiazide tablets are indicated for the treatment of hypertension, to lower blood pressure [see Dosage and Administration ( 2 )] . Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular (CV) events, primarily strokes and myocardial infarctions. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes including the class to which this drug principally belongs.
There are no controlled trials demonstrating risk reduction with olmesartan medoxomil and hydrochlorothiazide tablets. Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than one drug to achieve blood pressure goals.
For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program’s Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC). Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits.
The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly. Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy. Olmesartan medoxomil and hydrochlorothiazide tablets may be used alone, or in combination with other antihypertensive drugs.
Limitations of Use Olmesartan medoxomil and hydrochlorothiazide tablets is not indicated for the initial therapy of hypertension. Olmesartan medoxomil and hydrochlorothiazide tablets are a combination of olmesartan, an angiotensin II receptor blocker and hydrochlorothiazide, a thiazide diuretic indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions.
( 1 ) Limitations of Use Olmesartan medoxomil and hydrochlorothiazide tablets are not indicated for initial therapy
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended starting dose of olmesartan medoxomil and hydrochlorothiazide tablets are 40/12.5 mg once daily in patients whose blood pressure is not adequately controlled with olmesartan monotherapy. Dose can be titrated up to 40/25 mg if necessary. The recommended starting dose of olmesartan medoxomil and hydrochlorothiazide tablets are 20/12.5 mg once daily in patients whose blood pressure is not adequately controlled with HCT monotherapy or who experience dose-limiting adverse reactions with hydrochlorothiazide.
Dose can be titrated up to 40/25 mg if necessary. Patients titrated to the individual components (olmesartan and hydrochlorothiazide) may instead receive the corresponding dose of olmesartan medoxomil and hydrochlorothiazide tablets. Recommended starting dose in patients not adequately controlled with olmesartan monotherapy, 40/12.5 mg ( 2 ) Recommended starting dose in patients not adequately controlled with hydrochlorothiazide monotherapy, 20/12.5 mg ( 2 ) Adjust dose after 2 to 4 weeks, as needed, to a maximum of 40 mg / 25 mg olmesartan / hydrochlorothiazide ( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Olmesartan medoxomil and hydrochlorothiazide tablets are supplied as film-coated, non-scored tablets: 20 mg/12.5 mg beige, beveled edge round, film-coated tablets, debossed with "OLH" on one side and plain on other side 40 mg/12.5 mg beige, oval shaped, film-coated tablets debossed with "OLH" on one side and "12.5" on other side 40 mg/25 mg pink, oval shaped, film-coated tablets, debossed with "OLH" on one side and "25" on other side Tablets: (olmesartan medoxomil and hydrochlorothiazide) 20/12.5 mg; 40/12.5 mg; 40/25 mg
⛔ Contraindications ▾
4 CONTRAINDICATIONS Olmesartan medoxomil and hydrochlorothiazide tablets are contraindicated: In patients with hypersensitivity to any component of olmesartan medoxomil and hydrochlorothiazide tablets [see Adverse Reactions ( 6.1 , 6.2 )] In patients with anuria [see Warnings and Precautions ( 5.3 ) and Adverse Reactions ( 6.1 )] For co-administration with aliskiren in patients with diabetes [see Drug Interactions ( 7.4 )]. Hypersensitivity to any component of olmesartan medoxomil and hydrochlorothiazide tablets ( 4 ) Anuria (4) Do not co-administer aliskiren with olmesartan medoxomil and hydrochlorothiazide tablets in patients with diabetes.
( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypotension: Correct volume-depletion prior to administration. ( 5.2 ) Monitor renal function and potassium in susceptible patients ( 5.3 ) Observe for signs of fluid or electrolyte imbalance. ( 5.5 ) Acute angle-closure glaucoma ( 5.6 ) Sprue-like enteropathy has been reported. Consider discontinuation of olmesartan medoxomil and hydrochlorothiazide tablets in cases where no other etiology is found ( 5.8 )
5.1Fetal Toxicity Olmesartan medoxomil and hydrochlorothiazide tablets can cause fetal harm when administered to a pregnant women. Use of drugs that act on the renin-angiotensin system (RAS) during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations.
Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death. When pregnancy is detected, discontinue olmesartan medoxomil and hydrochlorothiazide tablets as soon as possible [see Use in Specific Populations ( 8.1 )]. Thiazides cross the placental barrier and appear in cord blood.
Adverse reactions include fetal or neonatal jaundice and thrombocytopenia [see Use in Specific Populations ( 8.1 )].
5.2Hypotension in Volume or Salt-Depleted Patients In patients with an activated renin-angiotensin system, such as volume- or salt-depleted patients (e.g., those being treated with high doses of diuretics), symptomatic hypotension may occur after initiation of treatment with olmesartan medoxomil and hydrochlorothiazide tablets. If hypotension does occur, the patient should be placed in the supine position and, if necessary, given an intravenous infusion of normal saline. When electrolyte and fluid imbalances have been corrected, olmesartan medoxomil and hydrochlorothiazide tablets usually can be continued without difficulty.
A transient hypotensive response is not a contraindication to further treatment.
5.3Impaired Renal Function Changes in renal function including acute renal failure can be caused by drugs that inhibit the renin-angiotensin system and by diuretics. Patients whose renal function may depend in part on the activity of the renin-angiotensin system ( e.g., patients with renal artery stenosis, chronic kidney disease, severe congestive heart failure, or volume depletion) may be at particular risk of developing acute renal failure on olmesartan medoxomil and hydrochlorothiazide tablets. Monitor renal function periodically in these patients.
Consider withholding or discontinuing therapy in patients who develop a clinically significant decrease in renal function on olmesartan medoxomil and hydrochlorothiazide tablets [see Drug Interactions ( 7 )].
5.4Hypersensitivity Reactions Hypersensitivity reactions to hydrochlorothiazide may occur in patients with or without a history of allergy or bronchial asthma, but are more likely in patients with such a history.
5.5Electrolyte and Metabolic Imbalances Olmesartan medoxomil and hydrochlorothiazide tablets contains hydrochlorothiazide which can cause hypokalemia and hyponatremia. Hypomagnesemia can result in hypokalemia which may be difficult to treat despite potassium repletion. Olmesartan medoxomil and hydrochlorothiazide tablets also contain olmesartan, a drug that inhibits the RAS.
Drugs that inhibit the RAS can cause hyperkalemia. Monitor serum electrolytes periodically. Hydrochlorothiazide may alter glucose tolerance and raise serum levels of cholesterol and triglycerides.
Hyperuricemia may occur or frank gout may be precipitated in patients receiving thiazide therapy. Hydrochlorothiazide decreases urinary calcium excretion and may cause elevations of serum calcium. Monitor calcium levels.
5.6Acute Myopia and Secondary Angle-Closure Glaucoma Hydrochlorothiazide, a sulfonamide, can cause an idiosyncratic reaction, resulting in acute transient myopia and acute angle-closure glaucoma. S… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions with olmesartan medoxomil and hydrochlorothiazide tablets are described elsewhere: Hypotension in Volume- or Salt-Depleted Patients [see Warnings and Precautions ( 5.2 )] Impaired Renal Function [see Warnings and Precautions ( 5.3 )] Hypersensitivity Reactions [see Warnings and Precautions ( 5.4 )] Electrolyte and Metabolic Imbalances [see Warnings and Precautions ( 5.5 )] Acute Myopia and Secondary Angle-Closure Glaucoma [see Warnings and Precautions ( 5.6 )] Systemic Lupus Erythematosus [see Warnings and Precautions ( 5.7 )] Sprue-Like Enteropathy [see Warnings and Precautions ( 5.8 )] Most common adverse reactions (incidence ≥2%) are nausea, hyperuricemia, dizziness, and upper respiratory infection ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Lifestar Pharma LLC at 1-888-995-4337 or FDA at 1-800-332-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. Olmesartan medoxomil and hydrochlorothiazide The concomitant use of olmesartan medoxomil and hydrochlorothiazide was evaluated for safety in 1243 hypertensive patients. Treatment with olmesartan medoxomil and hydrochlorothiazide was well tolerated, with an incidence of adverse events similar to that of placebo.
Adverse reactions were generally mild, transient and not dependent on the dose of olmesartan medoxomil and hydrochlorothiazide. The rate of withdrawals for adverse events in all trials of hypertensive patients was 2.0% (25/1243) on olmesartan medoxomil plus hydrochlorothiazide and 2.0% (7/342) on placebo. In a placebo-controlled, factorial clinical trial of olmesartan medoxomil (2.5 mg to 40 mg) and hydrochlorothiazide (12.5 mg to 25 mg), the following adverse reactions reported in Table 1 occurred in >2% of patients, and more often on the olmesartan medoxomil and hydrochlorothiazide combination than on placebo.
Table 1: Adverse Reactions in a Factorial Trial of Patients with Hypertension Olmesartan / HCTZ (N=247) (%) Olmesartan (N=125) (%) HCTZ (N=88) (%) Placebo (N=42) (%) Nausea 3 2 1 0 Hyperuricemia 4 0 2 2 Dizziness 9 1 8 2 Upper Respiratory Infection 7 6 7 0 Other adverse reactions that have been reported with an incidence of greater than 1.0%, whether or not attributed to treatment, in the more than 1200 hypertensive patients treated with olmesartan medoxomil and hydrochlorothiazide in controlled or open-label trials are listed below.
Body as a Whole: chest pain, back pain, peripheral edema Central and Peripheral Nervous System: vertigo Gastrointestinal: abdominal pain, dyspepsia, gastroenteritis, diarrhea Liver and Biliary System: SGOT increased, GGT increased, ALT increased Metabolic and Nutritional: creatine phosphokinase increased Musculoskeletal: arthritis, arthralgia, myalgia Respiratory System: coughing Skin and Appendages Disorders: rash Urinary System: hematuria Facial edema was reported in 2/1243 patients receiving olmesartan medoxomil and hydrochlorothiazide.
Angioedema has been reported with angiotensin II receptor antagonists, including olmesartan medoxomil and hydrochlorothiazide. Hydrochlorothiazide Other adverse reactions that have been reported with hydrochlorothiazide are listed below: Body as a Whole: weakness Digestive: pancreatitis, jaundice (intrahepatic cholestatic jaundice), sialadenitis, cramping, gastric irritation Hematologic: aplastic anemia, agranulocytosis, leukopenia, hemolytic anemia, thrombocytopenia Hypersensitivity: purpura, photosensitivity, urticaria, necrotizing angiitis (vasculitis and cutaneous vasculitis), fever, respiratory distress including pneumonitis and pulmonary edema, anaphylactic reactions Metabolic: glycosuria, hyperuricemia Musculoskeletal: muscle spasm Nervous System/Psychiatric:… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Agent increasing potassium levels may lead to increase in serum potassium ( 7.1 ) Lithium: Risk of lithium toxicity ( 7.2 ) Non-Steroidal Anti-Inflammatory Drugs (NSAIDs): Reduced diuretic, natriuretic and antihypertensive effects; increased risk of renal toxicity ( 7.3 ) Dual inhibition of the renin-angiotensin system: Increased risk of renal impairment, hypotension, and hyperkalemia ( 7.4 ) Colesevelam hydrochloride: Consider administering olmesartan at least 4 hours before colesevelam hydrochloride dose ( 7.5 ) Antidiabetic drugs: Dosage adjustment may be required ( 7.6 ) Cholestyramine and colestipol: Reduced absorption of thiazides ( 7.6 )
7.1Agents Increasing Serum Potassium Coadministration of olmesartan medoxomil and hydrochlorothiazide tablets with other drugs that raise serum potassium levels may result in hyperkalemia. Monitor serum potassium in such patients.
7.2Lithium Increases in serum lithium concentrations and lithium toxicity have been reported during concomitant administration of lithium with angiotensin II receptor antagonists or hydrochlorothiazide. Monitor serum lithium levels during concomitant use.
7.3Non-Steroidal Anti-Inflammatory Agents Including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors) Olmesartan medoxomil In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, co-administration of NSAIDs, including selective COX-2 inhibitors, with angiotensin II receptor antagonists (including olmesartan medoxomil) may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving olmesartan medoxomil and NSAID therapy.
The antihypertensive effect of angiotensin II receptor antagonists, including olmesartan medoxomil, may be attenuated by NSAIDs including selective COX-2 inhibitors. Hydrochlorothiazide In some patients the administration of an NSAID can reduce the diuretic, natriuretic, and antihypertensive effects of thiazide diuretics. Therefore, monitor blood pressure closely.
7.4Dual Blockade of the Renin Angiotensin System Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. Most patients receiving the combination of two RAS inhibitors do not obtain any additional benefit compared to monotherapy. In general, avoid combined use of RAS inhibitors.
Closely monitor blood pressure, renal function and electrolytes in patients on olmesartan medoxomil and hydrochlorothiazide tablets and other agents that affect the RAS. Do not co-administer aliskiren with olmesartan medoxomil and hydrochlorothiazide tablets in patients with diabetes [see Contraindications ( 4 )] . Avoid use of aliskiren with olmesartan medoxomil and hydrochlorothiazide tablets in patients with renal impairment (GFR <60 ml/min).
7.5Colesevelam Hydrochloride Concurrent administration of bile acid sequestering agent colesevelam hydrochloride reduces the systemic exposure and peak plasma concentration of olmesartan. Administration of olmesartan at least 4 hours prior to colesevelam hydrochloride decreased the drug interaction effect. Consider administering olmesartan at least 4 hours before the colesevelam hydrochloride dose [see Clinical Pharmacology ( 12.3 )] .
7.6Use of Hydrochlorothiazide with Other Drugs When administered concurrently the following drugs may interact with thiazide diuretics: Antidiabetic drugs (oral agents and insulin): Dosage adjustment of the antidiabetic drug may be required. Ion exchange resins: Staggering the dosage of hydrochlorothiazide and ion exchange resins (e.g., cholestyramine, colestipol) such that hydrochlorothiazide is administered at least 4 hours before or 4 – 6 hours after the administration of resins would poten… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding is not recommended ( 8.2 ).
8.1Pregnancy Risk Summary Olmesartan medoxomil and hydrochlorothiazide tablets can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue olmesartan medoxomil and hydrochlorothiazide tablets as soon as possible. Use alternative antihypertensive therapy during pregnancy. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2%–4% and 15%–20%, respectively. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section and post-partum hemorrhage).
Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Olmesartan Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death.
Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury.
Closely observe infants with histories of in utero exposure to olmesartan medoxomil and hydrochlorothiazide tablets for hypotension, oliguria, and hyperkalemia. If oliguria or hypotension occur, utilize measures to maintain adequate blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and supporting renal function [see Use in Specific Populations ( 8.4 )].
Hydrochlorothiazide Thiazides can cross the placenta, and concentrations reached in the umbilical vein approach those in the maternal plasma. Hydrochlorothiazide, like other diuretics, can cause placental hypoperfusion. It accumulates in the amniotic fluid, with reported concentrations up to 19 times that in umbilical vein plasma.
Use of thiazides during pregnancy is associated with a risk of fetal or neonatal jaundice or thrombocytopenia. Since they do not prevent or alter the course of preeclampsia, these drugs should not be used to treat hypertension in pregnant women. The use of HCTZ for other indications (e.g., heart disease) in pregnancy should be avoided.
Data Animal Data Olmesartan No teratogenic effects were observed when olmesartan medoxomil was administered to pregnant rats at oral doses up to 1000 mg/kg/day (240 times the maximum recommended human dose [MRHD] on a mg/m 2 basis) or pregnant rabbits at oral doses up to 1 mg/kg/day (half the MRHD on a mg/m 2 basis; higher doses could not be evaluated for effects on fetal development as they were lethal to the does). In rats, significant decreases in pup birth weight and weight gain were observed at doses ≥1.6 mg/kg/day, and delays in developmental milestones (delayed separation of ear… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Olmesartan medoxomil and hydrochlorothiazide tablets can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue olmesartan medoxomil and hydrochlorothiazide tablets as soon as possible. Use alternative antihypertensive therapy during pregnancy. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2%–4% and 15%–20%, respectively. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section and post-partum hemorrhage).
Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Olmesartan Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death.
Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury.
Closely observe infants with histories of in utero exposure to olmesartan medoxomil and hydrochlorothiazide tablets for hypotension, oliguria, and hyperkalemia. If oliguria or hypotension occur, utilize measures to maintain adequate blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and supporting renal function [see Use in Specific Populations ( 8.4 )].
Hydrochlorothiazide Thiazides can cross the placenta, and concentrations reached in the umbilical vein approach those in the maternal plasma. Hydrochlorothiazide, like other diuretics, can cause placental hypoperfusion. It accumulates in the amniotic fluid, with reported concentrations up to 19 times that in umbilical vein plasma.
Use of thiazides during pregnancy is associated with a risk of fetal or neonatal jaundice or thrombocytopenia. Since they do not prevent or alter the course of preeclampsia, these drugs should not be used to treat hypertension in pregnant women. The use of HCTZ for other indications (e.g., heart disease) in pregnancy should be avoided.
Data Animal Data Olmesartan No teratogenic effects were observed when olmesartan medoxomil was administered to pregnant rats at oral doses up to 1000 mg/kg/day (240 times the maximum recommended human dose [MRHD] on a mg/m 2 basis) or pregnant rabbits at oral doses up to 1 mg/kg/day (half the MRHD on a mg/m 2 basis; higher doses could not be evaluated for effects on fetal development as they were lethal to the does). In rats, significant decreases in pup birth weight and weight gain were observed at doses ≥1.6 mg/kg/day, and delays in developmental milestones (delayed separation of ear auricula, eruption of lower incisors, appearance of abdominal hair, descent of tes… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of olmesartan medoxomil and hydrochlorothiazide tablets in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of olmesartan medoxomil and hydrochlorothiazide tablets did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal or cardiac function and of concomitant diseases or other drug therapy.
Olmesartan and hydrochlorothiazide are substantially excreted by the kidney, and the risk of toxic reactions to olmesartan medoxomil and hydrochlorothiazide tablets may be greater in patients with impaired renal function.
🆘 Overdosage ▾
10 OVERDOSAGE Olmesartan medoxomil Limited data are available related to overdosage of olmesartan medoxomil in humans. The most likely manifestations of overdosage would be hypotension and tachycardia; bradycardia could be encountered if parasympathetic (vagal) stimulation occurs. If symptomatic hypotension should occur, supportive treatment should be initiated.
The dialyzability of olmesartan is unknown. No lethality was observed in acute toxicity studies in mice and rats given single oral doses up to 2000 mg/kg olmesartan medoxomil. The minimum lethal oral dose of olmesartan medoxomil in dogs was greater than 1500 mg/kg.
Hydrochlorothiazide The most common signs and symptoms of hydrochlorothiazide overdose observed in humans are those caused by electrolyte depletion (hypokalemia, hypochloremia, hyponatremia) and dehydration resulting from excessive diuresis. If digitalis has also been administered, hypokalemia may accentuate cardiac arrhythmias. The degree to which hydrochlorothiazide is removed by hemodialysis has not been established.
The oral LD 50 of hydrochlorothiazide is greater than 10 g/kg in both mice and rats.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Olmesartan medoxomil Angiotensin II is formed from angiotensin I in a reaction catalyzed by angiotensin converting enzyme (ACE, kininase II). Angiotensin II is the principal pressor agent of the renin-angiotensin system, with effects that include vasoconstriction, stimulation of synthesis and release of aldosterone, cardiac stimulation and renal reabsorption of sodium. Olmesartan blocks the vasoconstrictor effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor in vascular smooth muscle.
Its action is, therefore, independent of the pathways for angiotensin II synthesis. An AT 2 receptor is found also in many tissues, but this receptor is not known to be associated with cardiovascular homeostasis. Olmesartan has more than a 12,500-fold greater affinity for the AT 1 receptor than for the AT 2 receptor.
Blockade of the angiotensin II receptor inhibits the negative regulatory feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity (PRA) and circulating angiotensin II levels do not overcome the effect of olmesartan on blood pressure. Hydrochlorothiazide Hydrochlorothiazide is a thiazide diuretic. Thiazides affect the renal tubular mechanisms of electrolyte reabsorption, directly increasing excretion of sodium and chloride in approximately equivalent amounts.
Indirectly, the diuretic action of hydrochlorothiazide reduces plasma volume, with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss, and decreases in serum potassium. The renin-aldosterone link is mediated by angiotensin II, so co-administration of an angiotensin II receptor antagonist tends to reverse the potassium loss associated with these diuretics. The mechanism of the antihypertensive effect of thiazides is not fully understood.
12.2Pharmacodynamics Olmesartan medoxomil Olmesartan medoxomil doses of 2.5 to 40 mg inhibit the pressor effects of angiotensin I infusion. The duration of the inhibitory effect was related to dose, with doses of olmesartan medoxomil >40 mg giving >90% inhibition at 24 hours. Plasma concentrations of angiotensin I and angiotensin II and plasma renin activity (PRA) increase after single and repeated administration of olmesartan medoxomil to healthy subjects and hypertensive patients.
Repeated administration of up to 80 mg olmesartan medoxomil had minimal influence on aldosterone levels and no effect on serum potassium. Hydrochlorothiazide After oral administration of hydrochlorothiazide, diuresis begins within 2 hours, peaks in about 4 hours and lasts about 6 to 12 hours. Drug Interactions Hydrochlorothiazide Alcohol, barbiturates, or narcotics: Potentiation of orthostatic hypotension may occur.
Skeletal muscle relaxants, non-depolarizing (e.g., tubocurarine): Increased responsiveness to the muscle relaxant may occur. Digitalis glycosides: Thiazide-induced hypokalemia or hypomagnesemia may predispose to digoxin toxicity.
12.3Pharmacokinetics Absorption Olmesartan: Olmesartan medoxomil is completely bioactivated by ester hydrolysis to olmesartan during absorption from the gastrointestinal tract. The absolute bioavailability of olmesartan is approximately 26%. After oral administration, the peak plasma concentration (C max ) of olmesartan is reached after 1 to 2 hours.
Food does not affect the bioavailability of olmesartan. Olmesartan shows linear pharmacokinetics following single oral doses of up to 320 mg and multiple oral doses of up to 80 mg. Steady-state levels of olmesartan are achieved within 3 to 5 days and no accumulation in plasma occurs with once-daily dosing.
Hydrochlorothiazide: The estimated absolute bioavailability of hydrochlorothiazide after oral administration is about 70%. Peak plasma hydrochlorothiazide concentrations (C max ) are reached within 2 to 5 hours after oral administration. There is no clinically significant effect… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Olmesartan medoxomil Angiotensin II is formed from angiotensin I in a reaction catalyzed by angiotensin converting enzyme (ACE, kininase II). Angiotensin II is the principal pressor agent of the renin-angiotensin system, with effects that include vasoconstriction, stimulation of synthesis and release of aldosterone, cardiac stimulation and renal reabsorption of sodium. Olmesartan blocks the vasoconstrictor effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor in vascular smooth muscle.
Its action is, therefore, independent of the pathways for angiotensin II synthesis. An AT 2 receptor is found also in many tissues, but this receptor is not known to be associated with cardiovascular homeostasis. Olmesartan has more than a 12,500-fold greater affinity for the AT 1 receptor than for the AT 2 receptor.
Blockade of the angiotensin II receptor inhibits the negative regulatory feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity (PRA) and circulating angiotensin II levels do not overcome the effect of olmesartan on blood pressure. Hydrochlorothiazide Hydrochlorothiazide is a thiazide diuretic. Thiazides affect the renal tubular mechanisms of electrolyte reabsorption, directly increasing excretion of sodium and chloride in approximately equivalent amounts.
Indirectly, the diuretic action of hydrochlorothiazide reduces plasma volume, with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss, and decreases in serum potassium. The renin-aldosterone link is mediated by angiotensin II, so co-administration of an angiotensin II receptor antagonist tends to reverse the potassium loss associated with these diuretics. The mechanism of the antihypertensive effect of thiazides is not fully understood.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Olmesartan medoxomil and hydrochlorothiazide tablets are supplied as follows: Olmesartan/HCTZ Shape Color Debossing Side 1 Side 2 20/12.5 mg Round Beige OLH Plain on other side 40/12.5 mg Oval Beige OLH 12.5 40/25 mg Oval Pink OLH 25 Tablets are packaged as follows: NDC 70756-xxx-xx 20/12.5 mg 40/12.5 mg 40/25 mg Bottle of 30 tablets 812-30 813-30 814-30 Bottle of 90 tablets 812-90 813-90 814-90 Bottle of 500 tablets 812-51 813-51 814-51 Bottle of 1000 tablets 812-12 813-12 814-12 Storage Store at 20°-25°C (68°-77°F) [ see USP Controlled Room Temperature ].
Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. Keep this and all medicines out of the reach of children.
📋 Description ▾
11 DESCRIPTION Olmesartan medoxomil and hydrochlorothiazide tablets are a combination of an angiotensin II receptor antagonist (AT 1 subtype), olmesartan medoxomil, and a thiazide diuretic, hydrochlorothiazide (HCTZ). Olmesartan medoxomil is 1H-Imidazole-5-Carboxylic Acid, 4-(1-Hydroxy-1-Methylethyl)-2-Propyl-1-[[2’-1H-Tetrazol-5yl)[1, 1’-Biphenyl]-4-yl]Methyl]-, (5-Methyl-2-Oxo-1, 3-Dioxol-4-yl) Methyl Ester. Its empirical formula is C 29 H 30 N 6 O 6 and its structural formula is: Olmesartan medoxomil is a white to off white powder with a molecular weight of 558.59.
It is slightly soluble in acetone and methanol, very slightly soluble in ethanol and practically insoluble in water. Hydrochlorothiazide is 6-chloro-3,4-dihydro-2 H -1,2,4-benzo-thiadiazine-7-sulfonamide 1,1-dioxide. Its empirical formula is C 7 H 8 ClN 3 O 4 S 2 and its structural formula is: Hydrochlorothiazide is a white, or practically white, practically odorless, crystalline powder with a molecular weight of 297.74.
Hydrochlorothiazide is freely soluble in sodium hydroxide solution, in n-butyl amine and in dimethylformamide; very slightly soluble in water, sparingly soluble in methanol, insoluble in ether, in chloroform and in dilute mineral acids. Olmesartan medoxomil and hydrochlorothiazide tablets are available for oral administration in tablets containing 20 mg or 40 mg of olmesartan medoxomil combined with 12.5 mg of hydrochlorothiazide, or 40 mg of olmesartan medoxomil combined with 25 mg of hydrochlorothiazide. Inactive ingredients include: hydroxy propyl cellulose, hypromellose, iron oxide red, iron oxide yellow, lactose monohydrate, low substituted hydroxy propyl cellulose, magnesium stearate, microcrystalline cellulose, talc and titanium dioxide. olme-hctz-structure-1 olme-hctz-structure-2
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Pregnancy: Advise female patients of childbearing age about the consequences of exposure to olmesartan medoxomil and hydrochlorothiazide tablets during pregnancy. Discuss treatment options with women planning to become pregnant. Tell patients to report pregnancies to their physicians as soon as possible [see Warnings and Precautions ( 5.1 )] and Use in Specific Populations ( 8.1 )].
Lactation: Advise nursing women not to breastfeed during treatment with olmesartan medoxomil and hydrochlorothiazide tablets [see Use in Specific Populations ( 8.2 )] . Symptomatic hypotension and syncope: Advise patients that lightheadedness can occur, especially during the first days of therapy, and to report this symptom to a healthcare provider. Inform patients that dehydration from inadequate fluid intake, excessive perspiration, vomiting, or diarrhea may lead to an excessive fall in blood pressure.
If syncope occurs advise patients, to contact their healthcare provider. Potassium Supplements: Advise patients not to use potassium supplements or salt substitutes containing potassium without consulting their healthcare provider. Acute myopia and secondary angle-closure glaucoma: Advise patients to discontinue olmesartan medoxomil and hydrochlorothiazide tablets and seek immediate medical attention if they experience symptoms of acute myopia or secondary angle-closure glaucoma [see Warnings and Precautions ( 5.6 )] .
Non-melanoma Skin Cancer: Instruct patients taking hydrochlorothiazide to protect skin from the sun and undergo regular skin cancer screening. Manufactured by: Umedica Laboratories Pvt. Ltd.
Plot No. 221 and 221/1, GIDC, IInd Phase Vapi, Gujarat 396195, India Made in India Manufactured for: Lifestar Pharma LLC 1200 MacArthur Blvd. Mahwah, NJ 07430 USA Revised: May 2025, V-05 *The other brands listed are trademarks of their respective owners and are not trademarks of Umedica Laboratories Pvt.
Ltd. The makers of these brands are not affiliated with and do not endorse Umedica Laboratories Pvt. Ltd. or its products.
🍼 Nursing Mothers ▾
8.2Lactation Risk Summary There is limited information regarding the presence of Olmesartan medoxomil and hydrochlorothiazide tablets in human milk, the effects on the breastfed infant, or the effects on milk production. Olmesartan is present in rat milk (see Data) . Hydrochlorothiazide is present in human milk.
Because of the potential for adverse effects on the nursing infant, advise a nursing woman that breastfeeding is not recommended during treatment with olmesartan medoxomil and hydrochlorothiazide tablets. Data Presence of olmesartan in milk was observed after a single oral administration of 5 mg/kg [ 14 C] olmesartan medoxomil to lactating rats.
🧬 Pharmacokinetics ▾
12.2Pharmacodynamics Olmesartan medoxomil Olmesartan medoxomil doses of 2.5 to 40 mg inhibit the pressor effects of angiotensin I infusion. The duration of the inhibitory effect was related to dose, with doses of olmesartan medoxomil >40 mg giving >90% inhibition at 24 hours. Plasma concentrations of angiotensin I and angiotensin II and plasma renin activity (PRA) increase after single and repeated administration of olmesartan medoxomil to healthy subjects and hypertensive patients.
Repeated administration of up to 80 mg olmesartan medoxomil had minimal influence on aldosterone levels and no effect on serum potassium. Hydrochlorothiazide After oral administration of hydrochlorothiazide, diuresis begins within 2 hours, peaks in about 4 hours and lasts about 6 to 12 hours. Drug Interactions Hydrochlorothiazide Alcohol, barbiturates, or narcotics: Potentiation of orthostatic hypotension may occur.
Skeletal muscle relaxants, non-depolarizing (e.g., tubocurarine): Increased responsiveness to the muscle relaxant may occur. Digitalis glycosides: Thiazide-induced hypokalemia or hypomagnesemia may predispose to digoxin toxicity.
🧬 Pharmacodynamics ▾
12.3Pharmacokinetics Absorption Olmesartan: Olmesartan medoxomil is completely bioactivated by ester hydrolysis to olmesartan during absorption from the gastrointestinal tract. The absolute bioavailability of olmesartan is approximately 26%. After oral administration, the peak plasma concentration (C max ) of olmesartan is reached after 1 to 2 hours.
Food does not affect the bioavailability of olmesartan. Olmesartan shows linear pharmacokinetics following single oral doses of up to 320 mg and multiple oral doses of up to 80 mg. Steady-state levels of olmesartan are achieved within 3 to 5 days and no accumulation in plasma occurs with once-daily dosing.
Hydrochlorothiazide: The estimated absolute bioavailability of hydrochlorothiazide after oral administration is about 70%. Peak plasma hydrochlorothiazide concentrations (C max ) are reached within 2 to 5 hours after oral administration. There is no clinically significant effect of food on the bioavailability of hydrochlorothiazide.
The pharmacokinetics of hydrochlorothiazide is dose proportional in the range of 12.5 to 75 mg. Distribution Olmesartan: The volume of distribution of olmesartan is approximately 17 L. Olmesartan is highly bound to plasma proteins (99%) and does not penetrate red blood cells.
The protein binding is constant at plasma olmesartan concentrations well above the range achieved with recommended doses. In rats, olmesartan crossed the blood-brain barrier poorly, if at all. Olmesartan passed across the placental barrier in rats and was distributed to the fetus.
Olmesartan was distributed to milk at low levels in rats. Hydrochlorothiazide: Hydrochlorothiazide binds to albumin (40 to 70%) and distributes into erythrocytes. Following oral administration, plasma hydrochlorothiazide concentrations decline bi-exponentially, with a mean distribution half-life of about 2 hours and an elimination half-life of about 10 hours.
Hydrochlorothiazide crosses the placental but not the blood-brain barrier and is excreted in breast milk. Metabolism Olmesartan: Olmesartan does not undergo further metabolism. Hydrochlorothiazide: Hydrochlorothiazide is not metabolized.
Elimination Olmesartan: Olmesartan appears to be eliminated in a biphasic manner with a terminal elimination half-life of approximately 13 hours. Total plasma clearance of olmesartan is
1.3 L/h, with a renal clearance of
0.6L/h. Approximately 35% to 50% of the absorbed dose is recovered in urine while the remainder is eliminated in feces via the bile. Hydrochlorothiazide: About 70% of an orally administered dose of hydrochlorothiazide is eliminated in the urine as unchanged drug.
Specific populations Olmesartan medoxomil Pediatric Patients: The pharmacokinetics of olmesartan were studied in pediatric hypertensive patients aged 1 to16 years. The clearance of olmesartan in pediatric patients was similar to that in adult patients when adjusted by the body weight. Olmesartan pharmacokinetics have not been investigated in pediatric patients less than 1 year of age.
Geriatric Patients: The pharmacokinetics of olmesartan were studied in the elderly (≥65 years). Overall, maximum plasma concentrations of olmesartan were similar in young adults and the elderly. Modest accumulation of olmesartan was observed in the elderly with repeated dosing; AUC ss, τ was 33% higher in elderly patients, corresponding to an approximate 30% reduction in CL R .
Male and Female Patients: Minor differences were observed in the pharmacokinetics of olmesartan in women compared to men. AUC and C max were 10-15% higher in women than in men. Patients with Renal Impairment: In patients with renal insufficiency, serum concentrations of olmesartan were elevated compared to subjects with normal renal function.
After repeated dosing, the AUC was approximately tripled in patients with severe renal impairment (creatinine clearance <20 mL/min). The pharmacokinetics of olmesartan in patients undergoing hemodialysis has not been studied. Patients with Hepa… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Olmesartan medoxomil and hydrochlorothiazide In clinical trials 1230 patients were exposed to the combination of olmesartan medoxomil (2.5 mg to 40 mg) and hydrochlorothiazide (12.5 mg to 25 mg). These trials included one placebo-controlled factorial trial in mild-moderate hypertensive patients (n=502) with combinations of olmesartan medoxomil (10 mg, 20 mg, 40 mg, or placebo) and hydrochlorothiazide (12.5 mg, 25 mg, or placebo). The antihypertensive effect of the combination on trough blood pressure was related to the dose of each component (see Table 2).
Once-daily dosing with 20 mg olmesartan medoxomil and 12.5 mg hydrochlorothiazide, 40 mg olmesartan medoxomil and 12.5 mg hydrochlorothiazide or 40 mg olmesartan medoxomil and 25 mg hydrochlorothiazide produced mean placebo-adjusted blood pressure reductions at trough (24 hours post-dosing) ranging from 17/8 to 24/14 mmHg. Table 2: Placebo-Adjusted Reductions in Sitting Systolic/Diastolic Blood Pressure (mmHg) HCTZ Olmesartan Medoxomil 0 mg 10 mg 20 mg 40 mg 0 mg -- 7/5 12/5 13/7 12.5 mg 5/1 17/8 17/8 16/10 25 mg 14/5 19/11 22/11 24/14 The antihypertensive effect had onset within 1 week and was near maximal at 4 weeks.
The antihypertensive effect was independent of gender, but there were too few subjects to identify response differences based on race or age greater than or less than 65 years. No appreciable changes in trough heart rate were observed with combination therapy. There are no trials of olmesartan medoxomil and hydrochlorothiazide tablets demonstrating reductions in cardiovascular risk in patients with hypertension, but at least one drug pharmacologically similar to olmesartan medoxomil has demonstrated such benefits, and hydrochlorothiazide demonstrated reduction of cardiovascular risk in patients with hypertension.
Olmesartan medoxomil The antihypertensive effects of olmesartan medoxomil have been demonstrated in seven placebo-controlled studies at doses ranging from 2.5 to 80 mg for 6 to 12 weeks, each showing statistically significant reductions in peak and trough blood pressure. A total of 2693 patients (2145 olmesartan medoxomil; 548 placebo) with essential hypertension were studied. Olmesartan medoxomil once daily (QD) lowered diastolic and systolic blood pressure.
The response was dose-related. An olmesartan medoxomil dose of 20 mg daily produced a trough sitting blood pressure (BP) reduction over placebo of about 10/6 mmHg, and a dose of 40 mg daily produced a trough sitting BP reduction over placebo of about 12/7 mmHg. Olmesartan medoxomil doses greater than 40 mg had little additional effect.
The onset of the antihypertensive effect occurred within 1 week and was largely manifest after 2 weeks. The blood pressure lowering effect was maintained throughout the 24-hour period with olmesartan medoxomil once daily, with trough-to-peak ratios for systolic and diastolic response between 60 and 80%. The blood pressure lowering effect of olmesartan medoxomil, with and without hydrochlorothiazide, was maintained in patients treated for up to 1 year.
There was no evidence of tachyphylaxis during long-term treatment with olmesartan medoxomil or rebound effect following abrupt withdrawal of olmesartan medoxomil after 1 year of treatment. The antihypertensive effect of olmesartan medoxomil was similar in men and women and in patients older and younger than 65 years. The effect was smaller in black patients (usually a low-renin population), as has been seen with other ACE inhibitors, angiotensin receptor blockers, and beta-blockers.
Olmesartan medoxomil had an additional blood pressure lowering effect when added to hydrochlorothiazide.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Olmesartan medoxomil and hydrochlorothiazide No carcinogenicity studies with olmesartan medoxomil and hydrochlorothiazide have been conducted. Olmesartan medoxomil and hydrochlorothiazide in a ratio of 20:12.5 were negative in the Salmonella-Escherichia coli/ mammalian microsome reverse mutation test up to the maximum recommended plate concentration for the standard assays. Olmesartan medoxomil and hydrochlorothiazide were tested individually and in combination ratios of 40:12.5, 20:12.5 and 10:12.5, for clastogenic activity in the in vitro Chinese hamster lung (CHL) chromosomal aberration assay.
A positive response was seen for each component and combination ratio. However, no synergism in clastogenic activity was detected between olmesartan medoxomil and hydrochlorothiazide at any combination ratio. Olmesartan medoxomil and hydrochlorothiazide in a ratio of 20:12.5, administered orally, tested negative in the in vivo mouse bone marrow erythrocyte micronucleus assay at administered doses of up to 3144 mg/kg.
No studies of impairment of fertility with olmesartan medoxomil and hydrochlorothiazide have been conducted. Olmesartan medoxomil Olmesartan medoxomil was not carcinogenic when administered by dietary administration to rats for up to 2 years. The highest dose tested (2000 mg/kg/day) was, on a mg/m 2 basis, about 480 times the maximum recommended human dose (MRHD) of 40 mg/day.
Two carcinogenicity studies conducted in mice, a 6-month gavage study in the p53 knockout mouse and a 6-month dietary administration study in the Hras2 transgenic mouse, at doses of up to 1000 mg/kg/day (about 120 times the MRHD), revealed no evidence of a carcinogenic effect of olmesartan medoxomil. Both olmesartan medoxomil and olmesartan tested negative in the in vitro Syrian hamster embryo cell transformation assay and showed no evidence of genetic toxicity in the Ames (bacterial mutagenicity) test. However, both were shown to induce chromosomal aberrations in cultured cells in vitro (Chinese hamster lung), and both tested positive for thymidine kinase mutations in the in vitro mouse lymphoma assay.
Olmesartan medoxomil tested negative in vivo for mutations in the MutaMouse intestine and kidney, and for clastogenicity in mouse bone marrow (micronucleus test) at oral doses of up to 2000 mg/kg (olmesartan not tested). Fertility of rats was unaffected by administration of olmesartan medoxomil at dose levels as high as 1000 mg/kg/day (240 times the MRHD) in a study in which dosing was begun 2 (female) or 9 (male) weeks prior to mating. Hydrochlorothiazide Two-year feeding studies in mice and rats conducted under the auspices of the National Toxicology Program (NTP) uncovered no evidence of a carcinogenic potential of hydrochlorothiazide in female mice (at doses of up to approximately 600 mg/kg/day) or in male and female rats (at doses of up to approximately 100 mg/kg/day).
The NTP, however, found equivocal evidence for hepatocarcinogenicity in male mice. Hydrochlorothiazide was not genotoxic in vitro in the Ames mutagenicity assay of Salmonella typhimurium strains TA 98, TA 100, TA 1535, TA 1537 and TA 1538, or in the Chinese Hamster Ovary (CHO) test for chromosomal aberrations. It was also not genotoxic in vivo in assays using mouse germinal cell chromosomes, Chinese hamster bone marrow chromosomes, or the Drosophila sex-linked recessive lethal trait gene.
Positive test results were obtained in the in vitro CHO Sister Chromatid Exchange (clastogenicity) assay, the Mouse Lymphoma Cell (mutagenicity) assay and the Aspergillus nidulans non-disjunction assay. Hydrochlorothiazide had no adverse effects on the fertility of mice and rats of either sex in studies wherein these species were exposed, via their diet, to doses of up to 100 and 4 mg/kg, respectively, prior to mating and throughout gestation.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Olmesartan medoxomil and hydrochlorothiazide No carcinogenicity studies with olmesartan medoxomil and hydrochlorothiazide have been conducted. Olmesartan medoxomil and hydrochlorothiazide in a ratio of 20:12.5 were negative in the Salmonella-Escherichia coli/ mammalian microsome reverse mutation test up to the maximum recommended plate concentration for the standard assays. Olmesartan medoxomil and hydrochlorothiazide were tested individually and in combination ratios of 40:12.5, 20:12.5 and 10:12.5, for clastogenic activity in the in vitro Chinese hamster lung (CHL) chromosomal aberration assay.
A positive response was seen for each component and combination ratio. However, no synergism in clastogenic activity was detected between olmesartan medoxomil and hydrochlorothiazide at any combination ratio. Olmesartan medoxomil and hydrochlorothiazide in a ratio of 20:12.5, administered orally, tested negative in the in vivo mouse bone marrow erythrocyte micronucleus assay at administered doses of up to 3144 mg/kg.
No studies of impairment of fertility with olmesartan medoxomil and hydrochlorothiazide have been conducted. Olmesartan medoxomil Olmesartan medoxomil was not carcinogenic when administered by dietary administration to rats for up to 2 years. The highest dose tested (2000 mg/kg/day) was, on a mg/m 2 basis, about 480 times the maximum recommended human dose (MRHD) of 40 mg/day.
Two carcinogenicity studies conducted in mice, a 6-month gavage study in the p53 knockout mouse and a 6-month dietary administration study in the Hras2 transgenic mouse, at doses of up to 1000 mg/kg/day (about 120 times the MRHD), revealed no evidence of a carcinogenic effect of olmesartan medoxomil. Both olmesartan medoxomil and olmesartan tested negative in the in vitro Syrian hamster embryo cell transformation assay and showed no evidence of genetic toxicity in the Ames (bacterial mutagenicity) test. However, both were shown to induce chromosomal aberrations in cultured cells in vitro (Chinese hamster lung), and both tested positive for thymidine kinase mutations in the in vitro mouse lymphoma assay.
Olmesartan medoxomil tested negative in vivo for mutations in the MutaMouse intestine and kidney, and for clastogenicity in mouse bone marrow (micronucleus test) at oral doses of up to 2000 mg/kg (olmesartan not tested). Fertility of rats was unaffected by administration of olmesartan medoxomil at dose levels as high as 1000 mg/kg/day (240 times the MRHD) in a study in which dosing was begun 2 (female) or 9 (male) weeks prior to mating. Hydrochlorothiazide Two-year feeding studies in mice and rats conducted under the auspices of the National Toxicology Program (NTP) uncovered no evidence of a carcinogenic potential of hydrochlorothiazide in female mice (at doses of up to approximately 600 mg/kg/day) or in male and female rats (at doses of up to approximately 100 mg/kg/day).
The NTP, however, found equivocal evidence for hepatocarcinogenicity in male mice. Hydrochlorothiazide was not genotoxic in vitro in the Ames mutagenicity assay of Salmonella typhimurium strains TA 98, TA 100, TA 1535, TA 1537 and TA 1538, or in the Chinese Hamster Ovary (CHO) test for chromosomal aberrations. It was also not genotoxic in vivo in assays using mouse germinal cell chromosomes, Chinese hamster bone marrow chromosomes, or the Drosophila sex-linked recessive lethal trait gene.
Positive test results were obtained in the in vitro CHO Sister Chromatid Exchange (clastogenicity) assay, the Mouse Lymphoma Cell (mutagenicity) assay and the Aspergillus nidulans non-disjunction assay. Hydrochlorothiazide had no adverse effects on the fertility of mice and rats of either sex in studies wherein these species were exposed, via their diet, to doses of up to 100 and 4 mg/kg, respectively, prior to mating and throughout gestation.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL Olmesartan Medoxomil and Hydrochlorothiazide Tablets 20 mg/12.5 mg- NDC 70756-812-30 -30s Bottle Label Olmesartan Medoxomil and Hydrochlorothiazide Tablets 40 mg/12.5 mg- NDC 70756-813-90 -90s Bottle Label Olmesartan Medoxomil and Hydrochlorothiazide Tablets 40 mg/25 mg- NDC 70756-814-12 -1000s Bottle Label Olmesartan Medoxomil and Hydrochlorothiazide Tablets 20mg/12.5mg 30s Olmesartan Medoxomil and Hydrochlorothiazide Tablets 40mg/12.5mg 90s Olmesartan Medoxomil and Hydrochlorothiazide Tablets 40 mg/25 mg 1000s