
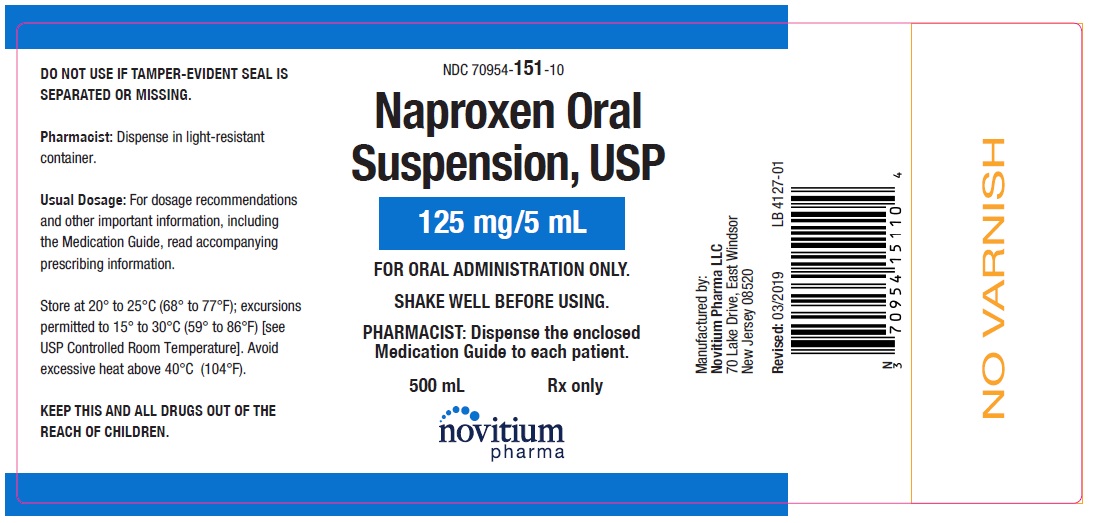
Naproxen Oral Suspension 125 mg/5mL Suspension, 500 mL
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Nonsteroidal Anti-inflammatory Drug class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Prescription naproxen is used to relieve pain, tenderness, swelling, and stiffness caused by osteoarthritis (arthritis caused by a breakdown of the lining of the joints), rheumatoid arthritis (arthritis caused by swelling of the lining of the joints), juvenile arthritis (a form of joint disease in children), and ankylosing spondylitis (arthritis that mainly affects the spine). Prescription naproxen tablets, extended-release tablets, and suspension are also used to relieve shoulder pain caused by bursitis (inflammation of a fluid-filled sac in the shoulder joint), tendinitis (inflammation of th...
Read the full MedlinePlus article ↗- They're very similar — naproxen sodium is just the salt form of naproxen, and it dissolves in water more quickly. That means your body absorbs naproxen sodium a bit faster, so it t...
- What's the difference between naproxen and naproxen sodium — are they the same thing?
- You can take it either way, but taking it with food, milk, or a full glass of water is a good idea because it helps protect your stomach. Naproxen can irritate the lining of your s...
- Can I take naproxen on an empty stomach, or do I need to eat first?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII K679OBS311
Carboxymethylcellulose sodium is a plant-derived thickening agent made from cellulose. In medicines, it acts as a binder to hold ingredients together, a disintegrant to help the tablet break apart, or a thickener in liquids.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII 88XHZ13131
Fumaric acid is an organic acid used in medications as a buffer and pH regulator. It helps maintain the proper acidity level in the medicine and may aid in tablet disintegration.
-
UNII 8136Y38GY5
A plant-derived thickening agent made from cellulose. It increases the thickness and consistency of liquid medicines, helping them coat surfaces and flow smoothly.
-
UNII A2I8C7HI9T
Methylparaben is a preservative derived from benzoic acid that prevents growth of bacteria, fungi, and mold in medicines. It extends the product's shelf life and maintains safety during storage.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.191 | $95.60 / 500 ml |
| Medicaid paysCMS SDUD · 12 mo | $0.3352 | $167.60 / 500 ml |
| Medicare drug plans payPart D · Q2 2026 | $0.4321 | $216.05 / 500 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Naproxen 125 mg/5mL 42192-0619-16 | Acella | 473 ml | $0.117 | AB | Availability likely | save 39% |
| Naproxen 25 mg/mL 69238-1730-02 | Amneal | 473 ml | $0.117 | AB | Availability likely | save 39% |
| Naproxen 125 mg/5mL 00054-3630-63 | Hikma | 500 ml | $0.191 | AB | Availability likely | — |
| Naproxen 25 mg/mL 31722-0682-05 | Camber | 500 ml | $0.191 | AB | Availability likely | — |
| Naproxen Oral Suspension 125 mg/5mLthis 70954-0151-10 | ANI | 500 ml | $0.191 | AB | Availability likely | — |
| Naproxen 125 mg/5mL 59651-0528-47 | Aurobindo | 1 bottle | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 70954-0151-10 You're viewing this | 500 mL in 1 BOTTLE (70954-151-10) | 2021-03-12 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
BOXED WARNING WARNING: RISK OF SERIOUS CARDIOVASCULAR AND GASTROINTESTINAL EVENTS Cardiovascular Thrombotic Events Nonsteroidal anti-inflammatory drugs (NSAIDs) cause an increased risk of serious cardiovascular thrombotic events, including myocardial infarction and stroke, which can be fatal. This risk may occur early in treatment and may increase with duration of use [see Warnings and Precautions (5.1)]. Naproxen oral suspension is contraindicated in the setting of coronary artery bypass graft (CABG) surgery [see Contraindications (4), Warnings and Precautions (5.1)].
Gastrointestinal Bleeding, Ulceration, and Perforation NSAIDs cause an increased risk of serious gastrointestinal (GI) adverse events including bleeding, ulceration, and perforation of the stomach or intestines, which can be fatal. These events can occur at any time during use and without warning symptoms. Elderly patients and patients with a prior history of peptic ulcer disease and/or GI bleeding are at greater risk for serious GI events [see Warnings and Precautions (5.2)].
WARNING: RISK OF SERIOUS CARDIOVASCULAR AND GASTROINTESTINAL EVENTS See full prescribing information for complete boxed warning. Nonsteroidal anti-inflammatory drugs (NSAIDs) cause an increased risk of serious cardiovascular thrombotic events, including myocardial infarction and stroke, which can be fatal. This risk may occur early in treatment and may increase with duration of use.
(5.1) Naproxen oral suspension is contraindicated in the setting of coronary artery bypass graft (CABG) surgery. (4, 5.1) NSAIDs cause an increased risk of serious gastrointestinal (GI) adverse events including bleeding, ulceration, and perforation of the stomach or intestines, which can be fatal. These events can occur at any time during use and without warning symptoms.
Elderly patients and patients with a prior history of peptic ulcer disease and/or GI bleeding are at greater risk for serious GI events. (5.2)
🎯 Indications and Usage ▾
1 INDICATIONS & USAGE Naproxen oral suspension is indicated for: the relief of the signs and symptoms of: rheumatoid arthritis osteoarthritis ankylosing spondylitis polyarticular juvenile idiopathic arthritis tendonitis bursitis acute gout the management of: pain. primary dysmenorrhea Naproxen oral suspension is a non-steroidal anti-inflammatory drug indicated for: the relief of the signs and symptoms of: rheumatoid arthritis osteoarthritis ankylosing spondylitis polyarticular juvenile idiopathic arthritis tendonitis bursitis acute gout the management of: pain. primary dysmenorrhea
⏱️ Dosage and Administration ▾
2 DOSAGE & ADMINISTRATION Use the lowest effective dose for shortest duration consistent with individual patient treatment goals. (2) Rheumatoid Arthritis, Osteoarthritis, and Ankylosing Spondylitis Naproxen oralsuspension 250 mg (10 mL) twice daily or 375 mg (15 mL) twice daily or 500 mg (20 mL) twice daily The dose may be adjusted up or down depending on the clinical response of the patient. In patients who tolerate lower doses well, the dose may be increased to naproxen 1500 mg/day for up to 6 months.
Polyarticular Juvenile Idiopathic Arthritis Recommended total daily dose of naproxen is approximately 10 mg/kg given in 2 divided doses. The following table may be used as a guide for dosing of naproxen oral suspension: Patient's Weight Dose Administered as 13 kg (29 lb) 62.5 mg twice daily 2.5 mL (1/2 tsp) twice daily 25 kg (55 lb) 125 mg twice daily 5 mL (1 tsp) twice daily 38 kg (84 lb) 187.5 mg twice daily 7.5 mL (1 1/2 tsp) twice daily Management of Pain, Primary Dysmenorrhea, and Acute Tendonitis and Bursitis The recommended starting dose of naproxen oral suspension is 500 mg (20 mL), followed by 250 mg (10 mL) every 6 to 8 hours as required.
Acute Gout The recommended starting dose is 750 mg (30 mL) of naproxen oral suspension followed by 250 mg (10 mL) every 8 hours until the attack has subsided
2.1General Dosing Instructions Carefully consider the potential benefits and risks of naproxen oral suspension and other treatment options before deciding to use naproxen oral suspension. Use the lowest effective dose for the shortest duration consistent with individual patient treatment goals [see Warnings and Precautions (5)]. After observing the response to initial therapy with naproxen oral suspension, the dose and frequency should be adjusted to suit an individual patient’s needs.
Always use a calibrated measuring device when administering naproxen oral suspension to ensure the dose is measured and administered accurately. A household teaspoon or tablespoon is not an adequate measuring device, especially when one-half of a teaspoonful is to be measured. Given the variability of the household spoon measure, it is strongly recommended that caregivers obtain and use a calibrated measuring device.
Health care providers should recommend an appropriate measuring device that can measure and deliver the prescribed dose accurately, and instruct caregivers to use extreme caution in measuring the dosage. Naproxen-containing products such as naproxen oral suspension and other naproxen products should not be used concomitantly since they all circulate in the plasma as the naproxen anion.
2.2Rheumatoid Arthritis, Osteoarthritis and Ankylosing Spondylitis The recommended dosage of naproxen oral suspension is shown in Table 1. Table 1: Recommended dosages of naproxen oral suspension Naproxen oral suspension 250 mg (10 mL) twice daily or 375 mg (15 mL) twice daily or 500 mg (20 mL) twice daily Naproxen oral suspension should be shaken gently before use. During long-term administration, the dose of naproxen may be adjusted up or down depending on the clinical response of the patient.
A lower daily dose may suffice for long-term administration. The morning and evening doses do not have to be equal in size and administration of the drug more frequently than twice daily does not generally make a difference in response. In patients who tolerate lower doses well, the dose may be increased to naproxen 1500 mg/day for limited periods of up to 6 months when a higher level of anti-inflammatory/analgesic activity is required.
When treating such patients with naproxen 1500 mg/day, the physician should observe sufficient increased clinical benefits to offset the potential increased risk.
2.3Polyarticular Juvenile Idiopathic Arthritis The use of naproxen oral suspension is recommended for juvenile arthritis in children 2 years or older because it allows for more flexible dose titration based on the child’s weight. In pediatric patients, doses of 5 mg…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS & STRENGTHS Naproxen oral suspension, USP: 125 mg/5 mL (contains 39 mg sodium): Available in 500 mL light-resistant bottles Naproxen oral suspension: 125 mg/5 mL (contains 39 mg sodium)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Naproxen oral suspension is contraindicated in the following patients: Known hypersensitivity (e.g., anaphylactic reactions and serious skin reactions) to naproxen or any components of the drug product [see Warnings and Precautions (5.7,5.9)] History of asthma, urticaria, or other allergic-type reactions after taking aspirin or other NSAIDs. Severe, sometimes fatal, anaphylactic reactions to NSAIDs have been reported in such patients [see Warnings and Precautions (5.7,5.8)] In the setting of coronary artery bypass graft (CABG) surgery [see Warnings and Precautions (5.1)] • Known hypersensitivity to naproxen or any components of the drug product • History of asthma, urticaria, or other allergic-type reactions after taking aspirin or other NSAIDs • In the setting of CABG surgery
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hepatotoxicity : Inform patients of warning signs and symptoms of hepatotoxicity. Discontinue if abnormal liver tests persist or worsen or if clinical signs and symptoms of liver disease develop. (5.3) Hypertension : Patients taking some antihypertensive medications may have impaired response to these therapies when taking NSAIDs.
Monitor blood pressure. (5.4, 7) Heart Failure and Edema: Avoid use of naproxen oral suspension in patients with severe heart failure unless benefits are expected to outweigh risk of worsening heart failure. (5.5) Renal Toxicity : Monitor renal function in patients with renal or hepatic impairment, heart failure, dehydration, or hypovolemia.
Avoid use of naproxen oral suspension in patients with advanced renal disease unless benefits are expected to outweigh risk of worsening renal function. (5.6) Anaphylactic Reactions: Seek emergency help if an anaphylactic reaction occurs. (5.7) Exacerbation of Asthma Related to Aspirin Sensitivity: Naproxen oral suspension is contraindicated in patients with aspirin-sensitive asthma.
Monitor patients with preexisting asthma (without aspirin sensitivity). (5.8) Serious Skin Reactions : Discontinue naproxen oral suspension at first appearance of skin rash or other signs of hypersensitivity. (5.9) Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS) : Discontinue and evaluate clinically (5.10).
Fetal Toxicity : Limit use of NSAIDs, including naproxen oral suspension, between about 20 to 30 weeks in pregnancy due to the risk of oligohydramnios/fetal dysfunction. Avoid use of NSAIDs in women at about 30 weeks gestation and later in pregnancy due to the risks of oligohydramnios/fetal renal dysfunction and premature closure of the fetal ductus arteriosus. (5.11, 8.1) Hematologic Toxicity : Monitor hemoglobin or hematocrit in patients with any signs or symptoms of anemia.
(5.12, 7)
5.1Cardiovascular Thrombotic Events Clinical trials of several COX-2 selective and nonselective NSAIDs of up to three years duration have shown an increased risk of serious cardiovascular (CV) thrombotic events, including myocardial infarction (MI) and stroke, which can be fatal. Based on available data, it is unclear that the risk for CV thrombotic events is similar for all NSAIDs. The relative increase in serious CV thrombotic events over baseline conferred by NSAID use appears to be similar in those with and without known CV disease or risk factors for CV disease.
However, patients with known CV disease or risk factors had a higher absolute incidence of excess serious CV thrombotic events, due to their increased baseline rate. Some observational studies found that this increased risk of serious CV thrombotic events began as early as the first weeks of treatment. The increase in CV thrombotic risk has been observed most consistently at higher doses.
To minimize the potential risk for an adverse CV event in NSAID-treated patients, use the lowest effective dose for the shortest duration possible. Physicians and patients should remain alert for the development of such events, throughout the entire treatment course, even in the absence of previous CV symptoms. Patients should be informed about the symptoms of serious CV events and the steps to take if they occur.
There is no consistent evidence that concurrent use of aspirin mitigates the increased risk of serious CV thrombotic events associated with NSAID use. The concurrent use of aspirin and an NSAID, such as naproxen, increases the risk of serious gastrointestinal (GI) events [see Warnings and Precautions (5.2)]. Status Post Coronary Artery Bypass Graft (CABG) Surgery Two large, controlled clinical trials of a COX-2 selective NSAID for the treatment of pain in the first 10 to 14 days following CABG surgery found an increased incidence of myocardial infarction and stroke.
NSAIDs are contraindicated in the setting of CABG [see Contraindications (4)]. Post-MI Patients Observational studies conducted in the D…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: Cardiovascular Thrombotic Events [ see Warnings and Precautions (5.1)] GI Bleeding, Ulceration and Perforation [ see Warnings and Precautions (5.2) ] Hepatotoxicity [ see Warnings and Precautions (5.3) ] Hypertension [ see Warnings and Precautions (5.4) ] Heart Failure and Edema [ see Warnings and Precautions (5.5) ] Renal Toxicity and Hyperkalemia [ see Warnings and Precautions (5.6) ] Anaphylactic Reactions [ see Warnings and Precautions (5.7) ] Serious Skin Reactions [ see Warnings and Precautions (5.9) ] Hematologic Toxicity [ see Warnings and Precautions (5.12) ] Most common adverse reactions to naproxen were dyspepsia, abdominal pain, nausea, headache, rash, ecchymosis, and edema.
(6.1) To report SUSPECTED ADVERSE REACTIONS, contact Novitium Pharma LLC at 1-855-204-1431 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse reactions reported in controlled clinical trials in 960 patients treated for rheumatoid arthritis or osteoarthritis are listed below. In general, reactions in patients treated chronically were reported 2 to 10 times more frequently than they were in short-term studies in the 962 patients treated for mild to moderate pain or for dysmenorrhea.
The most frequent complaints reported related to the gastrointestinal tract. A clinical study found gastrointestinal reactions to be more frequent and more severe in rheumatoid arthritis patients taking daily doses of 1500 mg naproxen compared to those taking 750 mg naproxen. In controlled clinical trials with about 80 pediatric patients and in well-monitored, open-label studies with about 400 pediatric patients with polyarticular juvenile idiopathic arthritis treated with naproxen, the incidence of rash and prolonged bleeding times were greater, the incidence of gastrointestinal and central nervous system reactions were about the same, and the incidence of other reactions were lower in pediatric patients than in adults.
In patients taking naproxen in clinical trials, the most frequently reported adverse experiences in approximately 1% to 10% of patients are: Gastrointestinal (GI) Experiences, including : heartburn*, abdominal pain*, nausea*, constipation*, diarrhea, dyspepsia, stomatitis Central Nervous System : headache*, dizziness*, drowsiness*, lightheadedness, vertigo Dermatologic : pruritus (itching)*, skin eruptions*, ecchymoses*, sweating, purpura Special Senses : tinnitus*, visual disturbances, hearing disturbances Cardiovascular : edema*, palpitations General: dyspnea*, thirst *Incidence of reported reaction between 3% and 9%.
Those reactions occurring in less than 3% of the patients are unmarked. In patients taking NSAIDs, the following adverse experiences have also been reported in approximately 1% to 10% of patients. Gastrointestinal (GI) Experiences, including : flatulence, gross bleeding/perforation, GI ulcers (gastric/duodenal), vomiting General: abnormal renal function, anemia, elevated liver enzymes, increased bleeding time, rashes
6.2Postmarketing Experience The following adverse reactions have been identified during post approval use of naproxen. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. The following are additional adverse experiences reported in <1% of patients taking naproxen during clinical trials and through postmarketing reports.
Those adverse reactions observed through postmarketing reports are italicized. Body as a Whole : anaphylactoid reactions, angioneurotic edema, m…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS See Table 1 for clinically significant drug interactions with naproxen. Table 1: Clinically Significant Drug Interactions with Naproxen. Drugs That Interfere with Hemostasis Clinical Impact: Naproxen and anticoagulants such as warfarin have a synergistic effect on bleeding.
The concomitant use of naproxen and anticoagulants have an increased risk of serious bleeding compared to the use of either drug alone. Serotonin release by platelets plays an important role in hemostasis. Case- control and cohort epidemiological studies showed that concomitant use of drugs that interfere with serotonin reuptake and an NSAID may potentiate the risk of bleeding more than an NSAID alone.
Intervention: Monitor patients with concomitant use of naproxen oral suspension with anticoagulants (e.g., warfarin), antiplatelet agents (e.g., aspirin), selective serotonin reuptake inhibitors (SSRIs), and serotonin norepinephrine reuptake inhibitors (SNRIs) for signs of bleeding [ see Warnings and Precautions (5.12) ]. Aspirin Clinical Impact: A pharmacodynamic (PD) study has demonstrated an interaction in which lower dose naproxen (220mg/day or 220mg twice daily) interfered with the antiplatelet effect of low-dose immediate-release aspirin, with the interaction most marked during the washout period of naproxen [ see Clinical Pharmacology (12.2 )].
There is reason to expect that the interaction would be present with prescription doses of naproxen or with enteric-coated low-dose aspirin; however, the peak interference with aspirin function may be later than observed in the PD study due to the longer washout period. Controlled clinical studies showed that the concomitant use of NSAIDs and analgesic doses of aspirin does not produce any greater therapeutic effect than the use of NSAIDs alone. In a clinical study, the concomitant use of an NSAID and aspirin was associated with a significantly increased incidence of GI adverse reactions as compared to use of the NSAID alone [ see Warnings and Precautions (5.2) ].
Intervention: Because there may be an increased risk of cardiovascular events following discontinuation of naproxen due to the interference with the antiplatelet effect of aspirin during the washout period, for patients taking low-dose aspirin for cardioprotection who require intermittent analgesics, consider use of an NSAID that does not interfere with the antiplatelet effect of aspirin, or non-NSAID analgesics where appropriate. Concomitant use of naproxen oral suspension and analgesic doses of aspirin is not generally recommended because of the increased risk of bleeding [ see Warnings and Precautions (5.12) ] .
Naproxen oral suspension is not a substitute for low dose aspirin for cardiovascular protection. ACE Inhibitors, Angiotensin Receptor Blockers, and Beta-Blockers Clinical Impact: NSAIDs may diminish the antihypertensive effect of angiotensin converting enzyme (ACE) inhibitors, angiotensin receptor blockers (ARBs), or beta-blockers (including propranolol). In patients who are elderly, volume-depleted (including those on diuretic therapy), or have renal impairment, co-administration of an NSAID with ACE inhibitors or ARBs may result in deterioration of renal function, including possible acute renal failure.
These effects are usually reversible. Intervention: During concomitant use of naproxen oral suspension and ACE-inhibitors, ARBs, or beta-blockers, monitor blood pressure to ensure that the desired blood pressure is obtained. During concomitant use of naproxen oral suspension and ACE-inhibitors or ARBs in patients who are elderly, volume-depleted, or have impaired renal function, monitor for signs of worsening renal function [ see Warnings and Precautions (5.6 Renal Toxicity and Hyperkalemia) ].
When these drugs are administered concomitantly, patients should be adequately hydrated. Assess renal function at the beginning of the concomitant treatment and periodically thereafter. Diuretics Clinical Impact: Clinical studies,…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Infertility : NSAIDs are associated with reversible infertility. Consider withdrawal of naproxen oral suspension in women who have difficulties conceiving. (8.3) Renal Impairment: Naproxen-containing products are not recommended for use in patients with moderate to severe and severe renal impairment (creatinine clearance <30 mL/min). (8.7)
8.1Pregnancy Risk Summary Use of NSAIDs, including naproxen oral suspension, can cause premature closure of the fetal ductus arteriosus and fetal renal dysfunction leading to oligohydramnios and, in some cases, neonatal renal impairment. Because of these risks, limit dose and duration of naproxen oral suspension use between about 20 and 30 weeks of gestation, and avoid naproxen oral suspension use at about 30 weeks of gestation and later in pregnancy (see Clinical Considerations, Data). Premature Closure of Fetal Ductus Arteriosus Use of NSAIDs, including naproxen oral suspension, at about 30 weeks gestation or later in pregnancy increases the risk of premature closure of the fetal ductus arteriosus.
Oligohydramnios/Neonatal Renal Impairment Use of NSAIDs at about 20 weeks gestation or later in pregnancy has been associated with cases of fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment. Data from observational studies regarding other potential embryofetal risks of NSAID use in women in the first or second trimesters of pregnancy are inconclusive. In animal reproduction studies in rats, rabbits, and mice no evidence of teratogenicity or fetal harm when naproxen was administered during the period of organogenesis at doses 0.13, 0.26, and 0.6 times the maximum recommended human daily dose of 1500 mg/day, respectively.
Based on animal data, prostaglandins have been shown to have an important role in endometrial vascular permeability, blastocyst implantation, and decidualization. In animal studies, administration of prostaglandin synthesis inhibitors such as naproxen, resulted in increased pre-and post-implantation loss. Prostaglandins also have been shown to have an important role in fetal kidney development.
In published animal studies, prostaglandin synthesis inhibitors have been reported to impair kidney development when administered at clinically relevant doses. The estimated background risk of major birth defects and miscarriage for the indicated population(s) is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Premature Closure of Fetal Ductus Arteriosus Avoid use of NSAIDs in women at about 30 weeks gestation and later in pregnancy, because NSAIDs, including naproxen oral suspension, can cause premature closure of the fetal ductus arteriosus (see Data). Oligohydramnios/Neonatal Renal Impairment If an NSAID is necessary at about 20 weeks gestation or later in pregnancy, limit the use to the lowest effective dose and shortest duration possible.
If naproxen oral suspension treatment extends beyond 48 hours, consider monitoring with ultrasound for oligohydramnios. If oligohydramnios occurs, discontinue naproxen oral suspension, and follow up according to clinical practice (see Data). Labor or Delivery There are no studies on the effects of naproxen oral suspension during labor or delivery.
In animal studies, NSAIDS, including naproxen, inhibit prostaglandin synthesis, cause delayed parturition, and increase the incidence of stillbirth. Data Human Data There is some evidence to suggest that when inhibitors of prostaglandin synthesis are used to delay preterm labor there is an increased risk of neonatal complications such as necrotizing enterocolitis, patent ductus arteriosus and intracranial hemorrhage. Naproxen treatment given in late…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Use of NSAIDs, including naproxen oral suspension, can cause premature closure of the fetal ductus arteriosus and fetal renal dysfunction leading to oligohydramnios and, in some cases, neonatal renal impairment. Because of these risks, limit dose and duration of naproxen oral suspension use between about 20 and 30 weeks of gestation, and avoid naproxen oral suspension use at about 30 weeks of gestation and later in pregnancy (see Clinical Considerations, Data). Premature Closure of Fetal Ductus Arteriosus Use of NSAIDs, including naproxen oral suspension, at about 30 weeks gestation or later in pregnancy increases the risk of premature closure of the fetal ductus arteriosus.
Oligohydramnios/Neonatal Renal Impairment Use of NSAIDs at about 20 weeks gestation or later in pregnancy has been associated with cases of fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment. Data from observational studies regarding other potential embryofetal risks of NSAID use in women in the first or second trimesters of pregnancy are inconclusive. In animal reproduction studies in rats, rabbits, and mice no evidence of teratogenicity or fetal harm when naproxen was administered during the period of organogenesis at doses 0.13, 0.26, and 0.6 times the maximum recommended human daily dose of 1500 mg/day, respectively.
Based on animal data, prostaglandins have been shown to have an important role in endometrial vascular permeability, blastocyst implantation, and decidualization. In animal studies, administration of prostaglandin synthesis inhibitors such as naproxen, resulted in increased pre-and post-implantation loss. Prostaglandins also have been shown to have an important role in fetal kidney development.
In published animal studies, prostaglandin synthesis inhibitors have been reported to impair kidney development when administered at clinically relevant doses. The estimated background risk of major birth defects and miscarriage for the indicated population(s) is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Premature Closure of Fetal Ductus Arteriosus Avoid use of NSAIDs in women at about 30 weeks gestation and later in pregnancy, because NSAIDs, including naproxen oral suspension, can cause premature closure of the fetal ductus arteriosus (see Data). Oligohydramnios/Neonatal Renal Impairment If an NSAID is necessary at about 20 weeks gestation or later in pregnancy, limit the use to the lowest effective dose and shortest duration possible.
If naproxen oral suspension treatment extends beyond 48 hours, consider monitoring with ultrasound for oligohydramnios. If oligohydramnios occurs, discontinue naproxen oral suspension, and follow up according to clinical practice (see Data). Labor or Delivery There are no studies on the effects of naproxen oral suspension during labor or delivery.
In animal studies, NSAIDS, including naproxen, inhibit prostaglandin synthesis, cause delayed parturition, and increase the incidence of stillbirth. Data Human Data There is some evidence to suggest that when inhibitors of prostaglandin synthesis are used to delay preterm labor there is an increased risk of neonatal complications such as necrotizing enterocolitis, patent ductus arteriosus and intracranial hemorrhage. Naproxen treatment given in late pregnancy to delay parturition has been associated with persistent pulmonary hypertension, renal dysfunction and abnormal prostaglandin E levels in preterm infants.
Because of the known effects of nonsteroidal anti-inflammatory drugs on the fetal cardiovascular system (closure of ductus arteriosus), use during pregnancy (particularly starting at 30 weeks of gestation,…
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients below the age of 2 years have not been established. Pediatric dosing recommendations for polyarticular juvenile idiopathic arthritis are based on well-controlled studies. There are no adequate effectiveness or dose-response data for other pediatric conditions, but the experience in polyarticular juvenile idiopathic arthritis and other use experience have established that single doses of 2.5 to 5 mg/kg (as naproxen oral suspension), with total daily dose not exceeding 15 mg/kg/day, are well tolerated in pediatric patients over 2 years of age.
🧓 Geriatric Use ▾
8.5Geriatric Use The hepatic and renal tolerability of long-term naproxen administration was studied in two double-blind clinical trials involving 586 patients. Of the patients studied, 98 patients were age 65 and older and 10 of the 98 patients were age 75 and older. Naproxen was administered at doses of 375 mg twice daily or 750 mg twice daily for up to 6 months.
Transient abnormalities of laboratory tests assessing hepatic and renal function were noted in some patients, although there were no differences noted in the occurrence of abnormal values among different age groups. Elderly patients, compared to younger patients, are at greater risk for NSAID-associated serious cardiovascular, gastrointestinal, and/or renal adverse reactions. If the anticipated benefit for the elderly patient outweighs these potential risks, start dosing at the low end of the dosing range, and monitor patients for adverse effects [see Warnings and Precautions (5.1, 5.2, 5.3, 5.6,5.14)].
Studies indicate that although total plasma concentration of naproxen is unchanged, the unbound plasma fraction of naproxen is increased in the elderly. The clinical significance of this finding is unclear, although it is possible that the increase in free naproxen concentration could be associated with an increase in the rate of adverse events per a given dosage in some elderly patients. Caution is advised when high doses are required and some adjustment of dosage may be required in elderly patients.
As with other drugs used in the elderly, it is prudent to use the lowest effective dose. Experience indicates that geriatric patients may be particularly sensitive to certain adverse effects of nonsteroidal anti-inflammatory drugs. Elderly or debilitated patients seem to tolerate peptic ulceration or bleeding less well when these events do occur.
Most spontaneous reports of fatal GI events are in the geriatric population [see Warnings and Precautions (5.6)]. Naproxen is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
Geriatric patients may be at a greater risk for the development of a form of renal toxicity precipitated by reduced prostaglandin formation during administration of nonsteroidal anti-inflammatory drugs [see Warnings and Precautions (5.6)].
🆘 Overdosage ▾
10 OVERDOSAGE Symptoms following acute NSAID overdosages have been typically limited to lethargy, drowsiness, nausea, vomiting, and epigastric pain, which have been generally reversible with supportive care. Gastrointestinal bleeding has occurred. Hypertension, acute renal failure, respiratory depression, and coma have occurred, but were rare.
A few patients have experienced convulsions, but it is not clear whether or not these were drug-related. It is not known what dose of the drug would be life threatening [see Warnings and Precautions (5.1, 5.2)]. Manage patients with symptomatic and supportive care following an NSAID overdosage.
There are no specific antidotes. Hemodialysis does not decrease the plasma concentration of naproxen because of the high degree of its protein binding. Consider emesis and/or activated charcoal (60 to 100 grams in adults, 1 to 2 grams per kg of body weight in pediatric patients) and/or osmotic cathartic in symptomatic patients seen within four hours of ingestion or in patients with a large overdosage (5 to 10 times the recommended dosage).
Forced diuresis, alkalinization of urine, hemodialysis, or hemoperfusion may not be useful due to high protein binding. For additional information about overdosage treatment contact a poison control center (1-800-222-1222).
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Naproxen has analgesic, anti-inflammatory, and antipyretic properties. The mechanism of action of naproxen, like that of other NSAIDs, is not completely understood but involves inhibition of cyclooxygenase (COX-1 and COX-2). Naproxen is a potent inhibitor of prostaglandin synthesis in vitro.
Naproxen concentrations reached during therapy have produced in vivo effects. Prostaglandins sensitize afferent nerves and potentiate the action of bradykinin in inducing pain in animal models. Prostaglandins are mediators of inflammation.
Because naproxen is an inhibitor of prostaglandin synthesis, its mode of action may be due to a decrease of prostaglandins in peripheral tissues.
12.2Pharmacodynamics In a healthy volunteer study, 10 days of concomitant administration of naproxen 220 mg once-daily with low-dose immediate release aspirin (81 mg) showed an interaction with the antiplatelet activity of aspirin as measured by % serum thromboxane B2 inhibition at 24 hours following the day 10 dose [98.7% (aspirin alone) vs 93.1%(naproxen and aspirin)]. The interaction was observed even following discontinuation of naproxen on day 11 (while aspirin dose was continued) but normalized by day 13. In the same study, the interaction was greater when naproxen was administered 30 minutes prior to aspirin [98.7% vs 87.7%] and minimal when aspirin was administered 30 minutes prior to naproxen [98.7% vs 95.4%].
Following administration of naproxen 220 mg twice-daily with low-dose immediate release aspirin (first naproxen dose given 30 minutes prior to aspirin), the interaction was minimal at 24 h following day 10 dose [98.7% vs 95.7%]. However, the interaction was more prominent after discontinuation of naproxen (washout) on day 11 [98.7% vs 84.3%] and did not normalize completely by day 13 [98.5% vs 90.7%]. [see Drug Interactions (7)] .
12.3Pharmacokinetics Naproxen is rapidly and completely absorbed from the gastrointestinal tract with an in vivo bioavailability of 95%. The elimination half-life of naproxen ranges from 12 to 17 hours. Steady-state levels of naproxen are reached in 4 to 5 days, and the degree of naproxen accumulation is consistent with this half-life.
Absorption Peak plasma levels of naproxen given as naproxen oral suspension are attained in 1 to 4 hours. When naproxen oral suspension and immediate release naproxen tablets were given to fasted subjects (n=12) in a single-dose, crossover study, there were comparable pharmacokinetic parameters between the two formulations. Naproxen Oral Suspension Naproxen Tablets 500 mg C max (μg/mL) 64.3
71.1T max (hours) 2.6
2.3T 1/2 (hours) 16.8
16.3 AUC 0–t (μg·hr/mL) 1249 1218 Distribution Naproxen has a volume of distribution of
0.16L/kg. At therapeutic levels naproxen is greater than 99% albumin- bound. At doses of naproxen greater than 500 mg/day there is less than proportional increase in plasma levels due to an increase in clearance caused by saturation of plasma protein binding at higher doses (average trough Css 36.5, 49.2 and 56.4 mg/L with 500, 1000 and 1500 mg daily doses of naproxen, respectively).
The naproxen anion has been found in the milk of lactating women at a concentration equivalent to approximately 1% of maximum naproxen concentration in plasma [see Use in Specific Populations (8.2)] . Elimination Metabolism Naproxen is extensively metabolized in the liver to 6-0-desmethyl naproxen, and both parent and metabolites do not induce metabolizing enzymes. Both naproxen and 6-0-desmethyl naproxen are further metabolized to their respective acylglucuronide conjugated metabolites.
Excretion The clearance of naproxen is 0.13 mL/min/kg. Approximately 95% of the naproxen from any dose is excreted in the urine, primarily as naproxen (<1%), 6-0-desmethyl naproxen (<1%) or their conjugates (66% to 92%). The plasma half-life of the naproxen anion in humans ranges from 12 to 17 hours.
The corresponding half-lives of both naproxen’s metaboli…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Naproxen has analgesic, anti-inflammatory, and antipyretic properties. The mechanism of action of naproxen, like that of other NSAIDs, is not completely understood but involves inhibition of cyclooxygenase (COX-1 and COX-2). Naproxen is a potent inhibitor of prostaglandin synthesis in vitro.
Naproxen concentrations reached during therapy have produced in vivo effects. Prostaglandins sensitize afferent nerves and potentiate the action of bradykinin in inducing pain in animal models. Prostaglandins are mediators of inflammation.
Because naproxen is an inhibitor of prostaglandin synthesis, its mode of action may be due to a decrease of prostaglandins in peripheral tissues.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Naproxen oral suspension, USP: 125 mg/5 mL (contains 39 mg sodium) is available as: NDC 70954-151-10: 500 mL white colored light-resistant bottles . Storage Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Avoid excessive heat above 40°C (104°F). Dispense in light-resistant containers. Shake gently before use.
📋 Description ▾
11 DESCRIPTION Naproxen oral suspension, USP is available as a light-orange colored, pineapple flavored suspension containing 125 mg/5 mL of naproxen for oral administration. Naproxen is a propionic acid derivative related to the arylacetic acid group of nonsteroidal anti-inflammatory drugs. The chemical name is (S)-6-methoxy-α-methyl-2-naphthaleneacetic acid.
The molecular weight is 230.26. Its molecular formula is C 14 H 14 O 3 , and it has the following chemical structure. Naproxen is an odorless, white to off-white crystalline substance.
It is practically insoluble in water, soluble in ethanol and methanol. The octanol/water partition coefficient of naproxen at pH 7.4 is 1.6 to 1.8. The inactive ingredients in naproxen oral suspension are: sucrose, sorbitol solution, sodium chloride, methylparaben, fumaric acid, FD&C Yellow No.
6, pineapple flavor, propylene glycol, sodium carboxymethyl cellulose, polysorbate 80, colloidal silicon dioxide, hydroxyethyl cellulose and purified water. structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient and caregiver to read the FDA-approved patient labeling (Medication Guide) that accompanies each prescription dispensed. Inform patients, families, or their caregivers should be informed of the following information before initiating therapy with naproxen oral suspension and periodically during the course of ongoing therapy. Cardiovascular Thrombotic Events Advise patients to be alert for the symptoms of cardiovascular thrombotic events, including chest pain, shortness of breath, weakness, or slurring of speech, and to report any of these symptoms to their health care provider immediately [see Warnings and Precautions (5.1)].
Gastrointestinal Bleeding, Ulceration, and Perforation Advise patients to report symptoms of ulcerations and bleeding, including epigastric pain, dyspepsia, melena, and hematemesis to their health care provider. In the setting of concomitant use of low-dose aspirin for cardiac prophylaxis, inform patients of the increased risk for and the signs and symptoms of GI bleeding [see Warnings and Precautions (5.2)]. Hepatotoxicity Inform patients of the warning signs and symptoms of hepatotoxicity (e.g., nausea, fatigue, lethargy, pruritus, diarrhea, jaundice, right upper quadrant tenderness, and “flu-like” symptoms).
If these occur, instruct patients to stop naproxen oral suspension and seek immediate medical therapy [see Warnings and Precautions (5.3)]. Heart Failure and Edema Advise patients to be alert for the symptoms of congestive heart failure including shortness of breath, unexplained weight gain, or edema and to contact their healthcare provider if such symptoms occur [see Warnings and Precautions (5.5)]. Anaphylactic Reactions Inform patients of the signs of an anaphylactic reaction (e.g., difficulty breathing, swelling of the face or throat).
Instruct patients to seek immediate emergency help if these occur [see Contraindications (4) and Warnings and Precautions (5.7)]. Serious Skin Reactions, including DRESS Advise patients to stop taking naproxen oral suspension immediately if they develop any type of rash or fever and to contact their healthcare provider as soon as possible [see Warnings and Precautions (5.9, 5.10)]. Female Fertility Advise females of reproductive potential who desire pregnancy that NSAIDs, including naproxen oral suspension, may be associated with a reversible delay in ovulation [see Use in Specific Populations (8.3)].
Fetal Toxicity Inform pregnant women to avoid use of naproxen oral suspension and other NSAIDs starting at 30 weeks gestation because of the risk of the premature closing of the fetal ductus arteriosus. If treatment with naproxen oral suspension is needed for a pregnant woman between about 20 to 30 weeks gestation, advise her that she may need to be monitored for oligohydramnios, if treatment continues for longer than 48 hours [see Warnings and Precautions (5.11) and Use in Specific Populations (8.1)]. Avoid Concomitant Use of NSAIDs Inform patients that the concomitant use of naproxen oral suspension with other NSAIDs or salicylates (e.g., diflunisal, salsalate) is not recommended due to the increased risk of gastrointestinal toxicity, and little or no increase in efficacy [see Warnings and Precautions (5.2) and Drug Interactions (7)].
Alert patients that NSAIDs may be present in “over the counter” medications for treatment of colds, fever, or insomnia. Use of NSAIDS and Low-Dose Aspirin Inform patients not to use low-dose aspirin concomitantly with naproxen oral suspension until they talk to their healthcare provider [see Drug Interactions (7)]. Dosing Instructions Instruct patients on how to measure and take the correct dose of naproxen oral suspension and to always use a calibrated measuring device when administering naproxen oral suspension to ensure the dose is measured and administered accurately [see Dosage and Administration (2.1)].
If the prescribed concentration is changed, instruct patients on how to c…
💬 Medication Guide ▾
MEDICATION GUIDE Medication Guide for Nonsteroidal Anti-inflammatory Drugs (NSAIDs) What is the most important information I should know about medicines called Nonsteroidal Anti-inflammatory Drugs (NSAIDs)? NSAIDs can cause serious side effects, including: Increased risk of a heart attack or stroke that can lead to death. This risk may happen early in treatment and may increase: with increasing doses of NSAIDs with longer use of NSAIDs Do not take NSAIDs right before or after a heart surgery called a “coronary artery bypass graft (CABG)." Avoid taking NSAIDs after a recent heart attack, unless your healthcare provider tells you to.
You may have an increased risk of another heart attack if you take NSAIDs after a recent heart attack. Increased risk of bleeding, ulcers, and tears (perforation) of the esophagus (tube leading from the mouth to the stomach), stomach and intestines: anytime during use without warning symptoms that may cause death The risk of getting an ulcer or bleeding increases with: past history of stomach ulcers, or stomach or intestinal bleeding with use of NSAIDs taking medicines called “corticosteroids”, “anticoagulants”, “SSRIs”, or “SNRIs” increasing doses of NSAIDs older age longer use of NSAIDs poor health smoking advanced liver disease drinking alcohol bleeding problems NSAIDs should only be used: exactly as prescribed at the lowest dose possible for your treatment for the shortest time needed What are NSAIDs?
NSAIDs are used to treat pain and redness, swelling, and heat (inflammation) from medical conditions such as different types of arthritis, menstrual cramps, and other types of short-term pain. Who should not take NSAIDs? Do not take NSAIDs: if you have had an asthma attack, hives, or other allergic reaction with aspirin or any other NSAIDs. right before or after heart bypass surgery.
How should I take naproxen oral suspension? Use ONLY a calibrated measuring device to measure your dose of naproxen oral suspension. DO NOT use a household teaspoon or tablespoon.
Your pharmacist can provide you with the proper device to correctly measure your dose. Before taking NSAIDS, tell your healthcare provider about all of your medical conditions, including if you: have liver or kidney problems have high blood pressure have asthma are pregnant or plan to become pregnant. Taking NSAIDs at about 20 weeks of pregnancy or later may harm your unborn baby.
If you need to take NSAIDs for more than 2 days when you are between 20 and 30 weeks of pregnancy, your healthcare provider may need to monitor the amount of fluid in your womb around your baby. You should not take NSAIDs after about 30 weeks of pregnancy. are breastfeeding or plan to breast feed. Tell your healthcare provider about all of the medicines you take, including prescription or over-the-counter medicines, vitamins or herbal supplements.
NSAIDs and some other medicines can interact with each other and cause serious side effects. Do not start taking any new medicine without talking to your healthcare provider first. What are the possible side effects of NSAIDs?
NSAIDs can cause serious side effects, including: See “What is the most important information I should know about medicines called Nonsteroidal Anti-inflammatory Drugs (NSAIDs)?” new or worse high blood pressure heart failure liver problems including liver failure kidney problems including kidney failure low red blood cells (anemia) life-threatening skin reactions life-threatening allergic reactions Other side effects of NSAIDs include: stomach pain, constipation, diarrhea, gas, heartburn, nausea, vomiting, and dizziness.
Get emergency help right away if you get any of the following symptoms: shortness of breath or trouble breathing slurred speech chest pain swelling of the face or throat weakness in one part or side of your body Stop taking your NSAID and call your healthcare provider right away if you get any of the following symptoms: nausea vomit blood more tired or weaker than usual there is blo…