
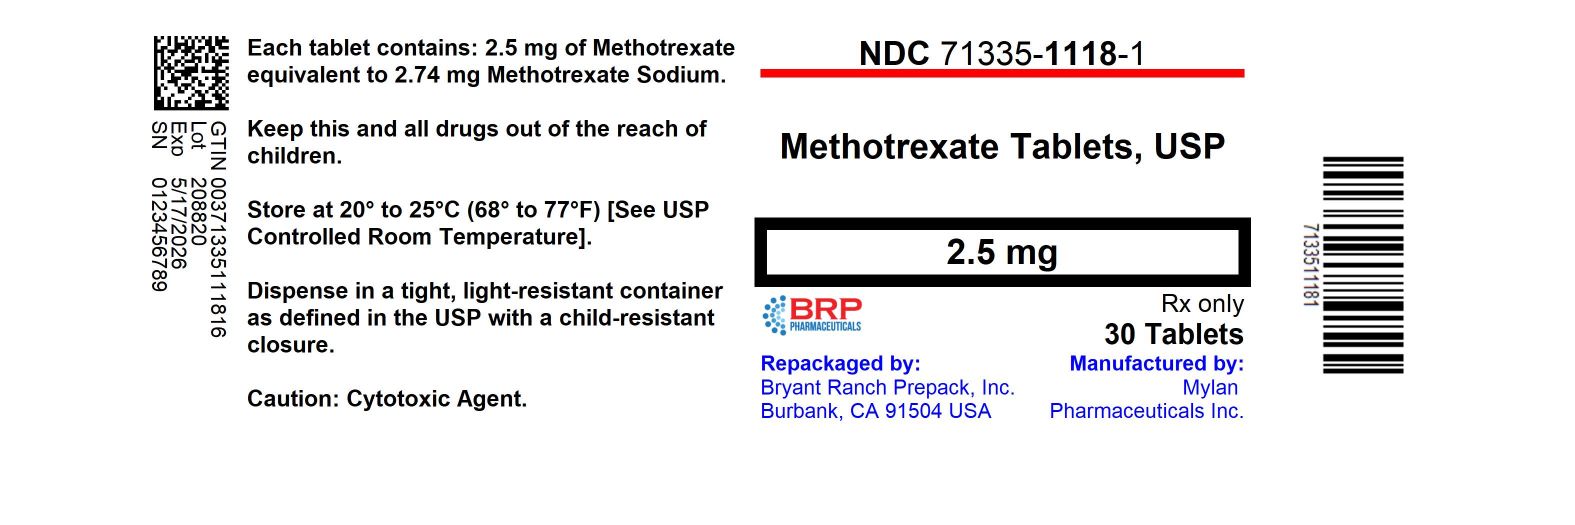
Methotrexate 2.5 mg Tablet, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Folate Analog Metabolic Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- That's a great question, and it's really important you keep that in mind. For arthritis and psoriasis, methotrexate is always dosed once weekly — not daily. The drug works in a way...
- Why am I only taking this once a week? That seems unusual.
- Mild nausea, some fatigue, or the occasional mouth sore are common and manageable — let your doctor know, but they usually don't require an urgent call. However, if you develop a f...
- What side effects should I just watch and wait on, versus call the doctor about right away?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Methotrexate — tap one for details:
Methotrexate may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 7T9FYH5QMK
A plant-derived powder that serves as a binder and filler in tablets and capsules. It helps hold ingredients together, adds bulk, and aids in smooth tablet disintegration when swallowed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 2A1Q1Q3557
Sodium carbonate monohydrate is an inorganic salt containing sodium, carbon, and water. It acts as a pH buffer and alkalizing agent in medicines, helping maintain the proper acid-base balance needed for product stability and function.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.4031 | $40.31 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Methotrexate 2.5 mg 00378-0014-01 | Mylan | 100 tablets | $0.157 | AB | Availability likely | — |
| Methotrexate 2.5 mg 00555-0572-02 | Teva | 100 tablets | $0.157 | AB | Availability likely | — |
| Methotrexate 2.5 mg 00904-7141-10 | Major | 20 tablets | $0.157 | AB | Availability likely | — |
| Methotrexate 2.5 mg 16729-0486-01 | Accord | 100 tablets | $0.157 | AB | Availability likely | — |
| Methotrexate 2.5 mg 47335-0235-83 | Sun | 100 tablets | $0.157 | AB | Availability likely | — |
| Methotrexate 2.5 mg 51079-0670-05 | Mylan | 20 tablets | $0.157 | AB | Availability likely | — |
| Methotrexate 2.5 mg 59651-0182-01 | Aurobindo | 100 tablets | $0.157 | AB | Availability likely | — |
| Methotrexate 2.5 mg 62135-0772-35 | Chartwell | 36 tablets | $0.157 | AB | Availability likely | — |
| Methotrexate 2.5 mg 62332-0730-31 | Alembic | 100 tablets | $0.157 | AB | Availability likely | — |
| Methotrexate Sodium 2.5 mg 64850-0330-01 | Elite | 100 tablets | $0.157 | AB | Availability likely | — |
| Methotrexate 2.5 mg 68382-0775-01 | Zydus | 100 tablets | $0.157 | AB | Availability likely | — |
| Methotrexate Sodium 2.5 mg 00054-4550-15 | Hikma | 36 tablets | $0.192 | AB | Discontinued | — |
| Methotrexate 2.5 mg 46708-0730-31 | Alembic | 100 tablets | — | AB | FDA listed | — |
| Methotrexate 2.5 mg 48433-0065-05 | Safecor | 20 tablets | — | AB | FDA listed | — |
| Methotrexate 2.5 mg 50090-5457-02 | A-S | 100 tablets | — | AB | Discontinued | — |
| Methotrexate 2.5 mg 50268-0554-15 | AvPAK | 50 tablets | — | AB | FDA listed | — |
| Methotrexate 2.5 mg 51407-0121-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Methotrexate 2.5 mg 67046-1524-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Methotrexate 2.5 mg 68071-3765-06 | NuCare | 60 tablets | — | AB | FDA listed | — |
| Methotrexate 2.5 mg 68071-3991-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Methotrexate 2.5 mg 70771-1058-00 | Zydus | 1000 tablets | — | AB | FDA listed | — |
| Methotrexate 2.5 mg 71335-0782-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Methotrexate 2.5 mgthis 71335-1118-04 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Methotrexate 2.5 mg 71335-1772-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Methotrexate 2.5 mg 71335-2221-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Methotrexate 2.5 mg 72162-2174-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Methotrexate 2.5 mg 72162-2647-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Methotrexate 2.5 mg 82804-0136-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Methotrexate 2.5 mg 42291-0594-01 | AvKARE | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-1118-01 | 30 TABLET in 1 BOTTLE (71335-1118-1) | 2019-02-25 | Active |
| 71335-1118-02 | 12 TABLET in 1 BOTTLE (71335-1118-2) | 2022-06-29 | Active |
| 71335-1118-03 | 20 TABLET in 1 BOTTLE (71335-1118-3) | 2022-06-29 | Active |
| 71335-1118-04 You're viewing this | 100 TABLET in 1 BOTTLE (71335-1118-4) | 2022-06-29 | Active |
| 71335-1118-05 | 36 TABLET in 1 BOTTLE (71335-1118-5) | 2022-06-29 | Active |
| 71335-1118-06 | 24 TABLET in 1 BOTTLE (71335-1118-6) | 2022-06-29 | Active |
| 71335-1118-07 | 90 TABLET in 1 BOTTLE (71335-1118-7) | 2022-06-29 | Active |
| 71335-1118-08 | 4 TABLET in 1 BOTTLE (71335-1118-8) | 2022-06-29 | Active |
You're viewing the largest of 8 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-1118-04?
What is the difference between NDC 71335-1118-04 and NDC 71335-1118-08?
What NDC number is used to bill for this package of Methotrexate 2.5 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: EMBRYO-FETAL TOXICITY, HYPERSENSITIVITY REACTIONS AND SEVERE ADVERSE REACTIONS • Methotrexate tablets can cause embryo-fetal toxicity, including fetal death. For non-neoplastic diseases, methotrexate tablets are contraindicated in pregnancy. For neoplastic diseases, advise females and males of reproductive potential to use effective contraception [see Contraindications (4) , Warnings and Precautions (5.1) , Use in Specific Populations (8.1 , 8.3) ] . • Methotrexate tablets are contraindicated in patients with a history of severe hypersensitivity reactions to methotrexate, including anaphylaxis [see Contraindications (4) , Warnings and Precautions (5.2) ] . • Serious adverse reactions, including death, have been reported with methotrexate.
Closely monitor for adverse reactions of the bone marrow, gastrointestinal tract, liver, lungs, skin, and kidneys. Withhold or discontinue methotrexate tablets as appropriate [see Warnings and Precautions (5.3 , 5.4 , 5.5 , 5.6 , 5.7 , 5.8) ] . WARNING: EMBRYO-FETAL TOXICITY, HYPERSENSITIVITY REACTIONS, and SEVERE ADVERSE REACTIONS See full prescribing information for complete boxed warning. • Methotrexate tablets can cause embryo-fetal toxicity, including fetal death.
For non-neoplastic diseases, methotrexate tablets are contraindicated in pregnancy. For neoplastic diseases, advise patients of reproductive potential of the potential risk to a fetus and to use effective contraception ( 4 , 5.1 , 8.1 , 8.3 ). • Methotrexate tablets are contraindicated in patients with a history of severe hypersensitivity reactions to methotrexate, including anaphylaxis ( 4 , 5.2 ). • Serious adverse reactions, including death, have been reported with methotrexate. Closely monitor for adverse reactions of the bone marrow, gastrointestinal tract, liver, lungs, skin, and kidneys.
Withhold or discontinue methotrexate tablets as appropriate ( 5.3 , 5.4 , 5.5 , 5.6 , 5.7 , 5.8 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Methotrexate tablets are a dihydrofolate reductase inhibitor indicated for the: • Treatment of adults and pediatric patients with acute lymphoblastic leukemia (ALL) as part of a combination chemotherapy maintenance regimen ( 1.1 ) • Treatment of adults with mycosis fungoides ( 1.1 ) • Treatment of adults with relapsed or refractory non-Hodgkin lymphoma as part of a metronomic combination regimen ( 1.1 ) • Treatment of adults with rheumatoid arthritis ( 1.2 ) • Treatment of pediatric patients with polyarticular juvenile idiopathic arthritis (pJIA) ( 1.3 ) • Treatment of adults with severe psoriasis ( 1.4 )
1.1Neoplastic Diseases Methotrexate tablets are indicated for the: • treatment of adults and pediatric patients with acute lymphoblastic leukemia (ALL) as part of a combination chemotherapy maintenance regimen. • treatment of adults with mycosis fungoides (cutaneous T-cell lymphoma) as a single agent or as part of a combination chemotherapy regimen. • treatment of adults with relapsed or refractory non-Hodgkin lymphomas as part of a metronomic combination chemotherapy regimen.
1.2Rheumatoid Arthritis Methotrexate tablets are indicated for the treatment of adults with rheumatoid arthritis.
1.3Polyarticular Juvenile Idiopathic Arthritis Methotrexate tablets are indicated for the treatment of pediatric patients with polyarticular Juvenile Idiopathic Arthritis (pJIA).
1.4Psoriasis Methotrexate tablets are indicated for the treatment of adults with severe psoriasis.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Instruct patients and caregivers to take the recommended dosage as directed, because medication errors have led to deaths. ( 2.1 , 5.9 ) • Verify pregnancy status in females of reproductive potential before starting methotrexate tablets ( 4 , 5.1 ). • ALL : The recommended dosage is 20 mg/m 2 orally once weekly as a part of a combination chemotherapy maintenance regimen. ( 2.2 ) • Mycosis fungoides : The recommended dosage is 25 to 75 mg orally once weekly as monotherapy; 10 mg/m 2 orally twice weekly as part of combination chemotherapy.
( 2.2 ) • Relapsed or refractory non-Hodgkin lymphoma : The recommended dosage is 2.5 mg orally two to four times per week as part of metronomic combination chemotherapy. ( 2.2 ) • Rheumatoid Arthritis : The recommended starting dosage is 7.5 mg orally once weekly; adjust dose to achieve an optimal response ( 2.3 ) • pJIA : The recommended starting dosage is 10 mg/m 2 orally once weekly; adjust dose to achieve an optimal response ( 2.4 ) • Psoriasis : The recommended dosage is 10 to 25 mg orally once weekly until adequate response is achieved.
( 2.5 )
2.1Important Dosage and Safety Information Verify pregnancy status in females of reproductive potential before starting methotrexate tablets [see Contraindications (4) , Warnings and Precautions (5.1) ] . Instruct patients and caregivers to take the recommended dosage as directed, because medication errors have led to deaths [see Warnings and Precautions (5.9) ] . When switching the dosing regimen from oral administration to intravenous, intramuscular, or subcutaneous administration, an alternative dosing regimen may be necessary.
Do not administer to patients who are unable to swallow a tablet. Methotrexate tablets are a cytotoxic drug. Follow applicable special handling and disposal procedures.
1
2.2Recommended Dosage for Neoplastic Diseases Acute Lymphoblastic Leukemia The recommended starting dosage of methotrexate tablets is 20 mg/m 2 orally once weekly, as part of a combination chemotherapy maintenance regimen. After initiating methotrexate tablets, periodically monitor absolute neutrophil count (ANC) and platelet count and adjust the dose to maintain ANC at a desirable level and for excessive myelosuppression. Mycosis Fungoides The recommended dosage of methotrexate tablets is 25 to 75 mg orally once weekly when administered as a single agent or 10 mg/m 2 orally twice weekly as part of a combination chemotherapy regimen.
Relapsed or Refractory Non-Hodgkin Lymphomas The recommended dosage of methotrexate tablets is 2.5 mg orally 2 to 4 times per week (maximum 10 mg per week) as part of a metronomic combination chemotherapy regimen.
2.3Recommended Dosage for Rheumatoid Arthritis The recommended starting dosage of methotrexate tablets is 7.5 mg orally once weekly with escalation to achieve optimal response. Dosages of more than 20 mg once weekly result in an increased risk of serious adverse reactions, including myelosuppression. When responses are observed, the majority occurred between 3 and 6 weeks from initiation of treatment; however, responses have occurred up to 12 weeks after treatment initiation.
Administer folic acid or folinic acid to reduce the risk of methotrexate adverse reactions [see Warnings and Precautions (5.10) ].
2.4Recommended Dosage for Polyarticular Juvenile Idiopathic Arthritis The recommended starting dosage of methotrexate tablets is 10 mg/m 2 orally once weekly with escalation to achieve optimal response. Dosages of more than 30 mg/m 2 once weekly result in an increased risk of serious adverse reactions, including myelosuppression. When responses are observed, the majority occurred between 3 and 6 weeks from initiation of treatment; however, responses have occurred up to 12 weeks after treatment initiation.
Administer folic acid or folinic acid to reduce the risk of methotrexate adverse reactions [see Warnings and Precautions (5.10) ].
2.5 Recommended Dosage for Psoriasis The recom…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Methotrexate Tablets, USP are available containing 2.5 mg methotrexate, USP equivalent to 2.74 mg methotrexate sodium. • The 2.5 mg tablets are orange, round, scored tablets debossed with M above the score and 14 below the score on one side of the tablet and blank on the other side of the tablet. Tablets: 2.5 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Methotrexate tablets are contraindicated in: • Pregnant women receiving methotrexate tablets for treatment of non-neoplastic diseases [see Warnings and Precautions (5.1) , and Use in Specific Populations (8.1 , 8.3) ] . • Patients with a history of a severe hypersensitivity reactions, including anaphylaxis, to methotrexate [see Warnings and Precautions (5.2) ] . • In pregnancy for non-neoplastic diseases ( 4 ) • History of severe hypersensitivity to methotrexate ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Serious Infections : Monitor patients for infection during and after treatment with methotrexate tablets. Withhold or discontinue methotrexate tablets for serious infections as appropriate. ( 5.11 ) • Neurotoxicity : Monitor patients for neurotoxicity and withhold or discontinue methotrexate tablets as appropriate.
( 5.12 ) • Secondary Malignancies : Can occur with methotrexate. ( 5.13 ) • Tumor Lysis Syndrome : Institute appropriate prophylactic measures in patients at risk for tumor lysis syndrome prior to initiation of methotrexate tablets. ( 5.14 ) • Immunizations and Risk Live Vaccines : Immunizations with live vaccines is not recommended.
Follow current vaccination practice guidelines. ( 5.15 ) • Infertility : Can cause impairment of fertility, oligospermia, and menstrual dysfunction. ( 5.16 , 8.3 )
5.1Embryo-Fetal Toxicity Based on published reports and its mechanism of action, methotrexate tablets can cause fetal harm, including fetal death, when administered to a pregnant woman. Methotrexate tablets are contraindicated for use in pregnant women receiving methotrexate tablets for the treatment of non-malignant diseases. Advise pregnant women with neoplastic diseases of the potential risk to a fetus.
Advise females of reproductive potential to use effective contraception during treatment with methotrexate tablets and for 6 months after the final dose. Advise males with female partners of reproductive potential to use effective contraception during methotrexate tablets treatment and for 3 months after the final dose [see Contraindications (4) , Use in Specific Populations (8.1 , 8.3) ].
5.2Hypersensitivity Reactions Hypersensitivity reactions, including anaphylaxis, can occur with methotrexate [see Contraindications (4) , Adverse Reactions (6.1) ] . If anaphylaxis or other serious hypersensitivity reaction occurs, immediately and permanently discontinue methotrexate tablets [see Dosage and Administration (2.6) ].
5.3Myelosuppression Methotrexate suppresses hematopoiesis and can cause severe and life-threatening pancytopenia, anemia, leukopenia, neutropenia, and thrombocytopenia [see Adverse Reactions (6.1) ] . Obtain blood counts at baseline, periodically during treatment, and as clinically indicated. Monitor patients for clinical complications of myelosuppression.
Withhold, dose reduce, or discontinue methotrexate tablets taking into account the importance of methotrexate tablet treatment in the context of the severity of the disease being treated, the severity of the adverse drug reaction, and availability of alternative therapy [see Dosage and Administration (2.6) ].
5.4Gastrointestinal Toxicity Diarrhea, vomiting, nausea, and stomatitis occurred in up to 10% of patients receiving methotrexate for treatment of non-neoplastic diseases. Hemorrhagic enteritis and fatal intestinal perforation have been reported [see Adverse Reactions (6.1 , 6.2) ] . Patients with peptic ulcer disease or ulcerative colitis are at a greater risk of developing severe gastrointestinal adverse reactions [see Drug Interactions (7.1) ] .
Withhold or discontinue methotrexate tablets for severe gastrointestinal toxicity taking into account the importance of methotrexate tablet treatment in the context of the severity of the disease being treated, the severity of the adverse drug reaction, and availability of alternative therapy [see Dosage and Administration (2.6) ].
5.5Hepatotoxicity Methotrexate can cause severe and potentially irreversible hepatotoxicity, including fibrosis, cirrhosis, and fatal liver failure [see Adverse Reactions (6.1) ]. The safety of methotrexate tablets in patients with hepatic disease is unknown. The risk of hepatotoxicity is increased with heavy alcohol consumption.
In patients with psoriasis, fibrosis or cirrhosis may occur in the absence of symptoms or abnormal liver tests; the risk of hepatotoxicity appears to increase with total cumulative dose and generally occurs after receipt of a…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: • Hypersensitivity Reactions [see Warnings and Precautions (5.2) ] • Myelosuppression [see Warnings and Precautions (5.3) ] • Gastrointestinal Toxicity [see Warnings and Precautions (5.4) ] • Hepatotoxicity [see Warnings and Precautions (5.5) ] • Pulmonary Toxicity [see Warnings and Precautions (5.6) ] • Dermatologic Reactions [see Warnings and Precautions (5.7) ] • Renal Toxicity [see Warnings and Precautions (5.8) ] • Serious Infections [see Warnings and Precautions (5.11) ] • Neurotoxicity [see Warnings and Precautions (5.12) ] • Secondary Malignancies [see Warnings and Precautions (5.13) ] • Tumor Lysis Syndrome [see Warnings and Precautions (5.14) ] • Increased Risk of Adverse Reactions Due to Third-Space Accumulation [see Warnings and Precautions (5.17) ] Common adverse reactions include ulcerative stomatitis, leukopenia, nausea, abdominal distress.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Mylan at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials and other studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Common adverse reactions were: ulcerative stomatitis, leukopenia, nausea, and abdominal distress. Other clinically relevant adverse reactions were infection, malaise, fatigue, chills, fever, and dizziness.
Rheumatoid Arthritis The most common adverse reactions of methotrexate that exceeded the rate of placebo in 12- to 18-week double-blind studies in patients (n = 128) with rheumatoid arthritis are listed below. Patients received methotrexate 7.5 to 15 mg orally once weekly. Most patients received concomitant nonsteroidal anti-inflammatory drugs (NSAIDs) and some also received corticosteroids.
Hepatic histology was not examined in these short-term studies. Incidence ≥ 10%: Elevated liver tests 15%, nausea/vomiting 10% Incidence 3% to < 10%: Stomatitis, thrombocytopenia (platelet count < 100,000/mm 3 ) Incidence 1% to < 3%: Rash/pruritus/dermatitis, diarrhea, alopecia, leukopenia (white blood cell count < 3000/mm 3 ), pancytopenia, dizziness Two other controlled trials of patients (n = 680) with rheumatoid arthritis who received methotrexate 7.5 mg to 15 mg orally once weekly showed the following serious adverse reaction: Incidence 1%: Interstitial pneumonitis Other less common adverse reactions were: anemia, headache, upper respiratory infection, anorexia, arthralgias, chest pain, coughing, dysuria, eye discomfort, epistaxis, fever, infection, sweating, tinnitus, vaginal discharge.
Polyarticular Juvenile Idiopathic Arthritis (pJIA) The most common adverse reactions reported in patients 2 to 18 years of age with pJIA treated with methotrexate 5 mg/m 2 to 20 mg/m 2 orally once weekly or 0.1 to 0.65 mg/kg orally once weekly were as follows: elevated liver tests 14%; gastrointestinal reactions (e.g., nausea, vomiting, diarrhea) 11%; stomatitis 2%; leukopenia 2%; headache 1.2%; alopecia 0.5%; dizziness 0.2%; rash 0.2%. Most patients received concomitant NSAIDs and some also received corticosteroids.
Psoriasis In two published series of adults with psoriasis (n = 204, 248) who received methotrexate up to 25 mg per week for up to 4 years, adverse reaction rates were similar to those in patients with rheumatoid arthritis, except for alopecia, photosensitivity, and “burning of skin lesions” (3% to 10% each). Painful plaque erosions have been reported.
6.2Postmarketing Experience The following adverse reactions have been identified during postapproval use of methotrexate. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency o…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Refer to the full prescribing information for drug interactions with methotrexate. ( 7 )
7.1Effects of Other Drugs on Methotrexate Drugs that Increase Methotrexate Exposure Coadministration of methotrexate with the following products may increase methotrexate plasma concentrations, which may increase the risk of methotrexate severe adverse reactions. In some cases, the coadministration of methotrexate with these products may also subsequently reduce active metabolite formation, which may decrease the clinical effectiveness of methotrexate. Increased organ specific adverse reactions may also occur when methotrexate is coadministered with hepatotoxic or nephrotoxic products.
If coadministration cannot be avoided, monitor closely for methotrexate adverse reactions when coadministered with: • Oral antibiotics (including neomycin) • Oral or intravenous penicillin or sulfonamide antibiotics • Highly protein-bound drugs (e.g., oral anticoagulants, phenytoin, salicylates, sulfonamides, sulfonylureas, and tetracyclines) • Probencid • Antifolate drugs (e.g., dapsone, pemetrexed, pyrimethamine and sulfonamides) • Aspirin and other nonsteroidal anti-inflammatory drugs • Hepatotoxic products • Proton pump inhibitors • Weak acids (e.g., salicylates) • Nephrotoxic products Nitrous Oxide Coadministration of methotrexate with nitrous oxide anesthesia potentiates the effect of methotrexate on folate-dependent metabolic pathways, which may increase the risk of severe methotrexate adverse reactions.
Avoid nitrous oxide anesthesia in patients receiving methotrexate. Consider alternative therapies in patients who have received prior nitrous oxide anesthesia. Folic Acid Coadministration of methotrexate with folic acid or its derivatives decreases the clinical effectiveness of methotrexate in patients with neoplastic diseases.
Methotrexate competes with reduced folates for active transport across cell membranes. Instruct patients to take folic or folinic acid only as directed by their healthcare provider [see Warnings and Precautions (5.10) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation : Instruct not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Methotrexate tablets are contraindicated in pregnant women with non-neoplastic diseases [see Contraindications (4) ]. Based on published reports and its mechanism of action [see Clinical Pharmacology (12.1) ], methotrexate can cause embryo-fetal toxicity and fetal death when administered to a pregnant woman. There are no animal data that meet current standards for nonclinical developmental toxicity studies.
Advise pregnant women with neoplastic diseases of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Human Data Published data from case reports, literature reviews, and observational studies report that methotrexate exposure during pregnancy is associated with an increased risk of embryo-fetal toxicity and fetal death.
Methotrexate exposure during the first trimester of pregnancy is associated with an increased incidence of spontaneous abortions and multiple adverse developmental outcomes, including skull anomalies, facial dysmorphism, central nervous system abnormalities, limb abnormalities, and sometimes cardiac anomalies and intellectual impairment. Adverse outcomes associated with exposure during second and third trimesters of pregnancy include intrauterine growth restriction and functional abnormalities. Because methotrexate is widely distributed and persists in the body for a prolonged period, there is a potential risk to the fetus from preconception methotrexate exposure.
A prospective multicenter study evaluated pregnancy outcomes in women taking methotrexate less than or equal to 30 mg/week after conception. The rate of spontaneous abortion and miscarriage in pregnant women exposed to methotrexate was 42% (95% confidence interval [95% CI] 29, 59), which was higher than in unexposed patients with autoimmune disease (22%; 95% CI: 17, 30) and unexposed patients with nonautoimmune disease (17%; 95% CI: 13, 23). Of the live births, the rate of major birth defects in pregnant women exposed to methotrexate after conception was higher than in unexposed patients with autoimmune disease (adjusted odds ratio (OR) 1.8 [95% CI: 0.6, 6]) and unexposed patients with non-autoimmune disease (adjusted OR 3.1 [95% CI: 1, 10]) (2.9%).
Major birth defects associated with pregnancies exposed to methotrexate after conception were not always consistent with methotrexate-associated adverse developmental outcomes.
8.2Lactation Risk Summary Limited published literature report the presence of methotrexate in human milk in low amounts, with the highest breast milk to plasma concentration ratio reported to be 0.08:1. There are no data on the effects of methotrexate or its metabolites on the breastfed child or their effects on milk production. Because of the potential for serious adverse reactions in a breastfed child, instruct women not to breastfeed during treatment with methotrexate tablets and for 1 week after the final dose.
8.3Females and Males of Reproductive Potential Methotrexate can cause malformations and fetal death at doses less than or equal to the recommended clinical doses [see Use in Specific Populations (8.1) ]. Pregnancy Testing Verify the pregnancy status of females of reproductive potential prior to initiating methotrexate tablets [see Contraindications (4) , Use in Specific Populations (8.1) ]. Contraception Females Advise females of reproductive potential to use effective contraception during treatment with methotrexate tablets and for 6 months after the final dose.
Males Methotrexate can cause chromosomal damage to sperm cells. Advise males with female partners of reproductive potential to use effective contraception during treatment with methotrexate tablets and for 3 months after the final dose. Infertility Females Based on published reports of female…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Methotrexate tablets are contraindicated in pregnant women with non-neoplastic diseases [see Contraindications (4) ]. Based on published reports and its mechanism of action [see Clinical Pharmacology (12.1) ], methotrexate can cause embryo-fetal toxicity and fetal death when administered to a pregnant woman. There are no animal data that meet current standards for nonclinical developmental toxicity studies.
Advise pregnant women with neoplastic diseases of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Human Data Published data from case reports, literature reviews, and observational studies report that methotrexate exposure during pregnancy is associated with an increased risk of embryo-fetal toxicity and fetal death.
Methotrexate exposure during the first trimester of pregnancy is associated with an increased incidence of spontaneous abortions and multiple adverse developmental outcomes, including skull anomalies, facial dysmorphism, central nervous system abnormalities, limb abnormalities, and sometimes cardiac anomalies and intellectual impairment. Adverse outcomes associated with exposure during second and third trimesters of pregnancy include intrauterine growth restriction and functional abnormalities. Because methotrexate is widely distributed and persists in the body for a prolonged period, there is a potential risk to the fetus from preconception methotrexate exposure.
A prospective multicenter study evaluated pregnancy outcomes in women taking methotrexate less than or equal to 30 mg/week after conception. The rate of spontaneous abortion and miscarriage in pregnant women exposed to methotrexate was 42% (95% confidence interval [95% CI] 29, 59), which was higher than in unexposed patients with autoimmune disease (22%; 95% CI: 17, 30) and unexposed patients with nonautoimmune disease (17%; 95% CI: 13, 23). Of the live births, the rate of major birth defects in pregnant women exposed to methotrexate after conception was higher than in unexposed patients with autoimmune disease (adjusted odds ratio (OR) 1.8 [95% CI: 0.6, 6]) and unexposed patients with non-autoimmune disease (adjusted OR 3.1 [95% CI: 1, 10]) (2.9%).
Major birth defects associated with pregnancies exposed to methotrexate after conception were not always consistent with methotrexate-associated adverse developmental outcomes.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of methotrexate tablets in pediatric patients have been established for the treatment of ALL as part of the combination chemotherapy maintenance regimen and the treatment of pJIA [see Indications and Usage (1) , Dosage and Administration (2) ]. No new safety signals have been observed in pediatric patients in clinical studies [see Adverse Reactions (6.1) ]. The safety and effectiveness of methotrexate tablets have not been established in pediatric patients for the other indications [see Indications and Usage (1) ].
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of methotrexate did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects.
🆘 Overdosage ▾
10 OVERDOSAGE Overdosage, including fatal overdosage, has occurred with methotrexate [see Warnings and Precautions (5.9) ]. Manifestations: Manifestations of methotrexate overdosage include adverse reactions reported at pharmacologic doses, particularly hematologic and gastrointestinal reactions (e.g., leukopenia, thrombocytopenia, anemia, pancytopenia, myelosuppression, mucositis, stomatitis, oral ulceration, nausea, vomiting, gastrointestinal ulceration, or gastrointestinal bleeding). In some cases, no symptoms were reported; however, sepsis or septic shock, renal failure, and aplastic anemia were also reported.
Management: Leucovorin and levoleucovorin are indicated for diminishing the methotrexate adverse reactions of methotrexate overdosage. Administer leucovorin or levoleucovorin as soon as possible after methotrexate overdosage). Monitor serum creatinine and methotrexate levels to guide leucovorin or levoleucovorin therapy.
Refer to the leucovorin or levoleucovorin prescribing information for additional dosage information. Glucarpidase is indicated for the treatment of toxic plasma methotrexate concentrations (> 1 micromole per liter) in patients with delayed methotrexate clearance due to impaired renal function. Refer to the glucarpidase prescribing information for additional dosage information.
Administer concomitant hydration and urinary alkalinization. Neither hemodialysis nor peritoneal dialysis has been shown to improve methotrexate elimination; however, methotrexate has been effectively cleared with acute, intermittent hemodialysis using a high-flux dialyzer.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Methotrexate inhibits dihydrofolic acid reductase. Dihydrofolates must be reduced to tetrahydrofolates by this enzyme before they can be utilized as carriers of one-carbon groups in the synthesis of purine nucleotides and thymidylate. Therefore, methotrexate interferes with DNA synthesis, repair, and cellular replication.
Actively proliferating tissues such as malignant cells, bone marrow, fetal cells, buccal and intestinal mucosa, and cells of the urinary bladder are in general more sensitive to this effect of methotrexate. The mechanism of action in rheumatoid arthritis and in psoriasis is unknown.
12.3Pharmacokinetics Absorption At doses of 30 mg/m 2 or less, the mean bioavailability is approximately 60%. Peak plasma concentrations are reached within 0.75 to 6 hours following oral administration. Methotrexate may undergo enterohepatic recirculation; however, this pathway has not been fully characterized.
Effect of Food Food has been shown to delay absorption and reduce peak concentration. Distribution Methotrexate in serum is approximately 50% protein bound. Methotrexate does not penetrate the blood-cerebrospinal fluid barrier at concentrations achieved with the recommended dosages.
Elimination The elimination half-life of methotrexate is approximately 3 to 10 hours. Small amounts of methotrexate polyglutamates may remain in tissues for extended periods. The retention and prolonged drug action of these active metabolites vary among different cells, tissues, and tumors.
Nonlinear elimination due to saturation of renal tubular reabsorption has been observed in studies of patients with psoriasis receiving methotrexate doses between 7.5 mg and 30 mg. Metabolism Methotrexate is partially metabolized by intestinal flora after oral administration. Methotrexate primarily undergoes hepatic and intracellular metabolism to active polyglutamated forms which can be converted back to methotrexate by hydrolase enzymes.
Methotrexate also undergoes minor metabolism to active 7-hydroxymethotrexate. Excretion Methotrexate primarily undergoes renal excretion by glomerular filtration and active tubular secretion that is dependent upon dosage and route of administration. Biliary excretion accounts for ≤ 10% of the methotrexate dose.
Specific Populations The effect of hepatic impairment on the pharmacokinetics of methotrexate is unknown. Pediatric Patients In pediatric patients with leukemia, oral absorption (23% to 95%) of methotrexate is variable and dose-dependent. The difference between highest and lowest peak methotrexate concentrations (C max 0.11 to 2.3 micromolar after a 20 mg/m 2 dose) was 20-fold.
The time to peak concentration (T max 0.67 to 4 hours after a 15 mg/m 2 dose) and fraction of dose absorbed is variable. The absorption of doses greater than 40 mg/m 2 is significantly less than that of lower doses. In pediatric patients with pJIA, plasma concentrations of methotrexate are variable.
Following oral administration of methotrexate 6.4 mg/m 2 /week to 11.2 mg/m 2 /week, mean serum concentrations were 0.59 micromolar (0.03 to 1.40) at 1 hour, 0.44 micromolar (0.01 to 1.00) at 2 hours, and 0.29 micromolar (0.06 to 0.58) at 3 hours. In pediatric patients receiving methotrexate for acute lymphoblastic leukemia (6.3 mg/m 2 to 30 mg/m 2 ) or for JIA (3.75 mg/m 2 to 26.2 mg/m 2 ), the terminal half-life has been reported to range from 0.7 to 5.8 hours or from 0.9 to 2.3 hours, respectively. Patients with Renal impairment The elimination half-life of methotrexate is variable and increases with the severity of renal impairment.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Methotrexate inhibits dihydrofolic acid reductase. Dihydrofolates must be reduced to tetrahydrofolates by this enzyme before they can be utilized as carriers of one-carbon groups in the synthesis of purine nucleotides and thymidylate. Therefore, methotrexate interferes with DNA synthesis, repair, and cellular replication.
Actively proliferating tissues such as malignant cells, bone marrow, fetal cells, buccal and intestinal mucosa, and cells of the urinary bladder are in general more sensitive to this effect of methotrexate. The mechanism of action in rheumatoid arthritis and in psoriasis is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING NDC: 71335-1118-1: 30 Tablets in a BOTTLE NDC: 71335-1118-2: 12 Tablets in a BOTTLE NDC: 71335-1118-3: 20 Tablets in a BOTTLE NDC: 71335-1118-4: 100 Tablets in a BOTTLE NDC: 71335-1118-5: 36 Tablets in a BOTTLE NDC: 71335-1118-6: 24 Tablets in a BOTTLE NDC: 71335-1118-7: 90 Tablets in a BOTTLE NDC: 71335-1118-8: 4 Tablets in a BOTTLE Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 91504
📋 Description ▾
11 DESCRIPTION Methotrexate is dihydrofolate reductase inhibitor with the chemical name of N-[4-[[(2,4 diamino-6-pteridinyl) methyl]methylamino]benzoyl]-L glutamic acid. The molecular formula is C 20 H 22 N 8 O 5 and the molecular weight is 454.4 g/mol. The structural formula is: Methotrexate Tablets, USP for oral use are available in bottles of 100 tablets.
Each methotrexate tablet contains 2.5 mg methotrexate equivalent to 2.74 mg methotrexate sodium and the following inactive ingredients: colloidal silicon dioxide, FD&C Red No. 40 Aluminum Lake, lactose monohydrate, magnesium stearate, microcrystalline cellulose, pregelatinized starch (corn), sodium carbonate (monohydrate), sodium lauryl sulfate and sodium starch glycolate (potato).
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information ). Embryo-Fetal Toxicity • Advise females of reproductive potential of the potential risk to a fetus and to inform their healthcare provider of a known or suspected pregnancy [see Contraindications (4) , Warnings and Precautions (5.1) , Use in Specific Populations (8.1) ]. • Advise females of reproductive potential to use effective contraception during treatment with methotrexate tablets and for 6 months after the final dose [see Use in Specific Populations (8.3) ]. • Advise males of reproductive potential to use effective contraception during treatment with methotrexate tablets and for 3 months after the final dose [see Use in Specific Populations (8.3) ].
Hypersensitivity Reactions: Advise patients and their caregivers of the potential risk of hypersensitivity and that methotrexate tablets are contraindicated in patients with a history of hypersensitivity reactions to methotrexate. Instruct patients to seek immediate medical attention for signs of a hypersensitivity reaction [see Warnings and Precautions (5.2) ]. Myelosuppression and Serious Infections: Inform patients and their caregivers that methotrexate tablets can cause myelosuppression and the need for frequent monitoring of blood cell counts.
Advise patients and their caregivers to immediately report new onset fever, symptoms of infection, easy bruising or persistent bleeding to their healthcare provider [see Warnings and Precautions (5.3 , 5.11) ]. Gastrointestinal Toxicity: Advise patients and their caregivers to report new or worsening diarrhea, vomiting, or stomatitis to their healthcare provider. Advise patients to immediately contact their healthcare provider for high fever, rigors, persistent or severe abdominal pain, severe constipation, hematemesis, or melena [see Warnings and Precautions (5.4) ].
Hepatotoxicity: Advise patients and their caregivers to report signs or symptoms of hepatic toxicity to their healthcare provider [see Warnings and Precautions (5.5) ]. Pulmonary Toxicity: Advise patients and their caregivers to report new or worsening cough, fever, or dyspnea to their healthcare provider [see Warnings and Precautions (5.6) ]. Dermatologic Reactions: Advise patients and their caregivers that methotrexate tablets can cause serious skin rash and to immediately contact their healthcare provider for new or worsening skin rash.
Advise patients and their caregivers to avoid excessive sun exposure and use sun protection measures [see Warnings and Precautions (5.7) ]. Renal Toxicity: Advise patients and their caregivers to immediately contact their healthcare provider for signs or symptoms of renal toxicity, such as marked increases or decreases in urinary output [see Warnings and Precautions (5.8) ]. Risk of Serious Adverse Reactions with Medication Error: For patients who are prescribed a once weekly dosing regimen, advise patients and caregivers that the recommended dosage is to be taken once weekly as a single dose and that mistakenly taking the recommended weekly dosage once daily has led to fatal adverse reactions [see Warnings and Precautions (5.9) ].
Neurotoxicity: Advise patients and their caregivers to report new neurological signs or symptoms to their healthcare provider [see Warnings and Precautions (5.12) ]. Secondary Malignancies: Advise patients on the risk of second primary malignancies during treatment with methotrexate tablets [see Warnings and Precautions (5.13) ]. Lactation: Instruct women not to breastfeed during treatment with methotrexate tablets and for 1 week after the final dose [see Use in Specific Populations (8.2) ].
Infertility: Advise females and males of reproductive potential that methotrexate may impair fertility [see Warnings and Precautions (5.16) , Use in Specific Populations (8.3) ]. Drug Interactions: Advise patients and caregivers to inform their healthcare provider of all concomitant medications, inclu…