
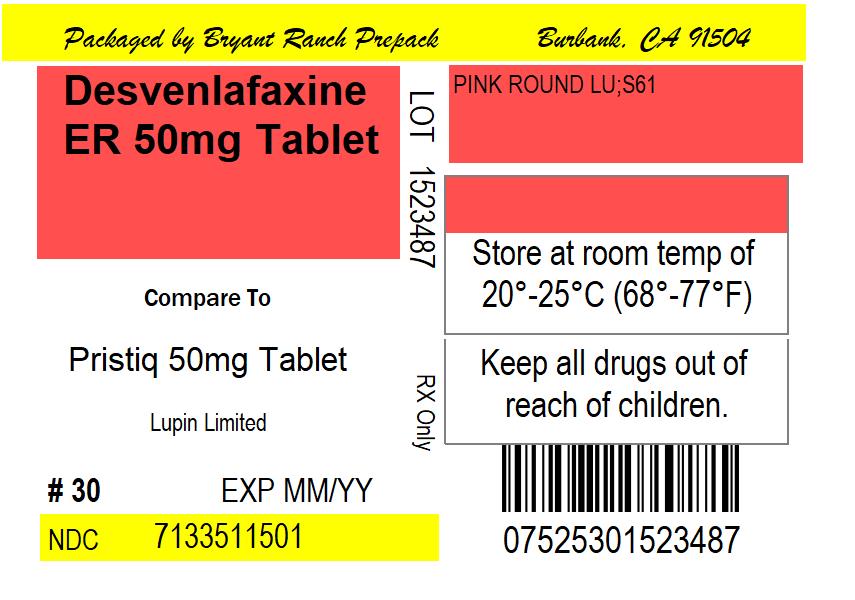
Desvenlafaxine Succinate 50 mg Tablet, Film Coated, Extended Release, 28-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Serotonin and Norepinephrine Reuptake Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Desvenlafaxine is used to treat depression. Desvenlafaxine is in a class of medications called selective serotonin and norepinephrine reuptake inhibitors (SNRIs). It works by increasing the amounts of serotonin and norepinephrine, natural substances in the brain that help maintain mental balance.
Read the full MedlinePlus article ↗- Desvenlafaxine is an antidepressant approved for adults with major depressive disorder (MDD). It belongs to a class called SNRIs — drugs that help keep more of two brain chemicals,...
- What is desvenlafaxine actually used for?
- Antidepressants like desvenlafaxine typically take time to work — it's not something you feel immediately. Clinical studies that showed effectiveness ran for about 8 weeks. Your pr...
- How long will it take before I start feeling better?
Patient education
Supplement & herbal interactions
Desvenlafaxine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.7941 | $22.23 / 28 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Desvenlafaxine 50 mg 00054-0400-13 | Hikma | 30 tablets | $0.395 | AB | Availability likely | — |
| Desvenlafaxine 50 mg 00591-3659-30 | Actavis | 30 tablets | $0.395 | AB | Availability likely | — |
| Desvenlafaxine Succinate 50 mg 33342-0388-07 | Macleods | 30 tablets | $0.395 | AB | Availability likely | — |
| Desvenlafaxine 50 mg 60687-0607-21 | American | 1 tablet | $0.395 | — | Availability likely | — |
| Desvenlafaxine 50 mg 70436-0012-04 | Slate | 30 tablets | $0.395 | AB | Availability likely | — |
| Desvenlafaxine 50 mg 72603-0556-01 | NorthStar | 30 tablets | $0.395 | AB | Availability likely | — |
| Pristiq Extended-Release 50 mg 00008-1211-01 | Wyeth | 90 tablets | $13.956 | AB | Availability likely | — |
| Desvenlafaxine 50 mg 10135-0821-10 | Marlex | 1000 tablets | — | AB | FDA listed | — |
| Desvenlafaxine 50 mg 46708-0540-10 | Alembic | 100 tablets | — | AB | FDA listed | — |
| Desvenlafaxine 50 mg 50090-4806-00 | A-S | 30 tablets | — | — | FDA listed | — |
| Desvenlafaxine 50 mg 50090-5293-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Desvenlafaxine Succinate 50 mg 50090-6894-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Desvenlafaxine 50 mg 50090-7737-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Desvenlafaxine 50 mg 51991-0311-01 | Breckenridge | 100 tablets | — | AB | FDA listed | — |
| Desvenlafaxine Er 50 mg 61919-0882-28 | Direct_Rx | 28 tablets | — | AB | FDA listed | — |
| Desvenlafaxine 50 mg 63629-7525-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Desvenlafaxine 50 mg 68071-3790-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Desvenlafaxine Succinate 50 mg 68180-0592-02 | Lupin | 500 tablets | — | AB | FDA listed | — |
| Desvenlafaxine 50 mg 68788-7194-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Desvenlafaxine 50 mg 68788-8760-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Desvenlafaxine Succinate 50 mgthis 71335-1150-02 | Bryant | 28 tablets | — | AB | FDA listed | — |
| Desvenlafaxine 50 mg 71335-1700-01 | Bryant | 30 tablets | — | — | FDA listed | — |
| Desvenlafaxine 50 mg 71335-1753-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Desvenlafaxine 50 mg 71335-2575-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| desvenlafaxine 50 mg 72189-0147-28 | DIRECT | 28 tablets | — | AB | FDA listed | — |
| Desvenlafaxine ER 50 mg 72189-0567-28 | Direct_rx | 28 tablets | — | AB | FDA listed | — |
| Desvenlafaxine 50 mg 72888-0143-00 | Advagen | 1000 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-1150-01 | 30 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE (71335-1150-1) | 2019-08-28 | Active |
| 71335-1150-02 You're viewing this | 28 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE (71335-1150-2) | 2019-03-13 | Active |
| 71335-1150-03 | 60 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE (71335-1150-3) | 2022-09-20 | Active |
| 71335-1150-04 | 90 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE (71335-1150-4) | 2022-09-20 | Active |
| 71335-1150-05 | 180 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE (71335-1150-5) | 2022-09-20 | Active |
You're viewing the smallest of 5 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-1150-02?
What is the difference between NDC 71335-1150-02 and NDC 71335-1150-01?
What NDC number is used to bill for this package of Desvenlafaxine Succinate 50 mg Tablet, Film Coated, Extended Release?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
BOXED WARNING WARNING: SUICIDAL THOUGHTS AND BEHAVIORS Antidepressants increased the risk of suicidal thoughts and behavior in children, adolescents, and young adults in short-term studies. These studies did not show an increase in the risk of suicidal thoughts and behavior with antidepressant use in patients over age 24; there was a reduction in risk with antidepressant use in patients aged 65 and older [see WARNINGS AND PRECAUTIONS ( 5.1 )]. In patients of all ages who are started on antidepressant therapy, monitor closely for worsening, and for emergence of suicidal thoughts and behaviors.
Advise families and caregivers of the need for close observation and communication with the prescriber [see WARNINGS AND PRECAUTIONS ( 5.1 )]. Desvenlafaxine extended-release tablets are not approved for use in pediatric patients [see USE IN SPECIFIC POPULATIONS ( 8.4 ) ] . WARNING: SUICIDAL THOUGHTS AND BEHAVIORS See full prescribing information for complete boxed warning.
Increased the risk of suicidal thoughts and behaviors in children, adolescents and young adults taking antidepressants ( 5.1 ). Closely monitor for clinical worsening and emergence of suicidal thoughts and behaviors ( 5.1 ). Desvenlafaxine extended-release tablets are not approved for use in pediatric patients ( 8.4 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Desvenlafaxine extended-release tablet is indicated for the treatment of adults with major depressive disorder (MDD) [see CLINICAL STUDIES ( 14 )]. Desvenlafaxine extended-release tablet, is a serotonin and norepinephrine reuptake inhibitor (SNRI) indicated for the treatment of adults with major depressive disorder (MDD) ( 1 ).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended dose: 50 mg once daily with or without food ( 2.1 ). There was no evidence that doses greater than 50 mg per day confer any additional benefit ( 2.1 ). The 25 mg per day dose is intended for a gradual reduction in dose when discontinuing treatment or dosing in severe renal and end-stage renal disease patients ( 2.1 ).
Discontinuation: Reduce dose gradually whenever possible ( 2.1 ). Take tablets whole; do not divide, crush, chew, or dissolve ( 2.1 ). Moderate renal impairment: Maximum dose 50 mg per day ( 2.2 ).
Severe renal impairment and end-stage renal disease: Maximum dose 25 mg per day or 50 mg every other day ( 2.2 ). Moderate to severe hepatic impairment: Maximum dose 100 mg per day ( 2.3 ).
2.1General Instructions for Use The recommended dose for desvenlafaxine extended-release tablets are 50 mg once daily, with or without food. The 50 mg dose is both a starting dose and the therapeutic dose. Desvenlafaxine extended-release tablets should be taken at approximately the same time each day.
Tablets must be swallowed whole with fluid and not divided, crushed, chewed, or dissolved. In clinical studies, doses of 10 mg to 400 mg per day were studied. In clinical studies, doses of 50 mg to 400 mg per day were shown to be effective, although no additional benefit was demonstrated at doses greater than 50 mg per day and adverse reactions and discontinuations were more frequent at higher doses.
The 25 mg per day dose is intended for a gradual reduction in dose when discontinuing treatment. When discontinuing therapy, gradual dose reduction is recommended whenever possible to minimize discontinuation symptoms [see DOSAGE AND ADMINISTRATION ( 2.5 ) and WARNINGS AND PRECAUTIONS ( 5.7 )] .
2.2Dosage Recommendations for Patients with Renal Impairment The maximum recommended dose in patients with moderate renal impairment (24-hr creatinine clearance [Cl Cr ] = 30 to 50 mL/min, Cockcroft-Gault [C-G]) is 50 mg per day. The maximum recommended dose in patients with severe renal impairment (Cl Cr 15 to 29 mL/min, C-G) or end-stage renal disease (ESRD, Cl Cr <15 mL/min, C-G) is 25 mg every day or 50 mg every other day. Supplemental doses should not be given to patients after dialysis [see USE IN SPECIFIC POPULATIONS ( 8.6 ) and CLINICAL PHARMACOLOGY ( 12.3 )].
2.3Dosage Recommendations for Patients with Hepatic Impairment The recommended dose in patients with moderate to severe hepatic impairment (Child-Pugh score 7 to 15) is 50 mg per day. Dose escalation above 100 mg per day is not recommended [see USE IN SPECIFIC POPULATIONS ( 8.7 ) and CLINICAL PHARMACOLOGY ( 12.3 )].
2.4Maintenance/Continuation/Extended Treatment It is generally agreed that acute episodes of major depressive disorder require several months or longer of sustained pharmacologic therapy. Longer-term efficacy of desvenlafaxine (50 to 400 mg) was established in two maintenance trials [see CLINICAL STUDIES ( 14 )]. Patients should be periodically reassessed to determine the need for continued treatment.
2.5Discontinuing Desvenlafaxine Adverse reactions may occur upon discontinuation of desvenlafaxine [see Warnings and Precautions ( 5.7 )]. Gradually reduce the dosage rather than stopping desvenlafaxine abruptly when discontinuing therapy with desvenlafaxine. In some patients, discontinuation may need to occur over a period of several months
2.6Switching Patients From Other Antidepressants to Desvenlafaxine Discontinuation symptoms have been reported when switching patients from other antidepressants, including venlafaxine, to desvenlafaxine. Tapering of the initial antidepressant may be necessary to minimize discontinuation symptoms .
2.7Switching Patients to or from a Monoamine Oxidase Inhibitor (MAOI) Intended to Treat Psychiatric Disorders At least 14 days should elapse between discontinuation of an MAOI intended to treat psychiatric disorders and initiation of therapy with desvenlafaxine extended-release tablets. Conversely,…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Desvenlafaxine extended-release tablets are available as 25 mg, 50 mg and 100 mg tablets. 25 mg, tan, biconvex, round shaped film-coated tablets, debossed with "LU" on one side and "S67" on the other side 50 mg, light pink, biconvex, round shaped film-coated tablets, debossed with "LU" on one side and "S61" on the other side. 100 mg, reddish-orange, biconvex, round shaped film-coated tablets, debossed with "LU" on one side and "S62" on the other side.
Desvenlafaxine extended-release tablets: 25 mg, 50 mg and 100 mg ( 3 ). Each tablet contains 38 mg, 76 mg or 152 mg of desvenlafaxine succinate monohydrate equivalent to 25 mg, 50 mg or 100 mg of desvenlafaxine, respectively ( 3 ).
⛔ Contraindications ▾
4 CONTRAINDICATIONS Hypersensitivity to desvenlafaxine succinate, venlafaxine hydrochloride or to any excipients in the desvenlafaxine formulation. Angioedema has been reported in patients treated with desvenlafaxine [see ADVERSE REACTIONS ( 6.1 )]. The use of MAOIs intended to treat psychiatric disorders with desvenlafaxine or within 7 days of stopping treatment with desvenlafaxine is contraindicated because of an increased risk of serotonin syndrome.
The use of desvenlafaxine within 14 days of stopping an MAOI intended to treat psychiatric disorders is also contraindicated [see DOSAGE AND ADMINISTRATION ( 2.7 ) and WARNINGS AND PRECAUTIONS ( 5.2 )]. Starting desvenlafaxine in a patient who is being treated with MAOIs such as linezolid or intravenous methylene blue is also contraindicated because of an increased risk of serotonin syndrome [see DOSAGE AND ADMINISTRATION ( 2.8 ) and WARNINGS AND PRECAUTIONS ( 5.2 )]. Hypersensitivity to desvenlafaxine succinate, venlafaxine hydrochloride or any excipients in the desvenlafaxine formulation ( 4 ).
Serotonin Syndrome and MAOIs : Do not use MAOIs intended to treat psychiatric disorders with desvenlafaxine or within 7 days of stopping treatment with desvenlafaxine. Do not use desvenlafaxine within 14 days of stopping an MAOI intended to treat psychiatric disorders. In addition, do not start desvenlafaxine in a patient who is being treated with linezolid or intravenous methylene blue ( 4 ).
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Serotonin Syndrome: Increased risk when co-adminstered with other serotonergic agents, but also when taken alone. If it occurs, discontinue desvenlafaxine and serotonergic agents and initiate supportive treatment ( 5.2 ). Elevated Blood Pressure: Control hypertension before initiating treatment.
Monitor blood pressure regularly during treatment ( 5.3 ). Increased Risk of Bleeding: Concomitant use of aspirin, NSAIDs, other antiplatelet drugs, warfarin, and other anticoagulants may increase this risk ( 5.4 ). Angle Closure Glaucoma: Avoid use of antidepressants, including desvenlafaxine in patients with untreated anatomically narrow angles treated ( 5.5 ).
Activation of Mania/Hypomania: Use cautiously in patients with Bipolar Disorder. Caution patients about risk of activation of mania/hypomania ( 5.6 ). Discontinuation Syndrome: Taper dose when possible and monitor for discontinuation symptoms ( 5.7 ).
Seizure : Can occur. Use cautiously in patients with seizure disorder ( 5.8 ). Hyponatremia: Can occur in association with SIADH ( 5.9 ).
Interstitial Lung Disease and Eosinophilic Pneumonia: Can occur ( 5.10 ). Sexual Dysfunction: Desvenlafaxine may cause symptoms of sexual dysfunction ( 5.11 )
5.1Suicidal Thoughts and Behaviors in Pediatric and Young Adult Patients Patients with MDD, both adult and pediatric, may experience worsening of their depression and/or the emergence of suicidal ideation and behavior (suicidality) or unusual changes in behavior, whether or not they are taking antidepressant medications, and this risk may persist until significant remission occurs. Suicide is a known risk of depression and certain other psychiatric disorders, and these disorders themselves are the strongest predictors of suicide.
There has been a long-standing concern, however, that antidepressants may have a role in inducing worsening of depression and the emergence of suicidality in certain patients during the early phases of treatment. Pooled analyses of short-term placebo-controlled studies of antidepressant drugs (SSRIs and others) showed that these drugs increase the risk of suicidal thinking and behavior (suicidality) in children, adolescents, and young adults (ages 18 to 24) with major depressive disorder (MDD) and other psychiatric disorders.
Short-term studies did not show an increase in the risk of suicidality with antidepressants compared to placebo in adults beyond age 24; there was a reduction with antidepressants compared to placebo in adults aged 65 and older. The pooled analyses of placebo-controlled studies in children and adolescents with MDD, obsessive compulsive disorder (OCD), or other psychiatric disorders included a total of 24 short-term studies of 9 antidepressant drugs in over 4,400 patients. The pooled analyses of placebo-controlled studies in adults with MDD or other psychiatric disorders included a total of 295 short-term studies (median duration of 2 months) of 11 antidepressant drugs in over 77,000 patients.
There was considerable variation in risk of suicidality among drugs, but a tendency toward an increase in the younger patients for almost all drugs studied. There were differences in absolute risk of suicidality across the different indications, with the highest incidence in MDD. The risk differences (drug vs. placebo), however, were relatively stable within age strata and across indications.
These risk differences (drug-placebo difference in the number of cases of suicidality per 1,000 patients treated) are provided in Table 1. Table 1 Age Range Drug-Placebo Difference in Number of Cases of Suicidality per 1,000 Patients Treated Increases Compared to Placebo <18 14 additional cases 18 to 24 5 additional cases Decreases Compared to Placebo 25 to 64 1 fewer case ≥65 6 fewer cases No suicides occurred in any of the pediatric studies. There were suicides in the adult studies, but the number was not sufficient to reach any conclusion about drug effect on suicide.
It is unknown wh…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the label. Hypersensitivity [see CONTRAINDICATIONS ( 4 )] Suicidal Thoughts and Behaviors in Pediatric and Young Adult Patients [see WARNINGS AND PRECAUTIONS ( 5.1 )] Serotonin Syndrome [see WARNINGS AND PRECAUTIONS ( 5.2 )] Elevated Blood Pressure [see WARNINGS AND PRECAUTIONS ( 5.3 )] Increased Risk of Bleeding [see WARNINGS AND PRECAUTIONS ( 5.4 )] Angle Closure Glaucoma [see WARNINGS AND PRECAUTIONS ( 5.5 )] Activation of Mania/ Hypomania [see WARNINGS AND PRECAUTIONS ( 5.6 )] Discontinuation Syndrome [see WARNINGS AND PRECAUTIONS ( 5.7 )] Seizure [see WARNINGS AND PRECAUTIONS ( 5.8 )] Hyponatremia [see WARNINGS AND PRECAUTIONS ( 5.9 )] Interstitial Lung Disease and Eosinophilic Pneumonia [see WARNINGS AND PRECAUTIONS ( 5.10 )] Sexual Dysfunction [see Warnings and Precautions [see WARNINGS AND PRECAUTIONS ( 5.11 )] Most common adverse reactions (incidence ≥5% and twice the rate of placebo in the 50 or 100 mg dose groups) were: nausea, dizziness, insomnia, hyperhidrosis, constipation, somnolence, decreased appetite, anxiety, and specific male sexual function disorders ( 6.1 ).
To report SUSPECTED ADVERSE REACTIONS, contact Lupin Pharmaceuticals Inc. at 1-800-399-2561, or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Studies Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in clinical practice. Patient Exposure Desvenlafaxine was evaluated for safety in 8,394 patients diagnosed with major depressive disorder who participated in multiple-dose pre-marketing studies, representing 2,784 patient-years of exposure.
Of the total 8,394 patients exposed to at least one dose of desvenlafaxine; 2,116 were exposed to desvenlafaxine for 6 months, representing 1,658 patient-years of exposure, and 421 were exposed for one year, representing 416 patient-years of exposure. Adverse Reactions Reported as Reasons for Discontinuation of Treatment In the pre-marketing pooled 8-week placebo-controlled studies in patients with MDD, 1,834 patients were exposed to desvenlafaxine (50 to 400 mg). Of the 1,834 patients, 12% discontinued treatment due to an adverse reaction, compared with 3% of the 1,116 placebo-treated patients.
At the recommended dose of 50 mg, the discontinuation rate due to an adverse reaction for desvenlafaxine succinate (4.1%) was similar to the rate for placebo (3.8%). For the 100 mg dose of desvenlafaxine the discontinuation rate due to an adverse reaction was 8.7%. The most common adverse reactions leading to discontinuation in at least 2% and at a rate greater than placebo of the desvenlafaxine treated patients in the short-term studies, up to 8 weeks, were: nausea (4%); dizziness, headache and vomiting (2% each).
In a longer-term study, up to 9 months, the most common was vomiting (2%). Common Adverse Reactions in Placebo-Controlled MDD Studies The most commonly observed adverse reactions in desvenlafaxine treated MDD patients in pre-marketing pooled 8-week, placebo-controlled, fixed-dose studies (incidence ≥ 5% and at least twice the rate of placebo in the 50 or 100 mg dose groups) were: nausea, dizziness, insomnia, hyperhidrosis, constipation, somnolence, decreased appetite, anxiety, and specific male sexual function disorders.
Table 2 shows the incidence of common adverse reactions that occurred in ≥ 2% of desvenlafaxine extended-release tablets treated MDD patients and twice the rate of placebo at any dose in the pre-marketing pooled 8-week, placebo-controlled, fixed dose clinical studies Table 2: Common Adverse Reactions (≥ 2% in any Fixed-Dose Group and Twice the Rate of Placebo) in Pre-marketing Pooled MDD 8-Week Placebo-Controlled Studies Percentage of Patients Reporting Reaction System Organ…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Drugs Having Clinically Important Interactions with Desvenlafaxine Table 8: Clinically Important Drug Interactions with Desvenlafaxine Monoamine Oxidase Inhibitors (MAOI) Clinical Impact The concomitant use of SSRIs and SNRIs including desvenlafaxine with MAOIs increases the risk of serotonin syndrome. Intervention Concomitant use of desvenlafaxine is contraindicated: ● With an MAOI intended to treat psychiatric disorders or within 7 days of stopping treatment with desvenlafaxine. ● Within 14 days of stopping an MAOI intended to treat psychiatric disorders. ● In a patient who is being treated with linezolid or intravenous methylene blue. [see DOSAGE AND ADMINISTRATION ( 2.7 ), CONTRAINDICATIONS ( 4 ) and WARNINGS AND PRECAUTIONS ( 5.2 )].
Examples selegiline, tranylcypromine, isocarboxazid, phenelzine, linezolid, methylene blue Other Serotonergic Drugs Clinical Impact Concomitant use of desvenlafaxine with other serotonergic drugs increases the risk of serotonin syndrome. Intervention Monitor for symptoms of serotonin syndrome when desvenlafaxine is used concomitantly with other drugs that may affect the serotonergic neurotransmitter systems. If serotonin syndrome occurs, consider discontinuation of desvenlafaxine and/or concomitant serotonergic drugs [see WARNINGS AND PRECAUTIONS ( 5.2 )].
Examples other SNRIs, SSRIs, triptans, tricyclic antidepressants, opioids, lithium, buspirone, amphetamines, tryptophan, and St. John's Wort Drugs that Interfere with Hemostasis Clinical Impact Concomitant use of desvenlafaxine with an antiplatelet or anticoagulant drug may potentiate the risk of bleeding. This may be due to the effect of desvenlafaxine on the release of serotonin by platelets.
Intervention Closely monitor for bleeding for patients receiving an antiplatelet or anticoagulant drug when desvenlafaxine is initiated or discontinued [see WARNINGS AND PRECAUTIONS ( 5.4 )] . Examples NSAIDs, aspirin, and warfarin Drugs that are Primarily Metabolized by CYP2D6 Clinical Impact Concomitant use of desvenlafaxine increases C max and AUC of a drug primarily metabolized by CYP2D6 which may increase the risk of toxicity of the CYP2D6 substrate drug [see CLINICAL PHARMACOLOGY ( 12.3 )] . Intervention Original dose should be taken when co-administered with desvenlafaxine 100 mg or lower.
Reduce the dose of these drugs by up to one-half if co-administered with 400 mg of desvenlafaxine. Examples desipramine, atomoxetine, dextromethorphan, metoprolol, nebivolol, perphenazine, tolterodine
7.2Drugs Having No Clinically Important Interactions with desvenlafaxine Based on pharmacokinetic studies, no dosage adjustment is required for drugs that are mainly metabolized by CYP3A4 (e.g., midazolam), or for drugs that are metabolized by both CYP2D6 and CYP3A4 (e.g., tamoxifen, aripiprazole), when administered concomitantly with desvenlafaxine [see CLINICAL PHARMACOLOGY ( 12.3 )].
7.3Alcohol A clinical study has shown that desvenlafaxine does not increase the impairment of mental and motor skills caused by ethanol. However, as with all CNS-active drugs, patients should be advised to avoid alcohol consumption while taking desvenlafaxine.
7.4Drug-Laboratory Test Interactions False-positive urine immunoassay screening tests for phencyclidine (PCP) and amphetamine have been reported in patients taking desvenlafaxine. This is due to lack of specificity of the screening tests. False positive test results may be expected for several days following discontinuation of desvenlafaxine therapy.
Confirmatory tests, such as gas chromatography/mass spectrometry, will distinguish desvenlafaxine from PCP and amphetamine.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Third trimester use may result in neonatal discontinuation syndrome ( 8.1 ). Geriatric Use: There is an increased incidence of orthostatic hypotension in desvenlafaxine treated patients ≥ 65 years ( 6.1 and 8.5 ).
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antidepressants during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Antidepressants at 1-844-405-6185. Risk Summary Based on data from published observational studies, exposure to SNRIs, particularly in the month before delivery, has been associated with a less than 2-fold increase in the risk of postpartum hemorrhage [see WARNINGS AND PRECAUTIONS ( 5.4 ) AND CLINICAL CONSIDERATIONS] .
There are no published studies on desvenlafaxine in pregnant women; however published epidemiologic studies of pregnant women exposed to venlafaxine, the parent compound, have not reported a clear association with adverse developmental outcomes (see Data) . There are risks associated with untreated depression in pregnancy and with exposure to SNRIs and SSRIs, including desvenlafaxine, during pregnancy ( see Clinical Considerations). In reproductive developmental studies in rats and rabbits treated with desvenlafaxine succinate, there was no evidence of teratogenicity at a plasma exposure (AUC) that is up to 19-times (rats) and 0.5-times (rabbits) the exposure at an adult human dose of 100 mg per day.
However, fetotoxicity and pup deaths were observed in rats at 4.5-times the AUC exposure observed with an adult human dose of 100 mg per day. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk : A prospective longitudinal study of 201 women with a history of major depression who were euthymic at the beginning of pregnancy, showed that women who discontinued antidepressant medication during pregnancy were more likely to experience a relapse of major depression than women who continued antidepressant medication.
Maternal Adverse Reactions: Exposure to desvenlafaxine in mid to late pregnancy may increase the risk for preeclampsia, and exposure to desvenlafaxine in the month before delivery may be associated with an increased risk of postpartum hemorrhage [see WARNINGS AND PRECAUTIONS ( 5.4 )] . Fetal/Neonatal adverse reactions: Exposure to SNRIs or SSRIs in late pregnancy may lead to an increased risk for neonatal complications requiring prolonged hospitalization, respiratory support, and tube feeding. Monitor neonates who were exposed to desvenlafaxine in the third trimester of pregnancy for drug discontinuation syndrome (see Data).
Data Human Data: Published epidemiological studies of pregnant women exposed to the parent compound venlafaxine have not reported a clear association with major birth defects or miscarriage. Methodological limitations of these observational studies include possible exposure and outcome misclassification, lack of adequate controls, adjustment for confounders, and confirmatory studies; therefore, these studies cannot establish or exclude any drug-associated risk during pregnancy. Retrospective cohort studies based on claims data have shown an association between venlafaxine use and preeclampsia, compared to depressed women who did not take an antidepressant during pregnancy.
One study that assessed venlafaxine exposure in the second trimester or first half of the third trimester and preeclampsia showed an increased risk compared to unexposed depressed women [adjusted (adj) RR 1.5…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antidepressants during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Antidepressants at 1-844-405-6185. Risk Summary Based on data from published observational studies, exposure to SNRIs, particularly in the month before delivery, has been associated with a less than 2-fold increase in the risk of postpartum hemorrhage [see WARNINGS AND PRECAUTIONS ( 5.4 ) AND CLINICAL CONSIDERATIONS] .
There are no published studies on desvenlafaxine in pregnant women; however published epidemiologic studies of pregnant women exposed to venlafaxine, the parent compound, have not reported a clear association with adverse developmental outcomes (see Data) . There are risks associated with untreated depression in pregnancy and with exposure to SNRIs and SSRIs, including desvenlafaxine, during pregnancy ( see Clinical Considerations). In reproductive developmental studies in rats and rabbits treated with desvenlafaxine succinate, there was no evidence of teratogenicity at a plasma exposure (AUC) that is up to 19-times (rats) and 0.5-times (rabbits) the exposure at an adult human dose of 100 mg per day.
However, fetotoxicity and pup deaths were observed in rats at 4.5-times the AUC exposure observed with an adult human dose of 100 mg per day. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk : A prospective longitudinal study of 201 women with a history of major depression who were euthymic at the beginning of pregnancy, showed that women who discontinued antidepressant medication during pregnancy were more likely to experience a relapse of major depression than women who continued antidepressant medication.
Maternal Adverse Reactions: Exposure to desvenlafaxine in mid to late pregnancy may increase the risk for preeclampsia, and exposure to desvenlafaxine in the month before delivery may be associated with an increased risk of postpartum hemorrhage [see WARNINGS AND PRECAUTIONS ( 5.4 )] . Fetal/Neonatal adverse reactions: Exposure to SNRIs or SSRIs in late pregnancy may lead to an increased risk for neonatal complications requiring prolonged hospitalization, respiratory support, and tube feeding. Monitor neonates who were exposed to desvenlafaxine in the third trimester of pregnancy for drug discontinuation syndrome (see Data).
Data Human Data: Published epidemiological studies of pregnant women exposed to the parent compound venlafaxine have not reported a clear association with major birth defects or miscarriage. Methodological limitations of these observational studies include possible exposure and outcome misclassification, lack of adequate controls, adjustment for confounders, and confirmatory studies; therefore, these studies cannot establish or exclude any drug-associated risk during pregnancy. Retrospective cohort studies based on claims data have shown an association between venlafaxine use and preeclampsia, compared to depressed women who did not take an antidepressant during pregnancy.
One study that assessed venlafaxine exposure in the second trimester or first half of the third trimester and preeclampsia showed an increased risk compared to unexposed depressed women [adjusted (adj) RR 1.57, 95% CI 1.29 to 1.91]. Preeclampsia was observed at venlafaxine doses equal to or greater than 75 mg/day and a duration of treatment >30 days. Another study that assessed venlafaxine exposure in gestational weeks 10 to 20 and preeclampsia showed an incr…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of desvenlafaxine, have not been established in pediatric patients for the treatment of MDD. Efficacy was not demonstrated in two adequate and well controlled, 8-week, randomized, double-blind, placebo-controlled, parallel group studies conducted in 587 patients (7 to 17 years of age) for the treatment of MDD. Antidepressants, such as desvenlafaxine, increase the risk of suicidal thoughts and behaviors in pediatric patients [see the Boxed Warning and Warnings and Precautions ( 5.1 ) ] .
Desvenlafaxine was associated with a decrease in body weight in placebo controlled trials in pediatric patients with MDD. The incidence of weight loss (≥3.5% of baseline weight) was 22%, 14%, and 7% for patients treated with low dose desvenlafaxine, high dose desvenlafaxine, and placebo, respectively. The risks associated with longer term desvenlafaxine use were assessed in 6-month, open-label extension studies in pediatric patients (7 to 17 years of age) with MDD.
Pediatric patients (7 to 17 years of age) had mean changes in weight that approximated expected changes, based on data from age-and sex-matched peers. In clinical trials, when compared to adult patients receiving the same dose of desvenlafaxine, exposure to desvenlafaxine was similar in adolescent patients 12 to 17 years of age, and was about 30% higher in pediatric patients 7 to 11 years of age. Juvenile Animal Studies In a juvenile animal study, male and female rats were treated with desvenlafaxine (75, 225 and 675 mg/kg/day) starting on postnatal day (PND) 22 through 112.
Behavioral deficits (longer time immobile in a motor activity test, longer time swimming in a straight channel test, and lack of habituation in an acoustic startle test) were observed in males and females but were reversed after a recovery period. A No Adverse Effect Level (NOAEL) was not identified for these deficits. The Low Adverse Effect Level (LOAEL) was 75 mg/kg/day which was associated with plasma exposure (AUC) twice the levels measured with a pediatric dose of 100 mg/day.
In a second juvenile animal study, male and female rats were administered desvenlafaxine (75, 225 or 675 mg/kg/day) for 8 to 9 weeks starting on PND 22 and were mated with naïve counterparts. Delays in sexual maturation and decreased fertility, number of implantation sites and total live embryos were observed in treated females at all doses. The LOAEL for these findings is 75 mg/kg/day which was associated with an AUC twice the levels measured with a pediatric dose of 100 mg/day.
These findings were reversed at the end of a 4-week recovery period. The relevance of these findings to humans is not known.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 4,158 patients in pre-marketing clinical studies with desvenlafaxine, 6% were 65 years of age or older. No overall differences in safety or efficacy were observed between these patients and younger patients; however, in the short-term placebo-controlled studies, there was a higher incidence of systolic orthostatic hypotension in patients ≥65 years of age compared to patients <65 years of age treated with desvenlafaxine [see ADVERSE REACTIONS ( 6.1 ) ]. For elderly patients, possible reduced renal clearance of desvenlafaxine should be considered when determining dose [see DOSAGE AND ADMINISTRATION ( 2.2 ) and CLINICAL PHARMACOLOGY ( 12.3 )] .
SSRIs and SNRIs, including desvenlafaxine, have been associated with cases of clinically significant hyponatremia in elderly patients, who may be at greater risk for this adverse event [see WARNINGS AND PRECAUTIONS ( 5.9 )] .
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Human Experience with Overdosage There is limited clinical trial experience with desvenlafaxine succinate overdosage in humans. However, desvenlafaxine is the major active metabolite of venlafaxine. Overdose experience reported with venlafaxine (the parent drug of desvenlafaxine) is presented below; the identical information can be found in the Overdosage section of the venlafaxine package insert.
In postmarketing experience, overdose with venlafaxine (the parent drug of desvenlafaxine) has occurred predominantly in combination with alcohol and/or other drugs. The most commonly reported events in overdosage include tachycardia, changes in level of consciousness (ranging from somnolence to coma), mydriasis, seizures, and vomiting. Electrocardiogram changes (e.g., prolongation of QT interval, bundle branch block, QRS prolongation), sinus and ventricular tachycardia, bradycardia, hypotension, rhabdomyolysis, vertigo, liver necrosis, serotonin syndrome, and death have been reported.
Published retrospective studies report that venlafaxine overdosage may be associated with an increased risk of fatal outcomes compared to that observed with SSRI antidepressant products, but lower than that for tricyclic antidepressants. Epidemiological studies have shown that venlafaxine-treated patients have a higher pre-existing burden of suicide risk factors than SSRI-treated patients. The extent to which the finding of an increased risk of fatal outcomes can be attributed to the toxicity of venlafaxine in overdosage, as opposed to some characteristic(s) of venlafaxine-treated patients, is not clear.
10.2Management of Overdosage No specific antidotes for desvenlafaxine are known. In managing over dosage, consider the possibility of multiple drug involvement. In case of overdose, call Poison Control Center at 1 800-222-1222 for latest recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The exact mechanism of the antidepressant action of desvenlafaxine is unknown, but is thought to be related to the potentiation of serotonin and norepinephrine in the central nervous system, through inhibition of their reuptake. Non-clinical studies have shown that desvenlafaxine is a potent and selective serotonin and norepinephrine reuptake inhibitor (SNRI).
12.2Pharmacodynamics Desvenlafaxine lacked significant affinity for numerous receptors, including muscarinic-cholinergic, H 1 -histaminergic, or a 1 -adrenergic receptors in vitro. Desvenlafaxine also lacked monoamine oxidase (MAO) inhibitory activity. ECG changes Electrocardiograms were obtained from 1,492 desvenlafaxine treated patients with major depressive disorder and 984 placebo-treated patients in clinical studies lasting up to 8 weeks.
No clinically relevant differences were observed between desvenlafaxine treated and placebo-treated patients for QT, QTc, PR, and QRS intervals. In a thorough QTc study with prospectively determined criteria, desvenlafaxine did not cause QT prolongation. No difference was observed between placebo and desvenlafaxine treatments for the QRS interval.
12.3Pharmacokinetics The single-dose pharmacokinetics of desvenlafaxine are linear and dose-proportional in a dose range of 50 to 600 mg (1 to 12 times the recommended approved dosage) per day. With once-daily dosing, steady-state plasma concentrations are achieved within approximately 4 to 5 days. At steady-state, multiple-dose accumulation of desvenlafaxine is linear and predictable from the single-dose pharmacokinetic profile.
Absorption The absolute oral bioavailability of desvenlafaxine after oral administration is about 80%. Effect of Food: Ingestion of a high-fat meal (800 to 1000 calories) increased desvenlafaxine C max about 16% and had no effect on AUC. Distribution Steady-state volume of distribution of desvenlafaxine is
3.4L/kg. Plasma protein binding of desvenlafaxine is 30% and is independent of drug concentration. Elimination Metabolism: Desvenlafaxine is primarily metabolized by conjugation (mediated by UGT isoforms) and, to a minor extent, through oxidative metabolism.
CYP3A4 mediates the oxidative metabolism (N-demethylation) of desvenlafaxine. The CYP2D6 metabolic pathway is not involved. The pharmacokinetics of desvenlafaxine was similar in subjects with CYP2D6 poor and extensive metabolizer phenotype.
Excretion: Approximately 45% of desvenlafaxine is excreted unchanged in urine at 72 hours after oral administration. Approximately 19% of the administered dose is excreted as the glucuronide metabolite and < 5% as the oxidative metabolite (N,O-didesmethylvenlafaxine) in urine. Specific Populations No clinically significant differences in the exposures of desvenlafaxine were observed based on ethnicity (White, Black, Hispanic).
The effect of intrinsic patient factors on the pharmacokinetics of desvenlafaxine is presented in Figure 1. Drug Interaction Studies Clinical Studies: Other Drugs on Desvenlafaxine The effect of ketoconazole on the exposures of desvenlafaxine is summarized in Figure 2. Desvenlafaxine on Other Drugs The effects of desvenlafaxine on the exposures of other drugs are summarized in Figure 3.
In Vitro Studies: Based on in vitro data, drugs that inhibit CYP isozymes 1A1, 1A2, 2A6, 2D6, 2C8, 2C9, 2C19, and 2E1 are not expected to have significant impact on the pharmacokinetic profile of desvenlafaxine. Desvenlafaxine does not inhibit CYP1A2, 2A6, 2C8, 2C9, 2C19, CYP2D6, or CYP3A4 isozymes. Desvenlafaxine does not induce CYP3A4 either.
Desvenlafaxine is not a substrate or an inhibitor for the P-glycoprotein (P-gp) transporter.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Desvenlafaxine extended-release tablets are available as follows: 50 mg, light pink, biconvex, round shaped film-coated tablets, debossed with "LU" on one side and "S61" on the other side. NDC 71335-1150-1: 30 Tablets in a BOTTLE NDC 71335-1150-2: 28 Tablets in a BOTTLE NDC 71335-1150-3: 60 Tablets in a BOTTLE NDC 71335-1150-4: 90 Tablets in a BOTTLE NDC 71335-1150-5: 180 Tablets in a BOTTLE Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Repackaged/Relabeled by: Bryant Ranch Prepack Burbank, CA 91504
📋 Description ▾
11 DESCRIPTION Desvenlafaxine is an extended-release tablet for oral administration that contains desvenlafaxine succinate, a structurally novel SNRI for the treatment of MDD. Desvenlafaxine (O-desmethylvenlafaxine) is the major active metabolite of the antidepressant venlafaxine, a medication used to treat major depressive disorder. Desvenlafaxine is designated RS -4-[2-dimethylamino-1-(1-hydroxycyclohexyl)ethyl]phenol and has the empirical formula of C 16 H 25 NO 2 (free base) and C 16 H 25 NO 2 •C 4 H 6 O 4 •H 2 O (succinate monohydrate).
Desvenlafaxine succinate monohydrate has a molecular weight of 399.48. The structural formula is shown below. Desvenlafaxine succinate monohydrate is a white to creamish crystalline powder that is soluble in water.
The solubility of desvenlafaxine succinate monohydrate is pH dependent. Its octanol: aqueous system (at pH 7.0) partition coefficient is 0.21. Desvenlafaxine is formulated as an extended-release tablet for once-a-day oral administration.
Each film-coated tablet contains 38 mg, 76 mg or 152 mg of desvenlafaxine succinate monohydrate equivalent to 25 mg, 50 mg or 100 mg of desvenlafaxine, respectively. Inactive ingredients for the 25 mg tablet consist of colloidal silicon dioxide, hypromellose, iron oxide black, iron oxide red, iron oxide yellow, magnesium stearate, microcrystalline cellulose, polyethylene glycol, polyvinyl alcohol, talc and titanium dioxide. Inactive ingredients for the 50 mg tablet consist of colloidal silicon dioxide, hypromellose, iron oxide red, iron oxide yellow, magnesium stearate, microcrystalline cellulose, polyethylene glycol, polyvinyl alcohol, talc and titanium dioxide.
Inactive ingredients for the 100 mg tablet consist of colloidal silicon dioxide, FD&C yellow #6 aluminum lake, hypromellose, iron oxide red, magnesium stearate, microcrystalline cellulose, polyethylene glycol, polyvinyl alcohol, talc and titanium dioxide.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Suicidal Thoughts and Behaviors Advise patients and caregivers to look for the emergence of suicidality, especially early during treatment and when the dose is adjusted up or down, and instruct them to report such symptoms to the healthcare provider [see BOXED WARNING and WARNINGS AND PRECAUTIONS ( 5.1 )]. Concomitant Medication Advise patients taking desvenlafaxine extended-release tablets not to use concomitantly other products containing desvenlafaxine or venlafaxine.
Healthcare professionals should instruct patients not to take desvenlafaxine with an MAOI or within 14 days of stopping an MAOI and to allow 7 days after stopping desvenlafaxine extended-release tablets before starting an MAOI [see CONTRAINDICATIONS ( 4 )]. Serotonin Syndrome Caution patients about the risk of serotonin syndrome, particularly with the concomitant use of desvenlafaxine extended-release tablets with other serotonergic agents (including triptans, tricyclic antidepressants, opioids, lithium, amphetamines, tryptophan, buspirone, and St.
John's Wort supplements) [see WARNINGS AND PRECAUTIONS ( 5.2 )]. Elevated Blood Pressure Advise patients that they should have regular monitoring of blood pressure when taking desvenlafaxine extended-release tablets [see WARNINGS AND PRECAUTIONS ( 5.3 )]. Increased Risk of Bleeding Inform patients about the concomitant use of desvenlafaxine extended-release tablets with NSAIDs, aspirin, other antiplatelet drugs, warfarin, or other coagulants because the combined use of has been associated with an increased risk of bleeding.
Advise patients to inform their healthcare providers if they are taking or planning to take any prescription or over-the-counter medications that increase the risk of bleeding [see WARNINGS AND PRECAUTIONS ( 5.4 )] . Activation of Mania/Hypomania Advise patients, their families and caregivers to observe for signs of activation of mania/hypomania [see WARNINGS AND PRECAUTIONS ( 5.6 )]. Discontinuation Syndrome Advise patients not to abruptly stop taking desvenlafaxine extended-release tablets without talking first with their healthcare professional.
Patients should be aware that discontinuation effects may occur when stopping desvenlafaxine extended-release tablets, and a dose of 25 mg per day is available for discontinuing therapy [see WARNINGS AND PRECAUTIONS ( 5.7 ) and ADVERSE REACTIONS ( 6.1 )]. Sexual Dysfunction Advise patients that use of Desvenlafaxine extended-release tablets may cause symptoms of sexual dysfunction in both male and female patients. Inform patients that they should discuss any changes in sexual function and potential management strategies with their healthcare provider [see Warnings and Precautions ( 5.11 )].
Switching Patients From Other Antidepressants to Desvenlafaxine Extended-Release Tablets Discontinuation symptoms have been reported when switching patients from other antidepressants, including venlafaxine, to desvenlafaxine extended-release tablets. Tapering of the initial antidepressant may be necessary to minimize discontinuation symptoms. Interference with Cognitive and Motor Performance Caution patients about operating hazardous machinery, including automobiles, until they are reasonably certain that desvenlafaxine extended-release tablets therapy does not adversely affect their ability to engage in such activities.
Alcohol Advise patients to avoid alcohol while taking desvenlafaxine extended-release tablets [see DRUG INTERACTIONS ( 7.3 )]. Allergic Reactions Advise patients to notify their physician if they develop allergic phenomena such as rash, hives, swelling, or difficulty breathing. Pregnancy Advise patients to notify their physician if they become pregnant or intend to become pregnant during therapy.
Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to desvenlafaxine extended-rele…
💬 Medication Guide ▾
SPL MEDGUIDE MEDICATION GUIDE Desvenlafaxine ( des-VEN-la-FAX-een ) Extended-Release Tablets Read this Medication Guide before you start taking Desvenlafaxine Extended-Release Tablets and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or treatment.
What is the most important information I should know about desvenlafaxine extended-release tablets? Desvenlafaxine extended-release tablets can cause serious side effects, including: Increased risk of suicidal thoughts or actions in some children and young adults within the first few months of treatment. Desvenlafaxine extended-release tablets is not for use in children.
Depression or other serious mental illnesses are the most important causes of suicidal thoughts or actions. How can I watch for and try to prevent suicidal thoughts and actions? Pay close attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings.
This is very important when an antidepressant medicine is started or when the dose is changed. Call the healthcare provider right away to report new or sudden changes in mood, behavior, thoughts, or feelings. Keep all follow-up visits with the healthcare provider as scheduled.
Call the healthcare provider between visits as needed, especially if you have concerns about symptoms. Call your healthcare provider right away if you have any of the following symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying attempts to commit suicide new or worse depression new or worse anxiety feeling very agitated or restless panic attacks trouble sleeping (insomnia) new or worse irritability acting aggressive, being angry, or violent acting on dangerous impulses an extreme increase in activity and talking (mania) other unusual changes in behavior or mood What is desvenlafaxine extended-release tablets?
Desvenlafaxine extended-release tablets is a prescription medicine used to treat adults with a certain type of depression called major depressive disorder (MDD). Desvenlafaxine extended-release tablets belongs to a class of medicines known as serotonin and norepinephrine reuptake inhibitors (SNRIs). Do not take desvenlafaxine extended-release tablets if you: are allergic to desvenlafaxine succinate, venlafaxine hydrochloride, or any of the ingredients in desvenlafaxine extended-release tablets.
See the end of this Medication Guide for a complete list of ingredients in desvenlafaxine extended-release tablets. take a monoamine oxidase inhibitor (MAOI) have stopped taking an MAOI in the last 14 days. Ask your healthcare provider or pharmacist if you are not sure if you take an MAOI. are being treated with the antibiotic linezolid or the intravenous methylene blue Do not start taking an MAOI for at least 7 days after you stop treatment with desvenlafaxine extended-release tablets. Before taking desvenlafaxine extended-release tablets tell your healthcare provider about all your medical conditions, including if you: have high blood pressure have heart problems have cerebrovascular problems or had a stroke have or had bleeding problems have, or have a family history of, bipolar disorder, mania or hypomania have high cholesterol or high triglycerides have or had depression, suicidal thoughts or behavior have kidney or liver problems have or had seizures or convulsions have low sodium levels in your blood are pregnant or plan to become pregnant.
Talk to your healthcare provider about the risk to your unborn baby if you take desvenlafaxine extended-release tablets during pregnancy. Tell your healthcare provider if you become pregnant or think you are pregnant during treatment with desvenlafaxine extended-release tablets. If you become pregnant during treatment with desvenlafaxine extended-release tablets, talk to your healthcare provider about registering with the National Pregnancy Registry for Antidepressants.…