
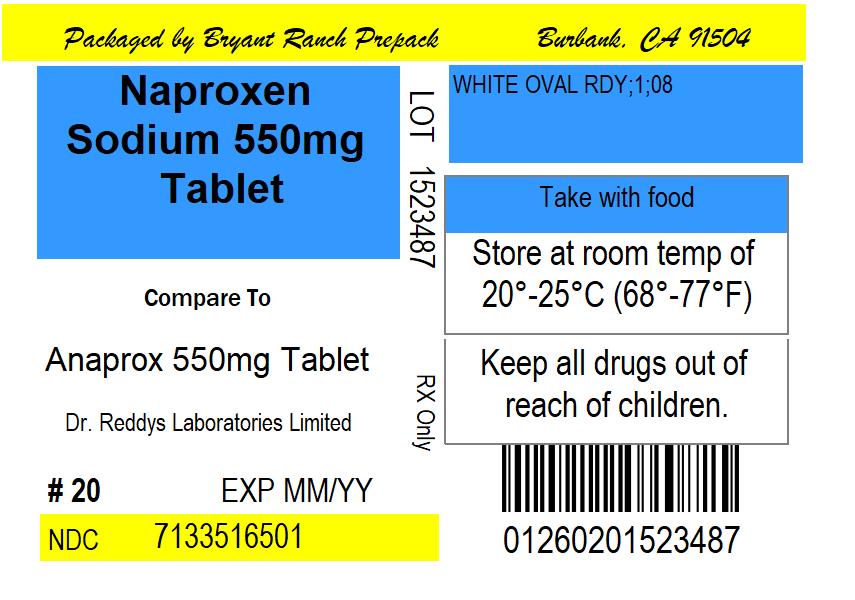
Naproxen sodium 550 mg Tablet, Film Coated, 56-count
Other active recalls for Naproxen Sodium (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Nonsteroidal Anti-inflammatory Drug class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- They're very similar — naproxen sodium is just the salt form of naproxen, and it dissolves in water more quickly. That means your body absorbs naproxen sodium a bit faster, so it t...
- What's the difference between naproxen and naproxen sodium — are they the same thing?
- You can take it either way, but taking it with food, milk, or a full glass of water is a good idea because it helps protect your stomach. Naproxen can irritate the lining of your s...
- Can I take naproxen on an empty stomach, or do I need to eat first?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Naproxen Sodium — tap one for details:
Naproxen Sodium may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1293 | $7.24 / 56 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Naproxen sodium 550 mg 43598-0495-01 | Dr. | 100 tablets | $0.225 | AB | Availability likely | — |
| Naproxen Sodium 550 mg 50228-0433-01 | ScieGen | 100 tablets | $0.225 | AB | Availability likely | — |
| Naproxen Sodium 550 mg 65862-0516-01 | Aurobindo | 100 tablets | $0.225 | — | Availability likely | — |
| Naproxen Sodium 550 mg 68462-0179-01 | Glenmark | 100 tablets | $0.225 | AB | Availability likely | — |
| Naproxen sodium 550 mg 50090-5238-03 | A-S | 20 tablets | — | AB | FDA listed | — |
| Naproxen sodium 550 mg 55700-0625-60 | Quality | 60 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 60760-0801-14 | ST. | 14 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 63629-8516-01 | Bryant | 500 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 63629-8517-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 68071-2333-02 | NuCare | 21 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 68788-7800-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 71205-0479-15 | Proficient | 15 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 71205-0631-15 | Proficient | 15 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 71335-0822-00 | Bryant | 6 tablets | — | AB | FDA listed | — |
| Naproxen sodium 550 mgthis 71335-1650-09 | Bryant | 56 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 71335-2294-01 | Bryant | 500 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 71335-3075-00 | Bryant | 6 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 71335-9663-00 | Bryant | 6 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 72189-0332-60 | Direct | 60 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 72789-0389-60 | PD-Rx | 60 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 76420-0627-01 | Asclemed | 100 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 80425-0531-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 80425-0532-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| Naproxen Sodium 550 mg 80425-0574-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| Naproxen sodium 550 mg 85509-1495-03 | PHOENIX | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-1650-00 | 6 TABLET, FILM COATED in 1 BOTTLE (71335-1650-0) | 2021-12-28 | Active |
| 71335-1650-01 | 20 TABLET, FILM COATED in 1 BOTTLE (71335-1650-1) | 2021-12-28 | Active |
| 71335-1650-02 | 100 TABLET, FILM COATED in 1 BOTTLE (71335-1650-2) | 2021-12-28 | Active |
| 71335-1650-03 | 30 TABLET, FILM COATED in 1 BOTTLE (71335-1650-3) | 2020-06-23 | Active |
| 71335-1650-04 | 120 TABLET, FILM COATED in 1 BOTTLE (71335-1650-4) | 2021-12-28 | Active |
| 71335-1650-05 | 60 TABLET, FILM COATED in 1 BOTTLE (71335-1650-5) | 2021-12-28 | Active |
| 71335-1650-06 | 90 TABLET, FILM COATED in 1 BOTTLE (71335-1650-6) | 2021-12-28 | Active |
| 71335-1650-07 | 42 TABLET, FILM COATED in 1 BOTTLE (71335-1650-7) | 2021-12-28 | Active |
| 71335-1650-08 | 14 TABLET, FILM COATED in 1 BOTTLE (71335-1650-8) | 2021-12-28 | Active |
| 71335-1650-09 You're viewing this | 56 TABLET, FILM COATED in 1 BOTTLE (71335-1650-9) | 2021-12-28 | Active |
You're viewing one of 10 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-1650-09?
What is the difference between NDC 71335-1650-09 and NDC 71335-1650-00?
What NDC number is used to bill for this package of Naproxen sodium 550 mg Tablet, Film Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RISK OF SERIOUS CARDIOVASCULAR AND GASTROINTESTINAL EVENTS Cardiovascular Thrombotic Events • Nonsteroidal anti-inflammatory drugs (NSAIDs) cause an increased risk of serious cardiovascular thrombotic events, including myocardial infarction and stroke, which can be fatal. This risk may occur early in treatment and may increase with duration of use [see Warnings and Precautions (5.1 )]. • Naproxen sodium tablets are contraindicated in the setting of coronary artery bypass graft (CABG) surgery [see Contraindications (4), Warnings and Precautions (5.1 )].
Gastrointestinal Bleeding, Ulceration, and Perforation NSAIDs cause an increased risk of serious gastrointestinal (GI) adverse events including bleeding, ulceration, and perforation of the stomach or intestines, which can be fatal. These events can occur at any time during use and without warning symptoms. Elderly patients and patients with a prior history of peptic ulcer disease and/or GI bleeding are at greater risk for serious GI events [see Warnings and Precautions ( 5.2 )].
WARNING: RISK OF SERIOUS CARDIOVASCULAR AND GASTROINTESTINAL EVENTS See full prescribing information for complete boxed warning . • Nonsteroidal anti-inflammatory drugs (NSAIDs) cause an increased risk of serious cardiovascular thrombotic events, including myocardial infarction and stroke, which can be fatal. This risk may occur early in treatment and may increase with duration of use. ( 5.1 ) • Naproxen sodium tablets are contraindicated in the setting of coronary artery bypass graft (CABG) surgery.
( 4 , 5.1) • NSAIDs cause an increased risk of serious gastrointestinal (GI) adverse events including bleeding, ulceration, and perforation of the stomach or intestines, which can be fatal. These events can occur at any time during use and without warning symptoms. Elderly patients and patients with a prior history of peptic ulcer disease and/or GI bleeding are at greater risk for serious GI events .
( 5.2 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Naproxen sodium tablets are indicated for: the relief of the signs and symptoms of: • rheumatoid arthritis • osteoarthritis • ankylosing spondylitis • Polyarticular Juvenile Idiopathic Arthritis Naproxen sodium tablets are also indicated for: the relief of signs and symptoms of: • tendonitis • bursitis • acute gout the management of: • pain • primary dysmenorrhea Naproxen sodium tablets are non-steroidal anti-inflammatory drugs indicated for: the relief of the signs and symptoms of: • rheumatoid arthritis • osteoarthritis • ankylosing spondylitis • polyarticular juvenile idiopathic arthritis Naproxen sodium tablets are also indicated for: the relief of signs and symptoms of: • tendonitis • bursitis • acute gout the management of: • pain • primary dysmenorrhea
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Use the lowest effective dosage for shortest duration consistent with individual patient treatment goals. ( 2.1) Rheumatoid Arthritis, Osteoarthritis, and Ankylosing Spondylitis Naproxen Sodium Tablets 275 mg (one-half tablet) 550 mg twice daily The dose may be adjusted up or down depending on the clinical response of the patient. In patients who tolerate lower doses well, the dose may be increased to naproxen 1,500 mg/day for up to 6 months.
Management of Pain, Primary Dysmenorrhea, and Acute Tendonitis and Bursitis Recommended starting dose 550 mg of naproxen sodium as naproxen sodium tablets is followed by 550 mg every 12 hours or 275 mg every 6 to 8 hours as required. The initial total daily dose should not exceed 1,375 mg of naproxen sodium.Thereafter, the total daily dose should not exceed 1,100 mg of naproxen sodium. Naproxen sodium is recommended for the management of acute painful conditions when prompt onset of pain relief is desired.
Acute Gout Naproxen sodium tablets may also be used at a starting dose of 825 mg followed by 275 mg every 8 hours.
2.1General Dosing Instructions Carefully consider the potential benefits and risks of naproxen sodium tablets are other treatment options before deciding to use naproxen sodium tablets. Use the lowest effective dose for the shortest duration consistent with individual patient treatment goals [see Warnings and Precautions ( 5 ) ]. After observing the response to initial therapy with naproxen sodium tablets, the dose and frequency should be adjusted to suit an individual patient’s needs.
Naproxen-containing products such as naproxen sodium tablets, and other naproxen products should not be used concomitantly since they all circulate in the plasma as the naproxen anion.
2.2Rheumatoid Arthritis, Osteoarthritis and Ankylosing Spondylitis The recommended dosages of naproxen sodium tablets, is shown in Table 1. Table 1: Recommended dosages for Naproxen Sodium Tablets Naproxen sodium tablets 275 mg (one half tablet) 550 mg (naproxen 500 mg with 50 mg sodium) twice daily During long-term administration, the dose of naproxen may be adjusted up or down depending on the clinical response of the patient. A lower daily dose may suffice for long-term administration.
The morning and evening doses do not have to be equal in size and administration of the drug more frequently than twice daily does not generally make a difference in response. In patients who tolerate lower doses well, the dose may be increased to naproxen 1,500 mg/day for limited periods of up to 6 months when a higher level of anti-inflammatory/analgesic activity is required. When treating such patients with naproxen 1,500 mg/day, the physician should observe sufficient increased clinical benefits to offset the potential increased risk.
2.3Polyarticular Juvenile Idiopathic Arthritis Naproxen solid-oral dosage forms may not allow for the flexible dose titration needed in pediatric patients with polyarticular juvenile idiopathic arthritis. A liquid formulation may be more appropriate for weight-based dosing and due to the need for dose flexibility in children. In pediatric patients, doses of 5 mg/kg/day produced plasma levels of naproxen similar to those seen in adults taking 500 mg of naproxen [see Clinical Pharmacology ( 12 )].
The recommended total daily dose of naproxen is approximately 10 mg/kg given in 2 divided doses.
2.4Management of Pain, Primary Dysmenorrhea, and Acute Tendonitis and Bursitis The recommended starting dose of naproxen sodium tablets is 550 mg followed by 550 mg every 12 hours or 275 mg (one half of a 550 mg tablet) every 6 to 8 hours as required. The initial total daily dose should not exceed 1,375 mg (two and one-half tablets) of naproxen sodium. Thereafter, the total daily dose should not exceed 1,100 mg of naproxen sodium.
Because the sodium salt of naproxen is more rapidly absorbed, naproxen sodium is recommended for the management of acute painful conditions when p…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS · Naproxen sodium tablets USP, 275 mg are white, film coated, capsule shaped, biconvex tablets, debossed ‘RDY’ on one side and ‘107’ on other side . · Naproxen sodium tablets USP, 550 mg are white, film coated, capsule shaped, biconvex tablets, debossed ‘RDY’ on one side and ‘108’ separating ‘1’ and ‘08’ with a breakline on other side. Naproxen sodium tablets: 275 mg, 550 mg (contains 50 mg of sodium)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Naproxen sodium tablets are contraindicated in the following patients: • Known hypersensitivity (e.g., anaphylactic reactions and serious skin reactions) to naproxen or any components of the drug product [see Warnings and Precautions ( 5.7 , 5.9 )] • History of asthma, urticaria, or other allergic-type reactions after taking aspirin or other NSAIDs. Severe, sometimes fatal, anaphylactic reactions to NSAIDs have been reported in such patients [see Warnings and Precautions ( 5.7 , 5.8 )] • In the setting of coronary artery bypass graft (CABG) surgery [see Warnings and Precautions ( 5.1)] • Known hypersensitivity to naproxen or any components of the drug product ( 4 ) • History of asthma, urticaria, or other allergic-type reactions after taking aspirin or other NSAIDs (4) • In the setting of CABG surgery (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hepatotoxicity : Inform patients of warning signs and symptoms of hepatotoxicity. Discontinue if abnormal liver tests persist or worsen or if clinical signs and symptoms of liver disease develop. ( 5.3) Hypertension : Patients taking some antihypertensive medications may have impaired response to these therapies when taking NSAIDs.
Monitor blood pressure. ( 5.4 , 7 ) Heart Failure and Edema : Avoid use of naproxen sodium in patients with severe heart failure unless benefits are expected to outweigh risk of worsening heart failure. ( 5.5 ) Renal Toxicity : Monitor renal function in patients with renal or hepatic impairment, heart failure, dehydration, or hypovolemia.
Avoid use of naproxen sodium in patients with advanced renal disease unless benefits are expected to outweigh risk of worsening renal function. ( 5.6 ) Anaphylactic Reactions : Seek emergency help if an anaphylactic reaction occurs. ( 5.7 ) Exacerbation of Asthma Related to Aspirin Sensitivity : Naproxen sodium is contraindicated in patients with aspirin-sensitive asthma.
Monitor patients with preexisting asthma (without aspirin sensitivity). ( 5.8) Serious Skin Reactions : Discontinue naproxen sodium at first appearance of skin rash or other signs of hypersensitivity. (5.9) Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS) : Discontinue and evaluate clinically ( 5.10 ).
Fetal Toxicity : Limit use of NSAIDs, including naproxen sodium, between about 20 to 30 weeks in pregnancy due to the risk of oligohydramnios/fetal dysfunction. Avoid use of NSAIDs in women at about 30 weeks gestation and later in pregnancy due to the risks of oligohydramnios/fetal renal dysfunction and premature closure of the fetal ductus arteriosus. ( 5.11 , 8.1 ) Hematologic Toxicity : Monitor hemoglobin or hematocrit in patients with any signs or symptoms of anemia.
( 5.12 , 7 )
5.1Cardiovascular Thrombotic Events Clinical trials of several COX-2 selective and nonselective NSAIDs of up to three years duration have shown an increased risk of serious cardiovascular (CV) thrombotic events, including myocardial infarction (MI) and stroke, which can be fatal. Based on available data, it is unclear that the risk for CV thrombotic events is similar for all NSAIDs. The relative increase in serious CV thrombotic events over baseline conferred by NSAID use appears to be similar in those with and without known CV disease or risk factors for CV disease.
However, patients with known CV disease or risk factors had a higher absolute incidence of excess serious CV thrombotic events, due to their increased baseline rate. Some observational studies found that this increased risk of serious CV thrombotic events began as early as the first weeks of treatment. The increase in CV thrombotic risk has been observed most consistently at higher doses.
To minimize the potential risk for an adverse CV event in NSAID-treated patients, use the lowest effective dose for the shortest duration possible. Physicians and patients should remain alert for the development of such events, throughout the entire treatment course, even in the absence of previous CV symptoms. Patients should be informed about the symptoms of serious CV events and the steps to take if they occur.
There is no consistent evidence that concurrent use of aspirin mitigates the increased risk of serious CV thrombotic events associated with NSAID use. The concurrent use of aspirin and an NSAID, such as naproxen, increases the risk of serious gastrointestinal (GI) events [see Warnings and Precautions ( 5.2 )]. Status Post Coronary Artery Bypass Graft (CABG) Surgery Two large, controlled clinical trials of a COX-2 selective NSAID for the treatment of pain in the first 10 to 14 days following CABG surgery found an increased incidence of myocardial infarction and stroke.
NSAIDs are contraindicated in the setting of CABG [see Contraindications ( 4 )]. Post-MI Patients Observational studies conducted in the Danish National Regi…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: • Cardiovascular Thrombotic Events [see Warnings and Precautions (5.1)] • GI Bleeding, Ulceration, and Perforation [see Warnings and Precautions ( 5.2 )] • Hepatotoxicity [see Warnings and Precautions (5.3) ] • Hypertension [see Warnings and Precautions (5.4 )] • Heart Failure and Edema [see Warnings and Precautions (5.5 )] • Renal Toxicity and Hyperkalemia [see Warnings and Precautions (5.6 )] • Anaphylactic Reactions [see Warnings and Precautions ( 5.7 )] • Serious Skin Reactions [see Warnings and Precautions ( 5.9 )] • Hematologic Toxicity [see Warnings and Precautions ( 5.12 )] Most common adverse reactions to naproxen were dyspepsia, abdominal pain, nausea, headache, rash, ecchymosis, and edema.
( 6.1) To report SUSPECTED ADVERSE REACTIONS, contact Dr. Reddy's Laboratories, Inc. at 1-888-375-3784 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse reactions reported in controlled clinical trials in 960 patients treated for rheumatoid arthritis or osteoarthritis are listed below. In general, reactions in patients treated chronically were reported 2 to 10 times more frequently than they were in short-term studies in the 962 patients treated for mild to moderate pain or for dysmenorrhea.
The most frequent complaints reported related to the gastrointestinal tract. A clinical study found gastrointestinal reactions to be more frequent and more severe in rheumatoid arthritis patients taking daily doses of 1,500 mg naproxen compared to those taking 750 mg naproxen. In controlled clinical trials with about 80 pediatric patients and in well-monitored, open-label studies with about 400 pediatric patients with polyarticular juvenile idiopathic arthritis treated with naproxen, the incidence of rash and prolonged bleeding times were greater, the incidence of gastrointestinal and central nervous system reactions were about the same, and the incidence of other reactions were lower in pediatric patients than in adults.
In patients taking naproxen in clinical trials, the most frequently reported adverse experiences in approximately 1% to 10% of patients were: Gastrointestinal (GI) Experiences, including : heartburn*, abdominal pain*, nausea*, constipation*, diarrhea, dyspepsia, stomatitis Central Nervous System : headache*, dizziness*, drowsiness*, lightheadedness, vertigo Dermatologic : pruritus (itching)*, skin eruptions*, ecchymoses*, sweating, purpura Special Senses : tinnitus*, visual disturbances, hearing disturbances Cardiovascular : edema*, palpitations General : dyspnea*, thirst *Incidence of reported reaction between 3% and 9%.
Those reactions occurring in less than 3% of the patients are unmarked. In patients taking NSAIDs, the following adverse experiences have also been reported in approximately 1% to 10% of patients. Gastrointestinal (GI) Experiences, including: flatulence, gross bleeding/perforation, GI ulcers (gastric/duodenal), vomiting General : abnormal renal function, anemia, elevated liver enzymes, increased bleeding time, rashes The following are additional adverse experiences reported in <1% of patients taking naproxen during clinical trials.
Gastrointestinal : pancreatitis, vomiting Hepatobiliary : jaundice Hemic and Lymphatic : melena, thrombocytopenia, agranulocytosis Nervous System : inability to concentrate Dermatologic : skin rashes
6.2Postmarketing Experience The following adverse reactions have been identified during post approval use of naproxen. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency o…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS See Table 1 for clinically significant drug interactions with naproxen. Table 1: Clinically Significant Drug Interactions with naproxen Drugs That Interfere with Hemostasis Clinical Impact: Naproxen and anticoagulants such as warfarin have a synergistic effect on bleeding. The concomitant use of naproxen and anticoagulants have an increased risk of serious bleeding compared to the use of either drug alone.
Serotonin release by platelets plays an important role in hemostasis. Case-control and cohort epidemiological studies showed that concomitant use of drugs that interfere with serotonin reuptake and an NSAID may potentiate the risk of bleeding more than an NSAID alone. Intervention: Monitor patients with concomitant use of naproxen sodium with anticoagulants (e.g., warfarin), antiplatelet agents (e.g., aspirin), selective serotonin reuptake inhibitors (SSRIs), and serotonin norepinephrine reuptake inhibitors (SNRIs) for signs of bleeding [see Warnings and Precautions ( 5.12 )].
Aspirin Clinical Impact: A pharmacodynamic (PD) study has demonstrated an interaction in which lower dose naproxen (220mg/day or 220mg twice daily) interfered with the antiplatelet effect of low-dose immediate-release aspirin, with the interaction most marked during the washout period of naproxen [ see Clinical Pharmacology ( 12.2 )] . There is reason to expect that the interaction would be present with prescription doses of naproxen or with enteric-coated low-dose aspirin; however, the peak interference with aspirin function may be later than observed in the PD study due to the longer washout period.
Controlled clinical studies showed that the concomitant use of NSAIDs and analgesic doses of aspirin does not produce any greater therapeutic effect than the use of NSAIDs alone. In a clinical study, the concomitant use of an NSAID and aspirin was associated with a significantly increased incidence of GI adverse reactions as compared to use of the NSAID alone [see Warnings and Precautions ( 5.2 )]. Intervention: Because there may be an increased risk of cardiovascular events following discontinuation of naproxen due to the interference with the antiplatelet effect of aspirin during the washout period, for patients taking low-dose aspirin for cardioprotection who require intermittent analgesics, consider use of an NSAID that does not interfere with the antiplatelet effect of aspirin, or non-NSAID analgesics where appropriate.
Concomitant use of naproxen sodium and analgesic doses of aspirin is not generally recommended because of the increased risk of bleeding [see Warnings and Precautions ( 5.12 )]. Naproxen sodium tablets are not substitutes for low dose aspirin for cardiovascular protection. ACE Inhibitors, Angiotensin Receptor Blockers, and Beta-Blockers Clinical Impact: NSAIDs may diminish the antihypertensive effect of angiotensin converting enzyme (ACE) inhibitors, angiotensin receptor blockers (ARBs), or beta-blockers (including propranolol).
In patients who are elderly, volume-depleted (including those on diuretic therapy), or have renal impairment, co-administration of an NSAID with ACE inhibitors or ARBs may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Intervention: During concomitant use of naproxen sodium and ACE-inhibitors, ARBs, or beta-blockers, monitor blood pressure to ensure that the desired blood pressure is obtained.
During concomitant use of naproxen sodium and ACE-inhibitors or ARBs in patients who are elderly, volume-depleted, or have impaired renal function, monitor for signs of worsening renal function [see Warnings and Precautions ( 5.6 )]. When these drugs are administered concomitantly, patients should be adequately hydrated. Assess renal function at the beginning of the concomitant treatment and periodically thereafter.
Diuretics Clinical Impact: Clinical studies, as well as post-marketing observations, showed that NSAIDs reduced th…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Infertility : NSAIDs are associated with reversible infertility. Consider withdrawal of naproxen sodium is in women who have difficulties conceiving. ( 8.3 ) Renal Impairmen t: Naproxen-containing products are not recommended for use in patients with moderate to severe and severe renal impairment (creatinine clearance <30 mL/min). ( 8.7 )
8.1Pregnancy Risk Summary Use of NSAIDs, including naproxen sodium tablets, can cause premature closure of the fetal ductus arteriosus and fetal renal dysfunction leading to oligohydramnios and, in some cases, neonatal renal impairment. Because of these risks, limit dose and duration of naproxen sodium tablets use between about 20 and 30 weeks of gestation, and avoid naproxen sodium tablets use at about 30 weeks of gestation and later in pregnancy (see Clinical Considerations, Data). Premature Closure of Fetal Ductus Arteriosus Use of NSAIDs, including naproxen sodium tablets, at about 30 weeks gestation or later in pregnancy increases the risk of premature closure of the fetal ductus arteriosus.
Oligohydramnios/Neonatal Renal Impairment Use of NSAIDs at about 20 weeks gestation or later in pregnancy has been associated with cases of fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment. Data from observational studies regarding other potential embryofetal risks of NSAID use in women in the first or second trimesters of pregnancy are inconclusive. In animal reproduction studies in rats, rabbits, and mice no evidence of teratogenicity or fetal harm when naproxen was administered during the period of organogenesis at doses 0.13, 0.26, and 0.6 times the maximum recommended human daily dose of 1,500 mg/day, respectively [see Data].
Based on animal data, prostaglandins have been shown to have an important role in endometrial vascular permeability, blastocyst implantation, and decidualization. In animal studies, administration of prostaglandin synthesis inhibitors such as naproxen, resulted in increased pre-and post-implantation loss. Prostaglandins also have been shown to have an important role in fetal kidney development.
In published animal studies, prostaglandin synthesis inhibitors have been reported to impair kidney development when administered at clinically relevant doses. The estimated background risk of major birth defects and miscarriage for the indicated population(s) is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Premature Closure of Fetal Ductus Arteriosus: Avoid use of NSAIDs in women at about 30 weeks gestation and later in pregnancy, because NSAIDs, including naproxen sodium tablets, can cause premature closure of the fetal ductus arteriosus (see Data) . Oligohydramnios/Neonatal Renal Impairment: If an NSAID is necessary at about 20 weeks gestation or later in pregnancy, limit the use to the lowest effective dose and shortest duration possible.
If naproxen sodium tablets treatment extends beyond 48 hours, consider monitoring with ultrasound for oligohydramnios. If oligohydramnios occurs, discontinue naproxen sodium tablets, and follow up according to clinical practice (see Data) . Labor or Delivery There are no studies on the effects of naproxen sodium during labor or delivery.
In animal studies, NSAIDS, including naproxen, inhibit prostaglandin synthesis, cause delayed parturition, and increase the incidence of stillbirth. Data Human Data There is some evidence to suggest that when inhibitors of prostaglandin synthesis are used to delay preterm labor, there is an increased risk of neonatal complications such as necrotizing enterocolitis, patent ductus arteriosus, and intracranial hemorrhage. Naproxen treatment given in lat…
🆘 Overdosage ▾
10 OVERDOSAGE Symptoms following acute NSAID overdosages have been typically limited to lethargy, drowsiness, nausea, vomiting, and epigastric pain, which have been generally reversible with supportive care. Gastrointestinal bleeding has occurred. Hypertension, acute renal failure, respiratory depression, and coma have occurred, but were rare [ see Warnings and Precautions ( 5.1 , 5.2 ) ].Because naproxen sodium may be rapidly absorbed, high and early blood levels should be anticipated.
A few patients have experienced convulsions, but it is not clear whether or not these were drug-related. It is not known what dose of the drug would be life threatening. [see Warnings and Precautions ( 5.1 , 5.2 , 5.4 , 5.6 )]. Manage patients with symptomatic and supportive care following an NSAID overdosage.
There are no specific antidotes. Consider emesis and/or activated charcoal (60 to 100 grams in adults, 1 to 2 grams per kg of body weight in pediatric patients) and/or osmotic cathartic in symptomatic patients seen within four hours of ingestion or in patients with a large overdosage (5 to 10 times the recommended dosage). Forced diuresis, alkalinization of urine, hemodialysis, or hemoperfusion may not be useful due to high protein binding.
For additional information about overdosage treatment contact a poison control center (1-800-222-1222).
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Naproxen has analgesic, anti-inflammatory, and antipyretic properties. Naproxen sodium has been developed as a more rapidly absorbed formulation of naproxen for use as an analgesic. The mechanism of action of naproxen, like that of other NSAIDs, is not completely understood but involves inhibition of cyclooxygenase (COX-1 and COX-2).
Naproxen is a potent inhibitor of prostaglandin synthesis in vitro . Naproxen concentrations reached during therapy have produced in vivo effects. Prostaglandins sensitize afferent nerves and potentiate the action of bradykinin in inducing pain in animal models.
Prostaglandins are mediators of inflammation. Because naproxen is an inhibitor of prostaglandin synthesis, its mode of action may be due to a decrease of prostaglandins in peripheral tissues.
12.2Pharmacodynamics In a healthy volunteer study, 10 days of concomitant administration of naproxen 220 mg once-daily with low-dose immediate-release aspirin (81 mg) showed an interaction with the antiplatelet activity of aspirin as measured by % serum thromboxane B2 inhibition at 24 hours following the day 10 dose [98.7% (aspirin alone) vs 93.1% (naproxen and aspirin)]. The interaction was observed even following discontinuation of naproxen on day 11 (while aspirin dose was continued) but normalized by day 13. In the same study, the interaction was greater when naproxen was administered 30 minutes prior to aspirin [98.7% vs 87.7%] and minimal when aspirin was administered 30 minutes prior to naproxen [98.7% vs 95.4%].
Following administration of naproxen 220 mg twice-daily with low-dose immediate-release aspirin (first naproxen dose given 30 minutes prior to aspirin), the interaction was minimal at 24 h following day 10 dose [98.7% vs 95.7%]. However, the interaction was more prominent after discontinuation of naproxen (washout) on day 11 [98.7% vs 84.3%] and did not normalize completely by day 13 [98.5% vs 90.7%]. [see Drug Interactions (7) ].
12.3Pharmacokinetics Naproxen and naproxen sodium are rapidly and completely absorbed from the gastrointestinal tract with an in vivo bioavailability of 95%. The different dosage forms of naproxen are bioequivalent in terms of extent of absorption (AUC) and peak concentration (C max ); however, the products do differ in their pattern of absorption. These differences between naproxen products are related to both the chemical form of naproxen used and its formulation.
Even with the observed differences in pattern of absorption, the elimination half-life of naproxen is unchanged across products ranging from 12 to 17 hours. Steady-state levels of naproxen are reached in 4 to 5 days, and the degree of naproxen accumulation is consistent with this half-life. This suggests that the differences in pattern of release play only a negligible role in the attainment of steady-state plasma levels.
Absorption Naproxen sodium: After oral administration of naproxen sodium, peak plasma levels are attained in 1 to 2 hours. The difference in rates between the two products is due to the increased aqueous solubility of the sodium salt of naproxen used in naproxen sodium tablets. Distribution Naproxen has a volume of distribution of
0.16L/kg. At therapeutic levels naproxen is greater than 99% albumin-bound. At doses of naproxen greater than 500 mg/day there is less than proportional increase in plasma levels due to an increase in clearance caused by saturation of plasma protein binding at higher doses (average trough C ss 36.5, 49.2 and 56.4 mg/L with 500, 1,000 and 1,500 mg daily doses of naproxen, respectively).
The naproxen anion has been found in the milk of lactating women at a concentration equivalent to approximately 1% of maximum naproxen concentration in plasma [see Use in Specific Populations ( 8.2 )]. Elimination Metabolism Naproxen is extensively metabolized in the liver to 6-0-desmethyl naproxen, and both parent and metabolites do not induce metabolizing enzymes. Bot…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Naproxen has analgesic, anti-inflammatory, and antipyretic properties. Naproxen sodium has been developed as a more rapidly absorbed formulation of naproxen for use as an analgesic. The mechanism of action of naproxen, like that of other NSAIDs, is not completely understood but involves inhibition of cyclooxygenase (COX-1 and COX-2).
Naproxen is a potent inhibitor of prostaglandin synthesis in vitro . Naproxen concentrations reached during therapy have produced in vivo effects. Prostaglandins sensitize afferent nerves and potentiate the action of bradykinin in inducing pain in animal models.
Prostaglandins are mediators of inflammation. Because naproxen is an inhibitor of prostaglandin synthesis, its mode of action may be due to a decrease of prostaglandins in peripheral tissues.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Naproxen sodium tablets USP, 550 mg are white, film coated, capsule shaped, biconvex tablets, debossed ‘RDY’ on one side and ‘108’ separating ‘1’ and ‘08’ with a breakline on other side. NDC: 71335-1650-1: 20 Tablets in a BOTTLE NDC: 71335-1650-2: 100 Tablets in a BOTTLE NDC: 71335-1650-3: 30 Tablets in a BOTTLE NDC: 71335-1650-4: 120 Tablets in a BOTTLE NDC: 71335-1650-5: 60 Tablets in a BOTTLE NDC: 71335-1650-6: 90 Tablets in a BOTTLE NDC: 71335-1650-7: 42 Tablets in a BOTTLE NDC: 71335-1650-8: 14 Tablets in a BOTTLE NDC: 71335-1650-9: 56 Tablets in a BOTTLE NDC: 71335-1650-0: 6 Tablets in a BOTTLE Store at 20°C to 25°C (68°F to 77°F) [See USP Controlled Room Temperature] in well-closed containers.
Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 91504
📋 Description ▾
11 DESCRIPTION Naproxen sodium tablets are nonsteroidal anti-inflammatory drugs available as follows: Naproxen sodium tablets are available as white tablets containing 275 mg and 500 mg of naproxen sodium for oral administration. Naproxen is a propionic acid derivative related to the arylacetic acid group of nonsteroidal anti-inflammatory drugs. The chemical name for naproxen sodium is (S)-6-methoxy-α-methyl-2-naphthaleneacetic acid, sodium salt.
Naproxen sodium has a molecular weight of 252.23 and a molecular formula of C 14 H 13 NaO 3 . Naproxen sodium has the following structure. Naproxen sodium USP is a white to creamy crystalline powder.
It is soluble in water and in methanol, sparingly soluble in alcohol, very slightly soluble in acetone and practically insoluble in chloroform and in toluene. The inactive ingredients in naproxen sodium tablets include: magnesium stearate, microcrystalline cellulose, povidone and talc. The coating suspension contains hypromellose 2910, polyethylene glycol 400 and titanium dioxide.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide) that accompanies each prescription dispensed. Inform patients, families, or their caregivers of the following information before initiating therapy with naproxen sodium and periodically during the course of ongoing therapy. Cardiovascular Thrombotic Events Advise patients to be alert for the symptoms of cardiovascular thrombotic events, including chest pain, shortness of breath, weakness, or slurring of speech, and to report any of these symptoms to their health care provider immediately [see Warnings and Precautions (5.1) ].
Gastrointestinal Bleeding, Ulceration, and Perforation Advise patients to report symptoms of ulcerations and bleeding, including epigastric pain, dyspepsia, melena, and hematemesis to their health care provider. In the setting of concomitant use of low-dose aspirin for cardiac prophylaxis, inform patients of the increased risk for and the signs and symptoms of GI bleeding [see Warnings and Precautions ( 5.2 )]. Hepatotoxicity Inform patients of the warning signs and symptoms of hepatotoxicity (e.g., nausea, fatigue, lethargy, pruritus, diarrhea, jaundice, right upper quadrant tenderness, and “flu-like” symptoms).
If these occur, instruct patients to stop naproxen sodium and seek immediate medical therapy [see Warnings and Precautions (5.3)] . Heart Failure and Edema Advise patients to be alert for the symptoms of congestive heart failure including shortness of breath, unexplained weight gain, or edema and to contact their healthcare provider if such symptoms occur [see Warnings and Precautions (5.5)] . Anaphylactic Reactions Inform patients of the signs of an anaphylactic reaction (e.g., difficulty breathing, swelling of the face or throat).
Instruct patients to seek immediate emergency help if these occur [see Contraindications ( 4 ) and Warnings and Precautions ( 5.7 )]. Serious Skin Reactions including Dress Advise patients to stop taking naproxen sodium immediately if they develop any type of rash or fever and to contact their healthcare provider as soon as possible [see Warnings and Precautions ( 5.9 , 5.10 ) ]. Female Fertility Advise females of reproductive potential who desire pregnancy that NSAIDs, including naproxen sodium, may be associated with a reversible delay in ovulation [see Use in Specific Populations ( 8.3 )].
Fetal Toxicity Inform pregnant women to avoid use of naproxen sodium and other NSAIDs starting at 30 weeks gestation because of the risk of the premature closing of the fetal ductus arteriosus. If treatment with naproxen sodium is needed for a pregnant woman between about 20 to 30 weeks gestation, advise her that she may need to be monitored for oligohydramnios, if treatment continues for longer than 48 hours [see Warnings and Precautions ( 5.11 ) and Use in Specific Populations ( 8.1 )]. Avoid Concomitant Use of NSAIDs Inform patients that the concomitant use of naproxen sodium with other NSAIDs or salicylates (e.g., diflunisal, salsalate) is not recommended due to the increased risk of gastrointestinal toxicity, and little or no increase in efficacy [see Warnings and Precautions ( 5.2 ) and Drug Interactions ( 7 )].
Alert patients that NSAIDs may be present in “over the counter” medications for treatment of colds, fever, or insomnia. Use of NSAIDS and Low-Dose Aspirin Inform patients not to use low-dose aspirin concomitantly with naproxen sodium until they talk to their healthcare provider [see Drug Interactions ( 7 )]. R X Only Distributor: Dr.
Reddy’s Laboratories Inc., Princeton, NJ 08540 Made in India Revised: 05/2024
💬 Medication Guide ▾
Medication Guide for Nonsteroidal Anti-Inflammatory Drugs (NSAIDs) What is the most important information I should know about medicines called Non-Steroidal Anti-Inflammatory Drugs (NSAIDs)? NSAIDs can cause serious side effects, including: Increased risk of a heart attack or stroke that can lead to death. This risk may happen early in treatment and may increase: with increasing doses of NSAIDs with longer use of NSAIDs Do not take NSAIDs right before or after a heart surgery called a “coronary artery bypass graft (CABG)”.
Avoid taking NSAIDs after a recent heart attack, unless your healthcare provider tells you to. You may have an increased risk of another heart attack if you take NSAIDs after a recent heart attack. Increased risk of bleeding, ulcers, and tears (perforation) of the esophagus (tube leading from the mouth to the stomach), stomach and intestines: anytime during use without warning symptoms that may cause death The risk of getting an ulcer or bleeding increases with: o past history of stomach ulcers, or stomach or intestinal bleeding with use of NSAIDs o taking medicines called “corticosteroids”, “anticoagulants”, “SSRIs”, or “SNRIs” o increasing doses of NSAIDs o longer use of NSAIDs o smoking o drinking alcohol o older age o poor health o advanced liver disease o bleeding problems NSAIDs should only be used: o exactly as prescribed o at the lowest dose possible for your treatment o for the shortest time needed What are NSAIDs?
NSAIDs are used to treat pain and redness, swelling, and heat (inflammation) from medical conditions such as different types of arthritis, menstrual cramps, and other types of short-term pain. Who should not take NSAIDs? Do not take NSAIDs: if you have had an asthma attack, hives, or other allergic reaction with aspirin or any other NSAIDs. right before or after heart bypass surgery.
Before taking NSAIDs, tell your healthcare provider about all of your medical conditions, including if you: have liver or kidney problems have high blood pressure have asthma are pregnant or plan to become pregnant. Taking NSAIDs at about 20 weeks of pregnancy or later may harm your unborn baby. If you need to take NSAIDs for more than 2 days when you are between 20 and 30 weeks of pregnancy, your healthcare provider may need to monitor the amount of fluid in your womb around your baby.
You should not take NSAIDs after about 30 weeks of pregnancy. are breastfeeding or plan to breastfeed. Tell your healthcare provider about all of the medicines you take, including prescription or over-the-counter medicines, vitamins or herbal supplements. NSAIDs and some other medicines can interact with each other and cause serious side effects.
Do not start taking any new medicine without talking to your healthcare provider first. What are the possible side effects of NSAIDs? NSAIDs can cause serious side effects, including: See “What is the most important information I should know about medicines called Nonsteroidal Anti-inflammatory Drugs (NSAIDs)?” new or worse high blood pressure heart failure liver problems including liver failure kidney problems including kidney failure low red blood cells (anemia) life-threatening skin reactions life-threatening allergic reactions Other side effects of NSAIDs include: stomach pain, constipation, diarrhea, gas, heartburn, nausea, vomiting, and dizziness.
Get emergency help right away if you have any of the following symptoms: shortness of breath or trouble breathing chest pain weakness in one part or side of your body slurred speech swelling of the face or throat Stop taking your NSAID and call your healthcare provider right away if you get any of the following symptoms: nausea more tired or weaker than usual diarrhea itching your skin or eyes look yellow indigestion or stomach pain flu-like symptoms vomit blood there is blood in your bowel movement or it is black and sticky like tar unusual weight gain skin rash or blisters with fever swelling of the arms and legs, hands and feet If y…