
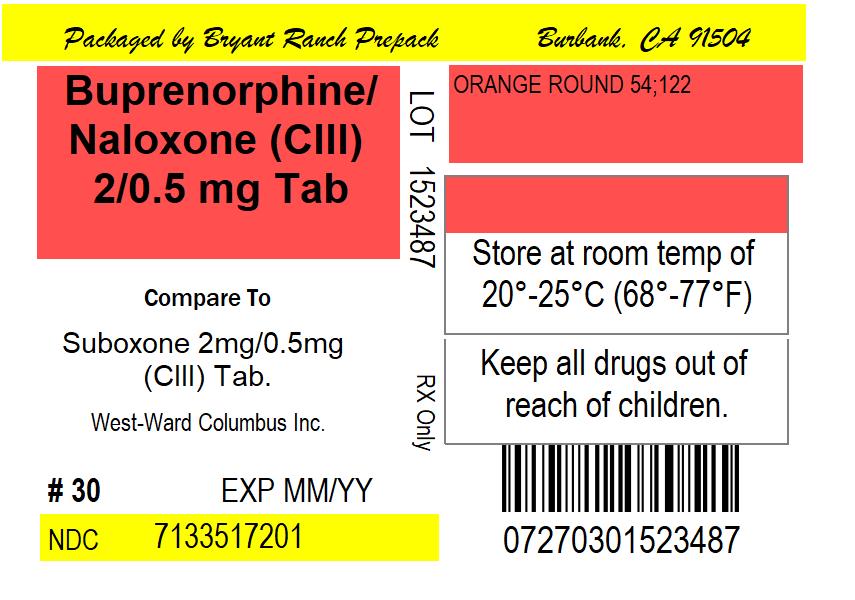
buprenorphine hydrochloride and naloxone hydrochloride dihydrate 2 mg; .5 mg Tablet, 10-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Partial Opioid Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Buprenorphine and the combination of buprenorphine and naloxone are used to treat opioid dependence (addiction to opioid drugs, including heroin and narcotic painkillers). Buprenorphine is in a class of medications called opioid partial agonist-antagonists and naloxone is in a class of medications called opioid antagonists. Buprenorphine alone and the combination of buprenorphine and naloxone work to prevent withdrawal symptoms when someone stops taking opioid drugs by producing similar effects to these drugs.
Read the full MedlinePlus article ↗- That's a really common question. Buprenorphine is technically a partial opioid — it does work on the same brain receptors as opioids like heroin or oxycodone. But it activates thos...
- What exactly does this medication do — is it just replacing one opioid with another?
- No — do not swallow it. Both the tablet and the Suboxone film need to dissolve right where you put them: the tablet goes under your tongue, and the film can go under your tongue or...
- How do I take the film or tablet — do I just swallow it?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 96K6UQ3ZD4
Sucralose is a synthetic sweetener made from sugar. It's added to medicines to improve taste without adding calories, helping make bitter or unpleasant-tasting drugs easier to take.
-
UNII B22547B95K
A salt derived from citric acid that helps maintain the proper acid-base balance in the medicine. It's used as a buffer to keep the product stable and at the right pH level.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.6705 | $6.71 / 10 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| buprenorphine and naloxone 2 mg/1; .5 mg 00054-0188-13 | Hikma | 30 tablets | $0.462 | AB | Availability likely | — |
| Buprenorphine and Naloxone 2 mg/1; .5 mg 00121-1018-30 | PAI | 30 tablets | $0.462 | AB | Availability likely | — |
| Buprenorphine and Naloxone 2 mg/1; .5 mg 00228-3154-03 | Actavis | 30 tablets | $0.462 | AB | Availability likely | — |
| Buprenorphine Hydrochloride and Naloxone Hydrochloride Dihydrate 2 mg/1; .5 mg 00406-8005-03 | SpecGx | 30 tablets | $0.462 | AB | Availability likely | — |
| buprenorphine hydrochloride and naloxone hydrochloride dihydrate 2 mg/1; .5 mg 00904-7009-06 | Major | 50 tablets | $0.462 | AB | Availability likely | — |
| BUPRENORPHINE HYDROCHLORIDE and NALOXONE HYDROCHLORIDE DIHYDRATE 2 mg/1; .5 mg 16729-0549-10 | Accord | 30 tablets | $0.462 | AB | Availability likely | — |
| Buprenorphine and Naloxone 2 mg/1; .5 mg 42858-0601-03 | Rhodes | 30 tablets | $0.462 | AB | Availability likely | — |
| Buprenorphine HCl and Naloxone HCl 2 mg/1; .5 mg 50268-0144-15 | AvPAK | 50 tablets | $0.462 | AB | Availability likely | — |
| Buprenorphine and Naloxone 2 mg/1; .5 mg 60687-0626-65 | American | 50 tablets | $0.462 | AB | Availability likely | — |
| Buprenorphine and Naloxone 2 mg/1; .5 mg 62175-0452-32 | Lannett | 30 tablets | $0.462 | AB | Availability likely | — |
| Buprenorphine HCl and Naloxone HCl 2 mg/1; .5 mg 65162-0416-03 | Amneal | 30 tablets | $0.462 | AB | Availability likely | — |
| Buprenorphine and Naloxone 2 mg/1; .5 mg 31722-0850-30 | Camber | 30 tablets | — | AB | FDA listed | — |
| buprenorphine hydrochloride and naloxone hydrochloride dihydrate .5 mg/1; 2 mg 51407-0948-30 | Golden | 30 tablets | — | AB | FDA listed | — |
| BUPRENORPHINE HYDROCHLORIDE and NALOXONE HYDROCHLORIDE DIHYDRATE 2 mg/1; .5 mg 58118-0549-08 | Clinical | 30 tablets | — | AB | FDA listed | — |
| buprenorphine hydrochloride and naloxone hydrochloride dihydrate 2 mg/1; .5 mg 58118-1188-08 | Clinical | 30 tablets | — | AB | FDA listed | — |
| Buprenorphine Hydrochloride and Naloxone Hydrochloride Dihydrate 2 mg/1; .5 mg 58118-8005-08 | Clinical | 30 tablets | — | AB | FDA listed | — |
| Buprenorphine and Naloxone 2 mg/1; .5 mg 62756-0969-64 | Sun | 30 tablets | — | AB | FDA listed | — |
| Buprenorphine HCl and Naloxone HCl 2 mg/1; .5 mg 63629-7269-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Buprenorphine and Naloxone 2 mg/1; .5 mg 63629-9482-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Buprenorphine And Naloxone 2 mg/1; .5 mg 67877-0607-30 | Ascend | 30 tablets | — | AB | FDA listed | — |
| buprenorphine hydrochloride and naloxone hydrochloride dihydrate 2 mg/1; .5 mg 70518-3862-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Buprenorphine and Naloxone 2 mg/1; .5 mg 71335-1296-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Buprenorphine HCl and Naloxone HCl 2 mg/1; .5 mg 71335-1514-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| buprenorphine hydrochloride and naloxone hydrochloride dihydrate 2 mg/1; .5 mg 71335-1653-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| buprenorphine hydrochloride and naloxone hydrochloride dihydrate 2 mg/1; .5 mgthis 71335-1720-02 | Bryant | 10 tablets | — | AB | FDA listed | — |
| Buprenorphine and Naloxone 2 mg/1; .5 mg 72162-1346-03 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Buprenorphine Hydrochloride and Naloxone Hydrochloride Dihydrate 2 mg/1; .5 mg 87441-0003-01 | Unit | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-1720-01 | 30 TABLET in 1 BOTTLE (71335-1720-1) | 2020-10-19 | Active |
| 71335-1720-02 You're viewing this | 10 TABLET in 1 BOTTLE (71335-1720-2) | 2022-07-01 | Active |
You're viewing the smallest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-1720-02?
What is the difference between NDC 71335-1720-02 and NDC 71335-1720-01?
What NDC number is used to bill for this package of buprenorphine hydrochloride and naloxone hydrochloride dihydrate 2 mg; .5 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Buprenorphine and Naloxone Sublingual Tablets are indicated for the maintenance treatment of opioid dependence. Buprenorphine and Naloxone Sublingual Tablets should be used as part of a complete treatment plan to include counseling and psychosocial support. Buprenorphine and Naloxone Sublingual Tablets contain buprenorphine, a partial opioid agonist, and naloxone, an opioid antagonist, and are indicated for the maintenance treatment of opioid dependence.
( 1 ) Buprenorphine and Naloxone Sublingual Tablets should be used as part of a complete treatment plan that includes counseling and psychosocial support. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Administer Buprenorphine and Naloxone Sublingual Tablets sublingually as a single daily dose. ( 2.1 ) • Strongly consider prescribing naloxone at the time Buprenorphine and Naloxone Sublingual Tablets are initiated or renewed because patients being treated for opioid use disorder have the potential for relapse, putting them at risk for opioid overdose ( 2.2 ) • To avoid precipitating withdrawal, induction with Buprenorphine Sublingual Tablets should be undertaken when objective and clear signs of withdrawal are evident.
After induction, doses of Buprenorphine and Naloxone Sublingual Tablets should be progressively adjusted to a level that holds the patient in treatment and suppresses opioid withdrawal signs and symptoms. ( 2.3 ) • The recommended target dosage of Buprenorphine and Naloxone Sublingual Tablets for maintenance is 16 mg/4 mg. ( 2.3 ) • Administer Buprenorphine and Naloxone Sublingual Tablets as directed in the Full Prescribing Information.
( 2.3 , 2.4 ) • When discontinuing treatment, gradually taper to avoid signs and symptoms of withdrawal. ( 2.7 )
2.1Important Dosage and Administration Information Buprenorphine and Naloxone Sublingual Tablets are administered sublingually as a single daily dose. Buprenorphine and Naloxone Sublingual Tablets should be used in patients who have been initially inducted using buprenorphine sublingual tablets. Medication should be prescribed in consideration of the frequency of visits.
Provision of multiple refills is not advised early in treatment or without appropriate patient follow-up visits.
2.2Patient Access to Naloxone for the Emergency Treatment of Opioid Overdose Discuss the availability of naloxone for the emergency treatment of opioid overdose with the patient and caregiver. Because patients being treated for opioid use disorder have the potential for relapse, putting them at risk for opioid overdose, strongly consider prescribing naloxone for the emergency treatment of opioid overdose, both when initiating and renewing treatment with Buprenorphine and Naloxone Sublingual Tablets. Also consider prescribing naloxone if the patient has household members (including children) or other close contacts at risk for accidental ingestion or opioid overdose [see Warnings and Precautions ( 5.3 )].
Advise patients and caregivers that naloxone may also be administered for a known or suspected overdose with Buprenorphine and Naloxone Sublingual Tablets itself. Higher than normal doses and repeated administration of naloxone may be necessary due to the long duration of action of Buprenorphine and Naloxone Sublingual Tablets and its affinity for the mu receptor [see Overdosage ( 10 )]. Inform patients and caregivers of their options for obtaining naloxone as permitted by individual state naloxone dispensing and prescribing requirements or guidelines (e.g., by prescription, directly from a pharmacist, or as part of a community-based program) [see Patient Counseling Information ( 17 )].
2.3Maintenance • The dosage of Buprenorphine and Naloxone Sublingual Tablets should be progressively adjusted in increments/decrements of 2 mg/0.5 mg or 4 mg/1 mg buprenorphine/naloxone to a level that holds the patient in treatment and suppresses opioid withdrawal signs and symptoms • The maintenance dose of Buprenorphine and Naloxone Sublingual Tablets is generally in the range of 4 mg/1 mg buprenorphine/naloxone to 24 mg/6 mg buprenorphine/naloxone per day depending on the individual patient. The recommended target dosage of Buprenorphine and Naloxone Sublingual Tablets is 16 mg/4 mg buprenorphine/naloxone/day as a single daily dose.
Dosages higher than 24 mg/6 mg have not been demonstrated to provide any clinical advantage. • When determining the prescription quantity for unsupervised administration, consider the patient’s level of stability, the security of his or her home situation, and other factors likely to affect the ability to manage supplies of take-home medicatio…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Buprenorphine and Naloxone Sublingual Tablets, USP are supplied as speckled-peach to peach, flat faced beveled edge tablets in two dosage strengths: • Buprenorphine 2 mg / naloxone 0.5 mg • Buprenorphine 8 mg / naloxone 2 mg Sublingual Tablet: • Buprenorphine 2 mg / naloxone 0.5 mg and • Buprenorphine 8 mg / naloxone 2 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Buprenorphine and Naloxone Sublingual Tablets are contraindicated in patients with a history of hypersensitivity to buprenorphine or naloxone as serious adverse reactions, including anaphylactic shock, have been reported [see Warnings and Precautions ( 5.9 )]. Hypersensitivity to buprenorphine or naloxone. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Addiction, Abuse, and Misuse : Buprenorphine can be abused in a similar manner to other opioids. Clinical monitoring appropriate to the patient’s level of stability is essential. Monitor patients for conditions indicative of diversion or progression of opioid dependence and addictive behaviors.
Multiple refills should not be prescribed early in treatment or without appropriate patient follow-up visits. ( 5.1 ) • Respiratory Depression : Life-threatening respiratory depression and death have occurred in association with buprenorphine use. Warn patients of the potential danger of self-administration of benzodiazepine or other CNS depressants while under treatment with Buprenorphine and Naloxone Sublingual Tablets.
( 5.2 , 5.3 ) • Unintentional Pediatric Exposure : Store Buprenorphine and Naloxone Sublingual Tablets safely out of the sight and reach of children. Buprenorphine can cause severe, possibly fatal, respiratory depression in children. ( 5.4 ) • Neonatal Opioid Withdrawal Syndrome : Neonatal opioid withdrawal syndrome (NOWS) is an expected and treatable outcome of prolonged use of opioids during pregnancy.
( 5.5 ) • Adrenal Insufficiency : If diagnosed, treat with physiologic replacement of corticosteroids, and wean patient off of the opioid. ( 5.6 ) • Risk of Opioid Withdrawal with Abrupt Discontinuation : If treatment is temporarily interrupted or discontinued, monitor patients for withdrawal and treat appropriately. ( 5.7 ) • Risk of Hepatitis, Hepatic Events : Monitor liver function tests prior to initiation and during treatment and evaluate suspected hepatic events.
( 5.8 ) • Precipitation of Opioid Withdrawal Signs and Symptoms : An opioid withdrawal syndrome is likely to occur with parenteral misuse of Buprenorphine and Naloxone Sublingual Tablets by individuals physically dependent on full opioid agonists, or by sublingual administration before the agonist effects of other opioids have subsided. ( 5.10 ) • Risk of Overdose in Opioid-Naïve Patients : Buprenorphine and Naloxone Sublingual Tablets are not appropriate as an analgesic. There have been reported deaths of opioid naïve individuals who received a 2 mg sublingual dose.
( 5.11 )
5.1Addiction, Abuse, and Misuse Buprenorphine and Naloxone Sublingual Tablets contain buprenorphine, a schedule III controlled substance that can be abused in a manner similar to other opioids, legal or illicit. Prescribe and dispense buprenorphine with appropriate precautions to minimize risk of misuse, abuse, or diversion, and ensure appropriate protection from theft, including in the home. Clinical monitoring appropriate to the patient’s level of stability is essential.
Multiple refills should not be prescribed early in treatment or without appropriate patient follow-up visits [see Drug Abuse and Dependence ( 9.2 )].
5.2Risk of Life-Threatening Respiratory and Central Nervous System (CNS) Depression Buprenorphine has been associated with life-threatening respiratory depression and death. Many, but not all, post-marketing reports regarding coma and death involved misuse by self-injection or were associated with the concomitant use of buprenorphine and benzodiazepines or other CNS depressant, including alcohol. Warn patients of the potential danger of self-administration of benzodiazepines or other CNS depressants while under treatment with Buprenorphine and Naloxone Sublingual Tablets [see Warnings and Precautions ( 5.3 ), Drug Interactions ( 7 )] .
Use Buprenorphine and Naloxone Sublingual Tablets with caution in patients with compromised respiratory function (e.g., chronic obstructive pulmonary disease, cor pulmonale, decreased respiratory reserve, hypoxia, hypercapnia, or pre-existing respiratory depression). Educate patients and caregivers on how to recognize respiratory depression and emphasize the importance of calling 911 or getting emergency medical help right away in the event of a known or suspected overdose [see Patient Counseling Informat…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described elsewhere in the labeling: • Addiction, Abuse, and Misuse [see Warnings and Precautions ( 5.1 )] • Respiratory and CNS Depression [see Warnings and Precautions ( 5.2 , 5.3 )] • Neonatal Opioid Withdrawal Syndrome [see Warnings and Precautions ( 5.5 )] • Adrenal Insufficiency [see Warnings and Precautions ( 5.6 )] • Opioid Withdrawal [see Warnings and Precautions ( 5.7 , 5.10 )] • Hepatitis, Hepatic Events [see Warnings and Precautions ( 5.8 )] • Hypersensitivity Reactions [see Warnings and Precautions ( 5.9 )] • Orthostatic Hypotension [see Warnings and Precautions ( 5.16 )] • Elevation of Cerebrospinal Fluid Pressure [see Warnings and Precautions ( 5.17 )] • Elevation of Intracholedochal Pressure [see Warnings and Precautions ( 5.18 )] Adverse events commonly observed with administration of buprenorphine/naloxone are oral hypoesthesia, glossodynia, oral mucosal erythema, headache, nausea, vomiting, hyperhidrosis, constipation, signs and symptoms of withdrawal, insomnia, pain, and peripheral edema.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Hikma Pharmaceuticals USA Inc. at 1-800-962-8364 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety of Buprenorphine and Naloxone Sublingual Tablets was evaluated in 497 opioid-dependent subjects. The prospective evaluation of Buprenorphine and Naloxone Sublingual Tablets was supported by clinical trials using buprenorphine sublingual tablets (buprenorphine tablets without naloxone) and other trials using buprenorphine sublingual solutions.
In total, safety data were available from 3,214 opioid-dependent subjects exposed to buprenorphine at doses in the range used in treatment of opioid addiction. Few differences in adverse event profile were noted between Buprenorphine and Naloxone Sublingual Tablets and buprenorphine sublingual tablets or buprenorphine administered as a sublingual solution. The following adverse events were reported to occur by at least 5% of patients in a 4-week study (Table 1).
Table 1. Adverse Events ≥ 5% by Body System and Treatment Group in a 4-week Study N (%) N (%) Body System/Adverse Event (COSTART Terminology) Buprenorphine and Naloxone Sublingual Tablets 16 mg/day N=107 Placebo N=107 Body as a Whole Asthenia 7 (6.5%) 7 (6.5%) Chills 8 (7.5%) 8 (7.5%) Headache 39 (36.4%) 24 (22.4%) Infection 6 (5.6%) 7 (6.5%) Pain 24 (22.4%) 20 (18.7%) Pain Abdomen 12 (11.2%) 7 (6.5%) Pain Back 4 (3.7%) 12 (11.2%) Withdrawal Syndrome 27 (25.2%) 40 (37.4%) Cardiovascular System Vasodilation 10 (9.3%) 7 (6.5%) Digestive System Constipation 13 (12.1%) 3 (2.8%) Diarrhea 4 (3.7%) 16 (15.0%) Nausea 16 (15.0%) 12 (11.2%) Vomiting 8 (7.5%) 5 (4.7%) Nervous System Insomnia 15 (14.0%) 17 (15.9%) Respiratory System Rhinitis 5 (4.7%) 14 (13.1%) Skin and Appendages Sweating 15 (14.0%) 11 (10.3%) The adverse event profile of buprenorphine was also characterized in the dose-controlled study of buprenorphine solution, over a range of doses in four months of treatment.
Table 2 shows adverse events reported by at least 5% of subjects in any dose group in the dose-controlled study. Table 2. Adverse Events (≥ 5%) by Body System and Treatment Group in a 16-Week Study Body System/ Adverse Event (COSTART Terminology) Buprenorphine Dose Sublingual solution.
Doses in this table cannot necessarily be delivered in tablet form, but for comparison purposes: “Very low” dose (1 mg solution) would be less than a tablet dose of 2 mg “Low” dose (4 mg solution) approximates a 6 mg tablet dose “Moderate” dose (8 mg solution) approximates a 12 mg tablet dose “High” dose (16 mg solution) approximates a 24 mg tablet dose Very Low (N=184)…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 3 includes clinically significant drug interactions with Buprenorphine and Naloxone Sublingual Tablets. Table 3. Clinically Significant Drug Interactions Benzodiazepines or Other Central Nervous System (CNS) Depressants Clinical Impact: Due to additive pharmacologic effects, the concomitant use of benzodiazepines or other CNS depressants, including alcohol, increases the risk of respiratory depression, profound sedation, coma, and death.
Intervention: Cessation of benzodiazepines or other CNS depressants is preferred in most cases of concomitant use. In some cases, monitoring in a higher level of care for taper may be appropriate. In others, gradually tapering a patient off of a prescribed benzodiazepine or other CNS depressant or decreasing to the lowest effective dose may be appropriate.
Before co-prescribing benzodiazepines for anxiety or insomnia, ensure that patients are appropriately diagnosed and consider alternative medications and non-pharmacologic treatments [see Warnings and Precautions ( 5.2 , 5.3 )]. If concomitant use is warranted, strongly consider prescribing naloxone for the emergency treatment of opioid overdose, as is recommended for all patients in treatment for opioid use disorder [see Warnings and Precautions ( 5.3 )]. Examples: Alcohol, non-benzodiazepine sedatives/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, and other opioids.
Inhibitors of CYP3A4 Clinical Impact: The concomitant use of buprenorphine and CYP3A4 inhibitors can increase the plasma concentration of buprenorphine, resulting in increased or prolonged opioid effects, particularly when an inhibitor is added after a stable dose of Buprenorphine and Naloxone Sublingual Tablets is achieved. After stopping a CYP3A4 inhibitor, as the effects of the inhibitor decline, the buprenorphine plasma concentration will decrease [see Clinical Pharmacology ( 12.3 )] , potentially resulting in decreased opioid efficacy or a withdrawal syndrome in patients who had developed physical dependence to buprenorphine.
Intervention: If concomitant use is necessary, consider dosage reduction of Buprenorphine and Naloxone Sublingual Tablets until stable drug effects are achieved. Monitor patients for respiratory depression and sedation at frequent intervals. If a CYP3A4 inhibitor is discontinued, consider increasing the Buprenorphine and Naloxone Sublingual Tablets dosage until stable drug effects are achieved.
Monitor for signs of opioid withdrawal. Examples: Macrolide antibiotics (e.g., erythromycin), azole-antifungal agents (e.g., ketoconazole), protease inhibitors (e.g., ritonavir) CYP3A4 Inducers Clinical Impact: The concomitant use of buprenorphine and CYP3A4 inducers can decrease the plasma concentration of buprenorphine [see Clinical Pharmacology ( 12.3 )] , potentially resulting in decreased efficacy or onset of a withdrawal syndrome in patients who have developed physical dependence to buprenorphine. After stopping a CYP3A4 inducer, as the effects of the inducer decline, the buprenorphine plasma concentration will increase [see Clinical Pharmacology ( 12.3 )] , which could increase or prolong both therapeutic effects and adverse reactions and may cause serious respiratory depression.
Intervention: If concomitant use is necessary, consider increasing the Buprenorphine and Naloxone Sublingual Tablets dosage until stable drug effects are achieved. Monitor for signs of opioid withdrawal. If a CYP3A4 inducer is discontinued, consider Buprenorphine and Naloxone Sublingual Tablets dosage reduction and monitor for signs of respiratory depression.
Examples: Rifampin, carbamazepine, phenytoin Antiretrovirals: Non-nucleoside reverse transcriptase inhibitors (NNRTIs) Clinical Impact: Non-nucleoside reverse transcriptase inhibitors (NNRTIs) are metabolized principally by CYP3A4. Efavirenz, nevirapine, and etravirine are known CYP3A inducers, whereas delavirdine is a CYP3A inhibitor. Significant pharm…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Lactation: Buprenorphine passes into mother’s milk. ( 8.2 ) • Geriatric Patients: Monitor for sedation and respiratory depression. ( 8.5 ) • Moderate and Severe Hepatic Impairment: Buprenorphine/naloxone products are not recommended in patients with severe hepatic impairment and may not be appropriate for patients with moderate hepatic impairment. ( 8.6 )
8.1Pregnancy Risk Summary The data on use of buprenorphine, one of the active ingredients in Buprenorphine and Naloxone Sublingual Tablets, in pregnancy, are limited; however, these data do not indicate an increased risk of major malformations specifically due to buprenorphine exposure. There are limited data from randomized clinical trials in women maintained on buprenorphine that were not designed appropriately to assess the risk of major malformations [ see Data ]. Observational studies have reported on congenital malformations among buprenorphine‐exposed pregnancies, but were also not designed appropriately to assess the risk of congenital malformations specifically due to buprenorphine exposure [ see Data ].
The extremely limited data on sublingual naloxone exposure in pregnancy are not sufficient to evaluate a drug‐associated risk. Reproductive and developmental studies in rats and rabbits identified adverse events at clinically relevant and higher doses. Embryo-fetal death was observed in both rats and rabbits administered buprenorphine during the period of organogenesis at doses approximately 6 and 0.3 times, respectively, the human sublingual dose of 16 mg/day of buprenorphine.
Pre- and post-natal development studies in rats demonstrated increased neonatal deaths at 0.3 times and above and dystocia at approximately 3 times the human sublingual dose of 16 mg/day of buprenorphine. No clear teratogenic effects were seen when buprenorphine was administered during organogenesis with a range of doses equivalent to or greater than the human sublingual dose of 16 mg/day of buprenorphine. However, increases in skeletal abnormalities were noted in rats and rabbits administered buprenorphine daily during organogenesis at doses approximately 0.6 times and approximately equal to the human sublingual dose of 16 mg/day of buprenorphine, respectively.
In a few studies, some events such as acephalus and omphalocele were also observed but these findings were not clearly treatment-related [ see Data ]. Based on animal data, advise pregnant women of the potential risk to a fetus. The estimated background risks of major birth defects and miscarriage for the indicated population are unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Disease-associated maternal and embryo-fetal risk Untreated opioid addiction in pregnancy is associated with adverse obstetrical outcomes such as low birth weight, preterm birth, and fetal death.
In addition, untreated opioid addiction often results in continued or relapsing illicit opioid use. Dose Adjustment during Pregnancy and the Postpartum Period Dosage adjustments of buprenorphine may be required during pregnancy, even if the patient was maintained on a stable dose prior to pregnancy. Withdrawal signs and symptoms should be monitored closely and the dose adjusted as necessary.
Fetal/Neonatal Adverse Reactions Neonatal opioid withdrawal syndrome may occur in newborn infants of mothers who are receiving treatment with Buprenorphine and Naloxone Sublingual Tablets. Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea, and/or failure to gain weight. Signs of neonatal withdrawal usually occur in the first days after birth.
The duration and severity of neonatal opioid withdrawal syndrome may va…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The data on use of buprenorphine, one of the active ingredients in Buprenorphine and Naloxone Sublingual Tablets, in pregnancy, are limited; however, these data do not indicate an increased risk of major malformations specifically due to buprenorphine exposure. There are limited data from randomized clinical trials in women maintained on buprenorphine that were not designed appropriately to assess the risk of major malformations [ see Data ]. Observational studies have reported on congenital malformations among buprenorphine‐exposed pregnancies, but were also not designed appropriately to assess the risk of congenital malformations specifically due to buprenorphine exposure [ see Data ].
The extremely limited data on sublingual naloxone exposure in pregnancy are not sufficient to evaluate a drug‐associated risk. Reproductive and developmental studies in rats and rabbits identified adverse events at clinically relevant and higher doses. Embryo-fetal death was observed in both rats and rabbits administered buprenorphine during the period of organogenesis at doses approximately 6 and 0.3 times, respectively, the human sublingual dose of 16 mg/day of buprenorphine.
Pre- and post-natal development studies in rats demonstrated increased neonatal deaths at 0.3 times and above and dystocia at approximately 3 times the human sublingual dose of 16 mg/day of buprenorphine. No clear teratogenic effects were seen when buprenorphine was administered during organogenesis with a range of doses equivalent to or greater than the human sublingual dose of 16 mg/day of buprenorphine. However, increases in skeletal abnormalities were noted in rats and rabbits administered buprenorphine daily during organogenesis at doses approximately 0.6 times and approximately equal to the human sublingual dose of 16 mg/day of buprenorphine, respectively.
In a few studies, some events such as acephalus and omphalocele were also observed but these findings were not clearly treatment-related [ see Data ]. Based on animal data, advise pregnant women of the potential risk to a fetus. The estimated background risks of major birth defects and miscarriage for the indicated population are unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Disease-associated maternal and embryo-fetal risk Untreated opioid addiction in pregnancy is associated with adverse obstetrical outcomes such as low birth weight, preterm birth, and fetal death.
In addition, untreated opioid addiction often results in continued or relapsing illicit opioid use. Dose Adjustment during Pregnancy and the Postpartum Period Dosage adjustments of buprenorphine may be required during pregnancy, even if the patient was maintained on a stable dose prior to pregnancy. Withdrawal signs and symptoms should be monitored closely and the dose adjusted as necessary.
Fetal/Neonatal Adverse Reactions Neonatal opioid withdrawal syndrome may occur in newborn infants of mothers who are receiving treatment with Buprenorphine and Naloxone Sublingual Tablets. Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea, and/or failure to gain weight. Signs of neonatal withdrawal usually occur in the first days after birth.
The duration and severity of neonatal opioid withdrawal syndrome may vary. Observe newborns for signs of neonatal opioid withdrawal syndrome and manage accordingly [see Warnings and Precautions ( 5.5 )] . Labor or Delivery Opioid‐dependent women on buprenorphine maintenance therapy may require additional analgesia during labor.
Data Human Data Studies have been conducted to evaluate neonatal outcomes in women exposed to buprenorphine during pregnancy. Limit…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of Buprenorphine and Naloxone Sublingual Tablets have not been established in pediatric patients. This product is not appropriate for the treatment of neonatal abstinence syndrome in neonates, because it contains naloxone, an opioid antagonist.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of Buprenorphine and Naloxone Sublingual Tablets, buprenorphine and naloxone sublingual film, or buprenorphine sublingual tablets did not include sufficient numbers of subjects aged 65 and over to determine whether they responded differently than younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. Due to possible decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy in geriatric patients, the decision to prescribe Buprenorphine and Naloxone Sublingual Tablets should be made cautiously in individuals 65 years of age or older and these patients should be monitored for signs and symptoms of toxicity or overdose.
🆘 Overdosage ▾
10 OVERDOSAGE Clinical Presentation The manifestations of acute overdose include pinpoint pupils, sedation, hypotension, hypoglycemia, respiratory depression, and death. Treatment of Overdose In the event of overdose, the respiratory and cardiac status of the patient should be monitored carefully. When respiratory or cardiac functions are depressed, primary attention should be given to the re-establishment of adequate respiratory exchange through provision of a patent airway and institution of assisted or controlled ventilation.
Oxygen, IV fluids, vasopressors, and other supportive measures should be employed as indicated. In the case of overdose, the primary management should be the re-establishment of adequate ventilation with mechanical assistance of respiration, if required. Naloxone may be of value for the management of buprenorphine overdose.
Higher than normal doses and repeated administration may be necessary. The long duration of action of Buprenorphine and Naloxone Sublingual Tablets should be taken into consideration when determining the length of treatment and medical surveillance needed to reverse the effects of an overdose. Insufficient duration of monitoring may put patients at risk.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Buprenorphine and Naloxone Sublingual Tablets contain buprenorphine and naloxone. Buprenorphine is a partial agonist at the mu-opioid receptor and an antagonist at the kappa-opioid receptor. Naloxone is an opioid antagonist and produces opioid withdrawal signs and symptoms in individuals physically dependent on full opioid agonists when administered parenterally.
12.2Pharmacodynamics Subjective Effects Comparisons of buprenorphine to full opioid agonists such as methadone and hydromorphone suggest that sublingual buprenorphine produces typical opioid agonist effects which are limited by a ceiling effect. In opioid-experienced subjects who were not physically dependent, acute sublingual doses of buprenorphine/naloxone tablets produced opioid agonist effects which reached a maximum between doses of 8 mg/2 mg and 16 mg/4 mg buprenorphine/naloxone. Opioid agonist ceiling-effects were also observed in a double-blind, parallel-group, dose-ranging comparison of single doses of buprenorphine sublingual solution (1, 2, 4, 8, 16, or 32 mg), placebo and a full agonist control at various doses.
The treatments were given in ascending dose order at intervals of at least one week to 16 opioid-experienced subjects who were not physically dependent. Both active drugs produced typical opioid agonist effects. For all measures for which the drugs produced an effect, buprenorphine produced a dose-related response.
However, in each case, there was a dose that produced no further effect. In contrast, the highest dose of the full agonist control always produced the greatest effects. Agonist objective rating scores remained elevated for the higher doses of buprenorphine (8 to 32 mg) longer than for the lower doses and did not return to baseline until 48 hours after drug administration.
The onset of effects appeared more rapidly with buprenorphine than with the full agonist control, with most doses nearing peak effect after 100 minutes for buprenorphine compared to 150 minutes for the full agonist control. Physiologic Effects Buprenorphine in IV (2, 4, 8, 12 and 16 mg) and sublingual (12 mg) doses have been administered to opioid-experienced subjects who were not physically dependent to examine cardiovascular, respiratory, and subjective effects at doses comparable to those used for treatment of opioid dependence.
Compared to placebo, there were no statistically significant differences among any of the treatment conditions for blood pressure, heart rate, respiratory rate, O 2 saturation, or skin temperature across time. Systolic BP was higher in the 8 mg group than placebo (3-hour AUC values). Minimum and maximum effects were similar across all treatments.
Subjects remained responsive to low voice and responded to computer prompts. Some subjects showed irritability, but no other changes were observed. The respiratory effects of sublingual buprenorphine were compared with the effects of methadone in a double-blind, parallel-group, dose-ranging comparison of single doses of buprenorphine sublingual solution (1, 2, 4, 8, 16, or 32 mg) and oral methadone (15, 30, 45, or 60 mg) in non-dependent, opioid-experienced volunteers.
In this study, hypoventilation not requiring medical intervention was reported more frequently after buprenorphine doses of 4 mg and higher than after methadone. Both drugs decreased O 2 saturation to the same degree. Effect of Naloxone Physiologic and subjective effects following acute sublingual administration of buprenorphine tablets and buprenorphine/naloxone tablets were similar at equivalent dose levels of buprenorphine.
Naloxone had no clinically significant effect when administered by the sublingual route, although blood levels of the drug were measurable. Buprenorphine/naloxone, when administered sublingually to an opioid-dependent cohort, was recognized as an opioid agonist, whereas when administered intramuscularly, combinations of buprenorphine with naloxone produced opioid…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Buprenorphine and Naloxone Sublingual Tablets contain buprenorphine and naloxone. Buprenorphine is a partial agonist at the mu-opioid receptor and an antagonist at the kappa-opioid receptor. Naloxone is an opioid antagonist and produces opioid withdrawal signs and symptoms in individuals physically dependent on full opioid agonists when administered parenterally.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Buprenorphine and Naloxone Sublingual Tablets, USP 2 mg/0.5 mg are supplied as speckled-peach to peach, flat faced beveled edge tablets with product identification “54” [above] “122” on one side and plain on the other. NDC: 71335-1720-1: 30 Tablets in a BOTTLE NDC: 71335-1720-2: 10 Tablets in a BOTTLE Storage Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Dispense in a tight, light-resistant container as defined in USP. Store Buprenorphine and Naloxone Sublingual Tablets securely and dispose of properly [see Patient CounselingInformation (17)].
Repackaged/Relabeled by: Bryant Ranch Prepack Burbank, CA 91504
📋 Description ▾
11 DESCRIPTION Buprenorphine and Naloxone Sublingual Tablets, USP are available in two dosage strengths intended for sublingual administration as follows: 2 mg buprenorphine with 0.5 mg naloxone free bases and 8 mg buprenorphine with 2 mg naloxone free bases. Each tablet also contains citric acid anhydrous, corn starch, FD & C yellow no. 6, lactose monohydrate, lemon-lime flavor, magnesium stearate, mannitol, povidone, sodium citrate dihydrate and sucralose.
Chemically, buprenorphine HCl is (6R, 7R, 14S)-17-Cyclopropylmethyl-7,8-dihydro-7-[(1S)-1-hydroxy-1,2,2-trimethylpropyl]-6-O--methyl-6,14-ethano-17-normorphine hydrochloride. It has the following chemical structure: Buprenorphine hydrochloride, USP has the molecular formula C 29 H 41 NO 4 • HCl and the molecular weight is 504.1. It is a white to almost white crystalline powder, sparingly soluble in water, freely soluble in methanol, soluble in alcohol, and practically insoluble in cyclohexane.
Chemically, naloxone HCl dihydrate, USP is 17-Allyl-4, 5 α-epoxy-3, 14-dihydroxymorphinan-6-one hydrochloride dihydrate. It has the following chemical structure: Naloxone hydrochloride dihydrate has the molecular formula C 19 H 22 ClNO 4, 2H 2 O and the molecular weight is 399.9. It is a white to slightly off-white powder or almost white crystalline powder and is freely soluble in water, soluble in alcohol, and practically insoluble in toluene and ether.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients to read the FDA-approved patient labeling (Medication Guide). Storage and Disposal Because of the risks associated with accidental ingestion, misuse, and abuse, advise patients to store Buprenorphine and Naloxone Sublingual Tablets securely, out of sight and reach of children, and in a location not accessible by others, including visitors to the home [see Warnings and Precautions ( 5.1 , 5.4 ), Abuse ( 9.2 )] . Inform patients that leaving Buprenorphine and Naloxone Sublingual Tablets unsecured can pose a deadly risk to others in the home.
Advise patients and caregivers that when medicines are no longer needed, they should be disposed of promptly. Expired, unwanted, or unused Buprenorphine and Naloxone Sublingual Tablets should be disposed of by flushing the unused medication down the toilet if a drug take-back option is not readily available. Inform patients that they can visit www.fda.gov/drugdisposal for a complete list of medicines recommended for disposal by flushing, as well as additional information on disposal of unused medicines.
Safe Use Before initiating treatment with Buprenorphine and Naloxone Sublingual Tablets, explain the points listed below to caregivers and patients. Instruct patients to read the Medication Guide each time Buprenorphine and Naloxone Sublingual Tablets are dispensed because new information may be available. • Buprenorphine and Naloxone Sublingual Tablets must be administered whole. Advise patients not to cut, chew, or swallow Buprenorphine and Naloxone Sublingual Tablets. • Inform patients and caregivers that potentially fatal additive effects may occur if Buprenorphine and Naloxone Sublingual Tablets are used with benzodiazepines or other CNS depressants, including alcohol.
Counsel patients that such medications should not be used concomitantly unless supervised by a health care provider [see Warnings and Precautions ( 5.2 , 5.3 ), Drug Interactions ( 7 )] . • Educate patients and caregivers on how to recognize respiratory depression and emphasize the importance of calling 911 or getting emergency medical help right away in the event of a known or suspected overdose [see Warnings and Precautions ( 5.2 )] . • Patient Access to Naloxone for the Emergency Treatment of Opioid Overdose Because patients being treated for opioid use disorder are at risk for relapse, discuss the importance of having access to naloxone with the patient and caregiver.
Also discuss the importance of having access to naloxone if there are household members (including children) or other close contacts at risk for accidental ingestion or opioid overdose. Inform patients and caregivers of the options for obtaining naloxone as permitted by individual state naloxone dispensing and prescribing requirements or guidelines (e.g., by prescription, directly from a pharmacist, or as part of a community-based program). Educate patients and caregivers on how to recognize the signs and symptoms of an opioid overdose.
Explain to patients and caregivers that naloxone’s effects are temporary, and that they must call 911 or get emergency medical help right away in all cases of known or suspected opioid overdose, even if naloxone is administered. Repeat administration may be necessary, particularly for overdose involving Buprenorphine and Naloxone Sublingual Tablets, because naloxone is often not effective at the doses available for patient access [Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.3 ), Overdosage ( 10 )] .
If naloxone is prescribed, also advise patients and caregivers: o How to treat with naloxone in the event of an opioid overdose o To tell family and friends about their naloxone and to keep it in a place where family and friends can easily access it in an emergency. o To read the Patient Information (or other educational material) that will come with their naloxone. Emphasize the importance of doing this before an opioid emergency happens, so the patient and…
💬 Medication Guide ▾
Medication Guide Buprenorphine (bue” pre nor’ feen) and Naloxone (nal ox’ one) Sublingual Tablets CIII Rx only IMPORTANT: Keep Buprenorphine and Naloxone Sublingual Tablets in a secure place away from children. Accidental use by a child is a medical emergency and can result in death. If a child accidentally uses Buprenorphine and Naloxone Sublingual Tablets, get emergency help or call 911 right away.
Tell your healthcare provider if you are living in a household where there are small children. What is the most important information I should know about Buprenorphine and Naloxone Sublingual Tablets? • Buprenorphine and Naloxone Sublingual Tablets contain a medicine called buprenorphine. Buprenorphine is an opioid that can cause serious and life-threatening problems, especially if you take or use certain other medicines or drugs. • Talk to your healthcare provider about naloxone.
Naloxone is a medicine that is available to patients for the emergency treatment of an opioid overdose, including accidental use of Buprenorphine and Naloxone Sublingual Tablets by a child. If naloxone is given, you must call 911 or get emergency medical help right away to treat an overdose or accidental use of an opioid. • Buprenorphine and Naloxone Sublingual Tablets may cause serious and life-threatening breathing problems. Get emergency help right away if you: o feel faint o have blurred vision o feel dizzy o have slurred speech o are confused o are breathing slower than normal o feel sleepy or uncoordinated o cannot think well or clearly • Do not take Buprenorphine and Naloxone Sublingual Tablets with certain medicines.
Taking Buprenorphine and Naloxone Sublingual Tablets with other opioid medicines, benzodiazepines, alcohol, or other central nervous system depressants (including street drugs) can cause severe drowsiness, decreased awareness, breathing problems, coma, and death. • Do not inject (“shoot-up”) Buprenorphine and Naloxone Sublingual Tablets. Injecting Buprenorphine and Naloxone Sublingual Tablets may cause life-threatening infections and other serious health problems. Injecting Buprenorphine and Naloxone Sublingual Tablets may cause sudden serious withdrawal symptoms such as pain, cramps, vomiting, diarrhea, anxiety, sleep problems, and cravings. • Do not switch from Buprenorphine and Naloxone Sublingual Tablets to other medicines that contain buprenorphine without talking with your healthcare provider.
The amount of buprenorphine in a dose of Buprenorphine and Naloxone Sublingual Tablets is not the same as in other medicines that contain buprenorphine. Your healthcare provider will prescribe a starting dose of Buprenorphine and Naloxone Sublingual Tablets that may be different than other buprenorphine containing medicines you may have been taking. • Do not stop taking Buprenorphine and Naloxone Sublingual Tablets suddenly. You could become sick and have withdrawal symptoms because your body has become used to the medicine (physical dependence).
Physical dependence is not the same as drug addiction. • In an emergency, have family members tell emergency department staff that you are physically dependent on an opioid and are being treated with Buprenorphine and Naloxone Sublingual Tablets. • Never give anyone else your Buprenorphine and Naloxone Sublingual Tablets. They could die from taking it. Selling or giving away Buprenorphine and Naloxone Sublingual Tablets is against the law. • Store Buprenorphine and Naloxone Sublingual Tablets securely, out of sight and reach of children, and in a location not accessible by others, including visitors to the home.
What are Buprenorphine and Naloxone Sublingual Tablets? • Buprenorphine and Naloxone Sublingual Tablets are a prescription medicine used to treat opioid addiction in adults and is part of a complete treatment program that also includes counseling and behavioral therapy. Who should not take Buprenorphine and Naloxone Sublingual Tablets? Do not take Buprenorphine and Naloxone Sublingual Tab…