
Valtoco diazepam 10 mg/.1mL Spray
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Benzodiazepine class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Diazepam nasal spray is used for emergency situations to control certain types of seizures. Diazepam is in a class of medications called benzodiazepines. It works by calming abnormal overactivity in the brain.
Read the full MedlinePlus article ↗- No, Valtoco is not a daily medication. It's a rescue spray you use at the moment of a seizure cluster — a sudden burst of repeated seizures that looks different from your or your c...
- What exactly is Valtoco used for — is it something I take every day?
- Valtoco comes ready to use — no assembly needed. Your caregiver sprays the full contents into one nostril (for lower doses) or one spray into each nostril using two separate device...
- How does my caregiver actually use the nasal spray during a seizure?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Diazepam — tap one for details:
Diazepam may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $366.664 | $733.33 / 2 vials |
| Medicaid paysCMS SDUD · 12 mo | $348.51 | $697.01 / 2 vials |
| Medicare drug plans payPart D · Q2 2026 | $369.71 | $739.41 / 2 vials |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Valtoco 10 mg/.1mL 72252-0520-04 | Neurelis, | 2 vials | $366.401 | — | Availability likely | +0% |
| Valtoco 10 mg/.1mLthis 72252-0510-02 | Neurelis, | 1 vial | $366.664 | — | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 12324852 ↗ | Method of use | U-4173 | Oct 16, 2032 |
| US 12337061 ↗ | Method of use | U-4173 | Jun 13, 2032 |
| US 12324852 ↗ | Method of use | U-4173 | Oct 16, 2032 |
| US 12337061 ↗ | Method of use | U-4173 | Jun 13, 2032 |
| US 12324852 ↗ | Method of use | U-4173 | Oct 16, 2032 |
| US 12337061 ↗ | Method of use | U-4173 | Jun 13, 2032 |
| US 12599611 ↗ | Method of use | U-4455 | Jun 10, 2042 |
| US 12599611 ↗ | Method of use | U-4455 | Jun 10, 2042 |
| US 12599611 ↗ | Method of use | U-4455 | Jun 10, 2042 |
| US 12268664 ↗ | Drug product | — | Mar 27, 2029 |
| US 12521400 ↗ | Drug product | — | Mar 27, 2029 |
| US 11793786 ↗ | Drug product | — | Mar 27, 2029 |
| US 12521400 ↗ | Drug product | — | Mar 27, 2029 |
| US 12521400 ↗ | Drug product | — | Mar 27, 2029 |
| US 8895546 ↗ | Drug product | — | Mar 27, 2029 |
| US 11793786 ↗ | Drug product | — | Mar 27, 2029 |
| US 11793786 ↗ | Drug product | — | Mar 27, 2029 |
| US 11241414 ↗ | Drug product | — | Mar 27, 2029 |
| US 12268664 ↗ | Drug product | — | Mar 27, 2029 |
| US 12268664 ↗ | Drug product | — | Mar 27, 2029 |
| US 11241414 ↗ | Drug product | — | Mar 27, 2029 |
| US 8895546 ↗ | Drug product | — | Mar 27, 2029 |
| US 8895546 ↗ | Drug product | — | Mar 27, 2029 |
| US 11241414 ↗ | Drug product | — | Mar 27, 2029 |
| Code | What it grants | Expires |
|---|---|---|
| NPP | New Patient Population | Apr 15, 2028 |
| ODE-279 | Orphan Drug Exclusivity (7-year) | Jan 10, 2027 |
| NPP | New Patient Population | Apr 15, 2028 |
| ODE-279 | Orphan Drug Exclusivity (7-year) | Jan 10, 2027 |
| NPP | New Patient Population | Apr 15, 2028 |
| ODE-279 | Orphan Drug Exclusivity (7-year) | Jan 10, 2027 |
Is there a generic version of VALTOCO 10 MG NASAL SPRAY?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 72252-0510-02 You're viewing this | 2 BLISTER PACK in 1 CARTON (72252-510-02) / 1 VIAL, SINGLE-DOSE in 1 BLISTER PACK / .1 mL in 1 VIAL, SINGLE-DOSE | $366.66 / ea | $733.33 | 2020-01-10 | Active |
| 72252-0510-05 | 5 BLISTER PACK in 1 CARTON (72252-510-05) / 1 VIAL, SINGLE-DOSE in 1 BLISTER PACK / .1 mL in 1 VIAL, SINGLE-DOSE | $365.51 / ea | $1,827.57 | 2025-02-28 | Active |
This pack effectively ties for the lowest per-ea cost of the 2 priced pack sizes ($366.66 NADAC).
This pack accounts for about 32% of this product's recent Medicaid fills; most go to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in NDC 72252-0510-02?
What NDC number is used to bill for this package of Valtoco diazepam 10 mg/.1mL Spray?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RISKS FROM CONCOMITANT USE WITH OPIOIDS; ABUSE, MISUSE, AND ADDICTION; and DEPENDENCE AND WITHDRAWAL REACTIONS Concomitant use of benzodiazepines and opioids may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing of these drugs for patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required.
Follow patients for signs and symptoms of respiratory depression and sedation [see Warnings and Precautions (5.1) and Drug Interactions (7.1) ] . The use of benzodiazepines, including VALTOCO, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose or death. Abuse and misuse of benzodiazepines commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes.
Before prescribing VALTOCO and throughout treatment, assess each patient's risk for abuse, misuse, and addiction [see Warnings and Precautions (5.2) ]. The continued use of benzodiazepines may lead to clinically significant physical dependence. The risks of dependence and withdrawal increase with longer treatment duration and higher daily dose.
Although VALTOCO is indicated only for intermittent use [see Indications and Usage (1) and Dosage and Administration (2) ] , if used more frequently than recommended, abrupt discontinuation or rapid dosage reduction of VALTOCO may precipitate acute withdrawal reactions, which can be life-threatening. For patients using VALTOCO more frequently than recommended, to reduce the risk of withdrawal reactions, use a gradual taper to discontinue VALTOCO [see Warnings and Precautions (5.3) ]. WARNING: RISKS FROM CONCOMITANT USE WITH OPIOIDS; ABUSE, MISUSE, AND ADDICTION; and DEPENDENCE AND WITHDRAWAL REACTIONS See full prescribing information for complete boxed warning Concomitant use of benzodiazepines and opioids may result in profound sedation, respiratory depression, coma, and death.
( 5.1 , 7.1 ) The use of benzodiazepines, including VALTOCO, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose or death. Before prescribing VALTOCO and throughout treatment, assess each patient's risk for abuse, misuse, and addiction. ( 5.2 ) Although VALTOCO is indicated only for intermittent use ( 1 , 2 ), if used more frequently than recommended, abrupt discontinuation or rapid dosage reduction of VALTOCO may precipitate acute withdrawal reactions, which can be life-threatening.
For patients using VALTOCO more frequently than recommended, to reduce the risk of withdrawal reactions, use a gradual taper to discontinue VALTOCO. ( 5.3 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE VALTOCO ® is indicated for the acute treatment of intermittent, stereotypic episodes of frequent seizure activity (i.e., seizure clusters, acute repetitive seizures) that are distinct from a patient's usual seizure pattern in patients with epilepsy 2 years of age and older. VALTOCO is a benzodiazepine indicated for the acute treatment of intermittent, stereotypic episodes of frequent seizure activity (i.e., seizure clusters, acute repetitive seizures) that are distinct from a patient's usual seizure pattern in patients with epilepsy 2 years of age and older.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administer VALTOCO by the nasal route only. ( 2.3 ) Dosage is dependent on the patient's age and weight. ( 2.2 ) Initial Dose: VALTOCO 5 mg and 10 mg doses are administered as a single spray intranasally into one nostril.
Administration of 15 mg and 20 mg doses requires two nasal spray devices, one spray into each nostril. ( 2.2 ) Second Dose: A second dose, when required, may be administered at least 4 hours after the initial dose. If administered, use a new blister pack.
( 2.2 ) Maximum Dosage and Treatment Frequency: Do not use more than 2 doses to treat a single episode. It is recommended that VALTOCO be used to treat no more than one episode every five days and no more than five episodes per month. ( 2.2 )
2.1Instructions Prior to Dosing Prior to treatment, healthcare professionals should instruct the individual administering VALTOCO on how to identify seizure clusters and use the product appropriately [see Dosage and Administration (2.3) and Patient Counseling Information (17) ].
2.2Dosing Information The recommended dose of VALTOCO nasal spray is 0.2 mg/kg to 0.5 mg/kg, depending on the patient's age and weight. See Table 1 and Table 2 for specific recommendations. Table 1: Recommended Dose Based on Age Age (Years) Recommended Dose 2 through 5 0.5 mg/kg 6 through 11 0.3 mg/kg 12 and older 0.2 mg/kg Table 2: Recommended Dosage and Administration for Adults and Pediatric Patients 2 Years of Age and Older Dose Based on Age and Weight Administration 2 to 5 Years of Age (0.5 mg/kg) 6 to 11 Years of Age (0.3 mg/kg) 12 Years of Age and Older (0.2 mg/kg) Dose (mg) Number of Nasal Spray Devices Number of Sprays Weight (kg) 6 to 11 10 to 18 14 to 27 5 One 5 mg device One spray in one nostril 12 to 22 19 to 37 28 to 50 10 One 10 mg device One spray in one nostril 23 to 33 38 to 55 51 to 75 15 Two 7.5 mg devices One spray in each nostril 56 to 74 76 and up 20 Two 10 mg devices One spray in each nostril Second Dose (if needed): A second dose, when required, may be administered after at least 4 hours after the initial dose.
If the second dose is to be administered, use a new blister pack of VALTOCO. Maximum Dosage and Treatment Frequency : Do not use more than 2 doses of VALTOCO to treat a single episode. Do not use VALTOCO to treat more than one episode every five days or more than five episodes per month.
2.3Important Administration Instructions VALTOCO is for intranasal use only. No device assembly is required. VALTOCO nasal spray delivers its entire contents upon activation. Do not prime or attempt to use for more than one administration per device. Patients and caregivers should be counseled to read carefully the "Instructions for Use" for complete directions on how to properly administer VALTOCO.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS VALTOCO is available in 5 mg, 7.5 mg, and 10 mg strengths. Each VALTOCO nasal spray device contains 0.1 mL solution. Nasal spray: 5 mg, 7.5 mg, or 10 mg of diazepam in 0.1 mL. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS VALTOCO nasal spray is contraindicated in patients with: Known hypersensitivity to diazepam Acute narrow angle glaucoma [see Warnings and Precautions (5.6) ] Hypersensitivity to diazepam. ( 4 ) Acute narrow-angle glaucoma. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS CNS Depression: Monitor for central nervous system (CNS) depression. May cause an increased CNS-depressant effect when used with alcohol or other CNS depressants. ( 5.4 , 7.2 ) Suicidal Behavior and Ideation: Monitor patients for suicidal ideation and behavior.
( 5.5 ) Glaucoma: VALTOCO can increase intraocular pressure in patients with glaucoma. VALTOCO may be used in patients with open-angle glaucoma only if they are receiving appropriate therapy. ( 4 , 5.6 ) Neonatal Sedation and Withdrawal Syndrome: VALTOCO use during pregnancy can result in neonatal sedation and/or neonatal withdrawal.
( 5.7 , 8.1 )
5.1Risk of Concomitant Use with Opioids Concomitant use of benzodiazepines, including VALTOCO, and opioids may result in profound sedation, respiratory depression, coma, and death [see Drug Interactions (7.1) ]. Because of these risks, reserve concomitant prescribing of benzodiazepines and opioids for patients for whom alternative treatment options are inadequate. Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioids alone.
If a decision is made to prescribe VALTOCO concomitantly with opioids, prescribe the lowest effective dosages and minimum durations of concomitant use, and follow patients closely for signs and symptoms of respiratory depression and sedation. Advise both patients and caregivers about the risks of respiratory depression and sedation when VALTOCO is used with opioids.
5.2Abuse, Misuse, and Addiction The use of benzodiazepines, including VALTOCO, exposes users to the risks of abuse, misuse, and addiction, which can lead to overdose or death. Abuse and misuse of benzodiazepines often (but not always) involve the use of doses greater than the maximum recommended dosage and commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes, including respiratory depression, overdose, or death [see Drug Abuse and Dependence (9.2) ] .
Before prescribing VALTOCO and throughout treatment, assess each patient's risk for abuse, misuse, and addiction. Use of VALTOCO, particularly in patients at elevated risk, necessitates counseling about the risks and proper use of VALTOCO along with monitoring for signs and symptoms of abuse, misuse, and addiction. Do not exceed the recommended dosing frequency; avoid or minimize concomitant use of CNS depressants and other substances associated with abuse, misuse, and addiction (e.g., opioid analgesics, stimulants); and advise patients on the proper disposal of unused drug.
If a substance use disorder is suspected, evaluate the patient and institute (or refer them for) early treatment, as appropriate.
5.3Dependence and Withdrawal Reactions After Use of VALTOCO More Frequently Than Recommended For patients using VALTOCO more frequently than recommended, to reduce the risk of withdrawal reactions, use a gradual taper to discontinue VALTOCO (a patient-specific plan should be used to taper the dose). Patients at an increased risk of withdrawal adverse reactions after benzodiazepine discontinuation or rapid dosage reduction include those who take higher dosages, and those who have had longer durations of use. Acute Withdrawal Reactions The continued use of benzodiazepines may lead to clinically significant physical dependence.
Although VALTOCO is indicated only for intermittent use [see Indications and Usage (1) and Dosage and Administration (2) ] , if used more frequently than recommended, abrupt discontinuation or rapid dosage reduction of VALTOCO, or administration of flumazenil (a benzodiazepine antagonist) may precipitate acute withdrawal reactions, which can be life-threatening (e.g., seizures) [see Drug Abuse and Dependence (9.3) ]. Protracted Withdrawal Syndrome In some cases, benzodiazepine users have developed a protracted withdrawal…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed elsewhere in the labeling: Risk of Concomitant Use with Opioids [see Warnings and Precautions (5.1) ] Abuse, Misuse, and Addiction [see Warnings and Precautions (5.2) ] Dependence and Withdrawal Reactions After Use of VALTOCO More Frequently Than Recommended [see Warnings and Precautions (5.3) ] CNS depression [see Warnings and Precautions (5.4) ] Suicidal Behavior and Ideation [see Warnings and Precautions (5.5) ] Glaucoma [see Warnings and Precautions (5.6) ] Neonatal Sedation and Withdrawal Syndrome [see Warnings and Precautions (5.7) ] Risk of Serious Adverse Reactions in Infants due to Benzyl Alcohol Preservative [see Warnings and Precautions (5.8) ].
The most common adverse reactions (at least 4%) were somnolence, headache, and nasal discomfort. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Neurelis, Inc. at 1-866-696-3873 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to the rates in the clinical studies of another drug and may not reflect the rates observed in practice. The safety of VALTOCO is supported by clinical trials using diazepam rectal gel, as well as open-label, repeat-dose studies of VALTOCO in healthy subjects and epilepsy patients. Diazepam Rectal Gel In studies previously conducted with diazepam rectal gel, adverse event data were collected from double-blind, placebo-controlled studies and open-label studies.
The majority of adverse events were mild to moderate in severity and transient in nature. Two patients who received diazepam rectal gel died seven to 15 weeks following treatment; neither of these deaths was deemed related to diazepam rectal gel. The most frequent adverse reactions (at least 4%) in the two double-blind, placebo-controlled studies were somnolence, headache, and diarrhea.
Adverse events were usually mild or moderate in intensity. Approximately 1.4% of the 573 patients who received diazepam rectal gel in clinical trials of epilepsy discontinued treatment because of an adverse event. The adverse reaction most frequently associated with discontinuation (occurring in three patients) was somnolence.
Other adverse reactions most commonly associated with discontinuation and occurring in two patients were hypoventilation and rash. Adverse reactions associated with discontinuation occurring in one patient were asthenia, hyperkinesia, incoordination, vasodilatation, and urticaria. In the two double-blind, placebo-controlled, parallel-group studies [see Clinical Studies (14) ] , the proportion of patients who discontinued treatment because of adverse events was 2% for the group treated with diazepam rectal gel, versus 2% for the placebo group.
In the diazepam rectal gel group, one patient discontinued because of rash and one patient discontinued because of lethargy. Table 4: Adverse Reactions That Occurred in Greater Than 1% Of Patients in Parallel-Group, Placebo-Controlled Trials with Diazepam Rectal Gel and More Common Than Placebo Adverse Reaction Diazepam Rectal Gel N=101 % Placebo N=104 % Somnolence 23 8 Headache 5 4 Diarrhea 4 <1 Ataxia 3 <1 Dizziness 3 2 Euphoria 3 0 Incoordination 3 0 Rash 3 0 Asthma 2 0 Vasodilation 2 0 VALTOCO (Diazepam Nasal Spray) Clinical studies of patients with epilepsy 2 years of age and older were conducted to support the safety and tolerability of VALTOCO for the treatment of acute repetitive seizures.
A total of 255 patients 2 years of age and older received VALTOCO, of whom 143 received VALTOCO for at least 1 year. Other than adverse reactions related to local nasal administration, the adverse reactions reported in these studies were similar to those seen in the efficacy trials of diazepam rectal gel. The most common local adverse reactions that occurred in at least 1% of VALTOCO-tr…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS CYP2C19 and CYP3A4 Inhibitors: Elimination of diazepam could be decreased with concurrent administration; therefore, adverse reactions with VALTOCO may be increased. ( 7.3 ) Inducers of CYP2C19 and CYP3A4 Inducers: Exposure of diazepam with concurrent administration may be decreased; therefore, efficacy with VALTOCO may be decreased. ( 7.3 )
7.1Effect of Concomitant Use of Benzodiazepines and Opioids The concomitant use of benzodiazepines and opioids increases the risk of respiratory depression because of actions at different receptor sites in the CNS that control respiration. Benzodiazepines interact at GABA- A sites, and opioids interact primarily at mu receptors. When benzodiazepines and opioids are combined, the potential for benzodiazepines to significantly worsen opioid-related respiratory depression exists [see Warnings and Precautions (5.1) ].
Limit dosage and duration of concomitant use of benzodiazepines and opioids, and follow patients closely for respiratory depression and sedation.
7.2CNS Depressants and Alcohol Coadministration of other CNS depressants (e.g., valproate) or consumption of alcohol may potentiate the CNS-depressant effects of diazepam [see Warnings and Precautions (5.4) ].
7.3Effect of Other Drugs on VALTOCO Metabolism Potential interactions may occur when diazepam is given concurrently with agents that affect CYP2C19 and CYP3A4 activity. Inhibitors of CYP2C19 and CYP3A4 Inhibitors of CYP2C19 (e.g., cimetidine, quinidine, and tranylcypromine) and CYP3A4 (e.g., ketoconazole, troleandomycin, and clotrimazole) could decrease the rate of diazepam elimination; therefore, adverse reactions to VALTOCO may be increased. Inducers of CYP2C19 and CYP3A4 Inducers of CYP2C19 (e.g., rifampin) and CYP3A4 (e.g., carbamazepine, phenytoin, dexamethasone, and phenobarbital) could increase the rate of diazepam elimination; therefore, efficacy of VALTOCO may be decreased.
7.4Effect of VALTOCO on the Metabolism of Other Drugs Diazepam is a substrate for CYP2C19 and CYP3A4; therefore, it is possible that VALTOCO may interfere with the metabolism of drugs which are substrates for CYP2C19 (e.g., omeprazole, propranolol, and imipramine) and CYP3A4 (e.g., cyclosporine, paclitaxel, theophylline, and warfarin) leading to a potential drug-drug interaction.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm. ( 8.1 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antiepileptic drugs (AEDs), such as VALTOCO, during pregnancy. Healthcare providers are encouraged to recommend that pregnant women who are taking VALTOCO during pregnancy enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org. Risk Summary Neonates born to mothers using benzodiazepines late in pregnancy have been reported to experience symptoms of sedation and/or neonatal withdrawal [see Warnings and Precautions (5.7) and Clinical Considerations ] .
Available data from published observational studies of pregnant women exposed to benzodiazepines do not report a clear association with benzodiazepines and major birth defects (see Human Data ) . In animal studies, administration of diazepam during the organogenesis period of pregnancy resulted in increased incidences of fetal malformations at doses greater than those used clinically. Data for diazepam and other benzodiazepines suggest the possibility of increased neuronal cell death and long-term effects on neurobehavioral and immunological function based on findings in animals following prenatal or early postnatal exposure at clinically relevant doses (see Animal Data ).
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Fetal/Neonatal Adverse Reactions Benzodiazepines cross the placenta and may produce respiratory depression, hypotonia, and sedation in neonates. Monitor neonates exposed to VALTOCO during pregnancy or labor for signs of sedation, respiratory depression, hypotonia, and feeding problems. Monitor neonates exposed to VALTOCO during pregnancy for signs of withdrawal.
Manage these neonates accordingly [see Warnings and Precautions (5.7) ] . Data Human Data Published data from observational studies on the use of benzodiazepines during pregnancy do not report a clear association with benzodiazepines and major birth defects. Although early studies reported an increased risk of congenital malformations with diazepam and chlordiazepoxide, there was no consistent pattern noted.
In addition, the majority of more recent case-control and cohort studies of benzodiazepine use during pregnancy, which were adjusted for confounding exposures to alcohol, tobacco, and other medications, have not confirmed these findings. Animal Data Diazepam has been shown to produce increased incidences of fetal malformations in mice and hamsters when given orally at single doses of 100 mg/kg or greater (approximately 13 times the maximum recommended human dose [MRHD = 0.6mg/kg/day] or greater on a mg/m 2 basis). Cleft palate and exencephaly are the most common and consistently reported malformations produced in these species by administration of high, maternally-toxic doses of diazepam during organogenesis.
In published animal studies, administration of benzodiazepines or other drugs that enhance GABAergic inhibition to neonatal rats has been reported to result in widespread apoptotic neurodegeneration in the developing brain at plasma concentrations relevant for seizure control in humans. The window of vulnerability to these changes in rats (postnatal days 0-14) includes a period of brain development that takes place during the third trimester of pregnancy in humans.
8.2Lactation Risk Summary Diazepam is excreted in human milk. There are reports of sedation, poor feeding, and poor weight gain in infants exposed to benzodiazepines through breast m…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antiepileptic drugs (AEDs), such as VALTOCO, during pregnancy. Healthcare providers are encouraged to recommend that pregnant women who are taking VALTOCO during pregnancy enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org. Risk Summary Neonates born to mothers using benzodiazepines late in pregnancy have been reported to experience symptoms of sedation and/or neonatal withdrawal [see Warnings and Precautions (5.7) and Clinical Considerations ] .
Available data from published observational studies of pregnant women exposed to benzodiazepines do not report a clear association with benzodiazepines and major birth defects (see Human Data ) . In animal studies, administration of diazepam during the organogenesis period of pregnancy resulted in increased incidences of fetal malformations at doses greater than those used clinically. Data for diazepam and other benzodiazepines suggest the possibility of increased neuronal cell death and long-term effects on neurobehavioral and immunological function based on findings in animals following prenatal or early postnatal exposure at clinically relevant doses (see Animal Data ).
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Fetal/Neonatal Adverse Reactions Benzodiazepines cross the placenta and may produce respiratory depression, hypotonia, and sedation in neonates. Monitor neonates exposed to VALTOCO during pregnancy or labor for signs of sedation, respiratory depression, hypotonia, and feeding problems. Monitor neonates exposed to VALTOCO during pregnancy for signs of withdrawal.
Manage these neonates accordingly [see Warnings and Precautions (5.7) ] . Data Human Data Published data from observational studies on the use of benzodiazepines during pregnancy do not report a clear association with benzodiazepines and major birth defects. Although early studies reported an increased risk of congenital malformations with diazepam and chlordiazepoxide, there was no consistent pattern noted.
In addition, the majority of more recent case-control and cohort studies of benzodiazepine use during pregnancy, which were adjusted for confounding exposures to alcohol, tobacco, and other medications, have not confirmed these findings. Animal Data Diazepam has been shown to produce increased incidences of fetal malformations in mice and hamsters when given orally at single doses of 100 mg/kg or greater (approximately 13 times the maximum recommended human dose [MRHD = 0.6mg/kg/day] or greater on a mg/m 2 basis). Cleft palate and exencephaly are the most common and consistently reported malformations produced in these species by administration of high, maternally-toxic doses of diazepam during organogenesis.
In published animal studies, administration of benzodiazepines or other drugs that enhance GABAergic inhibition to neonatal rats has been reported to result in widespread apoptotic neurodegeneration in the developing brain at plasma concentrations relevant for seizure control in humans. The window of vulnerability to these changes in rats (postnatal days 0-14) includes a period of brain development that takes place during the third trimester of pregnancy in humans.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of VALTOCO have been established in pediatric patients 2 years to 16 years of age. Use of VALTOCO in this age group is supported by evidence from adequate and well-controlled studies of diazepam rectal gel in adult and pediatric patients, adult bioavailability studies comparing VALTOCO with diazepam rectal gel, patient pharmacokinetic data, and open-label safety studies of VALTOCO including patients 2 years to 16 years of age [see Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , and Clinical Studies (14) ].
Safety and effectiveness of VALTOCO in pediatric patients below the age of 2 years have not been established. VALTOCO is not approved for use in neonates or infants. Prolonged CNS depression has been observed in neonates treated with diazepam.
Serious adverse reactions including fatal reactions and the "gasping syndrome" occurred in premature neonates and low-birth-weight infants in the neonatal intensive care unit who received drugs containing benzyl alcohol as a preservative. In these cases, benzyl alcohol dosages of 99 to 234 mg/kg/day produced high levels of benzyl alcohol and its metabolites in the blood and urine (blood levels of benzyl alcohol were 0.61 to 1.378 mmol/L). Additional adverse reactions included gradual neurological deterioration, seizures, intracranial hemorrhage, hematologic abnormalities, skin breakdown, hepatic and renal failure, hypotension, bradycardia, and cardiovascular collapse.
Preterm, low-birth-weight infants may be more likely to develop these reactions because they may be less able to metabolize benzyl alcohol. The minimum amount of benzyl alcohol at which serious adverse reactions may occur is not known (VALTOCO contains 10.5 mg of benzyl alcohol per 0.1 mL) [see Warnings and Precautions (5.8) ]
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of VALTOCO did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Therefore, in elderly patients, VALTOCO should be used with caution because of an increase in half-life with a corresponding decrease in the clearance of free diazepam [see Clinical Pharmacology (12.3) ] . It is also recommended that the dosage be decreased to reduce the likelihood of ataxia or oversedation.
🆘 Overdosage ▾
10 OVERDOSAGE Overdosage of benzodiazepines is characterized by central nervous system depression ranging from drowsiness to coma. In mild to moderate cases, symptoms can include drowsiness, confusion, dysarthria, lethargy, hypnotic state, diminished reflexes, ataxia, and hypotonia. Rarely, paradoxical or disinhibitory reactions (including agitation, irritability, impulsivity, violent behavior, confusion, restlessness, excitement, and talkativeness) may occur.
In severe overdosage cases, patients may develop respiratory depression and coma. Overdosage of benzodiazepines in combination with other CNS depressants (including alcohol and opioids) may be fatal [see Warnings and Precautions (5.2) ] . Markedly abnormal (lowered or elevated) blood pressure, heart rate, or respiratory rate raise the concern that additional drugs and/or alcohol are involved in the overdosage.
In managing benzodiazepine overdosage, employ general supportive measures, including intravenous fluids and airway maintenance. Flumazenil, a specific benzodiazepine receptor antagonist indicated for the complete or partial reversal of the sedative effects of benzodiazepines in the management of benzodiazepine overdosage, can lead to withdrawal and adverse reactions, including seizures, particularly in the context of mixed overdosage with drugs that increase seizure risk (e.g., tricyclic and tetracyclic antidepressants) and in patients with long-term benzodiazepine use and physical dependency.
The risk of withdrawal seizures with flumazenil use may be increased in patients with epilepsy. Flumazenil is contraindicated in patients who have received a benzodiazepine for control of a potentially life-threatening condition (e.g., status epilepticus). If the decision is made to use flumazenil, it should be used as an adjunct to, not as a substitute for, supportive management of benzodiazepine overdosage.
See the flumazenil injection Prescribing Information. Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdosage management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The exact mechanism of action for diazepam is not fully understood, but it is thought to involve potentiation of GABAergic neurotransmission resulting from binding at the benzodiazepine site of the GABA A receptor.
12.2Pharmacodynamics The effects of diazepam on the CNS are dependent on the dose administered, the route of administration, and the presence or absence of other medications.
12.3Pharmacokinetics Pharmacokinetic information for VALTOCO following nasal administration was obtained from studies conducted in healthy adult subjects, as well as adult and pediatric patients with epilepsy 2 years of age and older. Absorption In a pharmacokinetic study in healthy adult subjects, the highest plasma diazepam concentrations after nasal administration of VALTOCO was reached in 1.5 hours. The estimated volume of distribution of diazepam at steady-state is 0.8 to
1.0L/kg. The absolute bioavailability of VALTOCO relative to intravenous diazepam was 97%. The mean elimination half-life of diazepam following administration of a 10 mg dose of VALTOCO was found to be about 49.2 hours.
In another pharmacokinetic study in healthy adult subjects, diazepam plasma exposures (C max and AUC) increased approximately proportional to dose from 5 mg to 20 mg. In a relative bioavailability study in healthy adult subjects, diazepam exposure (C max and AUCs) was evaluated following administration of 15 and 20 mg of VALTOCO nasal spray and diazepam rectal gel. The diazepam PK parameters were 2 to 4-fold less variable for VALTOCO and within the range of those seen with diazepam rectal gel.
In a pharmacokinetic study in patients with epilepsy, pharmacokinetic parameters were similar between seizure versus non-seizure states. Distribution Both diazepam and its major active metabolite desmethyldiazepam bind extensively to plasma proteins (95-98%). Metabolism and Elimination In vitro studies using human liver preparations suggest that CYP2C19 and CYP3A4 are the principal isozymes involved in the initial oxidative metabolism of diazepam.
It has been reported in the literature that diazepam is extensively metabolized to one major active metabolite, desmethyldiazepam, and two minor active metabolites, 3- hydroxydiazepam (temazepam) and 3-hydroxy-N-diazepam (oxazepam), in plasma. At therapeutic doses, desmethyldiazepam is found in plasma at concentrations equivalent to those of diazepam while oxazepam and temazepam are not usually detectable. The metabolism of diazepam is primarily hepatic and involves demethylation (involving primarily CYP2C19 and CYP3A4) and 3-hydroxylation (involving primarily CYP3A4), followed by glucuronidation.
The marked inter-individual variability in the clearance of diazepam reported in the literature is probably attributable to variability of CYP2C19 (which is known to exhibit genetic polymorphism; about 3-5% of Caucasians have little or no activity and are "poor metabolizers") and CYP3A4. No inhibition was demonstrated in the presence of inhibitors selective for CYP2A6, CYP2C9, CYP2D6, CYP2E1, or CYP1A2, indicating that these enzymes are not significantly involved in metabolism of diazepam. Specific Populations Geriatric Patients A study of single dose IV administration of diazepam (0.1 mg/kg) indicates that the elimination half-life of diazepam increases linearly with age, ranging from about 15 hours at 18 years (healthy young adults) to about 100 hours at 95 years (healthy elderly) with a corresponding decrease in clearance of free diazepam [see Use in Specific Populations (8.5) ].
Pediatric Patients Literature review indicates that following IV administration (0.33 mg/kg), diazepam has a half-life in pediatric patients 6 to 12 years of age of approximately 15-21 hours. Based on simulation studies, in pediatric patients 2 to 5 years of age, median maximum plasma concentration (C max ) and median area under the plasma concentration curve (AUC 0-t ) of diazepam following a single…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The exact mechanism of action for diazepam is not fully understood, but it is thought to involve potentiation of GABAergic neurotransmission resulting from binding at the benzodiazepine site of the GABA A receptor.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
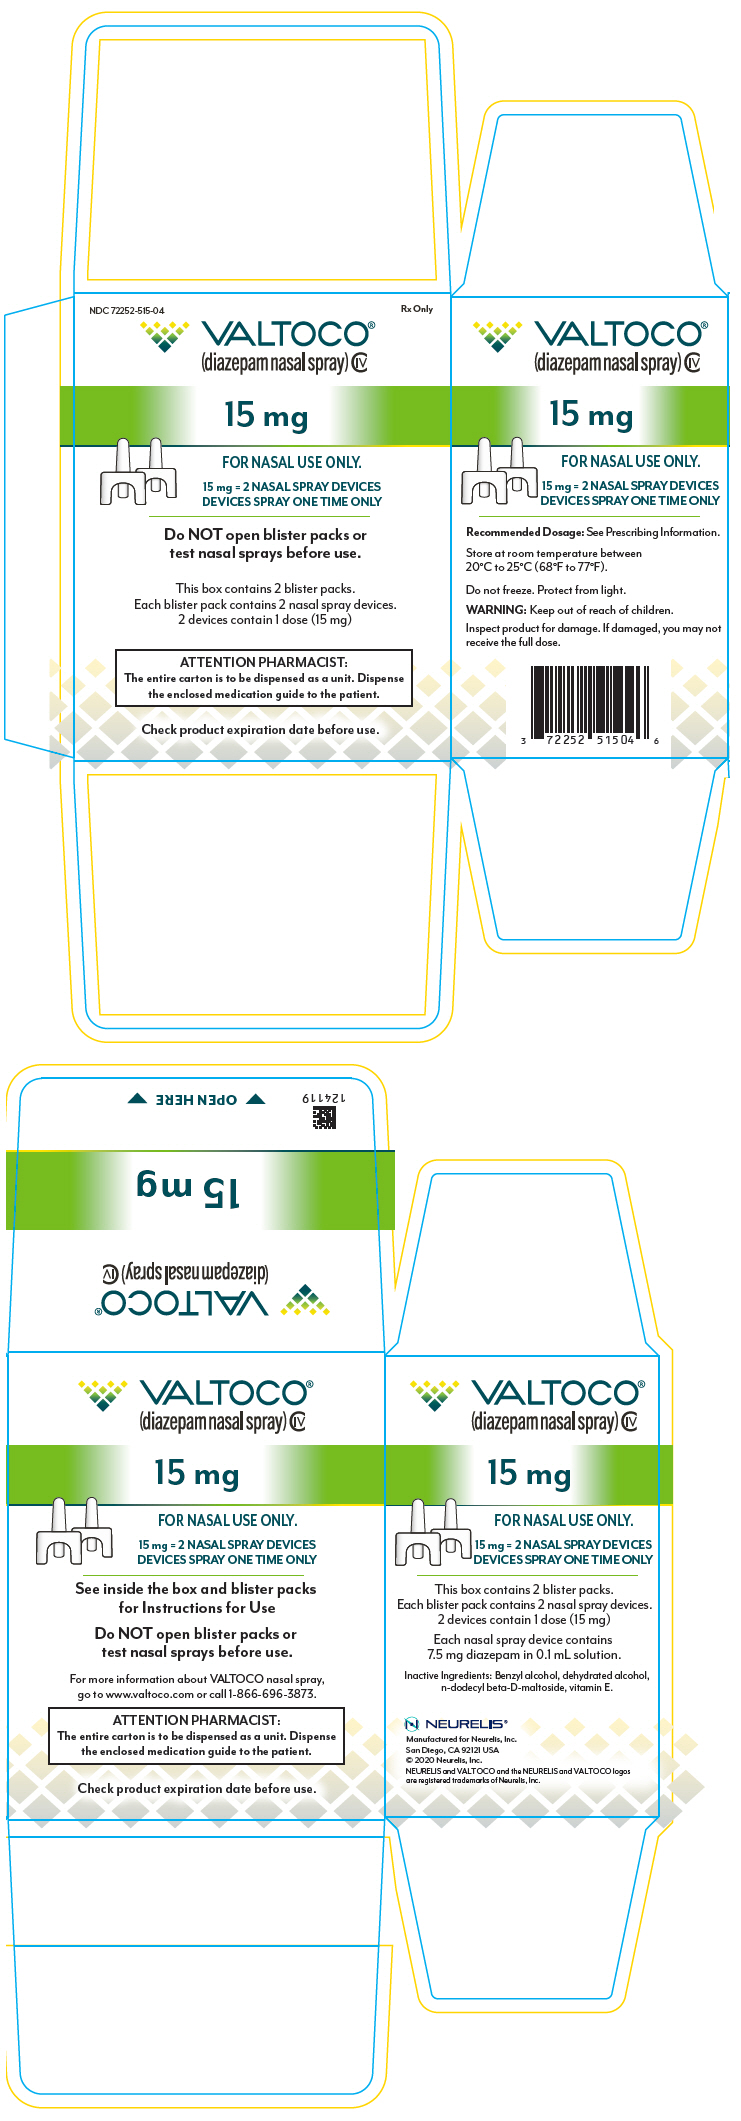
16.1How Supplied VALTOCO is available in 5 mg, 7.5 mg, and 10 mg strengths. VALTOCO is supplied and packaged in doses of 5 mg, 10 mg, 15 mg, or 20 mg (see Table 5 ). Table 5: Available Packaging Configurations Description Contents NDC Each Carton Contains 2 Doses 5 mg carton 2 individual blister packs, each containing one 5 mg nasal spray device 72252-505-02 10 mg carton 2 individual blister packs, each containing one 10 mg nasal spray device 72252-510-02 15 mg carton 2 individual blister packs, each containing two 7.5 mg nasal spray devices 72252-515-04 20 mg carton 2 individual blister packs, each containing two 10 mg nasal spray devices 72252-520-04 Each Carton Contains 5 Doses 5 mg carton 5 individual blister packs, each containing one 5 mg nasal spray device 72252-505-05 10 mg carton 5 individual blister packs, each containing one 10 mg nasal spray device 72252-510-05 15 mg carton 5 individual blister packs, each containing two 7.5 mg nasal spray devices 72252-515-10 20 mg carton 5 individual blister packs, each containing two 10 mg nasal spray devices 72252-520-10
16.2Storage and Handling Do not open individual blister packs or test nasal spray devices before use. Each single-dose nasal spray device sprays one (1) time and cannot be re-used. Do not use if the nasal spray unit appears damaged. Store VALTOCO at 20°C to 25°C (68°F to 77°F); excursions permitted from 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Do not freeze. Protect from light.
📦 Storage and Handling ▾
16.2Storage and Handling Do not open individual blister packs or test nasal spray devices before use. Each single-dose nasal spray device sprays one (1) time and cannot be re-used. Do not use if the nasal spray unit appears damaged. Store VALTOCO at 20°C to 25°C (68°F to 77°F); excursions permitted from 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Do not freeze. Protect from light.
📋 Description ▾
11 DESCRIPTION Diazepam, the active ingredient of VALTOCO nasal spray, is a benzodiazepine anticonvulsant with the chemical name 7-chloro-1,3-dihydro-1-methyl-5-phenyl-2H-1,4-benzodiazepin-2-one; its molecular formula is C 16 H 13 ClN 2 O and its molecular weight is 284.7 g/mol. The structural formula is as follows: The inactive ingredients in VALTOCO nasal spray include benzyl alcohol (10.5 mg per 0.1 mL), dehydrated alcohol, n-dodecyl beta-D-maltoside, and vitamin E. VALTOCO nasal spray is a clear pale amber liquid.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient and/or caregiver to read the FDA-approved patient labeling (Medication Guide and Instructions for Use) . Concomitant use with Opioids Concomitant use of benzodiazepines, including VALTOCO, and opioids may result in profound sedation, respiratory depression, coma, and death. Do not use such drugs concomitantly unless supervised by a health care provider [see Warnings and Precautions (5.1) ] .
Abuse, Misuse, and Addiction Inform patients that the use of VALTOCO more frequently than recommended, even at recommended dosages, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose and death, especially when used in combination with other medications (e.g., opioid analgesics), alcohol, and/or illicit substances. Inform patients about the signs and symptoms of benzodiazepine abuse, misuse, and addiction; to seek medical help if they develop these signs and/or symptoms; and on the proper disposal of unused drug [see Warnings and Precautions (5.2) and Drug Abuse and Dependence (9.2) ].
Withdrawal Reactions Inform patients that use of VALTOCO more frequently than recommended may lead to clinically significant physical dependence and that abrupt discontinuation or rapid dosage reduction of VALTOCO may precipitate acute withdrawal reactions, which can be life-threatening. Inform patients that in some cases, patients taking benzodiazepines have developed a protracted withdrawal syndrome with withdrawal symptoms lasting weeks to more than 12 months [see Warnings and Precautions (5.3) and Drug Abuse and Dependence (9.3) ].
Important Treatment Instructions Instruct patients and caregivers on what is and is not an intermittent and stereotypic episode of increased seizure activity (i.e., seizure cluster) that is appropriate for treatment, and the timing of administration in relation to the onset of the episode. Instruct patients and caregivers on what to observe following administration, and what would constitute an outcome requiring immediate medical attention. Instruct patients and caregivers not to administer a second dose of VALTOCO if they are concerned by the patient's breathing, the patient requires emergency rescue treatment with assisted breathing or intubation, or there is excessive sedation [see Use in Specific Populations (8.6) ].
Advise patients and caregivers on how frequently they can treat successive seizure cluster episodes over time. Pregnancy Advise pregnant females that the use of VALTOCO late in pregnancy can result in sedation (respiratory depression, lethargy, hypotonia) and/or withdrawal symptoms (hyperreflexia, irritability, restlessness, tremors, inconsolable crying, and feeding difficulties) in newborns [see Warnings and Precautions (5.7) and Use in Specific Populations (8.1) ] . Instruct patients to inform their healthcare provider if they are pregnant.
Encourage patients to enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry if they become pregnant while taking VALTOCO. The registry is collecting information about the safety of antiepileptic drugs during pregnancy [see Use in Specific Populations (8.1) ] . Lactation Counsel patients that diazepam, the active ingredient in VALTOCO, is excreted in breast milk.
Instruct patients to inform their healthcare provider if they are breastfeeding or intend to breastfeed. Instruct breastfeeding patients who take VALTOCO to monitor their infants for excessive sedation, poor feeding and poor weight gain, and to seek medical attention if they notice these signs [see Use in Specific Populations (8.2) ].
💬 Medication Guide ▾
MEDICATION GUIDE VALTOCO ® (val-toe-koe) (diazepam nasal spray), CIV This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: 04/2025 US-PRC-25-00100-v1 What is the most important information I should know about VALTOCO?
VALTOCO is a benzodiazepine medicine. Taking benzodiazepines with opioid medicines, alcohol, or other central nervous system (CNS) depressants (including street drugs) can cause severe drowsiness, breathing problems (respiratory depression), coma, and death. Get emergency medical help right away if any of the following happens: shallow or slowed breathing breathing stops (which may lead to the heart stopping) excessive sleepiness (sedation) Do not drive or operate heavy machinery until you know how taking VALTOCO with opioids affects you.
Risk of abuse, misuse, and addiction. There is a risk for abuse, misuse, and addiction with benzodiazepines, including VALTOCO, which can lead to overdose and serious side effects including coma and death. Serious side effects including coma and death have happened in people who have abused or misused benzodiazepines, including diazepam (the active ingredient in VALTOCO).
These serious side effects may also include delirium, paranoia, suicidal thoughts or actions, seizures, and difficulty breathing. Call your healthcare provider or go to the nearest hospital emergency room right away if you get any of these serious side effects. You can develop an addiction even if you use VALTOCO as prescribed by your healthcare provider.
Use VALTOCO exactly as your healthcare provider prescribed. Do not share your VALTOCO with other people. Keep VALTOCO in a safe place and away from children.
Physical dependence and withdrawal reactions . Benzodiazepines, including VALTOCO, can cause physical dependence and withdrawal reactions, especially if you use VALTOCO daily. VALTOCO is not intended for daily use.
Do not suddenly stop using VALTOCO without talking to your healthcare provider. Stopping VALTOCO suddenly can cause serious and life-threatening side effects, including, unusual movements, responses, or expressions, seizures, sudden and severe mental or nervous system changes, depression, seeing or hearing things that others do not see or hear, an extreme increase in activity or talking, losing touch with reality, and suicidal thoughts or actions. Call your healthcare provider or go to the nearest hospital emergency room right away if you get any of these symptoms.
Some people who suddenly stop benzodiazepines have symptoms that can last for several weeks to more than 12 months , including, anxiety, trouble remembering, learning, or concentrating, depression, problems sleeping, feeling like insects are crawling under your skin, weakness, shaking, muscle twitching, burning or prickling feeling in your hands, arms, legs or feet, and ringing in your ears. Physical dependence is not the same as drug addiction. Your healthcare provider can tell you more about the differences between physical dependence and drug addiction.
Do not use more VALTOCO than prescribed or use VALTOCO more often than prescribed. VALTOCO can make you sleepy or dizzy and can slow your thinking and motor skills. Do not drive, operate heavy machinery, or do other dangerous activities until you know how VALTOCO affects you.
Do not drink alcohol or take other drugs that may make you sleepy or dizzy while using VALTOCO without first talking to your healthcare provider. When taken with alcohol or drugs that cause sleepiness or dizziness, VALTOCO may make your sleepiness or dizziness worse. Like other antiepileptic medicines, VALTOCO may cause suicidal thoughts or actions in a small number of people, about 1 in 500.
Call your healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you : thoughts about suicide or dying feeling agitated or restless acting aggressive, being angry, or violent attempts to commit suicide panic attacks acting on dange…