
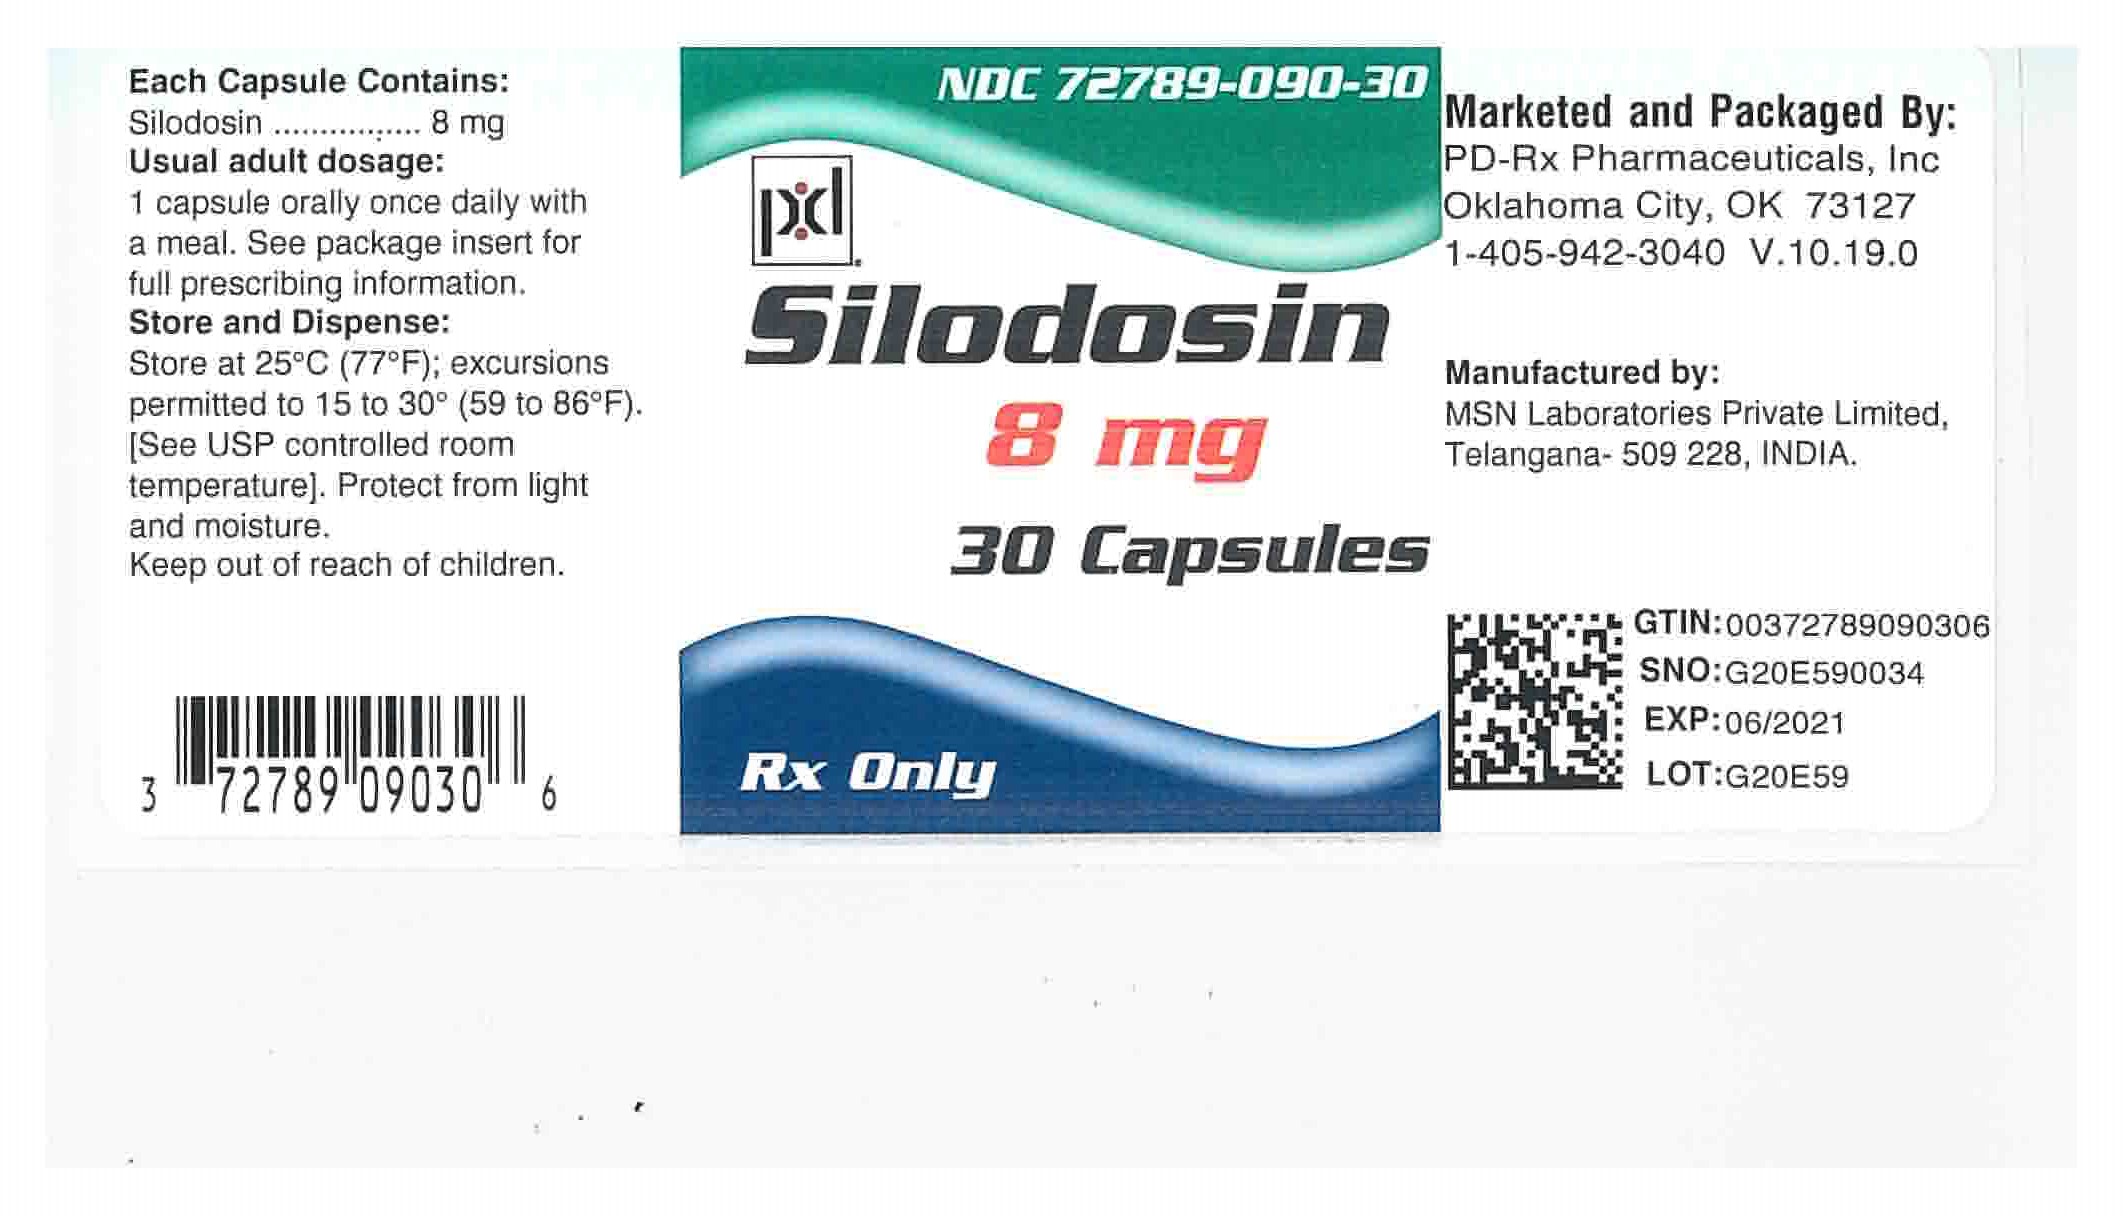
Silodosin 8 mg Capsule, 30-count — NDC 72789-090-30 (Billing 72789-0090-30)
This is a package of 30 capsules of Silodosin 8 mg Capsule from PD-Rx Pharmaceuticals, Inc., marketed since Dec 2018 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
Other active recalls for Silodosin (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 064847
- GCN: 16858
- GPI-14 (Medi-Span): 56852060000140
- HICL (First Databank): 036119
- AHFS class code: 12:16.04.12
- RxCUI (RxNorm): 809477
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the alpha-Adrenergic Blocker class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Silodosin is used to treat benign prostatic hyperplasia (BPH; enlarged prostate that can cause difficulty urinating, painful urination or increased urinary frequency or urgency). Silodosin is in a class of medications called alpha-blockers. It works by relaxing the muscles in the prostate and bladder so that urine can flow easily.
Read the full MedlinePlus article ↗- It treats the symptoms of an enlarged prostate (BPH), such as poor urine flow. It relaxes muscle in the prostate and bladder area. It is not a blood pressure medicine.
- Take one capsule once a day with a meal. If swallowing is hard, you can sprinkle the powder from an opened capsule on a spoonful of applesauce, swallow it right away, and follow wi...
- The most common is retrograde ejaculation, where semen goes backward, which goes away after stopping. Dizziness, diarrhea, headache and a stuffy nose can also happen. Stand up slow...
- Call if you faint, feel very dizzy, have swelling of the tongue or throat, a serious rash, or yellowing of your skin or eyes. Get help right away for an erection that will not go a...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Silodosin — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.7600 | $22.80 / 30 capsules |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 72789-0090-30 You're viewing this Main listing | 30 CAPSULE in 1 BOTTLE, PLASTIC | 2020-06-23 | — | Active |
| 72789-0090-90 72789-090-90 | 90 CAPSULE in 1 BOTTLE, PLASTIC | 2020-06-23 | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 72789-0090-90?
What NDC number is used to bill for this package of Silodosin 8 mg Capsule?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Silodosin 8 mg 27241-0145-01 | Ajanta | 30 capsules | $0.319 | AB | Availability likely | — |
| Silodosin 8 mg 31722-0636-30 | Camber | 30 capsules | $0.319 | AB | Availability likely | — |
| Silodosin 8 mg 33342-0385-07 | Macleods | 30 capsules | $0.319 | AB | Availability likely | — |
| Silodosin 8 mg 59651-0096-30 | Aurobindo | 30 capsules | $0.319 | AB | Availability likely | — |
| Silodosin 8 mg 69238-1420-03 | Amneal | 30 capsules | $0.319 | AB | Availability likely | — |
| Silodosin 8 mg 72205-0010-30 | Novadoz | 30 capsules | $0.319 | AB | Availability likely | — |
| Silodosin 8 mg 42291-0778-90 | AvKARE | 90 capsules | — | AB | FDA listed | — |
| Silodosin 8 mg 46708-0406-30 | Alembic | 30 capsules | — | — | FDA listed | — |
| Silodosin 8 mg 60219-1420-03 | Amneal | 30 capsules | — | AB | FDA listed | — |
| Silodosin 8 mg 62332-0406-30 | Alembic | 30 capsules | — | — | FDA listed | — |
| Silodosin 8 mg 68180-0741-02 | Lupin | 500 capsules | — | AB | FDA listed | — |
| Silodosin 8 mg 71335-3128-01 | Bryant | 30 capsules | — | AB | FDA listed | — |
| Silodosin 8 mg 72162-2447-03 | Bryant | 30 capsules | — | AB | FDA listed | — |
| Silodosin 8 mgthis 72789-0090-30 | PD-Rx | 30 capsules | — | AB | FDA listed | — |
| Silodosin 8 mg 82619-0114-01 | Creekwood | 30 capsules | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 7LVU907546
A silicate mineral compound that acts as an anti-caking agent and absorbent in tablets and powders. It helps prevent clumping, improve flow during manufacturing, and stabilize moisture content in the final product.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII MB5IUD6JUA
Shellac is a natural resin secreted by lac beetles, purified and processed into a coating material. It seals and protects tablets and capsules, controls how quickly the medicine dissolves, and gives pills their glossy finish.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Silodosin capsule, a selective alpha-1 adrenergic receptor antagonist, is indicated for the treatment of the signs and symptoms of benign prostatic hyperplasia (BPH) [see CLINICAL STUDIES (14) ]. Silodosin capsule is not indicated for the treatment of hypertension. Silodosin capsule, an alpha-1 adrenergic receptor antagonist, is indicated for the treatment of the signs and symptoms of benign prostatic hyperplasia (BPH).
Silodosin capsule is not indicated for the treatment of hypertension. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION 8 mg capsules taken orally once daily with a meal. ( 2.1 ) 4 mg capsules taken orally once daily with a meal for those with moderate renal impairment [Creatinine Clearance (CCr) 30 to 50 mL/min]. ( 2.2 )
2.1Dosing Information The recommended dose is 8 mg orally once daily with a meal. Patients who have difficulty swallowing pills and capsules may carefully open the silodosin capsule and sprinkle the powder inside on a tablespoonful of applesauce. The applesauce should be swallowed immediately (within 5 minutes) without chewing and followed with an 8 oz glass of cool water to ensure complete swallowing of the powder.
The applesauce used should not be hot, and it should be soft enough to be swallowed without chewing. Any powder/applesauce mixture should be used immediately (within 5 minutes) and not stored for future use. Subdividing the contents of a silodosin capsule is not recommended [see CLINICAL PHARMACOLOGY (12.3) ].
2.2Dosage Adjustment in Special Populations Renal impairment: Silodosin capsule is contraindicated in patients with severe renal impairment (CCr < 30 mL/min). In patients with moderate renal impairment (CCr 30 to 50 mL/min), the dose should be reduced to 4 mg once daily taken with a meal. No dosage adjustment is needed in patients with mild renal impairment (CCr 50 to 80 mL/min) [ see CONTRAINDICATIONS (4) , WARNINGS AND PRECAUTIONS (5.2) , USE IN SPECIFIC POPULATIONS (8.6) and CLINICAL PHARMACOLOGY (12.3) ].
Hepatic impairment: Silodosin capsules has not been studied in patients with severe hepatic impairment (Child-Pugh score ≥ 10) and is therefore contraindicated in these patients. No dosage adjustment is needed in patients with mild or moderate hepatic impairment [ see CONTRAINDICATIONS (4) , WARNINGS AND PRECAUTIONS (5.3) , USE IN SPECIFIC POPULATIONS (8.7) and CLINICAL PHARMACOLOGY (12.3) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS The 8 mg capsules are white to off white colored powder filled in size “1” hard gelatin capsules with white opaque body imprinted with “8 mg” and white opaque cap imprinted “S” with black ink. The 4 mg capsules are white to off white colored powder filled in size “3” hard gelatin capsules with white opaque body imprinted with “4 mg” and white opaque cap imprinted “S” with black ink. Capsules: 8 mg and 4 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Severe renal impairment (CCr < 30 mL/min) Severe hepatic impairment (Child-Pugh score ≥ 10) Concomitant administration with strong Cytochrome P450 3A4 (CYP3A4) inhibitors (e.g., ketoconazole, clarithromycin, itraconazole, ritonavir) [see DRUG INTERACTIONS (7.1) ] Patients with a history of hypersensitivity to silodosin or any of the ingredients of silodosin [see ADVERSE REACTIONS (6.2) and DESCRIPTION (11) ] Patients with severe renal impairment [Creatinine Clearance (CCr < 30 mL/min)]. ( 4 ) Patients with severe hepatic impairment (Child-Pugh score > 10).
( 4 ) Concomitant administration with strong Cytochrome P450 3A4 (CYP3A4) inhibitors (e.g., ketoconazole, clarithromycin, itraconazole, ritonavir). ( 4 ) Patients with a history of hypersensitivity to silodosin or any of the ingredients of silodosin.( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Postural hypotension, with or without symptoms (e.g., dizziness), may develop when beginning silodosin treatment.( 5.1 ) In patients with moderate renal impairment, silodosin dose should be reduced to 4 mg once daily.( 5.2 ) Silodosin should not be used in combination with other alpha-blockers.( 5.5 ) Examine patients thought to have BPH prior to starting therapy with silodosin to rule out the presence of carcinoma of the prostate.( 5.6 ) Inform patients planning cataract surgery to notify their ophthalmologist that they are taking silodosin because of the possibility of Intraoperative Floppy Iris Syndrome (IFIS).
( 5.7 )
5.1Orthostatic Effects Postural hypotension, with or without symptoms (e.g., dizziness) may develop when beginning silodosin treatment. As with other alpha-blockers, there is potential for syncope. Patients should be cautioned about driving, operating machinery, or performing hazardous tasks when initiating therapy [see ADVERSE REACTIONS (6) , USE IN SPECIFIC POPULATIONS (8.5) , CLINICAL PHARMACOLOGY (12.2) , and PATIENT COUNSELING INFORMATION (17) ].
5.2Renal Impairment In a clinical pharmacology study, plasma concentrations (AUC and C max ) of silodosin were approximately three times higher in subjects with moderate renal impairment compared with subjects with normal renal function, while half-lives of silodosin doubled in duration. The dose of silodosin should be reduced to 4 mg in patients with moderate renal impairment. Exercise caution and monitor such patients for adverse events [see USE IN SPECIFIC POPULATIONS (8.6) and CLINICAL PHARMACOLOGY (12.3) ].
Silodosin is contraindicated in patients with severe renal impairment [see CONTRAINDICATIONS (4) ].
5.3Hepatic Impairment Silodosin has not been tested in patients with severe hepatic impairment, and therefore, should not be prescribed to such patients [see CONTRAINDICATIONS (4) , USE IN SPECIFIC POPULATIONS (8.7) and CLINICAL PHARMACOLOGY (12.3) ].
5.4Pharmacokinetic Drug-Drug Interactions In a drug interaction study, co-administration of a single 8 mg dose of silodosin with 400 mg ketoconazole, a strong CYP3A4 inhibitor, caused a 3.8-fold increase in maximum plasma silodosin concentrations and 3.2-fold increase in silodosin exposure (i.e., AUC). Concomitant use of ketoconazole or other strong CYP3A4 inhibitors (e.g., itraconazole, clarithromycin, ritonavir) is therefore contraindicated [see DRUG INTERACTIONS (7.1) ].
5.5Pharmacodynamic Drug-Drug Interactions The pharmacodynamic interactions between silodosin and other alpha-blockers have not been determined. However, interactions may be expected, and silodosin should not be used in combination with other alpha-blockers [see DRUG INTERACTIONS (7.3) ]. A specific pharmacodynamic interaction study between silodosin and antihypertensive agents has not been performed.
However, patients in the Phase 3 clinical studies taking concomitant antihypertensive medications with silodosin did not experience a significant increase in the incidence of syncope, dizziness, or orthostasis. Nevertheless, exercise caution during concomitant use with antihypertensives and monitor patients for possible adverse events [see ADVERSE REACTIONS (6.1) and DRUG INTERACTIONS (7.6) ]. Caution is also advised when alpha-adrenergic blocking agents including silodosin are co-administered with PDE5 inhibitors.
Alpha-adrenergic blockers and PDE5 inhibitors are both vasodilators that can lower blood pressure. Concomitant use of these two drug classes can potentially cause symptomatic hypotension [see DRUG INTERACTIONS (7.5) ].
5.6Carcinoma of the Prostate Carcinoma of the prostate and BPH cause many of the same symptoms. These two diseases frequently co-exist. Therefore, patients thought to have BPH should be examined prior to starting therapy with silodosin to rule out the presence of carcinoma of the prostate.
5.7Intraoperative Floppy Iris Syndrome Intraoperative Floppy Iris Syndrome has been observed dur… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (incidence > 2%) are retrograde ejaculation, dizziness, diarrhea, orthostatic hypotension, headache, nasopharyngitis, and nasal congestion. ( 6) To report SUSPECTED ADVERSE REACTIONS, contact Novadoz Pharmaceuticals LLC at 1-855-668-2369 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. In U.S. clinical trials, 897 patients with BPH were exposed to 8 mg silodosin daily. This includes 486 patients exposed for 6 months and 168 patients exposed for 1 year.
The population was 44 to 87 years of age, and predominantly Caucasian. Of these patients, 42.8% were 65 years of age or older and 10.7% were 75 years of age or older. In double-blind, placebo controlled, 12-week clinical trials, 466 patients were administered silodosin and 457 patients were administered placebo.
At least one treatment-emergent adverse reaction was reported by 55.2% of silodosin treated patients (36.8% for placebo treated). The majority (72.1%) of adverse reactions for the silodosin treated patients (59.8% for placebo treated) were qualified by the investigator as mild. A total of 6.4% of silodosin treated patients (2.2% for placebo treated) discontinued therapy due to an adverse reaction (treatment-emergent), the most common reaction being retrograde ejaculation (2.8%) for silodosin treated patients.
Retrograde ejaculation is reversible upon discontinuation of treatment. Adverse Reactions observed in at least 2% of patients: The incidence of treatment-emergent adverse reactions listed in the following table were derived from two 12-week, multicenter, double-blind, placebo-controlled clinical studies of silodosin 8 mg daily in BPH patients. Adverse reactions that occurred in at least 2% of patients treated with silodosin and more frequently than with placebo are shown in Table 1.
Table 1 Adverse Reactions Occurring in ≥ 2% of Patients in 12-week, Placebo-Controlled Clinical Trials Adverse Reactions Silodosin N = 466 n (%) Placebo N = 457 n (%) Retrograde Ejaculation 131 (28.1) 4 (0.9) Dizziness 15 (3.2) 5 (1.1) Diarrhea 12 (2.6) 6 (1.3) Orthostatic Hypotension 12 (2.6) 7 (1.5) Headache 11 (2.4) 4 (0.9) Nasopharyngitis 11 (2.4) 10 (2.2) Nasal Congestion 10 (2.1) 1 (0.2) In the two 12-week, placebo-controlled clinical trials, the following adverse events were reported by between 1% and 2% of patients receiving silodosin and occurred more frequently than with placebo: insomnia, PSA increased, sinusitis, abdominal pain, asthenia, and rhinorrhea.
One case of syncope in a patient taking prazosin concomitantly and one case of priapism were reported in the silodosin treatment group. In a 9-month open-label safety study of silodosin, one case of Intraoperative Floppy Iris Syndrome (IFIS) was reported.
6.2Postmarketing Experience The following adverse reactions have been identified during post approval use of silodosin. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure: Skin and subcutaneous tissue disorders: toxic skin eruption, purpura, skin rash, pruritus, and urticaria Hepatobiliary disorders: jaundice, impaired hepatic function associated with increased transaminase values Immune system disorders: allergic-type reactions, not limited to skin reactions including swollen tongue and pharyngeal edema resulting in serious outcomes
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Strong P-glycoprotein inhibitors (e.g., cyclosporine): Co-administration may increase plasma silodosin concentration. Concomitant use is not recommended. ( 7.2 ) Alpha-blockers: Interactions involving concomitant use have not been determined.
However, interactions are expected and concomitant use is not recommended. ( 7.3 ) Concomitant use of PDE5 inhibitors with alpha-blockers including silodosin can potentially cause symptomatic hypotension. ( 5.5 ) ( 7.5 )
7.1Moderate and Strong CYP3A4 Inhibitors In a clinical metabolic inhibition study, a 3.8-fold increase in silodosin maximum plasma concentrations and 3.2-fold increase in silodosin exposure were observed with concurrent administration of a strong CYP3A4 inhibitor, 400 mg ketoconazole. Use of strong CYP3A4 inhibitors such as itraconazole or ritonavir may cause plasma concentrations of silodosin to increase. Concomitant administration of strong CYP3A4 inhibitors and silodosin is contraindicated [see CONTRAINDICATIONS (4) , WARNINGS AND PRECAUTIONS (5.4) and CLINICAL PHARMACOLOGY (12.3) ].
The effect of moderate CYP3A4 inhibitors on the pharmacokinetics of silodosin has not been evaluated. Concomitant administration with moderate CYP3A4 inhibitors (e.g., diltiazem, erythromycin, verapamil) may increase concentration of silodosin. Exercise caution and monitor patients for adverse events when co-administering silodosin with moderate CYP3A4 inhibitors.
7.2Strong P-glycoprotein (P-gp) Inhibitors In vitro studies indicated that silodosin is a P-gp substrate. Ketoconazole, a CYP3A4 inhibitor that also inhibits P-gp, caused significant increase in exposure to silodosin. Inhibition of P-gp may lead to increased silodosin concentration. Silodosin is therefore not recommended in patients taking strong P-gp inhibitors such as cyclosporine [see CLINICAL PHARMACOLOGY (12.3) ].
7.3Alpha-Blockers The pharmacodynamic interactions between silodosin and other alpha-blockers have not been determined. However, interactions may be expected, and silodosin should not be used in combination with other alpha-blockers [see WARNINGS AND PRECAUTIONS (5.5) ].
7.4Digoxin The effect of co-administration of silodosin and digoxin 0.25 mg/day for 7 days was evaluated in a clinical trial in 16 healthy males, aged 18 to 45 years. Concomitant administration of silodosin and digoxin did not significantly alter the steady state pharmacokinetics of digoxin. No dose adjustment is required.
7.5PDE5 Inhibitors Co-administration of silodosin with a single dose of 100 mg sildenafil or 20 mg tadalafil was evaluated in a placebo-controlled clinical study that included 24 healthy male subjects, 45 to 78 years of age. Orthostatic vital signs were monitored in the 12-hour period following concomitant dosing. During this period, the total number of positive orthostatic test results was greater in the group receiving silodosin plus a PDE5 inhibitor compared with silodosin alone.
No events of symptomatic orthostasis or dizziness were reported in subjects receiving silodosin with a PDE5 inhibitor.
7.6Other Concomitant Drug Therapy Antihypertensives The pharmacodynamic interactions between silodosin and antihypertensives have not been rigorously investigated in a clinical study. However, approximately one-third of the patients in clinical studies used concomitant antihypertensive medications with silodosin. The incidence of dizziness and orthostatic hypotension in these patients was higher than in the general silodosin population (4.6% versus 3.8% and 3.4% versus 3.2%, respectively).
Exercise caution during concomitant use with antihypertensives and monitor patients for possible adverse events [see WARNINGS AND PRECAUTIONS (5.5) ]. Metabolic Interactions In vitro data indicate that silodosin does not have the potential to inhibit or induce cytochrome P450 enzyme systems.
7.7Food Interactions The effect of a moderate fat, moderate calorie meal on silodosin pharmacokinetics was variable and decreased sil… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Renal impairment: Dose adjustment in moderate disease ( 2.2 ). Contraindicated in severe renal disease. ( 4 ) Hepatic impairment: Contraindicated in severe disease. ( 4 )
8.1Pregnancy Risk Summary Silodosin is not indicated for use in females.
8.2Lactation Silodosin is not indicated for use in females.
8.3Females and Males of Reproductive Potential Infertility Males Possible effects on male fertility could be observed based on findings in rats at exposures that were at least two times higher than at the MRHD (based on AUC). These findings may be reversible, and the clinical relevance is unknown [see NONCLINICAL TOXICOLOGY (13.1) ].
8.4Pediatric Use Silodosin is not indicated for use in pediatric patients. Safety and effectiveness in pediatric patients have not been established.
8.5Geriatric Use In double-blind, placebo-controlled, 12-week clinical studies of silodosin, 259 (55.6%) were under 65 years of age, 207 (44.4%) patients were 65 years of age and over, while 60 (12.9%) patients were 75 years of age and over. Orthostatic hypotension was reported in 2.3% of silodosin patients < 65 years of age (1.2% for placebo), 2.9% of silodosin patients ≥ 65 years of age (1.9% for placebo), and 5.0% of patients ≥ 75 years of age (0% for placebo). There were otherwise no significant differences in safety or effectiveness between older and younger patients [see CLINICAL PHARMACOLOGY (12.3) ].
8.6Renal Impairment The effect of renal impairment on silodosin pharmacokinetics was evaluated in a single dose study of six male patients with moderate renal impairment and seven male subjects with normal renal function. Plasma concentrations of silodosin were approximately three times higher in subjects with moderate renal impairment compared with subjects with normal renal function. Silodosin should be reduced to 4 mg per day in patients with moderate renal impairment.
Exercise caution and monitor patients for adverse events. Silodosin has not been studied in patients with severe renal impairment. Silodosin is contraindicated in patients with severe renal impairment [see CONTRAINDICATIONS (4) , WARNINGS AND PRECAUTIONS (5.2) and CLINICAL PHARMACOLOGY (12.3) ].
8.7Hepatic Impairment In a study comparing nine male patients with moderate hepatic impairment (Child-Pugh scores 7 to 9), to nine healthy male subjects, the single dose pharmacokinetics of silodosin were not significantly altered in patients with hepatic impairment. No dosing adjustment is required in patients with mild or moderate hepatic impairment. Silodosin has not been studied in patients with severe hepatic impairment.
Silodosin is contraindicated in patients with severe hepatic impairment [see CONTRAINDICATIONS (4) , WARNINGS AND PRECAUTIONS (5.3) and CLINICAL PHARMACOLOGY (12.3) ].
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Silodosin is not indicated for use in females.
🧒 Pediatric Use ▾
8.4Pediatric Use Silodosin is not indicated for use in pediatric patients. Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use In double-blind, placebo-controlled, 12-week clinical studies of silodosin, 259 (55.6%) were under 65 years of age, 207 (44.4%) patients were 65 years of age and over, while 60 (12.9%) patients were 75 years of age and over. Orthostatic hypotension was reported in 2.3% of silodosin patients < 65 years of age (1.2% for placebo), 2.9% of silodosin patients ≥ 65 years of age (1.9% for placebo), and 5.0% of patients ≥ 75 years of age (0% for placebo). There were otherwise no significant differences in safety or effectiveness between older and younger patients [see CLINICAL PHARMACOLOGY (12.3) ].
🆘 Overdosage ▾
10 OVERDOSAGE Silodosin was evaluated at doses of up to 48 mg/day in healthy male subjects. The dose-limiting adverse event was postural hypotension. Should overdose of silodosin lead to hypotension, support of the cardiovascular system is of first importance.
Restoration of blood pressure and normalization of heart rate may be accomplished by maintaining the patient in the supine position. If this measure is inadequate, administration of intravenous fluid should be considered. If necessary, vasopressors could be used, and renal function should be monitored and supported as needed.
Dialysis is unlikely to be of significant benefit since silodosin is highly (97%) protein bound.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Silodosin is a selective antagonist of post-synaptic alpha-1 adrenoreceptors, which are located in the human prostate, bladder base, bladder neck, prostatic capsule, and prostatic urethra. Blockade of these alpha-1 adrenoreceptors can cause smooth muscle in these tissues to relax, resulting in an improvement in urine flow and a reduction in BPH symptoms. An in vitro study examining binding affinity of silodosin to the three subtypes of the alpha-1 adrenoreceptors (alpha-1A, alpha-1B, and alpha-1D) was conducted.
The results of the study demonstrated that silodosin binds with high affinity to the alpha-1A subtype.
12.2Pharmacodynamics Orthostatic Effects A test for postural hypotension was conducted 2 to 6 hours after the first dose in the two 12-week, double-blind, placebo-controlled clinical studies. After the patient had been at rest in a supine position for 5 minutes, the patient was asked to stand. Blood pressure and heart rate were assessed at 1 minute and 3 minutes after standing.
A positive result was defined as a > 30 mmHg decrease in systolic blood pressure, or a > 20 mmHg decrease in diastolic blood pressure, or a > 20 bpm increase in heart rate [see WARNINGS AND PRECAUTIONS (5.1) ]. Table 2 Summary of Orthostatic Test Results in 12-week, Placebo-Controlled Clinical Trials Time of Measurement Test Result Silodosin N=466 n (%) Placebo N=457 n (%) 1 Minute After Standing Negative 459 (98.7) 454 (99.6) Positive 6 (1.3) 2 (0.4) 3 Minute After Standing Negative 456 (98.1) 454 (99.6) Positive 9(1.9) 2 (0.4) Cardiac Electrophysiology The effect of silodosin on QT interval was evaluated in a double-blind, randomized, active- (moxifloxacin) and placebo-controlled, parallel-group study in 189 healthy male subjects aged 18 to 45 years.
Subjects received either silodosin 8 mg, silodosin 24 mg, or placebo once daily for five days, or a single dose of moxifloxacin 400 mg on Day 5 only. The 24 mg dose of silodosin was selected to achieve blood levels of silodosin that may be seen in a “worst-case” scenario exposure (i.e., in the setting of concomitant renal disease or use of strong CYP3A4 inhibitors) [see CONTRAINDICATIONS (4) , WARNINGS AND PRECAUTIONS (5.3) and CLINICAL PHARMACOLOGY (12.3) ]. QT interval was measured during a 24-hour period following dosing on Day 5 (at silodosin steady state).
Silodosin was not associated with an increase in individual corrected (QTcI) QT interval at any time during steady state measurement, while moxifloxacin, the active control, was associated with a maximum 9.59 msec increase in QTcI. There has been no signal of Torsade de Pointes in the post-marketing experience with silodosin outside the United States.
12.3Pharmacokinetics The pharmacokinetics of silodosin have been evaluated in adult male subjects with doses ranging from 0.1 mg to 24 mg per day. The pharmacokinetics of silodosin are linear throughout this dosage range. Absorption The pharmacokinetic characteristics of silodosin 8 mg once daily were determined in a multi-dose, open-label, 7-day pharmacokinetic study completed in 19 healthy, target-aged (≥ 45 years of age) male subjects.
Table 3 presents the steady state pharmacokinetics of this study. Table 3 Mean (±SD) Steady State Pharmacokinetic Parameters in Healthy Males Following Silodosin 8 mg Once Daily with Food C max (ng/mL) t max (hours) t 1/2 (hours) AUC ss (ng•hr/mL) 61.6 ± 27.54 2.6 ± 0.90 13.3 ± 8.07 373.4 ± 164.94 C max = maximum concentration, t max = time to reach C max , t 1/2 = elimination half-life, AUC ss = steady state area under the concentration-time curve Figure 1 Mean (±SD) Silodosin Steady State Plasma Concentration-Time Profile in Healthy Target-Aged Subjects Following Silodosin 8 mg Once Daily with Food The absolute bioavailability is approximately 32%.
Food Effect The maximum effect of food (i.e., co-administration with a high fat, high calorie meal) on the PK of silodosin was not evaluated. The effect of a m… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Silodosin is a selective antagonist of post-synaptic alpha-1 adrenoreceptors, which are located in the human prostate, bladder base, bladder neck, prostatic capsule, and prostatic urethra. Blockade of these alpha-1 adrenoreceptors can cause smooth muscle in these tissues to relax, resulting in an improvement in urine flow and a reduction in BPH symptoms. An in vitro study examining binding affinity of silodosin to the three subtypes of the alpha-1 adrenoreceptors (alpha-1A, alpha-1B, and alpha-1D) was conducted.
The results of the study demonstrated that silodosin binds with high affinity to the alpha-1A subtype.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING White, opaque, hard gelatin 8 mg capsules . Cap is imprinted with “S” in black ink. Body is imprinted with “8 mg”.
8 mg capsules are supplied as: 30 capsules (NDC 72789-090-30) 90 capsules (NDC 72789-090-90) Bottles of 30 and 90 capsules are supplied with child-resistant closures. Storage Store at 25°C (77°F); excursions permitted to 15 to 30°C (59 to 86°F). [See USP controlled room temperature.] Protect from light and moisture. Keep out of reach of children.
📋 Description ▾
11 DESCRIPTION Silodosin capsules is the brand name for silodosin, a selective antagonist of alpha-1 adrenoreceptors. The chemical name of silodosin is 1-(3- Hydroxypropyl)-5-[(2R)-2-({2-[2-(2,2,2-trifluoroethoxy) phenoxy]ethyl} amino) propyl]-2,3-dihydro-1H-indole-7-carboxamide and the molecular formula is C 25 H 32 F 3 N 3 O 4 with a molecular weight of 495.53. The structural formula of silodosin is: Silodosin is a white to pale yellowish white powder that melts at approximately 104.72 to 107.5 °C.
It is freely soluble in acetic acid, and in absolute alcohol, and insoluble in water. Each Silodosin 8 mg capsule for oral administration contains 8 mg silodosin, and the following inactive ingredients: magnesium stearate, magnesium aluminometasilicate, mannitol, polysorbate 80 and pregelatinized starch. The size #1 hard gelatin capsules contain gelatin and titanium dioxide.
The capsules are printed with edible ink containing shellac, propylene glycol, black iron oxide and potassium hydroxide. Each Silodosin 4 mg capsule for oral administration contains 4 mg silodosin, and the following inactive ingredients: magnesium stearate, magnesium aluminometasilicate, mannitol, polysorbate 80 and pregelatinized starch. The size #3 hard gelatin capsules contain gelatin and titanium dioxide.
The capsules are printed with edible ink containing shellac, propylene glycol, black iron oxide and potassium hydroxide. structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients to take silodosin once daily with a meal [see Dosage and Administration (2.1) ] . Advise patients about the possible occurrence of symptoms related to postural hypotension (such as dizziness), and should be cautioned about driving, operating machinery, or performing hazardous tasks until they know how silodosin will affect them. This is especially important for those with low blood pressure or who are taking antihypertensive medications [see Warnings and Precautions (5.1) ].
Counsel patients on that the most common side effect seen with silodosin is an orgasm with reduced or no semen. This side effect does not pose a safety concern and is reversible with discontinuation of the product [see Adverse Reactions (6.1) ]. Counsel patients to tell their ophthalmologist about the use of silodosin before cataract surgery or other procedures involving the eyes, even if the patient is no longer taking silodosin [see Warnings and Precautions (5.7) ] .
Rx only Manufactured by: MSN Laboratories Private Limited Telangana – 509 228, INDIA Distributed by: Novadoz Pharmaceuticals LLC Piscataway, NJ 08854-3714 Issued on: January 2021
🍼 Nursing Mothers ▾
8.3Females and Males of Reproductive Potential Infertility Males Possible effects on male fertility could be observed based on findings in rats at exposures that were at least two times higher than at the MRHD (based on AUC). These findings may be reversible, and the clinical relevance is unknown [see NONCLINICAL TOXICOLOGY (13.1) ].
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of silodosin have been evaluated in adult male subjects with doses ranging from 0.1 mg to 24 mg per day. The pharmacokinetics of silodosin are linear throughout this dosage range. Absorption The pharmacokinetic characteristics of silodosin 8 mg once daily were determined in a multi-dose, open-label, 7-day pharmacokinetic study completed in 19 healthy, target-aged (≥ 45 years of age) male subjects.
Table 3 presents the steady state pharmacokinetics of this study. Table 3 Mean (±SD) Steady State Pharmacokinetic Parameters in Healthy Males Following Silodosin 8 mg Once Daily with Food C max (ng/mL) t max (hours) t 1/2 (hours) AUC ss (ng•hr/mL) 61.6 ± 27.54 2.6 ± 0.90 13.3 ± 8.07 373.4 ± 164.94 C max = maximum concentration, t max = time to reach C max , t 1/2 = elimination half-life, AUC ss = steady state area under the concentration-time curve Figure 1 Mean (±SD) Silodosin Steady State Plasma Concentration-Time Profile in Healthy Target-Aged Subjects Following Silodosin 8 mg Once Daily with Food The absolute bioavailability is approximately 32%.
Food Effect The maximum effect of food (i.e., co-administration with a high fat, high calorie meal) on the PK of silodosin was not evaluated. The effect of a moderate fat, moderate calorie meal was variable and decreased silodosin C max by approximately 18 to 43% and AUC by 4 to 49% across three different studies. In a single-center, open-label, single-dose, randomized, two-period crossover study in twenty healthy male subjects age 21 to 43 years under fed conditions, a study was conducted to evaluate the relative bioavailability of the contents of an 8 mg capsule (size #1) of silodosin sprinkled on applesauce compared to the product administered as an intact capsule.
Based on AUC 0 - 24 and C max , silodosin administered by sprinkling the contents of a silodosin capsule onto a tablespoonful of applesauce was found to be bioequivalent to administering the capsule whole. Distribution Silodosin has an apparent volume of distribution of
49.5L and is approximately 97% protein bound. Elimination Metabolism Silodosin undergoes extensive metabolism through glucuronidation, alcohol and aldehyde dehydrogenase, and cytochrome P450 3A4 (CYP3A4) pathways. The main metabolite of silodosin is a glucuronide conjugate (KMD-3213G) that is formed via direct conjugation of silodosin by UDP-glucuronosyltransferase 2B7 (UGT2B7).
Co-administration with inhibitors of UGT2B7 (e.g., probenecid, valproic acid, fluconazole) may potentially increase exposure to silodosin. KMD-3213G, which has been shown in vitro to be active, has an extended half-life (approximately 24 hours) and reaches plasma exposure (AUC) approximately four times greater than that of silodosin. The second major metabolite (KMD-3293) is formed via alcohol and aldehyde dehydrogenases and reaches plasma exposures similar to that of silodosin.
KMD-3293 is not expected to contribute significantly to the overall pharmacologic activity of silodosin. Excretion Following oral administration of 14C-labeled silodosin, the recovery of radioactivity after 10 days was approximately 33.5% in urine and 54.9% in feces. After intravenous administration, the plasma clearance of silodosin was approximately 10 L/hour.
Special Populations Race No clinical studies specifically investigating the effects of race have been performed. Geriatric In a study comparing 12 geriatric males (mean age 69 years) and 9 young males (mean age 24 years), the exposure (AUC) and elimination half-life of silodosin were approximately 15% and 20%, respectively, greater in geriatric than young subjects. No difference in the C max of silodosin was observed [see USE IN SPECIFIC POPULATIONS (8.5) ].
Pediatric Silodosin has not been evaluated in patients less than 18 years of age. Renal Impairment In a study with six subjects with moderate renal impairment, the total silodosin (bound and unbound) AUC, Cmax, and elimination half-life were 3.2-, 3.1-,… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Orthostatic Effects A test for postural hypotension was conducted 2 to 6 hours after the first dose in the two 12-week, double-blind, placebo-controlled clinical studies. After the patient had been at rest in a supine position for 5 minutes, the patient was asked to stand. Blood pressure and heart rate were assessed at 1 minute and 3 minutes after standing.
A positive result was defined as a > 30 mmHg decrease in systolic blood pressure, or a > 20 mmHg decrease in diastolic blood pressure, or a > 20 bpm increase in heart rate [see WARNINGS AND PRECAUTIONS (5.1) ]. Table 2 Summary of Orthostatic Test Results in 12-week, Placebo-Controlled Clinical Trials Time of Measurement Test Result Silodosin N=466 n (%) Placebo N=457 n (%) 1 Minute After Standing Negative 459 (98.7) 454 (99.6) Positive 6 (1.3) 2 (0.4) 3 Minute After Standing Negative 456 (98.1) 454 (99.6) Positive 9(1.9) 2 (0.4) Cardiac Electrophysiology The effect of silodosin on QT interval was evaluated in a double-blind, randomized, active- (moxifloxacin) and placebo-controlled, parallel-group study in 189 healthy male subjects aged 18 to 45 years.
Subjects received either silodosin 8 mg, silodosin 24 mg, or placebo once daily for five days, or a single dose of moxifloxacin 400 mg on Day 5 only. The 24 mg dose of silodosin was selected to achieve blood levels of silodosin that may be seen in a “worst-case” scenario exposure (i.e., in the setting of concomitant renal disease or use of strong CYP3A4 inhibitors) [see CONTRAINDICATIONS (4) , WARNINGS AND PRECAUTIONS (5.3) and CLINICAL PHARMACOLOGY (12.3) ]. QT interval was measured during a 24-hour period following dosing on Day 5 (at silodosin steady state).
Silodosin was not associated with an increase in individual corrected (QTcI) QT interval at any time during steady state measurement, while moxifloxacin, the active control, was associated with a maximum 9.59 msec increase in QTcI. There has been no signal of Torsade de Pointes in the post-marketing experience with silodosin outside the United States.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Benign Prostatic Hyperplasia Two 12-week, randomized, double-blind, placebo-controlled, multicenter studies were conducted with 8 mg daily of silodosin. In these two studies, 923 patients [mean age 64.6 years; Caucasian (89.3%), Hispanic (4.9%), Black (3.9%), Asian (1.2%), Other (0.8%)] were randomized and 466 patients received silodosin 8 mg daily. The two studies were identical in design except for the inclusion of pharmacokinetic sampling in Study 1.
The primary efficacy assessment was the International Prostate Symptom Score (IPSS) which evaluated irritative (frequency, urgency, and nocturia), and obstructive (hesitancy, incomplete emptying, intermittency, and weak stream) symptoms. Maximum urine flow rate (Qmax) was a secondary efficacy measure. Mean changes from baseline to last assessment (Week 12) in total IPSS score were statistically significantly greater for groups treated with silodosin than those treated with placebo in both studies (Table 4 and Figures 2 and 3).
Table 4 Mean Change (SD) from Baseline to Week 12 in International Prostate Symptom Score in Two Randomized, Controlled, Double-Blind Studies Study 1 Study 2 Total Symptom Score Silodosin 8 mg (n=233) Placebo (n=228) p-value Silodosin 8 mg (n=233) Placebo (n=228) p-value Baseline 21.5 (5.38) 21.4 (4.91) 21.2 (4.88) 21.2 (4.92) Week 12 / LOCF Change from baseline -6.5 (6.73) -3.6 (5.85) < 0.0001 -6.3 (6.54) -3.4 (5.83) < 0.0001 LOCF – Last observation carried forward for those not completing 12 weeks of treatment. Figure 2 Mean Change from Baseline in IPSS Total Score by Treatment Group and Visit in Study 1 B – Baseline determination taken Day 1 of the study before the initial dose.
Subsequent values are observed cases except for LOCF values. LOCF – Last observation carried forward for those not completing 12 weeks of treatment. Figure 3 Mean Change from Baseline in IPSS Total Score by Treatment Group and Visit in Study 2 B – Baseline determination taken Day 1 of the study before the initial dose.
Subsequent values are observed cases except for LOCF values. LOCF – Last observation carried forward for those not completing 12 weeks of treatment. Mean IPSS total score for silodosin once daily groups showed a decrease starting at the first scheduled observation and remained decreased through the 12 weeks of treatment in both studies.
Silodosin produced statistically significant increases in maximum urinary flow rates from baseline to last assessment (Week 12) versus placebo in both studies (Table 5 and Figures 4 and 5). Mean peak flow rate increased starting at the first scheduled observation at Day 1 and remained greater than the baseline flow rate through the 12 weeks of treatment for both studies. fig-2 fig-3 Table 5 Mean Change (SD) from Baseline in Maximum Urinary Flow Rate (mL/sec) in Two Randomized, Controlled, Double-Blind Studies Study 1 Study 2 Mean Maximum Flow rate (mL/sec) Silodosin 8 mg (n = 233) Placebo (n = 228) p-value Silodosin 8 mg (n = 233) Placebo (n = 229) p-value Baseline 9.0 (2.60) 9.0 (2.85) 8.4 (2.48) 8.7 (2.67) Week 12 / LOCF Change from Baseline 2.2 (4.31) 1.2 (3.81) 0.0060 2.9 (4.53) 1.9 (4.82) 0.0431 LOCF – Last observation carried forward for those not completing 12 weeks of treatment.
Figure 4 Mean Change from Baseline in Qmax (mL/sec) by Treatment Group and Visit in Study 1 B – Baseline determination taken Day 1 of the study before the initial dose. Subsequent values are observed cases except for LOCF values. LOCF – Last observation carried forward for those not completing 12 weeks of treatment.
Note – The first Qmax assessments at Day 1 were taken 2 to 6 hours after patients received the first dose of double-blind medication. Note – Measurements at each visit were scheduled 2 to 6 hours after dosing (approximate peak plasma silodosin concentration). Figure 5 Mean Change from Baseline in Qmax (mL/sec) by Treatment Group and Visit in Study 2 B – Baseline determination taken Day 1 of the study before the… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, and Impairment of Fertility In a 2-year oral carcinogenicity study in rats administered doses up to 150 mg/kg/day [about 8 times the exposure at the MRHD based on AUC of silodosin], an increase in thyroid follicular cell tumor incidence was seen in male rats receiving doses of150 mg/kg/day. Silodosin induced stimulation of thyroid stimulating hormone (TSH) secretion in the male rat as a result of increased metabolism and decreased circulating levels of thyroxine (T 4 ). These changes are believed to produce specific morphological and functional changes in the rat thyroid including hypertrophy, hyperplasia, and neoplasia.
Silodosin did not alter TSH or T 4 levels in clinical trials and no effects based on thyroid examinations were noted. The relevance to human risk of these thyroid tumors in rats is not known. In a 2-year oral carcinogenicity study in mice administered doses up to 100 mg/kg/day in males (about 9 times the exposure at the MRHD based on AUC of silodosin) and 400 mg/kg/day in females (about 72 times the exposure at the MRHD based on AUC), there were no significant tumor findings in male mice.
Female mice treated for 2 years with doses of 150 mg/kg/day (about 29 times the exposure at the MRHD based on AUC) or greater had statistically significant increases in the incidence of mammary gland adenoacanthomas and adenocarcinomas. The increased incidence of mammary gland neoplasms in female mice was considered secondary to silodosin-induced hyperprolactinemia measured in the treated mice. Elevated prolactin levels were not observed in clinical trials.
The relevance to human risk of prolactin-mediated endocrine tumors in mice is not known. Rats and mice do not produce glucuronidated silodosin, which is present in human serum at approximately four times the level of circulating silodosin and which has similar pharmacological activity to silodosin. Silodosin produced no evidence of mutagenic or genotoxic potential in the in vitro Ames assay, mouse lymphoma assay, unscheduled DNA synthesis assay and the in vivo mouse micronucleus assay.
A weakly positive response was obtained in two in vitro Chinese Hamster Lung (CHL) tests for chromosomal aberration assays at high, cytotoxic concentrations. Treatment of male rats with silodosin for 15 days resulted in decreased fertility at the high dose of 20 mg/kg/day (about 2 times the exposure at the MRHD based on AUC) which was reversible following a two-week recovery period. No effect was observed at 6 mg/kg/day.
The clinical relevance of this finding is not known. In a fertility study in female rats, the high dose of 20 mg/kg/day (about 1 to 4 times the exposure at the MRHD based on AUC) resulted in estrus cycle changes, but no effect on fertility. No effect on the estrus cycle was observed at 6 mg/kg/day.
In a male rat fertility study, sperm viability and count were significantly lower after administration of 600 mg/kg/day (about 65 times the exposure at the MRHD based on AUC) for one month. Histopathological examination of infertile males revealed changes in the testes and epididymides at 200 mg/kg/day (about 30 times the exposure at the MRHD based on AUC).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, and Impairment of Fertility In a 2-year oral carcinogenicity study in rats administered doses up to 150 mg/kg/day [about 8 times the exposure at the MRHD based on AUC of silodosin], an increase in thyroid follicular cell tumor incidence was seen in male rats receiving doses of150 mg/kg/day. Silodosin induced stimulation of thyroid stimulating hormone (TSH) secretion in the male rat as a result of increased metabolism and decreased circulating levels of thyroxine (T 4 ). These changes are believed to produce specific morphological and functional changes in the rat thyroid including hypertrophy, hyperplasia, and neoplasia.
Silodosin did not alter TSH or T 4 levels in clinical trials and no effects based on thyroid examinations were noted. The relevance to human risk of these thyroid tumors in rats is not known. In a 2-year oral carcinogenicity study in mice administered doses up to 100 mg/kg/day in males (about 9 times the exposure at the MRHD based on AUC of silodosin) and 400 mg/kg/day in females (about 72 times the exposure at the MRHD based on AUC), there were no significant tumor findings in male mice.
Female mice treated for 2 years with doses of 150 mg/kg/day (about 29 times the exposure at the MRHD based on AUC) or greater had statistically significant increases in the incidence of mammary gland adenoacanthomas and adenocarcinomas. The increased incidence of mammary gland neoplasms in female mice was considered secondary to silodosin-induced hyperprolactinemia measured in the treated mice. Elevated prolactin levels were not observed in clinical trials.
The relevance to human risk of prolactin-mediated endocrine tumors in mice is not known. Rats and mice do not produce glucuronidated silodosin, which is present in human serum at approximately four times the level of circulating silodosin and which has similar pharmacological activity to silodosin. Silodosin produced no evidence of mutagenic or genotoxic potential in the in vitro Ames assay, mouse lymphoma assay, unscheduled DNA synthesis assay and the in vivo mouse micronucleus assay.
A weakly positive response was obtained in two in vitro Chinese Hamster Lung (CHL) tests for chromosomal aberration assays at high, cytotoxic concentrations. Treatment of male rats with silodosin for 15 days resulted in decreased fertility at the high dose of 20 mg/kg/day (about 2 times the exposure at the MRHD based on AUC) which was reversible following a two-week recovery period. No effect was observed at 6 mg/kg/day.
The clinical relevance of this finding is not known. In a fertility study in female rats, the high dose of 20 mg/kg/day (about 1 to 4 times the exposure at the MRHD based on AUC) resulted in estrus cycle changes, but no effect on fertility. No effect on the estrus cycle was observed at 6 mg/kg/day.
In a male rat fertility study, sperm viability and count were significantly lower after administration of 600 mg/kg/day (about 65 times the exposure at the MRHD based on AUC) for one month. Histopathological examination of infertile males revealed changes in the testes and epididymides at 200 mg/kg/day (about 30 times the exposure at the MRHD based on AUC).
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL 72789090 Label
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |