
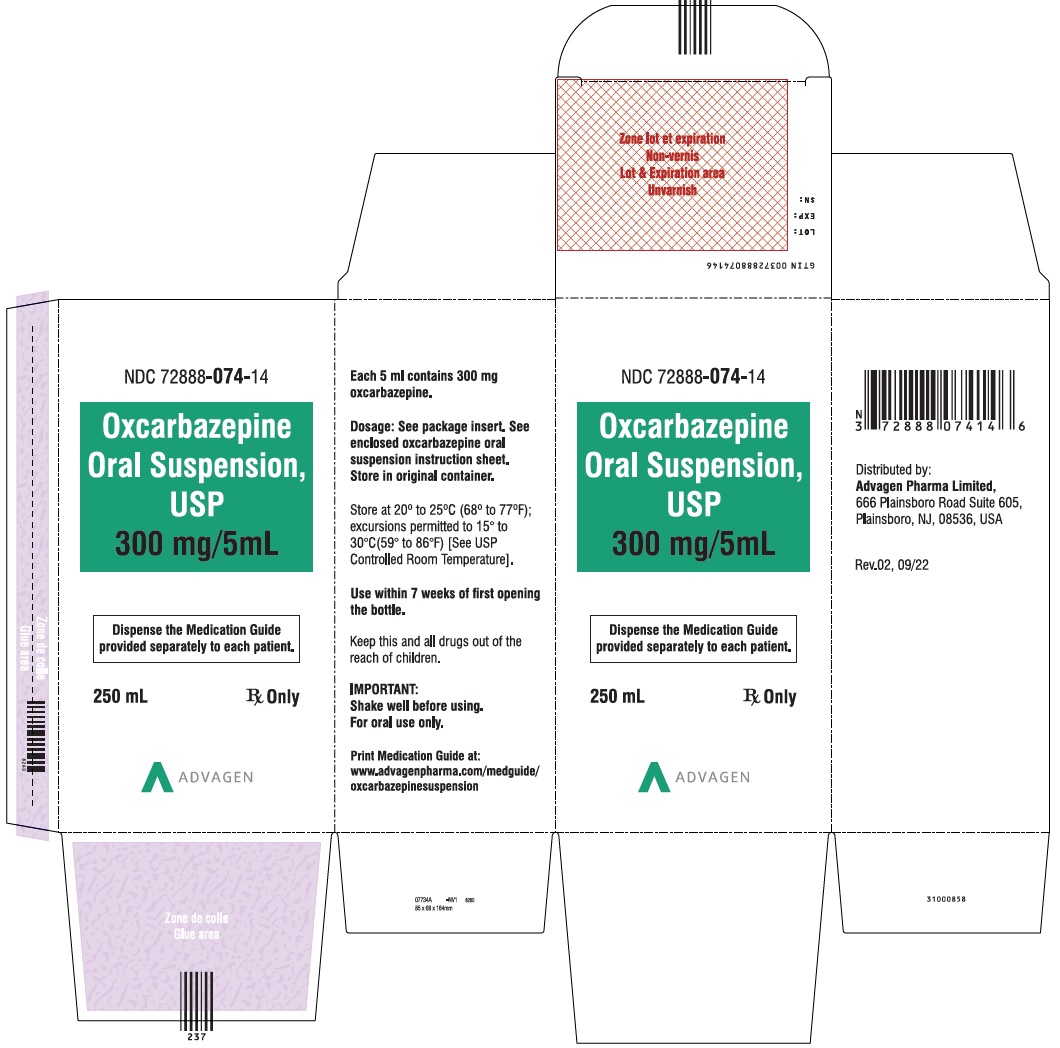
OXCARBAZEPINE 300 mg/5mL Suspension
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Anti-epileptic Agent class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Oxcarbazepine (Trileptal) is used alone or in combination with other medications to control certain types of seizures in adults and children. Oxcarbazepine extended-release tablets (Oxtellar XR) are used in combination with other medications to control certain types of seizures in adults and children 6 years of age and older. Oxcarbazepine is in a class of medications called anticonvulsants. It works by decreasing abnormal electrical activity in the brain.
Read the full MedlinePlus article ↗- Oxcarbazepine is used to treat partial-onset seizures — seizures that start in one part of the brain. It can be used on its own or together with other seizure medicines, depending...
- What is oxcarbazepine actually used for?
- Good news: the tablets and oral suspension can be taken with or without food, so you don't need to plan around meals. The extended-release tablet is taken once a day, while the reg...
- How should I take it — does it matter if I take it with food?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Oxcarbazepine — tap one for details:
Oxcarbazepine may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII K679OBS311
Carboxymethylcellulose sodium is a plant-derived thickening agent made from cellulose. In medicines, it acts as a binder to hold ingredients together, a disintegrant to help the tablet break apart, or a thickener in liquids.
-
UNII 817L1N4CKP
Malic acid is a naturally occurring organic acid found in fruits. It works as a buffer and flavor agent to maintain the medicine's pH balance and add tartness to the product.
-
UNII A2I8C7HI9T
Methylparaben is a preservative derived from benzoic acid that prevents growth of bacteria, fungi, and mold in medicines. It extends the product's shelf life and maintains safety during storage.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII Z8IX2SC1OH
Propylparaben is a chemical preservative used to prevent bacterial and fungal growth in medicines and personal care products. It helps extend shelf life and maintain product safety during storage.
-
UNII SB8ZUX40TY
Saccharin sodium is an artificial sweetener made from saccharin salt. It's added to medicines to improve taste, especially in liquid formulations for children or bitter drugs.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.117 | $29.20 / 250 ml |
| Medicaid paysCMS SDUD · 12 mo | $0.2240 | $56.00 / 250 ml |
| Medicare drug plans payPart D · Q2 2026 | $0.3492 | $87.30 / 250 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Oxcarbazepine 60 mg/mL 31722-0687-25 | Camber | 1 bottle | $0.117 | AB | Availability likely | — |
| Oxcarbazepine 300 mg/5mL 42806-0600-22 | EPIC | 1 bottle | $0.117 | AB | Availability likely | — |
| Oxcarbazepine 60 mg/mL 67877-0532-58 | Ascend | 250 ml | $0.117 | AB | Availability likely | — |
| Oxcarbazepine 300 mg/5mL 69452-0125-50 | Bionpharma | 1 bottle | $0.117 | AB | Availability likely | — |
| Oxcarbazepine 60 mg/mL 70377-0117-11 | Biocon | 1 bottle | $0.117 | AB | Availability likely | — |
| Oxcarbazepine 60 mg/mL 72603-0252-01 | NorthStar | 1 bottle | $0.117 | AB | Availability likely | — |
| Oxcarbazepine 300 mg/5mLthis 72888-0074-14 | Advagen | 1 bottle | $0.117 | AB | Availability likely | — |
| Trileptal 60 mg/mL 00078-0357-52 | Novartis | 250 ml | $1.930 | AB | Availability likely | +1553% |
| Oxcarbazepine 300 mg/5mL 10135-0798-41 | Marlex | 250 ml | — | AB | FDA listed | — |
| oxcarbazepine 300 mg/5mL 33342-0259-67 | Macleods | 1 bottle | — | AB | FDA listed | — |
| Oxcarbazepine 60 mg/mL 51672-1393-01 | Sun | 1 bottle | — | AB | Discontinued | — |
| Oxcarbazepine 300 mg/5mL 62135-0841-24 | Chartwell | 20 cups | — | AB | FDA listed | — |
| Oxcarbazepine 300 mg/5mL 65162-0649-48 | Amneal | 10 cups | — | AB | FDA listed | — |
| Oxcarbazepine 300 mg/5mL 68094-0123-62 | Precision | 10 cups | — | AB | FDA listed | — |
| Oxcarbazepine 300 mg/5mL 68999-0841-24 | Chartwell | 10 cups | — | AB | FDA listed | — |
| Oxcarbazepine 300 mg/5mL 72162-2088-02 | Bryant | 1 bottle | — | AB | FDA listed | — |
| Oxcarbazepine 300 mg/5mL 72162-2631-02 | Bryant | 250 ml | — | AB | FDA listed | — |
| Oxcarbazepine 300 mg/5mL 72205-0354-85 | Novadoz | 1 bottle | — | AB | FDA listed | — |
| Oxcarbazepine 300 mg/5mL 85742-0007-06 | Kanchan | 250 ml | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 72888-0074-14 You're viewing this | 1 BOTTLE in 1 CARTON (72888-074-14) / 250 mL in 1 BOTTLE | 2022-08-31 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Oxcarbazepine is indicated for use as monotherapy or adjunctive therapy in the treatment of partial-onset seizures in adults and as monotherapy in the treatment of partial-onset seizures in pediatric patients aged 4 years and above, and as adjunctive therapy in pediatric patients aged 2 years and above with partial-onset seizures. Oxcarbazepine is indicated for: Adults: Monotherapy or adjunctive therapy in the treatment of partial-onset seizures Pediatrics: - Monotherapy in the treatment of partial-onset seizures in children 4–16 years - Adjunctive therapy in the treatment of partial-onset seizures in children 2–16 years ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Adults: Initiate with a dose of 600 mg/day, given twice-a-day Adjunctive Therapy: Maximum increment of 600 mg/day at approximately weekly intervals. The recommended daily dose is 1200 mg/day ( 2.1 ) Conversion to Monotherapy: Withdrawal concomitant over 3 to 6 weeks; reach maximum dose of oxcarbazepine in 2 to 4 weeks with increments of 600 mg/day at weekly intervals to a recommended daily dose of 2400 mg/day ( 2.2 ) Initiation of Monotherapy: Increments of 300 mg/day every third day to a dose of 1200 mg/day ( 2.3 ) Initiate at one-half the usual starting dose and increase slowly in patients with a creatinine clearance < 30 mL/min, ( 2.7 ) Pediatrics: initiation with 8 to 10 mg/kg/day, given twice-a-day.
For patients aged 2 to < 4 years and under 20 kg, a starting dose of 16 to 20 mg/kg/day may be considered. Recommended daily dose is dependent upon patient weight. Adjunctive Patients (Aged 2–16 Years): For patients aged 4 to 16 years, target maintenance dose should be achieved over 2 weeks ( 2.4 ).
For patients aged 2 to < 4 years, maximum maintenance dose should be achieved over 2 to 4 weeks and should not to exceed 60 mg/kg/day ( 2.4 ) Conversion to Monotherapy for Patients (Aged 4–16 Years) Maximum increment of 10 mg/kg/day at weekly intervals, concomitant antiepileptic drugs can be completely withdrawn over 3 to 6 weeks ( 2.5 ) Initiation of Monotherapy for Patients (Aged 4–16 Years) Increments of 5 mg/kg/day every third day ( 2.6 )
2.1Adjunctive Therapy for Adults Initiate oxcarbazepine with a dose of 600 mg/day, given twice-a-day. If clinically indicated, the dose may be increased by a maximum of 600 mg/day at approximately weekly intervals; the maximum recommended daily dose is 1200 mg/day. Daily doses above 1200 mg/day show somewhat greater effectiveness in controlled trials, but most patients were not able to tolerate the 2400 mg/day dose, primarily because of central nervous (CNS) effects.
Dosage adjustment is recommended with concomitant use of strong CYP3A4 enzyme inducers or UDP glucouronosyltransferase (UGT) inducers, which include certain antiepileptic drugs (AEDs) [ see Drug Interactions ( 7.1 , 7.2 ) ].
2.2Conversion to Monotherapy for Adults Patients receiving concomitant AEDs may be converted to monotherapy by initiating treatment with oxcarbazepine at 600 mg/day (given in a twice-a-day regimen) while simultaneously initiating the reduction of the dose of the concomitant AEDs. The concomitant AEDs should be completely withdrawn over 3 to 6 weeks, while the maximum dose of oxcarbazepine should be reached in about 2 to 4 weeks. Oxcarbazepine may be increased as clinically indicated by a maximum increment of 600 mg/day at approximately weekly intervals to achieve the maximum recommended daily dose of 2400 mg/day.
A daily dose of 1200 mg/day has been shown in one study to be effective in patients in whom monotherapy has been initiated with oxcarbazepine. Patients should be observed closely during this transition phase.
2.3Initiation of Monotherapy for Adults Patients not currently being treated with AEDs may have monotherapy initiated with oxcarbazepine. In these patients, initiate oxcarbazepine at a dose of 600 mg/day (given a twice-a-day); the dose should be increased by 300 mg/day every third day to a dose of 1200 mg/day. Controlled trials in these patients examined the effectiveness of a 1200 mg/day dose; a dose of 2400 mg/day has been shown to be effective in patients converted from other AEDs to oxcarbazepine monotherapy (see above).
2.4Adjunctive Therapy for Pediatric Patients (Aged 2–16 Years) In pediatric patients aged 4–16 years, initiate oxcarbazepine at a daily dose of 8 to 10 mg/kg generally not to exceed 600 mg/day, given twice-a-day. The target maintenance dose of oxcarbazepine should be achieved over 2 weeks, and is dependent upon patient weight, according to the following chart: 20 to 29 kg – 900 mg/day 29.1 to 39 kg – 1200 mg/day > 39 kg – 1800 mg/day In the cli…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Oral Suspension 300 mg/5 mL (60 mg/mL): off-white to light orange suspension with plum lemon flavor. Oral suspension a 300 mg/5 mL (60 mg/mL) ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Oxcarbazepine is contraindicated in patients with a known hypersensitivity to oxcarbazepine or to any of its components, or to eslicarbazepine acetate [ see Warnings and Precautions ( 5.2 , 5.3 ) ]. Known hypersensitivity to oxcarbazepine or to any of its components, or to eslicarbazepine acetate ( 4 , 5.2 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hyponatremia: Monitor serum sodium levels ( 5.1 ) Cross Hypersensitivity Reaction to Carbamazepine: Discontinue immediately if hypersensitivity occurs ( 5.3 ) Serious Dermatological Reactions: If occurs consider discontinuation ( 5.4 ) Suicidal Behavior and Ideation: Monitor for suicidal thoughts/ behavior ( 5.5 ) Withdrawal of AEDs: Withdraw oxcarbazepine gradually ( 5.6 ) Cognitive/Neuropsychiatric Adverse Reactions: May cause cognitive dysfunction, somnolence, and coordination abnormalities.
Use caution when operating machinery ( 5.7 ) Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multi-Organ Hypersensitivity: Monitor and discontinue if another cause cannot be established ( 5.8 ) Hematologic Events: Consider discontinuing ( 5.9 ) Seizure Control During Pregnancy: Active metabolite may decrease ( 5.10 ) Risk of Seizure Aggravation: Discontinue if occurs. ( 5.11 )
5.1Hyponatremia Clinically significant hyponatremia (sodium < 125 mmol/L) can develop during oxcarbazepine use. In the 14 controlled epilepsy studies 2.5% of oxcarbazepine-treated patients (38/1,524) had a sodium of less than 125 mmol/L at some point during treatment, compared to no such patients assigned placebo or active control (carbamazepine and phenobarbital for adjunctive and monotherapy substitution studies, and phenytoin and valproate for the monotherapy initiation studies).Clinically significant hyponatremia generally occurred during the first 3 months of treatment with oxcarbazepine, although there were patients who first developed a serum sodium < 125 mmol/L more than 1 year after initiation of therapy.
Most patients who developed hyponatremia were asymptomatic but patients in the clinical trials were frequently monitored and some had their oxcarbazepine dose reduced, discontinued, or had their fluid intake restricted for hyponatremia. Whether or not these maneuvers prevented the occurrence of more severe events is unknown. Cases of symptomatic hyponatremia and syndrome of inappropriate antidiuretic hormone secretion (SIADH) have been reported during postmarketing use.
In clinical trials, patients whose treatment with oxcarbazepine was discontinued due to hyponatremia generally experienced normalization of serum sodium within a few days without additional treatment. Measurement of serum sodium levels should be considered for patients during maintenance treatment with oxcarbazepine, particularly if the patient is receiving other medications known to decrease serum sodium levels (e.g., drugs associated with inappropriate ADH secretion) or if symptoms possibly indicating hyponatremia develop (e.g., nausea, malaise, headache, lethargy, confusion, obtundation, or increase in seizure frequency or severity).
5.2Anaphylactic Reactions and Angioedema Rare cases of anaphylaxis and angioedema involving the larynx, glottis, lips and eyelids have been reported in patients after taking the first or subsequent doses of oxcarbazepine. Angioedema associated with laryngeal edema can be fatal. If a patient develops any of these reactions after treatment with oxcarbazepine, the drug should be discontinued and an alternative treatment started.
These patients should not be rechallenged with the drug [ see Warnings and Precautions ( 5.3 )].
5.3Cross Hypersensitivity Reaction to Carbamazepine Approximately 25% to 30% of patients who have had hypersensitivity reactions to carbamazepine will experience hypersensitivity reactions with oxcarbazepine. For this reason patients should be specifically questioned about any prior experience with carbamazepine, and patients with a history of hypersensitivity reactions to carbamazepine should ordinarily be treated with oxcarbazepine only if the potential benefit justifies the potential risk. If signs or symptoms of hypersensitivity develop, oxcarbazepine should be discontinued immediately [ see Warnings and Precautions ( 5.2 , 5.8 ) ].
5.4 Serious Dermatological Reactions Serious dermatological…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described below and elsewhere in the labeling: Hyponatremia [see Warnings and Precautions ( 5.1 )] Anaphylactic Reactions and Angioedema [see Warnings and Precautions ( 5.2 )] Cross Hypersensitivity Reaction to Carbamazepine [see Warnings and Precautions ( 5.3 )] Serious Dermatological Reactions [see Warnings and Precautions ( 5.4 )] Suicidal Behavior and Ideation [see Warnings and Precautions ( 5.5 )] Cognitive/Neuropsychiatric Adverse Reactions [see Warnings and Precautions ( 5.7 )] Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multi-Organ Hypersensitivity [see Warnings and Precautions ( 5.8 )] Hematologic Events [see Warnings and Precautions ( 5.9 )] The most common (≥ 10% more than placebo for adjunctive or low dose for monotherapy) adverse reactions in adults and pediatrics were: dizziness, somnolence, diplopia, fatigue, nausea, vomiting, ataxia, abnormal vision, headache, nystagmus, tremor, and abnormal gait.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Advagen Pharma Ltd, at +1 (866) 488-0312 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Most Common Adverse Reactions in All Clinical Studies Adjunctive Therapy/Monotherapy in Adults Previously Treated With Other AEDs The most common (≥ 10% more than placebo for adjunctive or low dose for monotherapy) adverse reactions with oxcarbazepine: dizziness, somnolence, diplopia, fatigue, nausea, vomiting, ataxia, abnormal vision, headache, nystagmus tremor, and abnormal gait.
Approximately 23% of these 1,537 adult patients discontinued treatment because of an adverse reaction. The adverse reactions most commonly associated with discontinuation were: dizziness (6.4%), diplopia (5.9%), ataxia (5.2%), vomiting (5.1%), nausea (4.9%), somnolence (3.8%), headache (2.9%), fatigue (2.1%), abnormal vision (2.1%), tremor (1.8%), abnormal gait (1.7%), rash (1.4%), and hyponatremia (1.0%). Monotherapy in Adults Not Previously Treated With Other AEDs The most common (≥ 5%) adverse reactions with oxcarbazepine in these patients were similar to those in previously treated patients.
Approximately 9% of these 295 adult patients discontinued treatment because of an adverse reaction. The adverse reactions most commonly associated with discontinuation were: dizziness (1.7%), nausea (1.7%), rash (1.7%), and headache (1.4%). Adjunctive Therapy/Monotherapy in Pediatric Patients 4 Years Old and Above Previously Treated With Other AEDs The most common (≥ 5%) adverse reactions with oxcarbazepine in these patients were similar to those seen in adults.
Approximately 11% of these 456 pediatric patients discontinued treatment because of an adverse reaction. The adverse reactions most commonly associated with discontinuation were: somnolence (2.4%), vomiting (2.0%), ataxia (1.8%), diplopia (1.3%), dizziness (1.3%), fatigue (1.1%), and nystagmus (1.1%). Monotherapy in Pediatric Patients 4 Years Old and Above Not Previously Treated With Other AEDs The most common (≥ 5%) adverse reactions with oxcarbazepine in these patients were similar to those in adults.
Approximately 9.2% of 152 pediatric patients discontinued treatment because of an adverse reaction. The adverse reactions most commonly associated (≥1%) with discontinuation were rash (5.3%) and maculopapular rash (1.3%). Adjunctive Therapy/Monotherapy in Pediatric Patients 1 Month to < 4 Years Old Previously Treated or Not Previously Treated With Other AEDs: The most common (≥ 5%) adverse reactions with oxcarbazepine in these patients were similar to those seen in older children and adults except for infections and infestations which were more frequently seen in these younger c…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Phenytoin: Increased phenytoin levels. Reduced dose of phenytoin may be required ( 7.1 ) Carbamazepine, Phenytoin, Phenobarbital: Decreased plasma levels of MHD (the active metabolite). Dose adjustments may be necessary ( 7.1 ) Oral Contraceptive: Oxcarbazepine may decrease the effectiveness of hormonal contraceptives ( 7.2 )
7.1Effect of Oxcarbazepine on Other Drugs Phenytoin levels have been shown to increase with concomitant use of oxcarbazepine at doses greater than 1200 mg/day [see Clinical Pharmacology ( 12.3 )] . Therefore, it is recommended that the plasma levels of phenytoin be monitored during the period of oxcarbazepine titration and dosage modification. A decrease in the dose of phenytoin may be required.
7.2Effect of Other Drugs on Oxcarbazepine Strong inducers of cytochrome P450 enzymes and/or inducers of UGT (e.g., rifampin, carbamazepine, phenytoin and phenobarbital) have been shown to decrease the plasma/serum levels of MHD, the active metabolite of oxcarbazepine (25% to 49%) [see Clinical Pharmacology ( 12.3 )]. If oxcarbazepine and strong CYP3A4 inducers, or UGT inducers are administered concurrently, it is recommended that the plasma levels of MHD be monitored during the period of oxcarbazepine titration. Dose adjustment of oxcarbazepine may be required after initiation, dosage modification, or discontinuation of such inducers.
7.3Hormonal Contraceptives Concurrent use of oxcarbazepine with hormonal contraceptives may render these contraceptives less effective [see Use in Specific Populations ( 8.3 ) and Clinical Pharmacology ( 12.3 )]. Studies with other oral or implant contraceptives have not been conducted.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: May cause fetal harm ( 8.1 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to AEDs, such as oxcarbazepine, during pregnancy. Encourage women who are taking oxcarbazepine during pregnancy to enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org/. Risk Summary Although oxcarbazepine is closely related structurally to carbamazepine, which is considered to be teratogenic in humans, available human data from published literature and ongoing pregnancy registry studies on use of oxcarbazepine during pregnancy have not demonstrated an increased prevalence of major congenital malformations with first trimester exposure.
However, all published studies reviewed have important methodological limitations, including unmeasured confounding and a small number of exposed cases (see Data) . There are risks to the mother and fetus associated with partial onset seizures (see Clinical Considerations) . There are no data on the risks associated with the use of oxcarbazepine and miscarriage or other adverse maternal outcomes.
Increased incidences of fetal structural abnormalities and other manifestations of developmental toxicity (embryolethality, growth retardation) were observed in the offspring of animals treated with either oxcarbazepine or its active 10-hydroxy metabolite (MHD) during pregnancy at doses similar to the maximum recommended human dose (MRHD). In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
Clinical Considerations Disease-associated Maternal and/or Embryofetal Risk Epilepsy, with or without exposure to antiepileptic drugs, has been associated with several adverse outcomes during pregnancy, including preeclampsia, preterm labor, antepartum and postpartum hemorrhage, placental abruption, poor fetal growth, prematurity, fetal death, and maternal mortality. The risk of maternal or fetal injury may be greatest for patients with untreated or poorly controlled convulsive seizures. Women with epilepsy who become pregnant should not abruptly discontinue antiepileptic drugs, including oxcarbazepine, due to the risk of status epilepticus or severe seizures, which may be life-threatening [see Warnings and Precautions ( 5.6 )] .
Maternal Adverse Reactions An increase in seizure frequency may occur during pregnancy because of altered levels of the active metabolite of oxcarbazepine. Monitor patients carefully during pregnancy and through the postpartum period [see Warnings and Precautions ( 5.10 )] . Data Human Data Data from a published retrospective cohort study and ongoing pregnancy registry studies on the use of oxcarbazepine during pregnancy have not demonstrated an increased prevalence of major congenital malformations with first trimester exposure.
A retrospective cohort study conducted in Nordic countries (Denmark, Finland, Iceland, Norway, and Sweden) from 1996-2020 found that there was no increased prevalence of major congenital malformations when pregnancies exposed to oxcarbazepine during the first trimester were compared to pregnancies exposed to lamotrigine (adjusted risk ratio =1.09; 95% CI 0.83 to 1.44; n pregnancies exposed to oxcarbazepine= 1,313, n exposed cases = 58). In an ongoing pregnancy registry that included data from over 40 countries from 1999 to 2022 and 443 pregnancies exposed to oxcarbazepine, oxcarbazepine exposure during the first trimester was not associated with major congenital malformations (adjusted odds ratio =1.09; 95% CI 0.56 to 2.13, n exposed cases = 10).
However, there are important methodological limitations of these studies including unmeasured confounding factors and…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to AEDs, such as oxcarbazepine, during pregnancy. Encourage women who are taking oxcarbazepine during pregnancy to enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org/. Risk Summary Although oxcarbazepine is closely related structurally to carbamazepine, which is considered to be teratogenic in humans, available human data from published literature and ongoing pregnancy registry studies on use of oxcarbazepine during pregnancy have not demonstrated an increased prevalence of major congenital malformations with first trimester exposure.
However, all published studies reviewed have important methodological limitations, including unmeasured confounding and a small number of exposed cases (see Data) . There are risks to the mother and fetus associated with partial onset seizures (see Clinical Considerations) . There are no data on the risks associated with the use of oxcarbazepine and miscarriage or other adverse maternal outcomes.
Increased incidences of fetal structural abnormalities and other manifestations of developmental toxicity (embryolethality, growth retardation) were observed in the offspring of animals treated with either oxcarbazepine or its active 10-hydroxy metabolite (MHD) during pregnancy at doses similar to the maximum recommended human dose (MRHD). In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
Clinical Considerations Disease-associated Maternal and/or Embryofetal Risk Epilepsy, with or without exposure to antiepileptic drugs, has been associated with several adverse outcomes during pregnancy, including preeclampsia, preterm labor, antepartum and postpartum hemorrhage, placental abruption, poor fetal growth, prematurity, fetal death, and maternal mortality. The risk of maternal or fetal injury may be greatest for patients with untreated or poorly controlled convulsive seizures. Women with epilepsy who become pregnant should not abruptly discontinue antiepileptic drugs, including oxcarbazepine, due to the risk of status epilepticus or severe seizures, which may be life-threatening [see Warnings and Precautions ( 5.6 )] .
Maternal Adverse Reactions An increase in seizure frequency may occur during pregnancy because of altered levels of the active metabolite of oxcarbazepine. Monitor patients carefully during pregnancy and through the postpartum period [see Warnings and Precautions ( 5.10 )] . Data Human Data Data from a published retrospective cohort study and ongoing pregnancy registry studies on the use of oxcarbazepine during pregnancy have not demonstrated an increased prevalence of major congenital malformations with first trimester exposure.
A retrospective cohort study conducted in Nordic countries (Denmark, Finland, Iceland, Norway, and Sweden) from 1996-2020 found that there was no increased prevalence of major congenital malformations when pregnancies exposed to oxcarbazepine during the first trimester were compared to pregnancies exposed to lamotrigine (adjusted risk ratio =1.09; 95% CI 0.83 to 1.44; n pregnancies exposed to oxcarbazepine= 1,313, n exposed cases = 58). In an ongoing pregnancy registry that included data from over 40 countries from 1999 to 2022 and 443 pregnancies exposed to oxcarbazepine, oxcarbazepine exposure during the first trimester was not associated with major congenital malformations (adjusted odds ratio =1.09; 95% CI 0.56 to 2.13, n exposed cases = 10).
However, there are important methodological limitations of these studies including unmeasured confounding factors and a small number of exposed cases in the registry. Animal Data When preg…
🧒 Pediatric Use ▾
8.4Pediatric Use Oxcarbazepine is indicated for use as adjunctive therapy for partial-onset seizures in patients aged 2 to 16 years. The safety and effectiveness for use as adjunctive therapy for partial-onset seizures in pediatric patients below the age of 2 have not been established. Oxcarbazepine is also indicated as monotherapy for partial-onset seizures in patients aged 4 to 16 years.
The safety and effectiveness for use as monotherapy for partial-onset seizures in pediatric patients below the age of 4 have not been established. Oxcarbazepine has been given to 898 patients between the ages of 1 month to 17 years in controlled clinical trials (332 treated as monotherapy) and about 677 patients between the ages of 1 month to 17 years in other trials [ see Warnings and Precautions ( 5.11 ), Adverse Reactions ( 6.1 ), Clinical Pharmacology ( 12.3 ), and Clinical Studies ( 14 ) ].
🧓 Geriatric Use ▾
8.5Geriatric Use There were 52 patients over age 65 in controlled clinical trials and 565 patients over the age of 65 in other trials. Following administration of single (300 mg) and multiple (600 mg/day) doses of oxcarbazepine in elderly volunteers (60 to 82 years of age), the maximum plasma concentrations and area under the curve (AUC) values of MHD were 30% to 60% higher than in younger volunteers (18 to 32 years of age). Comparisons of creatinine clearance in young and elderly volunteers indicate that the difference was due to age-related reductions in creatinine clearance.
Close monitoring of sodium levels is required in elderly patients at risk for hyponatremia [ see Warnings and Precautions ( 5.1 ) ].
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Human Overdose Experience Isolated cases of overdose with oxcarbazepine have been reported. The maximum dose taken was approximately 48,000 mg. All patients recovered with symptomatic treatment.
Nausea, vomiting, somnolence, aggression, agitation, hypotension, and tremor each occurred in more than one patient. Coma, confusional state, convulsion, dyscoordination, depressed level of consciousness, diplopia, dizziness, dyskinesia, dyspnea, QT prolongation, headache, miosis, nystagmus, overdose, decreased urine output, and blurred vision also occurred.
10.2Treatment and Management There is no specific antidote. Symptomatic and supportive treatment should be administered as appropriate. Removal of the drug by gastric lavage and/or inactivation by administering activated charcoal should be considered.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The pharmacological activity of oxcarbazepine is primarily exerted through the 10-monohydroxy metabolite (MHD) of oxcarbazepine [ see Clinical Pharmacology ( 12.3 ) ]. The precise mechanism by which oxcarbazepine and MHD exert their anti-seizure effect is unknown; however, in vitro electrophysiological studies indicate that they produce blockade of voltage-sensitive sodium channels, resulting in stabilization of hyperexcited neural membranes, inhibition of repetitive neuronal firing, and diminution of propagation of synaptic impulses.
These actions are thought to be important in the prevention of seizure spread in the intact brain. In addition, increased potassium conductance and modulation of high-voltage activated calcium channels may contribute to the anticonvulsant effects of the drug. No significant interactions of oxcarbazepine or MHD with brain neurotransmitter or modulator receptor sites have been demonstrated.
12.2Pharmacodynamics Oxcarbazepine and its active metabolite (MHD) exhibit anticonvulsant properties in animal seizure models. They protected rodents against electrically induced tonic extension seizures and, to a lesser degree, chemically induced clonic seizures, and abolished or reduced the frequency of chronically recurring focal seizures in Rhesus monkeys with aluminum implants. No development of tolerance (i.e., attenuation of anticonvulsive activity) was observed in the maximal electroshock test when mice and rats were treated daily for 5 days and 4 weeks, respectively, with oxcarbazepine or MHD.
12.3Pharmacokinetics Following oral administration of oxcarbazepine tablets, oxcarbazepine is completely absorbed and extensively metabolized to its pharmacologically active 10-monohydroxy metabolite (MHD). In a mass balance study in people, only 2% of total radioactivity in plasma was due to unchanged oxcarbazepine, with approximately 70% present as MHD, and the remainder attributable to minor metabolites. The half-life of the parent is about 2 hours, while the half-life of MHD is about 9 hours, so that MHD is responsible for most antiepileptic activity.
Absorption Based on MHD concentrations, oxcarbazepine tablets and suspension were shown to have similar bioavailability. After single-dose administration of oxcarbazepine tablets to healthy male volunteers under fasted conditions, the median t max was 4.5 (range 3 to 13) hours. After single-dose administration of oxcarbazepine to healthy male volunteers under fasted conditions, the median t max was 6 hours.
Steady-state plasma concentrations of MHD are reached within 2 to 3 days in patients when oxcarbazepine is given twice a day. At steady state the pharmacokinetics of MHD are linear and show dose proportionality over the dose range of 300 to 2400 mg/day. Food has no effect on the rate and extent of absorption of oxcarbazepine from oxcarbazepine tablets.
Although not directly studied, the oral bioavailability of the oxcarbazepine is unlikely to be affected under fed conditions. Therefore, oxcarbazepine tablets and suspension can be taken with or without food. Distribution The apparent volume of distribution of MHD is 49 L.
Approximately 40% of MHD is bound to serum proteins, predominantly to albumin. Binding is independent of the serum concentration within the therapeutically relevant range. Oxcarbazepine and MHD do not bind to alpha-1-acid glycoprotein.
Metabolism and Excretion Oxcarbazepine is rapidly reduced by cytosolic enzymes in the liver to its 10-monohydroxy metabolite, MHD, which is primarily responsible for the pharmacological effect of oxcarbazepine. MHD is metabolized further by conjugation with glucuronic acid. Minor amounts (4% of the dose) are oxidized to the pharmacologically inactive 10,11-dihydroxy metabolite (DHD).
Oxcarbazepine is cleared from the body mostly in the form of metabolites which are predominantly excreted by the kidneys. More than 95% of the dose appears in the urine, with less…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The pharmacological activity of oxcarbazepine is primarily exerted through the 10-monohydroxy metabolite (MHD) of oxcarbazepine [ see Clinical Pharmacology ( 12.3 ) ]. The precise mechanism by which oxcarbazepine and MHD exert their anti-seizure effect is unknown; however, in vitro electrophysiological studies indicate that they produce blockade of voltage-sensitive sodium channels, resulting in stabilization of hyperexcited neural membranes, inhibition of repetitive neuronal firing, and diminution of propagation of synaptic impulses.
These actions are thought to be important in the prevention of seizure spread in the intact brain. In addition, increased potassium conductance and modulation of high-voltage activated calcium channels may contribute to the anticonvulsant effects of the drug. No significant interactions of oxcarbazepine or MHD with brain neurotransmitter or modulator receptor sites have been demonstrated.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Oxcarbazepine Oral Suspension Oxcarbazepine Oral Suspension, USP, 300 mg/5 mL (60 mg/mL), Off-white to light orange suspension with plum lemon flavor. Available in properly labeled, sealed and damage/ leakage free amber glass bottles containing 250 mL of oral suspension. Supplied with a 10 mL dosing syringe and press-in bottle adapter.
NDC 72888-074-14 Store oxcarbazepine oral suspension, USP in the original container. Shake well before using. Use within 7 weeks of first opening the bottle.
Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Oxcarbazepine is an AED available as a 300 mg/5mL (60 mg/mL) oral suspension. Oxcarbazepine is 10,11-Dihydro-10-oxo-5 H -dibenz[b, f ]azepine-5-carboxamide, and its structural formula is: Oxcarbazepine, USP is light orange to creamish white or off-white powder. It is slightly soluble in chloroform, dichloromethane, acetone, and methanol and practically insoluble in ethanol, ether and water.
Its molecular weight is 252.27 g/mol. Oxcarbazepine oral suspension, USP contains the following inactive ingredients: malic acid, microcrystalline cellulose and carboxymethyl cellulose sodium, methyl paraben, propyl paraben, polyethylene glycol, propylene glycol, purified water, sodium saccharin, sorbitol, yellow plum lemon flavor. Sodium hydroxide solution may be added for adjustment of pH.
Oxcarbazepine chemical structural.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide and Instructions for Use). Administration Information Counsel patients that oxcarbazepine may be taken with or without food. For oxcarbazepine oral suspension, advise patients to shake the bottle well and prepare the dose immediately afterwards using the oral dosing syringe supplied.
Inform patients that oxcarbazepine oral suspension can be mixed in a small glass of water just prior to administration or, alternatively, may be swallowed directly from the syringe. Instruct patients to discard any unused oxcarbazepine oral suspension after 7 weeks of first opening the bottle [ see Dosage and Administration ( 2.8 ) and How Supplied/Storage and Handling ( 16 ) ]. Hyponatremia Advise patients that oxcarbazepine may reduce the serum sodium concentrations especially if they are taking other medications that can lower sodium.
Instruct patients to report symptoms of low sodium like nausea, tiredness, lack of energy, confusion, and more frequent or more severe seizures [ see Warnings and Precautions ( 5.1 ) ]. Anaphylactic Reactions and Angioedema Anaphylactic reactions and angioedema may occur during treatment with oxcarbazepine. Advise patients to report immediately signs and symptoms suggesting angioedema (swelling of the face, eyes, lips, tongue or difficulty in swallowing or breathing) and to stop taking the drug until they have consulted with their physician [ see Warnings and Precautions ( 5.2 ) ].
Cross Hypersensitivity Reaction to Carbamazepine Inform patients who have exhibited hypersensitivity reactions to carbamazepine that approximately 25% to 30% of these patients may experience hypersensitivity reactions with oxcarbazepine. Patients should be advised that if they experience a hypersensitivity reaction while taking oxcarbazepine they should consult with their physician immediately [ see Warnings and Precautions ( 5.3 ) ]. Serious Dermatological Reactions Advise patients that serious skin reactions have been reported in association with oxcarbazepine.
In the event a skin reaction should occur while taking oxcarbazepine, patients should consult with their physician immediately [ see Warnings and Precautions ( 5.4 ) ]. Suicidal Behavior and Ideation Patients, their caregivers, and families should be counseled that AEDs, including oxcarbazepine, may increase the risk of suicidal thoughts and behavior and should be advised of the need to be alert for the emergence or worsening of symptoms of depression, any unusual changes in mood or behavior, or the emergence of suicidal thoughts, behavior, or thoughts about self-harm.
Behaviors of concern should be reported immediately to healthcare providers [ see Warnings and Precautions ( 5.5 ) ]. Driving and Operating Machinery Advise patients that oxcarbazepine may cause adverse reactions, such as dizziness, somnolence, ataxia, visual disturbances, and depressed level of consciousness. Accordingly, advise patients not to drive or operate machinery until they have gained sufficient experience on oxcarbazepine to gauge whether it adversely affects their ability to drive or operate machinery [ see Warnings and Precautions ( 5.7 ) and Adverse Reactions ( 6 ) ].
Multi-Organ Hypersensitivity Instruct patients that a fever associated with other organ system involvement (e.g., rash, lymphadenopathy, hepatic dysfunction) may be drug-related and should be reported to their healthcare provider immediately [ see Warnings and Precautions ( 5.8 ) ]. Hematologic Events Advise patients that there have been rare reports of blood disorders reported in patients treated with oxcarbazepine. Instruct patients to immediately consult with their physician if they experience symptoms suggestive of blood disorders [ see Warnings and Precautions ( 5.9 ) ].
Drug Interactions Caution female patients of reproductive potential that the concurrent use of oxcarbazepine with hormonal contraceptives may render th…
💬 Medication Guide ▾
MEDICATION GUIDE Oxcarbazepine (ox-kar-BAY-zeh-peen) Oral Suspension, USP What is the most important information I should know about oxcarbazepine oral suspension? Do not stop taking oxcarbazepine oral suspension without first talking to your healthcare provider. Stopping oxcarbazepine oral suspension suddenly can cause serious problems.
Oxcarbazepine can cause serious side effects, including: Oxcarbazepine may cause the level of sodium in your blood to be low . Symptoms of low blood sodium include: nausea • confusion tiredness (lack of energy) • more frequent or more severe seizures headache Similar symptoms that are not related to low sodium may occur from taking oxcarbazepine oral suspension. You should tell your healthcare provider if you have any of these side effects and if they bother you or they do not go away.
Some other medicines can also cause low sodium in your blood. Be sure to tell your healthcare provider about all the other medicines that you are taking. Your healthcare provider may do blood tests to check your sodium levels during your treatment with oxcarbazepine oral suspension.
Oxcarbazepine may also cause allergic reactions or serious problems which may affect organs and other parts of your body like the liver or blood cells . You may or may not have a rash with these types of reactions. Call your healthcare provider right away if you have any of the following: swelling of your face, eyes, lips, or tongue • painful sores in the mouth or around your eyes trouble swallowing or breathing • yellowing of your skin or eyes a skin rash • unusual bruising or bleeding hives • severe fatigue or weakness fever, swollen glands, or sore throat that do not go away or come and go • severe muscle pain • frequent infections or infections that do not go away Many people who are allergic to carbamazepine are also allergic to oxcarbazepine.
Tell your healthcare provider if you are allergic to carbamazepine. Like other antiepileptic drugs, oxcarbazepine may cause suicidal thoughts or actions in a very small number of people, about 1 in 500. Call a healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying • trouble sleeping (insomnia) attempts to commit suicide • new or worse irritability new or worse depression • acting aggressive, being angry, or violent new or worse anxiety • acting on dangerous impulses feeling agitated or restless • an extreme increase in activity and talking (mania) panic attacks • other unusual changes in behavior or mood How can I watch for early symptoms of suicidal thoughts and actions?
Pay attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings. Keep all follow-up visits with your healthcare provider as scheduled. Call your healthcare provider between visits as needed, especially if you are worried about symptoms.
Do not stop taking oxcarbazepine oral suspension without first talking to a healthcare provider. Stopping oxcarbazepine oral suspension suddenly can cause serious problems. Stopping a seizure medicine suddenly in a patient who has epilepsy may cause seizures that will not stop (status epilepticus).
Suicidal thoughts or actions may be caused by things other than medicines. If you have suicidal thoughts or actions, your healthcare provider may check for other causes. What is oxcarbazepine oral suspension?
Oxcarbazepine oral suspension is a prescription medicine used: alone or with other medicines to treat partial-onset seizures in adults alone to treat partial-onset seizures in children 4 years of age and older with other medicines to treat partial-onset seizures in children 2 years of age and older It is not known if oxcarbazepine oral suspension is safe and effective for use alone to treat partial-onset seizures in children less than 4 years of age or for use with other medicines to treat partial-onset seizures in children less than 2 years of age.
Do not take oxca…