
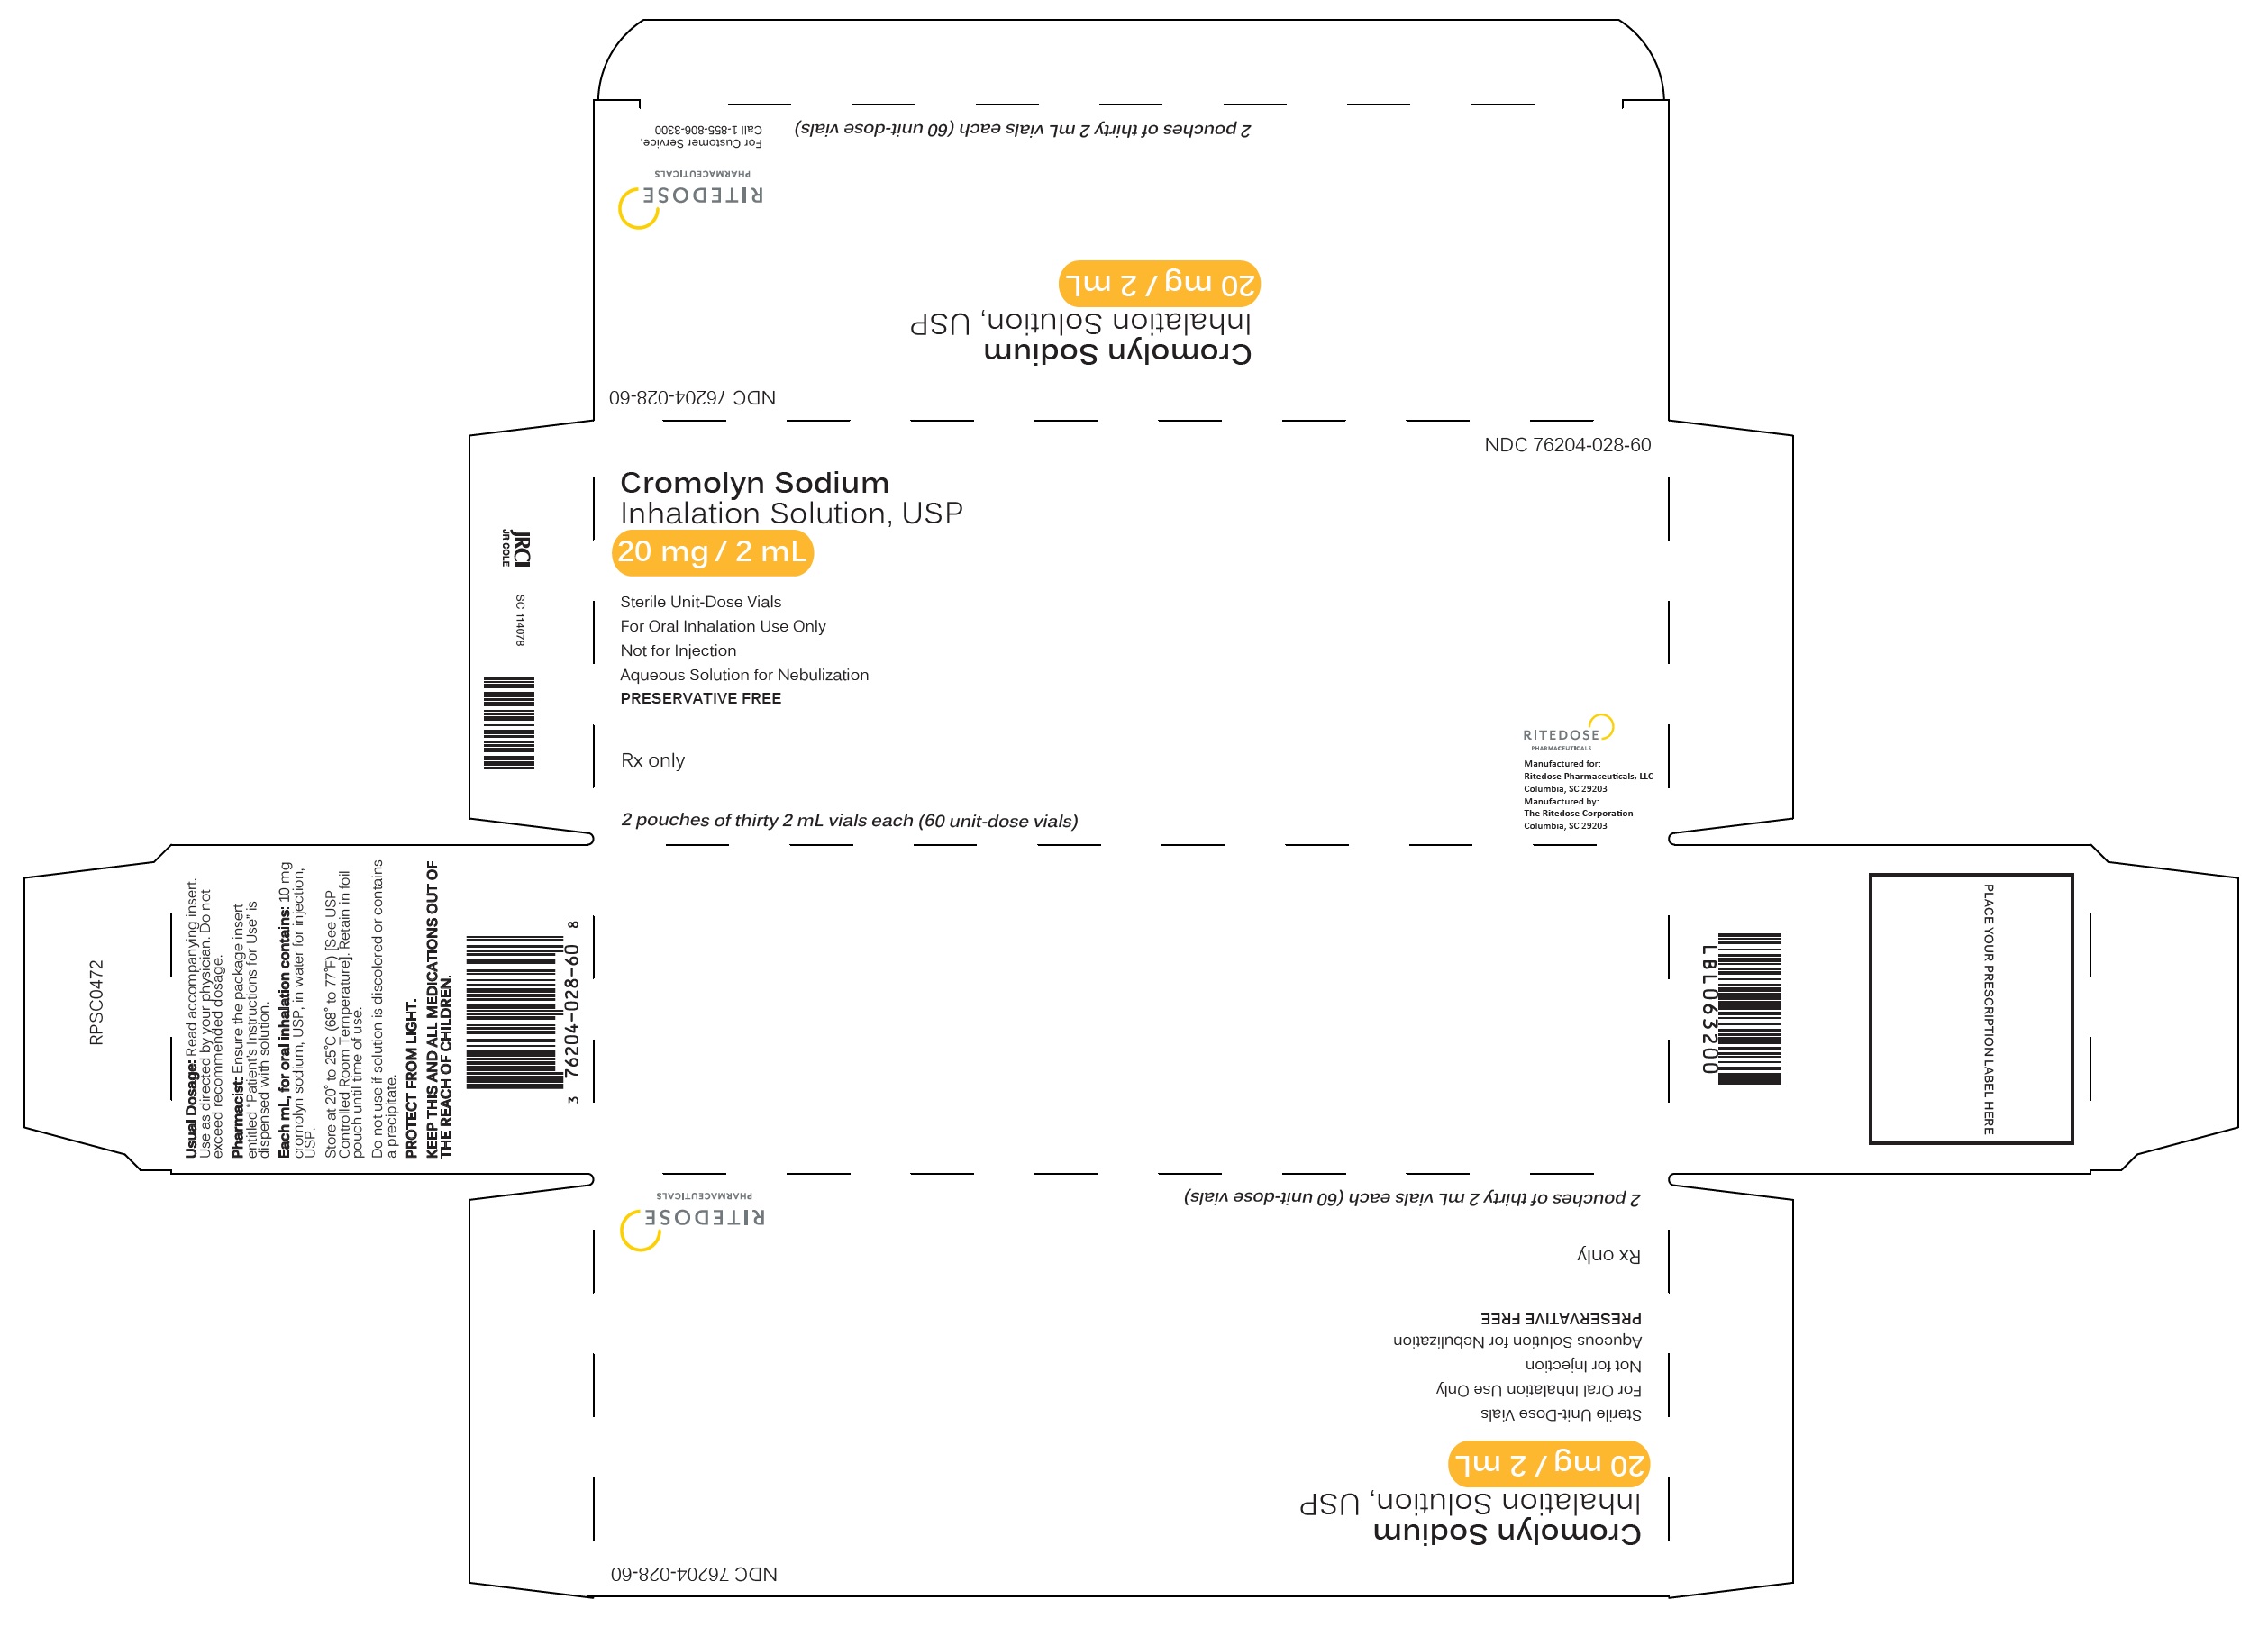
Cromolyn Sodium Inhalation Solution 20 mg/2mL Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Mast Cell Stabilizer class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Cromolyn oral inhalation is used to prevent the wheezing, shortness of breath, difficulty breathing, coughing, and chest tightness caused by asthma. It also is used to prevent breathing difficulties (bronchospasm) caused by exercise, cold and dry air, or by inhaling substances such as pet dander, pollen, dust mites, or chemicals, such as perfume. It works by preventing the release of substances that cause inflammation (swelling) in the air passages of the lungs.
Read the full MedlinePlus article ↗- No — and this is really important to understand. Cromolyn sodium is a preventive medicine only. It does not open your airways once they've tightened up. You should always have a se...
- Will this inhaler stop an asthma attack if I'm already having one?
- It can take several weeks of regular use before you feel the full benefit — though some people notice improvement sooner. The key is consistency. Taking it at the same times every...
- How long does it take before I notice it working?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
1 inactive ingredient listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.981 | $117.72 / 120 ml |
| Medicaid paysCMS SDUD · 12 mo | $1.01 | $121.63 / 120 ml |
| Medicare drug plans payPart D · Q2 2026 | $1.86 | $222.70 / 120 ml |
| Medicare Part B allowsASP · J7631 | $0.691 / J7631 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Cromolyn Sodium 20 mg/2mL 00172-6406-49 | Teva | 12 pouches | $0.981 | AN | Availability likely | — |
| Cromolyn Sodium 20 mg/2mL 42571-0350-09 | Micro | 12 ampules | $0.981 | AN | Discontinued | — |
| Cromolyn Sodium Inhalation Solution 20 mg/2mLthis 76204-0028-60 | Ritedose | 2 pouches | $0.981 | AN | Discontinued | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 76204-0028-60 You're viewing this | 2 POUCH in 1 CARTON (76204-028-60) / 30 AMPULE in 1 POUCH (76204-028-12) / 2 mL in 1 AMPULE | 2021-12-01 | Inactivated by FDA |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
Indications and Usage Cromolyn sodium inhalation solution USP is a prophylactic agent indicated in the management of patients with bronchial asthma. In patients whose symptoms are sufficiently frequent to require a continuous program of medication, cromolyn sodium inhalation solution USP is given by inhalation on a regular daily basis (see DOSAGE AND ADMINISTRATION ). The effect of cromolyn sodium is usually evident after several weeks of treatment, although some patients show an almost immediate response.
In patients who develop acute bronchoconstriction in response to exposure to exercise, toluene diisocyanate, environmental pollutants, etc., cromolyn sodium should be given shortly before exposure to the precipitating factor (see DOSAGE AND ADMINISTRATION ).
⏱️ Dosage and Administration ▾
Dosage and Administration For management of bronchial asthma in adults and pediatric patients (two years of age and over), the usual starting dosage is the contents of one vial administered by nebulization four times a day at regular intervals. Drug stability and safety of cromolyn sodium inhalation solution when mixed with other drugs in a nebulizer have not been established. Patients with chronic asthma should be advised that the effect of cromolyn sodium inhalation solution therapy is dependent upon its administration at regular intervals, as directed.
Cromolyn sodium inhalation solution should be introduced into the patient's therapeutic regimen when the acute episode has been controlled, the airway has been cleared and the patient is able to inhale adequately. For the prevention of acute bronchospasm which follows exercise or exposure to cold dry air, environmental agents (e.g., animal danders, toluene diisocyanate, pollutants), etc., the usual dose is the contents of one vial administered by nebulization shortly before exposure to the precipitating factor. It should be emphasized to the patient that the drug is poorly absorbed when swallowed and is not effective by this route of administration.
For additional information, see the accompanying leaflet entitled “Living a Full Life with Asthma” . Cromolyn Sodium Inhalation Solution Therapy in Relation to Other Treatments for Asthma: Non-steroidal agents: Cromolyn sodium inhalation solution should be added to the patient's existing treatment regimen (e.g., bronchodilators). When a clinical response to cromolyn sodium inhalation solution is evident, usually within two to four weeks, and if the asthma is under good control, an attempt may be made to decrease concomitant medication usage gradually.
If concomitant medications are eliminated or required on no more than a prn basis, the frequency of administration of cromolyn sodium inhalation solution may be titrated downward to the lowest level consistent with the desired effect. The usual decrease is from four to three vials per day. It is important that the dosage be reduced gradually to avoid exacerbation of asthma.
It is emphasized that in patients whose dosage has been titrated to fewer than four vials per day, an increase in the dose of cromolyn sodium inhalation solution and the introduction of, or increase in, symptomatic medications may be needed if the patient's clinical condition deteriorates. Corticosteroids: In patients chronically receiving corticosteroids for the management of bronchial asthma, the dosage should be maintained following the introduction of cromolyn sodium inhalation solution. If the patient improves, an attempt to decrease corticosteroids should be made.
Even if the corticosteroid-dependent patient fails to show symptomatic improvement following cromolyn sodium inhalation solution administration, the potential to reduce corticosteroids may nonetheless be present. Thus, gradual tapering of corticosteroid dosage may be attempted. It is important that the dose be reduced slowly, maintaining close supervision of the patient to avoid an exacerbation of asthma.
It should be borne in mind that prolonged corticosteroid therapy frequently causes an impairment in the activity of the hypothalamic-pituitary-adrenal axis and a reduction in the size of the adrenal cortex. A potentially critical degree of impairment or insufficiency may persist asymptomatically for some time even after gradual discontinuation of adrenocortical steroids. Therefore, if a patient is subjected to significant stress, such as a severe asthmatic attack, surgery, trauma or severe illness while being treated or within one year (occasionally up to two years) after corticosteroid treatment has been terminated, consideration should be given to reinstituting corticosteroid therapy.
When respiratory function is impaired, as may occur in severe exacerbation of asthma, a temporary increase in the amount of corticosteroids may be required to rega…
⛔ Contraindications ▾
Contraindications Cromolyn sodium inhalation solution is contraindicated in those patients who have shown hypersensitivity to cromolyn sodium.
⚠️ Warnings ▾
Warnings Cromolyn sodium inhalation solution has no role in the treatment of status asthmaticus. Anaphylactic reactions with cromolyn sodium administration have been reported rarely.
🤒 Adverse Reactions ▾
Adverse Reactions Clinical experience with the use of cromolyn sodium suggests that adverse reactions are rare events. The following adverse reactions have been associated with cromolyn sodium: cough, nasal congestion, nausea, sneezing, and wheezing. Other reactions have been reported in clinical trials; however, a causal relationship could not be established: drowsiness, nasal itching, nose bleed, nose burning, serum sickness, and stomachache.
In addition, adverse reactions have been reported with cromolyn sodium for inhalation capsules. The most common side effects are associated with inhalation of the powder and include transient cough (1 in 5 patients) and mild wheezing (1 in 25 patients). These effects rarely require treatment or discontinuation of the drug.
Information on the incidence of adverse reactions to cromolyn sodium for inhalation capsules has been derived from U.S. postmarketing surveillance experience. The following adverse reactions attributed to cromolyn sodium, based upon recurrence following readministration, have been reported in less than 1 in 10,000 patients: laryngeal edema, swollen parotid gland, angioedema, bronchospasm, joint swelling and pain, dizziness, dysuria and urinary frequency, nausea, cough, wheezing, headache, nasal congestion, rash, urticaria and lacrimation.
Other adverse reactions have been reported in less than 1 in 100,000 patients, and it is unclear whether these are attributable to the drug: anaphylaxis, nephrosis, periarteritic vasculitis, pericarditis, peripheral neuritis, pulmonary infiltrates with eosinophilia, polymyositis, exfoliative dermatitis, hemoptysis, anemia, myalgia, hoarseness, photodermatitis, and vertigo. Call your doctor for medical advice about side effects. You may report side effects to Ailex Pharmaceuticals, LLC at 1-888-514-4727 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug / Laboratory Test Interactions ▾
Drug Interaction During Pregnancy Cromolyn sodium and isoproterenol were studied following subcutaneous injections in pregnant mice. Cromolyn sodium alone in doses up to 540 mg/kg (approximately 27 times the maximum recommended adult human daily inhalation dose on a mg/m 2 basis) did not cause significant increases in resorptions or major malformations. Isoproterenol alone at a dose of 2.7 mg/kg (approximately 7 times the maximum recommended adult human daily inhalation dose on a mg/m 2 basis) increased both resorptions and malformations.
The addition of cromolyn sodium (approximately 27 times the maximum recommended adult human daily inhalation dose on a mg/m 2 basis) to isoproterenol (approximately 7 times the maximum recommended adult human daily inhalation dose on a mg/m 2 basis) appears to have increased the incidence of both resorptions and malformations.
🤰 Pregnancy ▾
Pregnancy: Teratogenic Effects, Pregnancy Category B Reproduction studies with cromolyn sodium administered subcutaneously to pregnant mice and rats at maximum daily doses of 540 mg/kg and 164 mg/kg, respectively, and intravenously to rabbits at a maximum daily dose of 485 mg/kg produced no evidence of fetal malformations. These doses represent approximately 27, 17, and 98 times, respectively, the maximum recommended adult human daily inhalation dose on a mg/m 2 basis. Adverse fetal effects (increased resorption and decreased fetal weight) were noted only at the very high parenteral doses that produced maternal toxicity.
There are, however, no adequate and well-controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients below the age of 2 years have not been established.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of cromolyn sodium inhalation solution did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients.
🆘 Overdosage ▾
Overdosage There is no clinical syndrome associated with an overdosage of cromolyn sodium. Acute toxicity testing in a wide variety of species has demonstrated that toxicity with cromolyn sodium occurs only with very high exposure levels, regardless of whether administration was parenteral, oral or by inhalation. Parenteral administration in mice, rats, guinea pigs, hamsters, and rabbits demonstrated a median lethal dose of approximately 4000 mg/kg.
Intravenous administration in monkeys also indicated a similar pattern of toxicity. The highest dose administered by the oral route in rats and mice was 8000 mg/kg, (approximately 261 and 130 times, respectively, the maximum recommended human daily inhalation dose on a mg/m 2 basis) and at this dose level no deaths occurred. By inhalation, even in long term studies, it proved impossible to achieve toxic dose levels of cromolyn sodium in a range of mammalian species.
🧬 Clinical Pharmacology ▾
Clinical Pharmacology In vitro and in vivo animal studies have shown that cromolyn sodium inhibits sensitized mast cell degranulation which occurs after exposure to specific antigens. Cromolyn sodium acts by inhibiting the release of mediators from mast cells. Studies show that cromolyn sodium indirectly blocks calcium ions from entering the mast cell, thereby preventing mediator release.
Cromolyn sodium inhibits both the immediate and non-immediate bronchoconstrictive reactions to inhaled antigen. Cromolyn sodium also attenuates bronchospasm caused by exercise, toluene diisocyanate, aspirin, cold air, sulfur dioxide, and environmental pollutants. Cromolyn sodium has no intrinsic bronchodilator or antihistamine activity.
After administration by inhalation, approximately 8% of the total cromolyn sodium dose administered is absorbed and rapidly excreted unchanged, approximately equally divided between urine and bile. The remainder of the dose is either exhaled or deposited in the oropharynx, swallowed and excreted via the alimentary tract.
📦 How Supplied / Storage and Handling ▾
How Supplied Cromolyn Sodium Inhalation Solution USP Unit-Dose 2 mL Vial is supplied as a colorless to pale yellow solution containing 20 mg cromolyn sodium, USP, in water for injection, USP, with 30 vials per foil pouch in a carton as listed below. 60 vials per carton (NDC 76204-028-60). Each vial is made from a low density polyethylene (LDPE) resin.
Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Do not use if solution is discolored or contains a precipitate. Retain in foil pouch until time of use.
PROTECT FROM LIGHT. KEEP THIS AND ALL MEDICATIONS OUT OF THE REACH OF CHILDREN. Manufactured for: Ritedose Pharmaceuticals, LLC Columbia, SC 29203 U.S.A.
Manufactured by: The Ritedose Corporation Columbia, SC 29203 U.S.A.
📋 Description ▾
Description The active ingredient of cromolyn sodium inhalation solution USP is cromolyn sodium, USP. It is an inhaled anti-inflammatory agent for the preventive management of asthma. Cromolyn sodium, USP is chemically designated as disodium 5,5'- [(2-hydroxytrimethylene)dioxy] bis [4-oxo-4H-1-benzopyran-2-carboxylate].
The molecular formula is C23H14Na2O11; the molecular weight is 512.34. Cromolyn sodium, USP is a water-soluble, odorless, white, hydrated crystalline powder. It is tasteless at first, but leaves a slightly bitter aftertaste.
Cromolyn sodium inhalation solution USP is clear, colorless to pale yellow, sterile and has a target pH of 5.5. The structural formula is: Each 2 mL vial for oral inhalation use only contains 20 mg cromolyn sodium, USP in water for injection, USP. figure-01
💬 Information for Patients ▾
Information for Patients Cromolyn sodium is to be taken as directed by the physician. Because it is preventive medication, it may take up to four weeks before the patient experiences maximum benefit. Cromolyn sodium should be used in a power-driven nebulizer with an adequate airflow rate equipped with a suitable face mask or mouthpiece.
Drug stability and safety of cromolyn sodium inhalation solution when mixed with other drugs in a nebulizer have not been established. For additional information, see the accompanying leaflet entitled Living a Full Life with Asthma.
Living a Full Life with Asthma Patient Instructions Cromolyn Sodium Inhalation Solution, USP You or your child may be among the millions of Americans who have asthma. For most patients, asthma need not limit your lifestyle, if you closely follow the asthma management plan your doctor provides you. Your doctor has given you this instruction sheet to help you learn more about asthma and ways to control it.
WHAT IS ASTHMA? Asthma is a disease that causes patients to have difficulty breathing. Asthma “attacks” occur when the air passages (airways) to the lungs close up, blocking air from passing through.
The closing up is caused by two things: The muscles around the airways tighten (constrict) making the airway narrower, and The passage lining swells and produces larger amounts of mucus (a sticky liquid normally found in airways). This swelling is caused by a certain type of inflammation that can build up in the airways of patients with asthma. Inflammation and the airway sensitivity that results from it cause further attacks to occur. figure 02 WHAT CAUSES THESE ATTACKS?
Asthma experts know that patients with asthma have attacks because their airways are inflamed and over reactive. Their lungs become super-sensitive to certain irritants or “triggers”, such as cold dry air, pollen, smoke, or cat dander. In the presence of such triggers, someone with asthma may have an attack, and attacks may occur more often.
Asthma triggers fall into 6 categories: Substances that cause allergies (pollens, animal dander, molds, house dust, some foods and medicines) Infections that affect breathing (colds, flu) Emotional stress (difficult situations at home, school, or work) Strenuous exercise Irritating gases (chlorine, perfume, tobacco smoke) Sudden changes in temperature or humidity figure 03 HOW TO PREVENT ASTHMA ATTACKS No medicine or procedure will “cure” asthma. The key to asthma relief, therefore, is to prevent attacks and to relieve attack symptoms if they do occur.
A successful prevention plan* will do the following: Keep your activities, including exercise, at normal levels. Keep your lungs functioning normally or at a near-normal level. Prevent symptoms such as coughing or breathlessness that can keep you up at night, or occur in the early morning hours, or after exertion.
Prevent asthma attacks from happening. Avoid unpleasant or harmful side effects that may result from using asthma medicine. The best way to prevent asthma attacks is to avoid the triggers that bother you or your child.
Try to identify the specific things that cause problems for you - things such as certain foods, house dust, or animal dander. Avoiding these triggers may be difficult or unpleasant. You may need to find a new home for a family pet or remove a carpet or a favorite stuffed toy.
Even though these steps are difficult, they may be necessary in order to help prevent asthma attacks. If house dust is a trigger, remove dust-collectors such as feather pillows, mattresses, quilts, and carpets from the bedroom. Mattresses and pillows can be covered with allergen-free covers.
If a certain food triggers attacks, keep it out of your diet. Irritants in the air can be reduced by air conditioning, electrostatic air filters, or small-pore (HEPA) filters. Be careful of certain medicines.
Aspirin and aspirin-like pain relievers, for example, can trigger attacks in some people and should be avoided if they do. *…