
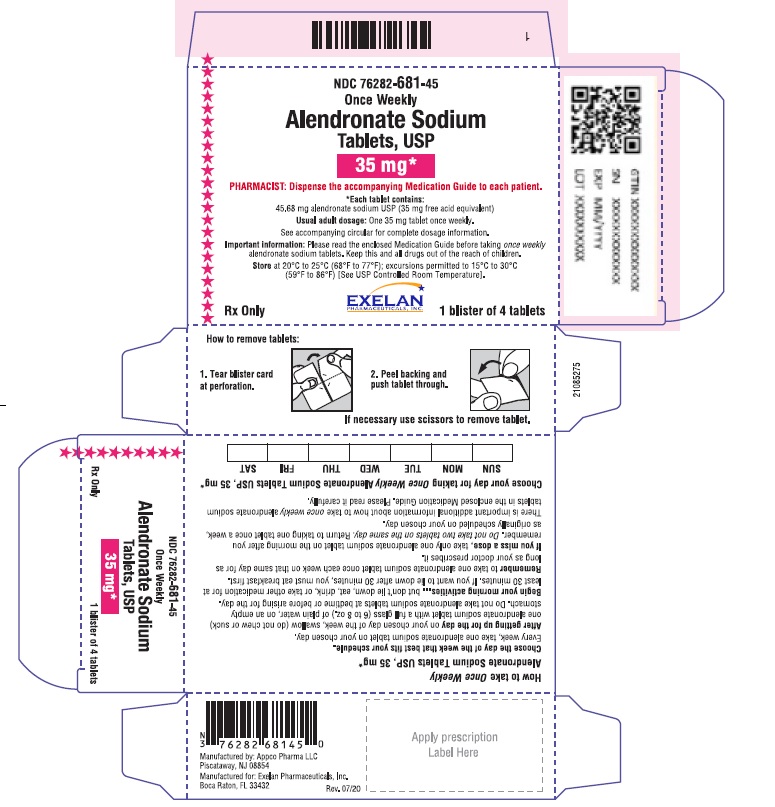
ALENDRONATE SODIUM 35 mg Tablet, 12-count
Other active recalls for Alendronate Sodium (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Bisphosphonate class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Unfortunately, going back to bed after taking it is one of the biggest things to avoid. Alendronate can irritate the lining of your esophagus — the tube that connects your mouth to...
- Why do I have to stay sitting or standing for 30 minutes after taking alendronate? Can't I just go back to bed?
- It matters a lot — studies have shown that taking alendronate with coffee or orange juice reduces how much of the medication your body absorbs by about 60%. That means the drug may...
- Why does it matter so much that I take it with plain water? What happens if I use coffee or juice?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Alendronate Sodium — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.2763 | $3.32 / 12 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Alendronate Sodium 35 mg 16714-0632-01 | NorthStar | 4 tablets | $0.284 | AB | Availability likely | — |
| Alendronate Sodium 35 mg 65862-0328-04 | Aurobindo | 4 tablets | $0.284 | AB | Availability likely | — |
| Alendronate Sodium 35 mg 69097-0223-76 | Cipla | 12 tablets | $0.284 | AB | Availability likely | — |
| Alendronate Sodium 35 mg 00115-1679-26 | Amneal | 12 tablets | $0.337 | — | FDA listed | — |
| Alendronate 35 mg 10135-0718-12 | Marlex | 12 tablets | — | AB | FDA listed | — |
| Alendronate Sodium 35 mg 50090-5474-00 | A-S | 4 tablets | — | AB | FDA listed | — |
| Alendronate Sodium 35 mg 60723-0207-31 | Hangzhou | 4 tablets | — | — | FDA listed | — |
| Alendronate Sodium 35 mg 64980-0341-12 | Rising | 12 tablets | — | AB | FDA listed | — |
| Alendronate Sodium 35 mg 70518-1192-01 | REMEDYREPACK | 12 tablets | — | AB | FDA listed | — |
| Alendronate Sodium 35 mgthis 76282-0681-46 | EXELAN | 12 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 76282-0681-46 You're viewing this | 3 BLISTER PACK in 1 CARTON (76282-681-46) / 4 TABLET in 1 BLISTER PACK (76282-681-45) | 2021-02-02 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Alendronate sodium is a bisphosphonate indicated for: Treatment and prevention of osteoporosis in postmenopausal women ( 1.1 , 1.2 ) Treatment to increase bone mass in men with osteoporosis ( 1.3 ) Treatment of glucocorticoid-induced osteoporosis ( 1.4 ) Treatment of Paget's disease of bone ( 1.5 ) Limitations of use: Optimal duration of use has not been determined. For patients at low- risk for fracture, consider drug discontinuation after 3 to 5 years of use. (1.6)
1.1Treatment of Osteoporosis in Postmenopausal Women Alendronate sodium tablets, USP are indicated for the treatment of osteoporosis in postmenopausal women. In postmenopausal women, alendronate sodium tablets, USP increases bone mass and reduces the incidence of fractures, including those of the hip and spine (vertebral compression fractures). [See Clinical Studies ( 14.1 ).]
1.2Prevention of Osteoporosis in Postmenopausal Women Alendronate sodium tablets, USP are indicated for the prevention of postmenopausal osteoporosis [see Clinical Studies ( 14.2 )].
1.3Treatment to Increase Bone Mass in Men with Osteoporosis Alendronate sodium tablets, USP are indicated for treatment to increase bone mass in men with osteoporosis [see Clinical Studies ( 14.3 )].
1.4Treatment of Glucocorticoid-Induced Osteoporosis Alendronate sodium tablets, USP are indicated for the treatment of glucocorticoid-induced osteoporosis in men and women receiving glucocorticoids in a daily dosage equivalent to 7.5 mg or greater of prednisone and who have low bone mineral density [see Clinical Studies ( 14.4 )].
1.5Treatment of Paget's Disease of Bone Alendronate sodium tablets, USP are indicated for the treatment of Paget's disease of bone in men and women. Treatment is indicated in patients with Paget's disease of bone who have alkaline phosphatase at least two times the upper limit of normal, or those who are symptomatic, or those at risk for future complications from their disease. [See Clinical Studies ( 14.5 ).]
1.6Important Limitations of Use The optimal duration of use has not been determined. The safety and effectiveness of alendronate sodium for the treatment of osteoporosis are based on clinical data of four years duration. All patients on bisphosphonate therapy should have the need for continued therapy re-evaluated on a periodic basis.
Patients at low-risk for fracture should be considered for drug discontinuation after 3 to 5 years of use. Patients who discontinue therapy should have their risk for fracture re-evaluated periodically.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Treatment of osteoporosis in postmenopausal women and in men: 10 mg daily or 70 mg (tablet) once weekly. ( 2.1 , 2.3 ) Prevention of osteoporosis in postmenopausal women: 5 mg daily or 35 mg once weekly. ( 2.2 ) Glucocorticoid-induced osteoporosis: 5 mg daily; or 10 mg daily in postmenopausal women not receiving estrogen.
( 2.4 ) Paget's disease: 40 mg daily for six months. ( 2.5 ) Instruct patients to: ( 2.6 ) o Swallow tablets whole with 6-8 ounces plain water at least 30 minutes before the first food, drink, or medication of the day. o Not lie down for at least 30 minutes after taking alendronate sodium tablets and until after food.
2.1Treatment of Osteoporosis in Postmenopausal Women The recommended dosage is: ●one 70 mg tablet once weekly or ●one 10 mg tablet once daily
2.2Prevention of Osteoporosis in Postmenopausal Women The recommended dosage is: • one 35 mg tablet once weekly or • one 5 mg tablet once daily
2.3Treatment to Increase Bone Mass in Men with Osteoporosis The recommended dosage is: • one 70 mg tablet once weekly or • one 10 mg tablet once daily
2.4Treatment of Glucocorticoid-Induced Osteoporosis The recommended dosage is one 5 mg tablet once daily, except for postmenopausal women not receiving estrogen, for whom the recommended dosage is one 10 mg tablet once daily.
2.5Treatment of Paget's Disease of Bone The recommended treatment regimen is 40 mg once a day for six months. Re-treatment of Paget's Disease Re-treatment with alendronate sodium tablets, may be considered, following a six-month post-treatment evaluation period in patients who have relapsed, based on increases in serum alkaline phosphatase, which should be measured periodically. Re-treatment may also be considered in those who failed to normalize their serum alkaline phosphatase.
2.6Important Administration Instructions Instruct patients to do the following: Take alendronate sodium tablets at least one-half hour before the first food, beverage, or medication of the day with plain water only [see Patient Counseling Information ( 17.2 )]. Other beverages (including mineral water), food, and some medications are likely to reduce the absorption of alendronate sodium tablets [see Drug Interactions ( 7.1 )]. Waiting less than 30 minutes, or taking alendronate sodium tablets with food, beverages (other than plain water) or other medications will lessen the effect of alendronate sodium tablets, by decreasing its absorption into the body.
Take alendronate sodium tablets upon arising for the day. To facilitate delivery to the stomach and thus reduce the potential for esophageal irritation, an alendronate sodium tablet should be swallowed with a full glass of water (6-8 ounces). Patients should not lie down for at least 30 minutes and until after their first food of the day.
Alendronate sodium tablets should not be taken at bedtime or before arising for the day. Failure to follow these instructions may increase the risk of esophageal adverse experiences [see Warnings and Precautions ( 5.1 ) and Patient Counseling Information ( 17.2 )] .
2.7Recommendations for Calcium and Vitamin D Supplementation Instruct patients to take supplemental calcium if dietary intake is inadequate [see Warnings and Precautions ( 5.2 )] . Patients at increased risk for vitamin D insufficiency (e.g., over the age of 70 years, nursing home-bound, or chronically ill) may need vitamin D supplementation. Patients with gastrointestinal malabsorption syndromes may require higher doses of vitamin D supplementation and measurement of 25-hydroxyvitamin D should be considered.
Patients treated with glucocorticoids should receive adequate amounts of calcium and vitamin D.
2.8Administration Instructions for Missed Doses If a once-weekly dose of alendronate sodium tablets is missed, instruct patients to take one dose on the morning after they remember. They should not take two doses on the same day but should return to taking one dose once a week, as original…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 5 mg, 10 mg, 35 mg, 40 mg and 70 mg ( 3 ) Alendronate Sodium Tablets, USP 5 mg are white, circular, biconvex tablets debossed with 'C234' on one side and plain on the other side. Alendronate Sodium Tablets, USP 10 mg are white, oval shaped, biconvex tablets debossed with 'C235' on one side and plain on the other side. Alendronate Sodium Tablets, USP 35 mg are white, capsule shaped, biconvex tablets debossed with 'C223' on one side and plain on the other side.
Alendronate Sodium Tablets, USP 40 mg are white, circular, biconvex tablets debossed with 'C236' on one side and plain on the other side. Alendronate Sodium Tablets, USP 70 mg are white, capsule shaped, biconvex tablets debossed with 'C224' on one side and plain on the other side.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Abnormalities of the esophagus which delay emptying such as stricture or achalasia ( 4 , 5.1 ) Inability to stand/sit upright for at least 30 minutes ( 2.6 , 4 , 5.1 ) Hypocalcemia ( 4 , 5.2 ) Hypersensitivity to any component of this product ( 4 , 6.2 ) Alendronate sodium tablets are contraindicated in patients with the following conditions: Abnormalities of the esophagus which delay esophageal emptying such as stricture or achalasia [see Warnings and Precautions ( 5.1 )] Inability to stand or sit upright for at least 30 minutes [see Dosage and Administration ( 2.6 ); Warnings and Precautions ( 5.1 )] Hypocalcemia [see Warnings and Precautions ( 5.2 )] Hypersensitivity to any component of this product.
Hypersensitivity reactions including urticaria and angioedema have been reported [see Adverse Reactions ( 6.2 )] .
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Upper Gastrointestinal Adverse Reactions can occur. Instruct patients to follow dosing instructions. Discontinue if new or worsening symptoms occur.
( 5.1 ) Hypocalcemia can worsen and must be corrected prior to use. ( 5.2 ) Severe Bone, Joint, Muscle Pain may occur. Discontinue use if severe symptoms develop.
( 5.3 ) Osteonecrosis of the Jaw has been reported. ( 5.4 ) Atypical Femur Fractures have been reported. Patients with new thigh or groin pain should be evaluated to rule out an incomplete femoral fracture.
( 5.5 )
5.1Upper Gastrointestinal Adverse Reactions Alendronate sodium, like other bisphosphonates administered orally, may cause local irritation of the upper gastrointestinal mucosa. Because of these possible irritant effects and a potential for worsening of the underlying disease, caution should be used when alendronate sodium is given to patients with active upper gastrointestinal problems (such as known Barrett's esophagus, dysphagia, other esophageal diseases, gastritis, duodenitis, or ulcers). Esophageal adverse experiences, such as esophagitis, esophageal ulcers and esophageal erosions, occasionally with bleeding and rarely followed by esophageal stricture or perforation, have been reported in patients receiving treatment with oral bisphosphonates including alendronate sodium.
In some cases these have been severe and required hospitalization. Physicians should therefore be alert to any signs or symptoms signaling a possible esophageal reaction and patients should be instructed to discontinue alendronate sodium and seek medical attention if they develop dysphagia, odynophagia, retrosternal pain or new or worsening heartburn. The risk of severe esophageal adverse experiences appears to be greater in patients who lie down after taking oral bisphosphonates including alendronate sodium and/or who fail to swallow oral bisphosphonates including alendronate sodium with the recommended full glass (6-8 ounces) of water, and/or who continue to take oral bisphosphonates including alendronate sodium after developing symptoms suggestive of esophageal irritation.
Therefore, it is very important that the full dosing instructions are provided to, and understood by, the patient [see Dosage and Administration ( 2.6 )] . In patients who cannot comply with dosing instructions due to mental disability, therapy with alendronate sodium should be used under appropriate supervision. There have been post-marketing reports of gastric and duodenal ulcers with oral bisphosphonate use, some severe and with complications, although no increased risk was observed in controlled clinical trials [see Adverse Reactions ( 6.2 )] .
5.2Mineral Metabolism Hypocalcemia must be corrected before initiating therapy with alendronate sodium [see Contraindications ( 4 )]. Other disorders affecting mineral metabolism (such as vitamin D deficiency) should also be effectively treated. In patients with these conditions, serum calcium and symptoms of hypocalcemia should be monitored during therapy with alendronate sodium.
Presumably due to the effects of alendronate sodium on increasing bone mineral, small, asymptomatic decreases in serum calcium and phosphate may occur, especially in patients with Paget's disease, in whom the pretreatment rate of bone turnover may be greatly elevated, and in patients receiving glucocorticoids, in whom calcium absorption may be decreased. Ensuring adequate calcium and vitamin D intake is especially important in patients with Paget's disease of bone and in patients receiving glucocorticoids.
5.3Musculoskeletal Pain In post-marketing experience, severe and occasionally incapacitating bone, joint, and/or muscle pain has been reported in patients taking bisphosphonates that are approved for the prevention and treatment of osteoporosis [see Adverse Reactions ( 6.2 )]. This category of drugs includes alendronate sodium. Most of the patients were postmenopausal women. The time to onset of symptoms varied fr…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (greater than or equal to 3%) are abdominal pain, acid regurgitation, constipation, diarrhea, dyspepsia, musculoskeletal pain, nausea. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Exelan Pharmaceuticals, Inc., at 1-866-604-3268 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Treatment of Osteoporosis in Postmenopausal Women Daily Dosing The safety of alendronate sodium in the treatment of postmenopausal osteoporosis was assessed in four clinical trials that enrolled 7453 women aged 44-84 years.
Study 1 and Study 2 were identically designed, three-year, placebo-controlled, double-blind, multicenter studies (United States and Multinational n=994); Study 3 was the three-year vertebral fracture cohort of the Fracture Intervention Trial [FIT] (n=2027) and Study 4 was the four-year clinical fracture cohort of FIT (n=4432). Overall, 3620 patients were exposed to placebo and 3432 patients exposed to alendronate sodium. Patients with pre-existing gastrointestinal disease and concomitant use of non-steroidal anti-inflammatory drugs were included in these clinical trials.
In Study 1 and Study 2 all women received 500 mg elemental calcium as carbonate. In Study 3 and Study 4 all women with dietary calcium intake less than 1000 mg per day received 500 mg calcium and 250 international units Vitamin D per day. Among patients treated with alendronate 10 mg or placebo in Study 1 and Study 2, and all patients in Study 3 and Study 4, the incidence of all-cause mortality was 1.8% in the placebo group and 1.8% in the alendronate sodium group.
The incidence of serious adverse event was 30.7% in the placebo group and 30.9% in the alendronate sodium group. The percentage of patients who discontinued the study due to any clinical adverse event was 9.5% in the placebo group and 8.9% in the alendronate sodium group. Adverse reactions from these studies considered by the investigators as possibly, probably, or definitely drug related in greater than or equal to 1% of patients treated with either alendronate sodium or placebo are presented in Table 1.
Table 1: Osteoporosis Treatment Studies in Postmenopausal Women Adverse Reactions Considered Possibly, Probably, or Definitely Drug Related by the Investigators and Reported in Greater Than or Equal to 1% of Patients * 10 mg/day for three years † 5 mg/day for 2 years and 10 mg/day for either 1 or 2 additional years United States/Multinational Studies Fracture Intervention Trial Alendronate sodium * % (n=196) Placebo % (n=397) Alendronate sodium † % (n=3236) Placebo % (n=3223) Gastrointestinal abdominal pain 6.6 4.8 1.5 1.5 nausea 3.6 4.0 1.1 1.5 dyspepsia 3.6 3.5 1.1 1.2 constipation 3.1 1.8 0.0 0.2 diarrhea 3.1 1.8 0.6 0.3 flatulence 2.6 0.5 0.2 0.3 acid regurgitation 2.0 4.3 1.1 0.9 esophageal ulcer 1.5 0.0 0.1 0.1 vomiting 1.0 1.5 0.2 0.3 dysphagia 1.0 0.0 0.1 0.1 abdominal distention 1.0 0.8 0.0 0.0 gastritis 0.5 1.3 0.6
0.7Musculoskeletal musculoskeletal (bone, muscle or joint) pain 4.1 2.5 0.4 0.3 muscle cramp 0.0 1.0 0.2
0.1Nervous System/Psychiatric headache 2.6 1.5 0.2 0.2 dizziness 0.0 1.0 0.0
0.1Special Senses taste perversion 0.5 1.0 0.1
0.0Rash and erythema have occurred. Gastrointestinal Adverse Reactions: One patient treated with alendronate sodium (10 mg/day), who had a history of peptic ulcer disease and gastrectomy and who was taking concomitant aspirin, developed an anastomotic ulcer with mild hemorrhage, which was considered drug related. Aspirin and alendronate sodium were discontinued and the patient recovered.
In the Study 1 and Study 2 populations, 49-54% had a history of gastrointestinal disorders at baseline and 54-89%…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Calcium supplements, antacids, or oral medications containing multivalent cations interfere with absorption of alendronate. ( 2.6 , 7.1 ) Use caution when co-prescribing aspirin/nonsteroidal anti-inflammatory drugs that may worsen gastrointestinal irritation. ( 7.2 , 7.3 )
7.1Calcium Supplements/Antacids Co-administration of alendronate sodium and calcium, antacids, or oral medications containing multivalent cations will interfere with absorption of alendronate sodium. Therefore, instruct patients to wait at least one-half hour after taking alendronate sodium before taking any other oral medications.
7.2Aspirin In clinical studies, the incidence of upper gastrointestinal adverse events was increased in patients receiving concomitant therapy with daily doses of alendronate sodium greater than 10 mg and aspirin-containing products.
7.3Nonsteroidal Anti-Inflammatory Drugs Alendronate sodium may be administered to patients taking nonsteroidal anti-inflammatory drugs (NSAIDs). In a 3-year, controlled, clinical study (n=2027) during which a majority of patients received concomitant NSAIDs, the incidence of upper gastrointestinal adverse events was similar in patients taking alendronate sodium 5 or 10 mg/day compared to those taking placebo. However, since NSAID use is associated with gastrointestinal irritation, caution should be used during concomitant use with alendronate sodium.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Discontinue when pregnancy is recognized. ( 8.1 ) Alendronate sodium is not indicated for use in pediatric patients. ( 8.4 ) Alendronate sodium is not recommended in patients with renal impairment (creatinine clearance less than 35 mL/min). ( 5.6 , 8.6 )
8.1Pregnancy Risk Summary Available data on the use of alendronate sodium in pregnant women are insufficient to inform a drug-associated risk of adverse maternal or fetal outcomes. Discontinue alendronate sodium when pregnancy is recognized. In animal reproduction studies, daily oral administration of alendronate to rats from before mating through the end of gestation or lactation showed decreased postimplantation survival and decreased pup body weight gain starting at doses equivalent to less than half of the highest recommended 40 mg clinical daily dose (based on body surface area, mg/m 2 ).
Oral administration of alendronate to rats during organogenesis resulted in reduced fetal ossification starting at doses 3 times the 40 mg clinical daily dose. No similar fetal effects were observed in pregnant rabbits dosed orally during organogenesis at doses equivalent to approximately 10 times the 40 mg clinical daily dose. Delayed or failed delivery of offspring, protracted parturition, and late pregnancy maternal and fetal deaths due to maternal hypocalcemia occurred in rats at oral doses as low as one tenth the 40 mg clinical daily dose ( see Data) .
Bisphosphonates are incorporated into the bone matrix, from which they are gradually released over a period of years. The amount of bisphosphonate incorporated into adult bone and available for release into the systemic circulation is directly related to the dose and duration of bisphosphonate use. Consequently, based on the mechanism of action of bisphosphonates, there is a potential risk of fetal harm, predominantly skeletal, if a woman becomes pregnant after completing a course of bisphosphonate therapy.
The impact of variables such as time between cessation of bisphosphonate therapy to conception, the particular bisphosphonate used, and the route of administration (intravenous versus oral) on the risk has not been studied. The estimated background risk of major birth defects and miscarriage for the indicated population(s) is unknown. All pregnancies have a background risk of birth defects, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Animal Data Reproduction studies in rats dosed orally from before mating to the end of gestation or lactation showed decreased postimplantation survival starting at 2 mg/kg/day and decreased body weight gain starting at 1 mg/kg/day, doses equivalent to less than half the 40 mg clinical daily dose based on body surface area, mg/m 2 . Incidence of incomplete fetal ossification in vertebral, skull, and sternebral bones were increased in rats dosed orally during organogenesis starting at 10 mg/kg/day (approximately 3 times the 40 mg clinical daily dose).
No similar fetal effects were observed in pregnant rabbits dosed orally during organogenesis at up to 35 mg/kg/day (equivalent to approximately 10 times the 40 mg clinical daily dose). Both total and ionized calcium decreased in pregnant rats dosed orally with 15 mg/kg/day alendronate (approximately 4 times the 40 mg clinical daily dose) resulting in delays and failures of delivery. Protracted parturition due to maternal hypocalcemia was observed when rats were treated from before mating through gestation starting at 0.5 mg/kg/day (approximately one tenth the 40 mg clinical daily dose).
Maternotoxicity (late pregnancy deaths) also occurred in the female rats treated orally with 15 mg/kg/day (approximately 4 times the 40 mg clinical daily dose) for varying gestational time periods. These maternal deaths were lessened but not eliminated by cessation of…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data on the use of alendronate sodium in pregnant women are insufficient to inform a drug-associated risk of adverse maternal or fetal outcomes. Discontinue alendronate sodium when pregnancy is recognized. In animal reproduction studies, daily oral administration of alendronate to rats from before mating through the end of gestation or lactation showed decreased postimplantation survival and decreased pup body weight gain starting at doses equivalent to less than half of the highest recommended 40 mg clinical daily dose (based on body surface area, mg/m 2 ).
Oral administration of alendronate to rats during organogenesis resulted in reduced fetal ossification starting at doses 3 times the 40 mg clinical daily dose. No similar fetal effects were observed in pregnant rabbits dosed orally during organogenesis at doses equivalent to approximately 10 times the 40 mg clinical daily dose. Delayed or failed delivery of offspring, protracted parturition, and late pregnancy maternal and fetal deaths due to maternal hypocalcemia occurred in rats at oral doses as low as one tenth the 40 mg clinical daily dose ( see Data) .
Bisphosphonates are incorporated into the bone matrix, from which they are gradually released over a period of years. The amount of bisphosphonate incorporated into adult bone and available for release into the systemic circulation is directly related to the dose and duration of bisphosphonate use. Consequently, based on the mechanism of action of bisphosphonates, there is a potential risk of fetal harm, predominantly skeletal, if a woman becomes pregnant after completing a course of bisphosphonate therapy.
The impact of variables such as time between cessation of bisphosphonate therapy to conception, the particular bisphosphonate used, and the route of administration (intravenous versus oral) on the risk has not been studied. The estimated background risk of major birth defects and miscarriage for the indicated population(s) is unknown. All pregnancies have a background risk of birth defects, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Animal Data Reproduction studies in rats dosed orally from before mating to the end of gestation or lactation showed decreased postimplantation survival starting at 2 mg/kg/day and decreased body weight gain starting at 1 mg/kg/day, doses equivalent to less than half the 40 mg clinical daily dose based on body surface area, mg/m 2 . Incidence of incomplete fetal ossification in vertebral, skull, and sternebral bones were increased in rats dosed orally during organogenesis starting at 10 mg/kg/day (approximately 3 times the 40 mg clinical daily dose).
No similar fetal effects were observed in pregnant rabbits dosed orally during organogenesis at up to 35 mg/kg/day (equivalent to approximately 10 times the 40 mg clinical daily dose). Both total and ionized calcium decreased in pregnant rats dosed orally with 15 mg/kg/day alendronate (approximately 4 times the 40 mg clinical daily dose) resulting in delays and failures of delivery. Protracted parturition due to maternal hypocalcemia was observed when rats were treated from before mating through gestation starting at 0.5 mg/kg/day (approximately one tenth the 40 mg clinical daily dose).
Maternotoxicity (late pregnancy deaths) also occurred in the female rats treated orally with 15 mg/kg/day (approximately 4 times the 40 mg clinical daily dose) for varying gestational time periods. These maternal deaths were lessened but not eliminated by cessation of treatment. Calcium supplementation in the drinking water or by subcutaneous minipump to rats dosed orally with 15 mg/kg/day alendronate could not ameliorate the hypocalcemia or prevent the dystocia-related maternal and neonatal deaths.
However, intravenous calcium supplementation prevented mater…
🧒 Pediatric Use ▾
8.4Pediatric Use Alendronate sodium is not indicated for use in pediatric patients. The safety and efficacy of alendronate sodium were examined in a randomized, double-blind, placebo-controlled two-year study of 139 pediatric patients, aged 4-18 years, with severe osteogenesis imperfecta (OI). One-hundred-and-nine patients were randomized to 5 mg alendronate sodium daily (weight less than 40 kg) or 10 mg alendronate sodium daily (weight greater than or equal to 40 kg) and 30 patients to placebo.
The mean baseline lumbar spine BMD Z-score of the patients was -4.5. The mean change in lumbar spine BMD Z-score from baseline to Month 24 was 1.3 in the alendronate sodium-treated patients and 0.1 in the placebo-treated patients. Treatment with alendronate sodium did not reduce the risk of fracture.
Sixteen percent of the alendronate sodium patients who sustained a radiologically-confirmed fracture by Month 12 of the study had delayed fracture healing (callus remodeling) or fracture non-union when assessed radiographically at Month 24 compared with 9% of the placebo-treated patients. In alendronate sodium-treated patients, bone histomorphometry data obtained at Month 24 demonstrated decreased bone turnover and delayed mineralization time; however, there were no mineralization defects. There were no statistically significant differences between the alendronate sodium and placebo groups in reduction of bone pain.
The oral bioavailability in children was similar to that observed in adults. The overall safety profile of alendronate sodium in osteogenesis imperfecta patients treated for up to 24 months was generally similar to that of adults with osteoporosis treated with alendronate sodium. However, there was an increased occurrence of vomiting in osteogenesis imperfecta patients treated with alendronate sodium compared to placebo.
During the 24-month treatment period, vomiting was observed in 32 of 109 (29.4%) patients treated with alendronate sodium and 3 of 30 (10%) patients treated with placebo. In a pharmacokinetic study, 6 of 24 pediatric osteogenesis imperfecta patients who received a single oral dose of alendronate sodium 35 or 70 mg developed fever, flu-like symptoms, and/or mild lymphocytopenia within 24 to 48 hours after administration. These events, lasting no more than 2 to 3 days and responding to acetaminophen, are consistent with an acute-phase response that has been reported in patients receiving bisphosphonates, including alendronate sodium. [See Adverse Reactions ( 6.2 ).]
🧓 Geriatric Use ▾
8.5Geriatric Use Of the patients receiving alendronate sodium in the Fracture Intervention Trial (FIT), 71% (n=2302) were greater than or equal to 65 years of age and 17% (n=550) were greater than or equal to 75 years of age. Of the patients receiving alendronate sodium in the United States and Multinational osteoporosis treatment studies in women, osteoporosis studies in men, glucocorticoid-induced osteoporosis studies, and Paget's disease studies [see Clinical Studies ( 14.1 ), ( 14.3 ), ( 14.4 ), ( 14.5 )], 45%, 54%, 37%, and 70%, respectively, were 65 years of age or over.
No overall differences in efficacy or safety were observed between these patients and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE Significant lethality after single oral doses was seen in female rats and mice at 552 mg/kg (3256 mg/m 2 ) and 966 mg/kg (2898 mg/m 2 ), respectively. In males, these values were slightly higher, 626 and 1280 mg/kg, respectively. There was no lethality in dogs at oral doses up to 200 mg/kg (4000 mg/m 2 ).
No specific information is available on the treatment of overdosage with alendronate sodium. Hypocalcemia, hypophosphatemia, and upper gastrointestinal adverse events, such as upset stomach, heartburn, esophagitis, gastritis, or ulcer, may result from oral overdosage. Milk or antacids should be given to bind alendronate.
Due to the risk of esophageal irritation, vomiting should not be induced and the patient should remain fully upright. Dialysis would not be beneficial.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Animal studies have indicated the following mode of action. At the cellular level, alendronate shows preferential localization to sites of bone resorption, specifically under osteoclasts. The osteoclasts adhere normally to the bone surface but lack the ruffled border that is indicative of active resorption.
Alendronate does not interfere with osteoclast recruitment or attachment, but it does inhibit osteoclast activity. Studies in mice on the localization of radioactive [ 3 H]alendronate in bone showed about 10-fold higher uptake on osteoclast surfaces than on osteoblast surfaces. Bones examined 6 and 49 days after [ 3 H]alendronate administration in rats and mice, respectively, showed that normal bone was formed on top of the alendronate, which was incorporated inside the matrix.
While incorporated in bone matrix, alendronate is not pharmacologically active. Thus, alendronate must be continuously administered to suppress osteoclasts on newly formed resorption surfaces. Histomorphometry in baboons and rats showed that alendronate treatment reduces bone turnover (i.e., the number of sites at which bone is remodeled).
In addition, bone formation exceeds bone resorption at these remodeling sites, leading to progressive gains in bone mass.
12.2Pharmacodynamics Alendronate is a bisphosphonate that binds to bone hydroxyapatite and specifically inhibits the activity of osteoclasts, the bone-resorbing cells. Alendronate reduces bone resorption with no direct effect on bone formation, although the latter process is ultimately reduced because bone resorption and formation are coupled during bone turnover. Osteoporosis in Postmenopausal Women Osteoporosis is characterized by low bone mass that leads to an increased risk of fracture.
The diagnosis can be confirmed by the finding of low bone mass, evidence of fracture on x-ray, a history of osteoporotic fracture, or height loss or kyphosis, indicative of vertebral (spinal) fracture. Osteoporosis occurs in both males and females but is most common among women following the menopause, when bone turnover increases and the rate of bone resorption exceeds that of bone formation. These changes result in progressive bone loss and lead to osteoporosis in a significant proportion of women over age 50.
Fractures, usually of the spine, hip, and wrist, are the common consequences. From age 50 to age 90, the risk of hip fracture in white women increases 50-fold and the risk of vertebral fracture 15-to 30-fold. It is estimated that approximately 40% of 50-year-old women will sustain one or more osteoporosis-related fractures of the spine, hip, or wrist during their remaining lifetimes.
Hip fractures, in particular, are associated with substantial morbidity, disability, and mortality. Daily oral doses of alendronate (5, 20, and 40 mg for six weeks) in postmenopausal women produced biochemical changes indicative of dose-dependent inhibition of bone resorption, including decreases in urinary calcium and urinary markers of bone collagen degradation (such as deoxypyridinoline and crosslinked N-telopeptides of type I collagen). These biochemical changes tended to return toward baseline values as early as 3 weeks following the discontinuation of therapy with alendronate and did not differ from placebo after 7 months.
Long-term treatment of osteoporosis with alendronate sodium 10 mg/day (for up to five years) reduced urinary excretion of markers of bone resorption, deoxypyridinoline and cross-linked N-telopeptides of type I collagen, by approximately 50% and 70%, respectively, to reach levels similar to those seen in healthy premenopausal women. Similar decreases were seen in patients in osteoporosis prevention studies who received alendronate sodium 5 mg/day. The decrease in the rate of bone resorption indicated by these markers was evident as early as one month and at three to six months reached a plateau that was maintained for the entire duration of treatme…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Animal studies have indicated the following mode of action. At the cellular level, alendronate shows preferential localization to sites of bone resorption, specifically under osteoclasts. The osteoclasts adhere normally to the bone surface but lack the ruffled border that is indicative of active resorption.
Alendronate does not interfere with osteoclast recruitment or attachment, but it does inhibit osteoclast activity. Studies in mice on the localization of radioactive [ 3 H]alendronate in bone showed about 10-fold higher uptake on osteoclast surfaces than on osteoblast surfaces. Bones examined 6 and 49 days after [ 3 H]alendronate administration in rats and mice, respectively, showed that normal bone was formed on top of the alendronate, which was incorporated inside the matrix.
While incorporated in bone matrix, alendronate is not pharmacologically active. Thus, alendronate must be continuously administered to suppress osteoclasts on newly formed resorption surfaces. Histomorphometry in baboons and rats showed that alendronate treatment reduces bone turnover (i.e., the number of sites at which bone is remodeled).
In addition, bone formation exceeds bone resorption at these remodeling sites, leading to progressive gains in bone mass.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied 35 mg Tablets Alendronate Sodium Tablets USP, 35 mg are white, capsule shaped, biconvex tablets debossed with 'C223' on one side and plain on the other side. NDC 76282-681-45 Unit-of-use blister package of 4 NDC 76282-681-46 Unit-of-use blister package of 12 (3 X 4) 70 mg Tablets Alendronate Sodium Tablets USP, 70 mg are white, capsule shaped, biconvex tablets debossed with 'C224' on one side and plain on the other side. NDC 76282-682-45 Unit-of-use blister package of 4 NDC 76282-682-46 Unit-of-use blister package of 12 (3 X 4) Storage Store at 20°C to 25°C (68°F to77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Dispense in a tight, light-resistant container.
📋 Description ▾
11 DESCRIPTION Alendronate sodium is a bisphosphonate that acts as a specific inhibitor of osteoclast-mediated bone resorption. Bisphosphonates are synthetic analogs of pyrophosphate that bind to the hydroxyapatite found in bone. Alendronate sodium is chemically described as (4-amino-1-hydroxybutylidene) bisphosphonic acid monosodium salt trihydrate.
The empirical formula of alendronate sodium is C 4 H 12 NNaO 7 P 2 •3H 2 O and its formula weight is 325.12. The structural formula is: Alendronate sodium is a white, crystalline, nonhygroscopic powder. It is soluble in water, very slightly soluble in alcohol, and practically insoluble in chloroform.
Each tablet, for oral administration contains: 6.53, 13.05, 45.68, 52.21 or 91.37 mg of alendronate monosodium salt trihydrate, which is the molar equivalent of 5, 10, 35, 40 and 70 mg, respectively, of free acid, and the following inactive ingredients: magnesium stearate, mannitol, microcrystalline cellulose, sodium starch glycolate and starch. 1
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Instruct patients to read the Medication Guide before starting therapy with alendronate sodium and to reread it each time the prescription is renewed.
17.1Osteoporosis Recommendations, Including Calcium and Vitamin D Supplementation Instruct patients to take supplemental calcium and vitamin D, if daily dietary intake is inadequate. Weight-bearing exercise should be considered along with the modification of certain behavioral factors, such as cigarette smoking and/or excessive alcohol consumption, if these factors exist.
17.2Dosing Instructions Instruct patients that the expected benefits of alendronate sodium may only be obtained when it is taken with plain water the first thing upon arising for the day at least 30 minutes before the first food, beverage, or medication of the day. Even dosing with orange juice or coffee has been shown to markedly reduce the absorption of alendronate sodium [see Clinical Pharmacology ( 12.3 )] . Instruct patients not to chew or suck on the tablet because of a potential for oropharyngeal ulceration.
Instruct patients to swallow each tablet of alendronate sodium with a full glass of water (6-8 ounces) to facilitate delivery to the stomach and thus reduce the potential for esophageal irritation. Instruct patients not to lie down for at least 30 minutes and until after their first food of the day. Instruct patients not to take alendronate sodium at bedtime or before arising for the day.
Patients should be informed that failure to follow these instructions may increase their risk of esophageal problems. Instruct patients that if they develop symptoms of esophageal disease (such as difficulty or pain upon swallowing, retrosternal pain or new or worsening heartburn) they should stop taking alendronate sodium and consult their physician. If patients miss a dose of once weekly alendronate sodium, instruct patients to take one dose on the morning after they remember.
They should not take two doses on the same day but should return to taking one dose once a week, as originally scheduled on their chosen day. Manufactured by: Appco Pharma LLC Piscataway, NJ 08854 Manufactured for: Exelan Pharmaceuticals, Inc. Boca Raton, FL 33432 Revised: 07/2020
💬 Medication Guide ▾
MEDICATION GUIDE Alendronate Sodium Tablets, USP (a len' droe nate soe' dee um) Read the Medication Guide that comes with alendronate sodium tablets, USP before you start taking it and each time you get a refill. There may be new information. This Medication Guide does not take the place of talking with your doctor about your medical condition or treatment.
Talk to your doctor if you have any questions about alendronate sodium tablets, USP. What is the most important information I should know about alendronate sodium tablets, USP? Alendronate sodium tablets, USP can cause serious side effects including: Esophagus problems Low calcium levels in your blood (hypocalcemia) Bone, joint, or muscle pain Severe jaw bone problems (osteonecrosis) Unusual thigh bone fractures 1.
Esophagus problems. Some people who take alendronate sodium tablets, USP may develop problems in the esophagus (the tube that connects the mouth and the stomach). These problems include irritation, inflammation, or ulcers of the esophagus which may sometimes bleed.
It is important that you take alendronate sodium tablets, USP exactly as prescribed to help lower your chance of getting esophagus problems. (See the section "How should I take alendronate sodium tablets, USP?") Stop taking alendronate sodium tablets, USP and call your doctor right away if you get chest pain, new or worsening heartburn, or have trouble or pain when you swallow. 2.
Low calcium levels in your blood (hypocalcemia). Alendronate sodium tablets , USP may lower the calcium levels in your blood. If you have low blood calcium before you start taking alendronate sodium tablets , USP, it may get worse during treatment.
Your low blood calcium must be treated before you take alendronate sodium tablets , USP. Most people with low blood calcium levels do not have symptoms, but some people may have symptoms. Call your doctor right away if you have symptoms of low blood calcium such as: Spasms, twitches, or cramps in your muscles Numbness or tingling in your fingers, toes, or around your mouth Your doctor may prescribe calcium and vitamin D to help prevent low calcium levels in your blood, while you take alendronate sodium tablets, USP.
Take calcium and vitamin D as your doctor tells you to. 3. Bone, joint, or muscle pain.
Some people who take alendronate sodium tablets, USP develop severe bone, joint, or muscle pain. 4. Severe jaw bone problems (osteonecrosis).
Severe jaw bone problems may happen when you take alendronate sodium tablets , USP. Your doctor should examine your mouth before you start alendronate sodium tablets , USP. Your doctor may tell you to see your dentist before you start alendronate sodium tablets , USP.
It is important for you to practice good mouth care during treatment with alendronate sodium tablets , USP. 5. Unusual thigh bone fractures.
Some people have developed unusual fractures in their thigh bone. Symptoms of a fracture may include new or unusual pain in your hip, groin, or thigh. Call your doctor right away if you have any of these side effects.
What are alendronate sodium tablets, USP? Alendronate sodium tablets , USP are a prescription medicine used to: Treat or prevent osteoporosis in women after menopause. It helps reduce the chance of having a hip or spinal fracture (break).
Increase bone mass in men with osteoporosis. Treat osteoporosis in either men or women who are taking corticosteroid medicines. Treat certain men and women who have Paget's disease of the bone.
It is not known how long alendronate sodium tablets , USP works for the treatment and prevention of osteoporosis. You should see your doctor regularly to determine if alendronate sodium tablets, USP are still right for you. Alendronate sodium tablets , USP are not for use in children.
Who should not take alendronate sodium tablets, USP? Do not take alendronate sodium tablets, USP if you: Have certain problems with your esophagus, the tube that connects your mouth with your stomach Cannot stand or sit upr…