
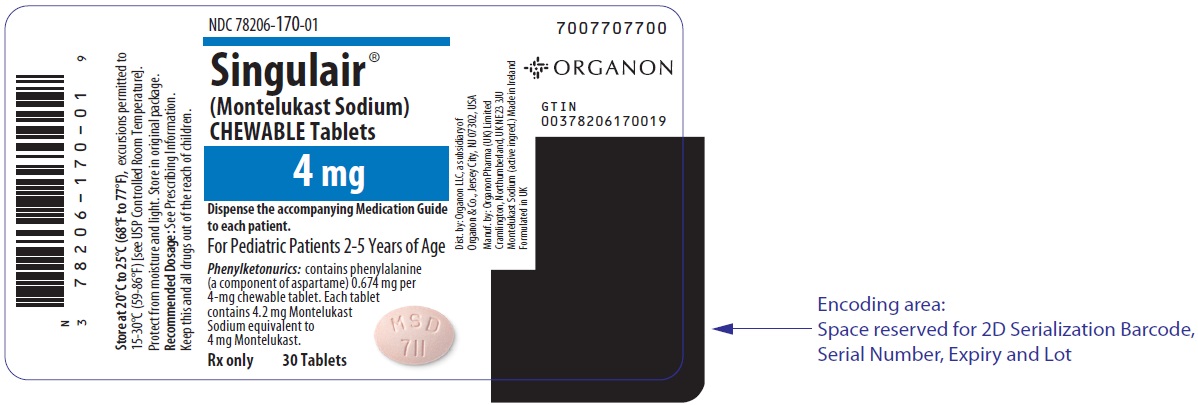
Singulair montelukast sodium 4 mg Tablet, Chewable, 30-count — NDC 78206-170-01 (Billing 78206-0170-01)
This is a package of 30 tablets of Singulair montelukast sodium 4 mg Tablet, Chewable from Organon LLC, marketed since Jun 2021 and currently FDA-listed. It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 044803
- GCN: 42373
- GPI-14 (Medi-Span): 44505050100516
- HICL (First Databank): 016911
- AHFS class code: 48:10.24.00
- RxCUI (RxNorm): 153892
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Leukotriene Receptor Antagonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Montelukast is used to prevent wheezing, difficulty breathing, chest tightness, and coughing caused by asthma in adults and children 12 months of age and older. Montelukast is also used to prevent bronchospasm (breathing difficulties) during exercise in adults and children 6 years of age and older. Montelukast is also used to treat the symptoms of seasonal (occurs only at certain times of the year), allergic rhinitis (a condition associated with sneezing and stuffy, runny or itchy nose) in adults and children 2 years of age and older, and perennial (occurs all year round) allergic rhinitis in...
Read the full MedlinePlus article ↗- It is used for long-term control of asthma, preventing breathing trouble triggered by exercise, and relieving seasonal and year-round allergy symptoms like a stuffy or runny nose....
- For asthma, take it once daily in the evening, with or without food. For exercise-triggered symptoms, take it at least 2 hours before exercise. If you have both asthma and allergie...
- No. Montelukast doesn't reverse an attack, so keep your rescue inhaler handy. You can keep taking montelukast during flare-ups, but use your rescue medicine when symptoms hit.
- Can I use it for a sudden asthma attack?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Montelukast Sodium — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $9.49 | $284.77 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 78206-0170-01 You're viewing this Main listing | 30 TABLET, CHEWABLE in 1 BOTTLE | 2021-06-01 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Montelukast Sodium 4 mg 13668-0079-05 | Torrent | 500 tablets | $0.075 | AB | Availability likely | — |
| montelukast sodium 4 mg 29300-0221-10 | Unichem | 1000 tablets | $0.075 | AB | Availability likely | — |
| Montelukast sodium 4 mg 33342-0110-07 | Macleods | 30 tablets | $0.075 | AB | Availability likely | — |
| Montelukast Sodium 4 mg 50268-0573-15 | AvPAK | 1 tablet | $0.075 | AB | Availability likely | — |
| Montelukast Sodium 4 mg 57237-0212-30 | Rising | 30 tablets | $0.075 | AB | Availability likely | — |
| Montelukast Sodium 4 mg 62135-0781-30 | Chartwell | 30 tablets | $0.075 | AB | Availability likely | — |
| Montelukast Sodium 4 mg 62175-0204-32 | Lannett | 30 tablets | $0.086 | AB | FDA listed | — |
| Montelukast Sodium 4 mg 27241-0016-03 | Ajanta | 30 tablets | $0.086 | — | FDA listed | — |
| montelukast sodium 4 mg 31722-0727-01 | Camber | 100 tablets | — | AB | FDA listed | — |
| Montelukast Sodium 4 mg 42291-0622-10 | AvKARE | 1000 tablets | — | AB | FDA listed | — |
| Montelukast Sodium 4 mg 43063-0381-21 | PD-Rx | 21 tablets | — | AB | FDA listed | — |
| montelukast sodium 4 mg 50090-2921-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| montelukast sodium 4 mg 50090-7920-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Montelukast Sodium 4 mg 55111-0593-05 | Dr.Reddy's | 500 tablets | — | AB | FDA listed | — |
| Montelukast Sodium 4 mg 63187-0550-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Montelukast Sodium 4 mg 63187-0751-30 | Proficient | 30 tablets | — | — | FDA listed | — |
| Montelukast Sodium 4 mg 65162-0771-03 | Amneal | 30 tablets | — | — | FDA listed | — |
| Montelukast Sodium 4 mg 65862-0567-05 | Aurobindo | 500 tablets | — | AB | FDA listed | — |
| Montelukast Sodium 4 mg 71205-0189-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| montelukast sodium 4 mg 71335-1602-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Singulair 4 mgthis 78206-0170-01 | Organon | 30 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII Z0H242BBR1
Aspartame is an artificial sweetener made from amino acids. It's added to medicines to improve taste, making bitter or unpleasant-tasting drugs easier to take.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SERIOUS NEUROPSYCHIATRIC EVENTS Serious neuropsychiatric (NP) events have been reported with the use of SINGULAIR. The types of events reported were highly variable, and included, but were not limited to, agitation, aggression, depression, sleep disturbances, suicidal thoughts and behavior (including suicide). The mechanisms underlying NP events associated with SINGULAIR use are currently not well understood [see Warnings and Precautions (5.1) ] .
Because of the risk of NP events, the benefits of SINGULAIR may not outweigh the risks in some patients, particularly when the symptoms of disease may be mild and adequately treated with alternative therapies. Reserve use of SINGULAIR for patients with allergic rhinitis who have an inadequate response or intolerance to alternative therapies [see Indications and Usage (1.3) ] . In patients with asthma or exercise-induced bronchoconstriction, consider the benefits and risks before prescribing SINGULAIR.
Discuss the benefits and risks of SINGULAIR with patients and caregivers when prescribing SINGULAIR. Advise patients and/or caregivers to be alert for changes in behavior or new NP symptoms when taking SINGULAIR. If changes in behavior are observed, or if new NP symptoms or suicidal thoughts and/or behavior occur, advise patients to discontinue SINGULAIR and contact a healthcare provider immediately [see Warnings and Precautions (5.1) ] .
WARNING: SERIOUS NEUROPSYCHIATRIC EVENTS See full prescribing information for complete boxed warning. Serious neuropsychiatric events have been reported in patients taking SINGULAIR ( 5.1 ). Discuss benefits and risks of SINGULAIR with patients and caregivers ( 5.1 ).
Monitor for neuropsychiatric symptoms in patients taking SINGULAIR ( 5.1 ). Discontinue SINGULAIR immediately if neuropsychiatric symptoms occur ( 5.1 ). Because the benefits of SINGULAIR may not outweigh the potential risk of neuropsychiatric symptoms in patients with allergic rhinitis, reserve use for patients who have an inadequate response or intolerance to alternative therapies ( 1.3 , 5.1 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE SINGULAIR is a leukotriene receptor antagonist indicated for: Prophylaxis and chronic treatment of asthma in patients 12 months of age and older ( 1.1 ). Acute prevention of exercise-induced bronchoconstriction (EIB) in patients 6 years of age and older ( 1.2 ). Relief of symptoms of allergic rhinitis (AR): seasonal allergic rhinitis (SAR) in patients 2 years of age and older, and perennial allergic rhinitis (PAR) in patients 6 months of age and older.
Reserve use for patients who have an inadequate response or intolerance to alternative therapies ( 1.3 ). Limitations of Use: Not indicated to treat an acute asthma attack ( 5.2 ).
1.1Asthma SINGULAIR ® is indicated for the prophylaxis and chronic treatment of asthma in adults and pediatric patients 12 months of age and older.
1.2Exercise-Induced Bronchoconstriction (EIB) SINGULAIR is indicated for prevention of exercise-induced bronchoconstriction (EIB) in patients 6 years of age and older.
1.3Allergic Rhinitis SINGULAIR is indicated for the relief of symptoms of seasonal allergic rhinitis in patients 2 years of age and older and perennial allergic rhinitis in patients 6 months of age and older. Because the benefits of SINGULAIR may not outweigh the risk of neuropsychiatric symptoms in patients with allergic rhinitis [see Warnings and Precautions (5.1) ] , reserve use for patients who have an inadequate response or intolerance to alternative therapies.
1.4Limitations of Use SINGULAIR is not indicated for the treatment of an acute asthma attack.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administration (by indications): Asthma: Once daily in the evening for patients 12 months and older ( 2.1 ). Acute prevention of EIB: One tablet at least 2 hours before exercise for patients 6 years of age and older ( 2.2 ). Seasonal allergic rhinitis: Once daily for patients 2 years and older ( 2.3 ).
Perennial allergic rhinitis: Once daily for patients 6 months and older ( 2.3 ). Dosage (by age): 15 years and older: one 10-mg tablet ( 2 ). 6 to 14 years: one 5-mg chewable tablet ( 2 ).
2 to 5 years: one 4-mg chewable tablet or one packet of 4-mg oral granules ( 2 ). 6 to 23 months: one packet of 4-mg oral granules ( 2 ). Patients with both asthma and allergic rhinitis should take only one dose daily in the evening ( 2.4 ).
For oral granules: Must administer within 15 minutes after opening the packet (with or without mixing with food) ( 2.5 ).
2.1Asthma For asthma, administer SINGULAIR orally once daily in the evening, with or without food. There have been no clinical trials in patients with asthma to evaluate the relative efficacy of morning versus evening dosing. The following doses are recommended: Table 1: Recommended Dosage in Asthma Age Dose Adult and adolescent patients 15 years of age and older one 10 mg tablet Pediatric patients 6 to 14 years of age one 5 mg chewable tablet Pediatric patients 2 to 5 years of age one 4 mg chewable tablet or one packet of oral granules Pediatric patients 12 to 23 months of age Safety and effectiveness in pediatric patients less than 12 months of age with asthma have not been established. one packet 4 mg oral granules Patients who miss a dose should take the next dose at their regular time and should not take 2 doses at the same time.
2.2Exercise-Induced Bronchoconstriction (EIB) For prevention of EIB, administer a single dose of SINGULAIR orally at least 2 hours, before exercise. The following doses are recommended: Table 2: Recommended Dosage in Exercise-Induced Bronchoconstriction (EIB) Age Dose Adult and adolescent patients 15 years of age and older one 10 mg tablet Pediatric patients 6 to 14 years of age Safety and effectiveness in patients younger than 6 years of age have not been established. one 5 mg chewable tablet An additional dose of SINGULAIR should not be taken within 24 hours of a previous dose.
Patients already taking SINGULAIR daily for another indication (including chronic asthma) should not take an additional dose to prevent EIB. All patients should have available for rescue a short-acting β-agonist. Daily administration of SINGULAIR for the chronic treatment of asthma has not been established to prevent acute episodes of EIB.
2.3Allergic Rhinitis For allergic rhinitis, administer SINGULAIR orally once daily without regard to time of food ingestion. Time of administration in patients with allergic rhinitis can be individualized to suit patient needs. The following doses for the treatment of symptoms of seasonal allergic rhinitis are recommended: Table 3: Recommended Dosage in Seasonal Allergic Rhinitis Age Dose Adult and adolescent patients 15 years of age and older one 10 mg tablet Pediatric patients 6 to 14 years of age one 5 mg chewable tablet Pediatric patients 2 to 5 years of age Safety and effectiveness in pediatric patients younger than 2 years of age with seasonal allergic rhinitis have not been established. one 4 mg chewable tablet or one packet of 4 mg oral granules The following doses for the treatment of symptoms of perennial allergic rhinitis are recommended: Table 4: Recommended Dosage in Perennial Allergic Rhinitis Age Dose Adult and adolescent patients 15 years of age and older one 10 mg tablet Pediatric patients 6 to 14 years of age one 5 mg chewable tablet Pediatric patients 2 to 5 years of age one 4 mg chewable tablet or one packet of 4 mg oral granules Pediatric patients 6 to 23 months of age Safety and effectiveness in pediatric patients younger than 6 months of age with perennial allergic rhinitis have not been esta… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 10 mg, beige, rounded square-shaped, film-coated tablets, with code MSD 117 on one side and SINGULAIR on the other. Chewable Tablets: 5 mg, pink, round, bi-convex-shaped, with code MSD 275 on one side and SINGULAIR on the other. Chewable Tablets: 4 mg, pink, oval, bi-convex-shaped, with code MSD 711 on one side and SINGULAIR on the other.
Oral Granules: 4 mg, white granules with 500 mg net weight, packed in a child-resistant foil packet. Tablets: 10 mg ( 3 ) Chewable tablets: 5 mg and 4 mg ( 3 ) Oral granules: 4 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS SINGULAIR is contraindicated in patients with hypersensitivity to any of its components. Hypersensitivity to any component of SINGULAIR ( 4 ).
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Do not prescribe SINGULAIR to treat an acute asthma attack ( 5.2 ). Advise patients to have appropriate rescue medication available ( 5.2 ). Inhaled corticosteroid may be reduced gradually.
Do not abruptly substitute SINGULAIR for inhaled or oral corticosteroids ( 5.3 ). Patients with known aspirin sensitivity should continue to avoid aspirin or non-steroidal anti-inflammatory agents while taking SINGULAIR ( 5.4 ). Systemic eosinophilia, sometimes presenting with clinical features of vasculitis consistent with Churg-Strauss syndrome, has been reported.
These events have been sometimes associated with the reduction of oral corticosteroid therapy ( 5.5 and 6.2 ). Inform patients with phenylketonuria that the 4-mg and 5-mg chewable tablets contain phenylalanine ( 5.6 ).
5.1Neuropsychiatric Events Serious neuropsychiatric (NP) events have been reported with use of SINGULAIR. These postmarketing reports have been highly variable and included, but were not limited to, agitation, aggressive behavior or hostility, anxiousness, depression, disorientation, disturbance in attention, dream abnormalities, dysphemia (stuttering), hallucinations, insomnia, irritability, memory impairment, obsessive-compulsive symptoms, restlessness, somnambulism, suicidal thoughts and behavior (including suicide), tic, and tremor.
NP events have been reported in adult, adolescent, and pediatric patients with and without a previous history of psychiatric disorder. NP events have been reported mostly during SINGULAIR treatment, but some were reported after SINGULAIR discontinuation. Animal studies showed that montelukast distributes into the brain in rats [see Clinical Pharmacology (12.3) ] ; however, the mechanisms underlying SINGULAIR-associated NP events are currently not well understood.
Based upon the available data, it is difficult to identify risk factors for or quantify the risk of NP events with SINGULAIR use. Because of the risk of NP events, the benefits of SINGULAIR may not outweigh the risks in some patients, particularly when the symptoms of disease may be mild and adequately treated with alternative therapies. Reserve use of SINGULAIR for patients with allergic rhinitis who have an inadequate response or intolerance to alternative therapies [see Indications and Usage (1.3) ] .
In patients with asthma or exercise-induced bronchoconstriction, consider the benefits and risks before prescribing SINGULAIR. Discuss the benefits and risks of SINGULAIR use with patients and caregivers when prescribing SINGULAIR. Advise patients and/or caregivers to be alert for changes in behavior or for new NP symptoms when taking SINGULAIR.
If changes in behavior are observed, or if new NP symptoms or suicidal thoughts and/or behavior occur, advise patients to discontinue SINGULAIR and contact a healthcare provider immediately. In many cases, symptoms resolved after stopping SINGULAIR therapy; however, in some cases symptoms persisted after discontinuation of SINGULAIR. Therefore, continue to monitor and provide supportive care until symptoms resolve.
Re-evaluate the benefits and risks of restarting treatment with SINGULAIR if such events occur.
5.2Acute Asthma SINGULAIR is not indicated for use in the reversal of bronchospasm in acute asthma attacks, including status asthmaticus. Patients should be advised to have appropriate rescue medication available. Therapy with SINGULAIR can be continued during acute exacerbations of asthma. Patients who have exacerbations of asthma after exercise should have available for rescue a short-acting inhaled β-agonist.
5.3Concomitant Corticosteroid Use While the dose of inhaled corticosteroid may be reduced gradually under medical supervision, SINGULAIR should not be abruptly substituted for inhaled or oral corticosteroids.
5.4Aspirin Sensitivity Patients with known aspirin sensitivity should continue avoidance of aspirin or non-steroidal anti-inflammatory agents while taking SINGULAIR. Although SINGULA… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Neuropsychiatric Events [see Warnings and Precautions (5.1) ] Most common adverse reactions (incidence ≥5% and greater than placebo listed in descending order of frequency): upper respiratory infection, fever, headache, pharyngitis, cough, abdominal pain, diarrhea, otitis media, influenza, rhinorrhea, sinusitis, otitis ( 6.1 ). To report SUSPECTED ADVERSE REACTIONS, contact Organon LLC, a subsidiary of Organon & Co., Inc., at 1-844-674-3200 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. In the following description of clinical trials experience, adverse reactions are listed regardless of causality assessment. The most common adverse reactions (incidence ≥5% and greater than placebo; listed in descending order of frequency) in controlled clinical trials were: upper respiratory infection, fever, headache, pharyngitis, cough, abdominal pain, diarrhea, otitis media, influenza, rhinorrhea, sinusitis, otitis.
Adults and Adolescents 15 Years of Age and Older with Asthma SINGULAIR has been evaluated for safety in approximately 2950 adult and adolescent patients 15 years of age and older in clinical trials. In placebo-controlled clinical trials, the following adverse reactions reported with SINGULAIR occurred in greater than or equal to 1% of patients and at an incidence greater than that in patients treated with placebo: Table 5: Adverse Reactions Occurring in ≥1% of Patients with an Incidence Greater than that in Patients Treated with Placebo SINGULAIR 10 mg/day (%) (n=1955) Placebo (%) (n=1180) Body As A Whole Pain, abdominal Asthenia/fatigue Fever Trauma 2.9 1.8 1.5 1.0 2.5 1.2 0.9
0.8Digestive System Disorders Dyspepsia Pain, dental Gastroenteritis, infectious 2.1 1.7 1.5 1.1 1.0
0.5Nervous System/Psychiatric Headache Dizziness 18.4 1.9 18.1
1.4Respiratory System Disorders Influenza Cough Congestion, nasal 4.2 2.7 1.6 3.9 2.4
1.3Skin/Skin Appendages Disorder Rash 1.6
1.2Laboratory Adverse Reactions Number of patients tested (SINGULAIR and placebo, respectively): ALT and AST, 1935, 1170; pyuria, 1924, 1159. ALT increased AST increased Pyuria 2.1 1.6 1.0 2.0 1.2
0.9The frequency of less common adverse reactions was comparable between SINGULAIR and placebo. The safety profile of SINGULAIR, when administered as a single dose for prevention of EIB in adult and adolescent patients 15 years of age and older, was consistent with the safety profile previously described for SINGULAIR. Cumulatively, 569 patients were treated with SINGULAIR for at least 6 months, 480 for one year, and 49 for two years in clinical trials.
With prolonged treatment, the adverse reaction profile did not significantly change. Pediatric Patients 6 to 14 Years of Age with Asthma SINGULAIR has been evaluated for safety in 476 pediatric patients 6 to 14 years of age. Cumulatively, 289 pediatric patients were treated with SINGULAIR for at least 6 months, and 241 for one year or longer in clinical trials.
The safety profile of SINGULAIR in the 8-week, double-blind, pediatric efficacy trial was generally similar to the adult safety profile. In pediatric patients 6 to 14 years of age receiving SINGULAIR, the following reactions occurred with a frequency ≥2% and more frequently than in pediatric patients who received placebo: pharyngitis, influenza, fever, sinusitis, nausea, diarrhea, dyspepsia, otitis, viral infection, and laryngitis. The frequency of less common adverse reactions was comparable between SINGULAIR and placebo.
With prolonged treatment, the adverse reaction profile did not significantly change. The safety profile of SINGULAIR, when admi… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS No dose adjustment is needed when SINGULAIR is co-administered with theophylline, prednisone, prednisolone, oral contraceptives, fexofenadine, digoxin, warfarin, gemfibrozil, itraconazole, thyroid hormones, sedative hypnotics, non-steroidal anti-inflammatory agents, benzodiazepines, decongestants, and Cytochrome P450 (CYP) enzyme inducers [see Clinical Pharmacology (12.3) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Available data from published prospective and retrospective cohort studies over decades with montelukast use in pregnant women have not established a drug-associated risk of major birth defects [see Data ] . In animal reproduction studies, no adverse developmental effects were observed with oral administration of montelukast to pregnant rats and rabbits during organogenesis at doses approximately 100 and 110 times, respectively, the maximum recommended human daily oral dose (MRHDOD) based on AUCs [see Data ].
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly or moderately controlled asthma in pregnancy increases the maternal risk of perinatal adverse outcomes such as preeclampsia and infant prematurity, low birth weight, and small for gestational age. Data Human Data Published data from prospective and retrospective cohort studies have not identified an association with SINGULAIR use during pregnancy and major birth defects. Available studies have methodologic limitations, including small sample size, in some cases retrospective data collection, and inconsistent comparator groups.
Animal Data In embryo-fetal development studies, montelukast administered to pregnant rats and rabbits during organogenesis (gestation days 6 to 17 in rats and 6 to 18 in rabbits) did not cause any adverse developmental effects at maternal oral doses up to 400 and 300 mg/kg/day in rats and rabbits, respectively (approximately 100 and 110 times the AUC in humans at the MRHDOD, respectively).
8.2Lactation Risk Summary A published clinical lactation study reports the presence of montelukast in human milk. Data available on the effects of the drug on infants, either directly [see Use in Specific Populations (8.4) ] or through breast milk, do not suggest a significant risk of adverse reactions from exposure to SINGULAIR. The effects of the drug on milk production are unknown.
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for SINGULAIR and any potential adverse reactions on the breastfed infant from SINGULAIR or from the underlying maternal condition.
8.4Pediatric Use Safety and effectiveness of SINGULAIR for asthma have been established in pediatric patients 6 to 14 years of age. Use of SINGULAIR for this indication is supported by evidence from well-controlled studies. Safety and efficacy data in this age group are similar to those seen in adults [see Adverse Reactions (6.1) , Clinical Pharmacology, Specific Populations (12.3) , and Clinical Studies (14.1 , 14.2 )].
The effectiveness of SINGULAIR for the treatment of seasonal allergic rhinitis in pediatric patients 2 to 14 years of age and for the treatment of perennial allergic rhinitis in pediatric patients 6 months to 14 years of age have been established and is supported by extrapolation from the demonstrated effectiveness in patients 15 years of age and older with allergic rhinitis as well as the assumption that the disease course, pathophysiology and the drug’s effect are substantially similar among these populations. The safety of SINGULAIR 4-mg chewable tablets in pediatric patients 2 to 5 years of age with asthma has been demonstrated by adequate and well-controlled data [see Adverse Reactions (6.1) ].
Effectiveness of SINGULAIR in this age group is extrapolated from the demonstrated effectiveness in patients 6 years of age and older with asthma and is based on similar pharmacokinetic data, as well as the assumption that the disease course, pathophysiology and the drug’s ef… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from published prospective and retrospective cohort studies over decades with montelukast use in pregnant women have not established a drug-associated risk of major birth defects [see Data ] . In animal reproduction studies, no adverse developmental effects were observed with oral administration of montelukast to pregnant rats and rabbits during organogenesis at doses approximately 100 and 110 times, respectively, the maximum recommended human daily oral dose (MRHDOD) based on AUCs [see Data ].
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly or moderately controlled asthma in pregnancy increases the maternal risk of perinatal adverse outcomes such as preeclampsia and infant prematurity, low birth weight, and small for gestational age. Data Human Data Published data from prospective and retrospective cohort studies have not identified an association with SINGULAIR use during pregnancy and major birth defects. Available studies have methodologic limitations, including small sample size, in some cases retrospective data collection, and inconsistent comparator groups.
Animal Data In embryo-fetal development studies, montelukast administered to pregnant rats and rabbits during organogenesis (gestation days 6 to 17 in rats and 6 to 18 in rabbits) did not cause any adverse developmental effects at maternal oral doses up to 400 and 300 mg/kg/day in rats and rabbits, respectively (approximately 100 and 110 times the AUC in humans at the MRHDOD, respectively).
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of SINGULAIR for asthma have been established in pediatric patients 6 to 14 years of age. Use of SINGULAIR for this indication is supported by evidence from well-controlled studies. Safety and efficacy data in this age group are similar to those seen in adults [see Adverse Reactions (6.1) , Clinical Pharmacology, Specific Populations (12.3) , and Clinical Studies (14.1 , 14.2 )].
The effectiveness of SINGULAIR for the treatment of seasonal allergic rhinitis in pediatric patients 2 to 14 years of age and for the treatment of perennial allergic rhinitis in pediatric patients 6 months to 14 years of age have been established and is supported by extrapolation from the demonstrated effectiveness in patients 15 years of age and older with allergic rhinitis as well as the assumption that the disease course, pathophysiology and the drug’s effect are substantially similar among these populations. The safety of SINGULAIR 4-mg chewable tablets in pediatric patients 2 to 5 years of age with asthma has been demonstrated by adequate and well-controlled data [see Adverse Reactions (6.1) ].
Effectiveness of SINGULAIR in this age group is extrapolated from the demonstrated effectiveness in patients 6 years of age and older with asthma and is based on similar pharmacokinetic data, as well as the assumption that the disease course, pathophysiology and the drug’s effect are substantially similar among these populations. Effectiveness in this age group is supported by exploratory efficacy assessments from a large, well-controlled safety study conducted in patients 2 to 5 years of age. The safety of SINGULAIR 4-mg oral granules in pediatric patients 12 to 23 months of age with asthma has been demonstrated in an analysis of 172 pediatric patients, 124 of whom were treated with SINGULAIR, in a 6-week, double-blind, placebo-controlled study [see Adverse Reactions (6.1) ].
Effectiveness of SINGULAIR in this age group is extrapolated from the demonstrated effectiveness in patients 6 years of age and older with asthma based on similar mean systemic exposure (AUC), and that the disease course, pathophysiology and the drug's effect are substantially similar among these populations, supported by efficacy data from a safety trial in which efficacy was an exploratory assessment. The safety of SINGULAIR 4-mg and 5-mg chewable tablets in pediatric patients aged 2 to 14 years with allergic rhinitis is supported by data from studies conducted in pediatric patients aged 2 to 14 years with asthma.
A safety study in pediatric patients 2 to 14 years of age with seasonal allergic rhinitis demonstrated a similar safety profile [see Adverse Reactions (6.1) ]. The safety of SINGULAIR 4-mg oral granules in pediatric patients as young as 6 months of age with perennial allergic rhinitis is supported by extrapolation from safety data obtained from studies conducted in pediatric patients 6 months to 23 months of age with asthma and from pharmacokinetic data comparing systemic exposures in patients 6 months to 23 months of age to systemic exposures in adults.
The safety and effectiveness in pediatric patients below the age of 12 months with asthma, 6 months with perennial allergic rhinitis, and 6 years with exercise-induced bronchoconstriction have not been established. Growth Rate in Pediatric Patients A 56-week, multi-center, double-blind, randomized, active- and placebo-controlled parallel group study was conducted to assess the effect of SINGULAIR on growth rate in 360 patients with mild asthma, aged 6 to 8 years. Treatment groups included SINGULAIR 5 mg once daily, placebo, and beclomethasone dipropionate administered as 168 mcg twice daily with a spacer device.
For each subject, a growth rate was defined as the slope of a linear regression line fit to the height measurements over 56 weeks. The primary comparison was the difference in growth rates between SINGULAIR and placebo groups. Growth rates, expressed as least-squares (LS)… [Excerpted — this section continues on DailyMed.]
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects in clinical studies of montelukast, 3.5% were 65 years of age and over, and 0.4% were 75 years of age and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. The pharmacokinetic profile and the oral bioavailability of a single 10-mg oral dose of montelukast are similar in elderly and younger adults.
The plasma half-life of montelukast is slightly longer in the elderly. No dosage adjustment in the elderly is required.
🆘 Overdosage ▾
10 OVERDOSAGE No specific information is available on the treatment of overdosage with SINGULAIR. In the event of overdose, it is reasonable to employ the usual supportive measures; e.g., remove unabsorbed material from the gastrointestinal tract, employ clinical monitoring, and institute supportive therapy, if required. It is not known whether montelukast is removed by peritoneal dialysis or hemodialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The cysteinyl leukotrienes (LTC 4 , LTD 4 , LTE 4 ) are products of arachidonic acid metabolism and are released from various cells, including mast cells and eosinophils. These eicosanoids bind to cysteinyl leukotriene (CysLT) receptors. The CysLT type-1 (CysLT 1 ) receptor is found in the human airway (including airway smooth muscle cells and airway macrophages) and on other pro-inflammatory cells (including eosinophils and certain myeloid stem cells).
CysLTs have been correlated with the pathophysiology of asthma and allergic rhinitis. In asthma, leukotriene-mediated effects include airway edema, smooth muscle contraction, and altered cellular activity associated with the inflammatory process. In allergic rhinitis, CysLTs are released from the nasal mucosa after allergen exposure during both early- and late-phase reactions and are associated with symptoms of allergic rhinitis.
Montelukast is an orally active compound that binds with high affinity and selectivity to the CysLT 1 receptor (in preference to other pharmacologically important airway receptors, such as the prostanoid, cholinergic, or β-adrenergic receptor). Montelukast inhibits physiologic actions of LTD 4 at the CysLT 1 receptor without any agonist activity.
12.2Pharmacodynamics Montelukast causes inhibition of airway cysteinyl leukotriene receptors as demonstrated by the ability to inhibit bronchoconstriction due to inhaled LTD 4 in asthmatics. Doses as low as 5 mg cause substantial blockage of LTD 4 -induced bronchoconstriction. In a placebo-controlled, crossover study (n=12), SINGULAIR inhibited early- and late-phase bronchoconstriction due to antigen challenge by 75% and 57%, respectively.
The effect of SINGULAIR on eosinophils in the peripheral blood was examined in clinical trials. In patients with asthma aged 2 years and older who received SINGULAIR, a decrease in mean peripheral blood eosinophil counts ranging from 9% to 15% was noted, compared with placebo, over the double-blind treatment periods. In patients with seasonal allergic rhinitis aged 15 years and older who received SINGULAIR, a mean increase of 0.2% in peripheral blood eosinophil counts was noted, compared with a mean increase of 12.5% in placebo-treated patients, over the double-blind treatment periods; this reflects a mean difference of 12.3% in favor of SINGULAIR.
The relationship between these observations and the clinical benefits of montelukast noted in the clinical trials is not known [see Clinical Studies (14) ].
12.3Pharmacokinetics Absorption Montelukast is rapidly absorbed following oral administration. After administration of the 10-mg film-coated tablet to fasted adults, the mean peak montelukast plasma concentration (C max ) is achieved in 3 to 4 hours (T max ). The mean oral bioavailability is 64%.
The oral bioavailability and C max are not influenced by a standard meal in the morning. For the 5-mg chewable tablet, the mean C max is achieved in 2 to 2.5 hours after administration to adults in the fasted state. The mean oral bioavailability is 73% in the fasted state versus 63% when administered with a standard meal in the morning.
For the 4-mg chewable tablet, the mean C max is achieved 2 hours after administration in pediatric patients 2 to 5 years of age in the fasted state. The 4-mg oral granule formulation is bioequivalent to the 4-mg chewable tablet when administered to adults in the fasted state. The co-administration of the oral granule formulation with applesauce did not have a clinically significant effect on the pharmacokinetics of montelukast.
A high fat meal in the morning did not affect the AUC of montelukast oral granules; however, the meal decreased C max by 35% and prolonged T max from 2.3 ± 1.0 hours to 6.4 ± 2.9 hours. The safety and effectiveness of SINGULAIR in patients with asthma were demonstrated in clinical trials in which the 10-mg film-coated tablet and 5-mg chewable tablet formulations were administer… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The cysteinyl leukotrienes (LTC 4 , LTD 4 , LTE 4 ) are products of arachidonic acid metabolism and are released from various cells, including mast cells and eosinophils. These eicosanoids bind to cysteinyl leukotriene (CysLT) receptors. The CysLT type-1 (CysLT 1 ) receptor is found in the human airway (including airway smooth muscle cells and airway macrophages) and on other pro-inflammatory cells (including eosinophils and certain myeloid stem cells).
CysLTs have been correlated with the pathophysiology of asthma and allergic rhinitis. In asthma, leukotriene-mediated effects include airway edema, smooth muscle contraction, and altered cellular activity associated with the inflammatory process. In allergic rhinitis, CysLTs are released from the nasal mucosa after allergen exposure during both early- and late-phase reactions and are associated with symptoms of allergic rhinitis.
Montelukast is an orally active compound that binds with high affinity and selectivity to the CysLT 1 receptor (in preference to other pharmacologically important airway receptors, such as the prostanoid, cholinergic, or β-adrenergic receptor). Montelukast inhibits physiologic actions of LTD 4 at the CysLT 1 receptor without any agonist activity.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING SINGULAIR 4 mg Oral Granules: white granules with 500 mg net weight, packed in a child-resistant foil packet. NDC 78206-171-01 unit of use carton with 30 packets. SINGULAIR 4 mg Tablets: pink, oval, bi-convex-shaped chewable tablets, with code MSD 711 on one side and SINGULAIR on the other.
NDC 78206-170-01 unit of use high-density polyethylene (HDPE) bottles of 30 with a polypropylene child-resistant cap, an aluminum foil induction seal, and silica gel desiccant. SINGULAIR 5 mg Tablets: pink, round, bi-convex-shaped chewable tablets, with code MSD 275 on one side and SINGULAIR on the other. NDC 78206-173-01 unit of use high-density polyethylene (HDPE) bottles of 30 with a polypropylene child-resistant cap, an aluminum foil induction seal, and silica gel desiccant.
SINGULAIR 10 mg Tablets: beige, rounded square-shaped, film-coated tablets, with code MSD 117 on one side and SINGULAIR on the other. NDC 78206-172-01 unit of use high-density polyethylene (HDPE) bottles of 30 with a polypropylene child-resistant cap, an aluminum foil induction seal, and silica gel desiccant NDC 78206-172-02 unit of use high-density polyethylene (HDPE) bottles of 90 with a polypropylene child-resistant cap, an aluminum foil induction seal, and silica gel desiccant. Storage Store SINGULAIR 4-mg oral granules, 4-mg chewable tablets, 5-mg chewable tablets and 10-mg film-coated tablets at 20°C to 25°C (68°F to 77°F), excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Protect from moisture and light. Store in original package.
📦 Storage and Handling ▾
Storage Store SINGULAIR 4-mg oral granules, 4-mg chewable tablets, 5-mg chewable tablets and 10-mg film-coated tablets at 20°C to 25°C (68°F to 77°F), excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Protect from moisture and light. Store in original package.
📋 Description ▾
11 DESCRIPTION Montelukast sodium, the active ingredient in SINGULAIR, is a selective and orally active leukotriene receptor antagonist that inhibits the cysteinyl leukotriene CysLT 1 receptor. Montelukast sodium is described chemically as [ R -( E )]-1-[[[1-[3-[2-(7-chloro-2-quinolinyl)ethenyl]phenyl]-3-[2-(1-hydroxy-1-methylethyl)phenyl]propyl]thio]methyl]cyclopropaneacetic acid, monosodium salt. The empirical formula is C 35 H 35 ClNNaO 3 S, and its molecular weight is 608.18.
The structural formula is: Montelukast sodium is a hygroscopic, optically active, white to off-white powder. Montelukast sodium is freely soluble in ethanol, methanol, and water and practically insoluble in acetonitrile. Each 10-mg film-coated SINGULAIR tablet contains 10.4 mg montelukast sodium, which is equivalent to 10 mg of montelukast, and the following inactive ingredients: microcrystalline cellulose, lactose monohydrate, croscarmellose sodium, hydroxypropyl cellulose, and magnesium stearate.
The film coating consists of: hydroxypropyl methylcellulose, hydroxypropyl cellulose, titanium dioxide, red ferric oxide, yellow ferric oxide, and carnauba wax. Each 4-mg and 5-mg chewable SINGULAIR tablet contains 4.2 and 5.2 mg montelukast sodium, respectively, which are equivalent to 4 and 5 mg of montelukast, respectively. Both chewable tablets contain the following inactive ingredients: mannitol, microcrystalline cellulose, hydroxypropyl cellulose, red ferric oxide, croscarmellose sodium, cherry flavor, aspartame, and magnesium stearate.
Each packet of SINGULAIR 4-mg oral granules contains 4.2 mg montelukast sodium, which is equivalent to 4 mg of montelukast. The oral granule formulation contains the following inactive ingredients: mannitol, hydroxypropyl cellulose, and magnesium stearate. image of montelukast sodium chemical structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION For the tablets and chewable tablets, advise the patient and/or caregiver to read the FDA-approved patient labeling ( Medication Guide ). For the oral granules, advise the patient and/or caregiver to read the FDA-approved patient labeling ( Medication Guide and Instructions for Use ). Advise patients about the potential risk for serious neuropsychiatric symptoms and behavioral changes with SINGULAIR use [see Warnings and Precautions (5.1) ] .
Discuss the benefits and risks of SINGULAIR with patients when prescribing or continuing treatment with SINGULAIR [see Warnings and Precautions (5.1) ] . Advise patients to monitor for changes in behavior or neuropsychiatric symptoms in patients taking SINGULAIR [see Warnings and Precautions (5.1) ] . Instruct patients to discontinue SINGULAIR and contact a healthcare provider immediately if changes in behavior or thinking that are not typical for the patient occur, or if the patient develops suicidal ideation or suicidal behavior [see Warnings and Precautions (5.1) ] .
Advise patients to take SINGULAIR daily as prescribed, even when they are asymptomatic, as well as during periods of worsening asthma, and to contact their physicians if their asthma is not well controlled. Advise patients that oral SINGULAIR is not for the treatment of acute asthma attacks. They should have appropriate short-acting inhaled β-agonist medication available to treat asthma exacerbations.
Patients who have exacerbations of asthma after exercise should be instructed to have available for rescue a short-acting inhaled β-agonist. Daily administration of SINGULAIR for the chronic treatment of asthma has not been established to prevent acute episodes of EIB [see Warnings and Precautions (5.2) ] . Advise patients to seek medical attention if short-acting inhaled bronchodilators are needed more often than usual, or if more than the maximum number of inhalations of short-acting bronchodilator treatment prescribed for a 24-hour period are needed.
Instruct patients to continue other anti-asthma medications as prescribed unless instructed by a physician. Instruct patients with known aspirin sensitivity to continue avoidance of aspirin or non-steroidal anti-inflammatory agents while taking SINGULAIR [see Warnings and Precautions (5.4) ] . Inform phenylketonuric patients that the 4-mg and 5-mg chewable tablets contain phenylalanine (a source of aspartame) [see Warnings and Precautions (5.6) ] .
💬 Medication Guide ▾
MEDICATION GUIDE SINGULAIR ® (SING-u-lair) (montelukast sodium) tablets chewable tablets oral granules This Medication Guide has been approved by the U.S. Food and Drug Administration Revised: 6/2021 What is the most important information I should know about SINGULAIR? Serious mental health problems have happened in people taking SINGULAIR or even after treatment has stopped.
This can happen in people with or without a history of mental health problems. Stop taking SINGULAIR and tell your healthcare provider right away if you or your child have any unusual changes in behavior or thinking, including any of these symptoms: agitation, including aggressive behavior or hostility attention problems bad or vivid dreams depression disorientation (confusion) feeling anxious irritability hallucinations (seeing or hearing things that are not really there) memory problems obsessive-compulsive symptoms restlessness sleep walking stuttering suicidal thoughts and actions (including suicide) tremor trouble sleeping uncontrolled muscle movements What is SINGULAIR?
SINGULAIR is a prescription medicine that blocks substances in the body called leukotrienes. This may help to improve symptoms of asthma and inflammation of the lining of the nose (allergic rhinitis). SINGULAIR does not contain a steroid.
SINGULAIR is used to: Prevent asthma attacks and for the long-term treatment of asthma in adults and children ages 12 months and older. Do not take SINGULAIR if you need relief right away for a sudden asthma attack. If you have an asthma attack, you should follow the instructions your healthcare provider gave you for treating asthma attacks.
Prevent exercise-induced asthma in people 6 years of age and older. Help control the symptoms of allergic rhinitis such as sneezing, stuffy nose, runny nose, and itching of the nose. SINGULAIR is used to treat the following in people who have already taken other medicines that did not work well enough or in people who could not tolerate other medicines: outdoor allergies that happen part of the year (seasonal allergic rhinitis) in adults and children ages 2 years and older, and indoor allergies that happen all year (perennial allergic rhinitis) in adults and children ages 6 months and older.
Do not take SINGULAIR if you are allergic to any of its ingredients. See the end of this Medication Guide for a complete list of the ingredients in SINGULAIR. Before taking SINGULAIR, tell your healthcare provider about all your medical conditions, including if you: are allergic to aspirin. have phenylketonuria.
SINGULAIR chewable tablets contain aspartame, a source of phenylalanine. have or have had mental health problems. are pregnant or plan to become pregnant. Talk to your healthcare provider if you are pregnant or plan to become pregnant, SINGULAIR may not be right for you. are breastfeeding or plan to breastfeed. It is not known if SINGULAIR passes into your breast milk.
Talk to your healthcare provider about the best way to feed your baby while taking SINGULAIR. Tell your healthcare provider about all the medicines you take, including prescription and over the counter medicines, vitamins, and herbal supplements. Some medicines may affect how SINGULAIR works, or SINGULAIR may affect how your other medicines work.
How should I take SINGULAIR? For anyone who takes SINGULAIR: Read the detailed Instructions for Use that comes with SINGULAIR oral granules. Take SINGULAIR exactly as prescribed by your healthcare provider.
Your healthcare provider will tell you how much SINGULAIR to take, and when to take it. Stop taking SINGULAIR and tell your healthcare provider right away if you or your child have any unusual changes in behavior or thinking. You can take SINGULAIR with food or without food.
See the section " How can I give SINGULAIR oral granules to my child? " in the Instructions for Use for information about what foods and liquids can be taken with SINGULAIR oral granules. If you or your child misses a dose of SINGULAIR,… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Montelukast is rapidly absorbed following oral administration. After administration of the 10-mg film-coated tablet to fasted adults, the mean peak montelukast plasma concentration (C max ) is achieved in 3 to 4 hours (T max ). The mean oral bioavailability is 64%.
The oral bioavailability and C max are not influenced by a standard meal in the morning. For the 5-mg chewable tablet, the mean C max is achieved in 2 to 2.5 hours after administration to adults in the fasted state. The mean oral bioavailability is 73% in the fasted state versus 63% when administered with a standard meal in the morning.
For the 4-mg chewable tablet, the mean C max is achieved 2 hours after administration in pediatric patients 2 to 5 years of age in the fasted state. The 4-mg oral granule formulation is bioequivalent to the 4-mg chewable tablet when administered to adults in the fasted state. The co-administration of the oral granule formulation with applesauce did not have a clinically significant effect on the pharmacokinetics of montelukast.
A high fat meal in the morning did not affect the AUC of montelukast oral granules; however, the meal decreased C max by 35% and prolonged T max from 2.3 ± 1.0 hours to 6.4 ± 2.9 hours. The safety and effectiveness of SINGULAIR in patients with asthma were demonstrated in clinical trials in which the 10-mg film-coated tablet and 5-mg chewable tablet formulations were administered in the evening without regard to the time of food ingestion. The safety of SINGULAIR in patients with asthma was also demonstrated in clinical trials in which the 4-mg chewable tablet and 4-mg oral granule formulations were administered in the evening without regard to the time of food ingestion.
The safety and effectiveness of SINGULAIR in patients with seasonal allergic rhinitis were demonstrated in clinical trials in which the 10-mg film-coated tablet was administered in the morning or evening without regard to the time of food ingestion. The comparative pharmacokinetics of montelukast when administered as two 5-mg chewable tablets versus one 10-mg film-coated tablet have not been evaluated. Distribution Montelukast is more than 99% bound to plasma proteins.
The steady state volume of distribution of montelukast averages 8 to 11 liters. Orally administered montelukast distributes into the brain in rats. Elimination The plasma clearance of montelukast averages 45 mL/min in healthy adults.
Following an oral dose of radiolabeled montelukast, 86% of the radioactivity was recovered in 5-day fecal collections and <0.2% was recovered in urine. Coupled with estimates of montelukast oral bioavailability, this indicates that montelukast and its metabolites are excreted almost exclusively via the bile. In several studies, the mean plasma half-life of montelukast ranged from 2.7 to 5.5 hours in healthy young adults.
The pharmacokinetics of montelukast are nearly linear for oral doses up to 50 mg. During once-daily dosing with 10-mg montelukast, there is little accumulation of the parent drug in plasma (14%). Metabolism Montelukast is extensively metabolized.
In studies with therapeutic doses, plasma concentrations of metabolites of montelukast are undetectable at steady state in adults and pediatric patients. In vitro studies using human liver microsomes indicate that CYP3A4, 2C8, and 2C9 are involved in the metabolism of montelukast. At clinically relevant concentrations, 2C8 appears to play a major role in the metabolism of montelukast.
Specific Populations Patients with Hepatic Impairment Patients with mild-to-moderate hepatic insufficiency and clinical evidence of cirrhosis had evidence of decreased metabolism of montelukast resulting in 41% (90% CI=7%, 85%) higher mean montelukast AUC following a single 10-mg dose. The elimination of montelukast was slightly prolonged compared with that in healthy subjects (mean half-life, 7.4 hours). No dosage adjustment is required in patients with mild-to-moderate hepat… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Montelukast causes inhibition of airway cysteinyl leukotriene receptors as demonstrated by the ability to inhibit bronchoconstriction due to inhaled LTD 4 in asthmatics. Doses as low as 5 mg cause substantial blockage of LTD 4 -induced bronchoconstriction. In a placebo-controlled, crossover study (n=12), SINGULAIR inhibited early- and late-phase bronchoconstriction due to antigen challenge by 75% and 57%, respectively.
The effect of SINGULAIR on eosinophils in the peripheral blood was examined in clinical trials. In patients with asthma aged 2 years and older who received SINGULAIR, a decrease in mean peripheral blood eosinophil counts ranging from 9% to 15% was noted, compared with placebo, over the double-blind treatment periods. In patients with seasonal allergic rhinitis aged 15 years and older who received SINGULAIR, a mean increase of 0.2% in peripheral blood eosinophil counts was noted, compared with a mean increase of 12.5% in placebo-treated patients, over the double-blind treatment periods; this reflects a mean difference of 12.3% in favor of SINGULAIR.
The relationship between these observations and the clinical benefits of montelukast noted in the clinical trials is not known [see Clinical Studies (14) ].
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Asthma Adults and Adolescents 15 Years of Age and Older with Asthma Clinical trials in adults and adolescents 15 years of age and older demonstrated there is no additional clinical benefit to montelukast doses above 10 mg once daily. The efficacy of SINGULAIR for the chronic treatment of asthma in adults and adolescents 15 years of age and older was demonstrated in two (U.S. and Multinational) similarly designed, randomized, 12-week, double-blind, placebo-controlled trials in 1576 patients (795 treated with SINGULAIR, 530 treated with placebo, and 251 treated with active control).
The median age was 33 years (range 15 to 85); 56.8% were females and 43.2% were males. The ethnic/racial distribution in these studies was 71.6% Caucasian, 17.7% Hispanic, 7.2% other origins and 3.5% Black. Patients had mild or moderate asthma and were non-smokers who required approximately 5 puffs of inhaled β-agonist per day on an "as-needed" basis.
The patients had a mean baseline percent of predicted forced expiratory volume in 1 second (FEV 1 ) of 66% (approximate range, 40 to 90%). The co-primary endpoints in these trials were FEV 1 and daytime asthma symptoms. In both studies after 12 weeks, a random subset of patients receiving SINGULAIR was switched to placebo for an additional 3 weeks of double-blind treatment to evaluate for possible rebound effects.
The results of the U.S. trial on the primary endpoint, morning FEV 1 , expressed as mean percent change from baseline averaged over the 12-week treatment period, are shown in FIGURE 2. Compared with placebo, treatment with one SINGULAIR 10-mg tablet daily in the evening resulted in a statistically significant increase in FEV 1 percent change from baseline (13.0%-change in the group treated with SINGULAIR vs. 4.2%-change in the placebo group, p<0.001); the change from baseline in FEV 1 for SINGULAIR was 0.32 liters compared with 0.10 liters for placebo, corresponding to a between-group difference of 0.22 liters (p<0.001, 95% CI 0.17 liters, 0.27 liters).
The results of the Multinational trial on FEV 1 were similar. Figure 2: FEV 1 Mean Percent Change from Baseline (U.S. Trial: SINGULAIR N=406; Placebo N=270) (ANOVA Model) The effect of SINGULAIR on other primary and secondary endpoints, represented by the Multinational study is shown in TABLE 6 .
Results on these endpoints were similar in the US study. Table 6: Effect of SINGULAIR on Primary and Secondary Endpoints in a Multinational Placebo-controlled Trial (ANOVA Model) SINGULAIR Placebo Endpoint N Baseline Mean Change from Baseline N Baseline Mean Change from Baseline Daytime Asthma Symptoms (0 to 6 scale) 372 2.35 -0.49 p<0.001, compared with placebo 245 2.40 -0.26 β-agonist (puffs per day) 371 5.35 -1.65 241 5.78 -0.42 AM PEFR (L/min) 372 339.57 25.03 244 335.24
1.83PM PEFR (L/min) 372 355.23 20.13 244 354.02 -0.49 Nocturnal Awakenings (#/week) 285 5.46 -2.03 195 5.57 -0.78 Both studies evaluated the effect of SINGULAIR on secondary outcomes, including asthma attack (utilization of health-care resources such as an unscheduled visit to a doctor's office, emergency room, or hospital; or treatment with oral, intravenous, or intramuscular corticosteroid), and use of oral corticosteroids for asthma rescue. In the Multinational study, significantly fewer patients (15.6% of patients) on SINGULAIR experienced asthma attacks compared with patients on placebo (27.3%, p<0.001).
In the US study, 7.8% of patients on SINGULAIR and 10.3% of patients on placebo experienced asthma attacks, but the difference between the two treatment groups was not significant (p=0.334). In the Multinational study, significantly fewer patients (14.8% of patients) on SINGULAIR were prescribed oral corticosteroids for asthma rescue compared with patients on placebo (25.7%, p<0.001). In the US study, 6.9% of patients on SINGULAIR and 9.9% of patients on placebo were prescribed oral corticosteroids for asthma rescue, but the difference between the two… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No evidence of tumorigenicity was seen in carcinogenicity studies of either 2 years in Sprague-Dawley rats or 92 weeks in mice at oral gavage doses up to 200 mg/kg/day or 100 mg/kg/day, respectively. The estimated exposure in rats was approximately 120 and 75 times the AUC for adults and children, respectively, at the maximum recommended daily oral dose. The estimated exposure in mice was approximately 45 and 25 times the AUC for adults and children, respectively, at the maximum recommended daily oral dose.
Montelukast demonstrated no evidence of mutagenic or clastogenic activity in the following assays: the microbial mutagenesis assay, the V-79 mammalian cell mutagenesis assay, the alkaline elution assay in rat hepatocytes, the chromosomal aberration assay in Chinese hamster ovary cells, and in the in vivo mouse bone marrow chromosomal aberration assay. In fertility studies in female rats, montelukast produced reductions in fertility and fecundity indices at an oral dose of 200 mg/kg (estimated exposure was approximately 70 times the AUC for adults at the maximum recommended daily oral dose).
No effects on female fertility or fecundity were observed at an oral dose of 100 mg/kg (estimated exposure was approximately 20 times the AUC for adults at the maximum recommended daily oral dose). Montelukast had no effects on fertility in male rats at oral doses up to 800 mg/kg (estimated exposure was approximately 160 times the AUC for adults at the maximum recommended daily oral dose).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No evidence of tumorigenicity was seen in carcinogenicity studies of either 2 years in Sprague-Dawley rats or 92 weeks in mice at oral gavage doses up to 200 mg/kg/day or 100 mg/kg/day, respectively. The estimated exposure in rats was approximately 120 and 75 times the AUC for adults and children, respectively, at the maximum recommended daily oral dose. The estimated exposure in mice was approximately 45 and 25 times the AUC for adults and children, respectively, at the maximum recommended daily oral dose.
Montelukast demonstrated no evidence of mutagenic or clastogenic activity in the following assays: the microbial mutagenesis assay, the V-79 mammalian cell mutagenesis assay, the alkaline elution assay in rat hepatocytes, the chromosomal aberration assay in Chinese hamster ovary cells, and in the in vivo mouse bone marrow chromosomal aberration assay. In fertility studies in female rats, montelukast produced reductions in fertility and fecundity indices at an oral dose of 200 mg/kg (estimated exposure was approximately 70 times the AUC for adults at the maximum recommended daily oral dose).
No effects on female fertility or fecundity were observed at an oral dose of 100 mg/kg (estimated exposure was approximately 20 times the AUC for adults at the maximum recommended daily oral dose). Montelukast had no effects on fertility in male rats at oral doses up to 800 mg/kg (estimated exposure was approximately 160 times the AUC for adults at the maximum recommended daily oral dose).
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE SINGULAIR ® (SING-u-lair) (montelukast sodium) oral granules This Instructions for Use contains information on how to use SINGULAIR oral granules. Important Information: Before giving a dose of SINGULAIR oral granules, read this Instructions for Use to be sure you prepare and give the oral granules correctly. Give SINGULAIR oral granules to your child exactly as instructed by your healthcare provider.
Stop giving SINGULAIR and tell your healthcare provider right away if your child has any unusual changes in behavior or thinking. Continue to give your child their asthma medicines as prescribed, unless your healthcare provider tells you to change how you give these medicines. You can give SINGULAIR oral granules with food or without food.
How can I give SINGULAIR oral granules to my child? Do not open the packet until ready to use. There are different ways you can give SINGULAIR 4-mg oral granules.
You should choose the best method for your child: right into the mouth dissolved in 1 teaspoonful (5 mL) of cold or room temperature baby formula or breast milk mixed with 1 spoonful of one of the following soft foods at cold or room temperature: applesauce, mashed carrots, rice, or ice cream. Give the child all of the mixture within 15 minutes. Do not store any leftover SINGULAIR mixture (oral granules mixed with food, baby formula, or breast milk) for use at a later time.
Throw away any unused portion. Do not mix SINGULAIR oral granules with any liquid drink other than baby formula or breast milk. Your child may drink other liquids after swallowing the mixture.
How should I store SINGULAIR? Store SINGULAIR at room temperature between 68°F to 77°F (20°C to 25°C). Keep SINGULAIR in the package it comes in.
Keep SINGULAIR in a dry place and keep it away from light. Keep SINGULAIR and all medicines out of the reach of children. Dist. by: Organon LLC, a subsidiary of ORGANON & Co., Jersey City, NJ 07302, USA For patent information: www.organon.com/our-solutions/patent/ Copyright © 2021 Organon Global Inc.
All rights reserved. usifu-og0476-og-2106r000 For more information, call 1-844-674-3200 This Instructions for Use has been approved by the U.S. Food and Drug Administration Revised: June 2021
📄 Recent Major Changes ▾
Indications and Usage ( 1.3 , 1.4 ) 02/2021 Dosage and Administration ( 2.1 , 2.2 , 2.3 , 2.4 ) 02/2021 Warnings and Precautions ( 5.1 , 5.6 ) 02/2021
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 4 mg Packet Carton Singulair ® 4 mg (Montelukast Sodium) ORAL GRANULES NDC 78206-171-01 For Pediatric Patients 6 months to 5 years of age. Dist. by: Organon LLC, a subsidiary of ORGANON & Co., Jersey City, NJ 07302, USA Manuf. by: Patheon Manufacturing Services LLC Greenville, NC 27834, USA Montelukast Sodium (active ingred.) Made in Ireland Formulated in USA Attention Health Care Professional: Dispense the enclosed Medication Guide to each patient. DIRECTIONS FOR USE: See accompanying Prescribing Information.
Once opened, use the contents of this packet within 15 minutes (with or without mixing with food). Discard any unused portion. Rx only PRINCIPAL DISPLAY PANEL - 4 mg Packet Carton
PRINCIPAL DISPLAY PANEL - 4 mg Tablet Bottle Label NDC 78206-170-01 Singulair ® (Montelukast Sodium) CHEWABLE Tablets 4 mg Dispense the accompanying Medication Guide to each patient. For Pediatric Patients 2-5 Years of Age Phenylketonurics: contains phenylalanine (a component of aspartame) 0.674 mg per 4-mg chewable tablet. Each tablet contains 4.2 mg Montelukast Sodium equivalent to 4 mg Montelukast.
Rx only 30 Tablets PRINCIPAL DISPLAY PANEL - 4 mg Tablet Bottle Label
PRINCIPAL DISPLAY PANEL - 5 mg Tablet Bottle Label NDC 78206-173-01 Singulair ® (Montelukast Sodium) CHEWABLE Tablets 5 mg Dispense the accompanying Medication Guide to each patient. For Pediatric Patients 6-14 Years of Age Phenylketonurics: contains phenylalanine (a component of aspartame) 0.842 mg per 5-mg chewable tablet. Each tablet contains 5.2 mg Montelukast Sodium equivalent to 5 mg Montelukast.
Rx only 30 Tablets PRINCIPAL DISPLAY PANEL - 5 mg Tablet Bottle Label
PRINCIPAL DISPLAY PANEL - 10 mg Tablet Bottle Label NDC 78206-172-01 Singulair ® (Montelukast Sodium) Tablets 10 mg Dispense the accompanying Medication Guide to each patient. For Adults 15 Years of Age and Older Each tablet contains 10.4 mg Montelukast Sodium equivalent to 10 mg Montelukast. Rx only 30 Tablets PRINCIPAL DISPLAY PANEL - 10 mg Tablet Bottle Label
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |