
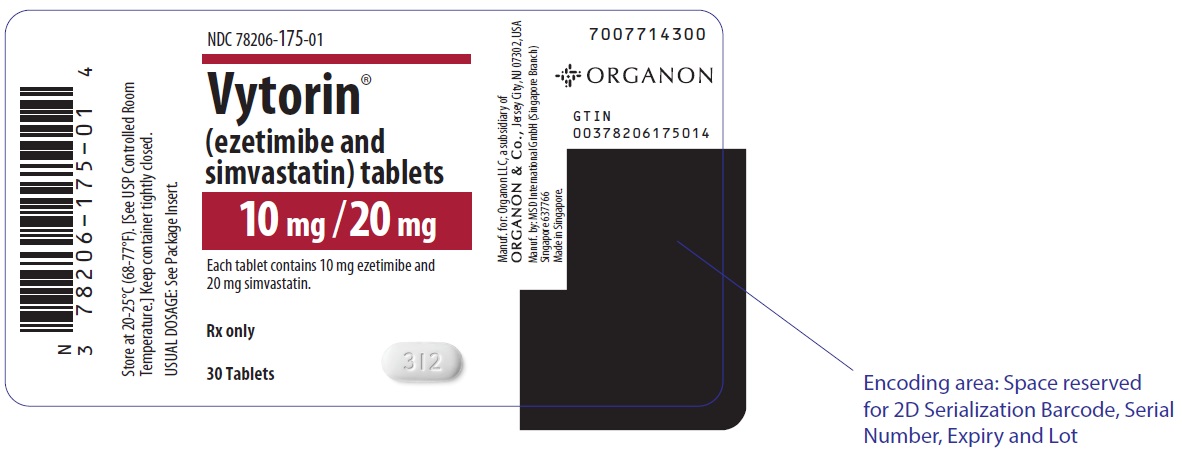
VYTORIN ezetimibe and simvastatin 10 mg; 20 mg Tablet, 30-count
Other active recalls for Ezetimibe And Simvastatin (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Dietary Cholesterol Absorption Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Ezetimibe is used along with diet, alone or in combination with another cholesterol-lowering medications (HMG-CoA reductase inhibitors [statins]) to reduce the amount of low-density lipoprotein (LDL) cholesterol ('bad cholesterol') in the blood in adults and children 10 years of age or older who have familial heterozygous hypercholesterolemia (an inherited condition in which cholesterol cannot be removed from the body normally). It is also used along with diet, alone or in combination with other cholesterol-lowering medications (HMG-CoA reductase inhibitors [statins] or fenofibrate) in adults...
Read the full MedlinePlus article ↗- Great question. Your body gets cholesterol from two sources: food you eat and what your liver makes on its own. Ezetimibe handles the first source — it blocks cholesterol from bein...
- What exactly does this medication do, and why do I need two drugs in one pill?
- Take it once a day in the evening — that timing helps because your body tends to make more cholesterol overnight. You can take it with or without food, so meal timing is flexible....
- When should I take it, and does it matter if I eat first?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII REK4960K2U
Butylated hydroxyanisole is a synthetic preservative that prevents oils and fats in medicines from spoiling or becoming rancid. It keeps the medicine stable and extends its shelf life.
-
UNII 2968PHW8QP
A weak organic acid derived from citrus fruits or made through fermentation. It works as a buffer to control pH, a preservative to extend shelf life, and a flavoring agent in medications.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 8D4SNN7V92
Propyl gallate is a synthetic antioxidant derived from gallic acid. It prevents oils and fats in the medicine from oxidizing and spoiling, helping the product stay stable and effective during storage.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $13.621 | $408.62 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $14.19 | $425.84 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ezetimibe and Simvastatin 10 mg/1; 20 mg 43598-0744-10 | Dr.Reddys | 1000 tablets | $0.228 | AB | Availability likely | save 98% |
| ezetimibe and simvastatin 10 mg/1; 20 mg 16714-0779-01 | NORTHSTAR | 30 tablets | $0.267 | AB | Discontinued | save 98% |
| Ezetimibe and Simvastatin 10 mg/1; 20 mg 69238-1156-03 | Amneal | 30 tablets | $0.482 | — | FDA listed | save 96% |
| Vytorin 10 mg/1; 20 mgthis 78206-0175-01 | Organon | 30 tablets | $13.621 | AB | Availability likely | — |
| Ezetimibe and Simvastatin 10 mg/1; 20 mg 51407-0191-10 | Golden | 1000 tablets | — | AB | FDA listed | — |
| Ezetimibe and Simvastatin 10 mg/1; 20 mg 59651-0836-30 | Aurobindo | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe and Simvastatin 10 mg/1; 20 mg 67877-0508-01 | Ascend | 1000 tablets | — | AB | FDA listed | — |
| ezetimibe and simvastatin 10 mg/1; 20 mg 68462-0322-10 | Glenmark | 1000 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 78206-0175-01 You're viewing this | 30 TABLET in 1 BOTTLE (78206-175-01) | $13.62 / ea | $408.62 | 2021-06-01 | Active |
| 78206-0175-02 | 90 TABLET in 1 BOTTLE (78206-175-02) | $13.62 / ea | $1,225.85 | 2021-06-01 | Active |
You're viewing the smallest of 2 pack sizes for this product.
This pack has the lowest per-ea cost of the 2 priced pack sizes ($13.62 NADAC).
Pack size FAQ
What quantity is in NDC 78206-0175-01?
What is the difference between NDC 78206-0175-01 and NDC 78206-0175-02?
What NDC number is used to bill for this package of VYTORIN ezetimibe and simvastatin 10 mg; 20 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE VYTORIN VYTORIN ® is a combination of simvastatin and ezetimibe indicated: As an adjunct to diet to reduce elevated low density lipoprotein cholesterol (LDL-C): In adults with primary hyperlipidemia. In adults and pediatric patients aged 10 years and older with heterozygous familial hypercholesterolemia (HeFH). As an adjunct to other LDL-C-lowering therapies to reduce elevated LDL-C in adults with homozygous familial hypercholesterolemia (HoFH).
Simvastatin Simvastatin, when used as a component of VYTORIN, is indicated to reduce the risk of total mortality by reducing risk of coronary heart disease death, non-fatal myocardial infarction and stroke, and the need for coronary and non-coronary revascularization procedures in adults with established coronary heart disease, cerebrovascular disease, peripheral vascular disease, and/or diabetes, who are at high risk of coronary heart disease events. VYTORIN is a combination of ezetimibe, a dietary cholesterol absorption inhibitor, and simvastatin, an HMG-CoA reductase inhibitor (statin) indicated: ( 1 ) As an adjunct to diet to reduce elevated low density lipoprotein cholesterol (LDL-C): In adults with primary hyperlipidemia.
In adults and pediatric patients aged 10 years and older with heterozygous familial hypercholesterolemia (HeFH). As an adjunct to other LDL-C lowering therapies to reduce LDL-C in adults with homozygous familial hypercholesterolemia (HoFH). Simvastatin Simvastatin, when used as a component of VYTORIN, is indicated to reduce the risk of total mortality by reducing risk of coronary heart disease death, non-fatal myocardial infarction and stroke, and the need for coronary and non-coronary revascularization procedures in adults with established coronary heart disease, cerebrovascular disease, peripheral vascular disease, and/or diabetes, who are at high risk of coronary heart disease events.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Important Dosage and Administration Information: ( 2.1 ) Take VYTORIN orally once daily in the evening with or without food. Maximum recommended dosage is VYTORIN 10/40 mg once daily. VYTORIN 10/80 mg daily dosage is restricted to patients who have been taking VYTORIN 10/80 mg daily chronically (e.g., for 12 months or more) without evidence of muscle toxicity.
For patients that require a high-intensity statin or are unable to achieve their LDL-C goal receiving VYTORIN 10/40 mg daily, prescribe alternative LDL-C-lowering treatment. If as dose is missed, take the missed dose as soon as possible. Do not double the next dose.
Assess LDL-C when clinically appropriate, as early as 2 weeks after initiating VYTORIN, and adjust the dosage if necessary. Adults: Recommended dosage range of 10/10 mg to 10/40 mg once daily. ( 2.2 ) See full prescribing information for VYTORIN dosage modifications due to drug interactions.
( 2.3 ) Patients with Renal Impairment: Doses exceeding 10/20 mg should be used with caution and close monitoring in patients with moderate to severe renal impairment. ( 2.4 )
2.1Important Dosage and Administration Information Take VYTORIN orally once daily in the evening with or without food. The maximum recommended dosage is VYTORIN 10/40 mg once daily. The VYTORIN 10/80 mg daily dosage is restricted to adult patients who have been taking VYTORIN 10/80 mg daily chronically (e.g., for 12 months or more) without evidence of muscle toxicity [see Warnings and Precautions (5.1) ] .
For patients that require a high-intensity statin or are unable to achieve their LDL-C goal receiving VYTORIN 10/40 mg daily, prescribe alternative LDL-C-lowering treatment. If as dose is missed, take the missed dose as soon as possible. Do not double the next dose.
Assess LDL-C when clinically appropriate, as early as 4 weeks after initiating VYTORIN, and adjust the dosage if necessary.
2.2Recommended Dosage in Adult Patients The recommended dosage range of VYTORIN 10/10 mg to 10/40 mg once a day.
2.3Recommended Dosage in Pediatric Patients 10 Years of Age and Older with HeFH The recommended dosage range of VYTORIN 10/10 mg to 10/40 mg once a day.
2.4Recommended Dosage in Patients with Renal Impairment Renal impairment is a risk factor for statin-associated myopathy. Doses of VYTORIN exceeding 10/20 mg should be used with caution and close monitoring in patients with moderate to severe renal impairment [see Warnings and Precautions (5.1) and Use in Specific Populations (8.6) ] . There are no dosage adjustment recommendations for patients with mild renal impairment.
2.5Dosage Modifications Due to Drug Interactions Concomitant use of VYTORIN with the following drugs requires dosage modification of VYTORIN [see Warnings and Precautions (5.1) and Drug Interactions (7.1) ] . Patients taking Lomitapide Reduce the dosage of VYTORIN by 50%. Do not exceed VYTORIN 10/20 mg once daily (or 10/40 mg once daily for patients who have previously taken VYTORIN 10/80 mg daily chronically while taking lomitapide) [see Dosage and Administration (2.1) ] .
Patients taking Verapamil, Diltiazem, or Dronedarone Do not exceed VYTORIN 10/10 mg once daily. Patients taking Amiodarone, Amlodipine, or Ranolazine Do not exceed VYTORIN 10/20 mg once daily. Patients taking Bile Acid Sequestrants In patients taking a bile acid sequestrant, administer VYTORIN at least 2 hours before or 4 hours after the bile acid sequestrant.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS VYTORIN tablets: 10/10, (ezetimibe 10 mg and simvastatin 10 mg tablets) are white to off-white capsule-shaped and debossed with “311” on one side. 10/20, (ezetimibe 10 mg and simvastatin 20 mg tablets) are white to off-white capsule-shaped and debossed with “312” on one side. 10/40, (ezetimibe 10 mg and simvastatin 40 mg tablets) are white to off-white capsule-shaped and debossed with “313” on one side.
10/80, (ezetimibe 10 mg and simvastatin 80 mg tablets) are white to off-white capsule-shaped and debossed with “315” on one side. Tablets (ezetimibe mg/simvastatin mg): 10/10, 10/20, 10/40, 10/80 ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS VYTORIN is contraindicated in the following conditions: Concomitant use of strong CYP3A4 inhibitors (select azole anti-fungals, macrolide antibiotics, anti-viral medications, and nefazodone) [see Drug Interactions (7.1) ] . Concomitant use of cyclosporine, danazol, or danazol [see Drug Interactions (7.1) ] . Acute liver failure or decompensated cirrhosis [see Warnings and Precautions (5.3) ] .
Hypersensitivity to simvastatin, ezetimibe, or any excipients in VYTORIN. Hypersensitivity reactions, including anaphylaxis, angioedema, and Stevens-Johnson syndrome, have been reported [see Adverse Reactions (6.2) ] . Concomitant use of strong CYP3A4 inhibitors (select azole anti-fungals, macrolide antibiotics, anti-viral medications and nefazodone).
( 4 ) Concomitant use of cyclosporine, danazol or gemfibrozil. ( 4 ) Acute liver failure or decompensated cirrhosis. ( 4 ) Hypersensitivity to simvastatin, ezetimibe or any excipient of VYTORIN.
( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Myopathy and Rhabdomyolysis: Risk factors include age 65 years or greater, uncontrolled hypothyroidism, renal impairment, concomitant use with certain other drugs, and higher VYTORIN dosage. Chinese patients may be at higher risk for myopathy. Discontinue VYTORIN if markedly elevated CK levels occur or myopathy is diagnosed or suspected.
Temporarily discontinue VYTORIN in patients experiencing an acute or serious condition at high risk of developing renal failure secondary to rhabdomyolysis. Inform patients of the risk of myopathy and rhabdomyolysis when starting or increasing VYTORIN dosage. Instruct patients to promptly report unexplained muscle pain, tenderness, or weakness, particularly if accompanied by malaise or fever.
( 5.1 ) Immune-Mediated Necrotizing Myopathy (IMNM): Rare reports of IMNM, an autoimmune myopathy, have been reported. Discontinue VYTORIN if IMNM is suspected. ( 5.2 ) Hepatic Dysfunction: Increases in serum transaminases have occurred, some persistent.
Rare reports of fatal and non-fatal hepatic failure have occurred. Consider testing liver enzyme before initiating therapy and as clinically indicated thereafter. If serious hepatic injury with clinical symptoms and/or hyperbilirubinemia or jaundice occurs, promptly discontinue VYTORIN.
( 5.3 )
5.1Myopathy and Rhabdomyolysis VYTORIN may cause myopathy and rhabdomyolysis. Acute kidney injury secondary to myoglobinuria and rare fatalities have occurred as a result of rhabdomyolysis in patients treated with statins, including VYTORIN. In clinical trials of 24,747 simvastatin-treated patients with a median follow-up of 4 years, the incidence of myopathy, defined as unexplained muscle weakness, pain, or tenderness accompanied by creatinine kinase (CK) increases greater than ten times the upper limit of normal (10 X ULN), were approximately 0.03%, 0.08%, and 0.61% in patients treated with simvastatin 20 mg, 40 mg, and 80 mg daily, respectively.
In another clinical trial of 12,064 simvastatin-treated patients (with a history of myocardial infarction) with a mean follow-up of 6.7 years, the incidences of myopathy in patients taking simvastatin 20 mg and 80 mg daily were approximately 0.02% and 0.9%, respectively. The incidences of rhabdomyolysis (defined as myopathy with a CK >40 X ULN) in patients taking simvastatin 20 mg and 80 mg daily were approximately 0% and 0.4%, respectively [see Adverse Reactions (6.1) ] . In the Trial of Heart and Renal Protection (SHARP), 9270 patients with chronic kidney disease were allocated to receive VYTORIN 10/20 mg daily (n=4650) or placebo (n=4620).
During a median follow-up period of 4.9 years, the incidence of myopathy (defined as unexplained muscle weakness or pain with a serum creatine kinase [CK] >10 times upper limit of normal [ULN]) was 0.2% for VYTORIN and 0.1% for placebo: the incidence of rhabdomyolysis (defined as myopathy with a CK > 40 times ULN) was 0.09% for VYTORIN and 0.02% for placebo. In postmarketing experience with ezetimibe, cases of myopathy and rhabdomyolysis have been reported. Most patients who developed rhabdomyolysis were taking a statin prior to initiating ezetimibe.
However, rhabdomyolysis has been reported with ezetimibe monotherapy and with the addition of ezetimibe to agents known to be associated with increased risk of rhabdomyolysis, such as fibric acid derivatives. VYTORIN and a fenofibrate, if taking concomitantly, should both be immediately discontinued if myopathy is diagnosed or suspected. Risk Factors for Myopathy Risk factors for myopathy include age 65 years or greater, uncontrolled hypothyroidism, renal impairment, concomitant use with certain other drugs (including other lipid-lowering therapies), and higher VYTORIN dosage; Chinese patients on VYTORIN may be at higher risk for myopathy [see Contraindications (4) , Drug Interactions (7.1) , and Use in Specific Populations (8.8) ] .
The risk of myopathy is increased by elevated plasma levels of simvastatin a…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed in greater detail in other sections of the label: Myopathy and Rhabdomyolysis [see Warnings and Precautions (5.1) ] Immune-Mediated Necrotizing Myopathy [see Warnings and Precautions (5.2) ] Hepatic Dysfunction [see Warnings and Precautions (5.3) ] Increases in HbA1c and Fasting Serum Glucose Levels [see Warnings and Precautions (5.4) ] Common (incidence ≥2% and greater than placebo) adverse reactions in clinical trials: headache, increased ALT, myalgia, upper respiratory tract infection, and diarrhea.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Organon LLC, a subsidiary of Organon & Co., at 1-844-674-3200 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. VYTORIN In the VYTORIN (ezetimibe and simvastatin) placebo-controlled clinical trials database of 1420 patients (age range 20-83 years, 52% female, 87% White, 3% Black or African American, 3% Asians, 5% other races identified as Hispanic or Latino ethnicity) with a median treatment duration of 27 weeks, 5% of patients on VYTORIN and 2.2% of patients on placebo discontinued due to adverse reactions.
The most commonly reported adverse reactions (incidence ≥2% and greater than placebo) in controlled clinical trials were: headache (5.8%), increased ALT (3.7%), myalgia (3.6%), upper respiratory tract infection (3.6%), and diarrhea (2.8%). The most common adverse reactions in the group treated with VYTORIN that led to treatment discontinuation and occurred at a rate greater than placebo were: increased ALT (0.9%), myalgia (0.6%), increased AST (0.4%), and back pain (0.4%). VYTORIN has been evaluated for safety in more than 10,189 patients in clinical trials.
Table 1 summarizes the frequency of clinical adverse reactions reported in ≥2% of patients treated with VYTORIN (n=1420) and at an incidence greater than placebo from four placebo-controlled trials. Table 1 Includes two placebo-controlled combination studies in which the active ingredients equivalent to VYTORIN were coadministered and two placebo-controlled studies in which VYTORIN was administered. : Adverse Reactions Reported ≥2% of Patients Treated with VYTORIN at an Incidence Greater than Placebo Regardless of Causality % Placebo N = 371 % Ezetimibe 10 mg N = 302 % Simvastatin All doses.
N = 1234 % VYTORIN N = 1420 Headache 5.4 6.0 5.9
5.8Upper respiratory tract infection 2.7 5.0 5.0
3.6Myalgia 2.4 2.3 2.6
3.6Diarrhea 2.2 5.0 3.7
2.8Pain in extremity 1.3 3.0 2.0
2.3Influenza 0.8 1.0 1.9
2.3Study of Heart and Renal Protection In SHARP , 9270 patients were allocated to VYTORIN 10/20 mg daily (n=4650) or placebo (n=4620) for a median follow-up period of 4.9 years. The proportion of patients who permanently discontinued trial treatment as a result of either an adverse event or abnormal safety blood result was 10.4% vs. 9.8% among patients allocated to VYTORIN and placebo, respectively.
Comparing those allocated to VYTORIN vs. placebo, the incidence of myopathy (defined as unexplained muscle weakness or pain with a serum CK >10 times ULN) was 0.2% vs. 0.1% and the incidence of rhabdomyolysis (defined as myopathy with a CK >40 times ULN) was 0.09% vs. 0.02%, respectively.
Consecutive elevations of transaminases (>3 X ULN) occurred in 0.7% vs. 0.6%, respectively. Patients were asked about the occurrence of unexplained muscle pain or weakness at each trial visit: 21.5% vs.
20.9% patients ever reported muscle symptoms in the VYTORIN and placebo groups, respectively. Cancer was diagnosed during the trial in 9.4% vs. 9.5% of patients assigned to VYTORIN and placebo, respectively.
Ezetimibe Other adverse reactions reported with ezetimibe in placebo-control…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS VYTORIN See full prescribing information for details regarding concomitant use of VYTORIN with other drugs or grapefruit juice that increase the risk of myopathy and rhabdomyolysis. ( 2.3 , 7.1 ) Cholestyramine: Combination decreases exposure of ezetimibe. ( 2.3 , 7.2 ) Coumarin Anticoagulants: Obtain INR before VYTORIN initiation and monitor INR during VYTORIN dosage initiation or adjustment.
( 7.3 ) Digoxin : During VYTORIN initiation, monitor digoxin levels. ( 7.3 ) Fenofibrates: Combination increases exposure of ezetimibe. If cholelithiasis is suspected in a patient receiving ezetimibe and a fenofibrate, gallbladder studies are indicated and alternative lipid-lowering therapy should be considered.
( 7.3 , 12.3 )
7.1Drug Interactions that Increase the Risk of Myopathy and Rhabdomyolysis with VYTORIN VYTORIN is a substrate of CYP3A4 and of the transport protein OATP1B1. VYTORIN plasma levels can be significantly increased with concomitant administration of inhibitors of CYP3A4 and OATP1B1. Table 2 includes a list of drugs that increase the risk of myopathy and rhabdomyolysis when used concomitantly with VYTORIN and instructions for preventing or managing them [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.3) ] .
Table 2: Drug Interactions that Increase the Risk of Myopathy and Rhabdomyolysis with VYTORIN Strong CYP3A4 inhibitors Clinical Impact: Simvastatin is a substrate of CYP3A4. Concomitant use of strong CYP3A4 inhibitors with VYTORIN increases simvastatin exposure and increases the risk of myopathy and rhabdomyolysis, particularly with higher VYTORIN dosages. Intervention: Concomitant use of strong CYP3A4 inhibitors with VYTORIN is contraindicated [see Contraindications (4) ] .
If treatment with a CYP3A4 inhibitor is unavoidable, suspend VYTORIN during the course of strong CYP3A4 inhibitor treatment. Examples: Select azole anti-fungals (e.g., itraconazole, ketoconazole, posaconazole, and voriconazole), select macrolide antibiotics (e.g., erythromycin and clarithromycin, telithromycin), select HIV protease inhibitors (e.g., nelfinavir, ritonavir, and darunavir/ritonavir), select HCV protease inhibitors (e.g., boceprevir and telaprevir), cobicistat-containing products, and nefazodone. Cyclosporine, Danazol, or Gemfibrozil Clinical Impact: The risk of myopathy and rhabdomyolysis is increased with concomitant use of cyclosporine, danazol, or gemfibrozil with VYTORIN.
Gemfibrozil may cause myopathy when given alone. Intervention: Concomitant use of cyclosporine, danazol, or gemfibrozil with VYTORIN is contraindicated [see Contraindications (4) ] . Amiodarone, Dronedarone, Ranolazine, or Calcium Channel Blockers Clinical Impact: The risk of myopathy and rhabdomyolysis is increased by concomitant use of amiodarone, dronedarone, ranolazine, or calcium channel blockers with VYTORIN.
Intervention: For patients taking verapamil, diltiazem, or dronedarone, do not exceed VYTORIN 10/10 mg daily. For patients taking amiodarone, amlodipine, or ranolazine, do not exceed VYTORIN 10/20 mg daily [see Dosage and Administration (2.3) ] . Lomitapide Clinical Impact: Simvastatin exposure is approximately doubled with concomitant use of lomitapide and the risk of myopathy and rhabdomyolysis is increased.
Intervention: Reduce the dose of VYTORIN by 50% if initiating lomitapide. Do not exceed VYTORIN 10/20 mg daily (or VYTORIN 10/40 mg daily for patients who have previously taken VYTORIN 10/80 mg daily chronically) while taking lomitapide [see Dosage and Administration (2.1 , 2.3) ] . Daptomycin Clinical Impact: Cases of rhabdomyolysis have been reported with simvastatin administered with daptomycin.
Both VYTORIN and daptomycin can cause myopathy and rhabdomyolysis when given alone and the risk of myopathy and rhabdomyolysis may be increased by coadministration. Intervention: If treatment with daptomycin is required, consider temporarily suspending VYTORIN during the course of daptomycin treatment. Niacin C…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: May cause fetal harm ( 8.1 ) Lactation: Breastfeeding not recommended during treatment with VYTORIN. ( 8.2 )
8.1Pregnancy VYTORIN Risk Summary Discontinue VYTORIN when pregnancy is recognized. Alternatively, consider the ongoing therapeutic needs of the individual patient. VYTORIN decreases synthesis of cholesterol and possibly other biologically active substances derived from cholesterol; therefore, VYTORIN may cause fetal harm when administered to pregnant patients based on the mechanism of action [see Clinical Pharmacology (12.1) ] .
In addition, treatment of hyperlipidemia is not generally necessary during pregnancy. Atherosclerosis is a chronic process and the discontinuation of lipid-lowering drugs during pregnancy should have little impact on the outcome of long-term therapy of primary hyperlipidemia for most patients. Available data from case series and prospective and retrospective observational cohort studies over decades of use with statins in pregnant women have not identified a drug-associated risk of major congenital malformations.
Published data from prospective and retrospective observational cohort studies with VYTORIN use in pregnant women are insufficient to determine if there is a drug-associated risk of miscarriage (see Data ) . In animal reproduction studies, no adverse developmental effects were observed in pregnant rats or rabbits orally administered simvastatin during the period of organogenesis at doses that resulted in 2.5 and 2 times, respectively, the human exposure at the maximum recommended human dosage of 80 mg/day, based on body surface area (mg/m 2 ).
In animal reproduction studies, no adverse developmental effects were observed in pregnant rats and rabbits orally administered ezetimibe during the period of organogenesis at doses that resulted in up to 10 and 150 times, respectively, the human exposure at the MRHD, based on AUC (see Data ). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Human Data Ezetimibe There are insufficient data on ezetimibe use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. Simvastatin A Medicaid cohort linkage trial of 1152 statin-exposed pregnant women compared to 886,996 controls did not find a significant teratogenic effect from maternal use of statins in the first trimester of pregnancy, after adjusting for potential confounders – including maternal age, diabetes mellitus, hypertension, obesity, and alcohol and tobacco use – using propensity score-based methods.
The relative risk of congenital malformations between the group with statin use and the group with no statin use in the first trimester was 1.07 (95% confidence interval 0.85 to 1.37) after controlling for confounders, particularly pre-existing diabetes mellitus. There were also no statistically significant increases in any of the organ-specific malformations assessed after accounting for confounders. In the majority of pregnancies, statin treatment was initiated prior to pregnancy and was discontinued at some point in the first trimester when pregnancy was identified.
Trial limitations include reliance on physician coding to define the presence of a malformation, lack of control for certain confounders such as body mass index, use of prescription dispensing as verification for the use of a statin, and lack of information on non-live births. Animal Data Ezetimibe In oral (gavage) embryo-fetal development studies of ezetimibe conducted in rats (gestation days 6-15) and rabbits (gestation days 7-19), there was no evidence of maternal toxicity or embryolethality at any dose tested (250, 500, 1000 mg/kg/day) at exposure equivalent to 10 to 150…
🤰 Pregnancy ▾
8.1Pregnancy VYTORIN Risk Summary Discontinue VYTORIN when pregnancy is recognized. Alternatively, consider the ongoing therapeutic needs of the individual patient. VYTORIN decreases synthesis of cholesterol and possibly other biologically active substances derived from cholesterol; therefore, VYTORIN may cause fetal harm when administered to pregnant patients based on the mechanism of action [see Clinical Pharmacology (12.1) ] .
In addition, treatment of hyperlipidemia is not generally necessary during pregnancy. Atherosclerosis is a chronic process and the discontinuation of lipid-lowering drugs during pregnancy should have little impact on the outcome of long-term therapy of primary hyperlipidemia for most patients. Available data from case series and prospective and retrospective observational cohort studies over decades of use with statins in pregnant women have not identified a drug-associated risk of major congenital malformations.
Published data from prospective and retrospective observational cohort studies with VYTORIN use in pregnant women are insufficient to determine if there is a drug-associated risk of miscarriage (see Data ) . In animal reproduction studies, no adverse developmental effects were observed in pregnant rats or rabbits orally administered simvastatin during the period of organogenesis at doses that resulted in 2.5 and 2 times, respectively, the human exposure at the maximum recommended human dosage of 80 mg/day, based on body surface area (mg/m 2 ).
In animal reproduction studies, no adverse developmental effects were observed in pregnant rats and rabbits orally administered ezetimibe during the period of organogenesis at doses that resulted in up to 10 and 150 times, respectively, the human exposure at the MRHD, based on AUC (see Data ). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Human Data Ezetimibe There are insufficient data on ezetimibe use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. Simvastatin A Medicaid cohort linkage trial of 1152 statin-exposed pregnant women compared to 886,996 controls did not find a significant teratogenic effect from maternal use of statins in the first trimester of pregnancy, after adjusting for potential confounders – including maternal age, diabetes mellitus, hypertension, obesity, and alcohol and tobacco use – using propensity score-based methods.
The relative risk of congenital malformations between the group with statin use and the group with no statin use in the first trimester was 1.07 (95% confidence interval 0.85 to 1.37) after controlling for confounders, particularly pre-existing diabetes mellitus. There were also no statistically significant increases in any of the organ-specific malformations assessed after accounting for confounders. In the majority of pregnancies, statin treatment was initiated prior to pregnancy and was discontinued at some point in the first trimester when pregnancy was identified.
Trial limitations include reliance on physician coding to define the presence of a malformation, lack of control for certain confounders such as body mass index, use of prescription dispensing as verification for the use of a statin, and lack of information on non-live births. Animal Data Ezetimibe In oral (gavage) embryo-fetal development studies of ezetimibe conducted in rats (gestation days 6-15) and rabbits (gestation days 7-19), there was no evidence of maternal toxicity or embryolethality at any dose tested (250, 500, 1000 mg/kg/day) at exposure equivalent to 10 to 150 times the clinical exposure, based on AUC, in rats and rabbits.
In rats, increased incidences of common fetal skeletal findings (extra pair of thoraci…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of ezetimibe in combination with a statin as an adjunct to diet to reduce LDL-C have been established in pediatric patients 10 years of age and older with HeFH. Use of VYTORIN for this indication is based on a double-blind, placebo-controlled clinical trial in 248 pediatric patients (142 males and 106 postmenarchal females) 10 years of age and older with HeFH [see Clinical Studies (14) ] . In this limited controlled trial, there was no significant effect on growth or sexual maturation in the adolescent males or females, or on menstrual cycle length in females.
The safety and effectiveness of VYTORIN have not been established in pediatric patients younger than 10 years of age with HeFH, or in pediatric patients with other types of hyperlipidemia.
🧓 Geriatric Use ▾
8.5Geriatric Use Advanced age (≥65 years) is a risk factor for VYTORIN-associated myopathy and rhabdomyolysis. Dose selection for an elderly patient should be cautious, recognizing the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy and the higher risk of myopathy. Monitor geriatric patients receiving VYTORIN for the increased risk of myopathy [see Warnings and Precautions (5.1) ] .
Of the 10,189 patients who received VYTORIN in clinical studies, 3242 (32%) were 65 and older (this included 844 (8%) who were 75 and older). No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE No specific antidotes for VYTORIN are known. In the event of an overdose with VYTORIN, consider contacting the Poison Help Line (1-800-222-1222) or a medical toxicologist for overdosage management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action VYTORIN Plasma cholesterol is derived from intestinal absorption and endogenous synthesis. VYTORIN contains ezetimibe and simvastatin, two lipid-lowering compounds with complementary mechanisms of action. Ezetimibe Ezetimibe reduces blood cholesterol by inhibiting the absorption of cholesterol by the small intestine.
The molecular target of ezetimibe has been shown to be the sterol transporter, Niemann-Pick C1-Like 1 (NPC1L1), which is involved in the intestinal uptake of cholesterol and phytosterols. Ezetimibe localizes at the brush border of the small intestine and inhibits the absorption of cholesterol, leading to a decrease in the delivery of intestinal cholesterol to the liver. This causes a reduction of hepatic cholesterol stores and an increase in clearance of cholesterol from the blood.
Simvastatin Simvastatin is a prodrug and is hydrolyzed to its active β-hydroxyacid form, simvastatin acid, after administration. Simvastatin acid and its metabolites are inhibitors of HMG-CoA reductase, the rate-limiting enzyme converts HMG-CoA to mevalonate, a precursor of cholesterol.
12.2Pharmacodynamics VYTORIN reduces total cholesterol (total-C), LDL-C, apolipoprotein (Apo) B, and non-high-density lipoprotein cholesterol (non-HDL-C) in patients with hyperlipidemia. Ezetimibe In a 2-week clinical trial in 18 hypercholesterolemic patients, ezetimibe inhibited intestinal cholesterol absorption by 54%, compared with placebo. Ezetimibe had no clinically meaningful effect on the plasma concentrations of the fat-soluble vitamins A, D, and E and did not impair adrenocortical steroid hormone production.
Simvastatin Inhibition of HMG-CoA reductase by simvastatin acid accelerates the expression of LDL-receptors, followed by the uptake of LDL-C from blood to the liver, leading to a decrease in plasma LDL-C and total cholesterol. Sustained inhibition of cholesterol synthesis in the liver also decreases levels of very-low density lipoproteins. The maximum LDL-C reduction of ZOCOR is usually achieved by 4 weeks and is maintained after that.
12.3Pharmacokinetics The results of a bioequivalence trial in healthy subjects demonstrated that the VYTORIN (ezetimibe and simvastatin) 10 mg/10 mg to 10 mg/80 mg combination tablets are bioequivalent to coadministration of corresponding doses of ezetimibe (ZETIA ® ) and simvastatin (ZOCOR ® ) as individual tablets. Absorption Ezetimibe After oral administration, ezetimibe is absorbed and extensively conjugated to a pharmacologically active phenolic glucuronide (ezetimibe-glucuronide). Mean maximum plasma concentrations (C max ) occur within 1 to 2 hours for ezetimibe-glucuronide and 4 to 12 hours for ezetimibe.
The absolute bioavailability of ezetimibe cannot be determined as the compound is virtually insoluble in aqueous media suitable for injection. Simvastatin The availability of the β-hydroxyacid to the systemic circulation following an oral dose of simvastatin was found to be less than 5% of the dose, consistent with extensive hepatic first-pass extraction. Effect of Food on Oral Absorption Ezetimibe Concomitant food administration (high-fat or non-fat meals) had no effect on the extent of absorption of ezetimibe when administered as 10-mg tablets.
The C max value of ezetimibe was increased by 38% with consumption of high-fat meals. Simvastatin Relative to the fasting state, the plasma profiles of both active and total inhibitors of HMG-CoA reductase were not affected when simvastatin was administered immediately before an American Heart Association recommended low-fat meal. Distribution Ezetimibe Ezetimibe and ezetimibe-glucuronide are highly bound (>90%) to human plasma proteins.
Simvastatin Both simvastatin and its β-hydroxyacid metabolite are highly bound (approximately 95%) to human plasma proteins. When radiolabeled simvastatin was administered to rats, simvastatin-derived radioactivity crossed the blood-brain barrier. Elimination Metabolism Ezet…
🧬 Mechanism of Action ▾
12.1Mechanism of Action VYTORIN Plasma cholesterol is derived from intestinal absorption and endogenous synthesis. VYTORIN contains ezetimibe and simvastatin, two lipid-lowering compounds with complementary mechanisms of action. Ezetimibe Ezetimibe reduces blood cholesterol by inhibiting the absorption of cholesterol by the small intestine.
The molecular target of ezetimibe has been shown to be the sterol transporter, Niemann-Pick C1-Like 1 (NPC1L1), which is involved in the intestinal uptake of cholesterol and phytosterols. Ezetimibe localizes at the brush border of the small intestine and inhibits the absorption of cholesterol, leading to a decrease in the delivery of intestinal cholesterol to the liver. This causes a reduction of hepatic cholesterol stores and an increase in clearance of cholesterol from the blood.
Simvastatin Simvastatin is a prodrug and is hydrolyzed to its active β-hydroxyacid form, simvastatin acid, after administration. Simvastatin acid and its metabolites are inhibitors of HMG-CoA reductase, the rate-limiting enzyme converts HMG-CoA to mevalonate, a precursor of cholesterol.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING VYTORIN tablets are supplied as follows: Strength How Supplied NDC Tablet Description 10/10 mg unit of use bottles of 30 78206-174-01 white to off-white capsule-shaped tablets with code “311” on one side unit of use bottles of 90 78206-174-02 10/20 mg unit of use bottles of 30 78206-175-01 white to off-white capsule-shaped tablets with code “312” on one side unit of use bottles of 90 78206-175-02 10/40 mg unit of use bottles of 30 78206-176-01 white to off-white capsule-shaped tablets with code “313” on one side unit of use bottles of 90 78206-176-02 10/80 mg unit of use bottles of 30 78206-177-01 white to off-white capsule-shaped tablets with code “315” on one side unit of use bottles of 90 78206-177-02 Storage Store at 68°F to 77°F (20°C to 25°C). [See USP Controlled Room Temperature.] Keep container tightly closed.
📦 Storage and Handling ▾
Storage Store at 68°F to 77°F (20°C to 25°C). [See USP Controlled Room Temperature.] Keep container tightly closed.
📋 Description ▾
11 DESCRIPTION VYTORIN contains ezetimibe, a dietary cholesterol absorption inhibitor, and simvastatin, an HMG CoA reductase inhibitor. The chemical name of ezetimibe is 1-(4-fluorophenyl)-3(R)-[3-(4-fluorophenyl)-3(S)-hydroxypropyl]-4(S)-(4-hydroxyphenyl)-2-azetidinone. The empirical formula is C 24 H 21 F 2 NO 3 and its molecular weight is 409.4.
Ezetimibe is a white, crystalline powder that is freely to very soluble in ethanol, methanol, and acetone and practically insoluble in water. Its structural formula is: Simvastatin, an inactive lactone, is hydrolyzed to the corresponding β-hydroxyacid form, which is an inhibitor of HMG-CoA reductase. Simvastatin is butanoic acid, 2,2-dimethyl-,1,2,3,7,8,8a-hexahydro-3,7-dimethyl-8-[2-(tetrahydro-4-hydroxy-6-oxo-2 H -pyran-2-yl)-ethyl]-1-naphthalenyl ester, [1 S -[1α,3α,7β,8β(2 S *,4 S *),-8aβ]].
The empirical formula of simvastatin is C 25 H 38 O 5 and its molecular weight is 418.57. Simvastatin is a white to off-white, nonhygroscopic, crystalline powder that is practically insoluble in water and freely soluble in chloroform, methanol and ethanol. Its structural formula is: VYTORIN is available for oral use as tablets containing 10 mg of ezetimibe, and 10 mg of simvastatin (VYTORIN 10/10), 20 mg of simvastatin (VYTORIN 10/20), 40 mg of simvastatin (VYTORIN 10/40), or 80 mg of simvastatin (VYTORIN 10/80).
Each tablet contains the following inactive ingredients: butylated hydroxyanisole NF, citric acid monohydrate USP, croscarmellose sodium NF, hypromellose USP, lactose monohydrate NF, magnesium stearate NF, microcrystalline cellulose NF, and propyl gallate NF. Chemical Structure Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information ). Myopathy and Rhabdomyolysis Advise patients that VYTORIN may cause myopathy and rhabdomyolysis. Inform patients taking the 80 mg daily dose of simvastatin that they are at an increased risk.
Inform patients that the risk is also increased when taking certain types of medication or consuming grapefruit juice and they should discuss all medication, both prescription and over the counter, with their healthcare provider. Instruct patients to inform other healthcare providers prescribing a new medication or increasing the dose of an existing medication that they are taking VYTORIN. Instruct patients to promptly report any unexplained muscle pain, tenderness or weakness particularly if accompanied by malaise or fever [see Contraindications (4) , Warnings and Precautions (5.1) , and Drug Interactions (7.1) ] .
Hepatic Dysfunction Inform patients that VYTORIN may cause liver enzyme elevations and possibly liver failure. Advise patients to promptly report fatigue, anorexia, right upper abdominal discomfort, dark urine or jaundice [see Warnings and Precautions (5.3) ] . Increases in HbA1c and Fasting Serum Glucose Levels Inform patients that increases in HbA1c and fasting serum glucose levels may occur with VYTORIN.
Encourage patients to optimize lifestyle measures, including regular exercise, maintaining a healthy body weight, and making healthy food choices [see Warnings and Precautions (5.4) ] . Pregnancy Advise pregnant patients and patients who can become pregnant of the potential risk to a fetus. Advise patients to inform their healthcare provider of a known or suspected pregnancy to discuss if VYTORIN should be discontinued [see Use in Specific Populations (8.1) ] .
Lactation Advise patients that breastfeeding is not recommended during treatment with VYTORIN [see Use in Specific Populations (8.2) ] . Missed Dose Instruct patients to take VYTORIN only as prescribed. If a dose is missed, it should be taken as soon as possible.
Advise patients not to double their next dose.