
Chewable C- 500 Ingredients & Drug Interactions
by Nutri-West
What is this page for?
First and foremost: checking Chewable C- 500 against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Chewable C- 500 is a dietary supplement by Nutri-West with 5 active ingredients. Its ingredients are commonly taken for common cold and immune support, antioxidant support, skin health and collagen formation.Based on those ingredients, 1,503 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Beta-Carotene, Vitamin C, Sodium Ascorbate. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Chewable C- 500 by Nutri-West
Ask about any prescription or over-the-counter medication and we check it for interactions with Chewable C- 500 by Nutri-West — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Chewable C- 500 by Nutri-West
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Low disclosure
Chewable C-500 contains 7 active ingredients. The main component is vitamin C (in two forms: pure vitamin C and ascorbic acid), which supports immune function and acts as an antioxidant.
Acerola provides additional vitamin C from a natural fruit source. Rutin and hesperidin are bioflavonoids—plant compounds that often work alongside vitamin C.
Citrus bioflavonoids are a blend of related compounds. Beta-carotene is a precursor to vitamin A.
Sodium ascorbate is a buffered (stomach-friendly) form of vitamin C that also contributes sodium. The tablet also contains inactive ingredients—natural orange juice flavor, fructose, stearate, talc, stearic acid, and magnesium stearate—which are excipients that help form and flavor the chewable.
Does it work?
Not established
Vitamin C in this product is effective for treating vitamin C deficiency, and possibly effective for anemia of chronic disease, atrial fibrillation, cataracts, and reducing exercise-induced respiratory infections. Acerola is possibly effective for vitamin C deficiency.
For the other active ingredients—rutin, hesperidin, and citrus bioflavonoids—the evidence we hold does not establish effectiveness for common uses. Rutin and hesperidin show insufficient reliable evidence for conditions like diabetes, inflammatory bowel disease, aging skin, hemorrhoids, and nonalcoholic fatty liver disease.
Hesperidin is rated possibly ineffective for obesity and cholesterol.
How safe is it?
Well-documented data
Vitamin C is generally well tolerated at normal dietary and supplement doses. The most common side effects—abdominal cramps, heartburn, diarrhea, nausea, and headache—are more likely above 2 grams daily.
People prone to kidney stones should be cautious. Rare serious effects include kidney damage (hyperoxalosis and oxalate nephropathy), particularly with high-dose intravenous vitamin C.
Rutin may cause headache, flushing, or rash in some people and is generally well tolerated at food and short-term supplement doses, though long-term safety data are limited. Hesperidin is generally well tolerated at food amounts and short-term supplement use but has limited long-term data; a case of allergic dermatitis was reported with topical application.
Acerola is generally considered safe at food amounts and as directed on labels; however, a rare case of allergic reaction and one report of rectal obstruction have been documented. Sodium ascorbate is well tolerated at moderate intake but high sodium is linked to worsening blood pressure and kidney disease.
For pregnancy and lactation: vitamin C is likely safe at normal amounts but possibly unsafe at high doses—prenatal vitamin doses are fine, avoid high-dose supplements unless advised by your doctor. Rutin is likely safe in pregnancy.
Hesperidin is likely safe in pregnancy but should be avoided as a supplement during breastfeeding due to insufficient safety data. Acerola safety data during breastfeeding is not on file.
Sodium ascorbate is likely safe at normal dietary amounts in pregnancy but possibly unsafe at high doses.
Meds to double-check
Moderate interaction found
Before taking Chewable C-500, double-check with your pharmacist if you take estrogens (birth control pills, hormone replacement therapy), blood thinners like warfarin, chemotherapy drugs (especially alkylating agents and antitumor antibiotics), levothyroxine (thyroid medication), blood pressure medications, heart drugs like verapamil or diltiazem, diabetes medications, sedating drugs, lithium, HIV protease inhibitors like indinavir, antipsychotics like fluphenazine, or any sodium-containing medications. No interactions are documented for the ingredient we could not check.
The bottom line
Scorecard at a glanceFormula with limited ingredient disclosure with no established evidence rating for its marketed use. Moderate medication interactions have been identified, and safety information is well characterized.
This supplement is a solid option if you need vitamin C—it's effective for deficiency and possibly helpful for a few other conditions. If you take hormonal birth control, blood thinners, heart medications, diabetes drugs, blood pressure medication, or chemotherapy, talk to your pharmacist first.
People prone to kidney stones or who have high blood pressure should also check before starting.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 6 of 7 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Nov 25, 2013.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Chewable C- 500, straight from the product label.
| Brand | Nutri-West |
|---|---|
| Net contents | 90 Tablet(s) |
| Market status | On market |
| Date entered into DSLD | Nov 25, 2013 |
| DSLD ID | 27589 |
| Product type | Other Combinations |
| Supplement form | Tablet Or Pill |
| Dietary claims / uses | All Other |
| Intended target group(s) | Adult (18 - 50 Years), Dairy Free, Sugar Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for Chewable C- 500 by Nutri-West, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Vitamin C | 500 mg | 832% |
| Beta-Carotene | 1000 Unit(s) | -- |
| Ascorbic Acid | 0 NP | -- |
| Rutin | 0 NP | -- |
| Citrus Bioflavonoids | 0 NP | -- |
| Hesperidin | 0 NP | -- |
| Acerola | 0 NP | -- |
| Sodium Ascorbate | 0 NP | -- |
| Each naturally flavored chewable tablet contains | 0 NP | -- |
Other ingredients: Natural Orange Juice Flavor, Fructose, Stearate, Talc, Stearic Acid, Magnesium Stearate
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
General Statements
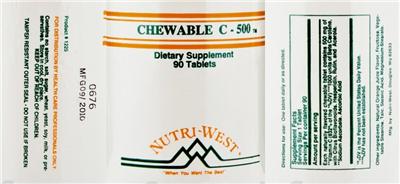
0676 MFG09/2010
FOR DISTRIBUTION BY HEALTH CARE PROFESSIONALS ONLY.
Manufactured under strict GMP and USP guidelines.
"When You Want The Best"
Precautions
KEEP OUT OF REACH OF CHILDREN.
TAMPER RESISTANT OUTER SEAL - DO NOT USE IF BROKEN.
FDA Statement of Identity
Dietary Supplement
Formulation
Contains no starch, salt, sugar, wheat, yeast, soy, milk, or preservatives.
Storage
Store in a cool, dry place.
Suggested/Recommended/Usage/Directions
Directions for use: One tablet daily or as directed.
General
Product # 1225
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Chewable C- 500 by Nutri-West label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Chewable C- 500 by Nutri-West
These are the 5 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Tablet(s) Dosage formTablet Or Pill Servings per container90 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Vitamin C
Interacts with207 drugs
Vitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for im...
Vitamin C monograph & interactionsBeta-Carotene
Interacts with387 drugs
Vitamin A is an essential nutrient important for vision, skin, immune function, and growth. Most people get enough from a balanced diet, and supplemen...
Beta-Carotene monograph & interactionsAscorbic Acid
Interacts with207 drugs
Vitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for im...
Ascorbic Acid monograph & interactionsSodium Ascorbate
Interacts with205 drugs
Sodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets g...
Sodium Ascorbate monograph & interactionsEach naturally flavored chewable tablet contains
Other (inactive) ingredients: Natural Orange Juice Flavor, Fructose, Stearate, Talc, Stearic Acid, Magnesium Stearate. These complete the product’s ingredient list but are not active constituents.
Chewable C- 500 by Nutri-West Drug Interactions
HelloPharmacist Interaction Report
Chewable C-500 by Nutri-West contains several ingredients with documented interactions with medications.
The most serious concern involves vitamin C and estrogens (birth control pills and hormone replacement therapy): vitamin C can increase blood estrogen levels by up to 55%, which may intensify estrogenic effects. Altogether, these interactions span 890 individual medications.
Read the full breakdown — every affected drug type, severity by severity
Vitamin C also interacts with blood thinners like warfarin—high doses can reduce warfarin's effectiveness by decreasing absorption. It may similarly reduce the activity of certain chemotherapy drugs (alkylating agents and antitumor antibiotics) through its antioxidant effects, though this remains theoretical.
Additionally, vitamin C can increase absorption of aluminum from aluminum-containing compounds, increase levothyroxine absorption, modestly reduce indinavir levels, decrease fluphenazine levels, and reduce the effectiveness of some antiretroviral drugs.
Hesperidin, another ingredient, may increase sedation when combined with sedating drugs (like benzodiazepines), raise the risk of low blood pressure with blood pressure medications, potentially increase bleeding risk with blood thinners, and theoretically boost levels of certain heart medications (verapamil and diltiazem). Rutin may raise the risk of low blood sugar (hypoglycemia) with diabetes medications.
Acerola contains vitamin C and carries similar but minor concerns with estrogens, blood thinners, and chemotherapy. Sodium ascorbate contributes sodium, which can interfere with blood pressure control, interact with lithium, and heighten sodium-related risks with certain medications.
We could not check the ingredient listed as "Each naturally flavored chewable tablet contains." Check your exact medications with the search tool on this page before starting.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Chewable C- 500?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Chewable C- 500 interact with 1,503 drugs. Click any drug to see the details.
3 of the 5 ingredients in Chewable C- 500 interact with drugs. Each result below shows which ingredient is responsible. Beta-Carotene Vitamin C Sodium Ascorbate
Sodium Picosulfate, Citric Acid, Magnesium Oxide (otc Drug)Pico-Salax
How Sodium Picosulfate, Citric Acid, Magnesium Oxide (otc Drug) interacts with Chewable C- 500 — through 1 ingredient. Tap an ingredient for the detail:
Ascorbic AcidCholine Magnesium Trisalicylate (trilisate) Minor
Interaction Summary
Acidification of the urine by vitamin C might increase choline magnesium trisalicylate levels.
Read the full Ascorbic Acid + Sodium Picosulfate, Citric Acid, Magnesium Oxide (otc Drug) interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Chewable C- 500 with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Beta-Carotene
Retinoids
Concomitant use of retinoids with vitamin A supplements might produce supratherapeutic vitamin A levels.
Retinoids, which are vitamin A derivatives, could have additive toxic effects when taken with vitamin A supplements.
Hepatotoxic Drugs
Theoretically, taking high doses of vitamin A in combination with other potentially hepatotoxic drugs might increase the risk of liver disease.
The tolerable upper intake level (UL) is the highest level of intake that is likely to pose no risk of adverse effects. Doses of vitamin A above the UL can cause hepatotoxicity, ranging from elevated liver enzymes to liver failure.
Tetracycline Antibiotics
Theoretically, taking tetracycline antibiotics with high doses of vitamin A can increase the risk of pseudotumor cerebri.
Benign intracranial hypertension (pseudotumor cerebri) can occur with tetracyclines and with acute or chronic vitamin A toxicity. Case reports suggest that taking tetracyclines and vitamin A concurrently can increase the risk of this condition. Avoid high doses of vitamin A in people taking tetracyclines chronically.
Warfarin (Coumadin)
Theoretically, high doses of vitamin A could increase the risk of bleeding with warfarin.
Vitamin A toxicity is associated with hemorrhage and hypoprothrombinemia, possibly due to vitamin K antagonism. Advise patients taking warfarin to avoid doses of vitamin A above the tolerable upper intake level of 10,000 IU/day for adults.
Vitamin C
Alkylating Agents
Theoretically, antioxidant effects of vitamin C might reduce the effectiveness of alkylating agents.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin C have on chemotherapy.
Aluminum
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Research in animals and humans shows that vitamin C increases aluminum absorption, theoretically by chelating aluminum and keeping it in solution where it is available for absorption. In people with normal renal function, urinary excretion of aluminum will likely increase, making aluminum retention and toxicity unlikely. Patients with renal failure who take aluminum-containing compounds such as phosphate binders should avoid vitamin C supplements in doses above the recommended dietary allowances.
Antitumor Antibiotics
Theoretically, the antioxidant effects of vitamin C might reduce the effectiveness of antitumor antibiotics.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as doxorubicin. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effects, if any, antioxidants such as vitamin C have on chemotherapy.
Estrogens
Vitamin C might increase blood levels of estrogens.
Increases in plasma estrogen levels of up to 55% occur under some circumstances when vitamin C is taken concurrently with oral contraceptives or hormone replacement therapy, including topical products. It is suggested that vitamin C prevents oxidation of estrogen in the tissues, regenerates oxidized estrogen, and reduces sulfate conjugation of estrogen in the gut wall. When tissue levels of vitamin C are high, these processes are already maximized and supplemental vitamin C does not have any effect on estrogen levels. Increases in plasma estrogen levels may occur when patients who are deficient in vitamin C take supplements. Monitor these patients for estrogen-related side effects.
Fluphenazine (Prolixin)
Theoretically, vitamin C might decrease levels of fluphenazine.
In one patient there was a clinically significant decrease in fluphenazine levels when vitamin C (500 mg twice daily) was started. The mechanism is not known, and there is no further data to confirm this interaction.
Indinavir (Crixivan)
Vitamin C can modestly reduce indinavir levels.
One pharmacokinetic study shows that taking vitamin C 1 gram orally once daily along with indinavir 800 mg orally three times daily reduces the area under the concentration-time curve of indinavir by 14%. The mechanism of this interaction is unknown, but it is unlikely to be clinically significant in most patients. The effect of higher doses of vitamin C on indinavir levels is unknown.
Levothyroxine (Synthroid, Others)
Vitamin C can increase levothyroxine absorption.
Two clinical studies in adults with poorly controlled hypothyroidism show that swallowing levothyroxine with a glass of water containing vitamin C 500-1000 mg in solution reduces thyroid stimulating hormone (TSH) levels and increases thyroxine (T4) levels when compared with taking levothyroxine alone. This suggests that vitamin C increases the oral absorption of levothyroxine, possibly due to a reduction in pH.
Warfarin (Coumadin)
High-dose vitamin C might reduce the levels and effectiveness of warfarin.
Vitamin C in high doses may cause diarrhea and possibly reduce warfarin absorption. There are reports of two people who took up to 16 grams daily of vitamin C and had a reduction in prothrombin time. Lower doses of 5-10 grams daily can also reduce warfarin absorption. In many cases, this does not seem to be clinically significant. However, a case of warfarin resistance has been reported for a patient who took vitamin C 500 mg twice daily. Cessation of vitamin C supplementation resulted in a rapid increase in international normalized ratio (INR). Tell patients taking warfarin to avoid taking vitamin C in excessively high doses (greater than 10 grams daily). Lower doses may be safe, but the anticoagulation activity of warfarin should be monitored. Patients who are stabilized on warfarin while taking vitamin C should avoid adjusting vitamin C dosage to prevent the possibility of warfarin resistance.
Acetaminophen (Tylenol, Others)
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
A small pharmacokinetic study in healthy volunteers shows that taking high-dose vitamin C (3 grams) 1.5 hours after taking acetaminophen 1 gram slightly increases the apparent half-life of acetaminophen from around 2.3 hours to 3.1 hours. Ascorbic acid competitively inhibits sulfate conjugation of acetaminophen. However, to compensate, elimination of acetaminophen glucuronide and unconjugated acetaminophen increases. This effect is not likely to be clinically significant.
Aspirin
Acidification of the urine by vitamin C might increase aspirin levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction is not clinically significant.
Choline Magnesium Trisalicylate (Trilisate)
Acidification of the urine by vitamin C might increase choline magnesium trisalicylate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Niacin
Vitamin C might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as vitamin C, or to the combination. It also is not known whether it will occur in other patient populations.
Salsalate (Disalcid)
Acidification of the urine by vitamin C might increase salsalate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams/day vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Sodium Ascorbate
Antihypertensive Drugs
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
High intake of dietary sodium can increase systolic and diastolic blood pressure. Also, high intake of sodium may necessitate increased use of antihypertensive medications to achieve blood pressure control in some patients, such as those with chronic kidney disease.
Corticosteroids
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Mineralocorticoids and some glucocorticoids (corticosteroids) cause sodium retention. This effect is dose-related and depends on mineralocorticoid potency. It is most common with hydrocortisone, cortisone, and fludrocortisone, followed by prednisone and prednisolone.
Didanosine (Videx)
Concomitant use of didanosine with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia.
Didanosine formulations contain a significant amount of sodium.
Lithium
Altering dietary intake of sodium might alter the levels and clinical effects of lithium.
High sodium intake can reduce plasma concentrations of lithium by increasing lithium excretion. Reducing sodium intake can significantly increase plasma concentrations of lithium and cause lithium toxicity in patients being treated with lithium carbonate. Stabilizing sodium intake is shown to reduce the percentage of patients with lithium level fluctuations above 0.8 mEq/L. Patients taking lithium should avoid significant alterations in their dietary intake of sodium.
Sodium Phosphates
Theoretically, concomitant use of sodium phosphate with sodium supplements might increase the risk of hypernatremia.
Use of high doses (> 45 mL in 24 hours) of sodium phosphate, such as those used for bowel cleansing before surgery, can lead to serious electrolyte disturbances, including hypernatremia. The risk of hypernatremia is highest in the elderly and people with other risk factors for electrolyte disturbances.
Sodium-Containing Drugs
Concomitant use of sodium-containing drugs with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia and long-term sodium-related complications.
The Chronic Disease Risk Reduction (CDRR) intake level of 2.3 grams of sodium daily indicates the intake at which it is believed that chronic disease risk increases for the apparently healthy population. Some medications contain high quantities of sodium. When used in conjunction with sodium supplements or high-sodium diets, the CDRR may be exceeded. Additionally, concomitant use may increase the risk for hypernatremia; this risk is highest in the elderly and people with other risk factors for electrolyte disturbances.
Tolvaptan (Samsca)
Theoretically, concomitant use of tolvaptan with sodium might increase the risk of hypernatremia.
Tolvaptan is a vasopressin receptor 2 antagonist that is used to increase sodium levels in patients with hyponatremia. Patients taking tolvaptan should use caution with the use of sodium salts such as sodium chloride.
Brand information
Manufacturer and brand details for Chewable C- 500, from the product label.
Chewable C- 500 by Nutri-West: Common Questions
Does Chewable C- 500 by Nutri-West interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Is this safe to take if I'm pregnant?
Can I take this while breastfeeding?
What are the most common side effects?
Will this actually help my immune system?
Is there anything else in here besides vitamin C?
Can I take this if I have kidney stones?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Chewable C- 500 is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Chewable C- 500’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Vitamin C
Interacts with 207 drugsVitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for immune function, collagen, and acts as an...
Read the full Vitamin C monograph → Herb & supplement monographVitamin A
Interacts with 387 drugsVitamin A is an essential nutrient important for vision, skin, immune function, and growth. Most people get enough from a balanced diet, and supplements are mainly useful for correcting a tr...
Read the full Vitamin A monograph → Herb & supplement monographQuercetin
Interacts with 1,169 drugsQuercetin is a plant flavonoid with antioxidant and anti-inflammatory properties found in many common foods and sold as a supplement. While early research is interesting for allergies, blood...
Read the full Quercetin monograph → Herb & supplement monographSodium
Interacts with 205 drugsSodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets get more than enough—often too much—from...
Read the full Sodium monograph →Sources & How We Checked
Chewable C- 500's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 182 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Vitamin C 51 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Back DJ, Breckenridge AM, MacIver M, et al. Interaction of ethinyloestradiol with ascorbic acid in man. Br Med J (Clin Res Ed) 1981;282:1516.
- Morris JC, Beeley L, Ballantine N. Interaction of ethinyloestradiol with ascorbic acid in man [letter]. Br Med J (Clin Res Ed) 1981;283:503.
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Dwyer JH, Merz NB, Shirocre AM, et al. Progression of early atherosclerosis and intake of vitamin C and vitamin E from supplements and food. The Los Angeles Atherosclerosis Study. 41st Annual Conference on Cardiovascular Disease Epidemiology and Prevent
- Levine M, Rumsey SC, Daruwala R, et al. Criteria and recommendations for vitamin C intake. JAMA 1999;281:1415-23. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Houston JB, Levy G. Drug biotransformation interactions in man VI: Acetaminophen and ascorbic acid. J Pharm Sci 1976;65:1218-21. PubMed
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Rosenthal G. Interaction of ascorbic acid and warfarin. JAMA 1971;215:1671. DOI
- Hume R, Johnstone JM, Weyers E. Interaction of ascorbic acid and warfarin. JAMA 1972;219:1479. DOI
- Smith EC, Skalski RJ, Johnson GC, Rossi GV. Interaction of ascorbic acid and warfarin. JAMA 1972;221:1166. DOI
- Traxer O, Huet B, Poindexter J, et al. Effect of ascorbic acid consumption on urinary stone risk factors. J Urol 2003;170:397-401.. PubMed
- Domingo JL, Gomez M, Llobet JM, Richart C. Effect of ascorbic acid on gastrointestinal aluminum absorption (letter). Lancet 1991;338:1467.
- Domingo JL, Gomez M, Llobet JM, Corbella J. Influence of some dietary constituents on aluminum absorption and retention in rats. Kidney Int 1991;39:598-601. PubMed
- Partridge NA, Regnier FE, White JL, Hem SL. Influence of dietary constituents on intestinal absorption of aluminum. Kidney Int 1989;35:1413-7. PubMed
- Mc Leod DC, Nahata MC. Inefficacy of ascorbic acid as a urinary acidifier (letter). N Engl J Med 1977;296:1413. DOI
- Hansten PD, Hayton WL. Effect of antacid and ascorbic acid on serum salicylate concentration. J Clin Pharmacol 1980;20:326-31. PubMed
- Dysken MW, Cumming RJ, Channon RA, Davis JM. Drug interaction between ascorbic acid and fluphenazine. JAMA 1979;241:2008. DOI
- Vihtamaki T, Parantainen J, Koivisto AM, et al. Oral ascorbic acid increases plasma oestradiol during postmenopausal hormone replacement therapy. Maturitas 2002;42:129-35. PubMed
- Slain D, Amsden JR, Khakoo RA, et al. Effect of high-dose vitamin C on the steady-state pharmacokinetics of the protease inhibitor indinavir in healthy volunteers. Pharmacotherapy 2005;25:165-70. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Feetam CL, Leach RH, Meynell MJ. Lack of a clinically important interaction between warfarin and ascorbic acid. Toxicol Appl Pharmacol 1975;31:544-7. PubMed
- Weintraub M, Griner PF. Warfarin and ascorbic acid: lack of evidence for a drug interaction. Toxicol Appl Pharmacol 1974;28:53-6. PubMed
- Lee DH, Folsom AR, Harnack L, et al. Does supplemental vitamin C increase cardiovascular disease risk in women with diabetes? Am J Clin Nutr 2004;80:1194-200. PubMed
- Taylor EN, Stampfer MJ, Curhan GC. Dietary factors and the risk of incident kidney stones in men: new insights after 14 years of follow-up. J Am Soc Nephrol 2004;15:3225-32. PubMed
- Ward NC, Hodgson JM, Croft KD, et al. The combination of vitamin C and grape-seed polyphenols increases blood pressure: a randomized, double-blind, placebo-controlled trial. J Hypertens 2005;23:427-34.. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Fairweather-Tait S, Hickson K, McGaw B, et al. Orange juice enhances aluminium absorption from antacid preparation. Eur J Clin Nutr. 1994;48(1):71-3.
- Gruenwald, J., Graubaum, H. J., Busch, R., and Bentley, C. Safety and tolerance of ester-C compared with regular ascorbic acid. Adv.Ther. 2006;23(1):171-178.
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Einerson, B., Nathorn, C., Kitiyakara, C., Sirada, M., and Thamlikitkul, V. The efficacy of ascorbic acid in suboptimal responsive anemic hemodialysis patients receiving erythropoietin: a meta-analysis. J Med.Assoc.Thai. 2011;94 Suppl 1:S134-S146.
- Li, G., Li, L., Yu, C., and Chen, L. Effect of vitamins C and E supplementation on Helicobacter pylori eradication: a meta-analysis. Br.J Nutr 2011;106(11):1632-1637.
- Chen X, Shen L, Gu X, et al. High-dose supplementation with vitamin C--induced pediatric urolithiasis: the first case report in a child and literature review. Urology. 2014;84(4):922-4. PubMed
- Sattar A, Willman JE, Kolluri R. Possible warfarin resistance due to interaction with ascorbic acid: case report and literature review. Am J Health Syst Pharm. 2013;70(9):782-6. PubMed
- Yaich S, Chaabouni Y, Charfeddine K, et al. Secondary oxalosis due to excess vitamin C intake: a cause of graft loss in a renal transplant recipient. Saudi J Kidney Dis Transpl. 2014;25(1):113-6. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Rumbold A, Ota E, Nagata C, Shahrook S, Crowther CA. Vitamin C supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004072. PubMed
- Seo MS, Kim JK, Shim JY. High-dose vitamin C promotes regression of multiple pulmonary metastases originating from hepatocellular carcinoma. Yonsei Med J. 2015;56(5):1449-52. PubMed
- Skelin M, Lucijanic T, Amidzic Klaric D, et al. Factors Affecting Gastrointestinal Absorption of Levothyroxine: A Review. Clin Ther. 2017 Feb;39(2):378-403. PubMed
- Jiang K, Tang K, Liu H, Xu H, Ye Z, Chen Z. Ascorbic acid supplements and kidney stones incidence among men and women: a systematic review and meta-analysis. Urol J. 2019;16(2):115-120.
- Thomas S, Patel D, Bittel B, et al. Effect of High-Dose Zinc and Ascorbic Acid Supplementation vs Usual Care on Symptom Length and Reduction Among Ambulatory Patients With SARS-CoV-2 Infection: The COVID A to Z Randomized Clinical Trial. JAMA Netw Open. 2 PubMed
- Giffen MA, McLemore JL. Hyperoxalosis Secondary to Intravenous Vitamin C Administration as a Non-Allopathic Treatment for Cancer. Acad Forensic Pathol 2019;9(1-2):118-126. PubMed
- Maike A, Sturgill D, Gallan A. Oxalate Nephropathy in a Renal Transplant Recipient After Receiving High Dose Ascorbic Acid. Am J Med Sci 2021. PubMed
- Shen ZY, Chen YR, Wang MC, Chang SS. High-dose vitamin C-induced acute oxalate nephropathy in a renal transplant recipient: a case report and literature review. Asian J Surg 2022. PubMed
- Yanase F, Spano S, Maeda A, et al. Mega-dose sodium ascorbate: a pilot, single-dose, physiological effect, double-blind, randomized, controlled trial. Crit Care 2023;27(1):371. PubMed
- Sharma Y, Sumanadasa S, Shahi R, et al. Efficacy and safety of vitamin C supplementation in the treatment of community-acquired pneumonia: a systematic review and meta-analysis with trial sequential analysis. Sci Rep 2024;14(1):11846. PubMed
- Pejcic AV, Petrovic NZ, Djordjic MD, Milosavljevic MN. Vitamin C Levels in Pregnant Women and the Efficacy of Vitamin C Supplements in Preventing Premature Rupture of Membranes: A Systematic Review and Meta-Analysis. Balkan Med J 2024;41(4):248-260. PubMed
Vitamin A 31 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Griffiths JK. The vitamin A paradox. J Pediatr 2000;137:604-7.. PubMed
- Hardman JG, Limbird LL, Molinoff PB, eds. Goodman and Gillman's The Pharmacological Basis of Therapeutics, 9th ed. New York, NY: McGraw-Hill, 1996.
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- FDA Talk Paper. Vitamin A and birth defects (T95-56). Food and Drug Administration, U.S. Department of Health and Human Services, Rockville, MD. October 6, 1995.
- Russell RM. The vitamin A spectrum: from deficiency to toxicity. Am J Clin Nutr 2000;71:878-84. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Feskanich D, Singh V, Willett WC, Colditz GA. Vitamin A intake and hip fractures among postmenopausal women. JAMA 2002;287:47-54. PubMed
- Melhus H, Michaelsson K, Kindmark A, et al. Excessive dietary intake of vitamin A is associated with reduced bone mineral density and increased risk for hip fracture. Ann Intern Med 1998;129:770-8. PubMed
- Michaelsson K, Lithell H, Vessby B, Melhus H. Serum retinol levels and the risk of fracture. N Engl J Med 2003;348:287-94.. PubMed
- Botterweck AA, van den Brandt PA, Goldbohm RA. Vitamins, carotenoids, dietary fiber, and the risk of gastric carcinoma: results from a prospective study after 6.3 years of follow-up. Cancer 2000;88:737-48.. DOI
- Meyskens FL Jr, Graham V, Chvapil M, et al. A phase I trial of beta-all-trans-retinoic acid delivered via a collagen sponge and a cervical cap for mild or moderate intraepithelial cervical neoplasia. J Natl Cancer Inst 1983;71:921-5..
- Hathcock JN, Hattan DG, Jenkins MY, et al. Evaluation of vitamin A toxicity. Am J Clin Nutr 1990;52:183-202.. PubMed
- Walters BN, Gubbay SS. Tetracycline and benign intracranial hypertension: report of five cases. Br Med J 1981;282:19-20.. PubMed
- Pearson MG, Littlewood SM, Bowden AN. Tetracycline and benign intracranial hypertension (letter). Br Med J 1981;282:568-9.. PubMed
- Azais-Braesco V, Pascal G. Vitamin A in pregnancy: requirements and safety limits. Am J Clin Nutr 2000;71:1325S-33S. PubMed
- Smedts HP, de Vries JH, Rakhshandehroo M, et al. High maternal vitamin E intake by diet or supplements is associated with congenital heart defects in the offspring. BJOG 2009;116:416-23. PubMed
- Grotto, I., Mimouni, M., Gdalevich, M., and Mimouni, D. Vitamin A supplementation and childhood morbidity from diarrhea and respiratory infections: a meta-analysis. J Pediatr 2003;142(3):297-304. PubMed
- Mahalanabis, D., Lahiri, M., Paul, D., Gupta, S., Gupta, A., Wahed, M. A., and Khaled, M. A. Randomized, double-blind, placebo-controlled clinical trial of the efficacy of treatment with zinc or vitamin A in infants and young children with severe acute l
- Long, K. Z., Montoya, Y., Hertzmark, E., Santos, J. I., and Rosado, J. L. A double-blind, randomized, clinical trial of the effect of vitamin A and zinc supplementation on diarrheal disease and respiratory tract infections in children in Mexico City, Mex
- Fritz, H., Kennedy, D., Fergusson, D., Fernandes, R., Doucette, S., Cooley, K., Seely, A., Sagar, S., Wong, R., and Seely, D. Vitamin A and retinoid derivatives for lung cancer: a systematic review and meta analysis. PLoS.One. 2011;6(6):e21107. PubMed
- Mayo-Wilson, E., Imdad, A., Herzer, K., Yakoob, M. Y., and Bhutta, Z. A. Vitamin A supplements for preventing mortality, illness, and blindness in children aged under 5: systematic review and meta-analysis. BMJ 2011;343:d5094. PubMed
- Mazumder S, Taneja S, Bhatia K, Yoshida S, Kaur J, Dube B, Toteja GS, Bahl R, Fontaine O, Martines J, Bhandari N; Neovita India Study Group. Efficacy of early neonatal supplementation with vitamin A to reduce mortality in infancy in Haryana, India (Neovit
- Baineni R, Gulati R, Delhi CK. Vitamin A toxicity presenting as bone pain. Arch Dis Child. 2017;102(6):556-8. PubMed
- Darlow BA, Graham PJ, Rojas-Reyes MX. Vitamin A supplementation to prevent mortality and short- and long-term morbidity in very low birth weight infants. Cochrane Database Syst Rev. 2016;(8):CD000501. PubMed
- Haider BA, Sharma R, Bhutta ZA. Neonatal vitamin A supplementation for the prevention of mortality and morbidity in term neonates in low and middle income countries. Cochrane Database Syst Rev. 2017;2:CD006980. PubMed
- Mohammad YM, Raslan IR, Al-Hussain FA. Idiopathic Intracranial Hypertension Induced by Topical Application of Vitamin A. J Neuroophthalmol. 2016;36(4):412-3. PubMed
- Masnadi Shirazi K, Nikniaz Z, Masnadi Shirazi A, Rohani M. Vitamin A supplementation decreases disease activity index in patients with ulcerative colitis: A randomized controlled clinical trial. Complement Ther Med. 2018 Dec;41:215-219. PubMed
- Ding Y, Hu P, Yang Y, et al. Impact of maternal daily oral low-dose vitamin A supplementation on the mother-infant pair: a randomised placebo-controlled trial in China. Nutrients 2021;13(7):2370. PubMed
- Knapik JJ, Hoedebecke SS. Vitamin A and bone fractures: systematic review and meta-analysis. J Spec Oper Med 2021;21(2):100-7. PubMed
- Imdad A, Mayo-Wilson E, Haykal MR, et al. Vitamin A supplementation for preventing morbidity and mortality in children from six months to five years of age. Cochrane Database Syst Rev 2022;3(3):CD008524. PubMed
Rutin 2 references
- Mehta DK (Ex Ed). British National Formulary, Number 37. British Medical Association and Royal Pharmaceutical Society of Great Britain: London, England, March 1999.
- Sun C, Wang L, Sun J, Wang Z, Tang Z. Hypoglycemic and hypolipidemic effects of rutin on hyperglycemic rats. J Tradit Chin Med. 2020;40(4):640-645.
Quercetin 26 references
- Shoskes DA, Zeitlin SI, Shahed A, Rajfer J. Quercetin in men with category III chronic prostatitis: A preliminary prospective, double-blind, placebo-controlled trial. Urol 1999;54:960-3. PubMed
- Starvic B. Quercetin in our diet: from potent mutagen to probable anticarcinogen. Clin Biochem 1994;27:245-8. PubMed
- Ferry DR, Smith A, Malkhandi J, et al. Phase I clinical trial of the flavonoid quercetin: Pharmacokinetics and evidence for in vivo tyrosine kinase inhibition. Clin Cancer Res 1996;2:659-67..
- Obach RS. Inhibition of human cytochrome P450 enzymes by constituents of St. John's wort, an herbal preparation used in the treatment of depression. J Pharmacol Exp Ther 2000;294:88-95. DOI
- Edwards RL, Lyon T, Litwin SE, et al. Quercetin reduces blood pressure in hypertensive subjects. J Nutr 2007;137:2405-11.
- Kim KA, Park PW, Kim HK, et al. Effect of quercetin on the pharmacokinetics of rosiglitazone, a CYP2C8 substrate, in healthy subjects. J Clin Pharmacol 2005;45:941-6. PubMed
- DiCenzo R, Frerichs V, Larppanichpoonphol P, et al. Effect of quercetin on the plasma and intracellular concentrations of saquinavir in healthy adults. Pharmacotherapy 2006;26:1255-61. PubMed
- Choi JS, Choi BC, Choi KE. Effect of quercetin on the pharmacokinetics of oral cyclosporine. Am J Health Syst Pharm 2004;61:2406-9. PubMed
- Choi JS, Jo BW, Kim YC. Enhanced paclitaxel bioavailability after oral administration of paclitaxel or prodrug to rats pretreated with quercetin. Eur J Pharm Biopharm 2004;57:313-8. PubMed
- Vaclavikova R, Horsky S, Simek P, Gut I. Paclitaxel metabolism in rat and human liver microsomes is inhibited by phenolic antioxidants. Naunyn Schmiedebergs Arch Pharmacol 2003;368:200-9. PubMed
- Di Bari L, Ripoli S, Pradhan S, Salvadori P. Interactions between quercetin and warfarin for albumin binding: A new eye on food/drug interference. Chirality 2010;22:593-6. PubMed
- Lamson, D. W. and Brignall, M. S. Antioxidants and cancer, part 3: quercetin. Altern.Med.Rev. 2000;5(3):196-208.
- Duan KM, Wang SY, Ouyang W, Mao YM, Yang LJ. Effect of quercetin on CYP3A activity in Chinese healthy participants. J Clin Pharmacol 2012;52(6):940-6. PubMed
- Wang SY, Duan KM, Li Y, et al. Effect of quercetin on P-glycoprotein transport ability in Chinese healthy subjects. Eur J Clin Nutr 2013;67(4):390-4. PubMed
- Nguyen MA, Staubach P, Wolffram S, Langguth P. Effect of single-dose and short-term administration of quercetin on the pharmacokinetics of talinolol in humans - Implications for the evaluation of transporter-mediated flavonoid-drug interactions. Eur J Pha PubMed
- Wu LX, Guo CX, Chen WQ, et al. Inhibition of the organic anion-transporting polypeptide 1B1 by quercetin: an in vitro and in vivo assessment. Br J Clin Pharmacol 2012;73(5):750-7.
- Ahrens MJ, Thompson DL. Effect of emulin on blood glucose in type 2 diabetics. J Med Food. 2013;16(3):211-5. PubMed
- Larson A, Witman MA, Guo Y, et al. Acute, quercetin-induced reductions in blood pressure in hypertensive individuals are not secondary to lower plasma angiotensin-converting enzyme activity or endothelin-1: nitric oxide. Nutr Res. 2012;32(8):557-64. PubMed
- Bedada SK, Neerati P. Evaluation of the effect of quercetin treatment on CYP2C9 enzyme activity of diclofenac in healthy human volunteers. Phytother Res. 2018 Feb;32(2):305-311. doi: 10.1002/ptr.5978. PubMed
- Zhao Q, Wei J, Zhang H. Effects of quercetin on the pharmacokinetics of losartan and its metabolite EXP3174 in rats. Xenobiotica 2019;49(5):563-8. PubMed
- Bhutani P, Rajanna PK, Paul AT. Impact of quercetin on pharmacokinetics of quetiapine: insights from in-vivo studies in wistar rats. Xenobiotica. 2020:1-7.
- Li C, Wang X, Bi Y, et al. Potent Inhibitors of Organic Anion Transporters 1 and 3 From Natural Compounds and Their Protective Effect on Aristolochic Acid Nephropathy. Toxicol Sci. 2020;175(2):279-291. PubMed
- Ni Y, Duan Z, Zhou D, et al. Identification of Structural Features for the Inhibition of OAT3-Mediated Uptake of Enalaprilat by Selected Drugs and Flavonoids. Front Pharmacol. 2020;11:802. PubMed
- Song YK, Yoon JH, Woo JK, et al. Quercetin is a flavonoid breast cancer resistance protein inhibitor with an impact on the oral pharmacokinetics of sulfasalazine in rats. Pharmaceutics 2020;12(5):397. PubMed
- Ahmad E, Jahangir M, Ismail MA, et al. Influence of quercetin pretreatment on pharmacokinetics of warfarin in rats. Curr Drug Saf 2022. PubMed
- Nambiar A, Kellogg D 3rd, Justice J, et al. Senolytics dasatinib and quercetin in idiopathic pulmonary fibrosis: results of a phase I, single-blind, single-center, randomized, placebo-controlled pilot trial on feasibility and tolerability. EBioMedicine 20 PubMed
Hesperidin 14 references
- Fernandez, S. P., Wasowski, C., Paladini, A. C., and Marder, M. Synergistic interaction between hesperidin, a natural flavonoid, and diazepam. Eur.J.Pharmacol. 4-11-2005;512(2-3):189-198. PubMed
- Jin, Y. R., Han, X. H., Zhang, Y. H., Lee, J. J., Lim, Y., Chung, J. H., and Yun, Y. P. Antiplatelet activity of hesperetin, a bioflavonoid, is mainly mediated by inhibition of PLC-gamma2 phosphorylation and cyclooxygenase-1 activity. Atherosclerosis 200
- Loscalzo, L. M., Wasowski, C., Paladini, A. C., and Marder, M. Opioid receptors are involved in the sedative and antinociceptive effects of hesperidin as well as in its potentiation with benzodiazepines. Eur.J.Pharmacol. 2-12-2008;580(3):306-313. PubMed
- Yamamoto, M., Suzuki, A., Jokura, H., Yamamoto, N., and Hase, T. Glucosyl hesperidin prevents endothelial dysfunction and oxidative stress in spontaneously hypertensive rats. Nutrition 2008;24(5):470-476. PubMed
- El-Readi, M. Z., Hamdan, D., Farrag, N., El-Shazly, A., and Wink, M. Inhibition of P-glycoprotein activity by limonin and other secondary metabolites from Citrus species in human colon and leukaemia cell lines. Eur.J.Pharmacol. 1-25-2010;626(2-3):139-145 PubMed
- Buckshee, K., Takkar, D., and Aggarwal, N. Micronized flavonoid therapy in internal hemorrhoids of pregnancy. Int J Gynaecol Obstet 1997;57(2):145-151. PubMed
- Uesawa, Y. and Mohri, K. Hesperidin in orange juice reduces the absorption of celiprolol in rats. Biopharm Drug Dispos. 2008;29(3):185-188. PubMed
- Cho, YA, Choi, DH, and Choi, JS. Effect of hesperidin on the oral pharmacokinetics of diltiazem and its main metabolite, desacetyldiltiazem, in rats. J Pharm Pharmacol. 2009;61(6):825-829. PubMed
- Piao, YJ and Choi, JS. Enhanced bioavailability of verapamil after oral administration with hesperidin in rats. Arch Pharm Res. 2008;31(4):518-522. PubMed
- Andersen KE. Hesperidin methyl chalcone?-?a new cosmetic contact allergen. Contact Dermatitis. 2015;72(6):402-4. PubMed
- Morand C, Dubray C, Milenkovic D, et al. Hesperidin contributes to the vascular protective effects of orange juice: a randomized crossover study in healthy volunteers. Am J Clin Nutr 2011;93(1):73-80. PubMed
- Homayouni F, Haidari F, Hedayati M, Zakerkish M, Ahmadi K. Blood pressure lowering and anti-inflammatory effects of hesperidin in type 2 diabetes; a randomized double-blind controlled clinical trial. Phytother Res. 2018;32(6):1073-1079. PubMed
- Mohammadi M, Ramezani-Jolfaie N, Lorzadeh E, Khoshbakht Y, Salehi-Abargouei A. Hesperidin, a major flavonoid in orange juice, might not affect lipid profile and blood pressure: A systematic review and meta-analysis of randomized controlled clinical trials PubMed
- Valls RM, Pedret A, Calderón-Pérez L, et al. Effects of hesperidin in orange juice on blood and pulse pressures in mildly hypertensive individuals: a randomized controlled trial (Citrus study). Eur J Nutr. 2021;60(3):1277-1288. PubMed
Acerola 20 references
- Back DJ, Breckenridge AM, MacIver M, et al. Interaction of ethinyloestradiol with ascorbic acid in man. Br Med J (Clin Res Ed) 1981;282:1516.
- Morris JC, Beeley L, Ballantine N. Interaction of ethinyloestradiol with ascorbic acid in man [letter]. Br Med J (Clin Res Ed) 1981;283:503.
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Rosenthal G. Interaction of ascorbic acid and warfarin. JAMA 1971;215:1671. DOI
- Hume R, Johnstone JM, Weyers E. Interaction of ascorbic acid and warfarin. JAMA 1972;219:1479. DOI
- Smith EC, Skalski RJ, Johnson GC, Rossi GV. Interaction of ascorbic acid and warfarin. JAMA 1972;221:1166. DOI
- Domingo JL, Gomez M, Llobet JM, Richart C. Effect of ascorbic acid on gastrointestinal aluminum absorption (letter). Lancet 1991;338:1467.
- Domingo JL, Gomez M, Llobet JM, Corbella J. Influence of some dietary constituents on aluminum absorption and retention in rats. Kidney Int 1991;39:598-601. PubMed
- Partridge NA, Regnier FE, White JL, Hem SL. Influence of dietary constituents on intestinal absorption of aluminum. Kidney Int 1989;35:1413-7. PubMed
- Mc Leod DC, Nahata MC. Inefficacy of ascorbic acid as a urinary acidifier (letter). N Engl J Med 1977;296:1413. DOI
- Hansten PD, Hayton WL. Effect of antacid and ascorbic acid on serum salicylate concentration. J Clin Pharmacol 1980;20:326-31. PubMed
- Vihtamaki T, Parantainen J, Koivisto AM, et al. Oral ascorbic acid increases plasma oestradiol during postmenopausal hormone replacement therapy. Maturitas 2002;42:129-35. PubMed
- Feetam CL, Leach RH, Meynell MJ. Lack of a clinically important interaction between warfarin and ascorbic acid. Toxicol Appl Pharmacol 1975;31:544-7. PubMed
- Weintraub M, Griner PF. Warfarin and ascorbic acid: lack of evidence for a drug interaction. Toxicol Appl Pharmacol 1974;28:53-6. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Denadai R, Souza FM, Valle MR. Fecal impaction by rectal acerola bezoar. Indian J Pediatr 2013;80(5):432-3. PubMed
- Raulf-Heimsoth M, Stark R, Sander I, et al. Anaphylactic reaction to apple juice containing acerola: cross-reactivity to latex due to prohevein. J Allergy Clin Immunol 2002;109(4):715-6. PubMed
Sodium 38 references
- Garabedian-Ruffalo SM, Ruffalo RL. Drug and nutrient interactions. Am Fam Physician 1986;33:165-74.
- Food and Drug Administration Science Background: Safety of Sodium Phosphates Oral Solution. September 17, 2001. Available at: http://www.fda.gov/cder/drug/safety/sodiumphospate.htm
- Coton T, Mallaret C, Coilliot C, Carre D, Guisset M. Severe acute ulcerated gastritis induced by salt. Presse Med 2009;38(3):499-500. PubMed
- Frings-Meuthen P, Buehlmeier J, Baecker N, et al. High sodium chloride intake exacerbates immobilization-induced bone resorption and protein losses. J Appl Physiol 2011;111(2):537-542. PubMed
- Frings-Meuthen P, Baecker N, Heer M. Low-grade metabolic acidosis may be the cause of sodium chloride-induced exaggerated bone resorption. J Bone Miner Res 2008;23(4):517-524. PubMed
- Alam S, Johnson AG. A meta-analysis of randomised controlled trials (RCT) among healthy normotensive and essential hypertensive elderly patients to determine the effect of high salt (NaCl) diet of blood pressure. J Hum Hypertens 1999;13(6):367-74.
- Boudville N, Ward S, Benaroia M, House AA. Increased sodium intake correlates with greater use of antihypertensive agents by subjects with chronic kidney disease. Am J Hypertens 2005;18(10):1300-5. PubMed
- Bennett WM. Drug interactions and consequences of sodium restriction. Am J Clin Nutr 1997;65(2 Suppl):678S-681S. PubMed
- Okusa MD, Crystal LJ. Clinical manifestations and management of acute lithium intoxication. Am J Med 1994;97(4):383-9. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary reference intakes for water, potassium, sodium, chloride, and sulfate. Washington, DC: National Academy Press, 2005. Available at: http://www.nap.edu/openbook.php?record_id=10925. DOI
- D'Elia L, Rossi G, Ippolito R, Cappuccio FP, Strazzullo P. Habitual salt intake and risk of gastric cancer: a meta-analysis of prospective studies. Clin Nutr 2012;31(4):489-98. PubMed
- Goldsmith SR. Hyponatremia in heart failure: time for a trial. J Card Fail 2013;19(6):398-400. PubMed
- Willocks L, Brettle R, Keen J, Valentine C, Pinching AJ. Formulations of didanosine (ddI) and salt overload. Lancet 1992;339(8786):190.
- Chen L, Zhang Z, Chen W, Whelton PK, Appel LJ. Lower Sodium Intake and Risk of Headaches: Results From the Trial of Nonpharmacologic Interventions in the Elderly. Am J Public Health. 2016;106(7):1270-5. PubMed
- Cook NR, Appel LJ, Whelton PK. Lower levels of sodium intake and reduced cardiovascular risk. Circulation. 2014;129(9):981-9. PubMed
- Cook NR, Appel LJ, Whelton PK. Sodium Intake and All-Cause Mortality Over 20 Years in the Trials of Hypertension Prevention. J Am Coll Cardiol. 2016;68(15):1609-1617. PubMed
- Mente A, O'Donnell M, Rangarajan S, et al. Associations of urinary sodium excretion with cardiovascular events in individuals with and without hypertension: a pooled analysis of data from four studies. Lancet. 2016;388(10043):465-75. PubMed
- Moosavian SP, Haghighatdoost F, Surkan PJ, Azadbakht L. Salt and obesity: a systematic review and meta-analysis of observational studies. Int J Food Sci Nutr. 2017;68(3):265-277. PubMed
- O'Donnell M, Mente A, Rangarajan S, et al. Urinary sodium and potassium excretion, mortality, and cardiovascular events. N Engl J Med. 2014;371(7):612-23. DOI
- Poggio R, Gutierrez L, Matta MG, Elorriaga N, Irazola V, Rubinstein A. Daily sodium consumption and CVD mortality in the general population: systematic review and meta-analysis of prospective studies. Public Health Nutr. 2015;18(4):695-704. PubMed
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
- Mahtani KR, Heneghan C, Onakpoya I, et al. Reduced Salt Intake for Heart Failure: A Systematic Review. JAMA Intern Med. 2018 Dec 1;178(12):1693-1700. PubMed
- Yancy CW. Sodium Restriction in Heart Failure: Too Much Uncertainty-Do the Trials. JAMA Intern Med. 2018 Dec 1;178(12):1700-1701. PubMed
- He FJ, Campbell NRC, Ma Y, MacGregor GA, Cogswell ME, Cook NR. Errors in estimating usual sodium intake by the Kawasaki formula alter its relationship with mortality: implications for public health. Int J Epidemiol. 2018;47(6):1784-1795. PubMed
- Murthy K, Ondrey GJ, Malkani N, et al. THE EFFECTS OF HYPONATREMIA ON BONE DENSITY AND FRACTURES: A SYSTEMATIC REVIEW AND META-ANALYSIS. Endocr Pract. 2019;25(4):366-378. PubMed
- Messerli FH, Hofstetter L, Syrogiannouli L, et al. Sodium intake, life expectancy, and all-cause mortality. Eur Heart J 2021;42(21):2103-2112. PubMed
- Graudal NA, Hubeck-Graudal T, Jurgens G. Effects of low sodium diet versus high sodium diet on blood pressure, renin, aldosterone, catecholamines, cholesterol, and triglyceride. Cochrane Database Syst Rev 2020;12(12):CD004022. PubMed
- Giatti S, Santos RB, Aielo AN, et al. Association of sodium with obstructive sleep apnea. The ELSA-Brasil study. Ann Am Thorac Soc 2021;18(3):502-510. PubMed
- Nan X, Lu H, Wu J, et al. The interactive association between sodium intake, alcohol consumption and hypertension among elderly in northern China: a cross-sectional study. BMC Geriatr 2021;21(1):135. PubMed
- Kyozuka H, Fukusda T, Murata T, et al. Impact of preconception sodium intake on hypertensive disorders of pregnancy: The Japan Environment and Children's study. Pregnancy Hypertens 2021;23:66-72. PubMed
- Zhao L, Ogden CL, Yang Q, et al. Association of usual sodium intake with obesity among US children and adolescents, NHANES 2009-2016. Obesity (Silver Spring) 2021;29(3):587-594. PubMed
- Ma Y, He FJ, Sun Q, et al. 24-Hour urinary sodium and potassium excretion and cardiovascular risk. N Engl J Med 2022;386(3):252-263. PubMed
- Liu J, Yang X, Zhang P, et al. Association of urinary sodium excretion and left ventricular hypertrophy in people with type 2 diabetes mellitus: A cross-sectional study. Front Endocrinol (Lausanne) 2021;12:728493. PubMed
- Filippini T, Malavolti M, Whelton PK, Vinceti M. Sodium intake and risk of hypertension: A systematic review and dose-response meta-analysis of observational cohort studies. Curr Hypertens Rep 2022;24(5):133-144. PubMed
- Wang DD, Li Y, Nguyen XT, et al. Dietary sodium and potassium intake and risk of non-fatal cardiovascular diseases: The million veteran program. Nutrients 2022;14(5):1121. PubMed
- Kwak JH, Park CH, Eun CS, et al. The associations of dietary intake of high sodium and low zinc with gastric cancer mortality: A prospective cohort study in Korea. Nutr Cancer 2022;74(10):3501-3508. PubMed
- George S, Maiti R, Mishra BR, Jena M, Mohapatra D. Effect of regulated add-on sodium chloride intake on stabilization of serum lithium concentration in bipolar disorder: A randomized controlled trial. Bipolar Disord 2023;25(1):66-75. PubMed
- Zhou TL, Schütten MTJ, Kroon AA, et al. Urinary Sodium Excretion and Salt Intake Are Not Associated With Blood Pressure Variability in a White General Population. J Am Heart Assoc 2023;12(1):e026578. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC