
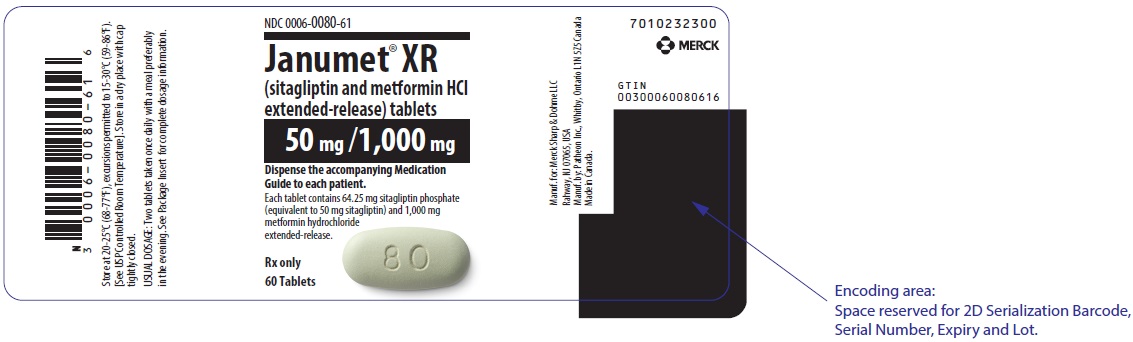
JANUMET XR sitagliptin and metformin hydrochloride 50 mg; 1000 mg Tablet, Film Coated, Extended Release, 1,000-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Dipeptidyl Peptidase 4 Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- It's a two-in-one pill that tackles high blood sugar in two different ways. The sitagliptin part helps your body hold onto natural gut hormones that tell your pancreas to release m...
- What exactly is this medication doing to help my blood sugar?
- Diarrhea, nausea, and stomach discomfort are the most common complaints, especially in the first few weeks. Taking it with meals — not on an empty stomach — is the single most impo...
- What stomach side effects should I expect when I start this medication?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII LMI26O6933
Alumina is a white powder form of aluminum oxide. It's used as a filler to add bulk to tablets and capsules, and sometimes as a thickening or anti-caking agent in powdered formulations.
-
UNII R12CBM0EIZ
A natural wax derived from a Brazilian palm tree, used as a coating and polish on tablets and capsules. It creates a smooth, shiny finish that protects the medicine and improves appearance.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII VM7F0B23ZI
Hypromellose 2208 is a plant-derived thickening agent that forms a protective coating on tablets and capsules. It slows down how quickly the medicine dissolves, controlling drug release into your body.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII D3741U8K7L
A blue colorant derived from indigo dye. It's added to tablets and capsules to provide color identification and improve the appearance of the medication.
-
UNII 24H4NWX5CO
Kaolin is a naturally occurring clay mineral. It's used in tablets and capsules as a filler and absorbent to add bulk, improve texture, and help bind ingredients together.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII 8D4SNN7V92
Propyl gallate is a synthetic antioxidant derived from gallic acid. It prevents oils and fats in the medicine from oxidizing and spoiling, helping the product stay stable and effective during storage.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
15 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $5.276 | $5,276.20 / 1000 tablets |
| Medicaid paysCMS SDUD · 12 mo | $5.85 | $5,849.70 / 1000 tablets |
| Medicare drug plans payPart D · Q2 2026 | $5.28 | $5,283.50 / 1000 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Janumet Xr 50 mg/1; 1000 mgthis 00006-0080-82 | Merck | 1000 tablets | $5.276 | AB | Availability likely | — |
| Janumet Xr 50 mg/1; 1000 mg 50090-5504-00 | A-S | 60 tablets | — | AB | FDA listed | — |
| Sitagliptin and Metformin hydrochloride 50 mg/1; 1000 mg 10370-0318-02 | Par | 60 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 7326708 ↗ | Drug substance | U-1227 | Nov 24, 2026 |
| US 7326708 ↗ | Drug substance | U-1227 | Nov 24, 2026 |
| US 7326708 ↗ | Drug substance | U-1227 | Nov 24, 2026 |
| US 7326708*PED ↗ | Drug product | — | May 24, 2027 |
| US 7326708*PED ↗ | Drug product | — | May 24, 2027 |
| US 7326708*PED ↗ | Drug product | — | May 24, 2027 |
Is there a generic version of JANUMET XR 50-1,000 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 00006-0080-28 | 2 BOTTLE in 1 CARTON (0006-0080-28) / 14 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE (0006-0080-14) | — | — | 2012-02-02 | Active |
| 00006-0080-61 | 60 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE (0006-0080-61) | $5.28 / ea | $316.57 | 2012-02-02 | Active |
| 00006-0080-62 | 180 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE (0006-0080-62) | $5.28 / ea | $949.71 | 2012-02-02 | Active |
| 00006-0080-82 You're viewing this | 1000 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE (0006-0080-82) | $5.28 / ea | $5,276.19 | 2012-02-02 | Active |
This pack effectively ties for the lowest per-ea cost of the 3 priced pack sizes ($5.28 NADAC).
Pack size FAQ
What quantity is in NDC 00006-0080-82?
What is the difference between NDC 00006-0080-82 and NDC 00006-0080-61?
What NDC number is used to bill for this package of JANUMET XR sitagliptin and metformin hydrochloride 50 mg; 1000 mg Tablet, Film Coated, Extended Release?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: LACTIC ACIDOSIS Postmarketing cases of metformin-associated lactic acidosis have resulted in death, hypothermia, hypotension, and resistant bradyarrhythmias. The onset of metformin-associated lactic acidosis is often subtle, accompanied only by nonspecific symptoms such as malaise, myalgias, respiratory distress, somnolence, and abdominal pain. Metformin-associated lactic acidosis was characterized by elevated blood lactate levels (>5 mmol/Liter), anion gap acidosis (without evidence of ketonuria or ketonemia), an increased lactate/pyruvate ratio, and metformin plasma levels generally >5 mcg/mL [see Warnings and Precautions (5.1) ].
Risk factors for metformin-associated lactic acidosis include renal impairment, concomitant use of certain drugs (e.g., carbonic anhydrase inhibitors such as topiramate), age 65 years old or greater, having a radiological study with contrast, surgery and other procedures, hypoxic states (e.g., acute congestive heart failure), excessive alcohol intake, hepatic impairment, and mitochondrial diseases [see Warnings and Precautions (5.1) ] . Steps to reduce the risk of and manage metformin-associated lactic acidosis in these high-risk groups are provided in the full prescribing information [see Dosage and Administration (2.2) , Contraindications (4) , Warnings and Precautions (5.1) , Drug Interactions (7) , and Use in Specific Populations (8.6 , 8.7) ].
If metformin-associated lactic acidosis is suspected, immediately discontinue JANUMET XR and institute general supportive measures in a hospital setting. Prompt hemodialysis is recommended [see Warnings and Precautions (5.1) ]. WARNING: LACTIC ACIDOSIS See full prescribing information for complete boxed warning .
Postmarketing cases of metformin-associated lactic acidosis have resulted in death, hypothermia, hypotension, and resistant bradyarrhythmias. Symptoms included malaise, myalgias, respiratory distress, somnolence, and abdominal pain. Laboratory abnormalities included elevated blood lactate levels, anion gap acidosis, increased lactate/pyruvate ratio, and metformin plasma levels generally >5 mcg/mL.
( 5.1 ) Risk factors include renal impairment, concomitant use of certain drugs, age ≥65 years old, radiological studies with contrast, surgery and other procedures, hypoxic states, excessive alcohol intake, hepatic impairment, and mitochondrial diseases. Steps to reduce the risk of and manage metformin-associated lactic acidosis in these high-risk groups are provided in the Full Prescribing Information. ( 5.1 ) If lactic acidosis is suspected, discontinue JANUMET XR and institute general supportive measures in a hospital setting.
Prompt hemodialysis is recommended. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE JANUMET ® XR is indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus. JANUMET XR is a combination of sitagliptin, a dipeptidyl peptidase-4 (DPP-4) inhibitor, and metformin hydrochloride (HCl), a biguanide indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus. ( 1 ) Limitations of Use: Not for the treatment of type 1 diabetes.
( 1 ) Has not been studied in patients with a history of pancreatitis. ( 1 , 5.2 ) Limitations of Use JANUMET XR should not be used in patients with type 1 diabetes mellitus. JANUMET XR has not been studied in patients with a history of pancreatitis.
It is unknown whether patients with a history of pancreatitis are at increased risk for the development of pancreatitis while using JANUMET XR [see Warnings and Precautions (5.2) ].
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Take JANUMET XR orally once daily with a meal. Patients taking two JANUMET XR tablets should take the tablets together. ( 2.1 ) Individualize the dosage of JANUMET XR on the basis of the patient’s current regimen, effectiveness, and tolerability.
( 2.1 ) The maximum recommended daily dose is 100 mg of sitagliptin and 2000 mg of metformin HCl extended-release. ( 2.1 ) The recommended starting dose in patients not currently treated with metformin is 100 mg sitagliptin and 1000 mg metformin HCl once daily, with gradual dose escalation recommended to reduce the gastrointestinal effects due to metformin. ( 2.1 ) The starting dose in patients already treated with metformin should provide sitagliptin dosed as 100 mg and the dose of metformin already being taken once daily.
For patients taking metformin HCl 850 mg twice daily or 1000 mg twice daily, the recommended starting dose of JANUMET XR is two 50 mg sitagliptin and 1000 mg metformin HCl extended-release tablets once daily. ( 2.1 ) Maintain the same total daily dose of sitagliptin and metformin when changing between JANUMET and JANUMET XR. ( 2.1 ) Prior to initiation, assess renal function with estimated glomerular filtration rate (eGFR) ( 2.2 ) Do not use in patients with eGFR below 30 mL/min/1.73 m 2 .
Discontinue if eGFR later falls below 30 mL/min/1.73 m 2 . Initiation is not recommended in patients with eGFR between 30 – 45 mL/min/1.73 m 2 . Assess risk/benefit of continuing if eGFR falls below 45 mL/min/1.73 m 2 .
Limit dose of sitagliptin to 50 mg once daily if eGFR falls below 45 mL/min/1.73 m 2 . JANUMET XR may need to be discontinued at time of, or prior to, iodinated contrast imaging procedures. ( 2.3 )
2.1Recommended Dosing Take JANUMET XR orally once daily with a meal. Patients taking two JANUMET XR tablets should take the two tablets together once daily. Individualize the dosage of JANUMET XR on the basis of the patient’s current regimen, effectiveness, and tolerability.
The maximum recommended daily dose is 100 mg of sitagliptin and 2000 mg of metformin hydrochloride (HCl) extended-release. The recommended starting dose in patients not currently treated with metformin is 100 mg sitagliptin and 1000 mg metformin HCl extended-release once daily, with gradual dose escalation recommended to reduce gastrointestinal side effects associated with metformin. The starting dose in patients already treated with metformin should provide 100 mg sitagliptin and the previously prescribed dose of metformin.
For patients taking metformin HCl immediate-release 850 mg twice daily or 1000 mg twice daily, the recommended starting dose of JANUMET XR is two 50 mg sitagliptin and 1000 mg metformin HCl extended-release tablets taken together once daily. Maintain the same total daily dose of sitagliptin and metformin when changing between JANUMET (sitagliptin and metformin HCl immediate-release) and JANUMET XR. Do not split, crush or chew JANUMET XR tablets.
2.2Recommendations for Use in Renal Impairment Assess renal function prior to initiation of JANUMET XR and periodically thereafter. JANUMET XR is contraindicated in patients with an estimated glomerular filtration rate (eGFR) below 30 mL/min/1.73 m 2 . Discontinue JANUMET XR if the patient's eGFR later falls below 30 mL/min/1.73 m 2 [see Contraindications (4) and Warnings and Precautions (5.1) ] .
Initiation of JANUMET XR in patients with an eGFR between 30 and 45 mL/min/1.73 m 2 is not recommended. In patients taking JANUMET XR whose eGFR later falls below 45 mL/min/1.73 m 2 , assess the benefit risk of continuing therapy and limit dose of the sitagliptin component to 50 mg once daily.
2.3Discontinuation for Iodinated Contrast Imaging Procedures Discontinue JANUMET XR at the time of, or prior to, an iodinated contrast imaging procedure in patients with an eGFR between 30 and 60 mL/min/1.73 m 2 ; in patients with a history of liver disease, alcoholism, or heart failure; or in patients who will be administer…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: sitagliptin 100 mg and metformin HCl 1000 mg extended-release tablets are blue, bi-convex oval, film-coated tablets with “81” debossed on one side. sitagliptin 50 mg and metformin HCl 500 mg extended-release tablets are light blue, bi-convex oval, film-coated tablets with “78” debossed on one side. sitagliptin 50 mg and metformin HCl 1000 mg extended-release tablets are light green, bi-convex oval, film-coated tablets with “80” debossed on one side. JANUMET XR Tablets: sitagliptin 100 mg and metformin HCl 1000 mg extended-release sitagliptin 50 mg and metformin HCl 500 mg extended-release sitagliptin 50 mg and metformin HCl 1000 mg extended-release ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS JANUMET XR is contraindicated in patients with: Severe renal impairment (eGFR below 30 mL/min/1.73 m 2 ) [see Warnings and Precautions (5.1) ] . Acute or chronic metabolic acidosis, including diabetic ketoacidosis. History of a serious hypersensitivity reaction to JANUMET XR, sitagliptin, or metformin such as anaphylaxis or angioedema [see Warnings and Precautions (5.7) and Adverse Reactions (6.2) ].
Severe renal impairment: eGFR below 30 mL/min/1.73 m 2 . ( 4 ) Metabolic acidosis, including diabetic ketoacidosis. ( 4 ) History of a serious hypersensitivity reaction (e.g., anaphylaxis or angioedema) to JANUMET XR, sitagliptin, or metformin.
( 5.7 , 6.2 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Lactic Acidosis: See boxed warning . ( 5.1 ) Pancreatitis: There have been postmarketing reports of acute pancreatitis, including fatal and non-fatal hemorrhagic or necrotizing pancreatitis in patients treated with sitagliptin. If pancreatitis is suspected, promptly discontinue JANUMET XR.
( 5.2 ) Heart Failure: Has been observed with two other members of the DPP-4 inhibitor class. Consider risks and benefits of JANUMET XR in patients who have known risk factors for heart failure. Monitor patients for signs and symptoms.
( 5.3 ) Acute Renal Failure: Has been reported postmarketing sometimes requiring dialysis. Before initiating JANUMET XR and at least annually thereafter, assess renal function. ( 5.4 ) Vitamin B 12 Deficiency: Metformin may lower vitamin B 12 levels.
Measure hematologic parameters annually and vitamin B 12 at 2 to 3 year intervals and manage any abnormalities. ( 5.5 ) Hypoglycemia with Concomitant Use with Insulin or Insulin Secretagogues: Increased risk of hypoglycemia when used in combination with insulin and/or an insulin secretagogue. A lower dose of insulin or insulin secretagogue may be required.
( 5.6 ) Hypersensitivity Reactions: There have been postmarketing reports of serious allergic and hypersensitivity reactions in patients treated with sitagliptin, such as anaphylaxis, angioedema, and exfoliative skin conditions including Stevens-Johnson syndrome. Promptly stop JANUMET XR, assess for other potential causes, institute appropriate monitoring and treatment. ( 5.7 ) Severe and Disabling Arthralgia: Has been reported in patients taking DPP-4 inhibitors.
Consider as a possible cause for severe joint pain and discontinue drug if appropriate. ( 5.8 ) Bullous Pemphigoid: There have been postmarketing reports requiring hospitalization in patients taking DPP-4 inhibitors. Tell patients to report development of blisters or erosions.
If bullous pemphigoid is suspected, discontinue JANUMET XR. ( 5.9 )
5.1Lactic Acidosis There have been postmarketing cases of metformin-associated lactic acidosis, including fatal cases. These cases had a subtle onset and were accompanied by nonspecific symptoms such as malaise, myalgias, abdominal pain, respiratory distress, or increased somnolence; however, hypothermia, hypotension and resistant bradyarrhythmias have occurred with severe acidosis. Metformin-associated lactic acidosis was characterized by elevated blood lactate concentrations (>5 mmol/Liter), anion gap acidosis (without evidence of ketonuria or ketonemia), and an increased lactate/pyruvate ratio; metformin plasma levels were generally >5 mcg/mL.
Metformin decreases liver uptake of lactate increasing lactate blood levels which may increase the risk of lactic acidosis, especially in patients at risk. If metformin-associated lactic acidosis is suspected, general supportive measures should be instituted promptly in a hospital setting, along with immediate discontinuation of JANUMET XR. In JANUMET XR-treated patients with a diagnosis or strong suspicion of lactic acidosis, prompt hemodialysis is recommended to correct the acidosis and remove accumulated metformin (metformin is dialyzable, with a clearance of up to 170 mL/min under good hemodynamic conditions).
Hemodialysis has often resulted in reversal of symptoms and recovery. Educate patients and their families about the symptoms of lactic acidosis, and if these symptoms occur instruct them to discontinue JANUMET XR and report these symptoms to their health care provider. For each of the known and possible risk factors for metformin-associated lactic acidosis, recommendations to reduce the risk of and manage metformin-associated lactic acidosis are provided below: Renal Impairment: The postmarketing metformin-associated lactic acidosis cases primarily occurred in patients with significant renal impairment.
The risk of metformin accumulation and metformin-associated lactic acidosis increases with the severity of renal impairment because…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are also discussed elsewhere in the labeling: Lactic Acidosis [see Warnings and Precautions (5.1) ] Pancreatitis [see Warnings and Precautions (5.2) ] Heart Failure [see Warnings and Precautions (5.3) ] Acute Renal Failure [see Warnings and Precautions (5.4) ] Vitamin B 12 Deficiency [see Warnings and Precautions (5.5) ] Hypoglycemia with Concomitant Use with Insulin or Insulin Secretagogues [see Warnings and Precautions (5.6) ] Hypersensitivity Reactions [see Warnings and Precautions (5.7) ] Severe and Disabling Arthralgia [see Warnings and Precautions (5.8) ] Bullous Pemphigoid [see Warnings and Precautions (5.9) ] The most common adverse reactions reported in ≥5% of patients simultaneously started on sitagliptin and metformin and more commonly than in patients treated with placebo were diarrhea, upper respiratory tract infection, and headache.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Merck Sharp & Dohme LLC at 1-877-888-4231 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Sitagliptin and Metformin Immediate-Release Coadministration in Patients with Type 2 Diabetes Inadequately Controlled on Diet and Exercise Table 1 summarizes the most common (≥5% of patients) adverse reactions reported (regardless of investigator assessment of causality) in a 24-week placebo-controlled factorial study in which sitagliptin and metformin immediate-release were coadministered to patients with type 2 diabetes inadequately controlled on diet and exercise.
Table 1: Sitagliptin and Metformin Immediate-Release Coadministered to Patients with Type 2 Diabetes Inadequately Controlled on Diet and Exercise: Adverse Reactions Reported (Regardless of Investigator Assessment of Causality) in ≥5% of Patients Receiving Combination Therapy (and Greater than in Patients Receiving Placebo) Intent-to-treat population. Number of Patients (%) Placebo Sitagliptin 100 mg once daily Metformin HCl Immediate-Release 500 mg or 1000 mg twice daily Data pooled for the patients given the lower and higher doses of metformin.
Sitagliptin 50 mg twice daily + Metformin HCl Immediate- Release 500 mg or 1000 mg twice daily N = 176 N = 179 N = 364 N = 372 Diarrhea 7 (4.0) 5 (2.8) 28 (7.7) 28 (7.5) Upper Respiratory Tract Infection 9 (5.1) 8 (4.5) 19 (5.2) 23 (6.2) Headache 5 (2.8) 2 (1.1) 14 (3.8) 22 (5.9) Sitagliptin Add-on Therapy in Patients with Type 2 Diabetes Inadequately Controlled on Metformin Immediate-Release Alone In a 24-week placebo-controlled trial of sitagliptin 100 mg administered once daily added to a twice daily metformin immediate-release regimen, there were no adverse reactions reported regardless of investigator assessment of causality in ≥5% of patients and more commonly than in patients given placebo.
Discontinuation of therapy due to clinical adverse reactions was similar to the placebo treatment group (sitagliptin and metformin immediate-release, 1.9%; placebo and metformin immediate-release, 2.5%). Gastrointestinal Adverse Reactions The incidences of pre-selected gastrointestinal adverse experiences in patients treated with sitagliptin and metformin immediate-release were similar to those reported for patients treated with metformin immediate-release alone. See Table 2 .
Table 2: Pre-selected Gastrointestinal Adverse Reactions (Regardless of Investigator Assessment of Causality) Reported in Patients with Type 2 Diabetes Receiving Sitagliptin and Metformin Immediate-Release Number of Patients (%) Study of Sitagliptin and Metformin Immediate-Release in Patients Inadequately Controlled on Diet and Exercise Study of Sitagliptin Add-on in Patients Inadequately Controlled on Metformin Immediate-Release…
🔄 Drug Interactions ▾
Drug Interactions The concomitant use of JANUMET XR with specific drugs may increase the risk of metformin-associated lactic acidosis: those that impair renal function, result in significant hemodynamic change, interfere with acid-base balance or increase metformin accumulation [see Drug Interactions (7) ]. Therefore, consider more frequent monitoring of patients.
7 DRUG INTERACTIONS Table 4 presents clinically significant drug interactions with JANUMET XR: Table 4: Clinically Significant Drug Interactions with JANUMET XR Carbonic Anhydrase Inhibitors Clinical Impact: Carbonic anhydrase inhibitors frequently cause a decrease in serum bicarbonate and induce non-anion gap, hyperchloremic metabolic acidosis. Concomitant use of these drugs with JANUMET XR may increase the risk for lactic acidosis. Intervention: Consider more frequent monitoring of these patients.
Examples: Topiramate, zonisamide, acetazolamide or dichlorphenamide. Drugs that Reduce Metformin Clearance Clinical Impact: Concomitant use of drugs that interfere with common renal tubular transport systems involved in the renal elimination of metformin (e.g., organic cationic transporter-2 [OCT 2 ] / multidrug and toxin extrusion [MATE] inhibitors) could increase systemic exposure to metformin and may increase the risk for lactic acidosis [see Clinical Pharmacology (12.3) ]. Intervention: Consider the benefits and risks of concomitant use with JANUMET XR.
Examples: Ranolazine, vandetanib, dolutegravir, and cimetidine. Alcohol Clinical Impact: Alcohol is known to potentiate the effect of metformin on lactate metabolism. Intervention: Warn patients against alcohol intake while receiving JANUMET XR.
Insulin Secretagogues or Insulin Clinical Impact: Coadministration of JANUMET XR with an insulin secretagogue (e.g., sulfonylurea) or insulin may increase the risk of hypoglycemia. Intervention: Patients receiving an insulin secretagogue or insulin may require lower doses of the insulin secretagogue or insulin. Drugs Affecting Glycemic Control Clinical Impact: Certain drugs tend to produce hyperglycemia and may lead to loss of glycemic control.
Intervention: When such drugs are administered to a patient receiving JANUMET XR, observe the patient closely for loss of blood glucose control. When such drugs are withdrawn from a patient receiving JANUMET XR, observe the patient closely for hypoglycemia. Examples: Thiazides and other diuretics, corticosteroids, phenothiazines, thyroid products, estrogens, oral contraceptives, phenytoin, nicotinic acid, sympathomimetics, calcium channel blockers, and isoniazid.
Carbonic anhydrase inhibitors may increase risk of lactic acidosis. Consider more frequent monitoring. ( 7 ) Drugs that reduce metformin clearance (such as ranolazine, vandetanib, dolutegravir, and cimetidine) may increase the accumulation of metformin.
Consider the benefits and risks of concomitant use. ( 7 ) Alcohol can potentiate the effect of metformin on lactate metabolism. Warn patients against excessive alcohol intake.
( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Females and Males of Reproductive Potential: Advise premenopausal females of the potential for an unintended pregnancy. ( 8.3 ) Geriatric Use: Assess renal function more frequently. ( 8.5 ) Hepatic Impairment: Avoid use in patients with hepatic impairment. ( 8.7 )
8.1Pregnancy Risk Summary The limited available data with JANUMET XR in pregnant women are not sufficient to inform a drug-associated risk for major birth defects and miscarriage. Published studies with metformin use during pregnancy have not reported a clear association with metformin and major birth defect or miscarriage risk [see Data ] . There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy [see Clinical Considerations ] .
No adverse developmental effects were observed when sitagliptin was administered to pregnant rats and rabbits during organogenesis at oral doses up to 30-times and 20-times, respectively, the 100 mg clinical dose, based on AUC. No adverse developmental effects were observed when metformin was administered to pregnant Sprague Dawley rats and rabbits during organogenesis at doses up to 2- and 6-times, respectively, a 2000 mg clinical dose, based on body surface area [see Data ] . The estimated background risk of major birth defects is 6-10% in women with pre-gestational diabetes with a Hemoglobin A1c >7% and has been reported to be as high as 20-25% in women with a Hemoglobin A1c >10%.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, still birth, and macrosomia related morbidity.
Data Human Data Published data from post-marketing studies do not report a clear association with metformin and major birth defects, miscarriage, or adverse maternal or fetal outcomes when metformin is used during pregnancy. However, these studies cannot definitely establish the absence of any risk because of methodological limitations, including small sample size and inconsistent comparator groups. Animal Data Sitagliptin and Metformin No animal reproduction studies were conducted with the coadministration of sitagliptin and metformin.
Sitagliptin In embryo-fetal development studies, sitagliptin administered to pregnant rats and rabbits during organogenesis (gestation day 6 to 20) did not adversely affect developmental outcomes at oral doses up to 250 mg/kg (30-times the 100 mg clinical dose) and 125 mg/kg (20-times the 100 mg clinical dose), respectively, based on AUC. Higher doses in rats associated with maternal toxicity increased the incidence of rib malformations in offspring at 1000 mg/kg, or approximately 100-times the clinical dose, based on AUC.
Placental transfer of sitagliptin was observed in pregnant rats and rabbits. Sitagliptin administered to female rats from gestation day 6 to lactation day 21 caused no functional or behavioral toxicity in offspring of rats at doses up to 1000 mg/kg. Metformin Metformin did not cause adverse developmental effects when administered to pregnant Sprague Dawley rats and rabbits up to 600 mg/kg/day during the period of organogenesis.
This represents an exposure of about 2- and 6-times a 2000 mg clinical dose based on body surface area (mg/m 2 ) for rats and rabbits, respectively.
8.2Lactation Risk Summary There is no information regarding the presence of JANUMET XR in human milk, the effects on the breastfed infant, or the effects on milk production. Limited published studies report that metformin is present in human milk [see Data ] . There are no reports of adverse effects on breastfed infants exposed to…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The limited available data with JANUMET XR in pregnant women are not sufficient to inform a drug-associated risk for major birth defects and miscarriage. Published studies with metformin use during pregnancy have not reported a clear association with metformin and major birth defect or miscarriage risk [see Data ] . There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy [see Clinical Considerations ] .
No adverse developmental effects were observed when sitagliptin was administered to pregnant rats and rabbits during organogenesis at oral doses up to 30-times and 20-times, respectively, the 100 mg clinical dose, based on AUC. No adverse developmental effects were observed when metformin was administered to pregnant Sprague Dawley rats and rabbits during organogenesis at doses up to 2- and 6-times, respectively, a 2000 mg clinical dose, based on body surface area [see Data ] . The estimated background risk of major birth defects is 6-10% in women with pre-gestational diabetes with a Hemoglobin A1c >7% and has been reported to be as high as 20-25% in women with a Hemoglobin A1c >10%.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, still birth, and macrosomia related morbidity.
Data Human Data Published data from post-marketing studies do not report a clear association with metformin and major birth defects, miscarriage, or adverse maternal or fetal outcomes when metformin is used during pregnancy. However, these studies cannot definitely establish the absence of any risk because of methodological limitations, including small sample size and inconsistent comparator groups. Animal Data Sitagliptin and Metformin No animal reproduction studies were conducted with the coadministration of sitagliptin and metformin.
Sitagliptin In embryo-fetal development studies, sitagliptin administered to pregnant rats and rabbits during organogenesis (gestation day 6 to 20) did not adversely affect developmental outcomes at oral doses up to 250 mg/kg (30-times the 100 mg clinical dose) and 125 mg/kg (20-times the 100 mg clinical dose), respectively, based on AUC. Higher doses in rats associated with maternal toxicity increased the incidence of rib malformations in offspring at 1000 mg/kg, or approximately 100-times the clinical dose, based on AUC.
Placental transfer of sitagliptin was observed in pregnant rats and rabbits. Sitagliptin administered to female rats from gestation day 6 to lactation day 21 caused no functional or behavioral toxicity in offspring of rats at doses up to 1000 mg/kg. Metformin Metformin did not cause adverse developmental effects when administered to pregnant Sprague Dawley rats and rabbits up to 600 mg/kg/day during the period of organogenesis.
This represents an exposure of about 2- and 6-times a 2000 mg clinical dose based on body surface area (mg/m 2 ) for rats and rabbits, respectively.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of JANUMET XR have not been established in pediatric patients. Three 20-week double-blind, placebo-controlled studies each with 34-week extensions were conducted to evaluate the efficacy and safety of sitagliptin in 410 pediatric patients aged 10 to 17 years with inadequately controlled type 2 diabetes, with or without insulin therapy (HbA1c 6.5-10% for patients not on insulin, HbA1c 7-10% for patients on insulin). At study entry, patients in study 1 were not treated with oral antihyperglycemic agents; patients in studies 2 and 3 were on maximally tolerated metformin therapy.
The primary efficacy endpoint was the change from baseline in HbA1c after 20 weeks of therapy. The pre-specified primary efficacy analyses included data from study 1 and pooled data from studies 2 and 3, regardless of glycemic rescue or treatment discontinuation. In both efficacy analyses, the effect of treatment with sitagliptin was not significantly different from placebo.
In study 1, the mean baseline HbA1c was 7.5%, and 12% of patients were on insulin therapy. At week 20, the change from baseline in HbA1c in patients treated with sitagliptin (N=95) was 0.06% compared to 0.23% in patients treated with placebo (N=95), a difference of -0.17% (95% CI: -0.62, 0.28). In studies 2 and 3, the mean baseline HbA1c was 8.0%, 15% of patients were on insulin and 72% were on metformin HCl doses of greater than 1,500 mg daily.
At week 20, the change from baseline in HbA1c in patients treated with sitagliptin (N=107) was -0.23% compared to 0.09% in patients treated with placebo (N=113), a difference of -0.33% (95% CI: -0.70, 0.05).
🧓 Geriatric Use ▾
8.5Geriatric Use JANUMET XR In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and concomitant disease or other drug therapy and the higher risk of lactic acidosis. Renal function should be assessed more frequently in elderly patients [see Contraindications (4) , Warnings and Precautions (5.1 , 5.4) and Clinical Pharmacology (12.3) ]. Sitagliptin Of the total number of subjects (N=3884) in clinical studies of sitagliptin, 725 patients were 65 years and over, while 61 patients were 75 years and over.
No overall differences in safety or effectiveness were observed between subjects 65 years and over and younger subjects. While this and other reported clinical experience have not identified differences in responses between the elderly and younger patients, greater sensitivity of some older individuals cannot be ruled out. Metformin Controlled clinical studies of metformin did not include sufficient numbers of elderly patients to determine whether they respond differently from younger patients, although other reported clinical experience has not identified differences in responses between the elderly and young patients.
🆘 Overdosage ▾
10 OVERDOSAGE In the event of overdose with JANUMET XR, contact the Poison Control Center. In the event of an overdose, it is reasonable to employ supportive measures, e.g., remove unabsorbed material from the gastrointestinal tract, employ clinical monitoring (including obtaining an electrocardiogram), and institute supportive therapy as indicated by the patient's clinical status. Sitagliptin is modestly dialyzable.
In clinical studies, approximately 13.5% of the dose was removed over a 3- to 4-hour hemodialysis session. Prolonged hemodialysis may be considered if clinically appropriate. It is not known if sitagliptin is dialyzable by peritoneal dialysis.
Overdose of metformin has occurred, including ingestion of amounts greater than 50 grams. Hypoglycemia was reported in approximately 10% of cases, but no causal association with metformin has been established. Lactic acidosis has been reported in approximately 32% of metformin overdose cases [see Warnings and Precautions (5.1) ] .
Metformin is dialyzable with a clearance of up to 170 mL/min under good hemodynamic conditions. Therefore, hemodialysis may be useful for removal of accumulated drug from patients in whom metformin overdosage is suspected.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action JANUMET XR JANUMET XR tablets combine two antihyperglycemic agents with complementary mechanisms of action to improve glycemic control in adults with type 2 diabetes mellitus: sitagliptin, a dipeptidyl peptidase-4 (DPP-4) inhibitor, and metformin extended-release, a member of the biguanide class. Sitagliptin Sitagliptin is a DPP-4 inhibitor, which exerts its actions in patients with type 2 diabetes by slowing the inactivation of incretin hormones. Concentrations of the active intact hormones are increased by sitagliptin, thereby increasing and prolonging the action of these hormones.
Incretin hormones, including glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP), are released by the intestine throughout the day, and levels are increased in response to a meal. These hormones are rapidly inactivated by the enzyme DPP-4. The incretins are part of an endogenous system involved in the physiologic regulation of glucose homeostasis.
When blood glucose concentrations are normal or elevated, GLP-1 and GIP increase insulin synthesis and release from pancreatic beta cells by intracellular signaling pathways involving cyclic AMP. GLP-1 also lowers glucagon secretion from pancreatic alpha cells, leading to reduced hepatic glucose production. By increasing and prolonging active incretin levels, sitagliptin increases insulin release and decreases glucagon levels in the circulation in a glucose-dependent manner.
Sitagliptin demonstrates selectivity for DPP-4 and does not inhibit DPP-8 or DPP-9 activity in vitro at concentrations approximating those from therapeutic doses. Metformin Metformin is a biguanide that improves glycemic control in patients with type 2 diabetes mellitus, lowering both basal and postprandial plasma glucose. Metformin decreases hepatic glucose production, decreases intestinal absorption of glucose, and improves insulin sensitivity by increasing peripheral glucose uptake and utilization.
With metformin therapy, insulin secretion remains unchanged while fasting insulin levels and day-long plasma insulin response may decrease.
12.2Pharmacodynamics Sitagliptin In patients with type 2 diabetes mellitus, administration of sitagliptin led to inhibition of DPP-4 enzyme activity for a 24-hour period. After an oral glucose load or a meal, this DPP-4 inhibition resulted in a 2- to 3-fold increase in circulating levels of active GLP-1 and GIP, decreased glucagon concentrations, and increased responsiveness of insulin release to glucose, resulting in higher C-peptide and insulin concentrations. The rise in insulin with the decrease in glucagon was associated with lower fasting glucose concentrations and reduced glucose excursion following an oral glucose load or a meal.
In studies with healthy subjects, sitagliptin did not lower blood glucose or cause hypoglycemia. Sitagliptin and Metformin Coadministration In a two-day study in healthy subjects, sitagliptin alone increased active GLP-1 concentrations, whereas metformin alone increased active and total GLP-1 concentrations to similar extents. Coadministration of sitagliptin and metformin had an additive effect on active GLP-1 concentrations.
Sitagliptin, but not metformin, increased active GIP concentrations. It is unclear what these findings mean for changes in glycemic control in patients with type 2 diabetes mellitus. Cardiac Electrophysiology In a randomized, placebo-controlled crossover study, 79 healthy subjects were administered a single oral dose of sitagliptin 100 mg, sitagliptin 800 mg (8 times the recommended dose), and placebo.
At the recommended dose of 100 mg, there was no effect on the QTc interval obtained at the peak plasma concentration, or at any other time during the study. Following the 800-mg dose, the maximum increase in the placebo-corrected mean change in QTc from baseline at 3 hours postdose was 8.0 msec. This increase is not considered to be clinically significant.
At th…
🧬 Mechanism of Action ▾
12.1Mechanism of Action JANUMET XR JANUMET XR tablets combine two antihyperglycemic agents with complementary mechanisms of action to improve glycemic control in adults with type 2 diabetes mellitus: sitagliptin, a dipeptidyl peptidase-4 (DPP-4) inhibitor, and metformin extended-release, a member of the biguanide class. Sitagliptin Sitagliptin is a DPP-4 inhibitor, which exerts its actions in patients with type 2 diabetes by slowing the inactivation of incretin hormones. Concentrations of the active intact hormones are increased by sitagliptin, thereby increasing and prolonging the action of these hormones.
Incretin hormones, including glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP), are released by the intestine throughout the day, and levels are increased in response to a meal. These hormones are rapidly inactivated by the enzyme DPP-4. The incretins are part of an endogenous system involved in the physiologic regulation of glucose homeostasis.
When blood glucose concentrations are normal or elevated, GLP-1 and GIP increase insulin synthesis and release from pancreatic beta cells by intracellular signaling pathways involving cyclic AMP. GLP-1 also lowers glucagon secretion from pancreatic alpha cells, leading to reduced hepatic glucose production. By increasing and prolonging active incretin levels, sitagliptin increases insulin release and decreases glucagon levels in the circulation in a glucose-dependent manner.
Sitagliptin demonstrates selectivity for DPP-4 and does not inhibit DPP-8 or DPP-9 activity in vitro at concentrations approximating those from therapeutic doses. Metformin Metformin is a biguanide that improves glycemic control in patients with type 2 diabetes mellitus, lowering both basal and postprandial plasma glucose. Metformin decreases hepatic glucose production, decreases intestinal absorption of glucose, and improves insulin sensitivity by increasing peripheral glucose uptake and utilization.
With metformin therapy, insulin secretion remains unchanged while fasting insulin levels and day-long plasma insulin response may decrease.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Tablets supplied as follows: Contents Description How Supplied NDC 50 mg sitagliptin and 500 mg metformin HCl extended-release light blue, bi-convex oval, film-coated tablets with “78” debossed on one side unit-of-use bottles of 60 NDC 0006-0078-61 unit-of-use bottles of 180 NDC 0006-0078-62 bulk bottles of 1000 NDC 0006-0078-82 50 mg sitagliptin and 1000 mg metformin HCl extended-release light green, bi-convex oval, film-coated tablets with “80” debossed on one side unit-of-use bottles of 60 NDC 0006-0080-61 unit-of-use bottles of 180 NDC 0006-0080-62 bulk bottles of 1000 NDC 0006-0080-82 100 mg sitagliptin and 1000 mg metformin HCl extended-release blue, bi-convex oval, film-coated tablets with “81” debossed on one side unit-of-use bottles of 30 NDC 0006-0081-31 unit-of-use bottles of 90 NDC 0006-0081-54 bulk bottles of 1000 NDC 0006-0081-82 Store at 20-25°C (68-77°F), excursions permitted to 15-30°C (59-86°F). [See USP Controlled Room Temperature.] Store in a dry place with cap tightly closed.
When container is subdivided, dispense into a USP tightly closed, moisture-resistant container.
📦 Storage and Handling ▾
Store at 20-25°C (68-77°F), excursions permitted to 15-30°C (59-86°F). [See USP Controlled Room Temperature.] Store in a dry place with cap tightly closed. When container is subdivided, dispense into a USP tightly closed, moisture-resistant container.
📋 Description ▾
11 DESCRIPTION JANUMET XR tablets for oral use contain two antihyperglycemic medications: sitagliptin and metformin extended-release. Sitagliptin Sitagliptin is an orally-active inhibitor of the dipeptidyl peptidase-4 (DPP-4) enzyme. Sitagliptin phosphate monohydrate drug substance is used to manufacture JANUMET XR.
Sitagliptin phosphate monohydrate is described chemically as 7-[(3R)-3-amino-1-oxo-4-(2,4,5-trifluorophenyl)butyl]-5,6,7,8-tetrahydro-3-(trifluoromethyl)-1,2,4-triazolo[4,3-α]pyrazine phosphate (1:1) monohydrate with an empirical formula of C 16 H 15 F 6 N 5 O•H 3 PO 4 •H 2 O and a molecular weight of 523.32. The structural formula is: Sitagliptin phosphate monohydrate is a white to off-white, crystalline, non-hygroscopic powder. It is soluble in water and N,N-dimethyl formamide; slightly soluble in methanol; very slightly soluble in ethanol, acetone, and acetonitrile; and insoluble in isopropanol and isopropyl acetate. image of sitagliptin chemical structure Metformin Metformin HCl ( N , N -dimethylimidodicarbonimidic diamide HCl) is a white to off-white crystalline compound with a molecular formula of C 4 H 11 N 5 •HCl and a molecular weight of 165.63.
Metformin HCl is freely soluble in water and is practically insoluble in acetone, ether, and chloroform. The pK a of metformin HCl is 12.4. The pH of a 1% aqueous solution of metformin HCl is 6.68.
The structural formula is as shown: image of metaformin chemical structure JANUMET XR JANUMET XR is available as film-coated tablets containing: 64.25 mg sitagliptin monohydrate equivalent to 50 mg sitagliptin and 389.93 mg of metformin equivalent to 500 mg metformin HCl (JANUMET XR 50/500). 64.25 mg sitagliptin monohydrate equivalent to 50 mg sitagliptin and 779.86 mg of metformin equivalent to 1000 mg metformin HCl (JANUMET XR 50/1000). 128.5 mg sitagliptin monohydrate equivalent to 100 mg sitagliptin and 779.86 mg of metformin equivalent to 1000 mg metformin HCl (JANUMET XR 100/1000).
All doses of JANUMET XR contain the following inactive ingredients: povidone, hypromellose, colloidal silicon dioxide, sodium stearyl fumarate, propyl gallate, polyethylene glycol, and kaolin. The JANUMET XR 50 mg/500 mg tablet contains the additional inactive ingredient microcrystalline cellulose. In addition, the film coating for all doses contains the following inactive ingredients: hypromellose, hydroxypropyl cellulose, titanium dioxide, FD&C #2/Indigo Carmine Aluminum Lake and carnauba wax.
The JANUMET XR 50 mg/1000 mg tablet film coating also contains the inactive ingredient yellow iron oxide.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide ). Lactic Acidosis Explain the risks of lactic acidosis, its symptoms, and conditions that predispose to its development. Advise patients to discontinue JANUMET XR immediately and to promptly notify their healthcare provider if unexplained hyperventilation, myalgias, malaise, unusual somnolence or other nonspecific symptoms occur.
Counsel patients against excessive alcohol intake and inform patients about the importance of regular testing of renal function while receiving JANUMET XR. Instruct patients to inform their doctor that they are taking JANUMET XR prior to any surgical or radiological procedure, as temporary discontinuation may be required [see Warnings and Precautions (5.1) ]. Pancreatitis Inform patients that acute pancreatitis has been reported during postmarketing use of JANUMET XR.
Inform patients that persistent severe abdominal pain, sometimes radiating to the back, which may or may not be accompanied by vomiting, is the hallmark symptom of acute pancreatitis. Instruct patients to promptly discontinue JANUMET XR and contact their physician if persistent severe abdominal pain occurs [see Warnings and Precautions (5.2) ]. Heart Failure Inform patients of the signs and symptoms of heart failure.
Before initiating JANUMET XR, ask patients about a history of heart failure or other risk factors for heart failure including moderate to severe renal impairment. Instruct patients to contact their health care provider as soon as possible if they experience symptoms of heart failure, including increasing shortness of breath, rapid increase in weight or swelling of the feet [see Warnings and Precautions (5.3) ]. Vitamin B 12 Deficiency Inform patients about the importance of regular monitoring of hematological parameters while receiving JANUMET XR [see Warnings and Precautions (5.5) ].
Hypoglycemia Inform patients that the incidence of hypoglycemia is increased when sitagliptin with or without metformin is added to an insulin secretagogue (e.g., sulfonylurea) or insulin therapy. Explain to patients receiving JANUMET XR in combination with these medications the risks of hypoglycemia, its symptoms and treatment and conditions that predispose to its development [see Warnings and Precautions (5.6) ]. Hypersensitivity Reactions Inform patients that allergic reactions have been reported during postmarketing use of sitagliptin, one of the components of JANUMET XR.
If symptoms of allergic reactions (including rash, hives, and swelling of the face, lips, tongue, and throat that may cause difficulty in breathing or swallowing) occur, patients must stop taking JANUMET XR and seek medical advice promptly. Severe and Disabling Arthralgia Inform patients that severe and disabling joint pain may occur with this class of drugs. The time to onset of symptoms can range from one day to years.
Instruct patients to seek medical advice if severe joint pain occurs [see Warnings and Precautions (5.8) ] . Bullous Pemphigoid Inform patients that bullous pemphigoid may occur with this class of drugs. Instruct patients to seek medical advice if blisters or erosions occur [see Warnings and Precautions (5.9) ].
Administration Instructions Inform patients that the tablets must be swallowed whole and never split, crushed or chewed. Incompletely Dissolved Tablets in Feces Inform patients that incompletely dissolved JANUMET XR tablets may be eliminated in the feces. Tell patients that, if they repeatedly see tablets in feces, they should report this finding to their health care provider.
Assess adequacy of glycemic control if a patient reports repeatedly observing tablets in feces. Females of Reproductive Age: Inform females that treatment with JANUMET XR may result in ovulation in some premenopausal anovulatory women which may lead to unintended pregnancy [see Use in Specific Populations (8.3) ] .
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: 8/2026 Medication Guide JANUMET ® XR (JAN-you-met XR) (sitagliptin and metformin hydrochloride extended-release) tablets, for oral use Read this Medication Guide carefully before you start taking JANUMET XR and each time you get a refill.
There may be new information. This information does not take the place of talking with your doctor about your medical condition or your treatment. If you have any questions about JANUMET XR, ask your doctor or pharmacist.
What is the most important information I should know about JANUMET XR? JANUMET XR can cause serious side effects, including: 1. Lactic Acidosis.
Metformin, one of the medicines in JANUMET XR, can cause a rare but serious condition called lactic acidosis (a buildup of an acid in the blood) that can cause death. Lactic acidosis is a medical emergency and must be treated in the hospital. Stop taking JANUMET XR and call your doctor right away if you have any of the following symptoms, which could be signs of lactic acidosis: you feel cold in your hands or feet you feel dizzy or lightheaded you have a slow or irregular heartbeat you feel very weak or tired you have unusual (not normal) muscle pain you have trouble breathing you feel sleepy or drowsy you have stomach pains, nausea or vomiting Most people who have had lactic acidosis with metformin have other things that, combined with the metformin, led to the lactic acidosis.
Tell your doctor if you have any of the following, because you have a higher chance for getting lactic acidosis with JANUMET XR if you: have severe kidney problems or your kidneys are affected by certain x-ray tests that use injectable dye have liver problems drink alcohol very often, or drink a lot of alcohol in short-term "binge" drinking get dehydrated (lose a large amount of body fluids). This can happen if you are sick with a fever, vomiting, or diarrhea. Dehydration can also happen when you sweat a lot with activity or exercise and do not drink enough fluids. have surgery have a heart attack, severe infection, or stroke are 65 years of age or older have a genetically inherited disease affecting mitochondria (the energy-producing parts within cells) such as mitochondrial encephalomyopathy with lactic acidosis, and stroke-like episodes (MELAS) syndrome and maternally inherited diabetes and deafness (MIDD) The best way to keep from having a problem with lactic acidosis from metformin is to tell your doctor if you have any of the problems in the list above.
Your doctor may decide to stop your JANUMET XR for a while if you have any of these things. JANUMET XR can have other serious side effects. See " What are the possible side effects of JANUMET XR? " 2.
Pancreatitis (inflammation of the pancreas) which may be severe and lead to death. Certain medical problems make you more likely to get pancreatitis. Before you start taking JANUMET XR, tell your doctor if you have ever had: pancreatitis stones in your gallbladder (gallstones) a history of alcoholism high blood triglyceride levels Stop taking JANUMET XR and call your doctor right away if you have pain in your stomach area (abdomen) that is severe and will not go away.
The pain may be felt going from your abdomen through to your back. The pain may happen with or without vomiting. These may be symptoms of pancreatitis.
3. Heart failure . Heart failure means that your heart does not pump blood well enough.
Before you start taking JANUMET XR, tell your doctor if you have ever had heart failure or have problems with your kidneys. Contact your doctor right away if you have any of the following symptoms: increasing shortness of breath or trouble breathing, especially when you lie down swelling or fluid retention, especially in the feet, ankles or legs an unusually fast increase in weight unusual tiredness These may be symptoms of heart failure. What is JANUMET XR?
JANUMET XR is a prescription medicine that contains 2 prescr…