
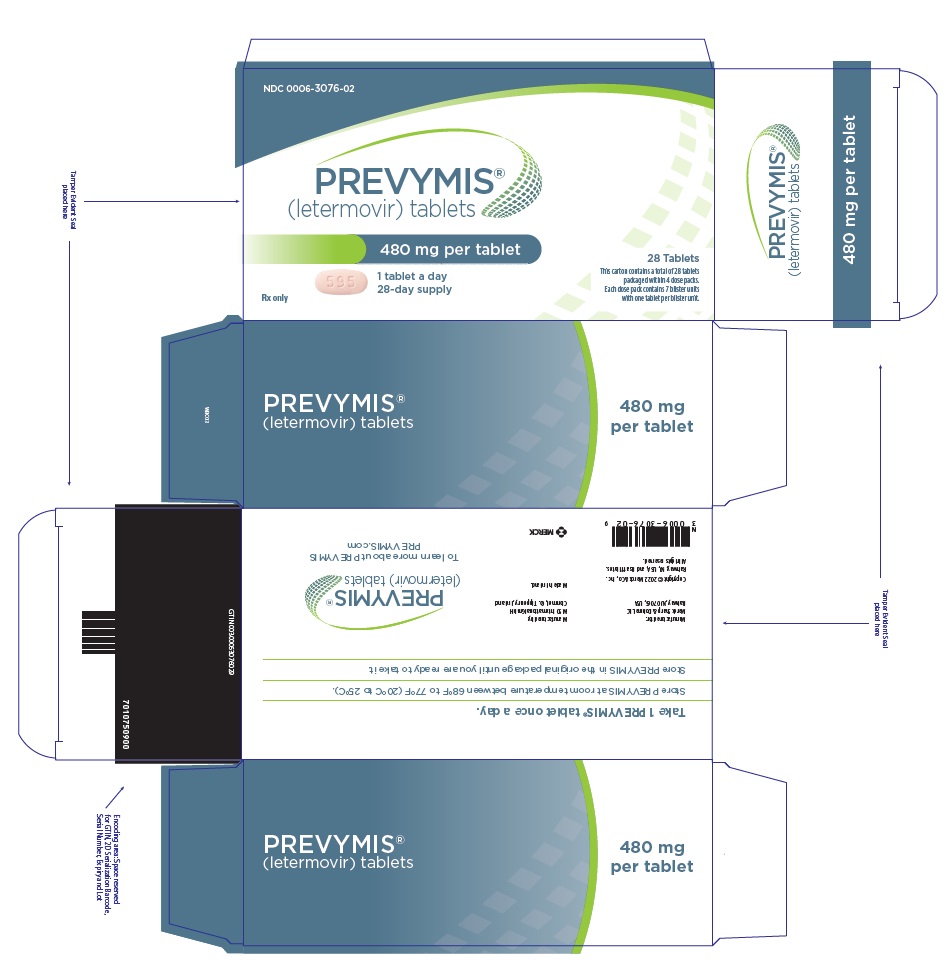
PREVYMIS LETERMOVIR 480 mg Tablet, Film Coated
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Cytomegalovirus DNA Terminase Complex Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Letermovir is used to help prevent cytomegalovirus (CMV) infection and disease in certain people who have received a hematopoietic stem-cell transplant (HSCT; a procedure that replaces diseased bone marrow with healthy bone marrow) and are at increased risk of developing a CMV infection. Letermovir is also used to help prevent CMV infection and disease in certain people who have received a kidney transplant and are at increased risk of developing a CMV infection. Letermovir is in a class of medications called antivirals. It works by slowing the growth of CMV.
Read the full MedlinePlus article ↗- Prevymis is an antiviral used to prevent a virus called CMV (cytomegalovirus) from becoming active and causing serious illness after your transplant. CMV is a very common virus tha...
- What exactly is this medication for? Why was I given it after my transplant?
- Good news — you can take the Prevymis tablet with or without food, whichever is easier for you. Just make sure to swallow the tablet whole and don't crush it. If you've been given...
- Can I take the tablet with food, or do I need to take it on an empty stomach?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII R12CBM0EIZ
A natural wax derived from a Brazilian palm tree, used as a coating and polish on tablets and capsules. It creates a smooth, shiny finish that protects the medicine and improves appearance.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 36SFW2JZ0W
Hypromellose 2910 is a plant-based thickening agent derived from cellulose. In medicines, it forms a protective coating on tablets or capsules and controls how quickly the drug dissolves and releases into your body.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII K0KQV10C35
Povidone K25 is a synthetic polymer made from vinyl pyrrolidone. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach for better absorption.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $270.78 | $7,581.73 / 28 tablets |
| Medicare drug plans payPart D · Q2 2026 | $268.47 | $7,517.12 / 28 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Prevymis 480 mgthis 00006-3076-02 | Merck | 7 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US RE46791 ↗ | Drug substance | — | Jan 18, 2029 |
| US RE46791 ↗ | Drug substance | — | Jan 18, 2029 |
| Code | What it grants | Expires |
|---|---|---|
| D-189 | Other change requiring clinical data (3-year) | Aug 2, 2026 |
| I-916 | New indication (3-year) | Jun 5, 2026 |
| NPP | New Patient Population | Aug 30, 2027 |
| ODE-423 | Orphan Drug Exclusivity (7-year) | Jun 5, 2030 |
| ODE-495 | Orphan Drug Exclusivity (7-year) | Aug 30, 2031 |
| ODE-497 | Orphan Drug Exclusivity (7-year) | Aug 30, 2031 |
| D-189 | Other change requiring clinical data (3-year) | Aug 2, 2026 |
| I-916 | New indication (3-year) | Jun 5, 2026 |
| NPP | New Patient Population | Aug 30, 2027 |
| ODE-423 | Orphan Drug Exclusivity (7-year) | Jun 5, 2030 |
| ODE-495 | Orphan Drug Exclusivity (7-year) | Aug 30, 2031 |
| ODE-497 | Orphan Drug Exclusivity (7-year) | Aug 30, 2031 |
Is there a generic version of PREVYMIS 480 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00006-3076-02 You're viewing this | 4 DOSE PACK in 1 CARTON (0006-3076-02) / 7 TABLET, FILM COATED in 1 DOSE PACK (0006-3076-01) | 2017-11-08 | Active |
| 00006-3076-04 | 14 BLISTER PACK in 1 CARTON (0006-3076-04) / 1 TABLET, FILM COATED in 1 BLISTER PACK (0006-3076-03) | 2017-11-08 | Active |
In Medicaid, this is the most-dispensed pack of this product — about 92% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 00006-3076-02?
What NDC number is used to bill for this package of PREVYMIS LETERMOVIR 480 mg Tablet, Film Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE PREVYMIS is a CMV DNA terminase complex inhibitor indicated for: Prophylaxis of cytomegalovirus (CMV) infection and disease in adult and pediatric patients 6 months of age and older and weighing at least 6 kg who are CMV-seropositive recipients [R+] of an allogeneic hematopoietic stem cell transplant (HSCT). ( 1.1 ) Prophylaxis of CMV disease in adult and pediatric patients 12 years of age and older and weighing at least 40 kg who are kidney transplant recipients at high risk (Donor CMV seropositive/Recipient CMV seronegative [D+/R-]).
( 1.2 )
1.1CMV Prophylaxis in Hematopoietic Stem Cell Transplant (HSCT) Recipients PREVYMIS ® is indicated for prophylaxis of cytomegalovirus (CMV) infection and disease in adult and pediatric patients 6 months of age and older and weighing at least 6 kg who are CMV-seropositive recipients [R+] of an allogeneic hematopoietic stem cell transplant (HSCT).
1.2CMV Prophylaxis in Kidney Transplant Recipients PREVYMIS is indicated for prophylaxis of CMV disease in adult and pediatric patients 12 years of age and older and weighing at least 40 kg who are kidney transplant recipients at high risk (Donor CMV seropositive/Recipient CMV seronegative [D+/R-]).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Adult and Pediatric Patients 12 Years of Age and Older and Weighing at least 30 kg Who Are HSCT Recipients or Adult and Pediatric Patients 12 Years of Age and Older and Weighing at least 40 kg Who Are Kidney Transplant Recipients: HSCT : 480 mg administered once daily orally or as an intravenous (IV) infusion over 1 hour through 100 days post-HSCT. In patients at risk for late CMV infection and disease, PREVYMIS may be continued through 200 days post-HSCT. ( 2.1 , 2.3 ) Kidney Transplant : 480 mg administered once daily orally or as an IV infusion over 1 hour through 200 days post-transplant.
( 2.1 , 2.3 ) Pediatric Patients 6 Months to Less than 12 Years of Age or 12 Years of Age and Older and Weighing Less than 30 kg Who Are HSCT Recipients: HSCT : Dosing based on weight administered once daily orally or as an IV infusion over 1 hour through 100 days post-HSCT. In patients at risk for late CMV infection and disease, PREVYMIS may be continued through 200 days post-HSCT. ( 2.1 , 2.5 ) PREVYMIS injection must be diluted prior to administration.
( 2.1 ) PREVYMIS injection must be administered through a sterile 0.2 micron or 0.22 micron polyethersulfone (PES) in-line filter. ( 2.1 , 2.10 ) Following the completion of PREVYMIS prophylaxis, monitoring for CMV reactivation in HSCT recipients is recommended. ( 2.2 ) Dosage Adjustment: If PREVYMIS is co-administered with cyclosporine, the dosage of PREVYMIS should be decreased to 240 mg once daily in adult and pediatric patients 12 years of age and older.
( 2.4 ) If PREVYMIS is co-administered with cyclosporine in pediatric patients less than 12 years of age, dose adjustment may be required. ( 2.6 ) Instructions for Use should be followed for preparation and administration of PREVYMIS oral pellets. ( 2.9 ) Do not use PREVYMIS injection with IV bags and infusion set materials containing the plasticizer diethylhexyl phthalate (DEHP).
( 2.10 , 2.13 )
2.1Important Dosing and Administration Information PREVYMIS is available in 3 dosage forms: PREVYMIS Tablets - Administer orally with or without food. - Swallow tablets whole. PREVYMIS Oral Pellets - Administer orally mixed with soft food or via nasogastric tube (NG tube) or gastric tube (G tube) [see Dosage and Administration (2.9) ] . - Do not crush or chew. PREVYMIS Injection - PREVYMIS injection must be diluted prior to administration. - Administer PREVYMIS through a sterile 0.2 micron or 0.22 micron polyethersulfone (PES) in-line filter. - Administer by intravenous infusion via a peripheral catheter or central venous line at a constant rate over 1 hour. - Do not administer as an intravenous bolus injection. - PREVYMIS injection, which contains hydroxypropyl betadex, should be used only in patients unable to take oral therapy.
Patients should be switched to oral PREVYMIS as soon as they are able to take oral medications. If possible, intravenous administration should not exceed 4 weeks [see Warnings and Precautions (5.2) ] . No dosage adjustment is necessary when switching formulations in adult and pediatric patients 12 years of age and older [see Dosage and Administration (2.3) ] .
Dosage adjustment may be necessary for pediatric patients less than 12 years of age when switching between oral and intravenous formulations (see Table 1 and Table 2 ) [see Dosage and Administration (2.5) ] .
2.2Patient Monitoring Following the completion of PREVYMIS prophylaxis, monitoring for CMV reactivation in HSCT recipients is recommended [see Clinical Studies (14.2) ] .
2.3Recommended Dosage for Adult and Pediatric Patients 12 Years of Age and Older Who Are HSCT or Kidney Transplant Recipients HSCT: Adult and Pediatric Patients 12 Years of Age and Older and Weighing at least 30 kg The recommended dosage of PREVYMIS is 480 mg administered orally or intravenously once daily. When PREVYMIS is administered orally, the recommended dosage is one 480 mg tablet once daily or two 240 mg tablets once daily. Four 120 mg packets of o…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablet: 240 mg; 480 mg ( 3 ) Oral Pellets: 20 mg or 120 mg per packet ( 3 ) Injection: 240 mg/12 mL (20 mg/mL) or 480 mg/24 mL (20 mg/mL) in a single-dose vial ( 3 ) Tablets PREVYMIS 240 mg tablet: yellow oval tablet with "591" on one side and corporate logo on the other side. PREVYMIS 480 mg tablet: pink oval, bi-convex tablet with "595" on one side and corporate logo on the other side. Oral Pellets PREVYMIS oral pellets: beige round pellets in packets.
Each packet contains 20 mg letermovir. PREVYMIS oral pellets: beige round pellets in packets. Each packet contains 120 mg letermovir.
Injection PREVYMIS 240 mg/12 mL (20 mg/mL) injection: clear and colorless solution in a single-dose vial. PREVYMIS 480 mg/24 mL (20 mg/mL) injection: clear and colorless solution in a single-dose vial.
⛔ Contraindications ▾
4 CONTRAINDICATIONS PREVYMIS is contraindicated in patients receiving pimozide or ergot alkaloids: Pimozide: Concomitant administration of PREVYMIS in patients receiving pimozide may result in increased concentrations of pimozide due to inhibition of cytochrome P450 3A (CYP3A) by letermovir, which may lead to QT prolongation and torsades de pointes [see Warnings and Precautions (5.1) and Drug Interactions (7.2 , 7.3) ] . Ergot alkaloids: Concomitant administration of PREVYMIS in patients receiving ergot alkaloids may result in increased concentrations of ergot alkaloids (ergotamine and dihydroergotamine) due to inhibition of CYP3A by letermovir, which may lead to ergotism [see Warnings and Precautions (5.1) and Drug Interactions (7.2 , 7.3) ] .
PREVYMIS is contraindicated with pitavastatin and simvastatin when co-administered with cyclosporine. Concomitant administration of PREVYMIS in combination with cyclosporine may result in significantly increased pitavastatin or simvastatin concentrations, which may lead to myopathy or rhabdomyolysis [see Warnings and Precautions (5.1) and Drug Interactions (7.2 , 7.3) ] . PREVYMIS is contraindicated with: Pimozide.
( 4 ) Ergot Alkaloids. ( 4 ) Pitavastatin and simvastatin when co-administered with cyclosporine. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Risk of Adverse Reactions or Reduced Therapeutic Effect Due to Drug Interactions: The concomitant use of PREVYMIS with certain drugs may result in potentially significant drug interactions, some of which may lead to adverse reactions (PREVYMIS or concomitant drugs) or reduced therapeutic effect of PREVYMIS or the concomitant drug. Consult the full prescribing information for contraindications and dosage recommendations for concomitant drugs. ( 4 , 5.1 , 7.1 , 7.2 , 7.3 ) Risks Associated with Hydroxypropyl Betadex Excipient in Intravenous Formulation: Intravenous formulation of PREVYMIS contains the excipient hydroxypropyl betadex.
PREVYMIS injection should be used only in patients unable to take oral therapy. If possible, intravenous administration should not exceed 4 weeks. In patients with renal impairment, accumulation of hydroxypropyl betadex may occur.
Animal studies have shown the potential for hydroxypropyl betadex to cause ototoxicity. ( 5.2 , 8.6 , 13.2 )
5.1Risk of Adverse Reactions or Reduced Therapeutic Effect Due to Drug Interactions The concomitant use of PREVYMIS and certain drugs may result in potentially significant drug interactions, some of which may lead to adverse reactions (PREVYMIS or concomitant drugs) or reduced therapeutic effect of PREVYMIS or the concomitant drug [see Contraindications (4) and Drug Interactions (7.1 , 7.2 , 7.3) ] . See Table 11 for steps to prevent or manage these possible or known significant drug interactions, including dosing recommendations.
Consider the potential for drug interactions prior to and during PREVYMIS therapy; review concomitant medications during PREVYMIS therapy; and monitor for adverse reactions associated with PREVYMIS and concomitant medications.
5.2Risks Associated with Hydroxypropyl Betadex Excipient in Intravenous Formulation Intravenous formulation of PREVYMIS contains the excipient hydroxypropyl betadex. PREVYMIS injection should be used only in patients unable to take oral therapy and patients should be switched to oral PREVYMIS as soon as they are able to take oral medications. If possible, intravenous administration should not exceed 4 weeks [see Dosage and Administration (2.1) ].
In patients with renal impairment, accumulation of hydroxypropyl betadex may occur. In adult patients with CLcr less than 50 mL/min and in pediatric patients with a similar degree of renal impairment (based on age-appropriate assessment of renal function) receiving PREVYMIS injection, closely monitor serum creatinine levels [see Dosage and Administration (2.7) and Use in Specific Populations (8.6) ] . Animal studies have shown the potential for hydroxypropyl betadex to cause ototoxicity [see Nonclinical Toxicology (13.2) ].
The active ingredient, letermovir, is not known to be associated with ototoxicity.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Adult HSCT Patients: Most common adverse events (occurring in at least 10% of subjects in the PREVYMIS group and at a frequency at least 2% greater than placebo) are nausea, diarrhea, vomiting, peripheral edema, cough, headache, fatigue, and abdominal pain. ( 6.1 ) Adult Kidney Transplant Patients: Most common adverse event (occurring in at least 10% of subjects in the PREVYMIS group and at a frequency greater than valganciclovir) is diarrhea. ( 6.1 ) Pediatric Patients: Adverse events in pediatric patients are similar to adults.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Merck Sharp & Dohme LLC at 1-877-888-4231 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adult CMV-seropositive Recipients [R+] of an Allogeneic HSCT Prophylaxis Through Week 14 (~100 days) Post-HSCT The safety of PREVYMIS was evaluated in a Phase 3 randomized, double-blind, placebo-controlled trial (P001) in which 565 subjects were randomized and treated with PREVYMIS (N=373) or placebo (N=192) through Week 14 post-HSCT.
Adverse events were those reported while subjects were on study medication or within two weeks of study medication completion/discontinuation. The mean time for reporting adverse events and laboratory abnormalities was approximately 22% longer in the PREVYMIS arm compared to the placebo arm. Cardiac Adverse Events The cardiac adverse event rate was higher in subjects receiving PREVYMIS (13%) compared to subjects receiving placebo (6%).
The most common cardiac adverse events were tachycardia (reported in 4% of PREVYMIS subjects and in 2% of placebo subjects) and atrial fibrillation (reported in 3% of PREVYMIS subjects and in 1% of placebo subjects). Among those subjects who experienced one or more cardiac adverse events, 85% of PREVYMIS and 92% of placebo subjects had events reported as mild or moderate in severity. Common Adverse Events The rate of adverse events occurring in at least 10% of subjects in the PREVYMIS group and at a frequency at least 2% greater than placebo are outlined in Table 8.
Table 8: Trial P001 All Grade Adverse Events Reported in ≥ 10% of PREVYMIS-Treated HSCT Recipients at a Frequency at least 2% Greater than Placebo Adverse Events PREVYMIS (N=373) Placebo (N=192) nausea 27% 23% diarrhea 26% 24% vomiting 19% 14% peripheral edema 14% 9% cough 14% 10% headache 14% 9% fatigue 13% 11% abdominal pain 12% 9% Overall, similar proportions of subjects in each group discontinued study medication due to an adverse event (13% of PREVYMIS subjects vs. 12% of placebo subjects). The most frequently reported adverse event that led to study drug discontinuation was nausea, occurring in 2% of PREVYMIS subjects and 1% of placebo subjects.
Hypersensitivity reaction, with associated moderate dyspnea, occurred in one subject following the first infusion of IV PREVYMIS after switching from oral PREVYMIS, leading to treatment discontinuation. Laboratory Abnormalities Selected laboratory abnormalities reported during treatment or within 2 weeks of stopping treatment are presented in Table 9. Table 9: Trial P001 Selected Laboratory Abnormalities PREVYMIS N=373 Placebo N=192 Absolute neutrophil count (cells/μL) < 500 19% 19% 500 – < 750 4% 7% 750 – < 1000 8% 9% Hemoglobin (g/dL) < 6.5 2% 1% 6.5 – < 8.0 14% 15% 8.0 – < 9.5 41% 43% Platelets (cells/μL) < 25000 27% 21% 25000 – < 50000 17% 18% 50000 – < 100000 20% 30% Serum creatinine (mg/dL) > 2.5 2% 3% > 1.5 – 2.5 17% 20% The median time to engraftment (defined as absolute neutrophil count ≥ 500/mm 3 on 3 consecutive days after transplantation) was 19 days in the PREVYMIS group and 18 days in the placebo group.
Prophylaxis From Week 14 (~100 days) Through Week 28 (~200 d…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Dosage Adjustment: If PREVYMIS is co-administered with cyclosporine, the dosage of PREVYMIS should be decreased to 240 mg once daily in adult and pediatric patients 12 years of age and older. ( 2.4 ) If PREVYMIS is co-administered with cyclosporine in pediatric patients less than 12 years of age, dose adjustment may be required. ( 2.6 ) Co-administration of PREVYMIS may alter the plasma concentrations of other drugs and other drugs may alter the plasma concentrations of PREVYMIS.
Consult the full prescribing information prior to and during treatment for potential drug interactions. ( 2.4 , 2.6 , 4 , 5.1 , 7.1 , 7.2 , 7.3 , 7.4 , 12.3 )
7.1Potential for Other Drugs to Affect PREVYMIS Letermovir is a substrate of organic anion-transporting polypeptide 1B1/3 (OATP1B1/3) and P-glycoprotein (P-gp) transporters and UDP-glucuronosyltransferase 1A1/3 (UGT1A1/3) enzymes. Co-administration of PREVYMIS with drugs that are inhibitors of OATP1B1/3 transporters may result in increases in letermovir plasma concentrations (Table 11). Co-administration of PREVYMIS with inducers of transporters (e.g., P-gp) and/or enzymes (e.g., UGTs) is not recommended due to the potential for a decrease in letermovir plasma concentrations (see Table 11 ) .
7.2Potential for PREVYMIS to Affect Other Drugs Co-administration of PREVYMIS with midazolam results in increased midazolam plasma concentrations, indicating that letermovir is a moderate inhibitor of CYP3A [see Clinical Pharmacology (12.3) ] . Co-administration of PREVYMIS with drugs that are CYP3A substrates may result in clinically relevant increases in the plasma concentrations of co-administered CYP3A substrates (Table 11) [see Contraindications (4) and Warnings and Precautions (5.1) ] . Letermovir is an inhibitor of OATP1B1/3 transporters.
Co-administration of PREVYMIS with drugs that are substrates of OATP1B1/3 transporters may result in a clinically relevant increase in plasma concentrations of co-administered OATP1B1/3 substrates (Table 11). The magnitude of CYP3A- and OATP1B1/3-mediated drug interactions on co-administered drugs may be different when PREVYMIS is co-administered with cyclosporine. See the prescribing information for cyclosporine for information on drug interactions with cyclosporine.
7.3Established and Other Potentially Significant Drug Interactions If dose adjustments of concomitant medications are made due to treatment with PREVYMIS, doses should be readjusted after treatment with PREVYMIS is completed. Table 11 provides a listing of established or potentially clinically significant drug interactions. The drug interactions described are based on adult studies conducted with PREVYMIS or are predicted drug interactions that may occur with PREVYMIS [see Contraindications (4) , Warnings and Precautions (5.1) , and Clinical Pharmacology (12.3) ] .
Table 11: Potentially Significant Drug Interactions: Alteration in Dose May Be Recommended Based on Results from Adult Drug Interaction Studies or Predicted Interactions This table is not all inclusive. (Information in the Table Applies to Co-administration of PREVYMIS and the Concomitant Drug without Cyclosporine, Unless Otherwise Indicated) Concomitant Drug Class and/or Clearance Pathway: Drug Name Effect on Concentration ↓ =decrease, ↑ =increase Clinical Comments Anti-arrhythmic Agents amiodarone ↑ amiodarone Close clinical monitoring for adverse events related to amiodarone is recommended during co-administration.
Frequently monitor amiodarone concentrations when amiodarone is co-administered with PREVYMIS. Antibiotics nafcillin ↓ letermovir Co-administration of PREVYMIS and nafcillin is not recommended due to potential for loss of efficacy of PREVYMIS. Anticoagulants warfarin ↓ warfarin When PREVYMIS is co-administered with warfarin, frequently monitor International Normalized Ratio (INR) Refer to the respective prescribing information. .
Anticonvulsants carbamazepine ↓ letermovir Co-administration of PREVYMIS and…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Renal Impairment: Closely monitor serum creatinine levels in patients with CLcr less than 50 mL/min using PREVYMIS injection. ( 8.6 ) Hepatic Impairment: PREVYMIS is not recommended for patients with severe (Child-Pugh C) hepatic impairment. ( 8.7 )
8.1Pregnancy Risk Summary No adequate human data are available to establish whether PREVYMIS poses a risk to pregnancy outcomes. In animal reproduction studies, embryo-fetal developmental toxicity (including fetal malformations) was observed in rats during the period of organogenesis at letermovir exposures (AUC) 11 times higher than human exposure at the recommended human dose (RHD). In rabbits, no embryo-fetal developmental toxicity was noted at exposures that were not maternally toxic (up to letermovir exposures 2 times higher than human exposure at the RHD).
In a rat pre/post-natal development study, total litter loss was observed at maternal letermovir exposures approximately 2 times higher than human exposure at the RHD (see Data ) . The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Data Animal Data Letermovir was administered orally to pregnant rats at 0, 10, 50 or 250 mg/kg/day from gestation days 6 to 17. Developmental toxicities, including skeletal malformations and umbilical cord shortening, were observed at 250 mg/kg/day (approximately 11 times higher than human exposure at the RHD). In addition, decreased fetal body weight and skeletal variations (due to maternal toxicity) were observed at this dose.
No embryo-fetal toxicities were observed at 50 mg/kg/day (approximately 3 times higher than human exposure at the RHD). Letermovir was administered orally to pregnant rabbits at 0, 25, 75 or 225 mg/kg/day from gestation days 6 to 20. Developmental toxicities, including spontaneous abortion, increased post-implantation loss, and skeletal variations, were observed at a maternally toxic dose (225 mg/kg/day; approximately 2 times higher than human exposure at the RHD).
No embryo-fetal toxicities were observed at 75 mg/kg/day (less than human exposure at the RHD). In the pre/post-natal development study, letermovir was administered orally to pregnant rats at 0, 10, 45 or 180 mg/kg/day from gestation day 6 to lactation day 22. At 180 mg/kg/day (approximately 2 times higher than human exposure at the RHD), total litter loss due to stillbirth or possible maternal neglect was observed in 5 of 23 pregnant females by post-partum/lactation day 4.
In surviving offspring, slight developmental delays in vaginal opening and pinna unfolding were accompanied by reduced body weight gain at this dose. No toxicities were observed at 45 mg/kg/day (similar to human exposure at the RHD).
8.2Lactation Risk Summary It is not known whether letermovir is present in human breast milk, affects human milk production, or has effects on the breastfed child. When administered to lactating rats, letermovir was present in the milk of lactating rats as well as the blood of nursing pups (see Data ) . The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for PREVYMIS and any potential adverse effects on the breastfed child from PREVYMIS or from the underlying maternal condition.
Data In a lactation study, letermovir was excreted in milk when administered intravenously (at 10 mg/kg) to lactating rats on post-partum/lactation day 10. Letermovir was also detected in the blood of nursing pups on post-partum/lactation day 21 in the pre/post-natal developmental study.
8.3Females and Males of Reproductive Potential Infertility There are no data on the effect of letermovir on human fertility. Decreased fertility due to testicular toxicity was observed in male rats [see Nonclinical Toxicology (13.1 , 13.2) ] .…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary No adequate human data are available to establish whether PREVYMIS poses a risk to pregnancy outcomes. In animal reproduction studies, embryo-fetal developmental toxicity (including fetal malformations) was observed in rats during the period of organogenesis at letermovir exposures (AUC) 11 times higher than human exposure at the recommended human dose (RHD). In rabbits, no embryo-fetal developmental toxicity was noted at exposures that were not maternally toxic (up to letermovir exposures 2 times higher than human exposure at the RHD).
In a rat pre/post-natal development study, total litter loss was observed at maternal letermovir exposures approximately 2 times higher than human exposure at the RHD (see Data ) . The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Data Animal Data Letermovir was administered orally to pregnant rats at 0, 10, 50 or 250 mg/kg/day from gestation days 6 to 17. Developmental toxicities, including skeletal malformations and umbilical cord shortening, were observed at 250 mg/kg/day (approximately 11 times higher than human exposure at the RHD). In addition, decreased fetal body weight and skeletal variations (due to maternal toxicity) were observed at this dose.
No embryo-fetal toxicities were observed at 50 mg/kg/day (approximately 3 times higher than human exposure at the RHD). Letermovir was administered orally to pregnant rabbits at 0, 25, 75 or 225 mg/kg/day from gestation days 6 to 20. Developmental toxicities, including spontaneous abortion, increased post-implantation loss, and skeletal variations, were observed at a maternally toxic dose (225 mg/kg/day; approximately 2 times higher than human exposure at the RHD).
No embryo-fetal toxicities were observed at 75 mg/kg/day (less than human exposure at the RHD). In the pre/post-natal development study, letermovir was administered orally to pregnant rats at 0, 10, 45 or 180 mg/kg/day from gestation day 6 to lactation day 22. At 180 mg/kg/day (approximately 2 times higher than human exposure at the RHD), total litter loss due to stillbirth or possible maternal neglect was observed in 5 of 23 pregnant females by post-partum/lactation day 4.
In surviving offspring, slight developmental delays in vaginal opening and pinna unfolding were accompanied by reduced body weight gain at this dose. No toxicities were observed at 45 mg/kg/day (similar to human exposure at the RHD).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of PREVYMIS have been established for: Prophylaxis of CMV infection and disease in pediatric CMV-seropositive recipients of an allogeneic HSCT 6 months of age and older and weighing at least 6 kg, and Prophylaxis of CMV disease in pediatric kidney transplant recipients 12 years of age and older and weighing at least 40 kg who are at high risk [D+/R-]. HSCT Recipients: The use of PREVYMIS for prophylaxis of CMV infection and disease in pediatric recipients of an allogeneic HSCT is supported by evidence from adequate and well-controlled studies in adults with additional pharmacokinetic and safety data from pediatric patients in Trial P030.
The safety and pharmacokinetic results were similar to those in adults [see Warnings and Precautions (5.2) , Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , Clinical studies (14.2 , 14.4) ]. Kidney Transplant Recipients: The use of PREVYMIS for prophylaxis of CMV disease in high-risk [D+/R-] kidney transplant recipients 12 years of age and older and weighing at least 40 kg is supported by evidence from an adequate and well-controlled study in adults and safety data from pediatric HSCT recipients (Trial P030).
Letermovir exposures are expected to be similar between adult and pediatric patients 12 years of age and older and weighing at least 40 kg [see Warnings and Precautions (5.2) , Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , Clinical studies (14.3 , 14.4) ]. The safety and effectiveness of PREVYMIS have not been established for: HSCT recipients less than 6 months of age or weighing less than 6 kg, or Kidney transplant recipients less than 12 years of age or weighing less than 40 kg.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 373 subjects treated with PREVYMIS in Trial P001, 56 (15%) subjects were 65 years of age or older. Of the 144 subjects treated with PREVYMIS in Trial P040, 32 (22%) subjects were 65 years of age or older. Of the 292 subjects treated with PREVYMIS in Trial P002, 48 (16%) subjects were 65 years of age or older.
Safety and efficacy were similar across older and younger subjects in each trial. No dosage adjustment of PREVYMIS is required based on age [see Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE There is no specific antidote for overdose with PREVYMIS. In case of overdose, it is recommended that the patient be monitored for adverse reactions and appropriate symptomatic treatment be instituted. It is unknown whether dialysis will result in meaningful removal of PREVYMIS from systemic circulation.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action PREVYMIS is an antiviral drug against CMV [see Microbiology (12.4) ] .
12.2Pharmacodynamics Cardiac Electrophysiology In a thorough QT trial in healthy adult subjects, letermovir at the therapeutic IV dose or at a dose of 2 times the approved IV dose did not prolong QTc to any clinically relevant extent.
12.3Pharmacokinetics The pharmacokinetic properties of letermovir are displayed in Table 12. Table 12: Absorption, Distribution, Metabolism, Elimination (ADME), and Pharmacokinetic Properties of PREVYMIS Values were obtained in studies of healthy adult subjects unless otherwise indicated. Pharmacokinetics in Adult HSCT Recipients Treatment Regimen Steady-state median (90% prediction interval) AUC (ng∙hr/mL) of PREVYMIS 480 mg oral once daily, no cyclosporine 34,400 (16,900, 73,700) 480 mg IV once daily, no cyclosporine 100,000 (65,300, 148,000) 240 mg oral once daily, with cyclosporine 60,800 (28,700, 122,000) 240 mg IV once daily, with cyclosporine 70,300 (46,200, 106,000) Pharmacokinetics in Adult Kidney Transplant Recipients Treatment Regimen Steady-state median (90% prediction interval) AUC (ng∙hr/mL) of PREVYMIS 480 mg oral once daily, no cyclosporine 62,700 (17,500, 139,000) 240 mg oral once daily, with cyclosporine 71,900 (42,400, 125,000) Pharmacokinetics in Adult Healthy Subjects Treatment Regimen Steady-state geometric mean AUC and Cmax of PREVYMIS 480 mg oral once daily Cmax: 13,000 ng/mL AUC: 71,500 ng•hr/mL Dose proportionality Greater than proportional following single and multiple oral or IV doses of PREVYMIS 240 mg and 480 mg Accumulation ratio Based on geometric mean data.
Cmax:
1.03 AUC:
1.22Time to steady-state 9-10 days Absorption Bioavailability Healthy adult subjects administered PREVYMIS without cyclosporine: 94% at an oral dose range of 240 mg to 480 mg Adult HSCT recipients administered PREVYMIS without cyclosporine: 35% with 480 mg oral once daily Adult HSCT recipients administered PREVYMIS with cyclosporine: 85% with 240 mg oral once daily Adult kidney transplant recipients administered PREVYMIS without cyclosporine: 56% 95% CI (46%, 65%) with 480 mg oral once daily Median Tmax (hr) 1.5 to 3.0 hr Effect of food (relative to fasting) Values refer to geometric mean ratio [fed/fasted] percentage and 90% confidence interval back transformed from linear mixed-effects model performed on natural log-transformed values.
The meal administered was a standard high fat and high calorie meal (33 grams protein, 65 grams carbohydrates, 58 grams fat; 920 total calories). AUC: 99.63% [84.27% - 117.80%] Cmax: 129.82% [104.35% -161.50%] Oral pellets versus tablet (fasting) AUC and Cmax values were comparable when comparing PREVYMIS tablet (240 mg) and PREVYMIS oral pellets (2 X 120 mg) Distribution Mean steady-state volume of distribution
45.5L following IV administration in adult HSCT recipients % In vitro bound to human plasma proteins 99% across the concentration range of 0.2 to 50 mg/L In vitro blood-to plasma ratio 0.56 across the concentration range of 0.1 to 10 mg/L Metabolism In vitro metabolism UGT1A1/1A3 (minor) Drug-related component in plasma 97% unchanged parent No major metabolites detected in plasma Elimination Route of elimination Hepatic uptake (OATP1B1/3) Mean terminal t 1/2 (hr) 12 hrs after dosing of PREVYMIS 480 mg IV once daily % of dose excreted in feces Single oral administration of radiolabeled letermovir in mass balance study.
93% % of dose excreted in urine <2% % of unchanged drug excreted in feces 70% Specific Populations Pediatric Patients Letermovir AUC in pediatric HSCT recipients was estimated using population pharmacokinetic analysis using Trial P030 data (see Table 13 and Table 14 ). Exposures for pediatric HSCT recipients for body weight bands 6 kg and above are within the range of exposures observed at the recommended doses of PREVYMIS in adults (see Table 12 ). Table 13: PREVYMIS AUC (ng•hr/mL) Values Following Once Daily Oral Ad…
🧬 Mechanism of Action ▾
12.1Mechanism of Action PREVYMIS is an antiviral drug against CMV [see Microbiology (12.4) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Tablets: Each PREVYMIS 240 mg tablet is a yellow oval tablet; each tablet is debossed with "591" on one side and corporate logo on the other side. Each PREVYMIS 480 mg tablet is a pink oval, bi-convex tablet debossed with "595" on one side and corporate logo on the other side. The 240 mg tablets are packaged into a carton (NDC 0006-3075-02) containing four (4) Child Resistant (CR) Dosepaks®, each containing a 7-count blister card for a total of 28 tablets, or into a carton (NDC 0006-3075-04) containing two (2) unit-dose 7-count blister cards for a total of 14 tablets.
The 480 mg tablets are packaged into a carton (NDC 0006-3076-02) containing four (4) Child Resistant (CR) Dosepaks®, each containing a 7-count blister card for a total of 28 tablets, or into a carton (NDC 0006-3076-04) containing two (2) unit-dose 7-count blister cards for a total of 14 tablets. Store PREVYMIS tablets in the original package until use to protect from moisture. Store PREVYMIS tablets at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Oral Pellets: PREVYMIS oral pellets are supplied as beige round pellets in packets. Each packet contains 20 mg of letermovir. PREVYMIS oral pellets are supplied as beige round pellets in packets.
Each packet contains 120 mg of letermovir. The 20 mg packets of PREVYMIS oral pellets are packaged into a carton (NDC 0006-5086-01). Each carton contains 30 child resistant packets.
The 120 mg packets of PREVYMIS oral pellets are packaged into a carton (NDC 0006-5085-01). Each carton contains 30 child resistant packets. Store PREVYMIS oral pellets in the original packet until use.
Store PREVYMIS oral pellets at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Injection: PREVYMIS is supplied as a sterile, clear and colorless solution for intravenous use of 240 mg/12 mL (20 mg/mL) or 480 mg/24 mL (20 mg/mL) that may contain a few product-related small translucent or white particles. The single-dose vials are supplied in cartons that contain a 240 mg single-dose vial (NDC 0006-5003-01) or a 480 mg single-dose vial (NDC 0006-5004-01).
Store PREVYMIS injection vials at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Store in the original carton to protect from exposure to light.
📦 Storage and Handling ▾
Store PREVYMIS tablets in the original package until use to protect from moisture. Store PREVYMIS tablets at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Store PREVYMIS injection vials at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Store in the original carton to protect from exposure to light.
📋 Description ▾
11 DESCRIPTION PREVYMIS contains letermovir, an inhibitor of the CMV DNA terminase complex, and is administered orally or by intravenous infusion. Letermovir has a molecular formula of C 29 H 28 F 4 N 4 O 4 and a molecular weight of 572.55. The chemical name for letermovir is (4 S )-2-{8-Fluoro-2-[4-(3- methoxyphenyl)piperazin-1-yl]-3-[2-methoxy-5- (trifluoromethyl)phenyl]-3,4-dihydroquinazolin-4-yl}acetic acid.
Letermovir is very slightly soluble in water. The chemical structure of letermovir is: PREVYMIS is available as 240 mg and 480 mg tablets. PREVYMIS tablets contain either 240 mg or 480 mg of letermovir and the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, magnesium stearate, microcrystalline cellulose, povidone 25, and film-coated with a coating material containing the following inactive ingredients: hypromellose 2910, iron oxide red (only for 480 mg tablets), iron oxide yellow, lactose monohydrate, titanium dioxide, and triacetin.
Carnauba wax is added as a polishing agent. PREVYMIS is available as 20 mg and 120 mg packets of oral pellets. PREVYMIS packets of oral pellets contain either 20 mg or 120 mg of letermovir.
PREVYMIS oral pellets contain the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, magnesium stearate, microcrystalline cellulose, povidone K-29/32, and are film-coated with a coating material containing the following inactive ingredients: hypromellose 2910, iron oxide red, iron oxide yellow, lactose monohydrate, titanium dioxide, and triacetin. PREVYMIS is also available as 240 mg/12 mL (20 mg/mL) and 480 mg/24 mL (20 mg/mL) injection for intravenous infusion. PREVYMIS injection is a clear, preservative-free sterile solution and may contain a few small translucent or white particles in single-dose vials of either 240 mg or 480 mg per vial.
Each 1 mL of solution contains 20 mg letermovir, hydroxypropyl betadex (150 mg), sodium chloride (3.1 mg), sodium hydroxide (1.2 mg), and Water for Injection. The amount of sodium hydroxide may be adjusted to achieve a pH of approximately 7.5. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information and Instructions for Use ). Drug Interactions Inform patients that PREVYMIS may interact with some drugs; therefore, advise patients to report the use of any prescription, non-prescription medication, or herbal products to their healthcare provider [see Dosage and Administration (2.4 , 2.6) , Contraindications (4) , Warnings and Precautions (5.1) , and Drug Interactions (7) ] . Risks Associated with Hydroxypropyl Betadex Excipient in Intravenous Formulation Inform patients that the intravenous formulation of PREVYMIS contains hydroxypropyl betadex which is eliminated through glomerular filtration and may accumulate in patients with renal impairment.
In animals, hydroxypropyl betadex has been shown to cause ototoxicity [see Warnings and Precautions (5.2) , Use in Specific Populations (8.6) and Nonclinical Toxicology (13.2) ]. Administration Inform patients that it is important not to miss or skip doses and to take PREVYMIS for the duration that is recommended by the healthcare provider. Instruct patients that if they miss a dose of PREVYMIS, they should take it as soon as they remember.
If they do not remember until it is time for the next dose, instruct them to skip the missed dose and go back to the regular schedule. Instruct patients not to double their next dose or take more than the prescribed dose. Advise patients that PREVYMIS injection should be used only in patients unable to take oral therapy and that patients should be switched to oral therapy as soon as they are able [see Dosage and Administration (2.1) ] .
For PREVYMIS oral pellets, advise patients or caregivers to read and follow the Instructions for Use for preparing and taking the correct dose [see Dosage and Administration (2.3 , 2.4 , 2.5 , 2.6 , 2.9) ] . Storage Advise patients to store PREVYMIS tablets and oral pellets in the original package until use [see How Supplied/Storage and Handling (16) ] .