
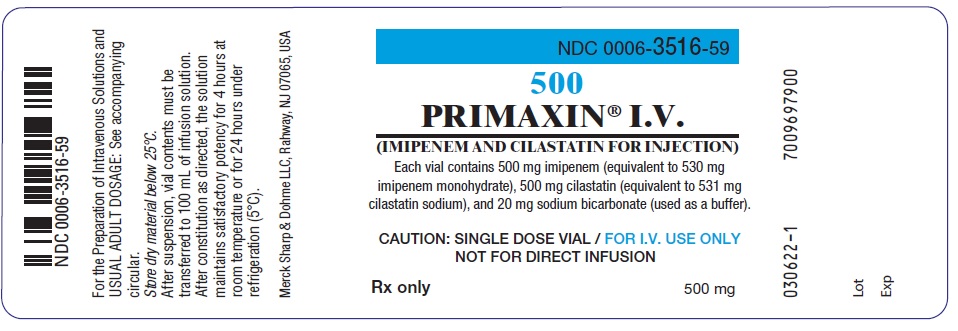
PRIMAXIN IV imipenem and cilastatin sodium 500 mg/100mL; 500 mg/100mL Injection, Powder, For Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Renal Dehydropeptidase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Imipenem and cilastatin injection is used to treat certain serious infections that are caused by bacteria. Imipenem is in a class of medications called carbapenem antibiotics. It works by killing bacteria. Cilastatin is in a class of medications called dehydropeptidase inhibitors. It works by helping imipenem stay active in your body for a longer period of time. Antibiotics such as imipenem and cilastatin injection will not work for colds, flu, or other viral infections. Taking antibiotics when they are not needed increases your risk of getting an infection later that resists antibiotic treatm...
Read the full MedlinePlus article ↗- This is a hospital-grade antibiotic designed for serious or complex infections that need fast, reliable delivery throughout your body. Giving it directly into a vein ensures it get...
- Why am I getting an antibiotic through an IV instead of just taking a pill?
- The most common things people notice are nausea, diarrhea, and some irritation or soreness around the IV site — those are usually manageable. The bigger things to flag immediately...
- What side effects should I actually watch out for during my infusion?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
20 mg / 100 mL
UNII 8MDF5V39QO
A white powder form of baking soda that acts as a buffer and pH regulator in medicines. It helps maintain the right acid-base balance and may aid tablet disintegration.
1 inactive ingredient listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $32.52 | $81,302.50 / 2500 ml |
| Medicare Part B allowsASP · J0743 | $6.517 / J0743 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Primaxin Iv 500 mg/100mL; 500 mg/100mLthis 00006-3516-59 | Merck | 25 vials | — | AP | FDA listed | — |
| Imipenem and Cilastatin 500 mg/1; 500 mg 44567-0705-10 | WG | 10 vials | — | AP | FDA listed | — |
| Imipenem and Cilastatin 500 mg/20mL; 500 mg/20mL 63323-0322-25 | Fresenius | 25 vials | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
🗺️ Medicaid utilization & spend
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00006-3516-59 You're viewing this | 25 VIAL, SINGLE-DOSE in 1 TRAY (0006-3516-59) / 100 mL in 1 VIAL, SINGLE-DOSE | 1985-11-26 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE PRIMAXIN for intravenous use is a combination of imipenem, a penem antibacterial, and cilastatin, a renal dehydropeptidase inhibitor, indicated for the treatment of the following serious infections caused by designated susceptible bacteria: Lower respiratory tract infections. ( 1.1 ) Urinary tract infections. ( 1.2 ) Intra-abdominal infections.
( 1.3 ) Gynecologic infections. ( 1.4 ) Bacterial septicemia. ( 1.5 ) Bone and joint infections.
( 1.6 ) Skin and skin structure infections. ( 1.7 ) Endocarditis. ( 1.8 ) Limitations of Use: PRIMAXIN is not indicated in patients with meningitis because safety and efficacy have not been established ( 1.9 ).
PRIMAXIN is not recommended in pediatric patients with CNS infections because of the risk of seizures ( 1.9 ). PRIMAXIN is not recommended in pediatric patients weighing less than 30 kg with impaired renal function ( 1.9 ). Usage: To reduce the development of drug resistant bacteria and maintain the effectiveness of PRIMAXIN and other antibacterial drugs, PRIMAXIN should be used only to treat infections that are proven or strongly suspected to be caused by bacteria ( 1.10 ).
1.1Lower Respiratory Tract Infections PRIMAXIN for intravenous use is indicated for the treatment of lower respiratory tract infections caused by susceptible strains of Staphylococcus aureus (penicillinase-producing isolates), Acinetobacter species, Enterobacter species, Escherichia coli , Haemophilus influenzae , Haemophilus parainfluenzae , Klebsiella species, Serratia marcescens.
1.2Urinary Tract Infections (complicated and uncomplicated) PRIMAXIN is indicated for the treatment of urinary tract infections (complicated and uncomplicated) caused by susceptible strains of Enterococcus faecalis , Staphylococcus aureus (penicillinase-producing isolates), Enterobacter species, Escherichia coli , Klebsiella species, Morganella morganii , Proteus vulgaris , Providencia rettgeri , Pseudomonas aeruginosa.
1.3Intra-Abdominal Infections PRIMAXIN is indicated for the treatment of intra-abdominal infections caused by susceptible strains of Enterococcus faecalis , Staphylococcus aureus (penicillinase-producing isolates), Staphylococcus epidermidis , Citrobacter species, Enterobacter species, Escherichia coli , Klebsiella species, Morganella morganii , Proteus species, Pseudomonas aeruginosa , Bifidobacterium species, Clostridium species, Eubacterium species, Peptococcus species, Peptostreptococcus species, Propionibacterium species, Bacteroides species including B. fragilis , Fusobacterium species .
1.4Gynecologic Infections PRIMAXIN is indicated for the treatment of gynecologic infections caused by susceptible strains of Enterococcus faecalis , Staphylococcus aureus (penicillinase-producing isolates), Staphylococcus epidermidis , Streptococcus agalactiae (Group B streptococci), Enterobacter species, Escherichia coli , Gardnerella vaginalis , Klebsiella species, Proteus species, Bifidobacterium species, Peptococcus species, Peptostreptococcus species, Propionibacterium species, Bacteroides species including B. fragilis.
1.5Bacterial Septicemia PRIMAXIN is indicated for the treatment of bacterial septicemia caused by susceptible strains of Enterococcus faecalis , Staphylococcus aureus (penicillinase-producing isolates), Enterobacter species, Escherichia coli , Klebsiella species, Pseudomonas aeruginosa , Serratia species, Bacteroides species including B. fragilis.
1.6Bone and Joint Infections PRIMAXIN is indicated for the treatment of bone and joint infections caused by susceptible strains of Enterococcus faecalis , Staphylococcus aureus (penicillinase-producing isolates), Staphylococcus epidermidis , Enterobacter species, Pseudomonas aeruginosa.
1.7Skin and Skin Structure Infections PRIMAXIN is indicated for the treatment of skin and skin structure infections caused by susceptible strains of Enterococcus faecalis , Staphylococcus aureus (penicillinase-producing isolates), Staphylococcus epidermi…
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The dosage of PRIMAXIN in adult patients should be based on suspected or confirmed pathogen susceptibility ( 2.1 ). For adult patients with normal renal function (creatinine clearance of greater than or equal to 90 mL/min), the recommended dosage regimens are: 500 mg every 6 hours OR 1000 mg every 8 hours OR 1000 mg every 6 hours ( 2.1 ). See full prescribing information for dosage recommendations in pediatric patients ( 2.2 ).
A reduction in dose must be made for a patient with a creatinine clearance of less than 90 mL/min ( 2.3 ). Patients with creatinine clearances of less than 15 mL/min should not receive PRIMAXIN unless hemodialysis is instituted within 48 hours ( 2.4 ). Reconstitute PRIMAXIN vial with appropriate diluent and dilute the reconstituted suspension with an appropriate infusion solution before administering by intravenous infusion ( 2.5 ).
2.1Dosage in Adults For Intravenous Injection Only The dosage of PRIMAXIN in adult patients should be based on suspected or confirmed pathogen susceptibility as shown in Table 1 below. The dosage recommendations for PRIMAXIN represent the quantity of imipenem to be administered. An equivalent amount of cilastatin is also present in the solution.
These doses should be used for patients with creatinine clearance of greater than or equal to 90 mL/min. A reduction in dose must be made for patients with creatinine clearance less than 90 mL/min as shown in Table 3 [see Dosage and Administration (2.3) ]. Recommend that the maximum total daily dosage not exceed 4 g/day.
Administer 500 mg by intravenous infusion over 20 to 30 minutes. Administer 1000 mg by intravenous infusion over 40 to 60 minutes. In patients who develop nausea during the infusion, the rate of infusion may be slowed.
Table 1: Dosage of PRIMAXIN in Adult Patients with Creatinine Clearance Greater than or Equal to 90 mL/min Suspected or Proven Pathogen Susceptibility Dosage of PRIMAXIN If the infection is suspected or proven to be due to a susceptible bacterial species 500 mg every 6 hours OR 1000 mg every 8 hours If the infection is suspected or proven to be due to bacterial species with intermediate susceptibility [see Microbiology (12.4) ] 1000 mg every 6 hours
2.2Dosage in Pediatric Patients PRIMAXIN is not recommended in pediatric patients with CNS infections because of the risk of seizures [see Use in Specific Populations (8.4) ]. PRIMAXIN is not recommended in pediatric patients <30 kg with renal impairment, as no data are available [see Use in Specific Populations (8.4) ]. Based on studies in adults, the maximum total daily dose in pediatric patients should not exceed 4 g/day [see Dosage and Administration (2.1) ].
The recommended dosage for pediatric patients with non-CNS infections is shown in Table 2 below: Table 2: Recommended PRIMAXIN Dosage in Pediatric Patients for Non-CNS Infections Age Dose (mg/kg) Doses less than or equal to 500 mg should be given by intravenous infusion over 20 to 30 minutes , Doses greater than 500 mg should be given by intravenous infusion over 40 to 60 minutes Recommend that the maximum total daily dosage not exceed 4g/day Frequency (hours) Greater than or equal to 3 Months of Age 15-25 mg/kg Every 6 hours Less than or equal to 3 months of age (Greater than or equal to 1,500 g body weight) 4 weeks to 3 months of age 25 mg/kg Every 6 hours 1 to 4 weeks of age 25 mg/kg Every 8 hours Less than 1 week of age 25 mg/kg Every 12 hours
2.3Dosage in Adult Patients with Renal Impairment Patients with creatinine clearance less than 90 mL/min require dosage reduction of PRIMAXIN as indicated in Table 3. The serum creatinine should represent a steady state of renal function. Use the Cockcroft-Gault method described below to calculate the creatinine clearance: Males: (weight in kg) × (140-age in years) (72) × serum creatinine (mg/100 mL) Females: (0.85) × (value calculated for males) Table 3: Dosage of PRIMAXIN for Adult Patients in Various Renal Function Groups…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For Injection PRIMAXIN is a sterile powder mixture for reconstitution in single-dose containers including vials containing: 500 mg imipenem (anhydrous equivalent) and 500 mg cilastatin (free acid equivalent) For Injection: PRIMAXIN is a sterile powder mixture for reconstitution in single-dose containers including vials containing: 500 mg imipenem (anhydrous equivalent) and 500 mg cilastatin (free acid equivalent) ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS PRIMAXIN is contraindicated in patients who have shown hypersensitivity to any component of this product. Known hypersensitivity to any component of PRIMAXIN ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypersensitivity Reactions: Serious and occasionally fatal hypersensitivity (anaphylactic) reactions have been reported in patients receiving therapy with beta-lactams. If an allergic reaction to PRIMAXIN occurs, discontinue the drug immediately ( 5.1 ). Seizure Potential: Seizures and other CNS adverse reactions, such as confusional states and myoclonic activity, have been reported during treatment with PRIMAXIN.
If focal tremors, myoclonus, or seizures occur, patients should be evaluated neurologically, placed on anticonvulsant therapy if not already instituted, and the dosage of PRIMAXIN re-examined to determine whether it should be decreased, or the antibacterial drug discontinued ( 5.2 ). Increased Seizure Potential Due to Interaction with Valproic Acid: Co-administration of PRIMAXIN, to patients receiving valproic acid or divalproex sodium results in a reduction in valproic acid concentrations. The valproic acid concentrations may drop below the therapeutic range as a result of this interaction, therefore increasing the risk of breakthrough seizures.
The concomitant use of PRIMAXIN and valproic acid/divalproex sodium is generally not recommended ( 5.3 , 7.3 ). Clostridioides difficile-Associated Diarrhea (CDAD): has been reported with use of PRIMAXIN and may range in severity from mild diarrhea to fatal colitis. Evaluate if diarrhea occurs ( 5.4 ).
5.1Hypersensitivity Reactions Serious and occasionally fatal hypersensitivity (anaphylactic) reactions have been reported in patients receiving therapy with beta-lactams. These reactions are more likely to occur in individuals with a history of sensitivity to multiple allergens. There have been reports of individuals with a history of penicillin hypersensitivity who have experienced severe hypersensitivity reactions when treated with another beta-lactam.
Before initiating therapy with PRIMAXIN, careful inquiry should be made concerning previous hypersensitivity reactions to penicillins, cephalosporins, other beta-lactams and other allergens. If an allergic reaction to PRIMAXIN occurs, discontinue the drug immediately. Serious anaphylactic reactions require immediate emergency treatment as clinically indicated.
5.2Seizure Potential Seizures and other CNS adverse experiences, such as confusional states and myoclonic activity, have been reported during treatment with PRIMAXIN, especially when recommended dosages were exceeded [see Adverse Reactions (6.1 , 6.2 )]. These experiences have occurred most commonly in patients with CNS disorders (e.g., brain lesions or history of seizures) and/or compromised renal function [see Use in Specific Populations (8.6) ] . However, there have been reports of CNS adverse experiences in patients who had no recognized or documented underlying CNS disorder or compromised renal function.
Anticonvulsant therapy should be continued in patients with known seizure disorders. If focal tremors, myoclonus, or seizures occur, patients should be evaluated neurologically, placed on anticonvulsant therapy if not already instituted, and the dosage of PRIMAXIN re-examined to determine whether it should be decreased, or the antibacterial drug discontinued.
5.3Increased Seizure Potential Due to Interaction with Valproic Acid Case reports in the literature have shown that co-administration of carbapenems, including PRIMAXIN, to patients receiving valproic acid or divalproex sodium results in a reduction in valproic acid concentrations. The valproic acid concentrations may drop below the therapeutic range as a result of this interaction, therefore increasing the risk of breakthrough seizures. Increasing the dose of valproic acid or divalproex sodium may not be sufficient to overcome this interaction.
The concomitant use of PRIMAXIN and valproic acid/divalproex sodium is generally not recommended. Antibacterials other than carbapenems should be considered to treat infections in patients whose seizures are well controlled on valproic acid…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described in greater detail in the Warnings and Precautions section. Hypersensitivity Reactions [see Warnings and Precautions (5.1) ] Seizure Potential [see Warnings and Precautions (5.2) ] Increased Seizure Potential Due to Interaction with Valproic Acid [see Warnings and Precautions (5.3) ] Clostridioides difficile -Associated Diarrhea (CDAD) [see Warnings and Precautions (5.4) ] Development of Drug-Resistant Bacteria [see Warnings and Precautions (5.5) ] The most frequently occurring adverse reactions (≥0.2%) in adults were phlebitis, nausea, diarrhea, vomiting, rash, pain injection site, fever, hypotension, seizures, erythema at injection site, dizziness, pruritus, vein induration, urticaria, somnolence ( 6.1 ).
The most frequently occurring adverse reactions (>1%) in pediatric patients greater than or equal to 3 months of age were diarrhea, rash, phlebitis, gastroenteritis, vomiting, IV site irritation, urine discoloration ( 6.1 ). The most frequently occurring adverse reactions (>1%) in neonates to 3 months of age were convulsions, diarrhea, oliguria/anuria, oral candidiasis, rash, tachycardia ( 6.1 ). To report SUSPECTED ADVERSE REACTIONS, contact Merck Sharp & Dohme LLC at 1-877-888-4231 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adult Patients During clinical investigations 1,723 patients were treated with PRIMAXIN. Table 4 shows the incidence of adverse reactions reported during the clinical investigations of adult patients treated with PRIMAXIN.
Table 4: Incidence (%) Adverse reactions with an incidence ≥0.2% of PRIMAXIN-treated adult patients. of Adverse Reactions Reported During Clinical Investigations of Adult Patients Treated with PRIMAXIN Body System Adverse Reactions Frequency (%) Local Administration site Phlebitis/thrombophlebitis 3.1% Pain at the injection site 0.7% Erythema at the injection site 0.4% Vein induration 0.2% Gastrointestinal Nausea 2.0% Diarrhea 1.8% Vomiting 1.5% Skin Rash 0.9% Pruritus 0.3% Urticaria 0.2% Vascular Hypotension 0.4% Body as a Whole Fever 0.5% Nervous system Seizures 0.4% Dizziness 0.3% Somnolence 0.2% Additional adverse reactions reported in less than 0.2% of the patients or reported since the drug was marketed are listed within each body system in order of decreasing severity [see Table 5 ] .
Table 5: Additional Adverse Reactions Occurring in Less than 0.2% of Adult Patients Listed within Each Body System in Order of Decreasing Severity Body System Adverse Reactions Gastrointestinal Pseudomembranous Colitis (the onset of Pseudomembranous colitis symptoms), Hemorrhagic Colitis Gastroenteritis Abdominal Pain Glossitis Tongue Papillar Hypertrophy Heartburn Pharyngeal Pain Increased Salivation CNS Encephalopathy Confusion Myoclonus Paresthesia Vertigo Headache Special Senses Hearing Loss Tinnitus Respiratory Chest Discomfort Dyspnea Hyperventilation Thoracic Spine Pain Cardiovascular Palpitations Tachycardia Skin Erythema Multiforme Angioneurotic Edema Flushing Cyanosis Hyperhidrosis Skin Texture Changes Candidiasis Pruritus Vulvae Local Administration site Infused vein infection Body as a Whole Polyarthralgia Asthenia/Weakness Renal Oliguria/Anuria Polyuria Adverse Laboratory Changes The following adverse laboratory changes were reported during clinical trials: Hepatic: Increased alanine aminotransferase (ALT or SGPT), aspartate aminotransferase (AST or SGOT), alkaline phosphatase, bilirubin, and lactate dehydrogenase (LDH) Hemic: Increased eosinophils, positive Coombs test, increased WBC, increased platelets, decreased hemoglobin and hematocrit, increased monocytes, abnormal prothrombin time, increased lymphocytes, in…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Ganciclovir: Generalized seizures have been reported in patients who received ganciclovir. Do not co-administer unless benefit outweighs risk ( 7.1 ). Probenecid: Concomitant administration of PRIMAXIN and probenecid results in increases in the plasma level and half-life of imipenem.
Concomitant administration is not recommended ( 7.2 ). Valproic acid/divalproex sodium: Concomitant use with PRIMAXIN is generally not recommended. Consider other antibacterial drugs to treat infections in patients whose seizures are well-controlled on valproic acid or divalproex sodium ( 5.3 , 7.3 ).
7.1Ganciclovir Generalized seizures have been reported in patients who received ganciclovir and PRIMAXIN. These drugs should not be used concomitantly with PRIMAXIN unless the potential benefits outweigh the risks.
7.2Probenecid Concomitant administration of PRIMAXIN and probenecid results in increases in the plasma level and half-life of imipenem. Therefore, it is not recommended that probenecid be given concomitantly with PRIMAXIN.
7.3Valproic Acid Case reports in the literature have shown that co-administration of carbapenems, including PRIMAXIN, to patients receiving valproic acid or divalproex sodium results in a reduction in valproic acid concentrations. The valproic acid concentrations may drop below the therapeutic range as a result of this interaction, therefore increasing the risk of breakthrough seizures. Although the mechanism of this interaction is unknown, data from in vitro and animal studies suggest that carbapenems may inhibit the hydrolysis of valproic acid's glucuronide metabolite (VPA-g) back to valproic acid, thus decreasing the serum concentrations of valproic acid [see Warnings and Precautions (5.3) ].
The concomitant use of PRIMAXIN and valproic acid/divalproex sodium is generally not recommended. Antibacterials other than carbapenems should be considered to treat infections in patients whose seizures are well-controlled on valproic acid or divalproex sodium.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Renal Impairment: Dosage adjustment is necessary in patients with renal impairment ( 2.3 ). Adult patients with creatinine clearances of less than or equal to 30 mL/min, whether or not undergoing hemodialysis, had a higher risk of seizure activity than those without impairment of renal function ( 5.2 ). Therefore, close adherence to the dosing guidelines and regular monitoring of creatinine clearance for these patients is recommended ( 8.6 ).
8.1Pregnancy Risk Summary Available data from a small number of postmarketing cases with PRIMAXIN use in pregnancy are not sufficient to identify any drug-associated risks for major birth defects, miscarriage, or adverse maternal or fetal outcomes. Developmental toxicity studies with imipenem and cilastatin sodium (alone or in combination) administered to mice, rats, rabbits, and monkeys at doses 0.4 to 2.9 times the recommended human dose (RHD), (based on body surface area), showed no drug-induced fetal malformations.
Embryofetal development studies with imipenem/cilastatin administered to cynomolgus monkeys at doses similar to the RHD (based on body surface area) showed an increase in embryonic loss (see Data ) . The background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
The background risk of major birth defects is 2-4% and of miscarriage is 15-20% of clinically recognized pregnancies within the general population. Data Animal Data Reproductive toxicity studies with imipenem and cilastatin (alone or in combination) administered to mice, rats, and rabbits showed no evidence of effects on embryofetal (mice, rats and rabbits) or pre/postnatal (rats) development. Imipenem was administered intravenously to rats (gestation days (GD) 7 to 17) and rabbits (GD 6 to 18) at doses up to 900 and 60 mg/kg/day, respectively, approximately 2.9 and 0.4 times the RHD (based on body surface area).
Cilastatin was administered subcutaneously to rats (GD 6 to 17) and intravenously to rabbits (GD 6 to 18) at doses up to 1000 and 300 mg/kg/day, respectively, approximately 3.2 and 1.9 times the RHD (based on body surface area). Imipenem/cilastatin was administered intravenously to mice at doses up to 320 mg/kg/day (GD 6 to 15). In two separate studies, imipenem/cilastatin was administered to rats (GD 6 to 17 and GD 15 to day 21 postpartum) both intravenously at doses up to 80 mg/kg/day and subcutaneously at 320 mg/kg/day.
The higher dose is approximately equal to the RHD (based on body surface area). Imipenem/cilastatin administered intravenously to pregnant cynomolgus monkeys during organogenesis at 100 mg/kg/day, approximately 0.6 times the RHD (based on body surface area), at an infusion rate mimicking human clinical use, was not associated with fetal malformations, but there was an increase in embryonic loss relative to controls. Imipenem/cilastatin administered to pregnant cynomolgus monkeys during organogenesis at 40 mg/kg/day by bolus intravenous injection caused significant maternal toxicity including death and embryofetal loss.
8.2Lactation Risk Summary There are insufficient data on the presence of imipenem/cilastatin in human milk, and no data on the effects on the breastfed child, or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for PRIMAXIN and any potential adverse effects on the breastfed child from PRIMAXIN or from the underlying maternal condition.
8.4Pediatric Use Use of PRIMAXIN in pediatric patients is supported by evidence from adequate and well-controlled trials of PRIMAXIN in adults and clinical studies in pediatric patients [see Dosage and Administration (2.2) and Clinical Pharmacology (12.3) ] . PRIMAXIN is not recommended in pediatric patients with CNS infections because of the risk of seizures. PRIMAXIN is not recommended in…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from a small number of postmarketing cases with PRIMAXIN use in pregnancy are not sufficient to identify any drug-associated risks for major birth defects, miscarriage, or adverse maternal or fetal outcomes. Developmental toxicity studies with imipenem and cilastatin sodium (alone or in combination) administered to mice, rats, rabbits, and monkeys at doses 0.4 to 2.9 times the recommended human dose (RHD), (based on body surface area), showed no drug-induced fetal malformations.
Embryofetal development studies with imipenem/cilastatin administered to cynomolgus monkeys at doses similar to the RHD (based on body surface area) showed an increase in embryonic loss (see Data ) . The background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
The background risk of major birth defects is 2-4% and of miscarriage is 15-20% of clinically recognized pregnancies within the general population. Data Animal Data Reproductive toxicity studies with imipenem and cilastatin (alone or in combination) administered to mice, rats, and rabbits showed no evidence of effects on embryofetal (mice, rats and rabbits) or pre/postnatal (rats) development. Imipenem was administered intravenously to rats (gestation days (GD) 7 to 17) and rabbits (GD 6 to 18) at doses up to 900 and 60 mg/kg/day, respectively, approximately 2.9 and 0.4 times the RHD (based on body surface area).
Cilastatin was administered subcutaneously to rats (GD 6 to 17) and intravenously to rabbits (GD 6 to 18) at doses up to 1000 and 300 mg/kg/day, respectively, approximately 3.2 and 1.9 times the RHD (based on body surface area). Imipenem/cilastatin was administered intravenously to mice at doses up to 320 mg/kg/day (GD 6 to 15). In two separate studies, imipenem/cilastatin was administered to rats (GD 6 to 17 and GD 15 to day 21 postpartum) both intravenously at doses up to 80 mg/kg/day and subcutaneously at 320 mg/kg/day.
The higher dose is approximately equal to the RHD (based on body surface area). Imipenem/cilastatin administered intravenously to pregnant cynomolgus monkeys during organogenesis at 100 mg/kg/day, approximately 0.6 times the RHD (based on body surface area), at an infusion rate mimicking human clinical use, was not associated with fetal malformations, but there was an increase in embryonic loss relative to controls. Imipenem/cilastatin administered to pregnant cynomolgus monkeys during organogenesis at 40 mg/kg/day by bolus intravenous injection caused significant maternal toxicity including death and embryofetal loss.
🧒 Pediatric Use ▾
8.4Pediatric Use Use of PRIMAXIN in pediatric patients is supported by evidence from adequate and well-controlled trials of PRIMAXIN in adults and clinical studies in pediatric patients [see Dosage and Administration (2.2) and Clinical Pharmacology (12.3) ] . PRIMAXIN is not recommended in pediatric patients with CNS infections because of the risk of seizures. PRIMAXIN is not recommended in pediatric patients less than 30 kg with renal impairment, as no data are available.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the approximately 3600 subjects ≥18 years of age in clinical studies of PRIMAXIN, including postmarketing studies, approximately 2800 received PRIMAXIN. Of the subjects who received PRIMAXIN, data are available on approximately 800 subjects who were 65 and over, including approximately 300 subjects who were 75 and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects.
Other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
No dosage adjustment is required based on age [see Clinical Pharmacology (12.3) ] . Dosage adjustment in the case of renal impairment is necessary [see Dosage and Administration (2.3) ].
🆘 Overdosage ▾
10 OVERDOSAGE In the case of overdosage, discontinue PRIMAXIN, treat symptomatically, and institute supportive measures as required. PRIMAXIN is hemodialyzable.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action PRIMAXIN is a combination of imipenem and cilastatin. Imipenem is a penem antibacterial drug [see Microbiology (12.4) ] . Cilastatin is a renal dehydropeptidase inhibitor that limits the renal metabolism of imipenem.
12.3Pharmacokinetics Intravenous infusion of PRIMAXIN over 20 minutes results in peak plasma levels of imipenem antimicrobial activity that range from 21 to 58 mcg/mL for the 500 mg dose, and from 41 to 83 mcg/mL for the 1000 mg dose. At these doses, plasma levels of imipenem antimicrobial activity decline to below 1 mcg/mL or less in 4 to 6 hours. Peak plasma levels of cilastatin following a 20-minute intravenous infusion of PRIMAXIN range from 31 to 49 mcg/mL for the 500 mg dose, and from 56 to 88 mcg/mL for the 1000 mg dose.
Distribution The binding of imipenem to human serum proteins is approximately 20% and that of cilastatin is approximately 40%. Imipenem has been shown to penetrate into human tissues, including vitreous humor, aqueous humor, lung, peritoneal fluid, CSF, bone, interstitial fluid, skin, and fascia. As there are no adequate and well-controlled studies of imipenem treatment in these additional body sites, the clinical significance of these tissue concentration data is unknown.
After a 1 gram dose of PRIMAXIN, the following average levels of imipenem were measured (usually at 1 hour post dose except where indicated) in the tissues and fluids listed in Table 9: Table 9: Average Levels of Imipenem Tissue or Fluid N Imipenem Level mcg/mL or mcg/g Range Vitreous Humor 3 3.4 (3.5 hours post dose) 2.88–3.6 Aqueous Humor 5 2.99 (2 hours post dose) 2.4–3.9 Lung Tissue 8 5.6 (median) 3.5–15.5 Sputum 1 2.1 — Pleural 1 22.0 — Peritoneal 12
23.9S.D.±5.3 (2 hours post dose) — Bile 2 5.3 (2.25 hours post dose) 4.6–6.0 CSF (uninflamed) 5 1.0 (4 hours post dose) 0.26–2.0 CSF (inflamed) 7 2.6 (2 hours post dose) 0.5–5.5 Fallopian Tubes 1 13.6 — Endometrium 1 11.1 — Myometrium 1 5.0 — Bone 10 2.6 0.4–5.4 Interstitial Fluid 12 16.4 10.0–22.6 Skin 12
4.4 NA Fascia 12
4.4NA Metabolism Imipenem, when administered alone, is metabolized in the kidneys by dehydropeptidase I, resulting in relatively low levels in urine. Cilastatin, an inhibitor of this enzyme, effectively prevents renal metabolism of imipenem so that when imipenem and cilastatin sodium are given concomitantly, adequate antibacterial levels of imipenem are achieved in the urine. Elimination The plasma half-life of each component is approximately 1 hour.
Approximately 70% of the administered imipenem is recovered in the urine within 10 hours after which no further urinary excretion is detectable. Urine concentrations of imipenem in excess of 10 mcg/mL can be maintained for up to 8 hours with PRIMAXIN at the 500 mg dose. Approximately 70% of the cilastatin sodium dose is recovered in the urine within 10 hours of administration of PRIMAXIN.
PRIMAXIN is hemodialyzable [see Overdosage (10) ]. No accumulation of imipenem/cilastatin in plasma or urine is observed with regimens administered as frequently as every 6 hours in patients with normal renal function. Specific Populations Geriatric Patients In healthy elderly volunteers (65 to 75 years of age with normal renal function for their age), the pharmacokinetics of a single dose of imipenem 500 mg and cilastatin 500 mg administered intravenously over 20 minutes are consistent with those expected in subjects with slight renal impairment for which no dosage alteration is considered necessary.
The mean plasma half-lives of imipenem and cilastatin are 91±7 minutes and 69±15 minutes, respectively. Multiple dosing has no effect on the pharmacokinetics of either imipenem or cilastatin, and no accumulation of imipenem/cilastatin is observed. Pediatric Patients Doses of 25 mg/kg/dose in patients 3 months to <3 years of age, and 15 mg/kg/dose in patients 3-12 years of age were associated with mean trough plasma concentrations of imipenem of 1.1±0.4 mcg/mL and 0.6±0.2 m…
🧬 Mechanism of Action ▾
12.1Mechanism of Action PRIMAXIN is a combination of imipenem and cilastatin. Imipenem is a penem antibacterial drug [see Microbiology (12.4) ] . Cilastatin is a renal dehydropeptidase inhibitor that limits the renal metabolism of imipenem.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied PRIMAXIN is supplied as a sterile powder mixture in single dose containers including vials containing imipenem (anhydrous equivalent) and cilastatin (free acid equivalent) as follows: Each PRIMAXIN Package Contains: National Drug Code (NDC) Number A tray of 25 vials, each vial containing 500 mg imipenem equivalent, 500 mg cilastatin equivalent, and 20 mg sodium bicarbonate as a buffer. (NDC 0006-3516-59)
16.2Storage and Handling Before Reconstitution: PRIMAXIN dry powder should be stored at a temperature below 25°C (77°F).
📦 Storage and Handling ▾
16.2Storage and Handling Before Reconstitution: PRIMAXIN dry powder should be stored at a temperature below 25°C (77°F).
📋 Description ▾
11 DESCRIPTION PRIMAXIN (imipenem and cilastatin) for Injection is a sterile formulation of imipenem, a penem antibacterial, and cilastatin, a renal dehydropeptidase inhibitor with sodium bicarbonate added as a buffer. PRIMAXIN is an antibacterial drug for intravenous administration. Imipenem (N-formimidoylthienamycin monohydrate) is a crystalline derivative of thienamycin, which is produced by Streptomyces cattleya .
Its chemical name is (5 R ,6 S )-3-[[2-(formimidoylamino)ethyl]thio]-6-[( R )-1-hydroxyethyl]-7-oxo-1-azabicyclo[3.2.0]hept-2-ene-2-carboxylic acid monohydrate. It is an off-white, nonhygroscopic crystalline compound with a molecular weight of 317.37. It is sparingly soluble in water and slightly soluble in methanol.
Its empirical formula is C 12 H 17 N 3 O 4 S∙H 2 O, and its structural formula is: Cilastatin sodium is the sodium salt of a derivatized heptenoic acid. Its chemical name is sodium ( Z )-7[[( R )-2-amino-2-carboxyethyl]thio]-2-[( S )-2,2-dimethylcyclopropanecarboxamido]-2-heptenoate. It is an off-white to yellowish-white, hygroscopic, amorphous compound with a molecular weight of 380.43.
It is very soluble in water and in methanol. Its empirical formula is C 16 H 25 N 2 O 5 SNa, and its structural formula is: Each single-dose vial of PRIMAXIN contains 500 mg imipenem (equivalent to 530 mg imipenem monohydrate), 500 mg cilastatin (equivalent to 531 mg cilastatin sodium), and 20 mg sodium bicarbonate (used as a buffer). PRIMAXIN is buffered to provide solutions in the pH range of 6.5 to 8.5.
There is no significant change in pH when solutions are prepared and used as directed [see How Supplied/Storage and Handling (16.1) ]. PRIMAXIN 500 contains 37.5 mg of sodium (1.6 mEq). Solutions of PRIMAXIN range from colorless to yellow.
Variations of color within this range do not affect the potency of the product. Chemical Structure Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients that allergic reactions, including serious allergic reactions, could occur and that serious reactions require immediate treatment. They should report any previous hypersensitivity reactions to PRIMAXIN, other carbapenems, beta-lactams or other allergens. Counsel patients that antibacterial drugs including PRIMAXIN should only be used to treat bacterial infections.
They do not treat viral infections (e.g., the common cold). When PRIMAXIN is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by PRIMAXIN or other antibacterial drugs in the future.
Counsel patients to inform their physician: if they have central nervous system disorders such as stroke or history of seizures. Seizures have been reported during treatment with PRIMAXIN and with closely related antibacterial drugs. if they are taking valproic acid or sodium valproate. Valproic acid concentrations in the blood may drop below the therapeutic range upon co-administration with PRIMAXIN.
If treatment with PRIMAXIN is necessary and continued, alternative or supplemental anti-convulsant medication to prevent and/or treat seizures may be needed. Advise patients that diarrhea is a common problem caused by antibacterial drugs and usually resolves when the drug is discontinued. Sometimes, frequent watery or bloody diarrhea may occur and may be a sign of a more serious intestinal infection.
If severe watery or bloody diarrhea develops, patients should contact their healthcare provider.