
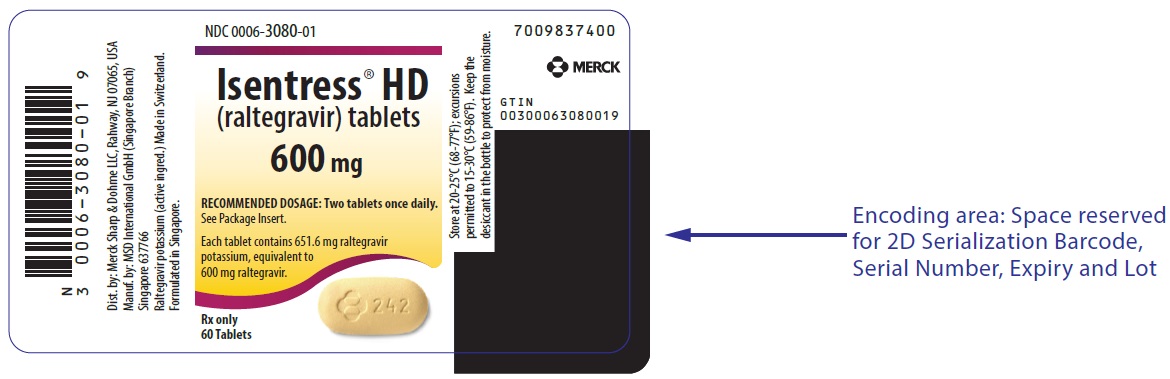
ISENTRESS RALTEGRAVIR 600 mg Tablet, Film Coated, 60-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Human Immunodeficiency Virus Integrase Strand Transfer Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Raltegravir is used to treat human immunodeficiency virus (HIV) infection. Raltegravir is in a class of medications called HIV integrase inhibitors. It works by decreasing the amount of HIV in the blood. Although raltegravir does not cure HIV, it may decrease your chance of developing acquired immunodeficiency syndrome (AIDS) and HIV-related illnesses. Taking these medications and making other lifestyle changes may decrease the risk of transmitting (spreading) the HIV virus to other people.
Read the full MedlinePlus article ↗- Raltegravir blocks an enzyme called integrase that HIV-1 uses to embed itself in your DNA. Without that step, the virus can't make copies of itself. The reason you need it alongsid...
- What exactly does raltegravir do — and why do I have to take other HIV medicines with it?
- It depends on the form you're taking. The good news is that all forms of raltegravir can be taken with or without food. That said, food does affect how much of the drug gets absorb...
- Does it matter what I eat when I take it?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Raltegravir — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII R12CBM0EIZ
A natural wax derived from a Brazilian palm tree, used as a coating and polish on tablets and capsules. It creates a smooth, shiny finish that protects the medicine and improves appearance.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $34.503 | $2,070.20 / 60 tablets |
| Medicaid paysCMS SDUD · 12 mo | $33.90 | $2,033.90 / 60 tablets |
| Medicare drug plans payPart D · Q2 2026 | $34.05 | $2,043.27 / 60 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Isentress 600 mgthis 00006-3080-01 | Merck | 60 tablets | $34.503 | — | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 7754731 ↗ | Drug substance | U-257 | Mar 11, 2029 |
| US 7754731 ↗ | Drug substance | U-257 | Mar 11, 2029 |
| US 8852632 ↗ | Drug substance | U-257 | Jan 28, 2028 |
| US 8771733 ↗ | Drug substance | U-257 | Jun 2, 2030 |
| US 8771733 ↗ | Drug substance | U-257 | Jun 2, 2030 |
| US 10772888 ↗ | Method of use | U-1663 | Mar 30, 2032 |
| US 9649311 ↗ | Drug product | — | Oct 21, 2030 |
| US 7754731*PED ↗ | Drug product | — | Sep 11, 2029 |
| US 9649311*PED ↗ | Drug product | — | Apr 21, 2031 |
| US 7754731*PED ↗ | Drug product | — | Sep 11, 2029 |
Is there a generic version of ISENTRESS HD 600 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00006-3080-01 You're viewing this | 60 TABLET, FILM COATED in 1 BOTTLE (0006-3080-01) | 2017-05-26 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Adult Patients: ISENTRESS and ISENTRESS HD are human immunodeficiency virus integrase strand transfer inhibitors (HIV-1 INSTI) indicated in combination with other antiretroviral agents for the treatment of HIV-1 infection in adult patients ( 1 ). Pediatric Patients: ISENTRESS is indicated in combination with other antiretroviral agents for the treatment of HIV-1 infection in pediatric patients weighing at least 2 kg ( 1 ). ISENTRESS HD is indicated in combination with other antiretroviral agents for the treatment of HIV-1 infection in pediatric patients weighing at least 40 kg ( 1 ).
Adult Patients: ISENTRESS ® and ISENTRESS ® HD are indicated in combination with other antiretroviral agents for the treatment of human immunodeficiency virus (HIV-1) infection in adult patients. Pediatric Patients: ISENTRESS is indicated in combination with other antiretroviral agents for the treatment of HIV-1 infection in pediatric patients weighing at least 2 kg. ISENTRESS HD is indicated in combination with other antiretroviral agents for the treatment of HIV-1 infection in pediatric patients weighing at least 40 kg.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION ISENTRESS and ISENTRESS HD can be administered with or without food ( 2.1 ). Do not substitute ISENTRESS chewable tablets or ISENTRESS for oral suspension for the ISENTRESS 400 mg or 600 mg film-coated tablet. See specific dosing guidance for chewable tablets and the formulation for oral suspension ( 2.1 ).
Adults Treatment-naïve patients or patients who are virologically suppressed on an initial regimen of ISENTRESS 400 mg twice daily: 1200 mg (2 × 600 mg) film-coated tablet orally, once daily or 400 mg film-coated tablet orally, twice daily ( 2.2 ). Treatment-experienced patients: 400 mg film-coated tablet orally, twice daily ( 2.2 ). During coadministration with rifampin in adults, 800 mg (2 × 400 mg) twice daily ( 2.2 ).
Pediatrics If weighing at least 40 kg, and either treatment-naïve patients or patients who are virologically suppressed on an initial regimen of ISENTRESS 400 mg twice daily: 1200 mg (2 × 600 mg) film-coated tablet orally, once daily or 400 mg film-coated tablet orally, twice daily or 300 mg (3 × 100 mg) chewable tablets, twice daily ( 2.3 ). If weighing at least 25 kg: One 400 mg film-coated tablet orally, twice daily. If unable to swallow a tablet, consider the chewable tablet, as specified in Table 2 ( 2.3 ).
If weighing at least 3 kg to less than 25 kg: Weight-based dosing using the chewable tablet or oral suspension, as specified in Table 4 ( 2.3 ). For neonates (birth to 4 weeks [28 days] of age): Weight-based dosing of the oral suspension as specified in Table 5 ( 2.3 ).
2.1General Dosing Recommendations Because the formulations have different pharmacokinetic profiles, do not substitute ISENTRESS chewable tablets or ISENTRESS for oral suspension for the ISENTRESS 400 mg film-coated tablet or the ISENTRESS HD 600 mg film-coated tablet. See specific dosing guidance for chewable tablets and the formulation for oral suspension. Because the extent to which ISENTRESS may be dialyzable is unknown, dosing before a dialysis session should be avoided [see Clinical Pharmacology (12.3) ] .
ISENTRESS film-coated tablets must be swallowed whole. ISENTRESS chewable tablets may be chewed or swallowed whole. Maximum daily dose is 300 mg taken by mouth twice daily.
For children who have difficulty chewing the 25 mg chewable tablet, the tablet may be crushed. Preparation of the crushed 25 mg chewable tablet: Place the tablet(s) in a small, clean cup. For each tablet, add a teaspoonful (~5 mL) of liquid (for example, water, juice, or breast milk).
Within 2 minutes, the tablet(s) will absorb the liquid and fall apart. Using a spoon, crush any remaining pieces of the tablet(s). Immediately administer the entire dose orally.
If any portion of the dose is left in the cup, add another teaspoonful (~5 mL) of liquid, swirl and administer immediately. ISENTRESS for oral suspension: See Instructions for Use for details on preparation and administration of ISENTRESS for oral suspension. Using the provided mixing cup, combine 10 mL of water and the entire contents of one packet of ISENTRESS for oral suspension and mix.
Each single-use packet for oral suspension contains 100 mg of raltegravir which is suspended in 10 mL of water giving a final concentration of 10 mg per mL. Maximum daily dose is 100 mg taken by mouth twice daily. Gently swirl the mixing cup for 45 seconds in a circular motion to mix the powder into a uniform suspension.
Do not shake. Once mixed, measure the prescribed dose volume of suspension with a syringe and administer the dose orally. The dose should be administered orally within 30 minutes of mixing.
Discard any remaining suspension into the trash.
2.2Adults The recommended adult dosage of ISENTRESS film-coated tablets is displayed in Table 1. ISENTRESS and ISENTRESS HD should be taken by mouth and may be taken with or without food [see Clinical Pharmacology (12.3) ] . Table 1: Dosing Recommendations for ISENTRESS and ISENTRESS HD in Adult Patients Population Recommended Dose Tr…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Film-coated Tablets 400 mg pink, oval-shaped, film-coated tablets with "227" on one side (ISENTRESS). 600 mg yellow, oval-shaped, film-coated tablets with corporate logo and "242" on one side and plain on the other side (ISENTRESS HD). Chewable Tablets 100 mg pale orange, oval-shaped, orange-banana flavored, chewable tablets scored on both sides and imprinted on one face with the corporate logo and "477" on opposite sides of the score.
25 mg pale yellow, round, orange-banana flavored, chewable tablets with the corporate logo on one side and "473" on the other side. For Oral Suspension 100 mg white to off-white, banana flavored, granular powder that may contain yellow or beige to tan particles in a child resistant single-use foil packet. Film-Coated Tablets: 400 mg ( 3 ).
Film-Coated Tablets: 600 mg ( 3 ). Chewable Tablets: 100 mg scored and 25 mg ( 3 ). For Oral Suspension: Single-use packet of 100 mg ( 3 ).
⛔ Contraindications ▾
4 CONTRAINDICATIONS None None ( 4) .
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Severe, potentially life-threatening and fatal skin reactions have been reported. This includes cases of Stevens-Johnson syndrome, hypersensitivity reaction and toxic epidermal necrolysis. Immediately discontinue treatment with ISENTRESS or ISENTRESS HD and other suspect agents if severe hypersensitivity, severe rash, or rash with systemic symptoms or liver aminotransferase elevations develops and monitor clinical status, including liver aminotransferases closely ( 5.1 ).
Monitor for Immune Reconstitution Syndrome ( 5.2 ). Inform patients with phenylketonuria that the 100 mg and 25 mg chewable tablets contain phenylalanine ( 5.3 ).
5.1Severe Skin and Hypersensitivity Reactions Severe, potentially life-threatening, and fatal skin reactions have been reported. These include cases of Stevens-Johnson syndrome and toxic epidermal necrolysis. Hypersensitivity reactions have also been reported and were characterized by rash, constitutional findings, and sometimes, organ dysfunction, including hepatic failure.
Discontinue ISENTRESS or ISENTRESS HD and other suspect agents immediately if signs or symptoms of severe skin reactions or hypersensitivity reactions develop (including, but not limited to, severe rash or rash accompanied by fever, general malaise, fatigue, muscle or joint aches, blisters, oral lesions, conjunctivitis, facial edema, hepatitis, eosinophilia, angioedema). Clinical status including liver aminotransferases should be monitored and appropriate therapy initiated. Delay in stopping ISENTRESS or ISENTRESS HD treatment or other suspect agents after the onset of severe rash may result in a life-threatening reaction.
5.2Immune Reconstitution Syndrome Immune reconstitution syndrome has been reported in patients treated with combination antiretroviral therapy, including ISENTRESS. During the initial phase of combination antiretroviral treatment, patients whose immune systems respond may develop an inflammatory response to indolent or residual opportunistic infections (such as Mycobacterium avium infection, cytomegalovirus, Pneumocystis jiroveci pneumonia, tuberculosis), which may necessitate further evaluation and treatment. Autoimmune disorders (such as Graves' disease, polymyositis, and Guillain-Barré syndrome) have also been reported to occur in the setting of immune reconstitution; however, the time to onset is more variable, and can occur many months after initiation of treatment.
5.3Phenylketonurics ISENTRESS Chewable Tablets contain phenylalanine, a component of aspartame. Each 25 mg ISENTRESS Chewable Tablet contains approximately 0.05 mg phenylalanine. Each 100 mg ISENTRESS Chewable Tablet contains approximately 0.10 mg phenylalanine. Phenylalanine can be harmful to patients with phenylketonuria.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The most common adverse reactions of moderate to severe intensity (≥2%) are insomnia, headache, dizziness, nausea and fatigue ( 6.1 ). Creatine kinase elevations were observed in subjects who received ISENTRESS or ISENTRESS HD.
Myopathy and rhabdomyolysis have been reported. Use with caution in patients at increased risk of myopathy or rhabdomyolysis, such as patients receiving concomitant medications known to cause these conditions and patients with a history of rhabdomyolysis, myopathy or increased serum creatine kinase ( 6.2 ). To report SUSPECTED ADVERSE REACTIONS, contact Merck Sharp & Dohme LLC at 1-877-888-4231 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Treatment-Naïve Adults The safety of ISENTRESS was evaluated in HIV-infected treatment-naïve subjects in 2 Phase III studies: STARTMRK evaluated ISENTRESS 400 mg twice daily versus efavirenz, both in combination with emtricitabine (+) tenofovir disoproxil fumarate (TDF), and ONCEMRK evaluated ISENTRESS HD 1200 mg (2 × 600 mg) once daily versus ISENTRESS 400 mg twice daily, both in combination with emtricitabine (+) tenofovir disoproxil fumarate. Safety data from these two studies are presented side-by-side in Tables 6 and 7 to simplify presentation; direct comparisons across trials should not be made due to differing duration of follow-up and study design.
STARTMRK (ISENTRESS 400 mg twice daily) In STARTMRK, subjects received ISENTRESS 400 mg twice daily (N=281) or efavirenz (EFV) 600 mg at bedtime (N=282) both in combination with emtricitabine (+) tenofovir disoproxil fumarate, (N=282). During double-blind treatment, the total follow-up for subjects receiving ISENTRESS 400 mg twice daily + emtricitabine (+) tenofovir disoproxil fumarate was 1104 patient-years and 1036 patient-years for subjects receiving efavirenz 600 mg at bedtime + emtricitabine (+) tenofovir disoproxil fumarate.
In STARTMRK, the rate of discontinuation of therapy due to adverse events through Week 240 was 5% in subjects receiving ISENTRESS + emtricitabine (+) tenofovir disoproxil fumarate and 10% in subjects receiving efavirenz + emtricitabine (+) tenofovir disoproxil fumarate. ONCEMRK (ISENTRESS HD 1200 mg [2 × 600 mg] once daily) In ONCEMRK, subjects received ISENTRESS HD 1200 mg once daily (n=531) or ISENTRESS 400 mg twice daily (n=266) both in combination with emtricitabine (+) tenofovir disoproxil fumarate. During double-blind treatment, the total follow-up for subjects with ISENTRESS HD 1200 mg once daily was 913 patient-years and for ISENTRESS 400 mg twice daily was 450 patient-years.
In ONCEMRK, the rate of discontinuation of therapy due to adverse events through Week 96 was 1% in subjects receiving ISENTRESS HD 1200 mg (2 × 600 mg) once daily and 2% in subjects receiving ISENTRESS 400 mg twice daily. Clinical adverse reactions of moderate to severe intensity occurring in ≥2% of treatment-naïve subjects treated with ISENTRESS 400 mg twice daily or efavirenz in STARTMRK through Week 240 or ISENTRESS HD 1200 mg once daily or ISENTRESS 400 mg twice daily in ONCEMRK through Week 96 are presented in Table 6.
In STARTMRK, clinical adverse reactions of all intensities (mild, moderate and severe) occurring in ≥2% of subjects on ISENTRESS 400 mg twice daily through Week 240 also include diarrhea, flatulence, asthenia, decreased appetite, abnormal dreams, depression and nightmare. In ONCEMRK, clinical adverse reactions of all intensities (mild, moderate and severe) occurring in ≥2% of subjects on ISENTRESS HD or ISENTRESS 400 mg twice daily through Week 96 also include abdominal pain, diarrhea, vomiting, and decreased appetite.
Table 6: Adverse Reactions Includes adverse experiences con…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Coadministration of ISENTRESS or ISENTRESS HD and other drugs may alter the plasma concentration of raltegravir. The potential for drug-drug interactions must be considered prior to and during therapy ( 7 ). Coadministration of ISENTRESS or ISENTRESS HD with drugs that are strong inducers of UGT1A1, such as rifampin, may result in reduced plasma concentrations of raltegravir ( 2.1 , 7.1 ).
7.1Effect of Other Agents on the Pharmacokinetics of Raltegravir Raltegravir is not a substrate of cytochrome P450 (CYP) enzymes. Based on in vivo and in vitro studies, raltegravir is eliminated mainly by metabolism via a UGT1A1-mediated glucuronidation pathway. Coadministration of ISENTRESS with drugs that inhibit UGT1A1 may increase plasma levels of raltegravir and coadministration of ISENTRESS with drugs that induce UGT1A1, such as rifampin, may reduce plasma levels of raltegravir (see Table 11 ).
Selected drug interactions are presented in Table 11 [see Clinical Pharmacology (12.3) ] . In some cases, recommendations differ for ISENTRESS versus ISENTRESS HD. Table 11: Selected Drug Interactions in Adults Concomitant Drug Class: Drug Name Effect on Concentration of Raltegravir Clinical Comment for ISENTRESS Clinical Comment for ISENTRESS HD Metal-Containing Antacids Aluminum and/or magnesium-containing antacids ↓ Coadministration or staggered administration is not recommended.
Calcium carbonate antacid ↓ No dose adjustment Co-administration is not recommended Other Agents Rifampin ↓ The recommended dosage is 800 mg twice daily during coadministration with rifampin. There are no data to guide co-administration of ISENTRESS with rifampin in patients below 18 years of age [see Dosage and Administration (2.1) ]. Coadministration is not recommended.
Tipranavir/ritonavir No dose adjustment Coadministration is not recommended Etravirine ↓ No dose adjustment Coadministration is not recommended. Strong inducers of drug metabolizing enzymes not mentioned above e.g., Carbamazepine Phenobarbital Phenytoin ↓↔ The impact of other strong inducers of drug metabolizing enzymes on raltegravir is unknown. Coadministration is not recommended.
7.2Drugs without Clinically Significant Interactions with ISENTRESS or ISENTRESS HD ISENTRESS In drug interaction studies performed using ISENTRESS film-coated tablets 400 mg twice daily dose, raltegravir did not have a clinically meaningful effect on the pharmacokinetics of the following: ethinyl estradiol/norgestimate, methadone, midazolam, lamivudine, tenofovir disoproxil fumarate, etravirine, darunavir/ritonavir, or boceprevir. Moreover, atazanavir, atazanavir/ritonavir, boceprevir, calcium carbonate antacids, darunavir/ritonavir, efavirenz, etravirine, omeprazole, or tipranavir/ritonavir did not have a clinically meaningful effect on the pharmacokinetics of 400 mg twice daily raltegravir.
No dose adjustment is required when ISENTRESS 400 mg twice daily is coadministered with these drugs. There is no predicted pharmacokinetic drug interaction between ISENTRESS and tenofovir alafenamide. ISENTRESS HD In drug interaction studies, efavirenz did not have a clinically meaningful effect on the pharmacokinetics of ISENTRESS HD 1200 mg (2 × 600 mg) once daily.
No dose adjustment is recommended when ISENTRESS HD 1200 mg once daily is coadministered with atazanavir, atazanavir/ritonavir, hormonal contraceptives, methadone, lamivudine, tenofovir disoproxil fumarate, darunavir/ritonavir, boceprevir, efavirenz and omeprazole. There is no predicted pharmacokinetic drug interaction between ISENTRESS HD and tenofovir alafenamide.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Women infected with HIV should be instructed not to breastfeed due to the potential for HIV transmission ( 8.2 ).
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the APR show no difference in the rate of overall birth defects for raltegravir compared to the background rate for major birth defects of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) (see Data ) .
The rate of miscarriage is not reported in the APR. The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15-20%. The background risk for major birth defects and miscarriage for the indicated population is unknown.
Methodological limitations of the APR include the use of MACDP as the external comparator group. The MACDP population is not disease-specific, evaluates women and infants from a limited geographic area, and does not include outcomes for births that occurred at <20 weeks gestation (see Data ) . In animal reproduction studies in rats and rabbits, no evidence of adverse developmental outcomes was observed with oral administration of raltegravir during organogenesis at doses that produced exposures up to approximately 4 times the maximum recommended human dose (MRHD) of 1200 mg (see Data ) .
Data Human Data Based on prospective reports from the APR of over 850 exposures to raltegravir during pregnancy resulting in live births (including over 450 exposures in the first trimester), there was no difference between the overall risk of birth defects for raltegravir compared with the background birth defect rate of 2.7% in the U.S. reference population of the MACDP. The prevalence of defects in live births was 3.1% (95% CI: 1.7% to 5.1%) following first trimester exposure to raltegravir-containing regimens and 3.7% (95% CI: 2.1% to 6.0%) following second and third trimester exposure to raltegravir-containing regimens.
There are limited data on the use of ISENTRESS 1200 mg (2 x 600 mg) once daily in pregnant women. Animal Data In a combined embryo/fetal and pre/postnatal development study, raltegravir was administered orally to rats at doses of 100, 300, 600 mg/kg/day on gestation day 6 to 20 or from gestation day 6 to lactation day 20. No effects on pre/postnatal development were observed up to the highest dose tested.
Embryo-fetal findings were limited to an increase in the incidence of supernumerary ribs in the 600 mg/kg/day group. Systemic exposure (AUC) at 600 mg/kg/day was approximately 3 times higher than exposure at the MRHD of 1200 mg. In pregnant rabbits, raltegravir was administered orally at doses of 100, 500, or 1000 mg/kg/day during the gestation days 7 to 20.
No embryo/fetal effects were noted up to the highest dose of 1000 mg/kg/day. Systemic exposure (AUC) at 1000 mg/kg/day was approximately 4 times higher than exposures at the MRHD of 1200 mg. In both species, raltegravir has been shown to cross the placenta, with fetal plasma concentrations observed in rats approximately 1.5 to 2.5 times greater than in maternal plasma and fetal plasma concentrations in rabbits approximately 2% that of maternal concentrations on gestation day 20.
8.2Lactation Risk Summary The Centers for Disease Control and Prevention recommend that HIV-1 infected mothers in the United States not breastfeed their infants to avoid risking postnatal transmission of HIV-1 infection. There are no data on the presence of raltegravir in human milk, the effects on the breastfed infant, or the effects on milk production. When administered to lactating rats, raltegravir was present in milk (see Data ).
Because of the potential for: 1) HIV transmission (in HIV-negative infants), 2) developing viral resista…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the APR show no difference in the rate of overall birth defects for raltegravir compared to the background rate for major birth defects of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) (see Data ) .
The rate of miscarriage is not reported in the APR. The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15-20%. The background risk for major birth defects and miscarriage for the indicated population is unknown.
Methodological limitations of the APR include the use of MACDP as the external comparator group. The MACDP population is not disease-specific, evaluates women and infants from a limited geographic area, and does not include outcomes for births that occurred at <20 weeks gestation (see Data ) . In animal reproduction studies in rats and rabbits, no evidence of adverse developmental outcomes was observed with oral administration of raltegravir during organogenesis at doses that produced exposures up to approximately 4 times the maximum recommended human dose (MRHD) of 1200 mg (see Data ) .
Data Human Data Based on prospective reports from the APR of over 850 exposures to raltegravir during pregnancy resulting in live births (including over 450 exposures in the first trimester), there was no difference between the overall risk of birth defects for raltegravir compared with the background birth defect rate of 2.7% in the U.S. reference population of the MACDP. The prevalence of defects in live births was 3.1% (95% CI: 1.7% to 5.1%) following first trimester exposure to raltegravir-containing regimens and 3.7% (95% CI: 2.1% to 6.0%) following second and third trimester exposure to raltegravir-containing regimens.
There are limited data on the use of ISENTRESS 1200 mg (2 x 600 mg) once daily in pregnant women. Animal Data In a combined embryo/fetal and pre/postnatal development study, raltegravir was administered orally to rats at doses of 100, 300, 600 mg/kg/day on gestation day 6 to 20 or from gestation day 6 to lactation day 20. No effects on pre/postnatal development were observed up to the highest dose tested.
Embryo-fetal findings were limited to an increase in the incidence of supernumerary ribs in the 600 mg/kg/day group. Systemic exposure (AUC) at 600 mg/kg/day was approximately 3 times higher than exposure at the MRHD of 1200 mg. In pregnant rabbits, raltegravir was administered orally at doses of 100, 500, or 1000 mg/kg/day during the gestation days 7 to 20.
No embryo/fetal effects were noted up to the highest dose of 1000 mg/kg/day. Systemic exposure (AUC) at 1000 mg/kg/day was approximately 4 times higher than exposures at the MRHD of 1200 mg. In both species, raltegravir has been shown to cross the placenta, with fetal plasma concentrations observed in rats approximately 1.5 to 2.5 times greater than in maternal plasma and fetal plasma concentrations in rabbits approximately 2% that of maternal concentrations on gestation day 20.
🧒 Pediatric Use ▾
8.4Pediatric Use ISENTRESS HIV-1 Infected Children The safety, tolerability, pharmacokinetic profile, and efficacy of twice daily ISENTRESS were evaluated in HIV-1 infected infants, children and adolescents 4 weeks to 18 years of age in an open-label, multicenter clinical trial, IMPAACT P1066 [see Dosage and Administration (2.3) , Clinical Pharmacology (12.3) and Clinical Studies (14.4) ] . The safety profile was comparable to that observed in adults [see Adverse Reactions (6.1) ] . HIV-1 Exposed Neonates The safety and pharmacokinetics of ISENTRESS for oral suspension were evaluated in 42 full-term HIV-1 exposed neonates at high risk of acquiring HIV-1 infection in a Phase 1, open-label, multicenter clinical study, IMPAACT P1110.
Cohort 1 neonates received 2 single doses of ISENTRESS for oral suspension: the first within 48 hours of birth and the second at 7 to 10 days of age. Cohort 2 neonates received daily dosing of ISENTRESS for oral suspension for 6 weeks: 1.5 mg/kg once daily starting within 48 hours of birth through day 7 (week 1); 3 mg/kg twice daily on days 8 to 28 of age (weeks 2 to 4); and 6 mg/kg twice daily on days 29 to 42 of age (weeks 5 and 6). Sixteen neonates were enrolled in Cohort 1 (10 were exposed and 6 were unexposed to raltegravir in utero ) and 26 in Cohort 2 (all unexposed to raltegravir in utero ); all infants received a standard of care antiretroviral drug regimen for prevention of mother to child transmission.
All enrolled neonates were followed for safety for a duration of 24 weeks. The 42 infants were 52% male, 69% Black and 12% Caucasian. HIV-1 status was assessed by nucleic acid test at birth, week 6 and week 24; all patients were HIV-1 negative at completion of the study.
The safety profile was comparable to that observed in adults [see Adverse Reactions (6.1) ] . ISENTRESS is not recommended in pre-term neonates or in pediatric patients weighing less than 2 kg. ISENTRESS HD ISENTRESS HD once daily has not been studied in pediatric patients.
However population PK modeling and simulation support the use of 1200 mg (2 × 600 mg) once daily in pediatric patients weighing at least 40 kg [see Clinical Pharmacology (12.3) ] .
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of ISENTRESS/ISENTRESS HD did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger subjects. In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE In the event of an overdose, it is reasonable to employ the standard supportive measures, e.g., remove unabsorbed material from the gastrointestinal tract, employ clinical monitoring (including obtaining an electrocardiogram), and institute supportive therapy if required. The extent to which ISENTRESS may be dialyzable is unknown.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Raltegravir is an HIV-1 antiviral drug [see Microbiology (12.4) ] .
12.2Pharmacodynamics In a monotherapy study raltegravir (400 mg twice daily) demonstrated rapid antiviral activity with mean viral load reduction of 1.66 log 10 copies/mL by day 10. Cardiac Electrophysiology At a dose 1.33 times the maximum approved recommended dose (and peak concentrations 1.25-fold higher than the maximum approved dose), raltegravir does not prolong the QT interval or PR interval to any clinically relevant extent.
12.3Pharmacokinetics Adults Absorption Raltegravir, given 400 mg twice daily, is absorbed with a T max of approximately 3 hours postdose in the fasted state in healthy subjects. Raltegravir 1200 mg once daily is rapidly absorbed with median T max of ~1.5 to 2 hours in the fasted state. Raltegravir increases dose proportionally (AUC and C max ) or slightly less than dose proportionally (C 12hr ) over the dose range 100 mg to 1600 mg.
The absolute bioavailability of raltegravir has not been established. The chewable tablet and oral suspension have higher oral bioavailability compared to the 400 mg film-coated tablet. Relative to the raltegravir 400 mg formulation, the raltegravir 600 mg formulation has higher relative bioavailability.
Steady-state is generally reached in 2 days, with little to no accumulation with multiple-dose administration for the 400 mg twice daily and 1200 once daily formulation. Effect of Food on Oral Absorption The food effect of various formulations are presented in Table 12. Table 12: Effect of Food on the Pharmacokinetics of Raltegravir Formulations PK parameter ratio (fed/fasted) Formulation Meal Type AUC Ratio (90% CI) C max Ratio (90% CI) C min Ratio (90% CI) Low fat meal: 300 Kcal, 2.5 g fat Moderate fat meal: 600 Kcal, 21 g fat High fat meal: 825 Kcal, 52 g fat 400 mg twice daily Low Fat 0.54 (0.41-0.71) 0.48 (0.35-0.67) 0.86 (0.54-1.36) Moderate Fat 1.13 (0.85-1.49) 1.05 (0.75-1.46) 1.66 (1.04-2.64) High Fat 2.11 (1.60-2.80) 1.96 (1.41-2.73) 4.13 (2.60-6.57) 1200 mg once daily Low Fat 0.58 (0.46-0.74) 0.48 (0.37-0.62) 0.84 (0.63-1.10) High Fat 1.02 (0.86-1.21) 0.72 (0.58-0.90) 0.88 (0.66-1.18) Chewable tablet High Fat 0.94 (0.78-1.14) 0.38 (0.28-0.52) 2.88 (2.21-3.75) Oral suspension The effect of food on oral suspension was not studied.
Distribution Raltegravir is approximately 83% bound to human plasma protein over the concentration range of 2 to 10 µM. In one study of HIV-1 infected subjects who received raltegravir 400 mg twice daily, raltegravir was measured in the cerebrospinal fluid. In the study (n=18), the median cerebrospinal fluid concentration was 5.8% (range 1 to 53.5%) of the corresponding plasma concentration.
This median proportion was approximately 3-fold lower than the free fraction of raltegravir in plasma. The clinical relevance of this finding is unknown. Metabolism and Excretion The apparent terminal half-life of raltegravir is approximately 9 hours, with a shorter α-phase half-life (~1 hour) accounting for much of the AUC.
Following administration of an oral dose of radiolabeled raltegravir, approximately 51 and 32% of the dose was excreted in feces and urine, respectively. In feces, only raltegravir was present, most of which is likely derived from hydrolysis of raltegravir-glucuronide secreted in bile as observed in preclinical species. Two components, namely raltegravir and raltegravir-glucuronide, were detected in urine and accounted for approximately 9 and 23% of the dose, respectively.
The major circulating entity was raltegravir and represented approximately 70% of the total radioactivity; the remaining radioactivity in plasma was accounted for by raltegravir-glucuronide. The major mechanism of clearance of raltegravir in humans is UGT1A1-mediated glucuronidation. Table 13: Multiple-Dose Pharmacokinetic Parameters of Raltegravir Following the Administration of 400 mg Twice Daily and 1200 mg Once Daily in HIV-infected Sub…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Raltegravir is an HIV-1 antiviral drug [see Microbiology (12.4) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING ISENTRESS tablets 400 mg are pink, oval-shaped, film-coated tablets with "227" on one side. They are supplied as follows: NDC 0006-0227-61 unit-of-use bottles of 60. ISENTRESS HD tablets 600 mg are yellow, oval-shaped, film-coated tablets with corporate logo and "242" on one side and plain on the other side.
They are supplied as follows: NDC 0006-3080-01 unit-of-use bottles of 60. ISENTRESS tablets 100 mg are pale orange, oval-shaped, orange-banana flavored, chewable tablets scored on both sides and imprinted on one face with the corporate logo and "477" on opposite sides of the score. They are supplied as follows: NDC 0006-0477-61 unit-of-use bottles of 60.
ISENTRESS tablets 25 mg are pale yellow, round, orange-banana flavored, chewable tablets with the corporate logo on one side and "473" on the other side. They are supplied as follows: NDC 0006-0473-61 unit-of-use bottles of 60. ISENTRESS for oral suspension 100 mg is a white to off-white granular powder that may contain yellow or beige to tan particles, in child resistant single-use foil packets, packaged as A kit with two 1 mL syringes, two 3 mL syringes, two 10 mL syringes and two mixing cups.
It is supplied as follows: NDC 0006-3603-61 unit of use carton with 60 packets. NDC 0006-3603-01 individual packet. Storage and Handling 400 mg Film-coated Tablets, 600 mg Film-coated Tablets, Chewable Tablets and For Oral Suspension Store at 20-25°C (68-77°F); excursions permitted to 15-30°C (59-86°F).
See USP Controlled Room Temperature. 400 mg Film-coated Tablets, 600 mg Film-coated Tablets and Chewable Tablets Store in the original package with the bottle tightly closed. Keep the desiccant in the bottle to protect from moisture.
For Oral Suspension Store in the original container. Do not open foil packet until ready for use.
📦 Storage and Handling ▾
Storage and Handling 400 mg Film-coated Tablets, 600 mg Film-coated Tablets, Chewable Tablets and For Oral Suspension Store at 20-25°C (68-77°F); excursions permitted to 15-30°C (59-86°F). See USP Controlled Room Temperature. 400 mg Film-coated Tablets, 600 mg Film-coated Tablets and Chewable Tablets Store in the original package with the bottle tightly closed.
Keep the desiccant in the bottle to protect from moisture. For Oral Suspension Store in the original container. Do not open foil packet until ready for use.
📋 Description ▾
11 DESCRIPTION ISENTRESS contains raltegravir potassium, a human immunodeficiency virus integrase strand transfer inhibitor. The chemical name for raltegravir potassium is N -[(4-Fluorophenyl) methyl]-1,6-dihydro-5-hydroxy-1-methyl-2-[1-methyl-1-[[(5-methyl-1,3,4-oxadiazol-2-yl)carbonyl]amino]ethyl]-6-oxo-4-pyrimidinecarboxamide monopotassium salt. The empirical formula is C 20 H 20 FKN 6 O 5 and the molecular weight is 482.51.
The structural formula is: Raltegravir potassium is a white to off-white powder. It is soluble in water, slightly soluble in methanol, very slightly soluble in ethanol and acetonitrile and insoluble in isopropanol. Each 400 mg film-coated tablet of ISENTRESS for oral administration contains 434.4 mg of raltegravir (as potassium salt), equivalent to 400 mg of raltegravir free phenol and the following inactive ingredients: calcium phosphate dibasic anhydrous, hypromellose 2208, lactose monohydrate, magnesium stearate, microcrystalline cellulose, poloxamer 407 (contains 0.01% butylated hydroxytoluene as antioxidant), sodium stearyl fumarate.
In addition, the film coating contains the following inactive ingredients: black iron oxide, polyethylene glycol 3350, polyvinyl alcohol, red iron oxide, talc and titanium dioxide. Each 600 mg film-coated tablet of ISENTRESS HD for oral administration contains 651.6 mg of raltegravir (as potassium salt), equivalent to 600 mg of raltegravir free phenol and the following inactive ingredients: croscarmellose sodium, hypromellose 2910, magnesium stearate, microcrystalline cellulose. The film coating contains the following inactive ingredients: ferrosoferric oxide, hypromellose 2910, iron oxide yellow, lactose monohydrate, triacetin and titanium dioxide.
The tablet may also contain trace amount of carnauba wax. Each 100 mg chewable tablet of ISENTRESS for oral administration contains 108.6 mg of raltegravir (as potassium salt), equivalent to 100 mg of raltegravir free phenol and the following inactive ingredients: ammonium hydroxide, crospovidone, ethylcellulose 20 cP, fructose, hydroxypropyl cellulose, hypromellose 2910/6cP, magnesium stearate, mannitol, medium chain triglycerides, monoammonium glycyrrhizinate, natural and artificial flavors (orange, banana, and masking that contains aspartame), oleic acid, PEG 400, red iron oxide, saccharin sodium, sodium citrate dihydrate, sodium stearyl fumarate, sorbitol, sucralose and yellow iron oxide.
Each 25 mg chewable tablet of ISENTRESS for oral administration contains 27.16 mg of raltegravir (as potassium salt), equivalent to 25 mg of raltegravir free phenol and the following inactive ingredients: ammonium hydroxide, crospovidone, ethylcellulose 20 cP, fructose, hydroxypropyl cellulose, hypromellose 2910/6cP, magnesium stearate, mannitol, medium chain triglycerides, monoammonium glycyrrhizinate, natural and artificial flavors (orange, banana, and masking that contains aspartame), oleic acid, PEG 400, saccharin sodium, sodium citrate dihydrate, sodium stearyl fumarate, sorbitol, sucralose and yellow iron oxide.
Each packet of ISENTRESS for oral suspension 100 mg, contains 108.6 mg of raltegravir (as potassium salt), equivalent to 100 mg of raltegravir free phenol and the following inactive ingredients: ammonium hydroxide, banana with other natural flavors, carboxymethylcellulose sodium, crospovidone, ethylcellulose 20 cP, fructose, hydroxypropyl cellulose, hypromellose 2910/6cP, macrogol/PEG 400, magnesium stearate, maltodextrin, mannitol, medium chain triglycerides, microcrystalline cellulose, monoammonium glycyrrhizinate, oleic acid, sorbitol, sucralose and sucrose.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Severe and Potentially Life-threatening Rash Inform patients that severe and potentially life-threatening rash has been reported. Advise patients to immediately contact their healthcare provider if they develop rash.
Instruct patients to immediately stop taking ISENTRESS or ISENTRESS HD and other suspect agents, and seek medical attention if they develop a rash associated with any of the following symptoms as it may be a sign of a more serious reaction such as Stevens-Johnson syndrome, toxic epidermal necrolysis or severe hypersensitivity: fever, generally ill feeling, extreme tiredness, muscle or joint aches, blisters, oral lesions, eye inflammation, facial swelling, swelling of the eyes, lips, mouth, breathing difficulty, and/or signs and symptoms of liver problems (e.g., yellowing of the skin or whites of the eyes, dark or tea colored urine, pale colored stools/bowel movements, nausea, vomiting, loss of appetite, or pain, aching or sensitivity on the right side below the ribs).
Inform patients that if severe rash occurs, their physician will closely monitor them, order laboratory tests and initiate appropriate therapy. Immune Reconstitution Syndrome Advise patients to inform their healthcare provider immediately of any symptoms of infection, as in some patients with advanced HIV infection (AIDS), signs and symptoms of inflammation from previous infections may occur soon after anti-HIV treatment is started [see Warnings and Precautions (5.2) ] . Rhabdomyolysis Before patients begin ISENTRESS or ISENTRESS HD, ask them if they have a history of rhabdomyolysis, myopathy or increased creatine kinase or if they are taking medications known to cause these conditions such as statins, fenofibrate, gemfibrozil or zidovudine [see Adverse Reactions (6.1) ] .
Instruct patients to immediately report to their healthcare provider any unexplained muscle pain, tenderness, or weakness while taking ISENTRESS. Phenylketonuria Alert patients with phenylketonuria that ISENTRESS Chewable Tablets contain phenylalanine [see Warnings and Precautions (5.3) ] . Drug Interactions Inform patients that ISENTRESS or ISENTRESS HD may interact with some drugs and ask them to identify all their current medications including over-the-counter agents [see Drug Interactions (7.2) ] .
Missed Dosage Inform patients that it is important to take ISENTRESS or ISENTRESS HD on a regular dosing schedule as instructed by their healthcare provider and to avoid missing doses as it can result in development of resistance [see Dosage and Administration (2) ] . Important Administration Instructions Film-Coated Tablets Inform patients that the film-coated tablets must be swallowed whole. Oral Suspension Instruct parents and/or caregivers to read the Instructions for Use before preparing and administering ISENTRESS for oral suspension to pediatric patients.
Instruct parents and/or caregivers that ISENTRESS for oral suspension should be administered within 30 minutes of mixing. Chewable Tablets Inform parents and/or caregivers that the chewable tablets can be chewed or swallowed whole. Additionally, the 25 mg chewable tablet may be crushed.
Instruct parents and/or caregivers that ISENTRESS 25 mg chewable tablets, if crushed, should be administered immediately [see Dosage and Administration (2.1) ] . Pregnancy Registry Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ISENTRESS or ISENTRESS HD during pregnancy [see Use in Specific Populations (8.1) ] . Lactation Instruct women with HIV-1 infection not to breastfeed because HIV-1 can be passed to the baby in the breast milk [see Use in Specific Populations (8.2) ] .