
Winrevair Sotatercept-Csrk Kit — NDC 0006-5091-01 (Billing 00006-5091-01)
This is a package of Winrevair Sotatercept-Csrk Kit from Merck Sharp & Dohme LLC, marketed since Mar 2024 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0006-5091-01 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0006 labeler · 5091 product · 01 package
- Package marketed since
- Mar 26, 2024
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 0006509101 3
- Medicaid fills, this package
- 3,705 prescriptions in the last four reported quarters
- FDA record last changed
- Oct 8, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 085894
- GCN: 55487
- HICL (First Databank): 049475
- AHFS class code: 48:92.00.00
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
Clinical
Sotatercept-csrk is used to treat pulmonary arterial hypertension (PAH; high blood pressure in the vessels carrying blood to the lungs, causing shortness of breath, dizziness, and tiredness) in adults. Sotatercept-csrk may improve the ability to exercise and slow the worsening of symptoms in individuals with PAH. Sotatercept-csrk is in a class of medications called activin signaling inhibitors. It works by blocking certain substances to slow or stop the tissue changes that happen with PAH.
Read the full MedlinePlus article ↗- It treats pulmonary arterial hypertension (PAH) in adults. That's high blood pressure in the lung arteries. It's meant to improve how well you can be active and lower the chance of...
- It's an injection under the skin, about once every 3 weeks. Your dose is based on your weight and starts lower. Your care team will follow your blood counts closely and may adjust...
- This medicine can raise your hemoglobin and lower your platelets. Both can matter for clotting and bleeding. Labs are checked before each of your first 5 doses and periodically aft...
- Common ones include headache, nosebleeds, rash, diarrhea, dizziness, skin redness, small visible red blood vessels and bleeding gums. Call your care team if bleeding is serious or...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $14,789.63 | — |
| Medicare drug plans payPart D · Q2 2026 | $15,539.39 | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00006-5091-01 You're viewing this Main listing | 1 KIT in 1 CARTON * 1 mL in 1 VIAL, SINGLE-DOSE * 1.3 mL in 1 SYRINGE | 2024-03-26 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Winrevairthis 00006-5091-01 | Merck | 1 kit | — | — | FDA listed | — |
| Winrevair 00006-5090-01 | Merck | 1 kit | — | — | FDA listed | — |
| Winrevair 00006-5087-01 | Merck | 1 kit | — | — | FDA listed | — |
| Winrevair 00006-5088-01 | Merck | 1 kit | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Purple Book · refreshed Oct 5, 2026
- CMS NADAC weekly file
Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Mar 26, 2036 |
Is there a biosimilar for WINREVAIR 60 MG ONE-VIAL KIT?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
- FDA Purple Book · refreshed Oct 5, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Sotatercept-Csrk inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Merck Sharp & Dohme LLC labeler code 00006
- Winrevair Sotatercept-Csrk Kit NDC 0006-5087-01
- Winrevair Sotatercept-Csrk Kit NDC 0006-5088-01
- Winrevair Sotatercept-Csrk Kit NDC 0006-5090-01
- IDVYNSO Doravirine, Islatravir 100 mg; .25 mg Tablet, Film Coated NDC 0006-5092-01
- Welireg belzutifan 40 mg Tablet, Film Coated NDC 0006-5331-01
- Steglatro ertugliflozin 5 mg Tablet, Film Coated NDC 0006-5363-03
- Steglatro ertugliflozin 15 mg Tablet, Film Coated NDC 0006-5364-03
- Steglujan ertugliflozin and sitagliptin 5 mg; 100 mg Tablet, Film Coated NDC 0006-5367-03
- Steglujan ertugliflozin and sitagliptin 15 mg; 100 mg Tablet, Film Coated NDC 0006-5368-03
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE WINREVAIR™ is indicated for the treatment of adults with pulmonary arterial hypertension (PAH, Group 1 pulmonary hypertension) to improve exercise capacity and World Health Organization (WHO) functional class (FC), and reduce the risk of clinical worsening events including hospitalization for PAH, lung transplantation and death [see Clinical Studies (14.1) ] . WINREVAIR is an activin signaling inhibitor indicated for the treatment of adults with pulmonary arterial hypertension (PAH, WHO Group 1 pulmonary hypertension) to improve exercise capacity and WHO functional class (FC), and reduce the risk of clinical worsening events, including hospitalization for PAH, lung transplantation and death.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended starting dose is 0.3 mg/kg by subcutaneous injection. ( 2.1 ) The recommended target dose is 0.7 mg/kg every 3 weeks by subcutaneous injection. ( 2.2 ) Dosage modifications due to increased hemoglobin (Hgb) and decreased platelets may be necessary.
Check Hgb and platelets before each dose for the first 5 doses, or longer if values are unstable, and monitor periodically thereafter. ( 2.3 ) See full prescribing information for preparation and administration instructions. ( 2.4 )
2.1Recommended Starting Dosage WINREVAIR is administered once every 3 weeks by subcutaneous injection according to patient body weight. The starting dose of WINREVAIR is 0.3 mg/kg. Obtain hemoglobin (Hgb) and platelet count prior to the first dose of WINREVAIR.
Do not initiate treatment if platelet count is <50,000/mm 3 (<50 x 10 9 /L) [see Dosage and Administration (2.3) ] . Injection volume for starting dose is calculated based on patient weight as follows: Injection Volume (mL) = Weight (kg) x 0.3 mg/kg 50 mg/mL Injection volume should be rounded to the nearest 0.1 mL. For example: (70 kg x 0.3 mg/kg) ÷ 50 mg/mL = 0.42 mL, rounds to 0.4 mL See Table 1 for selecting the appropriate kit based on calculated injection volume for starting dose.
Table 1: Kit Type Based on Injection Volume for Dose of 0.3 mg/kg Injection Volume (mL) Kit Type 0.2 to 0.9 45 mg kit (containing 1 x 45 mg vial) 1 to 1.1 60 mg kit (containing 1 x 60 mg vial)
2.2Recommended Target Dosage After verifying acceptable Hgb and platelet count, increase to the target dose of 0.7 mg/kg. Continue treatment at 0.7 mg/kg every 3 weeks unless dosage adjustments are required [see Dosage and Administration (2.3) ] . Injection volume for target dose is calculated based on patient weight as follows: Injection Volume (mL) = Weight (kg) x 0.7 mg/kg 50 mg/mL Injection volume should be rounded to the nearest 0.1 mL.
For example: (70 kg x 0.7 mg/kg) ÷ 50 mg/mL = 0.98 mL, rounds to 1 mL See Table 2 for selecting the appropriate kit based on calculated injection volume for target dose. Table 2: Kit Type Based on Injection Volume for Dose of 0.7 mg/kg Injection Volume (mL) Kit Type 0.4 to 0.9 45 mg kit (containing 1 x 45 mg vial) 1 to 1.2 60 mg kit (containing 1 x 60 mg vial) 1.3 to 1.8 90 mg kit (containing 2 x 45 mg vials) 1.9 to 2.4 120 mg kit (containing 2 x 60 mg vials) Missed Dose, Overdose, and Underdose If a dose of WINREVAIR is missed, administer as soon as possible.
If the missed dose of WINREVAIR is not administered within 3 days of the scheduled date, adjust the schedule to maintain 3-week dosing intervals. In case of an overdose, monitor for erythrocytosis [see Overdosage (10) ] .
2.3Dosage Modifications Due to Hemoglobin Increase or Platelet Count Decrease Check Hgb and platelet count before each dose for the first 5 doses, or longer if values are unstable. Thereafter, monitor Hgb and platelet count periodically [see Warnings and Precautions (5.1 , 5.2) ] . Delay treatment for at least 3 weeks if any of the following occur: Hgb increases >2.0 g/dL from the previous dose and is above ULN.
Hgb increases >4.0 g/dL from baseline. Hgb increases >2.0 g/dL above ULN. Platelet count decreases to <50,000/mm 3 (<50 x 10 9 /L).
Recheck Hgb and platelet count before reinitiating treatment. For treatment delays lasting >9 weeks, restart treatment at 0.3 mg/kg, and escalate to 0.7 mg/kg after verifying acceptable Hgb and platelet count.
2.4Preparation and Administration Administration is subject to monitoring of hemoglobin and platelet count [see Dosage and Administration (2.3) , Warnings and Precautions (5.1 , 5.2) ] . WINREVAIR is intended for use under the guidance of a healthcare professional. Patients and caregivers may administer WINREVAIR when considered appropriate and when they receive training and follow-up from the healthcare provider (HCP) on how to reconstitute, prepare, measure, and inject WINREVAIR [see Patient Counseling Information (17) ] .… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For injection: 45 mg white to off-white lyophilized cake or powder appearance in a single-dose vial. For injection: 60 mg white to off-white lyophilized cake or powder appearance in a single-dose vial. For injection: 45 mg lyophilized cake or powder in a single-dose vial ( 3 ) For injection: 60 mg lyophilized cake or powder in a single-dose vial ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Erythrocytosis: If severe, may increase the risk of thromboembolic events and hyperviscosity syndrome. Monitor Hgb before each dose for the first 5 doses, or longer if values are unstable, and periodically thereafter to determine if dose adjustments are required. ( 5.1 ) Severe Thrombocytopenia: May increase the risk of bleeding.
Monitor platelets before each dose for the first 5 doses, or longer if values are unstable, and periodically thereafter to determine if dose adjustments are required. ( 5.2 ) Serious Bleeding: Serious bleeding events were reported and were more likely with concomitant prostacyclin and/or antithrombotic agents, or with low platelet counts. Do not administer WINREVAIR if the patient is experiencing serious bleeding.
( 5.3 ) Embryo-Fetal Toxicity: May cause fetal harm. Advise females of reproductive potential of the potential risk to a fetus and use of effective contraception. ( 5.4 , 8.1 , 8.3 ) Impaired Fertility: May impair female and male fertility.
( 5.5 , 8.3 , 13.1 )
5.1Erythrocytosis WINREVAIR may increase hemoglobin. Severe erythrocytosis may increase the risk of thromboembolic events or hyperviscosity syndrome. In clinical studies, moderate elevations in Hgb (>2 g/dL above ULN) occurred in 15% of patients taking WINREVAIR while no elevations ≥4 g/dL above ULN were observed.
Monitor Hgb before each dose for the first 5 doses, or longer if values are unstable, and periodically thereafter, to determine if dose adjustments are required [see Dosage and Administration (2.3) , Adverse Reactions (6.1) ] .
5.2Severe Thrombocytopenia WINREVAIR may decrease platelet count. Severe thrombocytopenia may increase the risk of bleeding. In clinical studies, severe thrombocytopenia (platelet count <50,000/mm 3 [<50 x 10 9 /L]) occurred in 3% to 6% of patients taking WINREVAIR.
Thrombocytopenia occurred more frequently in patients also receiving prostacyclin infusion. Do not initiate treatment if platelet count is <50,000/mm 3 [see Dosage and Administration (2.3) ] . Monitor platelets before each dose for the first 5 doses, or longer if values are unstable, and periodically thereafter to determine whether dose adjustments are required. [see Dosage and Administration (2.3) , Adverse Reactions (6.1) ] .
5.3Serious Bleeding In clinical studies, serious bleeding (e.g., gastrointestinal, intracranial hemorrhage) was reported in 4% vs 1% (STELLAR) and 7% vs 5% (ZENITH) of patients taking WINREVAIR vs placebo, respectively [see Clinical Studies (14.1) ] . Patients with serious bleeding were more likely to be on prostacyclin background therapy and/or antithrombotic agents, or have low platelet counts. Advise patients about signs and symptoms of blood loss.
Evaluate and treat bleeding accordingly. Do not administer WINREVAIR if the patient is experiencing serious bleeding [see Warnings and Precautions (5.2) , Adverse Reactions (6.1) ] .
5.4Embryo-Fetal Toxicity Based on findings in animal reproduction studies, WINREVAIR may cause fetal harm when administered to a pregnant woman. In animal reproduction studies, administration of WINREVAIR to pregnant rats and rabbits during organogenesis resulted in adverse developmental outcomes, including increased embryo-fetal mortality, alterations to growth, and structural variations at exposures 4-fold and 0.6-fold (based on area under the curve [AUC]) those occurring at the maximum recommended human dose (MRHD), respectively.
Advise pregnant women of the potential risk to a fetus. Advise females of reproductive potential to use an effective method of contraception during treatment with WINREVAIR and for at least 4 months after the final dose [see Use in Specific Populations (8.1 , 8.3) ] .
5.5Impaired Fertility Based on findings in animals, WINREVAIR may impair female and male fertility. Advise patients on the potential effects on fertility [see Use in Specific Populations (8.3) , Nonclinical Toxicology (13.1) ].
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Erythrocytosis [see Warnings and Precautions (5.1) ] Severe Thrombocytopenia [see Warnings and Precautions (5.2) ] Serious Bleeding [see Warnings and Precautions (5.3) ] Embryo-Fetal Toxicity [see Warnings and Precautions (5.4) ] Impaired Fertility [see Warnings and Precautions (5.5) ] The most common (≥10% in patients receiving WINREVAIR and 5% more than placebo) adverse reactions were infections, epistaxis, telangiectasia, diarrhea, headache, rash, increased hemoglobin, dizziness, erythema, and gingival bleeding.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Merck Sharp & Dohme LLC at 1-877-888-4231 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. STELLAR The following data reflect exposure to WINREVAIR in the STELLAR trial. Adult PAH patients with WHO FC II or III (n=323) were randomized in a 1:1 ratio to receive WINREVAIR or placebo in combination with background standard of care therapies.
Patients received a starting dose of 0.3 mg/kg via SC injection and the dose was increased to the target dose of 0.7 mg/kg administered once every 3 weeks for 24 weeks. After completing the primary 24-week treatment phase, patients continued into a long-term double-blind (LTDB) treatment period, maintaining their randomized treatment assignment, until all patients completed the primary treatment period. The median duration of treatment was 273 days in the placebo group and 313 days in the WINREVAIR group [see Clinical Studies (14.1) ].
The most common adverse reactions occurring in STELLAR (≥10% for WINREVAIR and at least 5% more than placebo) are shown in Table 3 . Table 3: Adverse Reactions ≥10% in Patients Receiving WINREVAIR and at least 5% More Than Placebo in STELLAR Double-blind placebo-controlled period + Long-term double-blind period of STELLAR Adverse reaction WINREVAIR N=163 Placebo N=160 Headache 40 (24.5) 28 (17.5) Epistaxis 36 (22.1) 3 (1.9) Rash 33 (20.2) 13 (8.1) Telangiectasia 27 (16.6) 7 (4.4) Diarrhea 25 (15.3) 16 (10.0) Dizziness 24 (14.7) 10 (6.3) Erythema 22 (13.5) 5 (3.1) Increased Hemoglobin Increases in Hgb were managed by dose delays (10%), dose reductions (6%), or both (5%).
Shifts in Hgb from normal to above normal levels occurred in 87 (53%) patients receiving WINREVAIR and in 23 (14%) patients receiving placebo. Thrombocytopenia Decreases in platelets were managed by dose delays (2%), dose reductions (2%), or both (2%). Shifts in platelet count from normal to below normal occurred in 40 (25%) patients receiving WINREVAIR and in 26 (16%) patients receiving placebo.
Telangiectasia In patients exposed to WINREVAIR who experienced telangiectasia, the median time to onset was 36.1 weeks. Increased Blood Pressure In patients taking WINREVAIR, mean systolic/diastolic blood pressure increased from baseline by 2.2/4.9 mmHg at 24 weeks. In patients taking placebo, the change from baseline in mean blood pressure was -1.6/-0.6 mmHg.
Treatment Discontinuation The incidences of treatment discontinuations due to an adverse reaction were 4% in the WINREVAIR group and 7% in the placebo group. No specific adverse reactions causing treatment discontinuations occurred with a frequency greater than 1% and more often in the WINREVAIR group. ZENITH The following data reflect exposure to WINREVAIR in the ZENITH trial.
Adult PAH patients with WHO FC III or IV at high risk of mortality (n=172) were randomized in a 1:1 ratio to treatment with WINREVAIR or placebo in combination with background standard of care therapies. Patients who did not experience a primary endpoint event remained in the Double-Blind Placebo-Controll… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding not recommended. ( 8.2 )
8.1Pregnancy Risk Summary Based on findings in animal reproduction studies, WINREVAIR may cause fetal harm when administered to a pregnant woman. There are risks to the mother and the fetus associated with pulmonary arterial hypertension in pregnancy (see Clinical Considerations ) . There are no available data on WINREVAIR use in pregnant women to inform a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes.
In animal reproduction studies, administration of WINREVAIR to pregnant rats and rabbits during the period of organogenesis resulted in adverse developmental outcomes, including embryo-fetal mortality, alterations to growth, and structural variations at exposures 4-fold and 0.6-fold (based on area under the curve [AUC]) above those occurring at the maximum recommended human dose (MRHD), respectively (see Data ) . Advise pregnant women of the potential risk to a fetus [see Use in Specific Populations (8.3) ] . The background risk of major birth defects and miscarriage for the indicated population is not known.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Report exposure during pregnancy or lactation to the Merck Sharp & Dohme, LLC Adverse Event reporting line at 1-877-888-4231.
Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk In patients with pulmonary arterial hypertension, pregnancy is associated with an increased rate of maternal and fetal morbidity and mortality, including spontaneous abortion, intrauterine growth restriction, and premature labor. Data Animal Data In embryo-fetal developmental toxicity studies, pregnant animals were dosed subcutaneously with sotatercept-csrk during the period of organogenesis. Sotatercept-csrk was administered to rats on gestation days 6 and 13 at doses of 5, 15, or 50 mg/kg and to rabbits on gestation days 7 and 14 at doses of 0.5, 1.5, or 5 mg/kg.
Effects in both species included reductions in numbers of live fetuses and fetal body weights, delays in ossification, and increases in resorptions and post-implantation losses. In rats and rabbits, these effects were observed at exposures (based on area under the curve [AUC]) approximately 4-fold and 0.6-fold the maximum recommended human dose (MRHD), respectively. In rats only, skeletal variations (increased number of supernumerary ribs and changes in the number of thoracic or lumbar vertebrae) occurred at an exposure 15-fold the human exposure at the MRHD.
In a prenatal and postnatal development study in rats, sotatercept-csrk was administered subcutaneously at doses of 1.5 and 5 mg/kg on gestation days 6 and 13, or at dosages of 1.5, 5, or 10 mg/kg during lactation on days 1, 8, and 15. There were no adverse effects in first filial generation (F1) pups from dams dosed during gestation at estimated exposures up to 2-fold the MRHD. In F1 pups from dams dosed during lactation, decreases in pup weight correlated with delays in sexual maturation at estimated exposures (based on AUC) ≥2-fold the MRHD.
8.2Lactation Risk Summary There are no data on the presence of sotatercept-csrk in human milk, the effects on the breastfed infant, or the effects on milk production. Because of the potential for serious adverse reactions in the breastfed child, advise patients that breastfeeding is not recommended during treatment with WINREVAIR, and for 4 months after the final dose.
8.3Females and Males of Reproductive Potential WINREVAIR may cause fetal harm when administered to pregnant women [see Use in Specific Populations (8.1) ] . Pregnancy Testing Pregnancy testing is recommended for females of reproductive potential before starting WINREVAIR treatment. Contraception Females Advise… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings in animal reproduction studies, WINREVAIR may cause fetal harm when administered to a pregnant woman. There are risks to the mother and the fetus associated with pulmonary arterial hypertension in pregnancy (see Clinical Considerations ) . There are no available data on WINREVAIR use in pregnant women to inform a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes.
In animal reproduction studies, administration of WINREVAIR to pregnant rats and rabbits during the period of organogenesis resulted in adverse developmental outcomes, including embryo-fetal mortality, alterations to growth, and structural variations at exposures 4-fold and 0.6-fold (based on area under the curve [AUC]) above those occurring at the maximum recommended human dose (MRHD), respectively (see Data ) . Advise pregnant women of the potential risk to a fetus [see Use in Specific Populations (8.3) ] . The background risk of major birth defects and miscarriage for the indicated population is not known.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Report exposure during pregnancy or lactation to the Merck Sharp & Dohme, LLC Adverse Event reporting line at 1-877-888-4231.
Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk In patients with pulmonary arterial hypertension, pregnancy is associated with an increased rate of maternal and fetal morbidity and mortality, including spontaneous abortion, intrauterine growth restriction, and premature labor. Data Animal Data In embryo-fetal developmental toxicity studies, pregnant animals were dosed subcutaneously with sotatercept-csrk during the period of organogenesis. Sotatercept-csrk was administered to rats on gestation days 6 and 13 at doses of 5, 15, or 50 mg/kg and to rabbits on gestation days 7 and 14 at doses of 0.5, 1.5, or 5 mg/kg.
Effects in both species included reductions in numbers of live fetuses and fetal body weights, delays in ossification, and increases in resorptions and post-implantation losses. In rats and rabbits, these effects were observed at exposures (based on area under the curve [AUC]) approximately 4-fold and 0.6-fold the maximum recommended human dose (MRHD), respectively. In rats only, skeletal variations (increased number of supernumerary ribs and changes in the number of thoracic or lumbar vertebrae) occurred at an exposure 15-fold the human exposure at the MRHD.
In a prenatal and postnatal development study in rats, sotatercept-csrk was administered subcutaneously at doses of 1.5 and 5 mg/kg on gestation days 6 and 13, or at dosages of 1.5, 5, or 10 mg/kg during lactation on days 1, 8, and 15. There were no adverse effects in first filial generation (F1) pups from dams dosed during gestation at estimated exposures up to 2-fold the MRHD. In F1 pups from dams dosed during lactation, decreases in pup weight correlated with delays in sexual maturation at estimated exposures (based on AUC) ≥2-fold the MRHD.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of WINREVAIR have not been established in patients less than 18 years of age.
🧓 Geriatric Use ▾
8.5Geriatric Use A total of 127 patients ≥65 years of age participated in clinical studies for PAH, of which 99 (78%) were treated with WINREVAIR. No differences in efficacy of WINREVAIR were observed between the <65-year-old and ≥65-year-old subgroups. With the exception of bleeding events (a collective group of adverse events of clinical interest), there were no differences in safety between the <65-year-old and ≥65-year-old subgroups.
Bleeding events occurred more commonly in the older WINREVAIR subgroup, but with no imbalance between age subgroups for any specific bleeding event. Clinical studies of WINREVAIR did not include sufficient numbers of patients aged 75 and older to determine whether they respond differently from younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE In healthy volunteers, WINREVAIR dosed at 1 mg/kg resulted in increases in Hgb associated with hypertension; both improved with phlebotomy. In the event of overdose, monitor closely for increases in Hgb and blood pressure, and provide supportive care as appropriate. WINREVAIR is not dialyzable.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Sotatercept-csrk, a recombinant activin receptor type IIA-Fc (ActRIIA-Fc) fusion protein, is an activin signaling inhibitor that binds to activin A and other TGF- β superfamily ligands. As a result, sotatercept-csrk improves the balance between the pro-proliferative (ActRIIA/Smad2/3-mediated) and anti-proliferative (BMPRII/Smad1/5/8-mediated) signaling to modulate vascular proliferation. In rat models of PAH, a sotatercept-csrk analog reduced inflammation and inhibited proliferation of endothelial and smooth muscle cells in diseased vasculature.
These cellular changes were associated with thinner vessel walls, partial reversal of right ventricular remodeling, and improved hemodynamics.
12.2Pharmacodynamics STELLAR A greater decrease from baseline in pulmonary vascular resistance (PVR) was observed in the WINREVAIR group compared to the placebo group. The median treatment difference in PVR between sotatercept-csrk and placebo was -235 dynes*sec/cm 5 (95% CI: -288, -181). Sotatercept-csrk steady state exposure at 0.7 mg/kg dose was associated with near maximal reduction in PVR based on exposure-response analysis.
A greater decrease from baseline in NT-proBNP was observed in the WINREVAIR group compared to the placebo group. The median treatment difference in NT-proBNP between the sotatercept-csrk and placebo was -442 pg/mL (95% CI: -574, -310). ZENITH The median treatment difference in change in PVR from baseline between the sotatercept and placebo groups after 24 weeks was -340 dynes*sec/cm 5 (95% CI: -511, -168).
The median treatment difference in change in NT-proBNP from baseline between the sotatercept-csrk and placebo groups after 24 weeks was -2339 pg/mL (95% CI: -3379, -1299). The median treatment difference in change from baseline in mean pulmonary artery pressure (mPAP) between the sotatercept-csrk and placebo groups after 24 weeks was -21.2 mm Hg (95% CI: -27.8, -14.6).
12.3Pharmacokinetics Following subcutaneous administration of 0.7 mg/kg WINREVAIR every three weeks to PAH patients (PULSAR, SPECTRA, and STELLAR), the steady state geometric mean (%CV) area under the time concentration curve (AUC) is 171.3 mcg×d/mL (34.2%), and peak concentration (C max ) is 9.7 mcg/mL (30%). Sotatercept-csrk AUC and C max increased proportionally with dose. Steady state is achieved after approximately 15 weeks following initiation of multiple dosing.
The accumulation ratio of sotatercept-csrk AUC is approximately 2.2. Sotatercept-csrk pharmacokinetics were similar in PAH participants in ZENITH. Absorption Following subcutaneous administration, the absolute bioavailability of sotatercept-csrk is approximately 66%.
The sotatercept-csrk median time to peak drug concentration (T max ) is approximately 7 days (range from 2 to 8 days) following multiple SC administration every 4 weeks. Distribution The population PK model estimated volume of distribution (%CV) of sotatercept-csrk at steady state is approximately
5.3L (27.3%) in patients with PAH. Elimination The sotatercept-csrk effective half-life is approximately 24 days and its clearance is approximately
0.18L/day. Metabolism Sotatercept-csrk is expected to be metabolized into small peptides by catabolic pathways. Specific Populations No clinically significant differences in sotatercept-csrk pharmacokinetics (PK) were observed based on age (18 to 81 years of age), sex, race, mild to moderate (eGFR ranging from 30 to 89 mL/min) renal impairment (PAH patients), or end-stage kidney disease (eGFR <15 mL/min) with dialysis.
Based on limited data, severe renal impairment (eGFR ranging from 15 to 30 mL/min, n=3) had no impact on the PK of sotatercept-csrk. Sotatercept-csrk is not dialyzable. The effect of hepatic impairment on the PK of sotatercept-csrk has not been studied.
Body Weight The clearance (CL) and central volume of distribution (Vc) increase with increase in body weight. This effect is not clinically significant when sotatercept-… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Sotatercept-csrk, a recombinant activin receptor type IIA-Fc (ActRIIA-Fc) fusion protein, is an activin signaling inhibitor that binds to activin A and other TGF- β superfamily ligands. As a result, sotatercept-csrk improves the balance between the pro-proliferative (ActRIIA/Smad2/3-mediated) and anti-proliferative (BMPRII/Smad1/5/8-mediated) signaling to modulate vascular proliferation. In rat models of PAH, a sotatercept-csrk analog reduced inflammation and inhibited proliferation of endothelial and smooth muscle cells in diseased vasculature.
These cellular changes were associated with thinner vessel walls, partial reversal of right ventricular remodeling, and improved hemodynamics.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied WINREVAIR (sotatercept-csrk) for injection is a white to off-white lyophilized cake or powder appearance supplied in single-dose vials (45 mg or 60 mg) packaged in kits that contain one measuring syringe and one safety needle. Each kit also contains Sterile Water for Injection in prefilled syringes necessary to reconstitute the product, vial adapter(s), and alcohol pads, as shown in Table 7 . Table 7: Kit Contents Kit Vial Adapters Alcohol Pads Sterile Water for Injection in prefilled syringes NDC (1) 45 mg vial 1 4 (1) 1 mL syringe NDC # 0006-5090-01 (1) 60 mg vial 1 4 (1) 1.3 mL syringe NDC # 0006-5091-01 (2) 45 mg vials 2 8 (2) 1 mL syringes NDC # 0006-5087-01 (2) 60 mg vials 2 8 (2) 1.3 mL syringes NDC # 0006-5088-01
16.2Storage and Handling Store vials refrigerated at 2°C to 8°C (36°F to 46°F) in original carton to protect from light. Do not freeze. The kit should remain in the refrigerator until ready for use. The unused kit can be out of the refrigerator for (up to 25°C/77°F) up to 24 hours. For additional information on temperature excursions, call Merck Sharp & Dohme LLC at 1-800-672-6372.
16.1How Supplied WINREVAIR (sotatercept-csrk) for injection is a white to off-white lyophilized cake or powder appearance supplied in single-dose vials (45 mg or 60 mg) packaged in kits that contain one measuring syringe and one safety needle. Each kit also contains Sterile Water for Injection in prefilled syringes necessary to reconstitute the product, vial adapter(s), and alcohol pads, as shown in Table 7 . Table 7: Kit Contents Kit Vial Adapters Alcohol Pads Sterile Water for Injection in prefilled syringes NDC (1) 45 mg vial 1 4 (1) 1 mL syringe NDC # 0006-5090-01 (1) 60 mg vial 1 4 (1) 1.3 mL syringe NDC # 0006-5091-01 (2) 45 mg vials 2 8 (2) 1 mL syringes NDC # 0006-5087-01 (2) 60 mg vials 2 8 (2) 1.3 mL syringes NDC # 0006-5088-01
📦 Storage and Handling ▾
16.2Storage and Handling Store vials refrigerated at 2°C to 8°C (36°F to 46°F) in original carton to protect from light. Do not freeze. The kit should remain in the refrigerator until ready for use. The unused kit can be out of the refrigerator for (up to 25°C/77°F) up to 24 hours. For additional information on temperature excursions, call Merck Sharp & Dohme LLC at 1-800-672-6372.
📋 Description ▾
11 DESCRIPTION Sotatercept-csrk is a homodimeric recombinant fusion protein consisting of the extracellular domain of the human activin receptor type IIA (ActRIIA) linked to the human IgG1 Fc domain. The molecular weight based on the amino acid sequence of sotatercept-csrk is approximately 78 kDa as a homodimer. Sotatercept-csrk for injection is a sterile, preservative-free, white to off-white lyophilized cake or powder appearance in single-dose vials for subcutaneous administration after reconstitution.
Each 45 mg single-dose vial provides 45 mg of sotatercept-csrk and citric acid monohydrate (0.40 mg), polysorbate 80 (0.18 mg), sodium citrate (1.84 mg), and sucrose (72 mg) at pH 5.8. After reconstitution with 1 mL Sterile Water for Injection, the resulting concentration is 50 mg/mL of sotatercept-csrk and the nominal deliverable volume is 0.9 mL. Each 60 mg single-dose vial provides 60 mg of sotatercept-csrk and citric acid monohydrate (0.53 mg), polysorbate 80 (0.24 mg), sodium citrate (2.45 mg), and sucrose (96 mg) at pH 5.8.
After reconstitution with 1.3 mL Sterile Water for Injection, the resulting concentration is 50 mg/mL of sotatercept-csrk and the nominal deliverable volume is 1.2 mL.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients to read the FDA-approved patient labeling ( Patient Information and IFU ). Discuss the following with patients prior to and during treatment with WINREVAIR. Erythrocytosis Caution patients that WINREVAIR may raise Hgb to levels that increase their risk of thrombotic events.
Inform patients that Hgb levels will be assessed before at least the first 5 doses and then periodically, as dosage may need to be adjusted [see Warnings and Precautions (5.1) ] . Severe Thrombocytopenia Caution patients that WINREVAIR may cause platelet count to decrease, which if severe could cause bleeding. Inform patients that platelet count will be assessed before at least the first 5 doses and then periodically, as dosage may need to be adjusted [see Warnings and Precautions (5.2) ] .
Serious Bleeding Inform patients of the possibility of serious bleeding, which is more likely to occur if they have low platelet counts or while on prostacyclin background therapy and/or antithrombotic agents. Advise patients to notify their healthcare provider about signs and symptoms of bleeding [see Warnings and Precautions (5.3) ] . Embryo-Fetal Toxicity Advise females of reproductive potential of the potential risk to a fetus.
Advise females of reproductive potential to use effective contraception while receiving WINREVAIR and for at least 4 months after the final dose. Advise females to contact their healthcare provider if they become pregnant, or if pregnancy is suspected during treatment with WINREVAIR [see Warnings and Precautions (5.4) , Use in Specific Populations (8.1) ] . Report exposure during pregnancy or lactation to the Merck Sharp & Dohme, LLC Adverse Event reporting line at 1-877-888-4231.
Lactation Advise females not to breastfeed during treatment with WINREVAIR and for 4 months after the final dose [see Use in Specific Populations (8.2) ] . Females and Males of Reproductive Potential Advise females and males of reproductive potential that WINREVAIR may impair fertility [see Use in Specific Populations (8.3) , Nonclinical Toxicology (13.1) ] . Administration by Patient or Caregiver Review the IFU with the patient or caregiver step-by-step.
Provide training to the patient or caregiver regarding proper preparation and administration of WINREVAIR and decide whether a patient or caregiver is capable of preparing and administering WINREVAIR independently [see Dosage and Administration (2.4) ] . Make sure the patient or caregiver can do the following correctly: reconstitute the medicine, measure the correct amount of medicine according to the patient’s prescription, select and prepare a proper injection site, and inject the medicine subcutaneously. Incorrect Dose or Missed Dose Inform patients to call their healthcare provider for further instruction if they take more than or less than the correct dose.
Advise them about signs/symptoms to monitor for and what to do if any of these signs/symptoms should occur. Advise them that additional laboratory tests may be required prior to the next scheduled dose to ensure that the next dose can be safely administered. Instruct the patient that if they miss the prescribed dose of WINREVAIR, they should take it within 3 days and maintain the original schedule for the next dose.
If not taken within 3 days, instruct them to call their healthcare provider for guidance [see Dosage and Administration (2.2) ] . Manufactured by: Merck Sharp & Dohme LLC, Rahway, NJ 07065, USA U.S. license number 0002 For patent information: www.msd.com/research/patent Copyright © 2024-2026 Merck & Co., Inc., Rahway, NJ, USA, and its affiliates. All rights reserved. uspi-mk7962-i-2608r006
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Following subcutaneous administration of 0.7 mg/kg WINREVAIR every three weeks to PAH patients (PULSAR, SPECTRA, and STELLAR), the steady state geometric mean (%CV) area under the time concentration curve (AUC) is 171.3 mcg×d/mL (34.2%), and peak concentration (C max ) is 9.7 mcg/mL (30%). Sotatercept-csrk AUC and C max increased proportionally with dose. Steady state is achieved after approximately 15 weeks following initiation of multiple dosing.
The accumulation ratio of sotatercept-csrk AUC is approximately 2.2. Sotatercept-csrk pharmacokinetics were similar in PAH participants in ZENITH. Absorption Following subcutaneous administration, the absolute bioavailability of sotatercept-csrk is approximately 66%.
The sotatercept-csrk median time to peak drug concentration (T max ) is approximately 7 days (range from 2 to 8 days) following multiple SC administration every 4 weeks. Distribution The population PK model estimated volume of distribution (%CV) of sotatercept-csrk at steady state is approximately
5.3L (27.3%) in patients with PAH. Elimination The sotatercept-csrk effective half-life is approximately 24 days and its clearance is approximately
0.18L/day. Metabolism Sotatercept-csrk is expected to be metabolized into small peptides by catabolic pathways. Specific Populations No clinically significant differences in sotatercept-csrk pharmacokinetics (PK) were observed based on age (18 to 81 years of age), sex, race, mild to moderate (eGFR ranging from 30 to 89 mL/min) renal impairment (PAH patients), or end-stage kidney disease (eGFR <15 mL/min) with dialysis.
Based on limited data, severe renal impairment (eGFR ranging from 15 to 30 mL/min, n=3) had no impact on the PK of sotatercept-csrk. Sotatercept-csrk is not dialyzable. The effect of hepatic impairment on the PK of sotatercept-csrk has not been studied.
Body Weight The clearance (CL) and central volume of distribution (Vc) increase with increase in body weight. This effect is not clinically significant when sotatercept-csrk is administered using weight-based dosing as recommended.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics STELLAR A greater decrease from baseline in pulmonary vascular resistance (PVR) was observed in the WINREVAIR group compared to the placebo group. The median treatment difference in PVR between sotatercept-csrk and placebo was -235 dynes*sec/cm 5 (95% CI: -288, -181). Sotatercept-csrk steady state exposure at 0.7 mg/kg dose was associated with near maximal reduction in PVR based on exposure-response analysis.
A greater decrease from baseline in NT-proBNP was observed in the WINREVAIR group compared to the placebo group. The median treatment difference in NT-proBNP between the sotatercept-csrk and placebo was -442 pg/mL (95% CI: -574, -310). ZENITH The median treatment difference in change in PVR from baseline between the sotatercept and placebo groups after 24 weeks was -340 dynes*sec/cm 5 (95% CI: -511, -168).
The median treatment difference in change in NT-proBNP from baseline between the sotatercept-csrk and placebo groups after 24 weeks was -2339 pg/mL (95% CI: -3379, -1299). The median treatment difference in change from baseline in mean pulmonary artery pressure (mPAP) between the sotatercept-csrk and placebo groups after 24 weeks was -21.2 mm Hg (95% CI: -27.8, -14.6).
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Pulmonary Arterial Hypertension STELLAR The efficacy of WINREVAIR was evaluated in adult patients with PAH in the STELLAR trial (NCT04576988). STELLAR was a global, double-blind, placebo-controlled, multicenter, parallel-group clinical trial in which 323 patients with PAH (WHO Group 1, FC II or III) were randomized 1:1 to WINREVAIR (target dose 0.7 mg/kg) (n=163) or placebo (n=160) administered subcutaneously once every 3 weeks. Participants were: 79% female; had a median age of 48 years (range: 18 to 82 years), and median body weight of 68 kg (range: 38 to 141 kg); and 89% White, 2% Black/African American, 2% Asian, 0.3% American Indian or Alaska Native, 0.3% Native Hawaiian or Other Pacific Islander, 6% Missing/Other races.
The most common PAH etiologies were idiopathic PAH (59%), heritable PAH (18%), and PAH associated with connective tissue diseases (CTD) (15%). STELLAR excluded patients with human immunodeficiency virus (HIV)-associated PAH, PAH associated with portal hypertension, schistosomiasis-associated PAH, and pulmonary veno occlusive disease. The mean time from PAH diagnosis to screening was 8.8 years.
Most participants were receiving either three (61%) or two (35%) background drugs for PAH, and 40% were receiving prostacyclin infusions. Patients had a WHO FC II (49%) or III (51%) at baseline. The primary efficacy endpoint was the change from baseline at Week 24 in 6-Minute Walk Distance (6 MWD).
In the WINREVAIR group, the placebo-adjusted median increase in 6 MWD was 41 meters (95% CI: 28, 54; p<0.001). Figure 1 displays placebo-adjusted changes in 6 MWD at Week 24 in relevant subgroups. Figure 1: Change from Baseline in 6-Minute Walk Distance (meters) at Week 24 in Subgroups in STELLAR * Hodges-Lehmann location shift from placebo estimate (median of all paired differences).
ASE = asymptotic standard error. Change from baseline in 6 MWD at Week 24 for subjects who died was imputed to -2000 meters to receive the worst rank. Change from baseline in 6 MWD at Week 24 for subjects who had missing data due to a non-fatal clinical worsening event was imputed to -1000 meters to receive the next-worst rank.
Treatment with WINREVAIR led to an improvement from baseline by at least 1 WHO FC at Week 24 in 29% of patients compared to 14% of patients treated with placebo (p<0.001). Treatment with WINREVAIR resulted in an 84% reduction in the occurrence of death from any cause or PAH clinical worsening events compared to placebo (see Table 5 and Figure 2 ). These outcomes were captured until the last patient completed the Week 24 visit (data up to the data cutoff; median duration of exposure 33.6 weeks).
Table 5: Death from Any Cause or PAH Clinical Worsening Events in STELLAR WINREVAIR (N=163) n (%) Placebo (N=160) n (%) Hazard Ratio (95% CI) N = number of subjects in the category. 6 MWT = 6-Minute Walking Test Number of subjects who experienced death or at least one clinical worsening event 9 (5.5) 42 (26.3) 0.16 (0.08, 0.35) p<0.001 Assessment of clinical worsening events A subject can have more than one assessment recorded for their clinical worsening. Death 2 (1.2) 7 (4.4) Worsening-related listing for lung and/or heart transplant 1 (0.6) 2 (1.3) Need to initiate rescue therapy with an approved PAH therapy or the need to increase the dose of infusion prostacyclin by 10% or more 2 (1.2) 17 (10.6) Need for atrial septostomy There were no events of atrial septostomy.
0 (0.0) 0 (0.0) PAH-specific hospitalization (≥24 hours) 0 (0.0) 8 (5.0) Deterioration of PAH Deterioration of PAH is defined by both of the following events occurring at any time, even if they began at different times, as compared to their baseline values: (a) Worsened WHO functional class (II to III, III to IV, II to IV, etc.); and (b) Decrease in 6 MWD by ≥15% (confirmed by two 6 MWTs at least 4 hours apart but no more than one week). 4 (2.5) 15 (9.4) Figure 2: Time to Death from Any Cause or First Occurrence of PAH Clinical Worsening… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No carcinogenicity or mutagenicity studies have been conducted with sotatercept-csrk. In a fertility and early embryonic development study in female rats, sotatercept-csrk was administered SC once weekly at doses of 5, 15, and 50 mg/kg beginning 2 weeks prior to mating and through gestation day 7. At doses ≥15 mg/kg (≥9 fold the MRHD, based on estimated AUC), pregnancy rates were decreased and there were increases in preimplantation and postimplantation loss and reductions in live litter size.
Increased estrous cycle duration occurred at 50 mg/kg only (21-fold the MRHD, based on estimated AUC). In a fertility study in male rats, sotatercept-csrk was administered SC once weekly at doses of 0.3, 3, and 30 mg/kg for 13 weeks (beginning 10 weeks prior to mating). A subset of animals was examined after a 13-week recovery period.
At ≥0.3 mg/kg (0.5-fold the MRHD, based on estimated AUC) there were non-reversible histologic changes in the efferent ducts, testes, and epididymides. Reversible decreases in functional fertility endpoints occurred at 30 mg/kg (20-fold the MRHD, based on estimated AUC).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No carcinogenicity or mutagenicity studies have been conducted with sotatercept-csrk. In a fertility and early embryonic development study in female rats, sotatercept-csrk was administered SC once weekly at doses of 5, 15, and 50 mg/kg beginning 2 weeks prior to mating and through gestation day 7. At doses ≥15 mg/kg (≥9 fold the MRHD, based on estimated AUC), pregnancy rates were decreased and there were increases in preimplantation and postimplantation loss and reductions in live litter size.
Increased estrous cycle duration occurred at 50 mg/kg only (21-fold the MRHD, based on estimated AUC). In a fertility study in male rats, sotatercept-csrk was administered SC once weekly at doses of 0.3, 3, and 30 mg/kg for 13 weeks (beginning 10 weeks prior to mating). A subset of animals was examined after a 13-week recovery period.
At ≥0.3 mg/kg (0.5-fold the MRHD, based on estimated AUC) there were non-reversible histologic changes in the efferent ducts, testes, and epididymides. Reversible decreases in functional fertility endpoints occurred at 30 mg/kg (20-fold the MRHD, based on estimated AUC).
📄 Patient Package Insert ▾
This Patient Information has been approved by the U.S. Food and Drug Administration Revised: October 2025 PATIENT INFORMATION WINREVAIR™ (WIN-reh-vair) (sotatercept-csrk) for injection, for subcutaneous use What is WINREVAIR? WINREVAIR is a prescription medicine used to treat adults with pulmonary arterial hypertension (PAH).
PAH is a type of high blood pressure in the arteries of your lungs. WINREVAIR can: improve your ability to exercise and perform normal activities with fewer symptoms, and reduce the risk of your physical condition and symptoms worsening, including lowering your risk of hospitalization for PAH, lung transplant, and death. It is not known if WINREVAIR is safe and effective in children under 18 years of age.
What should I tell my healthcare provider before taking WINREVAIR? Tell your healthcare provider about: All of your medical conditions All of the medicines you take, including prescriptions and over-the-counter medicines, vitamins, or herbal supplements If you are able to get pregnant: WINREVAIR may harm your unborn baby. Tell your healthcare provider if you are pregnant or planning to get pregnant.
Tell your healthcare provider right away if you become pregnant or think you may be pregnant during treatment with WINREVAIR. Your healthcare provider should do a pregnancy test before you start taking WINREVAIR. You should use effective birth control during treatment with WINREVAIR and for at least 4 months after your final dose.
Ask your healthcare provider about birth control methods that may be right for you. You or your healthcare provider should report any exposure to WINREVAIR during pregnancy by calling 1-877-888-4231. If you are breastfeeding or planning to breastfeed: Tell your healthcare provider if you are breastfeeding or planning to breastfeed.
It is not known if WINREVAIR passes into breast milk. Do not breastfeed during treatment with WINREVAIR and for 4 months after your final dose. Talk to your healthcare provider about the best way to feed your baby.
You or your healthcare provider should report any exposure to WINREVAIR during breastfeeding by calling 1-877-888-4231. Before you take WINREVAIR: If your healthcare provider decides that you or a caregiver can give your injections of WINREVAIR at home, you or your caregiver should receive training from your healthcare provider on the right way to prepare and inject WINREVAIR. Do not try to inject WINREVAIR until you have been shown how to inject WINREVAIR by your healthcare provider.
Your healthcare provider will do a blood test before your first 5 doses of WINREVAIR, longer if needed, and then from time to time to check your levels of hemoglobin (a protein in red blood cells that carries oxygen) and platelets (blood cells that help blood clot). After each of these blood tests, your healthcare provider may delay treatment or change your dose if needed. See the detailed “ Instructions for Use ” booklet that comes with WINREVAIR for information on how to prepare and inject a dose of WINREVAIR.
How should I take WINREVAIR? Use WINREVAIR exactly as your healthcare provider tells you to. You will give WINREVAIR every 3 weeks as an injection just under your skin (subcutaneous) in your: stomach (abdomen) at least 2 inches away from the belly button, or upper thigh You should inject WINREVAIR right away after mixing the medicine powder with the sterile water for injection, but no later than 4 hours after mixing.
Your prescribed dose: Your healthcare provider will tell you how much WINREVAIR to inject and when to inject it. This is because your prescribed dose depends on your body weight and blood tests. Do not change your dose or stop taking WINREVAIR without talking to your healthcare provider.
Do not take WINREVAIR more often than your healthcare provider tells you to. If you are not sure when to take WINREVAIR, call your healthcare provider. Your healthcare provider may delay treatment, change your dose, or stop treatment depending on how you respo… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
Important: Read this booklet first Important INSTRUCTIONS FOR USE Mix WINREVAIR™ (WIN-reh-vair) (sotatercept-csrk) for injection, for subcutaneous use How to use your WINREVAIR injection kit Withdraw For package containing 1 vial For subcutaneous injection only (inject directly under the skin) Inject In this booklet: Before you start Important information for patients or caregivers Get to know the parts of your kit Important information you need to know before injecting WINREVAIR Storing your injection kit Get started Mix powdered medicine into liquid form Withdraw your prescribed dose Inject your medicine How to throw away WINREVAIR Frequently asked questions Before you start: Read this booklet Read this Instructions for Use from start to finish before using WINREVAIR and each time you get a refill.
There may be new information. Start with your healthcare provider Do not use WINREVAIR until your healthcare provider has shown you or your caregiver the right way to prepare and inject it. Your healthcare provider should show you how to inject WINREVAIR before you use it for the first time.
Questions? If you have questions about how to give WINREVAIR the right way or need more information, call your pharmacy or healthcare provider. For general product information visit www.WINREVAIR.com or call Merck Sharp & Dohme LLC at 1-800-672-6372.
Important information for patients or caregivers Before you prepare and inject WINREVAIR, you must be: trained by a healthcare provider following this Instructions for Use booklet step-by-step, and capable of independent administration of WINREVAIR as determined by a healthcare provider Before using WINREVAIR, make sure you are trained to do the following correctly: Reconstitute (mix) the medicine Measure the correct amount of medicine according to your prescription Select and prepare a proper injection site Inject the medicine subcutaneously Get to know the parts of your kit Top Tray Use to mix the medicine 1 Vial of WINREVAIR medicine powder 1 Prefilled syringe with sterile water for injection to mix medicine powder into liquid form 1 Vial adapter to connect the vial and syringe Bottom Tray Use to inject the medicine Needle for injection Empty dosing syringe to measure, withdraw, and inject your medicine Important information you need to know before injecting WINREVAIR You must mix WINREVAIR before using it.
Make sure the medicine powder in the vial is completely dissolved before you inject. Check your prescribed dose (amount in ‘mL’) each time you use WINREVAIR. Your prescribed dose may change.
Your prescribed dose is on the prescription label on your kit. Use only the supplies that are in the kit to prepare your prescribed dose. Do not open the package or mix the medicine until you are ready to use it.
Do not reuse any of the supplies. After your injection, throw away the used vials with any remaining WINREVAIR medicine, needle, caps, and syringes in a sharps container. See pages 36-37 for more information.
Storing your injection kit Store WINREVAIR injection kit in the refrigerator at 36°F to 46°F (2°C to 8°C). Do not freeze. Store in the original carton to protect from light.
Keep injection kit out of the reach of children and pets. Get started Before you can prepare and inject WINREVAIR, you must first be trained and determined to be capable of independent administration of WINREVAIR by a healthcare provider. 1 Check WINREVAIR injection kit and expiration date Remove the WINREVAIR injection kit from the refrigerator.
Check the expiration date and look for any signs of damage on the kit or on the supplies. If expired or damaged, do not use. Call your pharmacy to get a new kit.
Check that you have the medicine that your healthcare provider prescribed. 2 Let your kit come to room temperature, gather supplies, and wash your hands Wait 15 minutes to allow your kit to warm to room temperature. Cold medicine is more painful to inject.
Along with your kit, gather these items and find a clean, flat… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Indications and Usage ( 1 ) 10/2025
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 45 mg Vial Kit Carton NDC 0006-5090-01 WINREVAIR ™ (sotatercept-csrk) for injection 45 mg/vial Package contains 1 Vial Dose based on patient weight For Subcutaneous Use Only Must be reconstituted with diluent provided prior to administration 1 Single-Dose Vial Discard unused portion Rx only Principal Display Panel - 45 mg Vial Carton
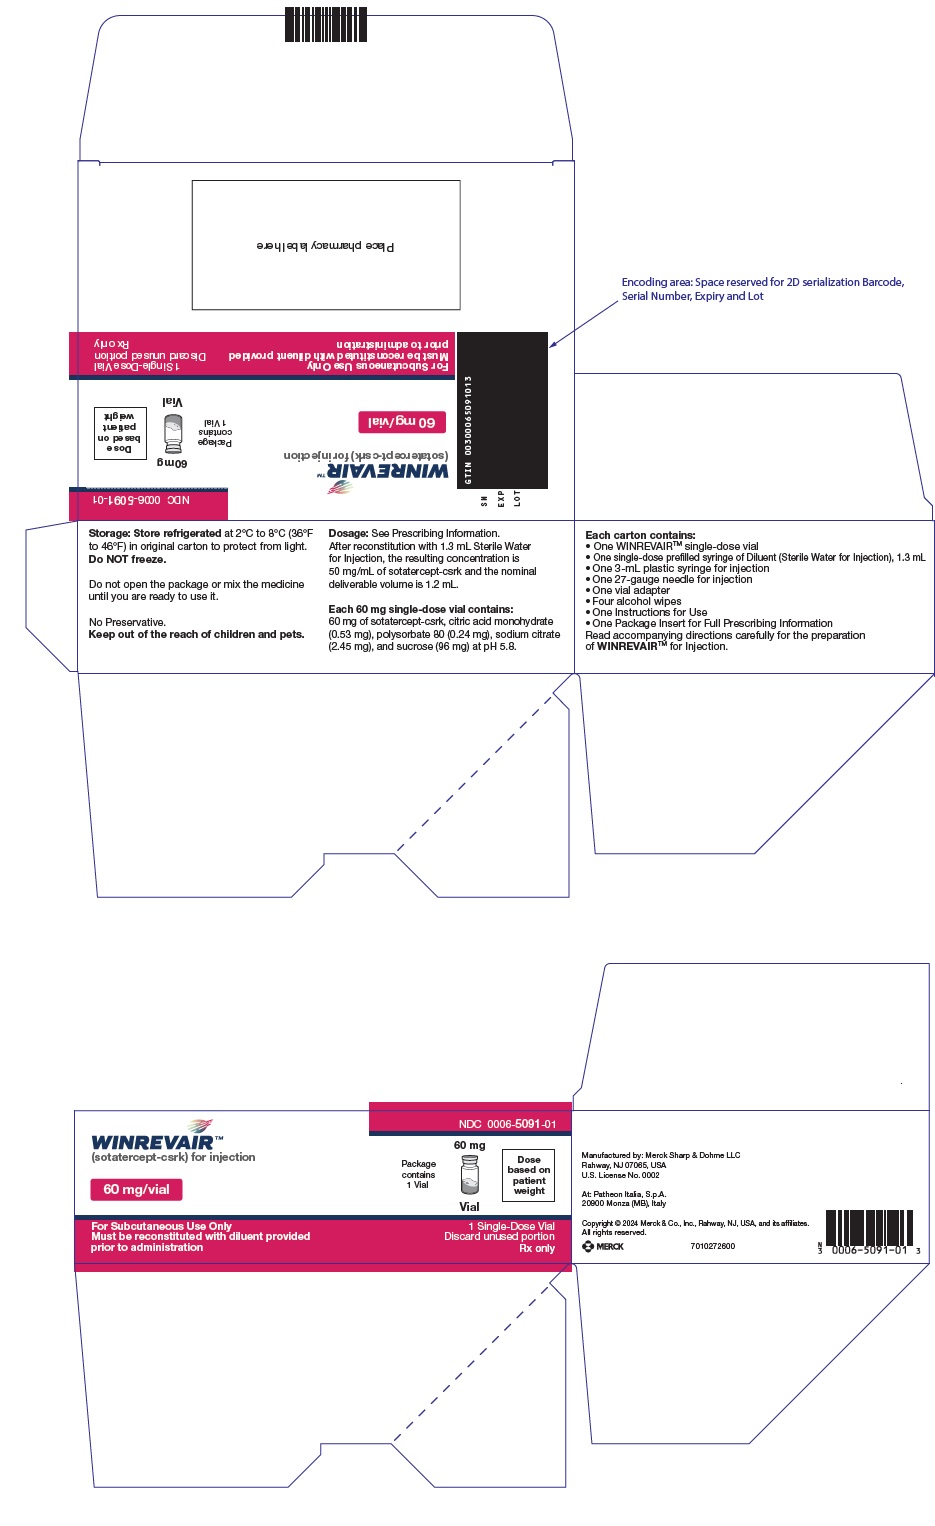
PRINCIPAL DISPLAY PANEL - 60 mg Vial Kit Carton NDC 0006-5091-01 WINREVAIR ™ (sotatercept-csrk) for injection 60 mg/vial Package contains 1 Vial Dose based on patient weight For Subcutaneous Use Only Must be reconstituted with diluent provided prior to administration 1 Single-Dose Vial Discard unused portion Rx only Principal Display Panel - 60 mg Vial Carton
PRINCIPAL DISPLAY PANEL - 45 mg 2 Vials Kit Carton NDC 0006-5087-01 WINREVAIR ™ (sotatercept-csrk) for injection 45 mg/vial Package contains 2 Vials Dose based on patient weight For Subcutaneous Use Only Must be reconstituted with diluent provided prior to administration 2 Single-Dose Vials Discard unused portion Rx only Principal Display Panel - 45 mg Vial Carton
PRINCIPAL DISPLAY PANEL - 60 mg 2 Vials Kit Carton NDC 0006-5088-01 WINREVAIR ™ (sotatercept-csrk) for injection 60 mg/vial Package contains 2 Vials Dose based on patient weight For Subcutaneous Use Only Must be reconstituted with diluent provided prior to administration 2 Single-Dose Vials Discard unused portion Rx only Principal Display Panel - 60 mg Vial Carton
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |