
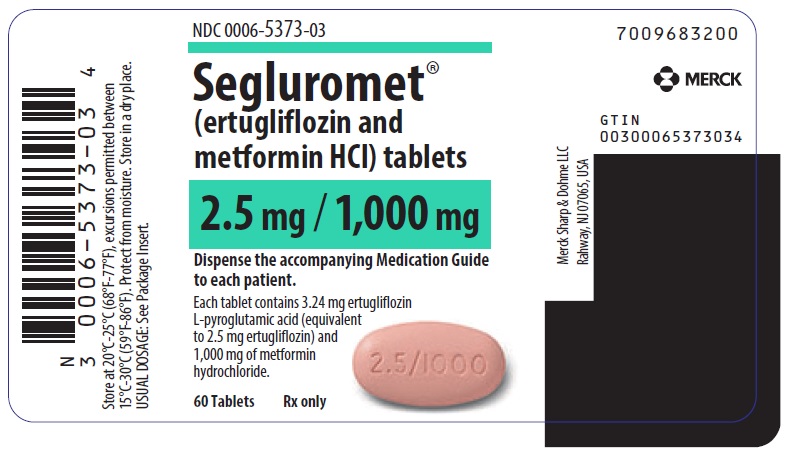
SEGLUROMET ertugliflozin and metformin hydrochloride 2.5 mg; 1000 mg Tablet, Film Coated, 60-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Sodium-glucose co-transporter 2 (SGLT2) inhibitors class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Ertugliflozin is to lower blood sugar levels in adults with type 2 diabetes (condition in which blood sugar is too high because the body does not make or use insulin normally). Ertugliflozin is in a class of medications called sodium-glucose co-transporter 2 (SGLT2) inhibitors. It works by helping the kidneys remove glucose (sugar) and excess fluid through the urine.
Read the full MedlinePlus article ↗- Segluromet helps lower your blood sugar in two different ways at once. The ertugliflozin part tells your kidneys to flush extra sugar out through your urine instead of sending it b...
- What exactly does Segluromet do for my diabetes?
- Yes — a few things are worth knowing about. The most urgent is lactic acidosis, which is a rare but serious side effect from the metformin in Segluromet. Watch for muscle aches, un...
- Is there anything I should watch out for that would mean I need to call a doctor right away?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII R12CBM0EIZ
A natural wax derived from a Brazilian palm tree, used as a coating and polish on tablets and capsules. It creates a smooth, shiny finish that protects the medicine and improves appearance.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII 9XZ8H6N6OH
A plant-based cellulose derivative used as a binder to hold tablet ingredients together, a thickener in liquids, and a coating agent to control how fast the medicine dissolves.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $5.744 | $344.66 / 60 tablets |
| Medicaid paysCMS SDUD · 12 mo | $5.83 | $349.63 / 60 tablets |
| Medicare drug plans payPart D · Q2 2026 | $5.86 | $351.44 / 60 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Segluromet 2.5 mg/1; 1000 mgthis 00006-5373-03 | Merck | 60 tablets | $5.744 | — | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9439902 ↗ | Method of use | U-2214 | Oct 21, 2030 |
| US 8080580 ↗ | Drug substance | U-2214 | Dec 19, 2031 |
| US 9439902 ↗ | Method of use | U-2214 | Oct 21, 2030 |
| US 8080580 ↗ | Drug substance | U-2214 | Dec 19, 2031 |
| US 8080580 ↗ | Drug substance | U-2214 | Dec 19, 2031 |
| US 8080580 ↗ | Drug substance | U-2214 | Dec 19, 2031 |
| US 9439902 ↗ | Method of use | U-2214 | Oct 21, 2030 |
| US 9439902 ↗ | Method of use | U-2214 | Oct 21, 2030 |
| US 9308204 ↗ | Drug product | — | Oct 21, 2030 |
| US 9308204 ↗ | Drug product | — | Oct 21, 2030 |
| US 9308204 ↗ | Drug product | — | Oct 21, 2030 |
| US 9308204 ↗ | Drug product | — | Oct 21, 2030 |
Is there a generic version of SEGLUROMET 2.5-1,000 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 00006-5373-03 You're viewing this | 60 TABLET, FILM COATED in 1 BOTTLE (0006-5373-03) | $5.74 / ea | $344.67 | 2017-12-19 | Active |
| 00006-5373-06 | 180 TABLET, FILM COATED in 1 BOTTLE (0006-5373-06) | $5.74 / ea | $1,034.00 | 2017-12-19 | Active |
| 00006-5373-07 | 500 TABLET, FILM COATED in 1 BOTTLE (0006-5373-07) | $5.21 / ea | $2,604.85 | 2017-12-19 | Active |
| 00006-5373-09 | 2 BOTTLE in 1 CARTON (0006-5373-09) / 14 TABLET, FILM COATED in 1 BOTTLE (0006-5373-08) | — | — | 2017-12-19 | Active |
Per ea, this pack runs about 10% above the cheapest pack (500-count, $5.21 vs $5.74 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 00006-5373-03?
What is the difference between NDC 00006-5373-03 and NDC 00006-5373-06?
What NDC number is used to bill for this package of SEGLUROMET ertugliflozin and metformin hydrochloride 2.5 mg; 1000 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: LACTIC ACIDOSIS Postmarketing cases of metformin-associated lactic acidosis have resulted in death, hypothermia, hypotension, and resistant bradyarrhythmias. The onset of metformin-associated lactic acidosis is often subtle, accompanied only by nonspecific symptoms such as malaise, myalgias, respiratory distress, somnolence, and abdominal pain. Metformin-associated lactic acidosis was characterized by elevated blood lactate levels (>5 mmol/Liter), anion gap acidosis (without evidence of ketonuria or ketonemia), an increased lactate/pyruvate ratio, and metformin plasma levels generally >5 mcg/mL [see Warnings and Precautions (5.1) ] .
Risk factors for metformin-associated lactic acidosis include renal impairment, concomitant use of certain drugs (e.g., carbonic anhydrase inhibitors such as topiramate), age 65 years old or greater, having a radiological study with contrast, surgery and other procedures, hypoxic states (e.g., acute congestive heart failure), excessive alcohol intake, hepatic impairment, and mitochondrial diseases [see Warnings and Precautions (5.1) ] . Steps to reduce the risk of and manage metformin-associated lactic acidosis in these high risk groups are provided in the Full Prescribing Information [see Dosage and Administration (2.2) , Contraindications (4) , Warnings and Precautions (5.1) , Drug Interactions (7) , and Use in Specific Populations (8.6 , 8.7 )] .
If metformin-associated lactic acidosis is suspected, immediately discontinue SEGLUROMET and institute general supportive measures in a hospital setting. Prompt hemodialysis is recommended [see Warnings and Precautions (5.1) ] . WARNING: LACTIC ACIDOSIS See full prescribing information for complete boxed warning .
Postmarketing cases of metformin-associated lactic acidosis have resulted in death, hypothermia, hypotension, and resistant bradyarrhythmias. Symptoms included malaise, myalgias, respiratory distress, somnolence, and abdominal pain. Laboratory abnormalities included elevated blood lactate levels, anion gap acidosis, increased lactate/pyruvate ratio, and metformin plasma levels generally >5 mcg/mL.
( 5.1 ) Risk factors include renal impairment, concomitant use of certain drugs, age ≥65 years old, radiological studies with contrast, surgery and other procedures, hypoxic states, excessive alcohol intake, hepatic impairment, and mitochondrial diseases. Steps to reduce the risk of and manage metformin-associated lactic acidosis in these high risk groups are provided in the Full Prescribing Information. ( 5.1 ) If lactic acidosis is suspected, discontinue SEGLUROMET and institute general supportive measures in a hospital setting.
Prompt hemodialysis is recommended. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE SEGLUROMET ® is indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus. SEGLUROMET is a combination of ertugliflozin, a sodium glucose co-transporter 2 (SGLT2) inhibitor, and metformin, a biguanide, indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus. ( 1 ) Limitations of Use: Not recommended for use to improve glycemic control in patients with type 1 diabetes mellitus.
( 1 ) Limitations of Use Not recommended for use to improve glycemic control in patients with type 1 diabetes mellitus [see Warnings and Precautions (5.2) ].
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Assess renal function prior to initiation and as clinically indicated. ( 2.1 ) Correct volume depletion before initiation. ( 2.1 ) Individualize the starting dosage based on the patient's current regimen.
( 2.2 ) Maximum recommended dosage is 7.5 mg ertugliflozin/1,000 mg metformin orally twice daily. ( 2.2 ) Take orally twice daily with meals, with gradual dose escalation. ( 2.2 ) Do not use in patients with an estimated glomerular filtration rate (eGFR) below 30 mL/minute/1.73 m 2 .
Use is not recommended in patients with an eGFR less than 45 mL/min/1.73 m 2 . ( 2.2 ) Use is contraindicated in patients with severe renal impairment (eGFR less than 30 mL/min/1.73 m 2 ), end stage-renal disease (ESRD), or on dialysis. ( 2.2 ) SEGLUROMET may need to be discontinued at time of, or prior to, iodinated contrast imaging procedures.
( 2.3 ) Withhold SEGLUROMET for at least 4 days, if possible, prior to surgery or procedures associated with prolonged fasting. ( 2.4 )
2.1Prior to Initiation of SEGLUROMET Assess renal function before initiating SEGLUROMET and as clinically indicated [see Warnings and Precautions (5.1 , 5.4) ] . Assess volume status. In patients with volume depletion, correct this condition before initiating SEGLUROMET [see Warnings and Precautions (5.4) and Use in Specific Populations (8.5 , 8.6) ].
2.2Recommended Dosage Individualize the starting dosage of SEGLUROMET, ertugliflozin and metformin hydrochloride (HCI), based on the patient’s current regimen, while not exceeding the maximum recommended oral daily dosage of 15 mg ertugliflozin and 2,000 mg metformin HCl: In patients on metformin HCI, switch to SEGLUROMET tablets containing 2.5 mg ertugliflozin, with a similar total oral daily dosage of metformin HCl. In patients on ertugliflozin, switch to SEGLUROMET tablets containing 500 mg metformin HCl, with a similar total oral daily dosage of ertugliflozin.
In patients already treated with ertugliflozin and metformin HCl, switch to SEGLUROMET tablets containing the same total oral daily dosage of ertugliflozin and a similar daily dosage of metformin HCI. Take SEGLUROMET orally twice daily with meals, with gradual dosage escalation for those initiating metformin HCl to reduce the gastrointestinal side effects due to metformin [see Adverse Reactions (6.1) ]. Dosing may be adjusted based on effectiveness and tolerability.
Use of SEGLUROMET is not recommended in patients with an estimated glomerular filtration rate (eGFR) less than 45 mL/min/1.73 m 2 . Use of SEGLUROMET is contraindicated in patients with severe renal impairment (eGFR less than 30 mL/min/1.73 m 2 ), end stage-renal disease (ESRD), or on dialysis [see Contraindications (4) ] .
2.3Discontinuation for Iodinated Contrast Imaging Procedures Discontinue SEGLUROMET at the time of, or prior to, an iodinated contrast imaging procedure in patients with an eGFR less than 60 mL/min/1.73 m 2 ; in patients with a history of liver disease, alcoholism or heart failure; or in patients who will be administered intra-arterial iodinated contrast. Re-evaluate eGFR 48 hours after the imaging procedure; restart SEGLUROMET if renal function is stable [see Warnings and Precautions (5.1) ] .
2.4Temporary Interruption for Surgery Withhold SEGLUROMET for at least 4 days, if possible, prior to surgery or procedures associated with prolonged fasting. Resume SEGLUROMET when the patient is clinically stable and has resumed oral intake [see Warnings and Precautions (5.2) and Clinical Pharmacology (12.2) ].
2.5Recommendations Regarding Missed Dose If a dose is missed, instruct patients to take the dose as soon as possible. Advise patients not to double up the next dose.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: ertugliflozin 2.5 mg and metformin HCl 500 mg, pink, oval, debossed with "2.5/500" on one side and plain on the other side. Tablets: ertugliflozin 2.5 mg and metformin HCl 1,000 mg, pink, oval, debossed with "2.5/1000" on one side and plain on the other side. Tablets: ertugliflozin 7.5 mg and metformin HCl 500 mg, red, oval, debossed with "7.5/500" on one side and plain on the other side.
Tablets: ertugliflozin 7.5 mg and metformin HCl 1,000 mg, red, oval, debossed with "7.5/1000" on one side and plain on the other side. Tablets: Ertugliflozin 2.5 mg and metformin hydrochloride 500 mg ( 3 ) Ertugliflozin 2.5 mg and metformin hydrochloride 1,000 mg ( 3 ) Ertugliflozin 7.5 mg and metformin hydrochloride 500 mg ( 3 ) Ertugliflozin 7.5 mg and metformin hydrochloride 1,000 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS SEGLUROMET is contraindicated in patients with: Hypersensitivity to ertugliflozin, metformin, or any excipient in SEGLUROMET. Reactions such as angioedema or anaphylaxis have occurred [see Adverse Reactions (6.2) ]. Severe renal impairment (eGFR less than 30 mL/min/1.73 m 2 ), end stage-renal disease (ESRD), or on dialysis [see Use in Specific Populations (8.6) ] .
Acute or chronic metabolic acidosis, including diabetic ketoacidosis, with or without coma. Severe renal impairment (eGFR less than 30 mL/min/1.73 m 2 ), end stage-renal disease, or patients on dialysis. ( 4 ) Metabolic acidosis, including diabetic ketoacidosis.
( 4 ) Hypersensitivity to ertugliflozin, metformin or any excipient. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Diabetic Ketoacidosis in Patients with Type 1 Diabetes Mellitus and Other Ketoacidosis: Consider ketone monitoring in patients at risk for ketoacidosis, as indicated. Assess for ketoacidosis regardless of presenting blood glucose levels and discontinue SEGLUROMET if ketoacidosis is suspected. Monitor patients for resolution of ketoacidosis before restarting.
( 5.2 ) Lower Limb Amputation: Monitor patients for infections or ulcers of lower limbs, and institute appropriate treatment. ( 5.3 ) Volume Depletion: May result in acute kidney injury. Before initiating, assess and correct volume status in patients with renal impairment, low systolic blood pressure, elderly patients, or patients on diuretics.
Monitor for signs and symptoms during therapy. ( 5.4 ) Genitourinary Infections, including Urosepsis, Pyelonephritis, Necrotizing Fasciitis of the Perineum (Fournier’s Gangrene), and Genital Mycotic Infections: Monitor patients for signs and symptoms of genitourinary infections and treat promptly, if indicated. Immediately evaluate patients presenting with pain or tenderness, erythema, or swelling in the genital or perineal area, along with fever or malaise, for necrotizing fasciitis and if suspected, discontinue SEGLUROMET, and promptly institute appropriate medical and/or surgical intervention.
( 5.5 ) Hypoglycemia with Concomitant Use with Insulin or Insulin Secretagogoues: Consider a lower dose of insulin or insulin secretagogue to reduce risk of hypoglycemia when used in combination. ( 5.6 ) Vitamin B 12 Deficiency: Metformin may lower vitamin B 12 levels. Measure hematological parameters annually.
( 5.7 )
5.1Lactic Acidosis There have been postmarketing cases of metformin-associated lactic acidosis, including fatal cases. These cases had a subtle onset and were accompanied by nonspecific symptoms such as malaise, myalgias, abdominal pain, respiratory distress, or increased somnolence; however, hypothermia, hypotension and resistant bradyarrhythmias have occurred with severe acidosis. Metformin-associated lactic acidosis was characterized by elevated blood lactate concentrations (>5 mmol/Liter), anion gap acidosis (without evidence of ketonuria or ketonemia), and an increased lactate: pyruvate ratio; metformin plasma levels were generally >5 mcg/mL.
Metformin decreases liver uptake of lactate increasing lactate blood levels which may increase the risk of lactic acidosis, especially in patients at risk. If metformin-associated lactic acidosis is suspected, general supportive measures should be instituted promptly in a hospital setting, along with immediate discontinuation of SEGLUROMET. In SEGLUROMET-treated patients with a diagnosis or strong suspicion of lactic acidosis, prompt hemodialysis is recommended to correct the acidosis and remove accumulated metformin (metformin hydrochloride is dialyzable, with a clearance of up to 170 mL/minute under good hemodynamic conditions).
Hemodialysis has often resulted in reversal of symptoms and recovery. Educate patients and their families about the symptoms of lactic acidosis and if these symptoms occur instruct them to discontinue SEGLUROMET and report these symptoms to their healthcare provider. For each of the known and possible risk factors for metformin-associated lactic acidosis, recommendations to reduce the risk of and manage metformin-associated lactic acidosis are provided below: Renal Impairment: The postmarketing metformin-associated lactic acidosis cases primarily occurred in patients with significant renal impairment.
The risk of metformin accumulation and metformin-associated lactic acidosis increases with the severity of renal impairment because metformin is substantially excreted by the kidney [see Warnings and Precautions (5.4) and Clinical Pharmacology (12.3) ] . Before initiating SEGLUROMET, obtain an eGFR. Use of SEGLUROMET is not recommended in patients with an eGFR less than 45 mL/min/1.73 m 2 .
SEGLUROMET is contraindicated in patients…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following important adverse reactions are described elsewhere in the labeling: Lactic Acidosis [see Boxed Warning and Warnings and Precautions (5.1) ] Diabetic Ketoacidosis in Patients with Type 1 Diabetes Mellitus and Other Ketoacidosis [see Warnings and Precautions (5.2) ] Lower Limb Amputation [see Warnings and Precautions (5.3) ] Volume Depletion [see Warnings and Precautions (5.4) ] Genitourinary Infections, including Urosepsis, Pyelonephritis, Necrotizing Fasciitis of the Perineum (Fournier’s Gangrene), and Genital Mycotic Infections [see Warnings and Precautions (5.5) ] Hypoglycemia with Concomitant Use with Insulin or Insulin Secretagogues [see Warnings and Precautions (5.6) ] Vitamin B 12 Deficiency [see Warnings and Precautions (5.7) ] Most common adverse reactions associated with ertugliflozin (incidence ≥5%) were female genital mycotic infections.
( 6.1 ) Most common adverse reactions associated with metformin (incidence ≥5%) were diarrhea, nausea, vomiting, flatulence, abdominal discomfort, indigestion, asthenia, and headache. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Merck Sharp & Dohme LLC at 1-877-888-4231 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Ertugliflozin and Metformin Hydrochloride The incidence and type of adverse reactions in the two 26-week, placebo-controlled trials of ertugliflozin 5 mg and 15 mg added to metformin HCl, representing a majority of data from the three 26-week, placebo-controlled trials, were similar to the adverse reactions described in Table 1 .
Ertugliflozin Pool of Placebo-Controlled Trials The data in Table 1 are derived from a pool of three 26-week, placebo-controlled trials. Ertugliflozin was used as monotherapy in one trial and as add-on therapy in two trials [see Clinical Studies (14) ] . These data reflect exposure of 1,029 patients to ertugliflozin with a mean exposure duration of approximately 25 weeks.
Patients received ertugliflozin 5 mg (N=519), ertugliflozin 15 mg (N=510), or placebo (N=515) once daily. The mean age of the population was 57 years and 2% were older than 75 years of age. Fifty-three percent (53%) of the population was male and 73% were White, 15% were Asian, and 7% were Black or African American.
At baseline the population had diabetes for an average of 7.5 years, had a mean HbA1c of 8.1%, and 19.4% had established microvascular complications of diabetes. Baseline renal function (mean eGFR 88.9 mL/min/1.73 m 2 ) was normal or mildly impaired in 97% of patients and moderately impaired in 3% of patients. Table 1 shows common adverse reactions associated with the use of ertugliflozin.
These adverse reactions were not present at baseline, occurred more commonly on ertugliflozin than on placebo, and occurred in at least 2% of patients treated with either ertugliflozin 5 mg or ertugliflozin 15 mg. Table 1: Adverse Reactions Reported in ≥2% of Patients with Type 2 Diabetes Mellitus Treated with Ertugliflozin The three placebo-controlled studies included one monotherapy trial and two add-on combination trials with metformin HCl or with metformin HCl and sitagliptin. and Greater than Placebo in Pooled Placebo-Controlled Clinical Studies of Ertugliflozin Monotherapy or Combination Therapy Number (%) of Patients Placebo N = 515 Ertugliflozin 5 mg N = 519 Ertugliflozin 15 mg N = 510 Female genital mycotic infections Includes: genital candidiasis, genital infection fungal, vaginal infection, vulvitis, vulvovaginal candidiasis, vulvovaginal mycotic infection, and vulvovaginitis.
Percentages calculated with the number of female patients in each group as denominator: placebo (N=235), ertugliflozin 5 mg (N=252), ertugliflozin 15 mg (N=24…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 3: Clinically Significant Drug Interactions with SEGLUROMET Carbonic Anhydrase Inhibitors Clinical Impact: The risk of lactic acidosis may increase due to concomitant use of Topiramate or other carbonic anhydrase inhibitors (e.g., zonisamide, acetazolamide or dichlorphenamide) with metformin. These drugs frequently cause a decrease in serum bicarbonate and induce non-anion gap, hyperchloremic metabolic acidosis. Intervention: more frequent monitoring of these patients.
Drugs that Reduce Metformin Clearance Clinical Impact: The risk of lactic acidosis may increase due to concomitant use of drugs that interfere with common renal tubular transport systems involved in the renal elimination of metformin (e.g., organic cationic transporter-2 [OCT2] / multidrug and toxin extrusion [MATE] inhibitors such as ranolazine, vandetanib, dolutegravir, and cimetidine) which increase systemic exposure to metformin Intervention Consider the benefits and risks of concomitant use. Alcohol Clinical Impact: Potentiate the effect of metformin on lactate metabolism.
Intervention: Warn patients against excessive alcohol intake while receiving SEGLUROMET. Insulin or Insulin Secretagogues Clinical Impact: The risk of hypoglycemia is increased when ertugliflozin is used in combination with insulin or an insulin secretagogue. Intervention: A lower dose of insulin or insulin secretagogue may be required to minimize the risk of hypoglycemia when used in combination with SEGLUROMET.
Drugs that Affect Glycemic Control Clinical Impact: Certain drugs tend to produce hyperglycemia and may lead to loss of glycemic control. These drugs include the thiazides and other diuretics, corticosteroids, phenothiazines, thyroid products, estrogens, oral contraceptives, phenytoin, nicotinic acid, sympathomimetics, calcium channel blocking drugs, and isoniazid. Intervention: When a patient is receiving SEGLUROMET along with such drugs, the patient should be closely observed to maintain adequate glycemic control.
Lithium Clinical Impact: Concomitant use of an SGLT2 inhibitor with lithium may decrease serum lithium concentrations. Intervention: Monitor serum lithium concentration more frequently during SEGLUROMET initiation and dosage changes. Positive Urine Glucose Test Clinical Impact: SGLT2 inhibitors increase urinary glucose excretion and will lead to positive urine glucose tests.
Intervention: Monitoring glycemic control with urine glucose tests is not recommended in patients taking SEGLUROMET. Use alternative methods to monitor glycemic control. Interference with 1,5-anhydroglucitol (1,5-AG) Assay Clinical Impact: Measurements of 1,5-AG are unreliable in assessing glycemic control in patients taking SGLT2 inhibitors.
Intervention: Monitoring glycemic control with 1,5-AG assay is not recommended. Use alternative methods to monitor glycemic control. Carbonic Anhydrase Inhibitors: May increase risk of lactic acidosis.
Consider more frequent monitoring. ( 7 ) Drugs that Reduce Metformin Clearance: May increase risk of lactic acidosis. Consider benefits and risks of concomitant use.
( 7 ) See full prescribing information for additional drug interactions and information on interference of SEGLUROMET with laboratory tests. ( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Advise females of the potential risk to a fetus, especially during the second and third trimesters. ( 8.1 ) Lactation: Breastfeeding not recommended. ( 8.2 ) Females and Males of Reproductive Potential: Advise premenopausal females of the potential for an unintended pregnancy.
( 8.3 ) Geriatrics: Higher incidence of adverse reactions related to reduced intravascular volume. ( 8.5 ) Renal impairment: Higher incidence of adverse reactions related to reduced intravascular volume and renal function. ( 8.6 ) Hepatic impairment : Avoid use in patients with hepatic impairment.
( 8.7 )
8.1Pregnancy Risk Summary Based on animal data showing adverse renal effects, from ertugliflozin, SEGLUROMET is not recommended during the second and third trimesters of pregnancy. Published studies with metformin use during pregnancy have not reported a clear association with metformin and major birth defect or miscarriage risk (see Data ) . The limited available data with SEGLUROMET in pregnant women are not sufficient to determine a drug-associated risk for major birth defects or miscarriage.
There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy (see Clinical Considerations ) . In animal studies, adverse renal changes were observed in rats when ertugliflozin was administered during a period of renal development corresponding to the late second and third trimesters of human pregnancy. Doses approximately 13 times the maximum clinical dose caused renal pelvic and tubule dilatations and renal mineralization that were not fully reversible.
There was no evidence of fetal harm in rats or rabbits at exposures of ertugliflozin approximately 300 times higher than the maximal clinical dose of 15 mg/day when administered during organogenesis (see Data ) . The estimated background risk of major birth defects is 6-10% in women with pre-gestational diabetes with a HbA1c >7 and has been reported to be as high as 20-25% in women with HbA1c >10. The estimated background risk of miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity.
Data Human Data Published data from postmarketing studies have not reported a clear association with metformin and major birth defects, miscarriage, or adverse maternal or fetal outcomes when metformin was used during pregnancy. However, these studies cannot definitely establish the absence of any metformin-associated risk because of methodological limitations, including small sample size and inconsistent comparator groups. Animal Data Ertugliflozin When ertugliflozin was orally administered to juvenile rats from PND 21 to PND 90, increased kidney weight, renal tubule and renal pelvis dilatation, and renal mineralization occurred at doses greater than or equal to 5 mg/kg (13-fold human exposures, based on AUC).
These effects occurred with drug exposure during periods of renal development in rats that correspond to the late second and third trimester of human renal development, and did not fully reverse within a 1-month recovery period. In embryo-fetal development studies, ertugliflozin (50, 100 and 250 mg/kg/day) was administered orally to rats on gestation days 6 to 17 and to rabbits on gestation days 7 to 19. Ertugliflozin did not adversely affect developmental outcomes in rats and rabbits at maternal exposures that were approximately 300 times the human exposure at the maximum clinical dose of 15 mg/day, based on AU…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on animal data showing adverse renal effects, from ertugliflozin, SEGLUROMET is not recommended during the second and third trimesters of pregnancy. Published studies with metformin use during pregnancy have not reported a clear association with metformin and major birth defect or miscarriage risk (see Data ) . The limited available data with SEGLUROMET in pregnant women are not sufficient to determine a drug-associated risk for major birth defects or miscarriage.
There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy (see Clinical Considerations ) . In animal studies, adverse renal changes were observed in rats when ertugliflozin was administered during a period of renal development corresponding to the late second and third trimesters of human pregnancy. Doses approximately 13 times the maximum clinical dose caused renal pelvic and tubule dilatations and renal mineralization that were not fully reversible.
There was no evidence of fetal harm in rats or rabbits at exposures of ertugliflozin approximately 300 times higher than the maximal clinical dose of 15 mg/day when administered during organogenesis (see Data ) . The estimated background risk of major birth defects is 6-10% in women with pre-gestational diabetes with a HbA1c >7 and has been reported to be as high as 20-25% in women with HbA1c >10. The estimated background risk of miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity.
Data Human Data Published data from postmarketing studies have not reported a clear association with metformin and major birth defects, miscarriage, or adverse maternal or fetal outcomes when metformin was used during pregnancy. However, these studies cannot definitely establish the absence of any metformin-associated risk because of methodological limitations, including small sample size and inconsistent comparator groups. Animal Data Ertugliflozin When ertugliflozin was orally administered to juvenile rats from PND 21 to PND 90, increased kidney weight, renal tubule and renal pelvis dilatation, and renal mineralization occurred at doses greater than or equal to 5 mg/kg (13-fold human exposures, based on AUC).
These effects occurred with drug exposure during periods of renal development in rats that correspond to the late second and third trimester of human renal development, and did not fully reverse within a 1-month recovery period. In embryo-fetal development studies, ertugliflozin (50, 100 and 250 mg/kg/day) was administered orally to rats on gestation days 6 to 17 and to rabbits on gestation days 7 to 19. Ertugliflozin did not adversely affect developmental outcomes in rats and rabbits at maternal exposures that were approximately 300 times the human exposure at the maximum clinical dose of 15 mg/day, based on AUC.
A maternally toxic dose (250 mg/kg/day) in rats (707 times the clinical dose) was associated with reduced fetal viability and a higher incidence of a visceral malformation (membranous ventricular septal defect). In the pre- and post-natal development study in pregnant rats, ertugliflozin was administered to the dams from gestation day 6 through lactation day 21 (weaning). Decreased post-natal growth (weight gain) was observed at maternal doses ≥100 mg/kg/day (greater than or equal to 331 times the human exposure at the maximum clinical dose of 15 mg/day, based on AUC).
Metformin HCl Metformin did not adversely affec…
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of SEGLUROMET in pediatric patients under 18 years of age have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use SEGLUROMET No dosage adjustment of SEGLUROMET is recommended based on age. Elderly patients are more likely to have decreased renal function. Because renal function abnormalities can occur after initiating ertugliflozin, and metformin is known to be substantially excreted by the kidneys, care should be taken in dose selection in the elderly.
Assess renal function in elderly patients prior to initiating dosing and periodically thereafter [see Dosage and Administration (2.1) and Warnings and Precautions (5.1 , 5.4) ] . Ertugliflozin In ertugliflozin clinical trials, a total of 876 (25.7%) patients treated with ertugliflozin were 65 years and older, and 152 (4.5%) patients treated with ertugliflozin were 75 years and older. Patients 65 years and older had a higher incidence of adverse reactions related to volume depletion compared to younger patients; events were reported in 1.1%, 2.2%, and 2.6% of patients treated with comparator, ertugliflozin 5 mg, and ertugliflozin 15 mg, respectively [see Warnings and Precautions (5.4) and Adverse Reactions (6.1) ] .
In VERTIS CV, a total of 2780 (50.5%) patients treated with ertugliflozin were 65 years and older, and 595 (10.8%) patients treated with ertugliflozin were 75 years and older. Safety and efficacy were generally similar for patients age 65 years and older compared to patients younger than 65. Metformin HCl Controlled clinical studies of metformin did not include sufficient numbers of elderly patients to determine whether they respond differently from younger patients, although other reported clinical experience has not identified differences in responses between the elderly and young patients.
In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy and the higher risk of lactic acidosis. Assess renal function more frequently in elderly patients [see Contraindications (4) , Warnings and Precautions (5.1) and Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE SEGLUROMET In the event of an overdose with SEGLUROMET, contact the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdosage management recommendations. Employ the usual supportive measures as dictated by the patient's clinical status. Ertugliflozin Removal of ertugliflozin by hemodialysis has not been studied.
Metformin HCl Overdose of metformin hydrochloride has occurred, including ingestion of amounts greater than 50 g (25 times the maximum recommended daily dose). Hypoglycemia was reported in approximately 10% of cases, but no causal association with metformin hydrochloride has been established. Lactic acidosis has been reported in approximately 32% of metformin overdose cases [see Warnings and Precautions (5.1) ] .
Metformin is dialyzable with a clearance of up to 170 mL/min under good hemodynamic conditions. Therefore, hemodialysis may be useful for removal of accumulated drug from patients in whom metformin overdosage is suspected.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action SEGLUROMET SEGLUROMET combines two antihyperglycemic agents with complementary mechanisms of action to improve glycemic control in patients with type 2 diabetes mellitus: ertugliflozin, a SGLT2 inhibitor, and metformin hydrochloride, a member of the biguanide class. Ertugliflozin SGLT2 is the predominant transporter responsible for reabsorption of glucose from the glomerular filtrate back into the circulation. Ertugliflozin is an inhibitor of SGLT2.
By inhibiting SGLT2, ertugliflozin reduces renal reabsorption of filtered glucose and lowers the renal threshold for glucose, and thereby increases urinary glucose excretion. Metformin HCl Metformin is an antihyperglycemic agent which improves glucose tolerance in patients with type 2 diabetes mellitus, lowering both basal and postprandial plasma glucose. Its pharmacologic mechanisms of action are different from other classes of oral antihyperglycemic agents.
Metformin decreases hepatic glucose production, decreases intestinal absorption of glucose, and improves insulin sensitivity by increasing peripheral glucose uptake and utilization. Metformin does not produce hypoglycemia in either patients with type 2 diabetes mellitus or normal subjects (except in special circumstances) [see Warnings and Precautions (5.6) ] and does not cause hyperinsulinemia. With metformin therapy, insulin secretion remains unchanged while fasting insulin levels and day-long plasma insulin response may actually decrease.
12.2Pharmacodynamics Ertugliflozin Urinary Glucose Excretion and Urinary Volume Dose-dependent increases in the amount of glucose excreted in urine were observed in healthy subjects and in patients with type 2 diabetes mellitus following single- and multiple-dose administration of ertugliflozin. Dose-response modeling indicates that ertugliflozin 5 mg and 15 mg result in near maximal urinary glucose excretion (UGE). Enhanced UGE is maintained after multiple-dose administration.
UGE with ertugliflozin also results in increases in urinary volume. Cardiac Electrophysiology The effect of ertugliflozin on QTc interval was evaluated in a Phase 1 randomized, placebo- and positive-controlled 3-period crossover study in 42 healthy subjects. At 6.7 times the therapeutic exposures with maximum recommended dose, ertugliflozin does not prolong QTc to any clinically relevant extent.
12.3Pharmacokinetics General Introduction Ertugliflozin The pharmacokinetics of ertugliflozin are similar in healthy subjects and patients with type 2 diabetes mellitus. The steady state mean plasma AUC and C max were 398 ng∙hr/mL and 81.3 ng/mL, respectively, with 5 mg ertugliflozin once-daily treatment, and 1,193 ng∙hr/mL and 268 ng/mL, respectively, with 15 mg ertugliflozin once-daily treatment. Steady-state is reached after 4 to 6 days of once-daily dosing with ertugliflozin.
Ertugliflozin does not exhibit time-dependent pharmacokinetics and accumulates in plasma up to 10-40% following multiple dosing. Absorption SEGLUROMET The effects of a high-fat meal on the pharmacokinetics of ertugliflozin and metformin when administered as SEGLUROMET tablets are comparable to those reported for the individual tablets. Food had no meaningful effect on AUC inf of ertugliflozin and metformin, but reduced mean ertugliflozin C max by approximately 41% and metformin C max by approximately 29% compared to the fasted condition.
Ertugliflozin Following single-dose oral administration of 5 mg and 15 mg of ertugliflozin, peak plasma concentrations of ertugliflozin occur at 1 hour postdose (median T max ) under fasted conditions. Plasma C max and AUC of ertugliflozin increase in a dose-proportional manner following single doses from 0.5 mg (0.1 times the lowest recommended dose) to 300 mg (20 times the highest recommended dose) and following multiple doses from 1 mg (0.2 times the lowest recommended dose) to 100 mg (6.7 times the highest recommended dose).
The absolute oral bioavailability of…
🧬 Mechanism of Action ▾
12.1Mechanism of Action SEGLUROMET SEGLUROMET combines two antihyperglycemic agents with complementary mechanisms of action to improve glycemic control in patients with type 2 diabetes mellitus: ertugliflozin, a SGLT2 inhibitor, and metformin hydrochloride, a member of the biguanide class. Ertugliflozin SGLT2 is the predominant transporter responsible for reabsorption of glucose from the glomerular filtrate back into the circulation. Ertugliflozin is an inhibitor of SGLT2.
By inhibiting SGLT2, ertugliflozin reduces renal reabsorption of filtered glucose and lowers the renal threshold for glucose, and thereby increases urinary glucose excretion. Metformin HCl Metformin is an antihyperglycemic agent which improves glucose tolerance in patients with type 2 diabetes mellitus, lowering both basal and postprandial plasma glucose. Its pharmacologic mechanisms of action are different from other classes of oral antihyperglycemic agents.
Metformin decreases hepatic glucose production, decreases intestinal absorption of glucose, and improves insulin sensitivity by increasing peripheral glucose uptake and utilization. Metformin does not produce hypoglycemia in either patients with type 2 diabetes mellitus or normal subjects (except in special circumstances) [see Warnings and Precautions (5.6) ] and does not cause hyperinsulinemia. With metformin therapy, insulin secretion remains unchanged while fasting insulin levels and day-long plasma insulin response may actually decrease.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING SEGLUROMET (ertugliflozin and metformin hydrochloride) tablets are available as follows: Strength Description How Supplied NDC ertugliflozin 2.5 mg and metformin hydrochloride 500 mg tablets pink, oval, debossed with “2.5/500” on one side and plain on the other side unit-of-use bottles of 60 0006-5369-03 unit-of-use bottles of 180 0006-5369-06 ertugliflozin 2.5 mg and metformin hydrochloride 1,000 mg tablets pink, oval, debossed with “2.5/1000” on one side and plain on the other side unit-of-use bottles of 60 0006-5373-03 unit-of-use bottles of 180 0006-5373-06 ertugliflozin 7.5 mg and metformin hydrochloride 500 mg tablets red, oval, debossed with “7.5/500” on one side and plain on the other side unit-of-use bottles of 60 0006-5370-03 unit-of-use bottles of 180 0006-5370-06 ertugliflozin 7.5 mg and metformin hydrochloride 1,000 mg tablets red, oval, debossed with “7.5/1000” on one side and plain on the other side unit-of-use bottles of 60 0006-5374-03 unit-of-use bottles of 180 0006-5374-06 Store at 20°C-25°C (68°F-77°F), excursions permitted between 15°C-30°C (between 59°F-86°F) [see USP Controlled Room Temperature].
Protect from moisture. Store in a dry place.
📦 Storage and Handling ▾
Store at 20°C-25°C (68°F-77°F), excursions permitted between 15°C-30°C (between 59°F-86°F) [see USP Controlled Room Temperature]. Protect from moisture. Store in a dry place.
📋 Description ▾
11 DESCRIPTION SEGLUROMET (ertugliflozin and metformin hydrochloride) tablet for oral use contains ertugliflozin L-pyroglutamic acid, a SGLT2 inhibitor, and metformin HCl, a member of the biguanide class. Ertugliflozin The chemical name of ertugliflozin L-pyroglutamic acid is (1 S ,2 S ,3 S ,4 R ,5 S )-5-(4-chloro-3-(4-ethoxybenzyl)phenyl)-1-(hydroxymethyl)-6,8-dioxabicyclo[3.2.1]octane-2,3,4-triol, compound with (2 S )-5-oxopyrrolidine-2-carboxylic acid. The molecular formula is C 27 H 32 ClNO 10 and the molecular weight is 566.00.
The chemical structure is: Ertugliflozin L-pyroglutamic acid is a white to off-white powder that is soluble in ethyl alcohol and acetone, slightly soluble in ethyl acetate and acetonitrile and very slightly soluble in water. Chemical Structure Metformin HCl Metformin hydrochloride ( N , N -dimethylimidodicarbonimidic diamide hydrochloride) is not chemically or pharmacologically related to any other classes of oral antihyperglycemic agents. The structural formula is as shown: Metformin HCl is a white to off-white crystalline compound with a molecular formula of C 4 H 11 N 5 ∙HCl and a molecular weight of 165.63.
Metformin hydrochloride is freely soluble in water and is practically insoluble in acetone, ether and chloroform. The pK a of metformin is 12.4. The pH of a 1% aqueous solution of metformin hydrochloride is 6.68.
SEGLUROMET is available as film-coated tablets containing: 3.24 mg ertugliflozin L-pyroglutamic acid equivalent to 2.5 mg of ertugliflozin and 500 mg metformin HCl (SEGLUROMET 2.5/500) 3.24 mg ertugliflozin L-pyroglutamic acid equivalent to 2.5 mg of ertugliflozin and 1,000 mg metformin HCl (SEGLUROMET 2.5/1000) 9.71 mg ertugliflozin L-pyroglutamic acid equivalent to 7.5 mg of ertugliflozin and 500 mg metformin HCl (SEGLUROMET 7.5/500) 9.71 mg ertugliflozin L-pyroglutamic acid equivalent to 7.5 mg of ertugliflozin and 1,000 mg metformin HCl (SEGLUROMET 7.5/1000) Inactive ingredients are povidone, microcrystalline cellulose, crospovidone, sodium lauryl sulfate, and magnesium stearate.
The film coating contains: hypromellose, hydroxypropyl cellulose, titanium dioxide, iron oxide red, and carnauba wax. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Lactic Acidosis Inform patients of the risks of lactic acidosis due to the metformin component, its symptoms, and conditions that predispose to its development [see Warnings and Precautions (5.1) ] . Advise patients to discontinue SEGLUROMET immediately and to notify their doctor promptly if unexplained hyperventilation, malaise, myalgia, unusual somnolence, slow or irregular heartbeat, sensation of feeling cold (especially in the extremities), or other nonspecific symptoms occur.
GI symptoms are common during initiation of metformin treatment and may occur during initiation of SEGLUROMET therapy; however, advise patients to consult their doctor if they develop unexplained symptoms. Although GI symptoms that occur after stabilization are unlikely to be drug related, such an occurrence of symptoms should be evaluated to determine if it may be due to metformin-induced lactic acidosis or other serious disease. Diabetic Ketoacidosis in Patients with Type 1 Diabetes Mellitus and Other Ketoacidosis Inform patients that SEGLUROMET can cause potentially fatal ketoacidosis and that type 2 diabetes mellitus and pancreatic disorders (e.g., history of pancreatitis or pancreatic surgery) are risk factors.
Educate all patients on precipitating factors (such as insulin dose reduction or missed insulin doses, infection, reduced caloric intake, ketogenic diet, surgery, dehydration, and alcohol abuse) and symptoms of ketoacidosis (including nausea, vomiting, abdominal pain, tiredness, and labored breathing). Inform patients that blood glucose may be normal even in the presence of ketoacidosis. Advise patients that they may be asked to monitor ketones.
If symptoms of ketoacidosis occur, instruct patients to discontinue SEGLUROMET and seek medical attention immediately [see Warnings and Precautions (5.2) ] . Lower Limb Amputation Counsel patients about the importance of routine preventative foot care. Instruct patients to monitor for new pain or tenderness, sores or ulcers, or infections involving the leg or foot and to seek medical advice immediately if such signs or symptoms develop [see Warnings and Precautions (5.3) ] .
Volume Depletion Inform patients that symptomatic hypotension may occur with SEGLUROMET and advise them to contact their doctor if they experience such symptoms [see Warnings and Precautions (5.4) ] . Inform patients that dehydration may increase the risk for hypotension, and to have adequate fluid intake. Genitourinary Infections, including Urosepsis, Pyelonephritis, Necrotizing Fasciitis of the Perineum (Fournier’s Gangrene), and Genital Mycotic Infections Counsel patients that genitourinary infections may occur when taking SEGLUROMET and may become serious.
Educate patients on the symptoms and advise them to seek medical advice if symptoms occur. Specifically, advise patients to promptly seek medical attention if they develop pain or tenderness, redness, or swelling of the genitals or the area from the genitals back to the rectum, along with a fever above 100.4°F or malaise [see Warnings and Precautions (5.5) ] . Hypoglycemia with Concomitant Use of Insulin or Insulin Secretagogue Inform patients that the incidence of hypoglycemia may increase when SEGLUROMET is used with insulin or an insulin secretagogue.
Educate patients or caregivers on the signs and symptoms of hypoglycemia [see Warnings and Precautions (5.6) ] . Fetal Toxicity Advise pregnant patients of the potential risk to a fetus with treatment with SEGLUROMET. Instruct patients to immediately inform their healthcare provider if pregnant or planning to become pregnant [see Use in Specific Populations (8.1) ].
Lactation Advise patients that use of SEGLUROMET is not recommended while breastfeeding [see Use in Specific Populations (8.2) ] . Pregnancy Inform female patients that treatment with metformin may result in an unintended pregnancy in some premen…
💬 Medication Guide ▾
Medication Guide SEGLUROMET ® [seg-LUR-oh-met] (ertugliflozin and metformin hydrochloride) tablets, for oral use This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: 8/2026 Read this Medication Guide carefully before you start taking SEGLUROMET and each time you get a refill.
There may be new information. This information does not take the place of talking with your healthcare provider about your medical condition or your treatment. What is the most important information I should know about SEGLUROMET?
SEGLUROMET may cause serious side effects, including: Lactic Acidosis. Metformin, one of the medicines in SEGLUROMET, can cause a rare but serious condition called lactic acidosis (a buildup of an acid in the blood) that can cause death. Lactic acidosis is a medical emergency and must be treated in the hospital.
Call your healthcare provider right away if you have any of the following symptoms, which could be signs of lactic acidosis: you feel cold in your hands or feet you feel very weak or tired you have trouble breathing you have stomach pains, nausea or vomiting you have a slow or irregular heartbeat you have unusual (not normal) muscle pain you have unusual sleepiness or sleep longer than usual you feel dizzy or lightheaded Most people who have had lactic acidosis had other conditions that, in combination with metformin use, led to the lactic acidosis.
Tell your healthcare provider if you have any of the following, because you have a higher chance for getting lactic acidosis with SEGLUROMET if you: have severe kidney problems or your kidneys are affected by certain x-ray tests that use injectable dye. have liver problems. drink alcohol very often or drink a lot of alcohol in the short term ("binge") drinking. get dehydrated (lose a large amount of body fluids). This can happen if you are sick with a fever, vomiting, or diarrhea. Dehydration can also happen when you sweat a lot with activity or exercise and do not drink enough fluids. have surgery. have a heart attack, severe infection, or stroke. have a genetically inherited disease affecting mitochondria (the energy-producing parts within cells) such as mitochondrial encephalomyopathy with lactic acidosis, and stroke-like episodes (MELAS) syndrome and maternally inherited diabetes and deafness (MIDD).
The best way to keep from having a problem with lactic acidosis from metformin is to tell your healthcare provider if you have any of the problems in the list above. Your healthcare provider may decide to stop your SEGLUROMET for a while if you have any of these things. Diabetic ketoacidosis (increased ketones in your blood or urine) in people with type 1 diabetes and other ketoacidosis.
SEGLUROMET can cause ketoacidosis that can be life-threatening and may lead to death. Ketoacidosis is a serious condition which needs to be treated in a hospital. People with type 1 diabetes have a high risk of getting ketoacidosis.
People with type 2 diabetes or pancreas problems also have an increased risk of getting ketoacidosis. Ketoacidosis can also happen in people who are sick, cannot eat or drink as usual, skip meals, are on a diet high in fat and low in carbohydrates (ketogenic diet), take less than the usual amount of insulin or miss insulin doses, drink too much alcohol, have a loss of too much fluid from the body (volume depletion), or who have surgery. Ketoacidosis can happen even if your blood sugar is less than 250 mg/dL.
Your healthcare provider may ask you to periodically check ketones in your urine or blood. Stop taking SEGLUROMET and call your healthcare provider or get medical help right away if you get any of the following. If possible, check for ketones in your urine or blood, even if your blood sugar is less than 250 mg/dL: nausea vomiting stomach-area (abdominal) pain tiredness trouble breathing ketones in your urine or blood Amputations.
SEGLUROMET may increase your risk of lower limb amputations. You may be at a higher risk of lo…