
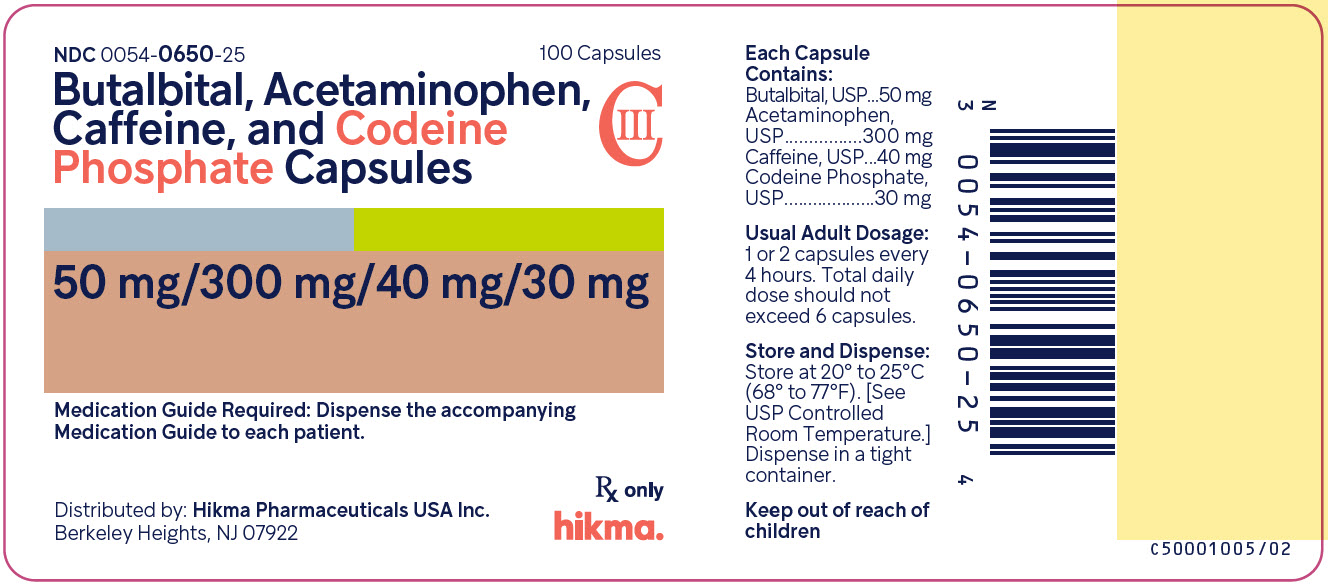
Butalbital, Acetaminophen, Caffeine and Codeine Phosphate 50 mg; 300 mg; 40 mg; 30 mg Capsule, 100-count — NDC 0054-0650-25 (Billing 00054-0650-25)
This is a package of 100 capsules of Butalbital, Acetaminophen, Caffeine and Codeine Phosphate 50 mg; 300 mg; 40 mg; 30 mg Capsule from Hikma Pharmaceuticals USA Inc., marketed since May 2022 and currently FDA-listed; retail pharmacies pay about $5.30 per capsule (NADAC). It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 071253
- GCN: 34988
- GPI-14 (Medi-Span): 65991004100113
- HICL (First Databank): 001713
- AHFS class code: 28:08.08.00
- RxCUI (RxNorm): 993943
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Anilides class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Acetaminophen, butalbital, and caffeine is used to relieve tension headaches. Acetaminophen, butalbital, and caffeine is in a class of medications called combination analgesics (pain relievers). This medication works by decreasing pain, slowing the nervous system, and narrowing swollen blood vessels in the head to provide tension headache relief.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $5.297 | $529.70 / 100 capsules |
| Medicaid paysCMS SDUD · 12 mo | $5.65 | $565.20 / 100 capsules |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00054-0650-25 You're viewing this Main listing | 100 CAPSULE in 1 BOTTLE | 2022-05-09 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Butalbital, Acetaminophen, Caffeine and Codeine Phosphate 50 mg/1; 300 mg/1; 40 mg/1; 30 mgthis 00054-0650-25 | Hikma | 100 capsules | $5.297 | AB | Availability likely | — |
| Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate 50 mg/1; 300 mg/1; 40 mg/1; 30 mg 00591-2641-01 | Actavis | 100 capsules | $5.297 | AB | Availability likely | — |
| Fioricet with Codeine 50 mg/1; 300 mg/1; 40 mg/1; 30 mg 52544-0082-01 | Actavis | 100 capsules | — | AB | Discontinued | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 5138Q19F1X
Ammonia is a colorless gas made from nitrogen and hydrogen. It's used in medicines as a pH buffer to maintain the correct acidity level and help keep the product stable.
-
UNII 92RU3N3Y1O
Dimethicone is a silicone-based oil that acts as an anti-foaming agent and lubricant in medicines. It reduces gas bubbles in liquid formulations and helps coat and protect the stomach lining when ingested.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SERIOUS AND LIFE-THREATENING RISKS FROM USE OF BUTALBITAL, ACETAMINOPHEN, CAFFEINE, AND CODEINE PHOSPHATE CAPSULES Addiction, Abuse, and Misuse Because the use of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules exposes patients and other users to the risks of opioid addiction, abuse, and misuse, which can lead to overdose and death, assess each patient’s risk prior to prescribing and reassess all patients regularly for the development of these behaviors and conditions [see Warnings and Precautions ( 5.1 )] .
Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression may occur with use of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules, especially during initiation or following a dosage increase. To reduce the risk of respiratory depression, proper dosing and titration of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules are essential [see Warnings and Precautions ( 5.2 )] . Accidental Ingestion Accidental ingestion of even one dose of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules, especially by children, can result in a fatal overdose of codeine [see Warnings and Precautions ( 5.2 )] .
Risks From Concomitant Use With Benzodiazepines Or Other CNS Depressants Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate [see Warnings and Precautions ( 5.3 ), Drug Interactions ( 7 )] .
Neonatal Opioid Withdrawal Syndrome (NOWS) Advise pregnant women using opioids for an extended period of time of the risk of Neonatal Opioid Withdrawal Syndrome, which may be life-threatening if not recognized and treated. Ensure that management by neonatology experts will be available at delivery [see Warnings and Precautions ( 5.4 )] . Opioid Analgesic Risk Evaluation and Mitigation Strategy (REMS) Healthcare providers are strongly encouraged to complete a REMS-compliant education program and to counsel patients and caregivers on serious risks, safe use, and the importance of reading the Medication Guide with each prescription [see Warnings and Precautions ( 5.5 )] .
Ultra-Rapid Metabolism of Codeine and Other Risk Factors for Life-threatening Respiratory Depression in Children Life-threatening respiratory depression and death have occurred in children who received codeine. Most of the reported cases occurred following tonsillectomy and/or adenoidectomy, and many of the children had evidence of being an ultra-rapid metabolizer of codeine due to a CYP2D6 polymorphism [see Warnings and Precautions ( 5.6 )] . Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules are contraindicated in children younger than 12 years of age and in children younger than 18 years of age following tonsillectomy and/or adenoidectomy [see Contraindications ( 4 )] .
Avoid the use of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules in adolescents 12 to 18 years of age who have other risk factors that may increase their sensitivity to the respiratory depressant effects of codeine. Interactions with Drugs Affecting Cytochrome P450 Isoenzymes The effects of concomitant use or discontinuation of cytochrome P450 3A4 inducers, 3A4 inhibitors, or 2D6 inhibitors with codeine are complex. Use of cytochrome P450 3A4 inducers, 3A4 inhibitors, or 2D6 inhibitors with Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules requires careful consideration of the effects on codeine, and the active metabolite, morphine [see Warnings and Precautions ( 5.7 )] .
Hepatotoxicity Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules contain acetaminophen. Acetaminophen… [Excerpted — this section continues on DailyMed.]
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules are indicated for the management of the symptom complex of tension (or muscle contraction) headache when non-opioid analgesic and alternative treatments are inadequate. Limitations of Use • Because of the risks of addiction, abuse, misuse, overdose, and death, which can occur at any dosage or duration, and persist over the course of therapy, [see Warnings and Precautions ( 5.1 )] , reserve opioid analgesics, including Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules, for use in patients for whom alternative treatment options are ineffective, not tolerated, or would be otherwise inadequate to provide sufficient management of pain.
Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules are a combination product of butalbital, a barbiturate; acetaminophen; caffeine, a methylxanthine; and codeine phosphate, an opioid agonist; and is indicated for the management of the symptom complex of tension (or muscle contraction) headache, when other non-opioid analgesic and alternative treatments are inadequate. ( 1 ) Limitations of Use • Because of the risks of addiction, abuse, misuse, overdose, and death, which can occur at any dosage or duration, and persist over the course of therapy, reserve opioid analgesics, including Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules, for use in patients for whom alternative treatment options are ineffective, not tolerated, or would be otherwise inadequate to provide sufficient management of pain.
( 1 , 5.1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules should be prescribed only by healthcare professionals who are knowledgeable about the use of opioids and how to mitigate the associated risks. ( 2.1 ) • Use the lowest effective dosage for the shortest duration of time consistent with individual patient treatment goals. Reserve titration to higher doses of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules for patients in whom lower doses are insufficiently effective and in whom the expected benefits of using a higher dose opioid clearly outweigh the substantial risks.
( 2.1 , 5 ) • Many acute pain conditions (e.g., the pain that occurs with a number of surgical procedures or acute musculoskeletal injuries) require no more than a few days of an opioid analgesic. Clinical guidelines on opioid prescribing for some acute pain conditions are available. ( 2.1 ) • Initiate the dosing regimen for each patient individually, taking into account the patient’s underlying cause and severity of pain, prior analgesic treatment and response, and risk factors for addiction, abuse, and misuse.
( 2.1 , 5.1 ) • Respiratory depression can occur at any time during opioid therapy, especially when initiating and following dosage increases with Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules. Consider this risk when selecting an initial dose and when making dose adjustments. ( 2.1 , 5.2 ) • Discuss opioid overdose reversal agents and options for acquiring them with the patient and/or caregiver, both when initiating and renewing treatment with Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate capsules, especially if the patient has additional risk factors for overdose, or close contacts at risk for exposure and overdose.
( 2.2 , 5.1 , 5.2 , 5.3 ) • Initiate treatment with one or two capsules every 4 hours as needed for pain and at the lowest dose necessary to achieve adequate analgesia. Titrate the dose based upon the individual patient’s response to their initial dose of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules. Total daily dosage should not exceed 6 capsules.
( 2.3 , 5 ) • Periodically reassess patients receiving Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules to evaluate the continued need for opioid analgesics to maintain pain control, for the signs or symptoms of adverse reactions, and for the development of addiction, abuse, or misuse. ( 2.4 ) • Do not rapidly reduce or abruptly discontinue Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules in a physically dependent patient because rapid reduction or abrupt discontinuation of opioid analgesics has resulted in serious withdrawal symptoms, uncontrolled pain, and suicide.
( 2.5 , 5.18 )
2.1Important Dosage and Administration Instructions • Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules should be prescribed only by healthcare professionals who are knowledgeable about the use of opioids and how to mitigate the associated risks. • Use the lowest effective dosage for the shortest duration of time consistent with individual patient treatment goals [see Warnings and Precautions ( 5 )] . Because the risk of overdose increases as opioid doses increase, reserve titration to higher doses of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules for patients in whom lower doses are insufficiently effective and in whom the expected benefits of using a higher dose opioid clearly outweigh the substantial risks. • Many acute pain conditions (e.g., the pain that occurs with a number of surgical procedures or acute musculoskeletal injuries) require no more than a few days of an opioid analgesic.
Clinical guidelines on opioid prescribing for some acute pain conditions are available. • There is variability in the opioid analgesic dose and duration needed to adequately manage pain due both to the cause of pain and to individual p… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Butalbital, Acetaminophen, and Caffeine and Codeine Phosphate Capsules, 50 mg/300 mg/40 mg/30mg Butalbital 50 mg, Acetaminophen 300 mg, Caffeine 40 mg, and Codeine Phosphate 30 mg capsules are supplied as a hard gelatin, size 0 capsule, with an opaque deep blue cap printed with “54 640” in white and an opaque white body, printed with “54 640” in black, containing a white to off white powder. Butalbital, Acetaminophen, and Caffeine and Codeine Phosphate Capsules, 50 mg/325 mg/40 mg/30mg Butalbital 50 mg, Acetaminophen 325 mg, Caffeine 40 mg, and Codeine Phosphate 30 mg capsules are supplied as a hard gelatin, size 0 capsule, with an opaque blue cap printed with “54 066” in white and an opaque gray to grayish pink body, printed with “54 066” in black, containing a white to off white powder. • Capsules: 50 mg butalbital, 300 mg acetaminophen, 40 mg caffeine, and 30 mg codeine phosphate. • Capsules: 50 mg butalbital, 325 mg acetaminophen, 40 mg caffeine, and 30 mg codeine phosphate.
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules are contraindicated for: • All children younger than 12 years of age [see Warnings and Precautions ( 5.6 )] . • Post-operative management in children younger than 18 years of age following tonsillectomy and/or adenoidectomy [see Warnings and Precautions ( 5.6 )] . Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules are also contraindicated in patients with: • Significant respiratory depression [see Warnings and Precautions ( 5.2 )] • Acute or severe bronchial asthma in an unmonitored setting or in the absence of resuscitative equipment [see Warnings and Precautions ( 5.10 )] • Concurrent use of monoamine oxidase inhibitors (MAOIs) or use of MAOIs within the last 14 days [see Warnings and Precautions ( 5.11 ), Drug Interactions ( 7 )] • Known or suspected gastrointestinal obstruction, including paralytic ileus [see Warnings and Precautions ( 5.15 )] • Known intolerance or hypersensitivity to acetaminophen, caffeine, butalbital, or codeine or to the components of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules • Porphyria • Children younger than 12 years of age.
( 4 ) • Post-operative management in children younger than 18 years of age following tonsillectomy and/or adenoidectomy. ( 4 ) • Significant respiratory depression. ( 4 ) • Acute or severe bronchial asthma in an unmonitored setting or in absence of resuscitative equipment.
( 4 ) • Concurrent use of monoamine oxidase inhibitors (MAOIs) or use of MAOIs within the last 14 days. ( 4 ) • Known or suspected gastrointestinal obstruction, including paralytic ileus. ( 4 ) • Intolerance or hypersensitivity to acetaminophen, caffeine, butalbital or codeine, or components of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules.
( 4 ) • Porphyria. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Opioid-Induced Hyperalgesia and Allodynia : Opioid-Induced Hyperalgesia (OIH) occurs when an opioid analgesic paradoxically causes an increase in pain, or an increase in sensitivity to pain. If OIH is suspected, carefully consider appropriately decreasing the dose of the current opioid analgesic or opioid rotation. ( 5.9 ) • Life-Threatening Respiratory Depression in Patients with Chronic Pulmonary Disease or in Elderly, Cachectic, or Debilitated Patients: Regularly evaluate patients, particularly during initiation and titration.
( 5.10 ) • Adrenal Insufficiency: If diagnosed, treat with physiologic replacement of corticosteroids, and wean patient off of the opioid. ( 5.12 ) • Severe Hypotension: Regularly evaluate patients during dosage initiation and titration. Avoid use of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules in patients with circulatory shock.
( 5.13 ) • Risks of Use in Patients with Increased Intracranial Pressure, Brain Tumors, Head Injury, or Impaired Consciousness: Monitor for sedation and respiratory depression. Avoid use of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules in patients with impaired consciousness or coma. ( 5.14 )
5.1Addiction, Abuse, and Misuse Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules contain codeine. Codeine in combination with butalbital, acetaminophen, and caffeine is a Schedule III controlled substance. As Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules contain butalbital and codeine, they expose users to the risks of addiction, abuse, and misuse [see Drug Abuse and Dependence ( 9 )].
Although the risk of addiction in any individual is unknown, it can occur in patients appropriately prescribed Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules. Addiction can occur at recommended dosages and if the drug is misused or abused. The risk of opioid-related overdose or overdose-related death is increased with higher opioid doses, and this risk persists over the course of therapy.
In postmarketing studies, addiction, abuse, misuse, and fatal and non-fatal opioid overdose were observed in patients with long-term opioid use [see Adverse Reactions ( 6 )] . Assess each patient’s risk for addiction, abuse, or misuse prior to prescribing Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules, and reassess all patients receiving Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules for the development of these behaviors and conditions. Risks are increased in patients with a personal or family history of substance abuse (including drug or alcohol abuse or addiction) or mental illness (e.g., major depression).
The potential for these risks should not, however, prevent the proper management of pain in any given patient. Patients at increased risk may be prescribed opioids such as Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules but use in such patients necessitates intensive counseling about the risks and proper use of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules along with frequent reevaluation for signs of addiction, abuse, and misuse. Consider recommending or prescribing an opioid overdose reversal agent [see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.2 )] .
Opioids and barbiturates are sought for nonmedical use and are subject to diversion from legitimate prescribed use. Consider these risks when prescribing or dispensing Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules. Strategies to reduce these risks include prescribing the drug in the smallest appropriate quantity and advising the patient on careful storage of the drug during the course of treatment and on the proper disposal of unused drug .
Contact local state professional licensing board or state-controlled substances authority for information on how to prevent and detect abuse or diversion of this product… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described, or described in greater detail, in other sections: • Addiction, Abuse, and Misuse [see Warnings and Precautions ( 5.1 )] • Life-Threatening Respiratory Depression [see Warnings and Precautions ( 5.2 )] • Interactions with Benzodiazepines and other CNS Depressants [see Warnings and Precautions ( 5.3 )] • Neonatal Opioid Withdrawal Syndrome [see Warnings and Precautions ( 5.4 )] • Ultra-Rapid Metabolism of Codeine and Other Risk Factors for Life-Threatening Respiratory Depression in Children [see Warnings and Precautions ( 5.6 )] • Hepatotoxicity [see Warnings and Precautions ( 5.8 )] • Opioid-Induced Hyperalgesia and Allodynia [see Warnings and Precautions ( 5.9 )] • Adrenal Insufficiency [see Warnings and Precautions ( 5.12 )] • Severe Hypotension [see Warnings and Precautions ( 5.13 )] • Gastrointestinal Adverse Reactions [see Warnings and Precautions ( 5.15 )] • Anaphylaxis [see Warnings and Precautions ( 5.16 )] • Seizures [see Warnings and Precautions ( 5.17 )] • Withdrawal [see Warnings and Precautions ( 5.18 )] • Serious Skin Reactions [see Warnings and Precautions ( 5.20 )] The following adverse reactions associated with the use of butalbital, acetaminophen, caffeine, and codeine phosphate were identified in clinical studies or post-marketing reports.
Because some of these reactions were reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Frequently Observed The most frequently reported adverse reactions were drowsiness, lightheadedness, dizziness, sedation, shortness of breath, nausea, vomiting, abdominal pain, and intoxicated feeling. Infrequently Observed All adverse events tabulated below are classified as infrequent.
Central Nervous : headache, shaky feeling, tingling, agitation, fainting, fatigue, heavy eyelids, high energy, hot spells, numbness, sluggishness, seizure. Mental confusion, excitement or depression can also occur due to intolerance, particularly in elderly or debilitated patients, or due to overdosage of butalbital. Autonomic Nervous : dry mouth, hyperhidrosis.
Gastrointestinal : difficulty swallowing, heartburn, flatulence, constipation. Cardiovascular : tachycardia. Musculoskeletal: leg pain, muscle fatigue.
Genitourinary: diuresis. Miscellaneous : pruritus, fever, earache, nasal congestion, tinnitus, euphoria, allergic reactions. The following adverse reactions have been voluntarily reported as temporally associated with Butalbital, Aspirin, Caffeine, and Codeine Phosphate Capsules, a related product containing aspirin, butalbital, caffeine, and codeine phosphate.
Central Nervous : abuse, addiction, anxiety, disorientation, hallucination, hyperactivity, insomnia, libido decrease, nervousness, neuropathy, psychosis, sexual activity increase, slurred speech, twitching, unconsciousness, vertigo. Autonomic Nervous : epistaxis, flushing, miosis, salivation. Gastrointestinal : anorexia, appetite increased, diarrhea, esophagitis, gastroenteritis, gastrointestinal spasms, hiccup, mouth burning, pyloric ulcer.
Cardiovascular : chest pain, hypotensive reaction, palpitations, syncope. Skin : erythema, erythema multiforme, exfoliative dermatitis, hives, rash, toxic epidermal necrolysis. Urinary : kidney impairment, urinary difficulty.
Miscellaneous : allergic reaction, anaphylactic shock, cholangiocarcinoma, drug interaction with erythromycin (stomach upset), edema. The following adverse reactions have been reported with the components of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules. Potential effects of high dosage are listed in the OVERDOSAGE section.
Acetaminophen : allergic reactions, rash, thrombocytopenia, agranulocytosis. Caffeine : cardiac stimulation, irritability, tremor, dependence, nephrotoxicity, hyperglycemia. Codeine : nausea, vomiting, drowsiness, lightheadedness, constipation,… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 1 includes clinically significant drug interactions with Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules. Table 1: Clinically Significant Drug Interactions with Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules Inhibitors of CYP3A4 Clinical Impact: The concomitant use of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules with CYP3A4 inhibitors may result in an increase in codeine plasma concentrations with subsequently greater metabolism by cytochrome CYP2D6, resulting in greater morphine levels, which could increase or prolong adverse reactions and may cause potentially fatal respiratory depression, particularly when an inhibitor is added after a stable dose of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules is achieved [see Warnings and Precautions ( 5.7 )] .
After stopping a CYP3A4 inhibitor, as the effects of the inhibitor decline, it may result in lower codeine levels, greater norcodeine levels, and less metabolism via 2D6 with resultant lower morphine levels [see Clinical Pharmacology ( 12.3 )] , resulting in decreased opioid efficacy or a withdrawal syndrome in patients who had developed physical dependence to codeine. Intervention: If concomitant use with CYP3A4 inhibitor is necessary, consider dosage reduction of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules until stable drug effects are achieved.
Evaluate patients at frequent intervals for respiratory depression and sedation. If a CYP3A4 inhibitor is discontinued, consider increasing the Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules dosage until stable drug effects are achieved. Evaluate for signs of opioid withdrawal.
Examples: Macrolide antibiotics (e.g., erythromycin), azole-antifungal agents (e.g., ketoconazole), protease inhibitors (e.g., ritonavir), grapefruit juice CYP3A4 Inducers Clinical Impact: The concomitant use of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules and CYP3A4 inducers can result in lower codeine levels, greater norcodeine levels, and less metabolism via 2D6 with resultant lower morphine levels [see Clinical Pharmacology ( 12.3 )] , resulting in decreased efficacy or onset of a withdrawal syndrome in patients who have developed physical dependence [see Warnings and Precautions ( 5.7 )] .
After stopping a CYP3A4 inducer, as the effects of the inducer decline, the codeine plasma concentration may increase with subsequently greater metabolism by cytochrome CYP2D6, resulting in greater morphine levels [see Clinical Pharmacology ( 12.3 )] , which could increase or prolong both the therapeutic effects and adverse reactions, and may cause serious respiratory depression. Intervention: If concomitant use of a CYP3A4 inducer is necessary, evaluate the patient at frequent intervals for reduced efficacy and signs of opioid withdrawal and consider increasing the Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules dosage as needed.
If a CYP3A4 inducer is discontinued, consider lowering Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules dosage until stable drug effects are achieved. Evaluate patients at frequent intervals for signs of respiratory depression and sedation. Examples: Rifampin, carbamazepine, phenytoin Inhibitors of CYP2D6 Clinical Impact: Codeine is metabolized by CYP2D6 to form morphine.
The concomitant use of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules and CYP2D6 inhibitors can increase the plasma concentration of codeine, but can decrease the plasma concentrations of active metabolite morphine, which could result in reduced analgesic efficacy or symptoms of opioid withdrawal, particularly when an inhibitor is added after a stable dose of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules is achieved [see Clinical Pharmacology ( 12.3 )] . After stopping a CYP2D6 inhibitor, as the effects of the inhibitor de… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Pregnancy: May cause fetal harm. ( 8.1 ) • Lactation: Breastfeeding not recommended. ( 8.2 ) • Geriatric: Respiratory depression has occurred after large initial doses were administered. Increase dosage slowly. ( 8.5 )
8.1Pregnancy Risk Summary Use of opioid analgesics for an extended period of time during pregnancy may cause neonatal opioid withdrawal syndrome [see Warnings and Precautions ( 5.4 )] . Available data with Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules in pregnant women are insufficient to inform a drug-associated risk for major birth defects and miscarriage. There are risks to the mother and infant associated with use of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules for an extended period of time during pregnancy (see Clinical Considerations) .
Animal reproduction studies have not been conducted with the combination of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules or with butalbital alone. In animal reproduction studies, codeine administration during organogenesis has been shown to produce delayed ossification in the offspring of mice at 2.8 times maximum recommended human dose (MRHD) of 180 mg/day, embryolethal and fetotoxic effects in the offspring of rats and hamsters at approximately 4 to 6 times the MRHD, and cranial malformations/cranioschisis in the offspring of hamsters between 2 and 8 times the MRHD.
Reproductive and developmental studies in rats and mice from the published literature identified adverse events at clinically relevant doses with acetaminophen. Treatment of pregnant rats with doses of acetaminophen approximately 2 times the maximum human daily dose (MHDD) showed evidence of fetotoxicity and increases in bone variations in the fetuses. In another study, necrosis was observed in the liver and kidney of both pregnant rats and fetuses at doses approximately 2 times the MHDD.
In mice treated with acetaminophen at doses within the clinical dosing range, cumulative adverse effects on reproduction were seen in a continuous breeding study. A reduction in number of litters of the parental mating pair was observed as well as retarded growth and abnormal sperm in their offspring and reduced birth weight in the next generation [ see Data ]. The background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Use of opioid analgesics for an extended period of time during pregnancy for medical or nonmedical purposes can result in physical dependence in the neonate and neonatal opioid withdrawal syndrome shortly after birth.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea and failure to gain weight. The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn. Observe newborns for symptoms of neonatal opioid withdrawal syndrome and manage accordingly [see Warnings and Precautions ( 5.4 )] .
Labor or Delivery Use of codeine during labor may lead to respiratory depression in the neonate. Opioids cross the placenta and may produce respiratory depression and psycho-physiologic effects in neonates. An opioid overdose reversal agent, such as naloxone or nalmefene, must be available for reversal of opioid-induced respiratory depression in the neonate.
Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules are not recommended for use in pregnant women during or immediately prior to labor, when other… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Use of opioid analgesics for an extended period of time during pregnancy may cause neonatal opioid withdrawal syndrome [see Warnings and Precautions ( 5.4 )] . Available data with Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules in pregnant women are insufficient to inform a drug-associated risk for major birth defects and miscarriage. There are risks to the mother and infant associated with use of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules for an extended period of time during pregnancy (see Clinical Considerations) .
Animal reproduction studies have not been conducted with the combination of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules or with butalbital alone. In animal reproduction studies, codeine administration during organogenesis has been shown to produce delayed ossification in the offspring of mice at 2.8 times maximum recommended human dose (MRHD) of 180 mg/day, embryolethal and fetotoxic effects in the offspring of rats and hamsters at approximately 4 to 6 times the MRHD, and cranial malformations/cranioschisis in the offspring of hamsters between 2 and 8 times the MRHD.
Reproductive and developmental studies in rats and mice from the published literature identified adverse events at clinically relevant doses with acetaminophen. Treatment of pregnant rats with doses of acetaminophen approximately 2 times the maximum human daily dose (MHDD) showed evidence of fetotoxicity and increases in bone variations in the fetuses. In another study, necrosis was observed in the liver and kidney of both pregnant rats and fetuses at doses approximately 2 times the MHDD.
In mice treated with acetaminophen at doses within the clinical dosing range, cumulative adverse effects on reproduction were seen in a continuous breeding study. A reduction in number of litters of the parental mating pair was observed as well as retarded growth and abnormal sperm in their offspring and reduced birth weight in the next generation [ see Data ]. The background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Use of opioid analgesics for an extended period of time during pregnancy for medical or nonmedical purposes can result in physical dependence in the neonate and neonatal opioid withdrawal syndrome shortly after birth.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea and failure to gain weight. The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn. Observe newborns for symptoms of neonatal opioid withdrawal syndrome and manage accordingly [see Warnings and Precautions ( 5.4 )] .
Labor or Delivery Use of codeine during labor may lead to respiratory depression in the neonate. Opioids cross the placenta and may produce respiratory depression and psycho-physiologic effects in neonates. An opioid overdose reversal agent, such as naloxone or nalmefene, must be available for reversal of opioid-induced respiratory depression in the neonate.
Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules are not recommended for use in pregnant women during or immediately prior to labor, when other analgesic techniques are more appropriate. Opioid analgesics, including Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules, can prolong labor through actions which temporarily reduce the strength, duration, and frequency of uterine c… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules in pediatric patients have not been established. Life-threatening respiratory depression and deaths have occurred in children who received codeine [see Warnings and Precautions ( 5.6 )] . In most of the reported cases, these events followed tonsillectomy and/or adenoidectomy, and many of the children had evidence of being ultra-rapid metabolizers of codeine (i.e., multiple copies of the gene for cytochrome P450 isoenzyme 2D6 or high morphine concentrations).
Children with sleep apnea may be particularly sensitive to the respiratory depressant effects of codeine. Because of the risk of life-threatening respiratory depression and death: • Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules are contraindicated for all children younger than 12 years of age [see Contraindications ( 4 )] . • Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules are contraindicated for post-operative management in pediatric patients younger than 18 years of age following tonsillectomy and/or adenoidectomy [see Contraindications ( 4 )] . • Avoid the use of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules in adolescents 12 to 18 years of age who have other risk factors that may increase their sensitivity to the respiratory depressant effects of codeine unless the benefits outweigh the risks.
Risk factors include conditions associated with hypoventilation, such as post-operative status, obstructive sleep apnea, obesity, severe pulmonary disease, neuromuscular disease, and concomitant use of other medications that cause respiratory depression [see Warnings and Precautions ( 5.6 )].
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
Butalbital is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function. Elderly patients (aged 65 years or older) may have increased sensitivity to Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules.
In general, use caution when selecting a dosage for an elderly patient, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy. Respiratory depression is the chief risk for elderly patients treated with opioids and has occurred after large initial doses were administered to patients who were not opioid-tolerant or when opioids were co-administered with other agents that depress respiration.
Titrate the dosage of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules slowly in geriatric patients and frequently reevaluate the patient for signs of respiratory depression [see Warnings and Precautions ( 5.10 )]. Components of this product are known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to regularly evaluate renal function.
🆘 Overdosage ▾
10 OVERDOSAGE Clinical Presentation Acute overdose with codeine can be manifested by respiratory depression, somnolence progressing to stupor or coma, skeletal muscle flaccidity, cold and clammy skin, constricted pupils, and, in some cases, pulmonary edema, bradycardia, hypotension, hypoglycemia, partial or complete airway obstruction, atypical snoring, and death. Marked mydriasis rather than miosis may be seen with hypoxia in overdose situations [see Clinical Pharmacology ( 12.2 )] . Toxic leukoencephalopathy has been reported after opioid overdose and can present hours, days, or weeks after apparent recovery from the initial intoxication.
Signs and Symptoms Symptoms attributable to acute barbiturate poisoning include drowsiness, confusion, and coma; respiratory depression; hypotension; and hypovolemic shock. Toxicity from codeine poisoning includes the opioid triad of: pinpoint pupils, depression of respiration, and loss of consciousness. Convulsions may occur.
In acetaminophen overdosage: dose dependent, potentially fatal hepatic necrosis is the most serious adverse effect. Renal tubular necrosis, hypoglycemic coma, and coagulation defects may also occur. Early symptoms following a potentially hepatotoxic overdose may include: nausea, vomiting, diaphoresis, and general malaise.
Clinical and laboratory evidence of hepatic toxicity may not be apparent until 48 to 72 hours post-ingestion. Acute caffeine poisoning may cause insomnia, restlessness, tremor, and delirium, tachycardia, and extrasystoles. Treatment of Overdose In case of overdose, priorities are the re-establishment of a patent and protected airway and institution of assisted or controlled ventilation, if needed.
Employ other supportive measures (including oxygen and vasopressors) in the management of circulatory shock and pulmonary edema as indicated. Cardiac arrest or arrhythmias will require advanced life-support measures. For clinically significant respiratory or circulatory depression secondary to opioid overdose, administer an opioid overdose reversal agent such as naloxone or nalmefene.
Because the duration of opioid reversal is expected to be less than the duration of action of codeine in Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules, carefully monitor the patient until spontaneous respiration is reliably re-established. If the response to an opioid overdose reversal agent is suboptimal or only brief in nature, administer additional reversal agent as directed by the product’s prescribing information. In an individual physically dependent on opioids, administration of the recommended usual dosage of the opioid overdose reversal agent will precipitate an acute withdrawal syndrome.
The severity of the withdrawal symptoms experienced will depend on the degree of physical dependence and the dose of the reversal agent administered. If a decision is made to treat serious respiratory depression in the physically dependent patient, administration of the reversal agent should be initiated with care and by titration with smaller than usual doses of the antagonist. A single or multiple drug overdose with Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules is a potentially lethal polydrug overdose, and consultation with a regional poison control center is recommended.
Immediate treatment includes support of cardiorespiratory function and measures to reduce drug absorption. Oxygen, intravenous fluids, vasopressors, and other supportive measures should be employed as indicated. Assisted or controlled ventilation should also be considered.
For respiratory depression due to overdosage or unusual sensitivity to codeine, parenteral naloxone is a specific and effective antagonist. Gastric decontamination with activated charcoal should be administered just prior to N-acetylcysteine (NAC) to decrease systemic absorption if acetaminophen ingestion is known or suspected to have occurred within a few hours of presentation. Serum acetaminophen le… [Excerpted — this section continues on DailyMed.]
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Butalbital, a barbiturate, is a GABA A receptor agonist and may inhibit excitatory AMPA receptors. The precise mechanism of the analgesic properties of acetaminophen is not established but is thought to involve central actions. Caffeine is a methylxanthine and CNS stimulant.
The exact mechanism with respect to the indication is not clear; however, the effects of caffeine may be due to antagonism of adenosine receptors. Codeine is an opioid agonist relatively selective for the mu-opioid receptor, but with a much weaker affinity than morphine. The analgesic properties of codeine have been speculated to come from its conversion to morphine, although the exact mechanism of analgesic action remains unknown.
12.2Pharmacodynamics Effects on the Central Nervous System Butalbital, a barbiturate, is a central nervous system (CNS) depressant that can produce sedation, respiratory depression, and euphoria. The potential impact of butalbital on painful stimuli is not clear and in some individuals barbiturates may increase reaction to painful stimuli. Codeine produces respiratory depression by direct action on brain stem respiratory centers.
The respiratory depression involves a reduction in the responsiveness of the brain stem respiratory centers to both increases in carbon dioxide tension and to electrical stimulation. Codeine causes miosis, even in total darkness. Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origins may produce similar findings).
Marked mydriasis rather than miosis may be seen due to hypoxia in overdose situations. Acetaminophen has been shown to have analgesic activity in animal and human studies. Effects on the Gastrointestinal Tract and Other Smooth Muscle Codeine causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum.
Digestion of food in the small intestine is delayed and propulsive contractions are decreased. Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm resulting in constipation. Other opioid-induced effects may include a reduction in biliary and pancreatic secretions, spasm of sphincter of Oddi, transient elevations in serum amylase, and opioid-induced esophageal dysfunction (OIED).
Effects on the Cardiovascular System Butalbital may decrease blood pressure and heart rate when administered at sedative and hypnotic doses. Codeine produces peripheral vasodilation which may result in orthostatic hypotension or syncope. Manifestations of histamine release and/or peripheral vasodilation may include pruritus, flushing, red eyes and sweating and/or orthostatic hypotension.
Effects on the Endocrine System Opioids inhibit the secretion of adrenocorticotropic hormone (ACTH), cortisol, and luteinizing hormone (LH) in humans [see Adverse Reactions ( 6 )] . They also stimulate prolactin, growth hormone (GH) secretion, and pancreatic secretion of insulin and glucagon. Use of opioids for an extended period of time may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility.
The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date [see Adverse Reactions ( 6 )] . Effects on the Immune System Opioids have been shown to have a variety of effects on components of the immune system in in vitro and animal models. The clinical significance of these findings is unknown.
Overall, the effects of opioids appear to be modestly immunosuppressive. Concentration–Efficacy Relationships The minimum effective analgesic concentration will vary widely among patients, espec… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Butalbital, a barbiturate, is a GABA A receptor agonist and may inhibit excitatory AMPA receptors. The precise mechanism of the analgesic properties of acetaminophen is not established but is thought to involve central actions. Caffeine is a methylxanthine and CNS stimulant.
The exact mechanism with respect to the indication is not clear; however, the effects of caffeine may be due to antagonism of adenosine receptors. Codeine is an opioid agonist relatively selective for the mu-opioid receptor, but with a much weaker affinity than morphine. The analgesic properties of codeine have been speculated to come from its conversion to morphine, although the exact mechanism of analgesic action remains unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules, 50 mg/300 mg/40 mg/30mg: Hard gelatin, size 0 capsule, with an opaque deep blue cap printed with “54 640” in white and an opaque white body, printed with “54 640” in black, containing a white to off white powder. NDC 0054- 0650 -25: Bottle of 100 Capsules Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules, 50 mg/325 mg/40 mg/30mg: Hard gelatin, size 0 capsule, with an opaque blue cap printed with “54 066” in white and an opaque gray to grayish pink body, printed with “54 066” in black, containing a white to off white powder.
NDC 0054- 3000 -01: Bottle of 100 Capsules Store at 20 to 25°C (68 to 77°F) [see USP Controlled Room Temperature]. Dispense in a tight container. Store Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules securely and dispose of properly.
📋 Description ▾
11 DESCRIPTION Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules are supplied in two strength combinations in capsule form for oral administration. Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules, 50 mg/300 mg/40 mg/30 mg contain: Butalbital, USP……………………50 mg Acetaminophen, USP…………….300 mg Caffeine, USP……………………..40 mg Codeine Phosphate, USP………….30 mg Butalbital, Acetaminophen, Caffeine and Codeine Phosphate Capsules, 50 mg/325 mg/40 mg/30 mg contain: Butalbital, USP……………………50 mg Acetaminophen, USP…………….325 mg Caffeine, USP……………………..40 mg Codeine Phosphate, USP………….30 mg Butalbital, USP (5-allyl-5-isobutylbarbituric acid), is a short-to intermediate-acting barbiturate.
It has the following structural formula: C 11 H 16 N 2 O 3 MW = 224.26 Acetaminophen, USP (4´-hydroxyacetanilide), is a non-opiate, non-salicylate analgesic and antipyretic. It has the following structural formula: C 8 H 9 NO 2 MW = 151.16 Caffeine, USP (1,3,7-trimethylxanthine), a methylxanthine, is a central nervous system stimulant. It has the following structural formula: C 8 H 10 N 4 O 2 MW = 194.19 Codeine Phosphate, USP (7,8-Didehydro-4,5α-epoxy-3-methoxy-17-methylmorphinan-6α-ol phosphate (1:1)(salt) hemihydrate) is an opioid agonist.
It has the following structural formula: C 18 H 21 NO 3 •H 3 PO 4 •1/2H 2 O MW = 406.37 Inactive Ingredients : pregelatinized starch. colloidal silicon dioxide, magnesium stearate. The capsule cap is printed with white ink. The white ink contains shellac glaze, titanium dioxide, ammonium hydroxide, propylene glycol, and simethicone.
The capsule body is printed with black ink. The black ink contains shellac glaze, iron oxide black, propylene glycol, and ammonium hydroxide. The capsule shell contains: gelatin, titanium dioxide for both strengths and FD&C red #40, FD&C blue #1 in the Butalbital, Acetaminophen, Caffeine and Codeine Phosphate Capsules, 50 mg/300 mg/40mg/30mg and FD&C red #3, FD&C blue #2, red iron oxide, yellow iron oxide in the Butalbital, Acetaminophen, Caffeine and Codeine Phosphate Capsules, 50 mg/325 mg/40mg/30mg. image-butalbital-usp-chem-structure image-acetaminophen-usp-chem-structure image-caffeine-usp-chem-structure codeine-phosphate-structural-formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Storage and Disposal Because of the risks associated with accidental ingestion, misuse, and abuse, advise patients to store Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules securely, out of sight and reach of children, and in a location not accessible by others, including visitors to the home [see Warnings and Precautions ( 5.1 , 5.2 ), Drug Abuse and Dependence ( 9.2 )] . Inform patients that leaving Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules unsecured can pose a deadly risk to others in the home.
Advise patients and caregivers that when medicines are no longer needed, they should be disposed of promptly. Inform patients that medicine take-back options are the preferred way to safely dispose of most types of unneeded medicines. If no take back programs or DEA-registered collectors are available, instruct patients to dispose of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules by following these four steps: • Mix Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules (do not crush) with an unpalatable substance such as dirt, cat litter, or used coffee grounds; • Place the mixture in a container such as a sealed plastic bag; • Throw the container in the household trash; • Remove all personal information on the prescription label of the empty bottle Inform patients that they can visit www.fda.gov/drugdisposal for additional information on disposal of unused medicines.
Addiction, Abuse, and Misuse Inform patients that the use of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules, even when taken as recommended, can result in addiction, abuse, and misuse, which can lead to overdose and death [see Warnings and Precautions ( 5.1 )]. Instruct patients not to share Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules with others and to take steps to protect Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules from theft or misuse. Life-Threatening Respiratory Depression Inform patients of the risk of life-threatening respiratory depression, including information that the risk is greatest when starting Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules or when the dosage is increased, and that it can occur even at recommended dosages.
Educate patients and caregivers on how to recognize respiratory depression and emphasize the importance of calling 911 or getting emergency medical help right away in the event of a known or suspected overdose [see Warnings and Precautions ( 5.2 )] . Accidental Ingestion Inform patients that accidental ingestion, especially by children, may result in respiratory depression or death [see Warnings and Precautions ( 5.2 )] . Risks from Concomitant Use with Benzodiazepines or Other CNS Depressants Inform patients and caregivers that potentially fatal additive effects may occur if Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules are used with benzodiazepines or other CNS depressants, including alcohol (e.g., non-benzodiazepine sedative/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, gabapentinoids [gabapentin or pregabalin], and other opioids), and not to use these concomitantly unless supervised by a healthcare provider [see Warnings and Precautions ( 5.3 ), Drug Interactions ( 7 )] .
Patient Access to an Opioid Overdose Reversal Agent for the Emergency Treatment of Opioid Overdose Inform patients and caregivers about opioid overdose reversal agents (e.g., naloxone, nalmefene). Discuss the importance of having access to an opioid overdose reversal agent, especially if the patient has risk factors for overdose (e.g., concomitant use of CNS depressants, a history of opioid use disorder, or prior opioid overdose) or if there are household members (including children) or other close contacts at risk… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
Medication Guide Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules, CIII Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules are: • A strong prescription pain medicine that contains an opioid (narcotic) that is indicated for the relief of the symptom complex of tension (or muscle contraction) headache, when other pain treatments such as non-opioid pain medicines do not treat your pain well enough or you cannot tolerate them. • An opioid pain medicine that can put you at risk for overdose and death.
Even if you take your dose correctly as prescribed you are at risk for opioid addiction, abuse, and misuse that can lead to death. Important information about Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules: • Get emergency help or call 911 right away if you take too much Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules (overdose). When you first start taking Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules, when your dose is changed, or if you take too much (overdose), serious or life-threatening breathing problems that can lead to death may occur.
Ask your healthcare provider about medicines like naloxone or nalmefene that can be used in an emergency to reverse an opioid overdose. • Taking Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules with other opioid medicines, benzodiazepines, gabapentinoids (gabapentin or pregabalin), alcohol, or other central nervous system depressants (including street drugs) can cause severe drowsiness, decreased awareness, breathing problems, coma, and death. • Never give anyone else your Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules.
They could die from taking it. Selling or giving away Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules is against the law. • Store Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules securely, out of sight and reach of children, and in a location not accessible by others, including visitors to the home. • Get emergency help right away if you take more than 4,000 mg of acetaminophen in 1 day. Taking Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules with other products that contain acetaminophen can lead to serious liver problems and death.
Important Information Guiding Use in Pediatric Patients: • Do not give Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules to a child younger than 12 years of age. • Do not give Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules to a child younger than 18 years of age after surgery to remove the tonsils and/or adenoids. • Avoid giving Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules to children between 12 to 18 years of age who have risk factors for breathing problems such as obstructive sleep apnea, obesity, or underlying lung problems.
Do not take Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules if you have: • severe asthma, trouble breathing, or other lung problems. • a bowel blockage or have narrowing of the stomach or intestines. Before taking Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules, tell your healthcare provider if you have a history of: • head injury, seizures • problems urinating • liver, kidney, thyroid problems • pancreas or gall bladder problems • abuse of street or prescription drugs, alcohol addiction, opioid overdose, or mental health problems • have been told by your healthcare provider that you are a “rapid metabolizer” of certain medicines Tell your healthcare provider if you are: • Noticing your pain getting worse.
If your pain gets worse after you take Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules, do not take more of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules without first talking to your healthcare provider. Talk to your healthcare provider if the pain that you have increases, if you feel mor… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The behavior of the individual components is described below. Butalbital Absorption Butalbital is well absorbed from the gastrointestinal tract. Distribution Butalbital is expected to distribute to most tissues in the body.
Barbiturates in general may appear in breast milk and readily cross the placental barrier. They are bound to plasma and tissue proteins to a varying degree and binding increases directly as a function of lipid solubility. The in vitro plasma protein binding of butalbital is 45% over the concentration range of 0.5 to 20 mcg/mL.
This falls within the range of plasma protein binding (20% to 45%) reported with other barbiturates such as phenobarbital, pentobarbital, and secobarbital sodium. The plasma-to-blood concentration ratio was almost unity indicating that there is no preferential distribution of butalbital into either plasma or blood cells. Elimination Elimination of butalbital is primarily via the kidney (59% to 88% of the dose) as unchanged drug or metabolites.
The plasma half-life is about 35 hours. Urinary excretion products include parent drug (about 3.6% of the dose), 5-isobutyl-5-(2,3-dihydroxypropyl) barbituric acid (about 24% of the dose), 5-allyl-5-(3-hydroxy-2-methyl-1-propyl) barbituric acid (about 4.8% of the dose), products with the barbituric acid ring hydrolyzed with excretion of urea (about 14% of the dose), as well as unidentified materials. Of the material excreted in the urine, 32% is conjugated. [See Overdosage ( 10 ) for toxicity information].
Acetaminophen Absorption Acetaminophen is rapidly absorbed from the gastrointestinal tract. Metabolism Acetaminophen is primarily metabolized in the liver by first-order kinetics and involves three principal separate pathways: conjugation with glucuronide; conjugation with sulfate; and oxidation via the cytochrome, P450-dependent, mixed-function oxidase enzyme pathway to form a reactive intermediate metabolite, which conjugates with glutathione and is then further metabolized to form cysteine and mercapturic acid conjugates.
The principal cytochrome P450 isoenzyme involved appears to be CYP2E1, with CYP1A2 and CYP3A4 as additional pathways. Distribution Acetaminophen is distributed throughout most body tissues. A small fraction (10-25%) of acetaminophen is bound to plasma proteins.
Elimination Elimination of acetaminophen is principally by liver metabolism (conjugation) and subsequent renal excretion of metabolites. Approximately 85% of an oral dose appears in the urine within 24 hours of administration, most as the glucuronide conjugate, with small amounts of other conjugates and unchanged drug. The plasma half-life is 1.25 to 3 hours, but may be increased by liver damage and following overdosage. [See Overdosage ( 10 ) for toxicity information].
Caffeine Absorption Like most xanthines, caffeine is rapidly absorbed. Distribution Caffeine is distributed in all body tissues and fluids, including the CNS, fetal tissues, and breast milk. Elimination Caffeine is cleared through metabolism and excretion in the urine.
Metabolism Caffeine is mainly metabolized by CYP1A2. Other enzymes, including CYP2E1, CYP3A4, CYP2C8 and CYP2C9 may play a minor role in its metabolism. Hepatic biotransformation prior to excretion results in about equal amounts of 1-methylxanthine and 1-methyluric acid.
Excretion Of the 70% of the dose that is recovered in the urine, only 3% is unchanged drug. The plasma half-life is about 3 hours . [See Overdosage ( 10 ) for toxicity information]. Codeine Absorption Codeine is readily absorbed from the gastrointestinal tract.
At therapeutic doses, the analgesic effect reaches a peak within 2 hours and persists between 4 and 6 hours. Distribution Codeine is rapidly distributed from the intravascular spaces to the various body tissues, with preferential uptake by parenchymatous organs such as the liver, spleen and kidney. Codeine crosses the blood-brain barrier, and is found in fetal tissue and breast milk.
The pl… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Effects on the Central Nervous System Butalbital, a barbiturate, is a central nervous system (CNS) depressant that can produce sedation, respiratory depression, and euphoria. The potential impact of butalbital on painful stimuli is not clear and in some individuals barbiturates may increase reaction to painful stimuli. Codeine produces respiratory depression by direct action on brain stem respiratory centers.
The respiratory depression involves a reduction in the responsiveness of the brain stem respiratory centers to both increases in carbon dioxide tension and to electrical stimulation. Codeine causes miosis, even in total darkness. Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origins may produce similar findings).
Marked mydriasis rather than miosis may be seen due to hypoxia in overdose situations. Acetaminophen has been shown to have analgesic activity in animal and human studies. Effects on the Gastrointestinal Tract and Other Smooth Muscle Codeine causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum.
Digestion of food in the small intestine is delayed and propulsive contractions are decreased. Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm resulting in constipation. Other opioid-induced effects may include a reduction in biliary and pancreatic secretions, spasm of sphincter of Oddi, transient elevations in serum amylase, and opioid-induced esophageal dysfunction (OIED).
Effects on the Cardiovascular System Butalbital may decrease blood pressure and heart rate when administered at sedative and hypnotic doses. Codeine produces peripheral vasodilation which may result in orthostatic hypotension or syncope. Manifestations of histamine release and/or peripheral vasodilation may include pruritus, flushing, red eyes and sweating and/or orthostatic hypotension.
Effects on the Endocrine System Opioids inhibit the secretion of adrenocorticotropic hormone (ACTH), cortisol, and luteinizing hormone (LH) in humans [see Adverse Reactions ( 6 )] . They also stimulate prolactin, growth hormone (GH) secretion, and pancreatic secretion of insulin and glucagon. Use of opioids for an extended period of time may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility.
The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date [see Adverse Reactions ( 6 )] . Effects on the Immune System Opioids have been shown to have a variety of effects on components of the immune system in in vitro and animal models. The clinical significance of these findings is unknown.
Overall, the effects of opioids appear to be modestly immunosuppressive. Concentration–Efficacy Relationships The minimum effective analgesic concentration will vary widely among patients, especially among patients who have been previously treated with opioid agonists. The minimum effective analgesic concentration of codeine for any individual patient may increase over time due to an increase in pain, the development of a new pain syndrome and/or the development of analgesic tolerance [see Dosage and Administration ( 2.1 , 2.3 )] .
Concentration–Adverse Reaction Relationships There is a relationship between increasing codeine plasma concentration and increasing frequency of dose-related opioid adverse reactions such as nausea, vomiting, CNS effects, and respiratory depression. In opioid-tolerant patients, the situation may be altered by the development of tolerance to opioid-related adverse reactions [see Dosage and Administration ( 2.1 , 2.3… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules contain codeine. Codeine in combination with butalbital, acetaminophen, and caffeine is a Schedule III controlled substance.
9.2Abuse Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules contain codeine, a substance with high potential for misuse and abuse, which can lead to the development of substance use disorder, including addiction [see Warnings and Precautions ( 5.1 )]. Misuse is the intentional use, for therapeutic purposes, of a drug by an individual in a way other than prescribed by a healthcare provider or for whom it was not prescribed. Abuse is the intentional, non-therapeutic use of a drug, even once, for its desirable psychological or physiological effects.
Drug addiction is a cluster of behavioral, cognitive, and physiological phenomena that may include a strong desire to take the drug, difficulties in controlling drug use (e.g., continuing drug use despite harmful consequences, giving a higher priority to drug use than other activities and obligations), and possible tolerance or physical dependence. Misuse and abuse of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules increases risk of overdose, which may lead to central nervous system and respiratory depression, hypotension, seizures, and death.
The risk is increased with concurrent abuse of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules with alcohol and/or other CNS depressants. Abuse of and addiction to opioids in some individuals may not be accompanied by concurrent tolerance and symptoms of physical dependence. In addition, abuse of opioids can occur in the absence of addiction.
All patients treated with opioids require careful and frequent reevaluation for signs of misuse, abuse, and addiction, because use of opioid analgesic products carries the risk of addiction even under appropriate medical use. Patients at high risk of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules abuse include those with a history of prolonged use of any opioid, including products containing codeine, those with a history of drug or alcohol abuse, or those who use Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules in combination with other abused drugs. “Drug-seeking” behavior is very common in persons with substance use disorders.
Drug-seeking tactics include emergency calls or visits near the end of office hours, refusal to undergo appropriate examination, testing, or referral, repeated “loss” of prescriptions, tampering with prescriptions, and reluctance to provide prior medical records or contact information for other treating healthcare provider(s). “Doctor shopping” (visiting multiple prescribers to obtain additional prescriptions) is common among people who abuse drugs and people with substance use disorder. Preoccupation with achieving adequate pain relief can be appropriate behavior in a patient with inadequate pain control.
Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules, like other opioids, can be diverted for nonmedical use into illicit channels of distribution. Careful record keeping of prescribing information, including quantity, frequency, and renewal requests, as required by state and federal law, is strongly advised. Proper assessment of the patient, proper prescribing practices, periodic reevaluation of therapy, and proper dispensing and storage are appropriate measures that help to limit abuse of opioid drugs.
Risks Specific to Abuse of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules Abuse of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules poses a risk of overdose and death. The risk is increased with concurrent use of Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules with alcohol and/or other CNS depressants. Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules… [Excerpted — this section continues on DailyMed.]
🔒 Controlled Substance ▾
9.1Controlled Substance Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules contain codeine. Codeine in combination with butalbital, acetaminophen, and caffeine is a Schedule III controlled substance.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Long-term studies in animals to evaluate the carcinogenic potential of the combination of butalbital, acetaminophen, caffeine, and codeine or butalbital alone have not been conducted. Two-year carcinogenicity studies with codeine sulfate have been conducted in F344/N rats and B6C3F1 mice. There was no evidence of carcinogenicity in male and female rats, respectively, at dietary doses up to 70 and 80 mg/kg/day of codeine sulfate (approximately 4 times the maximum recommended daily dose of 180 mg/day for adults on a mg/m 2 basis) for two years.
Similarly there was no evidence of carcinogenicity activity in male and female mice at dietary doses up to 400 mg/kg/day of codeine sulfate (approximately 10 times the maximum recommended daily dose of 180 mg/day for adults on a mg/m 2 basis) for two years. Long-term studies in mice and rats have been completed by the National Toxicology Program to evaluate the carcinogenic potential of acetaminophen. In 2-year feeding studies, F344/N rats and B6C3F1 mice were fed a diet containing acetaminophen up to 6000 ppm.
Female rats demonstrated equivocal evidence of carcinogenic activity based on increased incidences of mononuclear cell leukemia at 1.6 times the maximum human daily dose (MHDD) of 1950 mg/day, based on a body surface area comparison. In contrast, there was no evidence of carcinogenic activity in male rats that received up to 1.4 times or mice at up to 2.4 to 2.8 times the MHDD, based on a body surface area comparison. In a 2-year study in Sprague-Dawley rats, caffeine (as caffeine base) administered in drinking water was not carcinogenic in male rats at doses up to 102 mg/kg or in female rats at doses up to 170 mg/kg (approximately 4 and 7 times, respectively, the maximum human daily dose on a mg/m 2 basis).
In an 18-month study in C57BL/6 mice, no evidence of tumorigenicity was seen at dietary doses up to 55 mg/kg (equivalent to the MHDD on a mg/m 2 basis). Mutagenesis There are no genetic toxicology data for butalbital. Codeine sulfate was not mutagenic in the in vitro bacterial reverse mutation assay or clastogenic in the in vitro Chinese hamster ovary cell chromosome aberration assay.
In the published literature, acetaminophen has been reported to be clastogenic when administered at 1500 mg/kg/day to the rat model (7.2-times the MHDD, based on a body surface area comparison). In contrast, no clastogenicity was noted at a dose of 750 mg/kg/day (3.6-times the MHDD, based on a body surface area comparison), suggesting a threshold effect. Caffeine (as caffeine base) increased the sister chromatid exchange (SCE) SCE/cell metaphase (exposure time dependent) in an in vivo mouse metaphase analysis.
Caffeine also potentiated the genotoxicity of known mutagens and enhanced the micronuclei formation (5-fold) in folate-deficient mice. However, caffeine did not increase chromosomal aberrations in in vitro Chinese hamster ovary cell (CHO) and human lymphocyte assays and was not mutagenic in an in vitro CHO/hypoxanthine guanine phosphoribosyltransferase (HGPRT) gene mutation assay, except at cytotoxic concentrations. In addition, caffeine was not clastogenic in an in vivo mouse micronucleus assay.
Caffeine was negative in the in vitro bacterial reverse mutation assay (Ames test). Impairment of Fertility No adequate studies have been conducted in animals to characterize the impact of the combinations of butalbital, acetaminophen, caffeine, and codeine on fertility. There are also no data on butalbital alone or codeine alone.
In studies conducted by the National Toxicology Program, fertility assessments with acetaminophen have been completed in Swiss CD-1 mice via a continuous breeding study. There were no effects on fertility parameters in mice consuming up to 3.4 times the MHDD of acetaminophen, based on a body surface area comparison. Although there was no effect on sperm motility or sperm dens… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Long-term studies in animals to evaluate the carcinogenic potential of the combination of butalbital, acetaminophen, caffeine, and codeine or butalbital alone have not been conducted. Two-year carcinogenicity studies with codeine sulfate have been conducted in F344/N rats and B6C3F1 mice. There was no evidence of carcinogenicity in male and female rats, respectively, at dietary doses up to 70 and 80 mg/kg/day of codeine sulfate (approximately 4 times the maximum recommended daily dose of 180 mg/day for adults on a mg/m 2 basis) for two years.
Similarly there was no evidence of carcinogenicity activity in male and female mice at dietary doses up to 400 mg/kg/day of codeine sulfate (approximately 10 times the maximum recommended daily dose of 180 mg/day for adults on a mg/m 2 basis) for two years. Long-term studies in mice and rats have been completed by the National Toxicology Program to evaluate the carcinogenic potential of acetaminophen. In 2-year feeding studies, F344/N rats and B6C3F1 mice were fed a diet containing acetaminophen up to 6000 ppm.
Female rats demonstrated equivocal evidence of carcinogenic activity based on increased incidences of mononuclear cell leukemia at 1.6 times the maximum human daily dose (MHDD) of 1950 mg/day, based on a body surface area comparison. In contrast, there was no evidence of carcinogenic activity in male rats that received up to 1.4 times or mice at up to 2.4 to 2.8 times the MHDD, based on a body surface area comparison. In a 2-year study in Sprague-Dawley rats, caffeine (as caffeine base) administered in drinking water was not carcinogenic in male rats at doses up to 102 mg/kg or in female rats at doses up to 170 mg/kg (approximately 4 and 7 times, respectively, the maximum human daily dose on a mg/m 2 basis).
In an 18-month study in C57BL/6 mice, no evidence of tumorigenicity was seen at dietary doses up to 55 mg/kg (equivalent to the MHDD on a mg/m 2 basis). Mutagenesis There are no genetic toxicology data for butalbital. Codeine sulfate was not mutagenic in the in vitro bacterial reverse mutation assay or clastogenic in the in vitro Chinese hamster ovary cell chromosome aberration assay.
In the published literature, acetaminophen has been reported to be clastogenic when administered at 1500 mg/kg/day to the rat model (7.2-times the MHDD, based on a body surface area comparison). In contrast, no clastogenicity was noted at a dose of 750 mg/kg/day (3.6-times the MHDD, based on a body surface area comparison), suggesting a threshold effect. Caffeine (as caffeine base) increased the sister chromatid exchange (SCE) SCE/cell metaphase (exposure time dependent) in an in vivo mouse metaphase analysis.
Caffeine also potentiated the genotoxicity of known mutagens and enhanced the micronuclei formation (5-fold) in folate-deficient mice. However, caffeine did not increase chromosomal aberrations in in vitro Chinese hamster ovary cell (CHO) and human lymphocyte assays and was not mutagenic in an in vitro CHO/hypoxanthine guanine phosphoribosyltransferase (HGPRT) gene mutation assay, except at cytotoxic concentrations. In addition, caffeine was not clastogenic in an in vivo mouse micronucleus assay.
Caffeine was negative in the in vitro bacterial reverse mutation assay (Ames test). Impairment of Fertility No adequate studies have been conducted in animals to characterize the impact of the combinations of butalbital, acetaminophen, caffeine, and codeine on fertility. There are also no data on butalbital alone or codeine alone.
In studies conducted by the National Toxicology Program, fertility assessments with acetaminophen have been completed in Swiss CD-1 mice via a continuous breeding study. There were no effects on fertility parameters in mice consuming up to 3.4 times the MHDD of acetaminophen, based on a body surface area comparison. Although there was no effect on sperm motility or sperm density in the epididymis, the… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Boxed Warning 12/2025 Indications and Usage ( 1 ) 12/2025 Dosage and Administration ( 2.2 , 2.5 ) 12/2025 Warnings and Precautions ( 5.1 , 5.2 , 5.3 , 5.15 , 5.18 ) 12/2025
📄 Package Label / Principal Display Panel ▾
PACKAGE/LABEL PRINCIPAL DISPLAY PANEL NDC 0054- 0650 -25 100 Capsules Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules CIII 50 mg/300 mg/40 mg/30 mg Rx only 50mg-300mg-40mg-30mg bottle label image
PACKAGE/LABEL PRINCIPAL DISPLAY PANEL NDC 0054- 3000 -01 100 Capsules Butalbital, Acetaminophen, Caffeine, and Codeine Phosphate Capsules CIII 50 mg/325 mg/40 mg/30 mg Rx only 50mg-325mg-40mg-30mg bottle label image