
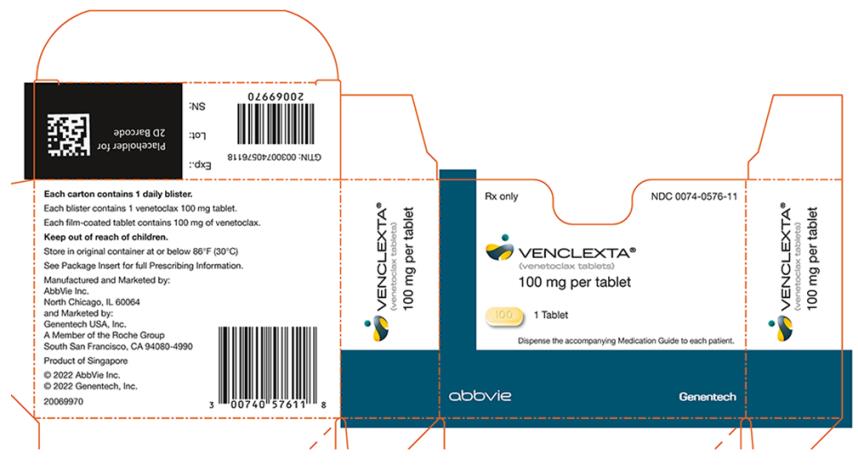
Venclexta Venetoclax 100 mg Tablet, Film Coated, 120-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the BCL-2 Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Venetoclax is a targeted cancer medicine that specifically attacks leukemia cells by blocking a protein called BCL-2, which those cells use to survive. Your doctor likely prescribe...
- What exactly is venetoclax and why has my doctor prescribed it?
- That gradual increase — called the ramp-up schedule — is one of the most important safety measures with this drug. When venetoclax starts killing leukemia cells, it can do so very...
- Why do I have to start at such a low dose and increase it slowly?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Venetoclax — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII L11K75P92J
A mineral salt made from calcium and phosphate. It acts as a filler and binder in tablets to add bulk and help hold the medicine together in solid form.
-
UNII D9C330MD8B
Copovidone is a synthetic polymer made by combining two types of plastic-like molecules. It acts as a binder and film-former to help hold tablet ingredients together and improve how the medicine dissolves in your body.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $131.92 | $15,829.88 / 120 tablets |
| Medicare drug plans payPart D · Q2 2026 | $131.79 | $15,815.35 / 120 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Venclexta 100 mgthis 00074-0576-22 | AbbVie | 120 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9539251 ↗ | Method of use | U-2538 | Sep 6, 2033 |
| US 9539251 ↗ | Method of use | U-2538 | Sep 6, 2033 |
| US 9174982 ↗ | Method of use | U-2537 | May 26, 2030 |
| US 9174982 ↗ | Method of use | U-2445 | May 26, 2030 |
| US 9174982 ↗ | Method of use | U-2323 | May 26, 2030 |
| US 9174982 ↗ | Method of use | U-2323 | May 26, 2030 |
| US 9174982 ↗ | Method of use | U-2537 | May 26, 2030 |
| US 9174982 ↗ | Method of use | U-2446 | May 26, 2030 |
| US 9174982 ↗ | Method of use | U-2537 | May 26, 2030 |
| US 9174982 ↗ | Method of use | U-2445 | May 26, 2030 |
| US 9174982 ↗ | Method of use | U-2446 | May 26, 2030 |
| US 9174982 ↗ | Method of use | U-2445 | May 26, 2030 |
| US 9174982 ↗ | Method of use | U-2446 | May 26, 2030 |
| US 11413282 ↗ | Method of use | U-3412 | Sep 6, 2033 |
| US 11413282 ↗ | Method of use | U-3412 | Sep 6, 2033 |
| US 11413282 ↗ | Method of use | U-3412 | Sep 6, 2033 |
| US 9174982 ↗ | Method of use | U-2323 | May 26, 2030 |
| US 11590128 ↗ | Method of use | U-3548 | Sep 6, 2033 |
| US 11590128 ↗ | Method of use | U-3548 | Sep 6, 2033 |
| US 11590128 ↗ | Method of use | U-3548 | Sep 6, 2033 |
| US 9539251 ↗ | Method of use | U-2538 | Sep 6, 2033 |
| US 10993942 ↗ | Method of use | U-3114 | Sep 6, 2033 |
| US 10993942 ↗ | Method of use | U-3114 | Sep 6, 2033 |
| US 10993942 ↗ | Method of use | U-3114 | Sep 6, 2033 |
| US 11110087 ↗ | Method of use | U-3222 | Sep 6, 2033 |
| US 11110087 ↗ | Method of use | U-3222 | Sep 6, 2033 |
| US 11110087 ↗ | Method of use | U-3222 | Sep 6, 2033 |
| US 11110087 ↗ | Method of use | U-3223 | Sep 6, 2033 |
| US 11110087 ↗ | Method of use | U-3223 | Sep 6, 2033 |
| US 11110087 ↗ | Method of use | U-3223 | Sep 6, 2033 |
| US 8546399 ↗ | Drug substance | — | Jun 27, 2031 |
| US 10730873 ↗ | Drug substance | — | Nov 21, 2031 |
| US 8546399 ↗ | Drug substance | — | Jun 27, 2031 |
| US 11369599 ↗ | Drug product | — | May 23, 2032 |
| US 8546399 ↗ | Drug substance | — | Jun 27, 2031 |
| US 11369599 ↗ | Drug product | — | May 23, 2032 |
| US 10730873 ↗ | Drug substance | — | Nov 21, 2031 |
| US 8722657 ↗ | Drug substance | — | Jan 29, 2032 |
| US 8722657 ↗ | Drug substance | — | Jan 29, 2032 |
| US 11369599 ↗ | Drug product | — | May 23, 2032 |
| US 10730873 ↗ | Drug substance | — | Nov 21, 2031 |
| US 8722657 ↗ | Drug substance | — | Jan 29, 2032 |
| Code | What it grants | Expires |
|---|---|---|
| ODE-239 | Orphan Drug Exclusivity (7-year) | May 15, 2026 |
| ODE-239 | Orphan Drug Exclusivity (7-year) | May 15, 2026 |
| ODE-239 | Orphan Drug Exclusivity (7-year) | May 15, 2026 |
Is there a generic version of VENCLEXTA 100 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00074-0576-11 | 1 BLISTER PACK in 1 CARTON (0074-0576-11) / 1 TABLET, FILM COATED in 1 BLISTER PACK | 2016-04-11 | Active |
| 00074-0576-22 You're viewing this | 120 TABLET, FILM COATED in 1 BOTTLE (0074-0576-22) | 2016-04-11 | Active |
| 00074-0576-30 | 1 BOTTLE in 1 CARTON (0074-0576-30) / 28 TABLET, FILM COATED in 1 BOTTLE | 2022-06-15 | Active |
| 00074-0576-34 | 1 BOTTLE in 1 CARTON (0074-0576-34) / 180 TABLET, FILM COATED in 1 BOTTLE | 2018-11-21 | Discontinued by firm |
In Medicaid, this is the most-dispensed pack of this product — about 76% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 00074-0576-22?
What is the difference between NDC 00074-0576-22 and NDC 00074-0576-11?
What NDC number is used to bill for this package of Venclexta Venetoclax 100 mg Tablet, Film Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE VENCLEXTA is a BCL-2 inhibitor indicated: For the treatment of adult patients with chronic lymphocytic leukemia (CLL) or small lymphocytic lymphoma (SLL). ( 1.1 ) In combination with azacitidine, or decitabine, or low-dose cytarabine for the treatment of newly diagnosed acute myeloid leukemia (AML) in adults 75 years or older, or who have comorbidities that preclude use of intensive induction chemotherapy. ( 1.2 )
1.1Chronic Lymphocytic Leukemia/Small Lymphocytic Lymphoma VENCLEXTA is indicated for the treatment of adult patients with chronic lymphocytic leukemia (CLL) or small lymphocytic lymphoma (SLL).
1.2Acute Myeloid Leukemia VENCLEXTA is indicated in combination with azacitidine, or decitabine, or low-dose cytarabine for the treatment of newly diagnosed acute myeloid leukemia (AML) in adults 75 years or older, or who have comorbidities that preclude use of intensive induction chemotherapy.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION See Full Prescribing Information for recommended VENCLEXTA dosages. ( 2.2 , 2.3 ) Take VENCLEXTA tablets orally once daily with a meal and water. ( 2.8 ) Provide prophylaxis for tumor lysis syndrome. ( 2.1 , 2.4 )
2.1Important Safety Information Assess patient-specific factors for level of risk of tumor lysis syndrome (TLS) and provide prophylactic hydration and anti-hyperuricemics to patients prior to first dose of VENCLEXTA to reduce risk of TLS [see Dosage and Administration ( 2.4 ) and Warnings and Precautions ( 5.1 )].
2.2Recommended Dosage for Chronic Lymphocytic Leukemia/Small Lymphocytic Lymphoma VENCLEXTA dosing begins with a 5-week ramp-up. The 5-week ramp-up dosing schedule is designed to gradually reduce tumor burden (debulk) and decrease the risk of TLS. VENCLEXTA 5-week Dose Ramp-Up Schedule Administer VENCLEXTA according to the 5-week ramp-up dosing schedule to the recommended dosage of 400 mg orally once daily as shown in Table 1 .
Table 1. Dosing Schedule for 5-Week Ramp-up Phase for Patients with CLL/SLL VENCLEXTA Oral Daily Dose Week 1 20 mg Week 2 50 mg Week 3 100 mg Week 4 200 mg Week 5 and beyond 400 mg The CLL/SLL Starting Pack provides the first 4 weeks of VENCLEXTA according to the ramp-up schedule [see How Supplied/Storage and Handling ( 16 )] . In Combination with Acalabrutinib Cycle 1 Day 1: Start acalabrutinib 100 mg orally approximately every 12 hours until disease progression, unacceptable toxicity or completion of 14 cycles of treatment.
Each cycle is 28 days. Refer to the acalabrutinib prescribing information for additional dosing information. Cycle 3 Day 1: start VENCLEXTA according to the 5-week ramp-up dosing schedule (see Table 1 ).
After completing the ramp-up phase, continue VENCLEXTA at a dose of 400 mg orally once daily until disease progression, unacceptable toxicity, or until the last day of Cycle 14. In Combination with Obinutuzumab Start obinutuzumab administration at 100 mg on Cycle 1 Day 1, followed by 900 mg on Cycle 1 Day 2. Administer 1,000 mg on Days 8 and 15 of Cycle 1 and on Day 1 of each subsequent 28-day cycle for a total of 6 cycles.
Refer to the obinutuzumab prescribing information for additional dosing information. On Cycle 1 Day 22, start VENCLEXTA according to the 5-week ramp-up dosing schedule (see Table 1 ). After completing the ramp-up phase on Cycle 2 Day 28, continue VENCLEXTA at a dose of 400 mg orally once daily from Cycle 3 Day 1 until the last day of Cycle 12.
In Combination with Rituximab Start rituximab administration after the patient has completed the 5-week ramp-up dosing schedule for VENCLEXTA (see Table 1 ) and has received VENCLEXTA at the recommended dosage of 400 mg orally once daily for 7 days. Administer rituximab on Day 1 of each 28-day cycle for 6 cycles, at a dose of 375 mg/m 2 intravenously for Cycle 1 and 500 mg/m 2 intravenously for Cycles 2-6. Continue VENCLEXTA 400 mg orally once daily for 24 months from Cycle 1 Day 1 of rituximab.
Refer to the rituximab prescribing information for additional dosing information. Monotherapy The recommended dosage of VENCLEXTA is 400 mg once daily after completion of the 5-week ramp-up dosing schedule (see Table 1 ). Continue VENCLEXTA until disease progression or unacceptable toxicity.
2.3Recommended Dosage for Acute Myeloid Leukemia The recommended dosage and ramp-up of VENCLEXTA depends upon the combination agent. Follow the dosing schedule, including the 3-day or 4-day dose ramp-up, as shown in Table 2. Start VENCLEXTA administration on Cycle 1 Day 1 in combination with: Azacitidine 75 mg/m 2 intravenously or subcutaneously once daily on Days 1-7 of each 28-day cycle; OR Decitabine 20 mg/m 2 intravenously once daily on Days 1-5 of each 28-day cycle; OR Cytarabine 20 mg/m 2 subcutaneously once daily on Days 1-10 of each 28-day cycle.
Table 2. Dosing Schedule for 3- or 4-Day Ramp-up Phase in Patients with AML VENCLEXTA Oral Daily Dose Day 1 100 mg Day 2 200 mg Day 3 400 mg D…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Table 9. VENCLEXTA Tablet Strength and Description Tablet Strength Description of Tablet 10 mg Round, biconvex shaped, pale yellow film-coated tablet debossed with “V” on one side and “10” on the other side 50 mg Oblong, biconvex shaped, beige film-coated tablet debossed with “V” on one side and “50” on the other side 100 mg Oblong, biconvex shaped, pale yellow film-coated tablet debossed with “V” on one side and “100” on the other side Tablets: 10 mg, 50 mg, 100 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Concomitant use of VENCLEXTA with strong CYP3A inhibitors at initiation and during the ramp-up phase is contraindicated in patients with CLL/SLL due to the potential for increased risk of tumor lysis syndrome [see Dosage and Administration ( 2.6 ) and Drug Interactions ( 7.1 )] . Concomitant use with strong CYP3A inhibitors at initiation and during ramp-up phase in patients with CLL/SLL is contraindicated. ( 2.6 , 4 , 7.1 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Tumor Lysis Syndrome (TLS): Anticipate TLS; assess risk in all patients. Premedicate with anti-hyperuricemics and ensure adequate hydration. Employ more intensive measures (intravenous hydration, frequent monitoring, hospitalization) as overall risk increases.
( 2.4 , 5.1 ) Neutropenia: Monitor blood counts. Interrupt dosing and resume at same or reduced dose. Consider supportive care measures.
( 2.5 , 5.2 ) Infections: Monitor for signs and symptoms of infection and treat promptly. Withhold for Grade 3 and 4 infection until resolution and resume at same or reduced dose. ( 2.5 , 5.3 ) Immunization: Do not administer live attenuated vaccines prior to, during, or after treatment with VENCLEXTA until B-cell recovery.
( 5.4 ) Embryo-Fetal Toxicity: May cause embryo-fetal harm. Advise females of reproductive potential of the potential risk to a fetus and to use effective contraception. ( 5.5 ) Treatment of patients with multiple myeloma with VENCLEXTA in combination with bortezomib plus dexamethasone is not recommended outside of controlled clinical trials.
( 5.6 )
5.1Tumor Lysis Syndrome Tumor lysis syndrome (TLS), including fatal events and renal failure requiring dialysis, has occurred in patients treated with VENCLEXTA [see Adverse Reactions ( 6.1 )]. VENCLEXTA can cause rapid reduction in tumor and thus poses a risk for TLS at initiation and during the ramp-up phase in all patients, and during reinitiation after dosage interruption in patients with CLL/SLL. Changes in blood chemistries consistent with TLS that require prompt management can occur as early as 6 to 8 hours following the first dose of VENCLEXTA and at each dose increase.
TLS, including fatal cases, has been reported after a single 20 mg dose of VENCLEXTA. In patients with CLL/SLL who followed the current (5-week) dose ramp-up and the TLS prophylaxis and monitoring measures, the rate of TLS was 2% in the VENCLEXTA CLL/SLL monotherapy trials. The rate of TLS remained consistent with VENCLEXTA in combination with obinutuzumab or rituximab.
With a 2- to 3-week dose ramp-up and higher starting dose in patients with CLL/SLL, the TLS rate was 13% and included deaths and renal failure [see Adverse Reactions ( 6.1 )] . In patients with AML who followed the current 3-day ramp-up dosing schedule and the TLS prophylaxis and monitoring measures, the rate of TLS was 1.1% in patients who received VENCLEXTA in combination with azacitidine (VIALE-A). In patients with AML who followed a 4-day ramp-up dosing schedule and the TLS prophylaxis and monitoring measures, the rate of TLS was 5.6% and included deaths and renal failure in patients who received VENCLEXTA in combination with low-dose cytarabine (VIALE-C) [see Adverse Reactions ( 6.1 )].
The risk of TLS is a continuum based on multiple factors, particularly reduced renal function, tumor burden, and type of malignancy. Splenomegaly may also increase the risk of TLS in patients with CLL/SLL. Assess all patients for risk and provide appropriate prophylaxis for TLS, including hydration and anti-hyperuricemics.
Monitor blood chemistries and manage abnormalities promptly. Employ more intensive measures (intravenous hydration, frequent monitoring, hospitalization) as overall risk increases. Interrupt dosing if needed; when restarting VENCLEXTA, follow dose modification guidance [see Dosage and Administration ( 2.1 , 2.2 , 2.3 , 2.4 ) and Use in Specific Populations ( 8.6 )].
Concomitant use of VENCLEXTA with P-gp inhibitors or strong or moderate CYP3A inhibitors increases venetoclax exposure, which may increase the risk of TLS at initiation and during the ramp-up phase of VENCLEXTA. For patients with CLL/SLL, coadministration of VENCLEXTA with strong CYP3A inhibitors at initiation and during the 5-week ramp-up phase is contraindicated [see Contraindications ( 4 )]. For patients with AML, reduce the dose of VENCLEXTA when coadministered with strong CYP3A inhibitors at initiation and during the 3- or 4-day ra…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Tumor Lysis Syndrome [see Warnings and Precautions ( 5.1 )] Neutropenia [see Warnings and Precautions ( 5.2 )] Infections [see Warnings and Precautions ( 5.3 )] In CLL/SLL, the most common adverse reactions (≥20%) for VENCLEXTA when given in combination with obinutuzumab or rituximab or as monotherapy are neutropenia, thrombocytopenia, anemia, diarrhea, nausea, upper respiratory tract infection, cough, musculoskeletal pain, fatigue, and edema.
( 6.1 ) In CLL/SLL, the most common adverse reactions (≥20%) for VENCLEXTA when given in combination with acalabrutinib are neutropenia, headache, diarrhea, musculoskeletal pain, and COVID-19. ( 6.1 ) In AML, the most common adverse reactions (≥30%) in combination with azacitidine or decitabine or low-dose cytarabine are nausea, diarrhea, thrombocytopenia, constipation, neutropenia, febrile neutropenia, fatigue, vomiting, edema, pyrexia, pneumonia, dyspnea, hemorrhage, anemia, rash, abdominal pain, sepsis, musculoskeletal pain, dizziness, cough, oropharyngeal pain, and hypotension.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact AbbVie Inc. at 1-800-633-9110 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely variable conditions, adverse event rates observed in clinical trials of a drug cannot be directly compared with rates of clinical trials of another drug and may not reflect the rates observed in practice. In CLL/SLL, the safety population reflects exposure to VENCLEXTA as monotherapy in patients in M13-982, M14-032, and M12-175 and in combination with obinutuzumab or rituximab in patients in CLL14 and MURANO. In this CLL/SLL safety population, the most common adverse reactions (≥20%) for VENCLEXTA were neutropenia, thrombocytopenia, anemia, diarrhea, nausea, upper respiratory tract infection, cough, musculoskeletal pain, fatigue, and edema.
In the CLL/SLL safety population that reflects exposure to VENCLEXTA in combination with acalabrutinib, the most common adverse reactions (≥20%) were neutropenia, headache, diarrhea, musculoskeletal pain, and COVID-19. In AML, the safety population reflects exposure to VENCLEXTA in combination with decitabine, azacitidine, or low-dose cytarabine in patients in M14-358, VIALE-A, and VIALE-C. In this safety population, the most common adverse reactions (≥30% in any trial) were nausea, diarrhea, thrombocytopenia, constipation, neutropenia, febrile neutropenia, fatigue, vomiting, edema, pyrexia, pneumonia, dyspnea, hemorrhage, anemia, rash, abdominal pain, sepsis, musculoskeletal pain, dizziness, cough, oropharyngeal pain, and hypotension.
Chronic Lymphocytic Leukemia/Small Lymphocytic Lymphoma VENCLEXTA in Combination with Acalabrutinib The safety of VENCLEXTA in combination with acalabrutinib (VEN+A) (N=291) versus fludarabine plus cyclophosphamide plus rituximab or bendamustine plus rituximab (FCR/BR) (N=259) was evaluated in AMPLIFY, a randomized, multicenter, open-label study in patients with previously untreated CLL [ see Clinical S tudies ( 14.1 ) ] . The median duration of exposure to VENCLEXTA was 11.1 months (range: 2 to 14 months) and to acalabrutinib was 12.9 months (range: 1 to 18 months) in the VEN+A arm.
Among patients who received VEN+A, 96% were exposed for 6 months or longer and 91% were exposed for greater than one year. Serious adverse reactions were reported in 25% of patients receiving VEN+A. The most common adverse reaction (≥2%) were COVID-19 including COVID-19 pneumonia (9%), second primary malignancies (2.7%), and neutropenia (2.1%).
Fatal adverse events occurred in 3.4% of patients. The most common fatal adverse events included COVID-19 and COVID-19 pneumonia. In the VEN+A arm, adverse reactions led to treatment discontinuation in 8% of patients.
Neutropenia led to discontinuation of VENCLEXTA in 0.3% of patients, dose reduc…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Strong or moderate CYP3A inhibitors or P-gp inhibitors: Adjust dosage of VENCLEXTA. ( 2.6 , 7.1 ) Strong or moderate CYP3A inducers: Avoid co-administration. ( 7.1 ) P-gp substrates: Take at least 6 hours before VENCLEXTA. ( 7.2 )
7.1Effects of Other Drugs on VENCLEXTA Strong or Moderate CYP3A Inhibitors or P-gp Inhibitors Concomitant use with a strong or moderate CYP3A inhibitor or a P-gp inhibitor increases venetoclax C max and AUC 0-INF [see Clinical Pharmacology ( 12.3 )] , which may increase VENCLEXTA toxicities, including the risk of TLS [see Warnings and Precautions ( 5.1 )] . Concomitant use with a strong CYP3A inhibitor at initiation and during the ramp-up phase in patients with CLL/SLL is contraindicated [see Contraindications ( 4 )] .
In patients with CLL/SLL taking a steady daily dosage (after ramp-up phase), consider alternative medications or adjust VENCLEXTA dosage and monitor more frequently for adverse reactions [see Dosage and Administration ( 2.5 , 2.6 )] . In patients with AML, adjust VENCLEXTA dosage and monitor more frequently for adverse reactions [see Dosage and Administration ( 2.5 , 2.6 )] . Resume the VENCLEXTA dosage that was used prior to concomitant use with a strong or moderate CYP3A inhibitor or a P-gp inhibitor 2 to 3 days after discontinuation of the inhibitor [see Dosage and Administration ( 2.5 , 2.6 )] .
Avoid grapefruit products, Seville oranges, and starfruit during treatment with VENCLEXTA, as they contain inhibitors of CYP3A. Strong or Moderate CYP3A Inducers Concomitant use with a strong CYP3A inducer decreases venetoclax C max and AUC 0-INF [see Clinical Pharmacology ( 12.3 )] , which may decrease VENCLEXTA efficacy. Avoid concomitant use of VENCLEXTA with strong CYP3A inducers or moderate CYP3A inducers.
7.2Effect of VENCLEXTA on Other Drugs Warfarin Concomitant use of VENCLEXTA increases warfarin C max and AUC 0-INF [see Clinical Pharmacology ( 12.3 )] , which may increase the risk of bleeding. Monitor international normalized ratio (INR) more frequently in patients using warfarin concomitantly with VENCLEXTA. P-gp Substrates Concomitant use of VENCLEXTA increases C max and AUC 0-INF of P-gp substrates [see Clinical Pharmacology ( 12.3 )] , which may increase toxicities of these substrates.
Avoid concomitant use of VENCLEXTA with a P-gp substrate. If a concomitant use is unavoidable, separate dosing of the P-gp substrate at least 6 hours before VENCLEXTA.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise women not to breastfeed. ( 8.2 ) Hepatic Impairment: Reduce the VENCLEXTA dose by 50% in patients with severe hepatic impairment. ( 2.7 , 8.7 )
8.1Pregnancy Risk Summary Based on findings in animals and its mechanism of action [see Clinical Pharmacology ( 12.1 )] , VENCLEXTA may cause embryo-fetal harm when administered to a pregnant woman. There are no available data on VENCLEXTA use in pregnant women to inform a drug-associated risk. Administration of venetoclax to pregnant mice during the period of organogenesis was fetotoxic at exposures 1.2 times the human exposure at the recommended dose of 400 mg daily based on AUC.
Advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal data In embryo-fetal development studies, venetoclax was administered to pregnant mice and rabbits during the period of organogenesis. In mice, venetoclax was associated with increased post-implantation loss and decreased fetal body weight at 150 mg/kg/day (maternal exposures approximately 1.2 times the human exposure at the recommended dose of 400 mg once daily).
No teratogenicity was observed in either the mouse or the rabbit.
8.2Lactation Risk Summary There are no data on the presence of VENCLEXTA in human milk or the effects on the breastfed child or milk production. Venetoclax was present in the milk when administered to lactating rats (see Data) . Because of the potential for serious adverse reactions in a breastfed child, advise women not to breastfeed during treatment with VENCLEXTA and for 1 week after the last dose.
Data Animal Data Venetoclax was administered (single dose; 150 mg/kg oral) to lactating rats 8 to 10 days post-parturition. Venetoclax in milk was 1.6 times lower than in plasma. Parent drug (venetoclax) represented the majority of the total drug-related material in milk, with trace levels of three metabolites.
8.3Females and Males of Reproductive Potential VENCLEXTA may cause fetal harm when administered to pregnant women [see Use in Specific Populations ( 8.1 )] . Pregnancy Testing Verify pregnancy status in females of reproductive potential prior to initiating VENCLEXTA. Contraception Advise females of reproductive potential to use effective contraception during treatment with VENCLEXTA and for 30 days after the last dose.
Infertility Based on findings in animals, VENCLEXTA may impair male fertility [see Nonclinical Toxicology ( 13.1 )] .
8.4Pediatric Use The safety and effectiveness of VENCLEXTA have not been established in pediatric patients. Juvenile Animal Toxicity Data In a juvenile toxicology study, mice were administered venetoclax at 10, 30, or 100 mg/kg/day by oral gavage from 7 to 60 days of age. Clinical signs of toxicity included decreased activity, dehydration, skin pallor, and hunched posture at ≥30 mg/kg/day.
In addition, mortality and body weight effects occurred at 100 mg/kg/day. Other venetoclax-related effects were reversible decreases in lymphocytes at ≥10 mg/kg/day; a dose of 10 mg/kg/day is approximately 0.06 times the clinical dose of 400 mg on a mg/m 2 basis for a 20 kg child.
8.5Geriatric Use Chronic Lymphocytic Leukemia/Small Lymphocytic Lymphoma Of the 352 patients with previously treated CLL/SLL evaluated for safety from 3 open-label trials of VENCLEXTA monotherapy, 57% (201/352) were ≥65 years of age and 18% (62/352) were ≥75 years of age. Of the 406 patients with CLL/SLL evaluated for safety from VENCLEXTA in combination with rituximab or obinutuzumab, 67% (273/406) were ≥65 years of age and 24% (97/406) were ≥75 years of age. No clinically meaningful differences…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings in animals and its mechanism of action [see Clinical Pharmacology ( 12.1 )] , VENCLEXTA may cause embryo-fetal harm when administered to a pregnant woman. There are no available data on VENCLEXTA use in pregnant women to inform a drug-associated risk. Administration of venetoclax to pregnant mice during the period of organogenesis was fetotoxic at exposures 1.2 times the human exposure at the recommended dose of 400 mg daily based on AUC.
Advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal data In embryo-fetal development studies, venetoclax was administered to pregnant mice and rabbits during the period of organogenesis. In mice, venetoclax was associated with increased post-implantation loss and decreased fetal body weight at 150 mg/kg/day (maternal exposures approximately 1.2 times the human exposure at the recommended dose of 400 mg once daily).
No teratogenicity was observed in either the mouse or the rabbit.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of VENCLEXTA have not been established in pediatric patients. Juvenile Animal Toxicity Data In a juvenile toxicology study, mice were administered venetoclax at 10, 30, or 100 mg/kg/day by oral gavage from 7 to 60 days of age. Clinical signs of toxicity included decreased activity, dehydration, skin pallor, and hunched posture at ≥30 mg/kg/day.
In addition, mortality and body weight effects occurred at 100 mg/kg/day. Other venetoclax-related effects were reversible decreases in lymphocytes at ≥10 mg/kg/day; a dose of 10 mg/kg/day is approximately 0.06 times the clinical dose of 400 mg on a mg/m 2 basis for a 20 kg child.
🧓 Geriatric Use ▾
8.5Geriatric Use Chronic Lymphocytic Leukemia/Small Lymphocytic Lymphoma Of the 352 patients with previously treated CLL/SLL evaluated for safety from 3 open-label trials of VENCLEXTA monotherapy, 57% (201/352) were ≥65 years of age and 18% (62/352) were ≥75 years of age. Of the 406 patients with CLL/SLL evaluated for safety from VENCLEXTA in combination with rituximab or obinutuzumab, 67% (273/406) were ≥65 years of age and 24% (97/406) were ≥75 years of age. No clinically meaningful differences in safety and effectiveness were observed between older and younger patients in these studies.
Of patients that received VENCLEXTA in combination with acalabrutinib in AMPLIFY, 33% (97/291) were ≥65 years of age, and 4.5% (13/291) were ≥75 years of age. In patients 65 years of age or older and younger than age 65, the fatal adverse reactions were 5% and 2.6%, respectively. No clinically relevant differences in efficacy were observed between patients ≥65 years of age and younger adults.
Acute Myeloid Leukemia Of the 283 patients who received VENCLEXTA with azacitidine in VIALE-A, 96% were ≥65 years of age and 60% were ≥75 years of age. Of the 13 patients who received VENCLEXTA in combination with decitabine in M14-358, 100% were ≥65 years of age and 62% were ≥75 years of age. Of the 142 patients who received VENCLEXTA in combination with low-dose cytarabine in VIALE-C, 92% were ≥65 years of age and 57% were ≥75 years of age.
Clinical studies of VENCLEXTA in patients with AML did not include sufficient numbers of younger adults to determine if patients 65 years of age and older respond differently from younger adults.
🆘 Overdosage ▾
10 OVERDOSAGE There is no specific antidote for VENCLEXTA. For patients who experience overdose, closely monitor and provide appropriate supportive treatment; during ramp-up phase interrupt VENCLEXTA and monitor carefully for signs and symptoms of TLS along with other toxicities [see Dosage and Administration ( 2.2 , 2.3 , 2.4 , 2.5 )] . Based on venetoclax large volume of distribution and extensive protein binding, dialysis is unlikely to result in significant removal of venetoclax.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Venetoclax is a selective and orally bioavailable small-molecule inhibitor of BCL-2, an anti-apoptotic protein. Overexpression of BCL-2 has been demonstrated in CLL and AML cells where it mediates tumor cell survival and has been associated with resistance to chemotherapeutics. Venetoclax helps restore the process of apoptosis by binding directly to the BCL-2 protein, displacing pro-apoptotic proteins like BIM, triggering mitochondrial outer membrane permeabilization and the activation of caspases.
In nonclinical studies, venetoclax has demonstrated cytotoxic activity in tumor cells that overexpress BCL-2.
12.2Pharmacodynamics Based on the exposure response analyses for efficacy, a relationship between drug exposure and a greater likelihood of response was observed in clinical studies in patients with CLL/SLL, and in patients with AML. Based on the exposure response analyses for safety, a relationship between drug exposure and a greater likelihood of some safety events was observed in clinical studies in patients with AML. No exposure-safety relationship was observed in patients with CLL/SLL at doses up to 1200 mg given as monotherapy and up to 600 mg given in combination with rituximab.
Cardiac Electrophysiology The effect of multiple doses of VENCLEXTA up to 1200 mg once daily (2 times the maximum approved recommended dosage) on the QTc interval was evaluated in an open-label, single-arm trial in 176 patients with previously treated hematologic malignancies. VENCLEXTA had no large effect on QTc interval (i.e., >20 ms) and there was no relationship between venetoclax exposure and change in QTc interval.
12.3Pharmacokinetics Venetoclax mean (± standard deviation) steady state C max was 2.1 ± 1.1 mcg/mL and AUC 0-24h was 32.8 ± 16.9 mcg•h/mL following administration of 400 mg once daily with a low-fat meal. Venetoclax steady state AUC increased proportionally over the dose range of 150 to 800 mg (0.25 to 1.33 times the maximum approved recommended dosage). The pharmacokinetics of venetoclax does not change over time.
Administration of crushed VENCLEXTA tablets has no impact on venetoclax AUC. Absorption Maximum plasma concentration of venetoclax was reached 5 to 8 hours following multiple oral administration under fed conditions. Effect of Food Administration with a low-fat meal (approximately 512 kilocalories, 25% fat calories, 60% carbohydrate calories, and 15% protein calories) increased venetoclax exposure by approximately 3.4-fold and administration with a high-fat meal (approximately 753 kilocalories, 55% fat calories, 28% carbohydrate calories, and 17% protein calories) increased venetoclax exposure by 5.1- to 5.3-fold compared with fasting conditions.
Distribution Venetoclax is highly bound to human plasma protein with unbound fraction in plasma <0.01 across a concentration range of 1-30 micromolar (0.87-26 mcg/mL). The mean blood-to-plasma ratio was 0.57. The apparent volume of distribution (Vd ss /F) of venetoclax ranged from 256-321 L in patients.
Elimination The terminal elimination half-life of venetoclax was approximately 26 hours. Metabolism Venetoclax is predominantly metabolized by CYP3A in vitro. The major metabolite identified in plasma, M27, has an inhibitory activity against BCL-2 that is at least 58-fold lower than venetoclax in vitro and its AUC represented 80% of the parent AUC.
Excretion After single oral dose of radiolabeled [ 14 C]-venetoclax 200 mg to healthy subjects, >99.9% of the dose was recovered in feces (21% as unchanged) and <0.1% in urine within 9 days. Specific Populations No clinically significant differences in the pharmacokinetics of venetoclax were observed based on age (19 to 93 years), sex, weight, mild to severe renal impairment (CLcr 15 to 89 mL/min, calculated by Cockcroft-Gault), or mild to moderate hepatic impairment (normal total bilirubin and aspartate transaminase (AST) > upper limit of normal (ULN) or total bilirubin 1 to 3…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Venetoclax is a selective and orally bioavailable small-molecule inhibitor of BCL-2, an anti-apoptotic protein. Overexpression of BCL-2 has been demonstrated in CLL and AML cells where it mediates tumor cell survival and has been associated with resistance to chemotherapeutics. Venetoclax helps restore the process of apoptosis by binding directly to the BCL-2 protein, displacing pro-apoptotic proteins like BIM, triggering mitochondrial outer membrane permeabilization and the activation of caspases.
In nonclinical studies, venetoclax has demonstrated cytotoxic activity in tumor cells that overexpress BCL-2.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING VENCLEXTA is dispensed as follows: Packaging Presentation Number of Tablets National Drug Code (NDC) CLL/SLL Starting Pack Each pack contains four weekly wallet blister packs: Week 1 (14 x 10 mg tablets) Week 2 (7 x 50 mg tablets) Week 3 (7 x 100 mg tablets) Week 4 (14 x 100 mg tablets) 0074-0579-28 Wallet containing 10 mg tablets 14 x 10 mg tablets 0074-0561-14 Wallet containing 50 mg tablets 7 x 50 mg tablets 0074-0566-07 Unit dose blister containing 10 mg tablets 2 x 10 mg tablets 0074-0561-11 Unit dose blister containing 50 mg tablet 1 x 50 mg tablet 0074-0566-11 Unit dose blister containing 100 mg tablet 1 x 100 mg tablet 0074-0576-11 Bottle containing 100 mg tablets 28 x 100 mg tablets 0074-0576-30 Bottle containing 100 mg tablets 120 x 100 mg tablets 0074-0576-22 VENCLEXTA 10 mg film-coated tablets are round, biconvex shaped, pale yellow debossed with “V” on one side and “10” on the other side.
VENCLEXTA 50 mg film-coated tablets are oblong, biconvex shaped, beige debossed with “V” on one side and “50” on the other side. VENCLEXTA 100 mg film-coated tablets are oblong, biconvex shaped, pale yellow debossed with “V” on one side and “100” on the other side. Store in original container at or below 86°F (30°C).
Dispense to patient in original container to protect from moisture.
📋 Description ▾
11 DESCRIPTION Venetoclax is a BCL-2 inhibitor. It is a light yellow to dark yellow solid with the empirical formula C 45 H 50 ClN 7 O 7 S and a molecular weight of 868.44. Venetoclax is described chemically as 4-(4-{[2-(4-chlorophenyl)-4,4-dimethylcyclohex-1-en-1-yl]methyl}piperazin-1-yl)- N -({3-nitro-4-[(tetrahydro-2 H -pyran-4-ylmethyl)amino]phenyl}sulfonyl)-2-(1 H -pyrrolo[2,3- b ]pyridin-5-yloxy)benzamide) and has the following chemical structure: Venetoclax has very low aqueous solubility.
VENCLEXTA tablets for oral use are supplied as pale yellow or beige tablets that contain 10 mg, 50 mg, or 100 mg venetoclax as the active ingredient. Each tablet also contains the following inactive ingredients: copovidone, colloidal silicon dioxide, polysorbate 80, sodium stearyl fumarate, and calcium phosphate dibasic. In addition, the 10 mg and 100 mg coated tablets include the following: iron oxide yellow, polyvinyl alcohol, polyethylene glycol, talc, and titanium dioxide.
The 50 mg coated tablets also include the following: iron oxide yellow, iron oxide red, iron oxide black, polyvinyl alcohol, talc, polyethylene glycol and titanium dioxide. Each tablet is debossed with “V” on one side and “10”, “50” or “100” corresponding to the tablet strength on the other side. the following chemical structure for Venetoclax is a BCL-2 inhibitor. It is a light yellow to dark yellow solid with the empirical formula C45H50ClN7O7S and a molecular weight of 868.44.
Venetoclax is described chemically as 4-(4-{[2-(4-chlorophenyl)-4,4-dimethylcyclohex-1-en-1-yl]methyl}piperazin-1-yl)-N-({3-nitro-4-[(tetrahydro-2H-pyran-4-ylmethyl)amino]phenyl}sulfonyl)-2-(1H-pyrrolo[2,3-b]pyridin-5-yloxy)benzamide).
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide ). Tumor Lysis Syndrome Advise patients of the potential risk of TLS, particularly at treatment initiation, during the ramp-up phase, and with resumption after an interruption and to immediately report any signs and symptoms associated with this event (fever, chills, nausea, vomiting, confusion, shortness of breath, seizure, irregular heartbeat, dark or cloudy urine, unusual tiredness, muscle or bone pain, and/or joint discomfort) to their health care provider (HCP) for evaluation [see Warnings and Precautions ( 5.1 )] .
Advise patients to be adequately hydrated every day when taking VENCLEXTA to reduce the risk of TLS. The recommended volume is 6 to 8 glasses (approximately 56 ounces total) of water each day. Patients should drink water starting 2 days before and on the day of the first dose, and every time the dose is increased [see Dosage and Administration ( 2.4 )] .
Advise patients of the importance of keeping scheduled appointments for blood work or other laboratory tests [see Dosage and Administration ( 2.4 )] . Advise patients that it may be necessary to take VENCLEXTA in the hospital or medical office setting to allow monitoring for TLS. Neutropenia Advise patients to contact their HCP immediately if they develop a fever or any signs of infection.
Advise patients of the need for periodic monitoring of blood counts [see Warnings and Precautions ( 5.2 )] . Infections Advise patients to contact their HCP immediately if they develop a fever or any signs of infection [see Warnings and Precautions ( 5.3 )] . Drug Interactions Advise patients to avoid consuming grapefruit products, Seville oranges, or starfruit during treatment with VENCLEXTA.
Advise patients that VENCLEXTA may interact with some drugs; therefore, advise patients to inform their health care provider of the use of any prescription medication, over-the-counter drugs, vitamins and herbal products [see Contraindications ( 4 ) and Drug Interactions ( 7.1 )] . Immunizations Advise patients to avoid vaccination with live vaccines because they may not be safe or effective during treatment with VENCLEXTA [see Warnings and Precautions ( 5.4 )] . Embryo-Fetal Toxicity Advise pregnant women of the potential risk to the fetus.
Advise females or reproductive potential to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions ( 5.5 ) and Use in Specific Populations ( 8.1 )] . Advise female patients of reproductive potential to use effective contraception during therapy and for 30 days after the last dose [see Use in Specific Populations ( 8.3 )] . Lactation Advise women not to breastfeed during treatment with VENCLEXTA and for 1 week after the last dose [see Use in Specific Populations ( 8.2 )] .
Infertility Advise males of reproductive potential that VENCLEXTA may impair fertility [see Use in Specific Populations ( 8.3 )] . Administration Advise patients to keep VENCLEXTA in original packaging or container. Advise patients to take VENCLEXTA exactly as prescribed and not to change their dose or to stop taking VENCLEXTA unless they are told to do so by their HCP.
Advise patients to take VENCLEXTA orally once daily, at approximately the same time each day, according to their HCP's instructions and that the tablets should be taken with a meal and water [see Dosage and Administration ( 2.8 )] . Advise patients to contact their HCP if they have trouble swallowing VENCLEXTA tablets. A dose in smaller sized tablets may be prescribed, or tablets may be crushed and mixed with ½ cup (4 ounces) of water, apple juice, apple sauce, or yogurt.
Take the entire dose immediately with a meal and water. Do not crush more than one dose at a time [see Dosage and Administration ( 2.8 )] . Crushed tablets may cause yellow staining, including of the skin.
Consider using disposable gloves when handling crushed tablets. Advise patients that if a…
💬 Medication Guide ▾
MEDICATION GUIDE VENCLEXTA ® (ven-KLEKS-tuh) (venetoclax tablets) What is the most important information I should know about VENCLEXTA? VENCLEXTA can cause serious side effects, including: Tumor lysis syndrome (TLS). TLS is caused by the fast breakdown of cancer cells.
TLS can cause kidney failure, the need for dialysis treatment, and may lead to death. Your healthcare provider will do tests to check your risk of getting TLS before you start taking VENCLEXTA. You will receive other medicines before starting and during treatment with VENCLEXTA to help reduce your risk of TLS.
You may also need to receive intravenous (IV) fluids into your vein. Your healthcare provider will do blood tests to check for TLS when you first start and during treatment with VENCLEXTA. It is important to keep your appointments for blood tests.
Tell your healthcare provider right away if you get any symptoms of TLS during treatment with VENCLEXTA, including: ○ fever ○ chills ○ nausea ○ vomiting ○ confusion ○ shortness of breath ○ seizures ○ irregular heartbeat ○ dark or cloudy urine ○ unusual tiredness ○ muscle or joint pain Drink plenty of water during treatment with VENCLEXTA to help reduce your risk of getting TLS . Drink 6 to 8 glasses (about 56 ounces total) of water each day, starting 2 days before your first dose, on the day of your first dose of VENCLEXTA, and each time your dose is increased.
Your healthcare provider may delay, decrease your dose, or stop treatment with VENCLEXTA if you get symptoms of TLS. When restarting VENCLEXTA after stopping for 1 week or longer, your healthcare provider may again check for your risk of TLS and change your dose. See " What are the possible side effects of VENCLEXTA? " for more information about side effects.
What is VENCLEXTA? VENCLEXTA is a prescription medicine used: to treat adults with chronic lymphocytic leukemia (CLL) or small lymphocytic lymphoma (SLL). in combination with azacitidine, or decitabine, or low-dose cytarabine to treat adults with newly diagnosed acute myeloid leukemia (AML) who: ○ are 75 years of age or older, or ○ have other medical conditions that prevent the use of standard chemotherapy. It is not known if VENCLEXTA is safe and effective in children.
Who should not take VENCLEXTA? People taking certain medicines during the beginning of VENCLEXTA treatment (when the dose is being slowly increased) are at increased risk of TLS. Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements.
VENCLEXTA and other medicines may affect each other causing serious side effects. Do not start new medicines during treatment with VENCLEXTA without first talking with your healthcare provider. Before taking VENCLEXTA, tell your healthcare provider about all of your medical conditions, including if you: have kidney problems have liver problems have problems with your body salts or electrolytes, such as potassium, phosphorus, or calcium have a history of high uric acid levels in your blood or gout are scheduled to receive a vaccine.
You should not receive a “live vaccine” before, during, or after treatment with VENCLEXTA, until your healthcare provider tells you it is okay. If you are not sure about the type of immunization or vaccine, ask your healthcare provider. These vaccines may not be safe or may not work as well during treatment with VENCLEXTA. are pregnant or plan to become pregnant.
VENCLEXTA may harm your unborn baby. Females who are able to become pregnant: Your healthcare provider should do a pregnancy test before you start treatment with VENCLEXTA. Use effective birth control during treatment and for 30 days after the last dose of VENCLEXTA.
If you become pregnant or think you are pregnant, tell your healthcare provider right away. are breastfeeding or plan to breastfeed. It is not known if VENCLEXTA passes into your breast milk. Do not breastfeed during treatment and for 1 week after the last dose…